
Like most parents across the land, I received a letter from the local council’s Director of Public Health this morning (forwarded by the school in an email) explaining that they have “advised [sic] schools that parents/carers/other visitors are not invited” to nativity plays this year. Not the end of the world in the grand scheme of things, of course – just another depressing example in the long litany of examples of children’s priorities being cast under a bus due to adult panic during the course of this pandemic.
Much more concerning, because of what it said about the mindset of the Director of Public Health in question, was this alarmingly blithe justification for continued restrictions in schools, buried in the body of the letter:
Much as we would all like it to be, the pandemic is not over. Whilst it is clear that the vaccination programme is effective in preventing serious disease and deaths, the vaccine is never going to stop all transmission, and resultant harm, on its own. [Emphasis added]
You couldn’t get a starker admission than this that we long ago moved beyond “flattening the curve” or staving off a dire public health emergency in a once-in-a-lifetime, never-to- be-repeated year. No: we are now in a different place altogether – one in which we must stop transmission “and resultant harm” for its own sake, forever. For how else are we supposed to interpret this statement? On what grounds will parents ever be allowed back into schools to watch nativity plays (or even properly meet their children’s teachers), if the requirement is for “all transmission and resultant harm” to end? We will never be in that position. So in what circumstance does the Director of Public Health envisage there ever will be a return to normal schooling? Ought this not to be made clear to local parents?
More broadly, this incident raises the question of how it is that something so fundamental – children’s schooling – has ended up beholden to the whim of unelected, largely unaccountable, public officials such as this. The local Director of Public Health in any given local authority cannot be voted out. They are not challenged by probing interviews in prominent media outlets. The means by which they are appointed is entirely opaque. And their policy positions, political backgrounds, and motivations are subject to essentially no public scrutiny. Yet they possess the power, at the sweep of a pen, to disrupt the lives of literally tens of thousands of people within their bailiwicks, with the only possible avenue of challenge being a prohibitively expensive and time-consuming claim for judicial review. This ought to be intolerable in a free society. Yet it is the position in which we find ourselves.
Once again, the Covid pandemic and its response have shone a harsh light on British democracy, and revealed it to be in a dilapidated state indeed.
November 29, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science | Covid-19, Human rights, UK |
Leave a comment
A Partial Review of Robert F. Kennedy, Jr., THE REAL ANTHONY FAUCI

Robert F. Kennedy, Jr.’s new book, The Real Anthony Fauci: Bill Gates, Big Pharma, and the Global War on Democracy and Public Health is not the book of a politician seeking attention. It is the book of a man determined to stake his own life in the resistance against the unfolding bio-terrorist assault on humankind by governments captive of the pharmaceutical industry. He is calling for mass insurrection, and his last word is: “I’ll see you on the barricades.” The book begins like this:
I wrote this book to help Americans—and citizens across the globe—understand the historical underpinnings of the bewildering cataclysm that began in 2020. In that single annus horribilis, liberal democracy effectively collapsed worldwide. The very governmental health regulators, social media eminences, and media companies that idealistic populations relied upon as champions of freedom, health, democracy, civil rights, and evidence-based public policy seemed to collectively pivot in a lockstep assault against free speech and personal freedoms. Suddenly, those trusted institutions seemed to be acting in concert to generate fear, promote obedience, discourage critical thinking, and herd seven billion people to march to a single tune, culminating in mass public health experiments with a novel, shoddily tested and improperly licensed technology so risky that manufacturers refused to produce it unless every government on Earth shielded them from liability. … Conscientious objectors who resisted these unwanted, experimental, zero-liability medical interventions faced orchestrated gaslighting, marginalization, and scapegoating. American lives and livelihoods were shattered by a bewildering array of draconian diktats imposed without legislative approval or judicial review, risk assessment, or scientific citation. So-called Emergency Orders closed our businesses, schools and churches, made unprecedented intrusions into privacy, and disrupted our most treasured social and family relationships.
 Kennedy is not a newcomer to this frightening dystopia. “My 40-year career as an environmental and public health advocate,” he writes, “gave me a unique understanding of the corrupting mechanisms of ‘regulatory capture,’ the process by which the regulator becomes beholden to the industry it’s meant to regulate.” From the time he entered the vaccine debate in 2005, he realized that “the pervasive web of deep financial entanglements between Pharma and the government health agencies had put regulatory capture on steroids.” The Centers for Disease Control and Prevention (CDC), for example, owns 57 vaccine patents and spent $4.9 billion in 2019 buying and distributing vaccines. The Food and Drug Administration (FDA) receives 45 percent of its budget from the pharmaceutical industry. The National Institutes of Health (NIH), with its $42 billion budget, owns hundreds of vaccine patents and often profits from the sale of products it supposedly regulates. High-level officials receive yearly emoluments of up to $150,000 in royalty payments on products that they help develop and then usher through the approval process.
Dr. Anthony Fauci, “America’s reigning health commissar,” stands at the summit of that Leviathan. From 1968, he occupied various posts at the National Institute of Allergy and Infectious Diseases (NIAID), a sub-agency of NIH, of which he became director in 1984. With a $417,608 annual salary, he is the highest paid of all federal employees, including the President. “His experiences surviving 50 years as the panjandrum of a key federal bureaucracy, having advised six Presidents, the Pentagon, intelligence agencies, foreign governments, and the WHO, seasoned him exquisitely for a crisis that would allow him to wield power enjoyed by few rulers and no doctor in history.” He has nurtured a complex web of financial entanglements that has transformed the NIH into a subsidiary of Big Pharma. Reaching into the deep pockets of the Clinton and Gates Foundations, he has used his $6 billion annual budget to achieve dominance and control over many agencies, including the World Health Organization (WHO). He can make and break careers, enrich or punish university research centers, and dictate the outcome of scientific research across the globe, consistently prioritizing pharmaceutical industry profits over public health.
Kennedy’s book documents Fauci’s “two-decade strategy of promoting false pandemics as a scheme for promoting novel vaccines,” as well as “his actions to conceal widespread contamination in blood and vaccines, his destructive vendettas against scientists who challenge the Pharma paradigm, [and] his deliberate sabotaging of patent-expired remedies against infectious diseases.”
But of course, Kennedy’s book is not about a man: it is about an irremediably corrupt and predatory system created in the U.S. and exported worldwide. Ultimately, however, the system is built and run by humans, and focusing on its most emblematic representative shows its very soul.
Kennedy’s book puts the current crisis in historical perspective. But it doesn’t tell the story chronologically. It starts with a very long first chapter on the current Covid crisis—a book by itself—, then goes back, from chapter 3, to the 1980s and the search for the AIDS vaccine, the template for today’s pharmaceutical coup. In this review, I will focus on the AIDS episode, because it is the least familiar part of a history covering fifty years, and it helps make sense of what is happening today. It is an incredible story, that I would have had difficulty believing just three years ago, but that our current enslavement now makes utterly credible.
The thirty-year decampment of journalistic scrutiny means that there is still no coherent public narrative chronicling Dr. Fauci’s futile quest for his “inevitable” AIDS vaccine, much less accountability. Industry and government scientists have instead shrouded the scandalous saga in secrecy, subterfuge, and prevarication, obscuring a thousand calamities and a sea of tears deserving its own book. Every meager effort to research the debacle—on Google, PubMed, news sites, and published clinical trial data—yields only shocking new atrocities—a grim, repetitive parade of horribles: heartbreaking tragedies, entrenched institutional arrogance and racism, broken promises, vast expenditures of squandered treasure, and the recurring chicanery of Anthony Fauci, Bob Gallo, and Bill Gates.
Kennedy deserves praise and gratitude for his courage to bring this controversy out into the open, in a clear and well-documented exposé. His book is destined to become a landmark in the struggle for Life and Truth—and in the Kennedy heroic saga. This article reflects only a fraction of what can be learned from its 480 pages packed with data and references. Since page numbers in the kindle edition (recommended for its thousand hyperlinks) differ from those in the printing book, I have dispensed with them.
In the Beginning
In the first lines of his 2014 book Thimerosal: Let the Science Speak (documenting an astonishing 1,135 percent higher rate of autism among children who took hepatitis B vaccines), Kennedy prudently claimed to be “pro-vaccine” and to “believe that vaccines have saves the lives of hundreds of millions of humans over the past century.” Kennedy makes no such disclaimer in his new book. Rather, he sides with the critics of the popular dogma that vaccines played the key role in abolishing mortal contagious illnesses in North America and Europe, citing a 2000 study by CDC and Johns Hopkins scientists that concluded: “nearly 90 percent of the decline in infectious disease mortality among US children occurred before 1940, when few antibiotics or vaccines were available.” The main causes of the dramatic 74 percent decline in infectious disease mortality in the first half of the twentieth century were improved nutrition and sanitation.
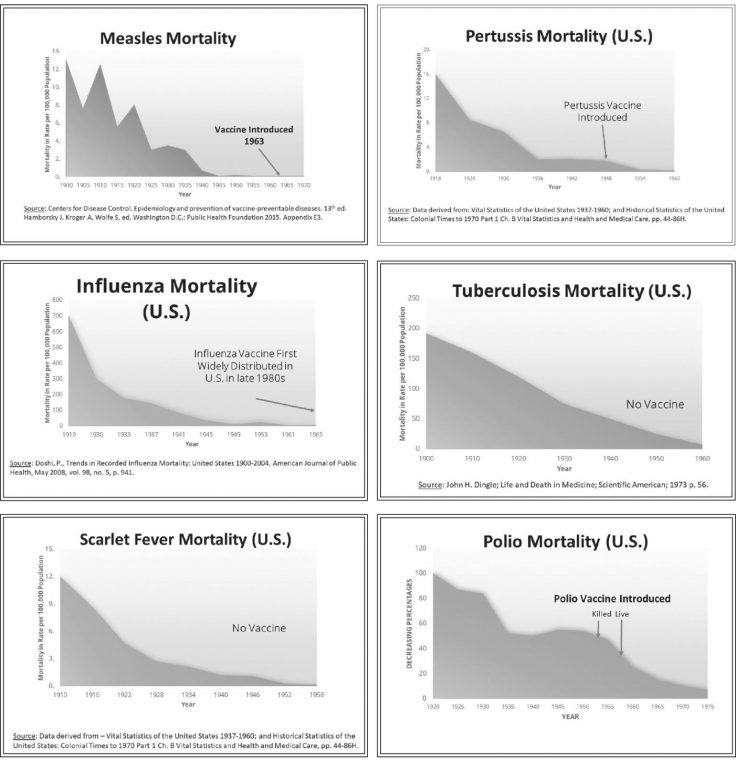
From Kennedy, The Real Anthony Fauci, 2021
This revisionist but objective perspective explains why Fauci and Gates’s obsession with vaccine-preventable diseases has caused negative overall impacts on public health in Africa and Asia, by proportionally reducing assistance streams for nutrition, clean water, transportation, hygiene, and economic development. Gates and Fauci have actually hijacked WHO’s public health agenda away from the projects that are proven to curb infectious diseases, and diverted international aid to wedge open emerging markets for their multinational partners.
To understand their craze for vaccines, Kennedy reminds us of the pioneering influence of the Rockefeller Foundation. In 1911, after the Supreme Court ruled that Standard Oil constituted an “unreasonable monopoly” and splintered it into thirty-four companies, John D. Rockefeller inaugurated what Bill Gates would later call “philanthrocapitalism.” He provided large grants to scientists for synthesizing and patenting chemical versions of the molecules identified in traditional medicine. The Foundation provided almost half of the initial budget for the League of Nations’ Health Organization (LNHO) in 1922, and populated its ranks with its veterans and favorites. It imbued the League with its technocratic philosophy of health, inherited by its successor body, the WHO, in 1948.
The Rockefeller Foundation launched a “public-private partnership” with pharmaceutical companies called the International Health Commission, which first set about inoculating the hapless populations of the colonized tropics with a yellow fever jab. By the time John D. Rockefeller, Jr. disbanded it in 1951, the International Health Commission had spent billions of dollars on tropical disease campaigns in almost 100 countries and colonies. These projects had a hidden agenda, according to a 2017 report, U.S. Philanthrocapitalism and the Global Health Agenda: they allowed the Rockefeller family to open developing world markets for oil, mining, banking and other profitable trades, including pharmaceutical profits that grew tremendously when, in the 1970s:
a wave of new technologies, including PCR and super powerful electron microscopes, had opened windows on teeming new worlds containing millions of species of previously unknown viruses to scientists. … The lure of fame and fortune ignited a chaotic revolution in virology as ambitious young PhDs scrambled to inculpate newly discovered microbes as the cause of old malignancies. … Under this new rubric, every theoretical breakthrough, every find, became potentially the basis for a new generation of drugs.
By the mid-1970s, the CDC was seeking to justify its existence by tracking small outbreaks of rabies. “Drumming up public fear of periodic pandemics was a natural way for NIAID and CDC bureaucrats to keep their agencies relevant. Dr. Fauci’s immediate boss and predecessor as NIAID Director, Richard M. Krause, helped pioneer this new strategy in 1976.” That year the fake swine flu epidemic was concocted. The experimental vaccine was so fraught with problems that the Health and Human Services (HHS) discontinued the jab after vaccinating 49 million Americans. According to news accounts, the incidence of flu was seven times greater among the vaccinated than the unvaccinated. Furthermore, the vaccine caused some 500 cases of the degenerative nerve disease Guillain-Barré Syndrome, 32 deaths, more than 400 paralyzations, and as many as 4,000 other injuries. Injured plaintiffs filed 1,604 lawsuits. By April 1985, the government had paid out $83,233,714 and spent tens of millions of dollars adjudicating and processing those claims.
Another scandal broke in 1983, when a NIH-funded UCLA study found that the DTP vaccine developed by Wyeth—now Pfizer—was killing or causing severe brain injury, including seizures and death, in one in every 300 vaccinated children. While protecting children against diphtheria, tetanus, and pertussis, the DTP vaccine had ruined their immune systems, making them vulnerable to a wide range of other deadly infections.
The resultant lawsuits caused the collapse of insurance markets for vaccines and threatened to bankrupt the industry. Wyeth claimed to be losing $20 in downstream liability for every dollar it earned on vaccine sales, and induced Congress to pass in 1986 the National Childhood Vaccine Injury Act, which shielded vaccine makers from liability. (This incentive for unrestricted greed was strengthened in 2005 when George W. Bush signed into law the Public Readiness and Emergency Preparedness Act).
AIDS and AZT
In 1984, when Fauci became director of NIAID, the AIDS crisis was spiraling out of control. That proved “a redemptive juncture for NIAID and the launch pad for Dr. Fauci’s stellar rise.” In an April 1984 press conference, NIH scientist Robert Gallo linked AIDS to the virus that was soon to be named HIV. Dr. Fauci then moved aggressively to claim jurisdiction for his agency over the National Cancer Institute (NCI), another sub-agency of NIH. “As the nation’s newly appointed AIDS czar, Dr. Fauci was now a gatekeeper for almost all AIDS research … parroting NCI’s vows to cure cancer, Dr. Fauci promised Congress that he would quickly produce drugs and vaccines to banish AIDS.”
At the same time, he was deliberately spreading contagion terror, warning in a 1983 fear-mongering article that “the scope of the syndrome may be enormous”, since “routine close contact, as within a family household, can spread the disease”—despite the fact that AIDS was almost exclusive to intravenous drug users and male homosexuals. A year later, Fauci was forced to concede that health officials had never detected a case of the disease spread through “casual contact.” Nevertheless, Dr. Fauci’s systematic response was “to amplify the widespread panic of dreaded pestilence that would naturally magnify his power, elevate his profile, and expand his influence. Amplifying terror of infectious disease was already an ingrained knee-jerk institutional response at NIAID.”
Having seized control over AIDS research, Fauci captured the new flood of congressional AIDS appropriations flowing to NIH through the lobbying of a newly organized gay community. By 1990, NIAID’s annual AIDS budget reached $3 billion. In the ensuing decades, the federal government spent over half a trillion dollars in the quest for an elusive vaccine that never materialized. Dr. Fauci pumped up taxpayers’ money into nearly 100 vaccine candidates, with no other result than “massive transfers of public lucre to Dr. Fauci’s Pharma partners,” and a sea of tears for millions of unfortunate human guinea pigs.
NIAID’s lack of in-house drug development capacity meant that Fauci had to farm out drug research to a network of so-called “principal investigators” (PIs), academic physicians and researchers controlled by pharmaceutical companies and acting as liaisons, recruiters and spokespersons.
PIs are pharmaceutical industry surrogates who play key roles promoting the pharmaceutical paradigm and functioning as high priests of all its orthodoxies, which they proselytize with missionary zeal. They use their seats on medical boards and chairmanships of university departments to propagate dogma and root out heresy. … They are the credentialed and trusted medical experts who prognosticate on television networks—now helplessly reliant on pharmaceutical ad revenue—to push out Pharma content.
Dr. Fauci’s choice to transfer virtually all of NIAID’s budget to pharmaceutical PIs for drug development was an abdication of the agency’s duty to find the source and eliminate the explosive epidemics of allergic and autoimmune disease that began under his watch around 1989. … NIAID money effectively became a giant subsidy to the blossoming pharmaceutical industry to incubate a pipeline of profitable new drugs targeted to treat the symptoms of those very diseases.
In the late 80s and early 90s, PIs received every year between 4 and 5 billions of dollars from NIH’s budget. But “legalized bribes” from drug companies and royalty payments from drug products often dwarfed their government funding. Celia Farber’s 2006 Harper’s article, “Out of Control: AIDS and the Destruction of Medical Science,” laid bare the culture of squalor, corruption, and vendetta at Fauci’s AIDS Branch, the Division of Acquired Immunodeficiency Syndrome (DAIDS).
Despite his miserable track record at reducing illness over the previous decade, Fauci persuaded President Bill Clinton, in May 1997, to set a new national goal for science. In a speech delivered at Morgan State University, Clinton—perhaps not without cryptic irony— imitated Kennedy’s May 25, 1961 moonshot promise, saying, “Today let us commit ourselves to developing an AIDS vaccine within the next decade.”
A year later, Bill Gates, who had just founded his International Aids Vaccine Initiative (IAVI), sealed a deal with Fauci. “Over the next two decades, that partnership would metastasize to include pharmaceutical companies, military and intelligence planners, and international health agencies all collaborating to promote weaponized pandemics and vaccines and a new brand of corporate imperialism rooted in the ideology of biosecurity.” The story of Gates’ involvement in the vaccine business, of his murderous experiments in Africa and India, and of his rise as the unofficial top sponsor of the WHO (ordering in 2011: “All 193 member states, you must make vaccines a central focus of your health systems”), is told in chapters 9 and 10 of Kennedy’s book.
When Dr. Fauci became head of NIAID, azidothymidine, known as AZT, was the only candidate as an AIDS remedy. AZT is a “DNA chain terminator,” randomly destroying DNA synthesis in reproducing cells. It had been developed in 1964 for cancer, but abandoned as too toxic even for short-term therapy. It was deemed so worthless that it was not even patented. In 1985, Samuel Broder, head of the National Cancer Institute (NCI), claimed having found that AZT killed HIV in test tubes. The British company Burroughs Wellcome then patented it as an AIDS remedy. “Recognizing financial opportunity in the desperate terror of young AIDS patients facing certain death, the drug company set the price at up to $10,000/year per patient—making AZT one of the most expensive drugs in pharmaceutical history. Since Burroughs Wellcome could manufacture AZT for pennies per dose, the company anticipated a bonanza.”
Fauci gave Burroughs Wellcome a monopoly control over the government’s HIV response. But all did not go smoothly. “AZT’s horrendous toxicity hobbled researchers struggling to design study protocols that would make it appear either safe or effective.” Another problem is that community-based doctors were achieving promising results with cheap, off-label therapeutic drugs. Dr. Fauci refused to test any of those repurposed drugs that had no Pharma patrons. When he did put on trial AL721, an antiviral that was far less toxic than AZT, he rigged the studies to fail, and abruptly cancelled Phase 2.
Meanwhile, he accelerated testing of AZT, skipping animal testing and allowing Burroughs Wellcome to proceed directly to human trials. In March 1987, Fauci’s team declared the human trials a success after only four months, and Fauci congratulated himself in front of the press. However, when in July 1987, the official report of Burroughs Wellcome’s Phase 2 trial was published, European scientists complained that raw data showed no benefit in reducing symptoms. FDA conducted its own investigation eighteen months later, but kept its results secret, until investigative journalist John Lauritsen obtained some of them by using the Freedom of Information Act; the documents showed that the Fauci/Burroughs Wellcome research teams had engaged in widespread data tampering. More than half of the AZT patients suffered adverse reactions so deadly that they needed multiple blood transfusions just to keep them alive. Nevertheless, Fauci kept on lying himself to the top of the world, with little scrutiny from mainstream media.
A key and enduring legacy of the AZT battle was Dr. Fauci’s emergence as the alpha wolf of HHS [Health and Human Services]. His enormous budget, and multiplying contacts on Capitol Hill, the White House, and the medical industry, thereafter allowed him to influence or ignore a succession of politically appointed HHS directors and to bully, manipulate, and dominate HHS’s other sister agencies, most notably FDA.
AZT was not the only subject of interest to Fauci. By June 2003, NIH was running 10,906 clinical trials on new antiviral concoctions in some four hundred clinical trials in ninety countries. Some of those trials seemed pulled out of Dickens’ worst nightmares. The Alliance for Human Research Protection (AHRP), a medical industry watchdog organization, has documented that between 1985 and 2005, NIAID conscripted at least 532 infants and children from foster care in New York City as subjects of clinical trials testing experimental AIDS drugs and vaccines. AHRP’s investigation revealed that many of those children were perfectly healthy and may not even have been HIV-infected. Yet 80 of them died. In 2004, journalist Liam Scheff chronicled Dr. Fauci’s secretive experiments on foster children at Incarnation Children’s Center (ICC) in New York City and numerous sister facilities between 1988 and 2002. These disclosures, comments Kennedy, beg many questions:
From what moral wilderness did the monsters who devised and condoned these experiments descend upon our idealistic country? How have they lately come to exercise such tyrannical power over our citizens? What sort of nation are we if we allow them to continue? Most trenchantly, does it not make sense that the malevolent minds, the elastic ethics, the appalling judgment, the arrogance, and savagery that sanctioned the barbaric brutalization of children at the Incarceration Convent House, and the torture of animals for industry profit, could also concoct a moral justification for suppressing lifesaving remedies and prolonging a deadly epidemic? Could these same dark alchemists justify a strategy of prioritizing their $48 billion vaccine project ahead of public health and human life? Did similar hubris—that deadly human impulse to play God—pave the lethal path to Wuhan and fuel the reckless decision to hack the codes of Creation and fabricate diabolical new forms of life—pandemic superbugs—in a ramshackle laboratory with scientists linked to the Chinese military?
Indeed, Kennedy shows in his final chapter, “Germ Games,” that Fauci’s investments in so-called “gain of function” experiments to engineer pandemic superbugs raise “the ironic possibility that Dr. Fauci may have played a role in triggering the global contagion that two US presidents entrusted him to manage.”
Africa is “the venue of choice for companies seeking cooperative government officials, compliant populations, the lowest per-patient enrollment costs, and lax oversight by media and regulatory officials.” In the early 1990s, African dictators rolled out the red carpet for Pharma, cashing in on the lucrative business of farming out their citizens for the booming clinical trial business. And on January 29, 2003, President George W. Bush announced at his State of the Union speech his Emergency Plan for AIDS Relief (PEPFAR), Fauci’s new swindle:
On the continent of Africa, nearly 30 million people have the AIDS virus. … Yet across that continent, only 50,000 AIDS victims—only 50,000—are receiving the medicine they need. … I ask the Congress to commit $15 billion over the next five years, including nearly $10 billion in new money, to turn the tide against AIDS in the most afflicted nations of Africa and the Caribbean.
Does HIV Cause AIDS?
Kennedy’s chapter 5, “The HIV Heresies,” opens up with the following note:
I hesitated to include this chapter because any questioning of the orthodoxy that HIV is the sole cause of AIDS remains an unforgivable—even dangerous—heresy among our reigning medical cartel and its media allies. But one cannot write a complete book about Tony Fauci without touching on the abiding—and fascinating—scientific controversy over what he characterizes as his “greatest accomplishment” and his “life’s work.”
The controversy illustrates how pharmaceutical industries and health agencies, acting in concert, engineer consensus on incomplete or fraudulent theories, and ruthlessly suppress dissent from even the most gifted recognized scientists. “From the outset,” Kennedy insists, “I want to make clear that I take no position on the relationship between HIV and AIDS.” However, there seems little doubt that his basic point is correct:
During the thirty-six years since Dr. Fauci and his colleague, Dr. Robert Gallo, first claimed that HIV is the sole cause of AIDS, no one has been able to point to a study that demonstrates their hypothesis using accepted scientific proofs. … Even today, incoherence, knowledge gaps, contradictions, and inconsistencies continue to bedevil the official dogma.
The success story of the HIV-AIDS dogma shows “many of the tactics Dr. Fauci has pioneered to dodge debate—bedazzling and bamboozling the press into ignoring legitimate inquiry of the credo, and undermining, gaslighting, punishing, bullying, intimidating, marginalizing, vilifying, and muzzling critics.” One of Fauci’s victims was Dr. Peter Duesberg, who in 1987 was still recognized as the world’s most accomplished retrovirologist. Duesberg argues that HIV does not cause AIDS but is essentially a “free rider” common to high-risk populations who suffer immune suppression due to environmental exposures. HIV, he says, is a harmless passenger virus that has almost certainly coexisted in humans for thousands of generations without causing diseases. While HIV may be sexually transmittable, Duesberg claims, AIDS is not.
Duesberg published his views in a groundbreaking 1987 article, then in a 724-page book, Inventing the AIDS Virus. Kennedy finds that “Duesberg’s rationales appear so clean, so elegantly crafted, and so compelling that, in reading them, it seems impossible that the entire [orthodox] hypothesis did not instantly collapse under the smothering weight of relentless logic.” But Fauci and Gallo never attempted to reply to Duesberg. Blaming AIDS on a virus was the gambit that had allowed NIAID to claim the jurisdiction—and cash flow—away from NCI, and Duesberg was severely punished for endangering this.
Dr. Fauci summoned the entire upper clergy of his HIV orthodoxy—and all of its lower acolytes and altar boys—to unleash a storm of fierce retribution on the Berkeley virologist and his followers. … the AIDS establishment, down to its lowliest doctor, publicly reviled Duesberg, NIH defunded him, and academia ostracized and exiled the brilliant Berkeley professor. The scientific press all but banished him. He became radioactive.
Surprisingly, however, Dr. Luc Montagnier, whose discovery of HIV Gallo had in fact stolen—as he admitted in 1991 after years of litigation—, became Duesberg’s most embarrassing convert, declaring at the San Francisco International AIDS Conference in June 1990, that “the HIV virus is harmless and passive, a benign virus.” He added that, according to his findings, HIV becomes dangerous only in the presence of a second organism, a bacteria-like bug called a mycoplasma. Montagnier, in fact, had never claimed that HIV was the only factor in AIDS, and grew increasingly skeptical of that theory. His repeated questioning of the establishment paradigm signaled the beginning of his vilification, for which his Nobel Prize hardly protected him.
Gallo’s “proof” that the cause of AIDS was a virus—as opposed to toxic exposures— provided the critical foundation stone of Dr. Fauci’s career. It allowed Fauci to capture the AIDS program and launch NIAID as the leading federal partner of the drug-production industry. This explains why Fauci never funded any study to explore whether HIV actually caused AIDS, and took vigorous preemptive action against any such study.
Kennedy cites other dissenting voices on AIDS epidemiology. Dr. Shyh-Ching Lo, the Chief Researcher in charge of AIDS programs for the Armed Forces Institute of Pathology, was shocked by Anthony Fauci’s unconventional claim that antibodies, normally the sign of a robust immune response, should, with HIV, be the signal for impending death. Since “HIV tests” do not in reality detect the elusive virus but only antibodies, there seems to be an Orwellian inversion at work. Kennedy also quotes Dr. David Rasnick, a PhD biochemist who has worked for thirty years in the pharmaceutical biotech field:
Fauci’s fundamental conundrum is that he has told everybody to diagnose AIDS based on the presence of HIV antibodies. With every other disease, the presence of antibodies is the signal that the patient has vanquished the disease. With AIDS, Fauci and Gallo, and now Gates, claim it’s a sign you’re about to die. Think about it; if the objective of an AIDS vaccine is to stimulate antibody production, then success would mean that every vaccinated person would also have an AIDS diagnosis. I mean, this is fodder for a comedy bit. It’s like someone gave the Three Stooges an annual billion-dollar budget!
The nature of AIDS—a syndrome, not a disease—is itself subject to questions, since it was made to encompass a galaxy of some thirty separate well-known diseases, all of which occur in individuals who have no HIV infection. “In the hands of Dr. Fauci’s opportunistic PIs, AIDS became an amorphous malady subject to ever-changing definitions, encompassing a multitude of old diseases in hosts who test positive for HIV.” Nobel Laureate Kary Mullis, the inventor of the PCR tests, pointed out that the PCR was capable of finding HIV signals in large segments of the population who suffered no AIDS symptoms. On the other hand, AIDS commonly occurs in people who test HIV negative, as Geoffrey Cowley documented in a 1992 Newsweek article, followed by Steve Heimoff in the Los Angeles Times.
These very inconsistencies were not a problem for Fauci and his standing army of pharmaceutical mercenaries. Quite the opposite: they opened up Africa’s AIDS bonanza. Researchers funded by Fauci, using PCR tests and murky statistical models, declared that up to 30 million Africans were suffering from AIDS, nearly half the adult population in some nations. While in Western nations, AIDS continued to be a disease of drug addicts and homosexual “poppers” (consumers of the amyl nitrite vasodilator providing relaxation of the anal musculature, packaged into the “popper” container patented by Burroughs Wellcome and advertised in the gay press throughout the AIDS epidemic), mysteriously, in Africa, 59 percent of AIDS cases were women, and 85 percent were heterosexuals.
But in the early 1990s, the character of AIDS changed dramatically with the proliferation of AZT. As they started to give AZT to people who were in fact not even sick but simply positive on the HIV test, AIDS started to look increasingly like AZT poisoning. And the death rate climbed precipitously. According to the Duesbergians, the vast majority of “AIDS deaths” after 1987 were actually caused by AZT. The medication that Dr. Fauci was prescribing to treat AIDS patients actually did what the virus could not: it caused AIDS itself. In 1988, the average survival time for patients taking AZT was four months. In 1997, recognizing the lethal effect of AZT, health officials lowered the dose; the average lifespan of AZT patients then rose to twenty-four months. According to Dr. Claus Köhnlein, a German oncologist, “We virtually killed a whole generation of AIDS patients without even noticing it because the symptoms of the AZT intoxication were almost indistinguishable from AIDS.”
Conclusion
In July 2019, Dr. Fauci made a surprise announcement: he finally had a working HIV vaccine, the potential “nail in the coffin” for the epidemic. He conceded that his new vaccine didn’t prevent transmission of AIDS, but predicted that those who took the jab would find that when they did get AIDS, the symptoms would be much reduced. Kennedy comments:
So confident was Dr. Fauci of the media’s slavish credulity that he assumed, correctly, that he’d never need to answer the many questions raised by this feverish gibberish. That entire odd proposition received zero critical press commentary. His success at slapping lipstick on this donkey and selling it to the world as a Thoroughbred may have emboldened his ruse—a year later—of placing similar cosmetics on the COVID vaccines that, likewise, neither prevent disease nor preclude transmission.
By 2019, the AIDS rope started to wear out. Who still cared about AIDS anyway? The “Covid-19 Pandemic” came as the perfect opportunity for a reset and an update in the pharmaceutical racket. As Winston Churchill reportedly said, “Never let a good crisis go to waste”. With complicit corporate media blacking out the scandalous track record of his white-coat mafia, Fauci emerged, again, as the good doctor, the savior.
“Is it fair to blame Dr. Fauci for a crisis that, of course, has many authors?” asks Kennedy. To some extent, it is.
Under Dr. Fauci’s leadership, the allergic, autoimmune, and chronic illnesses which Congress specifically charged NIAID to investigate and prevent, have mushroomed to afflict 54 percent of children, up from 12.8 percent when he took over NIAID in 1984. Dr. Fauci has offered no explanation as to why allergic diseases like asthma, eczema, food allergies, allergic rhinitis, and anaphylaxis suddenly exploded beginning in 1989, five years after he came to power. On its website, NIAID boasts that autoimmune disease is one of the agency’s top priorities. Some 80 autoimmune diseases, including juvenile diabetes and rheumatoid arthritis, Graves’ disease, and Crohn’s disease, which were practically unknown prior to 1984, suddenly became epidemic under his watch. Autism, which many scientists now consider an autoimmune disease, exploded from between 2/10,000 and 4/10,000 Americans when Tony Fauci joined NIAID, to one in thirty-four today. Neurological diseases like ADD/ADHD, speech and sleep disorders, narcolepsy, facial tics, and Tourette’s syndrome have become commonplace in American children. The human, health, and economic costs of chronic disease dwarf the costs of all infectious diseases in the United States. By this decade’s end, obesity, diabetes, and pre-diabetes are on track to debilitate 85 percent of America’s citizens. America is among the ten most over-weight countries on Earth. The health impacts of these epidemics—which fall mainly on the young—eclipse even the most exaggerated health impacts of COVID-19.
Dr. Fauci has done nothing to advance NIAID’s core obligation of researching the causes of chronic allergic and autoimmune diseases that have mushroomed under his tenure. Instead, Fauci has “reshaped NIAID into the leading incubator for new pharmaceutical products, many of which, ironically, profit from the cascading chronic disease pandemic.” Instead of researching the causes of Americans’ failing health, Dr. Fauci funnels the bulk of his $6 billion budget to the research and development of new drugs and vaccines that are largely responsible for weakening our natural immunity. “Of late, he has played a central role in undermining public health and subverting democracy and constitutional governance around the globe and in transitioning our civil governance toward medical totalitarianism.”
I was reminded of Dr. Knock, the central character of Jules Romains’s famous novel Knock or the Triumph of Medicine, written in 1923. Dr. Knock is a shady medical doctor of dubious competence who professes that “health” is an obsolete and unscientific concept, and that all men are sick and need to be informed about it by their doctor. To advance his plan of converting a whole town into permanent patients, he enlists the help of the school teacher and of the pharmacist, who suddenly sees his clientele booming (watch unforgettable moments of Guy Lefranc’s 1951 film adaptation with Louis Jouvet here and here).

Louis Jouvet as Dr. Knock in 1951
To some extent, however, Fauci is himself the product of a civilizational orientation that could only, in the long run, lead to the tyrannical medical technocracy that is now trying to enslave us. Rather than a new Dr. Frankenstein, Fauci is our own monster coming back after us. Kennedy hints at this vast aspect of the question, pointing to the need for deep questioning. The way Americans and Westerners in general have come to view health care has been shaped by the philosophy of the Rockefeller Foundation: “a pill for an ill.” In the debate between the “miasma theory”—that emphasizes preventing disease by fortifying the immune system through nutrition and by reducing exposures to environmental toxins and stresses—versus the “germ theory”—which blames disease on microscopic pathogens—we have unambiguously opted for the latter. We have signed up for an approach to disease that requires to identify the culpable germ and tailor a poison to kill it. The choice was not forced upon us. We have surrendered responsibility for our health to medical experts and insurance brokers.
As Dr. Claus Köhnlein and Torsten Engelbrecht observe in their book Virus Mania (2007) quoted by Kennedy: “The idea that certain microbes—above all fungi, bacteria, and viruses—are our great opponents in battle, causing certain diseases that must be fought with special chemical bombs, has buried itself deep into the collective conscience.” It is a warlike paradigm, perfectly suited for manufacturing consent on the way to dictatorship. As Kennedy wrote in his preface to Dr. Joseph Mercola and Ronni Cummins, The Truth About Covid-19 (2021), “demagogues must weaponize fear to justify their demands for blind obedience.”
Government technocrats, billionaire oligarchs, Big Pharma, Big Data, Big Media, the high-finance robber barons, and the military industrial intelligence apparatus love pandemics for the same reasons they love wars and terrorist attacks. Catastrophic crises create opportunities of convenience to increase both power and wealth.
Laurent Guyénot, PhD, is the author of The Unspoken Kennedy Truth and of a film on the same subject.
November 29, 2021
Posted by aletho |
Book Review, Corruption, Deception, Science and Pseudo-Science, Timeless or most popular, War Crimes | AIDS, AZT, FDA, NIAID, NIH, Rockefeller Foundation, United States |
Leave a comment
Last week, I showed up to a nice party with a bottle of Absinthe. I like the stuff but I was also performing an experiment. How long before someone at the party asks if Absinthe causes hallucinations and was thereby banned? It didn’t take long. The question came up repeatedly. What is the ingredient in this that is highly suspect? Oh yes, it’s wormwood. What is wormwood anyway? Is it like heroin?
So it went. And so it has been for the better part of one-hundred years. There is absolutely no medical basis for this at all. Wormwood has been used as a medicinal herb since the ancient world, and there is a great deal of legend surrounding it, but there is zero evidence that it has any hallucinogenic properties at all.
Incredibly, some research suggests that wormwood is possibly an early treatment for Covid that inhibits the reproduction of SARS-CoV-2!
What about the belief that it was banned? It was indeed banned, over most of the Western world since the late 19th century. It was only relegalized for import into the United States in 2007. Now there are micro-distilleries all over the country that make the real thing, the exact drink about which Oscar Wilde wrote:
After the first glass of absinthe you see things as you wish they were. After the second you see them as they are not. Finally you see things as they really are, and that is the most horrible thing in the world. I mean disassociated. Take a top hat. You think you see it as it really is. But you don’t because you associate it with other things and ideas. If you had never heard of one before, and suddenly saw it alone, you’d be frightened, or you’d laugh. That is the effect absinthe has, and that is why it drives men mad. Three nights I sat up all night drinking absinthe, and thinking that I was singularly clear-headed and sane. The waiter came in and began watering the sawdust.The most wonderful flowers, tulips, lilies and roses, sprang up, and made a garden in the cafe. “Don’t you see them?” I said to him. “Mais non, monsieur, il n’y a rien.”
Kind of makes you want to go out and buy a bottle right now. Fortunately you can, because your right to drink it has been restored. The century-old moral panic is over. However, with that change, some of the cachet has been drained away from this yummy drink, which, as it turns out, is just a drink like any other: if you drink too much, you get drunk. Nothing special here.
The irony of the history here is that it was precisely the dire warnings, first issued in French medical journals in the mid 19th century, that created the vast demand for absinthe all over Europe and America. Dangerous drink? Bring it on. The British medical journals seemed to agree that absinthe was highly dangerous, citing this strange experiment from 1869:
The question whether absinthe exerts any special action other than that of alcohol in general, has been revived by some experiments by MM. Magnan and Bouchereau in France. These gentlemen placed a guinea-pig under a glass case with a saucer full of essence of wormwood (which is one of the flavouring matters of absinthe) by his side. Another guinea-pig was similarly shut up with a saucer full of pure alcohol. A cat and a rabbit were respectively enclosed along with a saucer each full of wormwood. The three animals which inhaled the vapours of wormwood experienced, first, excitement, and then epileptiform convulsions. The guinea-pig which merely breathed the fumes of alcohol, first became lively, then simply drunk. Upon these facts it is sought to establish the conclusion that the effects of excessive absinthe drinking are seriously different from those of ordinary alcoholic intemperance.
You can imagine, then, why that generation of artists, poets, playwrights, and literary gadabouts immediately seized on this drink and caused it to be the most fashionable in the land, spreading the plague of absinthism far and wide. Paintings, poetry, music were written in homage to the great muse of the green fairy. No doubt that people believed it, just as Dumbo thought it was the feather that made him fly.
At the height of the absinthe mania in France, 5:00pm became known as “the green hour.” The French were drinking 5 times as much absinthe as wine. The French producers were shipping all over the world. It became the world’s most notorious drink.
Here we have a classic case: science speaks of danger, daring people jump on the trend, moralists get outraged, government acts. That is precisely the situation that lasted for 100 years until it became rather obvious that absinthe is just a normal liquor.
The reason it gained the reputation for making people insane – Vincent Van Gogh, for example – is that highly fashionable people were drinking far too much. It was a classic fallacy: post hoc ergo propter hoc. A confusion of cause and effect. That was enough to effect a century of prohibition.
Here is another article from The Lancet in 1873 about the vast multitudes of “victims of absinthe.”
Originally the only important ingredient in its composition, besides alcohol, was the essential oil of absinthium, or wormwood; and though, doubtless, this added something to the mischievous effects of the liquor, it would be impossible to trace to it, or to the other comparatively trivial ingredients, the more serious of the special results which are now observed to occur in the victims of absinthe. An analysis recently made at the Conservatoire des Arts shows that the absinthe now contains a large proportion of antimony, a poison which cannot fail to add largely to the irritant effects necessarily produced on the alimentary canal and the liver by constant doses of a concentrated alcoholic liquid. As at present constituted, therefore, and especially when drunk in the disastrous excess now common in Paris, and taken frequently upon an empty stomach, absinthe forms a chronic poison of almost unequalled virulence, both as an irritant to the stomach and bowels, and also as a destroyer of the nervous system.
Science has spoken. What can you do but ban it? That didn’t happen until 1915 (the same few years in which every terrible trend in politics happened, from income taxation to central banking).
By then, the drink became associated with elaborate rituals that survive to this day, such as the slow-drip fountain that pours over a special steel spoon that holds a sugar cube. So far as I can tell, the ritual is entirely for show (if you want a bit of sweet in your drink, just add simple syrup) but it’s also enormously fun to reenact the faux-decadence of the absinthe generation. Even now, Amazon offers many absinthe fountains, most in the Victorian style of course.
The war on absinthe – this won’t surprise you – created the opposite of its intended effect. It raised the status of the drink and created a completely unwarranted hysteria in both directions: overconsumption followed by bans followed by speakeasy indulgence. Can you think of anything else, perhaps, that has fit that general model? Marijuana perhaps? Liquor in general? Tobacco? Politically incorrect speech?
Bans stemming from moral panics never seem to end, and people never seem to learn from this classic example. But in this case, the bans gradually came to an end. We’ve lived a full fifteen years of Absinthe freedom. And sure enough, with that freedom has come a bit of blase attitude toward it. Now it sits on the shelf in the liquor store as just another cocktail mixture, alongside the elderflower liqueurs and peach schnapps. It is said to be favored by people on the Keto diet because of its low-carb, low-sugar content.
And yet, to this day, you will still find people who drink it only with great apprehension and with some anticipation that they will soon not be themselves once it is tasted. Drink enough of it, and it will become true. The same is the case with gin, tequila, and rum.
There is surely another lesson here. Science has long served to back public panic, and that panic usually involves some fear of physical and moral corruption. We saw it with Absinthe, and then alcohol Prohibition. We saw it with AIDS. And we’ve lived through it with Covid and all the variants (Omicron!), as a naive public held closely to the words of Anthony Fauci, as the nation’s poet-prophet of a respiratory virus held court for two years, with changing instructions and never-ending insight about the need for all of us to upend our lives to control the invisible enemy.
It’s my habit, and maybe it should be yours, to celebrate every bit of freedom we gain back from the armies of authoritarians who wield the power of the state to improve our health and our lives. It took one hundred years, but they finally got their mitts off this one market. The research suggesting wormwood as a Covid treatment merits a visit from the green fairy as soon as possible.
Jeffrey A. Tucker is Founder and President of the Brownstone Institute and the author of many thousands of articles in the scholarly and popular press and ten books in 5 languages, most recently Liberty or Lockdown.
November 28, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science, Timeless or most popular |
Leave a comment
In a sense, I can’t believe I’m writing this article. From a scientific perspective, this issue has been firmly settled. The answer is very clearly “NO!”. And yet, if I google “is saturated fat unhealthy?”, then seven of the top nine results proclaim with great certainty that “yes, it is”.
Here’s what the NHS says to people living in the UK: “Too much saturated fat can increase the amount of cholesterol in the blood, which increases your risk of developing heart disease.”
And here’s what the US government tells its citizens: “Eating too many foods high in saturated fats can be bad for your health. By replacing saturated fats with unsaturated fats, you may lower your risk of getting heart disease.”
To be fair, the US government doesn’t sound quite as confident as the UK health authorities. There’s a lot of “can” and “may” in that sentence. Which is actually a bit funny, when you consider that it was the US government that got the whole world to cut down on saturated fats in the first place.
Interestingly, none of the self-appointed fact checking organizations that have sprung up in recent years has yet tried to pull the NHS or the US government off the internet for spreading misinformation.
The claim that saturated fat is unhealthy originated with physiologist Ancel Keys in the mid-part of the twentieth century. He initially believed that cholesterol in the diet was what caused heart disease. Unfortunately, he soon noticed that feeding people cholesterol had no effect whatsoever on the cholesterol levels in their blood streams. So he was forced to abandon that line of thinking. On doing some further research, he noticed that increasing the proportion of saturated fat in the diet did however appear to increase cholesterol somewhat.
This led him to develop the diet-heart hypothesis, which basically says the following: Saturated fat in the diet leads to increased cholesterol levels in the blood stream, which causes heart disease. So it’s a two part hypothesis. As I’ve already discussed before on this blog, the second part of the hypothesis has been disproven – cholesterol in the blood stream does not cause heart disease.
But what about the first part? Even if not through the intermediate action on cholesterol, saturated fat might still somehow be unhealthy. Ancel Keys claimed to have evidence that high levels of saturated fat in the diet correlates with heart disease. This evidence came from a very shaky observational data set called the “Seven Countries Study”, in which Keys presented results from relatively small, hand-picked cohorts in seven countries, which appeared to show a correlation between saturated fat intake and heart disease (and ignored data from a bunch of other countries where no such correlation could be seen).
But it’s now more than forty years after the Seven Countries Study was published, and there is thus no reason to rely any longer on what Ancel Keys claimed to have found. We can instead look at the wealth of data that’s been produced since then.
Let’s start with what the observational data show. A meta-analysis was published in the American Journal of Clinical Nutrition in 2010 that sought to find if the prospective cohort studies that had been carried out up to that point supported the notion that saturated fat causes heart disease.
A meta-analysis is a pooled analysis, where you take a bunch of studies and add their results together, to get a higher degree of statistical accuracy. A prospective cohort study is a study where you find two groups of people that vary in some significant respect, for example in terms of how much saturated fat they eat, and then follow them over time to see what happens – it’s generally considered to be the highest quality type of observational study, although it doesn’t reach the level of quality of a randomized controlled trial, because it isn’t able to get rid of confounding effects to the level that a randomized trial can (if you need to brush up on scientific method in the health sciences, read this).
Why are we even bothering to look at observational studies at all then, instead of just jumping straight to randomized trials? Because observational studies are easier to do, so there are more of them, and they can gather a lot more data. While a randomized trial with a few thousand people is huge, an observational study with a few thousand people is tiny. Additionally, as mentioned, the initial recommendation to eat less saturated fat was based on a single observational study, and quite a small one at that (the Seven Countries Study included less than 13,000 people – “Seven Countries” makes it sound much bigger than it was). So it’s interesting to see if the vast mass of observational data that we have today bears out the initial findings of the Seven Countries Study.
The authors of the meta-analysis identified 21 prospective cohort studies, with a total of almost 400,000 participants. That’s a big data set. The studies followed participants for between five and 23 years.
So, what did they find?
The difference in risk of cardiovascular disease between the groups with a high intake of saturated fat and those with a low intake of saturated fat was exactly zero. There was no difference at all. If you look more closely at the different kinds of cardiovascular disease, then you see a slightly increased risk of coronary heart disease in the saturated fat group (7% increased relative risk), but a slightly decreased risk of stroke (21% decreased relative risk). Neither of those differences were statistically significant, however. And in observational data sets, with all the risks of confounding they face, anything less than a halving or doubling of risk should be ignored, since small differences between groups are almost certainly caused by confounding factors.
Let’s move on and look at what the randomized controlled trials show. A Cochrane review was published in 2020 that looked at the ability of a diet low in saturated fat to prevent heart disease and death. 15 trials were identified, with a total of roughly 55,000 participants, and included in Cochrane’s meta-analysis. In most of the trials, the intervention consisted of dietary advice, although a few also provided polyunsaturated fats (so-called “healthy oils”), and told people to replace their lard and butter with them, and one provided participants with complete meal replacements. The trials lasted from two to eight years, with an average duration of five years.
Eleven of the 15 trials measured intake of saturated fats at multiple time points, and could thus confirm that intake of saturated fats decreased in the intervention group as compared with the control group. This is good to know, since if that wasn’t the case then a lack of benefit in terms of heart disease risk could simply be due to not managing to get people to change their diets sufficiently. So we know for certain that saturated fat intake decreased in at least eleven of the fifteen trials. Did this have any meaningful impact on people’s risk of having a heart attack or dying?
No, is the short answer. In the low saturated fat group, 6.4% of participants died, while in the high saturated fat group, 6.2% of participants died. So 0.2% more people died in the low saturated fat group than in the high saturated fat group. As you would expect for such a small difference, it isn’t statistically significant.
After the dark magic known as Mantel-Haenszel weighting (a statistical technique used in meta-analysis in which studies with more precise results are given greater weight), the authors reach the conclusion that it’s actually the other way around, that marginally less people should have died in the low saturated fat group, but the difference still isn’t statistically significant.
So it’s not possible to conclude that a diet high in saturated fat increases overall mortality. What about if we look specifically at heart attacks?
Most heart attacks are not fatal, so it’s possible that an intervention could lower heart attacks without meaningfully impacting overall risk of death. In the low saturated fat group, 3.3% of participants had a heart attack. In the high saturated fat group, 3.1% of participants had a heart attack. So the people in the high saturated fat group actually experienced fewer heart attacks than the people in the low saturated fat group.
Again, after statistical weighting, it appears that there should have been slightly fewer heart attacks in the group with the low saturated fat diet (rougly 0.3% less). Just as before, however, the difference isn’t statistically significant. What that means is that the small difference that was found is within the margin of error.
To conclude, the sum of all the observational and randomized trial evidence now available to us does not allow us to conclude that there is any increased risk of cardiovascular disease or death with increased intake of saturated fat. Considering that the data sets that these conclusions are based on are massive, we can be certain that even if there were a benefit, it would be so tiny as to not be worth bothering with. It is therefore shocking that public health agencies still tell their populations to cut down on saturated fats, instead of focusing on the things that have actually been shown to make a difference.
November 28, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular |
Leave a comment
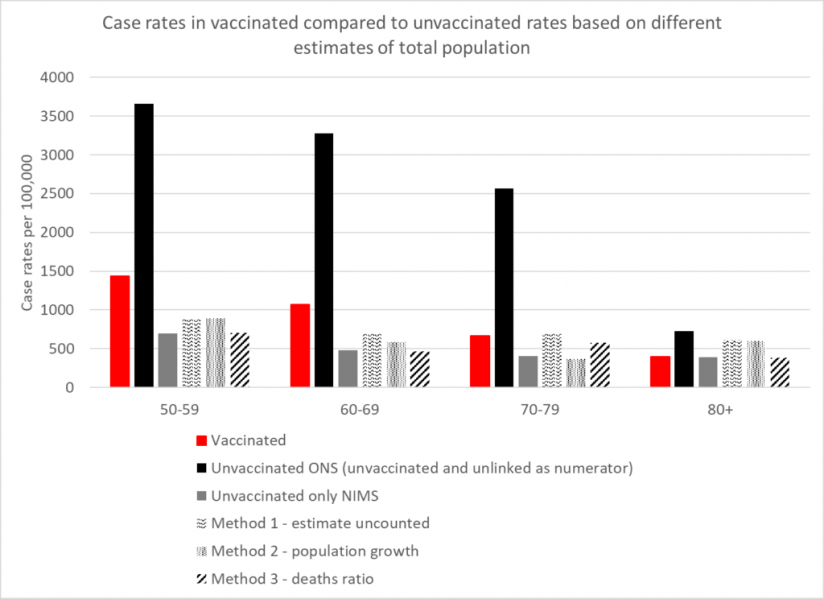
Back in October, when the critics rounded on the UKHSA for publishing vaccine data that didn’t fit the narrative, front and centre of their complaints was the claim that they were using poor estimates of the size of the unvaccinated population, and thus underestimating the infection rate in the unvaccinated. Cambridge’s Professor David Speigelhalter didn’t hold back, writing on Twitter that it was “completely unacceptable” for the agency to “put out absurd statistics showing case-rates higher in vaxxed than non-vaxxed” when it is “just an artefact of using hopelessly biased NIMS population estimates”.
To the UKHSA’s credit, while it conceded other points, it never gave in on this one, sticking to its view that the National Immunisation Management System (NIMS) was the “gold standard” for these estimates. It pointed out that ONS population estimates have problems of their own, not least that for some age groups the ONS supposes there to be fewer people in the population than the Government counts as being vaccinated.
How can we know which estimates are more accurate? A group of experts has applied analytical techniques in order to estimate the size of the unvaccinated population independently of ONS and NIMS figures. Using three different methods, experts from HART found that estimates from all three methods were in broad agreement with the NIMS estimates, whereas the ONS estimate was a much lower outlier.
The first method involves recognising that people not within the NHS database system still catch Covid and still get tested. Assuming these people have the same infection rates per 100,000 people as the unvaccinated, you can calculate how many people there are outside of the database system and add these to the NIMS totals.
The second method involves looking at the rate of growth of people with an NHS number, which has been remarkably steady at around 2.9% per year. If you assume that people who are not yet registered in the NHS will sometimes become sick enough to seek healthcare, and thus a record will be created for them, applying this growth rate to the 2011 ONS population estimates give another figure for the total population.
The third method involves assuming that, in low-Covid weeks, deaths within an age bracket should occur at a similar rate in vaccinated and unvaccinated, allowing the size of the total population to be inferred from the percentage of deaths in the unvaccinated.
The results in terms of reported infection rates according to the five different estimates are depicted in the chart above. They show that the ONS is a clear outlier, its estimates sitting far too low, and NIMS is likely to be much more accurate. The ONS puts the unvaccinated population at around 4.59 million whereas NIMS puts it at 9.92 million, a difference of 5.33 million. That’s a lot of people not to be included in estimates, and suggests, among other things, that the ONS has not adequately estimated the magnitude of illegal immigration into the country.
As well as vindicating the UKHSA in its decision to stick with NIMS over ONS, HART’s analysis also indicates that, contrary to the assertions of Prof Spiegelhalter, the UKHSA data showing infection rates higher in the vaccinated compared to the unvaccinated is not a mere artefact of using the wrong population estimates. There may be other biases in it, but this is not one of them.
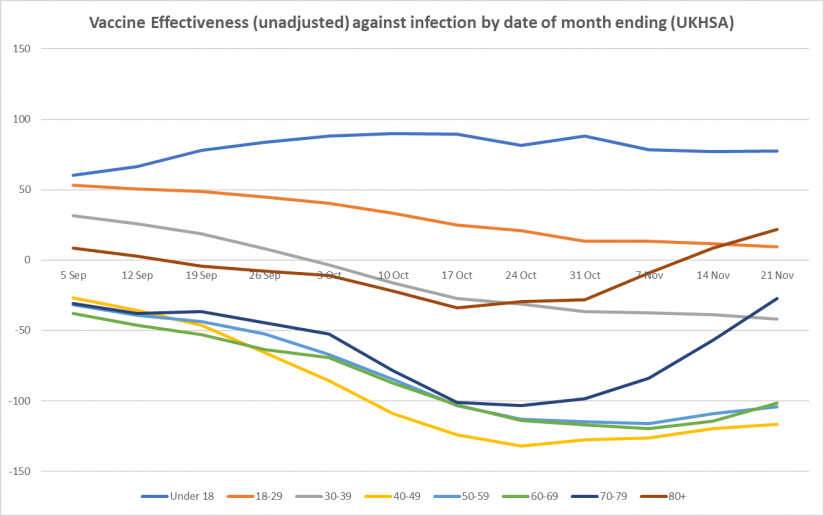
Here is the weekly update on unadjusted vaccine effectiveness based on the raw data in the UKHSA Vaccine Surveillance report. The unadjusted vaccine effectiveness estimates against infection have remained low in all adult age brackets this week, particularly in those aged 40-70, though there is little sign of further decline; in the older age groups (over 40), the recent vaccine effectiveness revival continues, possibly as a result of the third doses. There is also a sign of a rise in vaccine effectiveness against hospitalisation in the over-70s.



November 28, 2021
Posted by aletho |
Science and Pseudo-Science | COVID-19 Vaccine, UK |
Leave a comment
reports from SA indicate that the virus is VERY mild
aside from all the breathless reporting about “MOAR SPIKE MUTATIONS!!” i have yet to see a single report with any actual clinical evidence that the newly branded omicron variant is anything other than less dangerous than delta was.
it’s just, to steal a wonderful quote “mutational stargazing.”
this makes sense. not only are we continuing to evolve AWAY from an what looks near certain to be a lab engineered virulence optimum, but this is the natural path of viral evolution.
delta was a deeply attenuated version of prior versions. it’s original CFR was around 0.1%. this rose sharply over the summer as vaccine fade hit and this rise affected the vaccinated and the unvaccinated alike, so it appears to be a property of the virus, not of the vaccines. it was also mirrored by all cause mortality and so appears to be a real rise in fatality, not a definitional artifact.
i will still bet dollars to doughnuts that it was the vaccines themselves that, by being leaky but semi-protective, drove this inverted gradient to hotter strains.
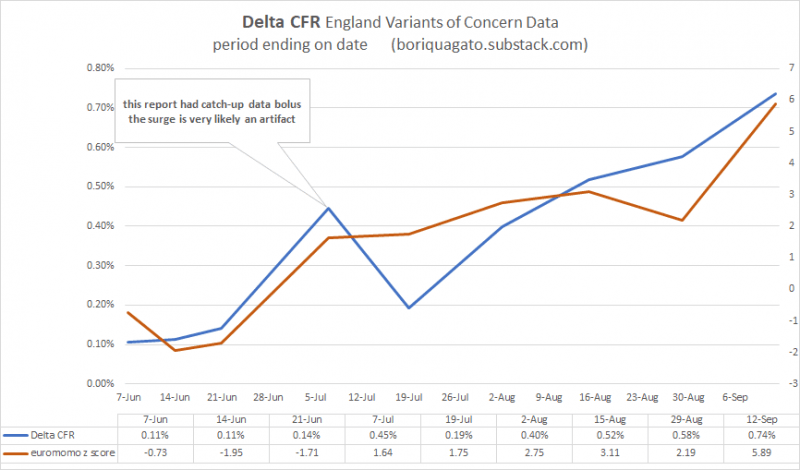
full discussion and data HERE.
a virus “wants” one thing: to spread. make a copy of me and pass it on. that’s the whole ballgame. harming the host and incapacitating them is maladaptive to this goal. mild viruses spread better. asymptomatic viruses spread best of all.
and that looks more and more like the case here. omicron looks milder than delta, especially than the souped up delta strains that emerged over the summer.
this is good news, not a reason for terror. the ideal outcome would be a virus with no symptoms and infinite spread that would immediately inoculate everyone.

primary symptoms appear to be lethargy. loss of taste and smell is largely absent.
ARTICLE
as this virus looks to outcompete delta, but with lower risk, the idea that we want to keep it out seems exactly wrong. this is the variant you want. more spread, considerably less risk, mostly asymptomatic, but will generate the real, sterilizing immunity that the vaccines do not.
this is how pandemics end, not how panics should begin.
watching the west once more lose its collective mind is just pathetic.
based on the early looks, this is not even a chipmunk in the road to swerve around, it’s the shadow of a chimpunk and it’s a less dangerous strain that the one we currently have and another even lower risk bite at the immunity apple.
whether it will follow delta in terms of vaccine mediated evolution toward hotter future strains is anyone’s guess (and certainly possible) but if it is, indeed, destined to do so, then that’s all the more reason to let it spread now.
“we should panic in case it turns out we need to panic” is simply not a basis for public health.
pandemics can and do end themselves and it’s become manifestly obvious that the vaccines developed here and pushed endlessly as panacea are of little to no help in that regard and quite a strong case to be made that they have made it, overall, worse for everyone, including the vaccinated.
boosters, lockdowns, and travel bans are not the way out. the generation of low risk natural herd immunity is.
it is long past time we stopped playing these stupid games.
the prizes we stand to win are not going to get any less stupid this time…
November 28, 2021
Posted by aletho |
Science and Pseudo-Science | Covid-19, COVID-19 Vaccine |
Leave a comment
I’m a voracious reader of Covid books but nothing could have prepared me for Scott Atlas’s A Plague Upon Our House, a full and mind-blowing account of the famed scientist’s personal experience with the Covid era and a luridly detailed account of his time at the White House. The book is hot fire, from page one to the last, and will permanently affect your view of not only this pandemic and the policy response but also the workings of public health in general.
Atlas’s book has exposed a scandal for the ages. It is enormously valuable because it fully blows up what seems to be an emerging fake story involving a supposedly Covid-denying president who did nothing vs. heroic scientists in the White House who urged compulsory mitigating measures consistent with prevailing scientific opinion. Not one word of that is true. Atlas’s book, I hope, makes it impossible to tell such tall tales without embarrassment.
Anyone who tells you this fictional story (including Deborah Birx) deserves to have this highly credible treatise tossed in his direction. The book is about the war between real science (and genuine public health), with Atlas as the voice for reason both before and during his time in the White House, vs. the enactment of brutal policies that never stood any chance of controlling the virus while causing tremendous damage to the people, to human liberty, to children in particular, but also to billions of people around the world.
For the reader, the author is our proxy, a reasonable and blunt man trapped in a world of lies, duplicity, backstabbing, opportunism, and fake science. He did his best but could not prevail against a powerful machine that cares nothing for facts, much less outcomes.
If you have heretofore believed that science drives pandemic public policy, this book will shock you. Atlas’s recounting of the unbearably poor thinking on the part of government-based “infectious disease experts” will make your jaw drop (thinking, for example, of Birx’s off-the-cuff theorizing about the relationship between masking and controlling case spreads).
Throughout the book, Atlas points to the enormous cost of the machinery of lockdowns, the preferred method of Anthony Fauci and Deborah Birx: missed cancer screenings, missed surgeries, nearly two years of educational losses, bankrupted small business, depression and drug overdoses, overall citizen demoralization, violations of religious freedom, all while public health massively neglected the actual at-risk population in long-term care facilities. Essentially, they were willing to dismantle everything we called civilization in the name of bludgeoning one pathogen without regard to the consequences.
The fake science of population-wide “models” drove policy instead of following the known information about risk profiles. “The one unusual feature of this virus was the fact that children had an extraordinarily low risk,” writes Atlas. “Yet this positive and reassuring news was never emphasized. Instead, with total disregard of the evidence of selective risk consistent with other respiratory viruses, public health officials recommended draconian isolation of everyone.”
“Restrictions on liberty were also destructive by inflaming class distinctions with their differential impact,” he writes, “exposing essential workers, sacrificing low-income families and kids, destroying single-parent homes, and eviscerating small businesses, while at the same time large companies were bailed out, elites worked from home with barely an interruption, and the ultra-rich got richer, leveraging their bully pulpit to demonize and cancel those who challenged their preferred policy options.”
In the midst of continued chaos, in August 2020, Atlas was called by Trump to help, not as a political appointee, not as a PR man for Trump, not as a DC fixer but as the only person who in nearly a year of unfolding catastrophe had a health-policy focus. He made it clear from the outset that he would only tell what he believed to be true; Trump agreed that this was precisely what he wanted and needed. Trump got an earful and gradually came around to a more rational view than that which caused him to wreck the American economy and society with his own hands and against his own instincts.
In Task Force meetings, Atlas was the only person who showed up with studies and on-the-ground information as opposed to mere charts of infections easily downloadable from popular websites. “A bigger surprise was that Fauci did not present scientific research on the pandemic to the group that I witnessed. Likewise, I never heard him speak about his own critical analysis of any published research studies. This was stunning to me. Aside from intermittent status updates about clinical trial enrollments, Fauci served the Task Force by offering an occasional comment or update on vaccine trial participant totals, mostly when the VP would turn to him and ask.”
When Atlas spoke up, it was almost always to contradict Fauci/Birx but he received no backing during meetings, only to have many people in attendance later congratulate him for speaking out. Still, he did have a convert in Trump himself, but by then it was too late: not even Trump could prevail against the wicked machine he had permissioned into operation.
It’s a Mr. Smith Goes to Washington story but applied to matters of public health. From the outset of this disease panic, policy came to be dictated by two government bureaucrats (Fauci and Birx) who, for some reason, were confident in their control over media, bureaucracies, and White House messaging, despite every attempt by the president, Atlas, and a few others to get them to pay attention to the actual science about which Fauci/Birx knew and care little.
Fortunately, we now have this book to set the record straight. It gives every reader an inside look at the workings of a system that wrecked our lives. If the book finally declines to offer an explanation for the hell that was visited upon us – every day we still ask the question why? – it does provide an accounting of the who, when, where, and what. Tragically, too many scientists, media figures, and intellectuals in general went along. Atlas’s account shows exactly what they signed up to defend, and it’s not pretty.
The cliche that kept coming to mind as I read is “breath of fresh air.” That metaphor describes the book perfectly: blessed relief from relentless propaganda. Imagine yourself trapped in an elevator with stultifying air in a building that is on fire and the smoke gradually seeps in from above. Someone is in there with you and he keeps assuring you that everything is fine, when it is obviously not.
That’s a pretty good description of how I felt from March 12, 2020 and onward. That was the day that President Trump spoke to the nation and announced that there would be no more travel from Europe. The tone in his voice was spooky. It was obvious that more was coming. He had clearly fallen sway to extremely bad advice, perhaps he was willing to push lockdowns as a plan to deal with a respiratory virus that was already widespread in the US from perhaps 5 to 6 months earlier.
It was the day that the darkness descended. A day later (March 13), the HHS distributed its lockdown plans for the nation. That weekend, Trump met for many hours with Anthony Fauci, Deborah Birx, son-in-law Jared Kushner, and only a few others. He came around to the idea of shutting down the American economy for two weeks. He presided over the calamitous March 16, 2020, press conference, at which Trump promised to beat the virus through general lockdowns.
Of course he had no power to do that directly but he could urge it to happen, all under the completely delusional promise that doing so would solve the virus problem. Two weeks later, the same gang persuaded him to extend the lockdowns.
Trump went along with the advice because it was the only advice he was fed at the time. They made it appear that the only choice that Trump had – if he wanted to beat the virus – was to wage war on his own policies that were pushing for a stronger, healthier economy. After surviving two impeachment attempts, and beating back years of hate from a nearly united media afflicted by severe derangement syndrome, Trump was finally hornswoggled.
Atlas writes: “On this highly important criterion of presidential management—taking responsibility to fully take charge of policy coming from the White House—I believe the president made a massive error in judgment. Against his own gut feeling, he delegated authority to medical bureaucrats, and then he failed to correct that mistake.”
The truly tragic fact that both Republicans and Democrats do not want spoken about is that this whole calamity did indeed begin with Trump’s decision. On this point, Atlas writes:
Yes, the president initially had gone along with the lockdowns proposed by Fauci and Birx, the “fifteen days to slow the spread,” even though he had serious misgivings. But I still believe the reason that he kept repeating his one question—“Do you agree with the initial shutdown?”—whenever he asked questions about the pandemic was precisely because he still had misgivings about it.
Large parts of the narrative are devoted to explaining precisely how and to what extent Trump had been betrayed. “They had convinced him to do exactly the opposite of what he would naturally do in any other circumstance,” Atlas writes, that is
“to disregard his own common sense and allow grossly incorrect policy advice to prevail… This president, widely known for his signature “You’re fired!” declaration, was misled by his closest political intimates. All for fear of what was inevitable anyway—skewering from an already hostile media. And on top of that tragic misjudgment, the election was lost anyway. So much for political strategists.”
There are so many valuable parts to the story that I cannot possibly recount them all. The language is brilliant, e.g. he calls the media “the most despicable group of unprincipled liars one could ever imagine.” He proves that assertion in page after page of shocking lies and distortions, mostly driven by political goals.
I was particularly struck by his chapter on testing, mainly because that whole racket mystified me throughout. From the outset, the CDC bungled the testing part of the pandemic story, attempting to keep the tests and process centralized in DC at the very time when the entire nation was in panic. Once that was finally fixed, months too late, mass and indiscriminate PCR testing became the desiderata of success within the White House. The problem was not just with the testing method:
“Fragments of dead virus hang around and can generate a positive test for many weeks or months, even though one is not generally contagious after two weeks. Moreover, PCR is extremely sensitive. It detects minute quantities of virus that do not transmit infection… Even the New York Times wrote in August that 90 percent or more of positive PCR tests falsely implied that someone was contagious. Sadly, during my entire time at the White House, this crucial fact would never even be addressed by anyone other than me at the Task Force meetings, let alone because for any public recommendation, even after I distributed data proving this critical point.”
The other problem is the wide assumption that more testing (however inaccurate) of whomever, whenever was always better. This model of maximizing tests seemed like a leftover from the HIV/AIDS crisis in which tracing was mostly useless in practice but at least made some sense in theory. For a widespread and mostly wild respiratory disease transmitted the way a cold virus is transmitted, this method was hopeless from the beginning. It became nothing but make work for tracing bureaucrats and testing enterprises that in the end only provided a fake metric of “success” that served to spread public panic.
Early on, Fauci had clearly said that there was no reason to get tested if you had no symptoms. Later, that common-sense outlook was thrown out the window and replaced with an agenda to test as many people as possible regardless of risk and regardless of symptoms. The resulting data enabled Fauci/Birx to keep everyone in a constant state of alarm. More test positivity to them implied only one thing: more lockdowns. Businesses needed to close harder, we all needed to mask harder, schools needed to stay closed longer, and travel needed to be ever more restricted. That assumption became so entrenched that not even the president’s own wishes (which had changed from Spring to Summer) made any difference.
Atlas’s first job, then, was to challenge this whole indiscriminate testing agenda. To his mind, testing needed to be about more than accumulating endless amounts of data, much of it without meaning; instead, testing should be directed toward a public-health goal. The people who needed tests were the vulnerable populations, particularly those in nursing homes, with the goal of saving lives among those who were actually threatened with severe outcomes. This push to test, contact trace, and quarantine anyone and everyone regardless of known risk was a huge distraction, and also caused huge disruption in schooling and enterprise.
To fix it meant changing the CDC guidelines. Atlas’s story of attempting to do that is eye-opening. He wrestled with every manner of bureaucrat and managed to get new guidelines written, only to find that they had been mysteriously reverted to the old guidelines one week later. He caught the “error” and insisted that his version prevail. Once they were issued by the CDC, the national press was all over it, with the story that the White House was pressuring the scientists at the CDC in terrible ways. After a week-long media storm, the guidelines changed yet again. All of Atlas’s work was made null.
Talk about discouraging! It was also Atlas’s first full experience in dealing with deep-state machinations. It was this way throughout the lockdown period, a machinery in place to implement, encourage, and enforce endless restrictions but no one person in particular was there to take responsibility for the policies or the outcomes, even as the ostensible head of state (Trump) was on record both publicly and privately opposing the policies that no one could seem to stop.
As an example of this, Atlas tells the story of bringing some massively important scientists to the White House to speak with Trump: Martin Kulldorff, Jay Bhattacharya, Joseph Ladapo, and Cody Meissner. People around the president thought the idea was great. But somehow the meeting kept being delayed. Again and again. When it finally went ahead, the schedulers only allowed for 5 minutes. But once they met with Trump himself, the president had other ideas and prolonged the meeting for an hour and a half, asking the scientists all kinds of questions about viruses, policy, the initial lockdowns, the risks to individuals, and so on.
The president was so impressed with their views and knowledge – what a dramatic change that must have been for him – that he invited filming to be done plus pictures to be taken. He wanted to make it a big public splash. It never happened. Literally. White House press somehow got the message that this meeting never happened. The first anyone will have known about it other than White House employees is from Atlas’s book.
Two months later, Atlas was instrumental in bringing in not only two of those scientists but also the famed Sunetra Gupta of Oxford. They met with the HHS secretary but this meeting too was buried in the press. No dissent was allowed. The bureaucrats were in charge, regardless of the wishes of the president.
Another case in point was during Trump’s own bout with Covid in early October. Atlas was nearly sure that he would be fine but he was forbidden from talking to the press. The entire White House communications office was frozen for four days, with no one speaking to the press. This was against Trump’s own wishes. This left the media to speculate that he was on his deathbed, so when he came back to the White House and announced that Covid is not to be feared, it was a shock to the nation. From my own point of view, this was truly Trump’s finest moment. To learn of the internal machinations happening behind the scenes is pretty shocking.
I can’t possibly cover the wealth of material in this book, and I expect this brief review to be one of several that I write. I do have a few disagreements. First, I think the author is too uncritical toward Operation Warp Speed and doesn’t really address how the vaccines were wildly oversold, to say nothing of growing concerns about safety, which were not addressed in the trials. Second, he seems to approve of Trump’s March 12th travel restrictions, which struck me as brutal and pointless, and the real beginning of the unfolding disaster. Third, Atlas inadvertently seems to perpetuate the distortion that Trump recommended ingesting bleach during a press conference. I know that this was all over the papers. But I’ve read the transcript of that press conference several times and find nothing like this. Trump actually makes clear that he was speaking about cleaning surfaces. This might be yet another case of outright media lies.
All that aside, this book reveals everything about the insanity of 2020 and 2021, years in which good sense, good science, historical precedent, human rights, and concerns for human liberty were all thrown into the trash, not just in the US but all over the world.
Atlas summarizes the big picture:
“in considering all the surprising events that unfolded in this past year, two in particular stand out. I have been shocked at the enormous power of government officials to unilaterally decree a sudden and severe shutdown of society—to simply close businesses and schools by edict, restrict personal movements, mandate behavior, regulate interactions with our family members, and eliminate our most basic freedoms, without any defined end and with little accountability.”
Atlas is correct that “the management of this pandemic has left a stain on many of America’s once noble institutions, including our elite universities, research institutes and journals, and public health agencies. Earning it back will not be easy.”
Internationally, we have Sweden as an example of a country that (mostly) kept its sanity. Domestically, we have South Dakota as an example of a place that stayed open, preserving freedom throughout. And thanks in large part to Atlas’s behind-the-scenes work, we have the example of Florida, whose governor did care about the actual science and ended up preserving freedom in the state even as the elderly population there experienced the greatest possible protection from the virus.
We all owe Atlas an enormous debt of gratitude, for it was he who persuaded the Florida governor to choose the path of focussed protection as advocated by the Great Barrington Declaration, which Atlas cites as the “single document that will go down as one of the most important publications in the pandemic, as it lent undeniable credibility to focused protection and provided courage to thousands of additional medical scientists and public health leaders to come forward.”
Atlas experienced the worst of the slings, arrows, and worse. The media and the bureaucrats tried to shut him up, shut him down, and body bag him professionally and personally. Cancelled, meaning removed from the roster of functional, dignified human beings. Even colleagues at Stanford University joined in the lynch mob, much to their disgrace. And yet this book is that of a man who has prevailed against them.
In that sense, it is easily the most crucial first-person account we have so far. It is gripping, revealing, devastating for the lockdowners and their vaccine-mandating successors, and a true classic that will stand the test of time. It’s simply not possible to write the history of this disaster without a close examination of this erudite first-hand account.
Jeffrey A. Tucker is Founder and President of the Brownstone Institute and the author of many thousands of articles in the scholarly and popular press and ten books in 5 languages, most recently Liberty or Lockdown.
November 28, 2021
Posted by aletho |
Book Review, Civil Liberties, Economics, Science and Pseudo-Science, Timeless or most popular | Covid-19, Florida, Human rights, United States |
Leave a comment
EARLIER this month Dr Byram Bridle, a Canadian viral immunologist whose faculty at the University of Ontario has disowned him for his repeated assertion that Covid-19 vaccines are not safe, gave a remarkable off-the-cuff interview to a reporter. Bridle starts by explaining the reasons why heavily vaccinated countries are experiencing high case rates, why adverse reactions are not being reported or diagnosed and discusses the overwhelming evidence for ivermectin as an ant-viral treatment for Covid where studies have been conducted correctly.
You can watch the full video below.
DR BYRAM BRIDLE: A recent study came out looking at 68 different countries and they plotted on a graph the case rate for Covid-19 and the vaccination rate in the country. And the more vaccinated the country is, the more problems they’re having with Covid-19. So these people have the vaccine. Remember all the antibody titers they’re showing, that’s in the blood, but these people, on average, are quite poorly protected in their upper airways. And it’s not the virus that’s deep down in the alveoli that gets transmitted to other people because of the dead airspace when we exhale. It’s the viral particles that are in the upper airways. So that’s why the vaccinated can spread this just as efficiently as somebody who’s completely unprotected. And so these vaccines on that basis, because they don’t come close to conferring sterilising immunity, they don’t properly protect the upper respiratory tract, they only confer about four and a half months of immunity, it’s absolutely 100 per cent impossible to achieve the goal of herd immunity with these vaccines. 100 per cent impossible.
What I’ve seen way too much of – and it does cause me very serious concern – is we’re seeing people who had cancers that were in remission or that were being well-controlled, and their cancers have gone completely out of control after getting the vaccine. And what we do know with the vaccine is the vaccine causes at least a temporary drop in T-cell numbers and those T-cells are part of our immune system, and they’re the critical weapons that our immune system has to fight off cancerous cells. So there’s a potential mechanism there. And all I can say is I’ve seen . . . I’ve had people contact me with way too many of these reports for me to feel comfortable. I do feel that that’s probably, I would say, my newest major safety concern. And it’s also the one that is going to be by far the most underreported on any adverse event database. Because if somebody’s had a cancer before the vaccine, there’s no way public health officials will ever link it to the vaccine. But what we’re seeing is oncology teams that had pushed the cancers into remission or keeping them well-controlled can no longer control them after the vaccine.
So we know in Canada it’s very upsetting, because in Canada we have a system that will never, never detect problems with these vaccines – that’s why we’ve always had to rely on other countries. Like with the AstraZeneca vaccine, we told Canadians that the AstraZeneca vaccine was 100 per cent safe, despite the fact that 12 European countries had paused the programme to look for potential links to the blood clotting, potentially fatal blood clotting. And we were told as Canadians that we didn’t have to worry because ours was from a . . . they announced that the problem was associated with a single batch from a single production facility in Europe and ours was coming from India and therefore it didn’t apply to us. The European Medicines Agency will tell you that was never the case. And of course, then eventually, after there were Canadians that did die and many that did have to be treated for the blood clots, then we finally admitted that it was a problem.
And that’s how our system . . . our system is never going to work, because this is the thing. First of all, we’re not informing people when they get the vaccine that they’re to report any unusual medical condition up to eight weeks after receiving a dose of the vaccine. And then the attending physician is required to, by law, to report anything unusual. Most physicians are not. And now some of them are . . . many don’t, because they don’t want to contradict the current narrative. And the College of Physicians and Surgeons of Ontario has turned out to be incredibly tyrannical and are crushing many physicians and threatening many who don’t go with this narrow public health narrative. Many also can’t get their submissions done because they’re onerous. So, for example, British Columbia can take up to 40 minutes to submit one of these reports, and you can imagine if there’s an Emergency Room physician who sees five people in a shift that come in with problems and have recently been vaccinated, they can’t afford to spend hours on that shift, reporting it, right?
So there’s many reasons why people aren’t reporting to the physicians, and there are many reasons why the physicians aren’t reporting to the local Medical Officer of Health. And that’s the next step is, if a physician submits it, it doesn’t necessarily go into our database, it goes to the local Medical Officer of Health. This is the thing: the physicians are not supposed to make a determination of whether they think the medical condition that’s occurred after the vaccine is or is not related to the vaccine. They’re not supposed to make that determination. The local Medical Officers of Health are. And as you can imagine, with the huge bias that exists there, the majority of them, we’re seeing unusually high percentages of these reports that do get submitted being rejected at the level of the local Medical Officer of Health. And then from there, the ones that they do approve go to the Public Health Agency of Canada and then they could be filed into our adverse event database. But because of that, because of all the filtering that’s going on, this is the problem. We’re not getting accurate numbers.
So yes, a statistician, of course, could be looking for these. But if you don’t get accurate numbers reported, you can do all the analysis you want, it’s not going to be accurate, right? Your analysis is only as accurate as the data, the raw data you have to work with.
A D-dimer test is definitely a good one to do, because it can be suggestive of micro clots, which could be an indicator of blood clotting. But yeah, we’re finding that most physicians won’t do it. And we’re also finding a shortage, actually, of the blood collection tubes that are needed to do that as well.
Yeah, yeah, no, this is a virus. But ivermectin has clear-cut antiviral properties. For example, it has multiple mechanisms of action, but one is it inhibits the binding of the spike protein on the virus to these receptors that we have on the cells of our lungs. And yeah, what’s interesting is a lot of countries . . . so, that’s what’s frustrating for me as a vaccine developer, I knew that there was going to be no outlet for the vaccines if there were effective early treatment strategies. So I followed the science for the early treatment strategies, and I saw that the studies were flawed early on.
For example, a lot of the studies that were being done were being done in countries where things like ivermectin were available over the counter. So in other words, they were testing their treatment group, which was getting a defined amount of ivermectin and comparing it to a control group which had an undefined amount of ivermectin. So essentially comparing ivermectin treatment to ivermectin treatment, right? And then they showed there was no benefit. Well, of course not. If you’re comparing, you know, a treatment group to a treatment group.
And so when the science has been done properly, there’s an overwhelming [body] of scientific data showing that it works. And so even though I love vaccines, I couldn’t help but wonder why we were providing initially this authorisation for interim use, what we call emergency use in the United States, because we had clear, effective early treatments. I have worked with many physicians. These things clearly work. In fact, a lot of the countries that are having the most success, like, for example, a lot of the low income countries have had no choice. I mean, look, they’ve been left to take the leftovers for the vaccines. They can’t afford a lot of expensive treatments. So they have been relying on these effective early treatment strategies using repurposed generic drugs that are really cheap, and they’ve had a huge success.
So, for example, Egypt is a good example. Egypt, you know, Egypt has a three per cent vaccination rate. Three per cent of their eligible population is double vaccinated compared with Canada, which is at around 64 or 66 per cent. And they have 14 cases of Covid-19 per 100,000 people per day on average, whereas we have about 570 cases per day, so vastly higher.
And this is what people are seeing. A recent study came out looking at 68 different countries, and they plotted on a graph the case rate for Covid-19 and the vaccination rate in the country. And the more vaccinated the country is, the more problems they’re having with Covid-19. And when you look at these countries that have low vaccination rates, they’ve been relying on effective early treatment strategies.
So for example, with Egypt, I didn’t realise, but I asked that question to my collaborators, ‘What is Egypt doing right that we’re not doing here in North America?’ They sent me the official treatment protocol for Covid-19. Do you know what the number one thing is that they go to first? [It] is hydroxychloroquine and number two is ivermectin.
And if you look at Israel – Israel has the highest vaccination rate in the world, right? And the Delta variant is completely out of control, which is why they’ve been administering the third dose, why they’ve committed to a fourth dose. And with these numbers I was telling you, so they have the highest vaccination rates. So again, keep this in mind so as to understand – Egypt: three per cent vaccination rate, 14 cases per 100,000 of the population per day. Israel is at over an 80 per cent vaccination rate and has over 5,000 cases right now per day.
So these things work best as an early treatment strategy, so they should be administered. The sooner you administer them, the better the outcome. So we’ve had physicians – and I know these people and they’re good friends of mine – who have been absolutely destroyed for using ivermectin with their patients, and they’ve kept their patients out of the hospital, they’ve kept them out of the ICU. I find this exceptionally frustrating because I keep getting criticised for raising my concerns about the vaccines and harms, and I have physicians coming at me and saying, ‘Well, if only you saw on the front lines what happens to people who die from Covid and how terrible it is.’ And yes, it’s awful, and I feel terrible for all of them. But the other thing that I point out is it’s estimated that more than half the people that have died in this pandemic would be alive today if we had accepted these early treatment strategies. That’s the reality, and I’ve seen it with every physician who has administered this. They talk about our ICUs being overrun, but every physician that I have worked with – and I’ve worked with many who have used these effective treatment strategies – they’ve kept their patients out of the ICU. They don’t go to the ICU and they don’t die.
Do you realise that the way we’ve been treating patients is they go to the hospital and if they aren’t sick enough to go on a respirator, they typically get sent home and it’s, you know, take fluids and some of these other . . . maybe some aspirin. It’s basically what were they like to call in medicine, ‘watchful waiting’, which means, ‘we’re going to do nothing’, right? And you literally have to wait till you’re sick enough to come in and basically be put in the ICU and put on a respirator.
That’s not how you treat disease, right? The earlier you intervene, the better the outcome. And we have these early treatment strategies, and I think it’s no coincidence the only one we’ve approved in Canada is called remdesivir. It does have genuine safety issues and does virtually nothing for Covid-19. But it’s on patent and there’s tons of money that can be made. These other ones are dirt cheap. Ivermectin, you can treat somebody for about a dollar a day. So they’ve been using it to great effect in all these low income countries. But in North America, we’ve refused to adopt these strategies.
And you have to understand, and they even talk about safety issues. Well, one of the things is, so, there’s rare cases of safety issues associated with using the veterinary form, and that’s simply because of calculation errors – people making simple mathematical errors when trying to convert to the human dose. And the reality is that ivermectin is on the list for the World Health Organisation of one of the 50 most needed drugs in the entire world, has an unbelievable safety record. It’s used worldwide to effectively treat all these parasitic diseases. It was approved by Health Canada in 2018 to treat exotic parasitic diseases when Canadians are travelling. And so there’s absolutely no excuse.
…
Dr Bridle: My own physician, honestly, criticised me, saying I’m giving out this messaging, talking about patients of hers that died.
I respectfully pointed out that I’m also on the front lines and I’m trying to deal on a daily basis with family members of people who have died from the Covid-19 vaccines. And so I’m seeing these horrible deaths as well on the other side.
And the difference to me is, had they not rejected these effective early treatment strategies, at least half of the patients that died in their practices would be alive today.
So I’m sorry, I don’t have a lot of patience for these physicians. And I’m just going to point out one thing as well that’s important for the general public to know. I usually don’t ever, ever criticise anybody’s expertise in their particular area of work. But we’re in unique times. And so I think the public needs to be aware.
We put a lot of faith in our physicians. The average family physician knows almost nothing about immunology and certainly about vaccines. People forget vaccinology is a sub-discipline of immunology. The average family physician in Canada gets between five and ten lectures in their first year on immunology, of which a tiny fraction of that is going to be dealing with vaccines.
They are not immunologists, they are not vaccinologists and they’re ignoring the vaccinologist here in Canada. They are promoting the vaccines and the reality is they don’t understand the science, and they do not have a deep enough understanding, on average, to understand the science and to understand the debates that are going on.
Interviewer: If information has been deliberately suppressed about these treatments, that would be a crime, seeing that people are dying?
Dr Bridle: Yes. Yes.
Interviewer: Doctor, will we see a national debate, like with top scientists on this subject ever in Canada? Like their side for pro, and our side? Do you think we’ll ever see that in Canada?
Dr Bridle: I and my colleagues have been open to that for months, many months. I would love to see it done. The public should be insisting on it, like the old-fashioned good scientific debates.
I would argue scientists can talk about the science. We can put aside our emotions. We can talk about it respectfully. I would argue what I would like to see happen is have a team – if it’s too big, it gets a little unwieldy – so I’d say between three and five scientists and/or physicians who want to debate both aspects of the Covid-19 policies and then have it moderated by somebody. And it has to be very public.
And that’s what I keep pointing out to the public. People who keep arguing that those of us who have legitimate concerns are wrong, providing misinformation, that we’re lying and that we don’t know what we’re talking about, have to keep asking themselves why then are many of us standing there in the arena like the gladiators of old? We’re standing in the arena, we’re waiting. None of their champions will step forward. None. We’ve tried it.
So we tried this in Ontario with (their Premier) Doug Ford. It was attempted in Alberta. It was attempted in Saskatchewan, where their premiers were also invited to have these open scientific discussions.
Nobody so far – and I know I’ve issued invitations. Every single person who attacks me I invite them to come on and talk publicly. I was even being interviewed once and live in the chat somebody was trolling the whole talk.
It was interesting. The person who was interviewing me stopped and invited the person to come on. They logged off pretty quickly. And that’s what we’re seeing over and over again. It’s remarkable.
I’ve asked thousands of people, not one person, not even one, in all these months has been willing to talk openly, publicly about the science and medicine underlying Covid-19. It’s exceptionally frustrating.
Even my own colleagues at the university who have attacked me, there are 83 of them, about that number, who signed a letter to the public saying that I was lying to the public, providing misinformation.
Do you realise some of these individuals were just down the hallway from me, in the same hallway, just a few doors down? None, not one of them, not one of those people was ever willing to talk to me on the phone, in a Zoom meeting or come to my office – and I have an open door policy and I invited many of them to do so – not one person.
And then, even after they signed that off, saying that I was giving misinformation, I had written a scientific document to outline the science that I’d been talking about, because this was birthed from a short interview that I gave on the radio, where I expressed concerns that the messenger RNA vaccines might be linked to the heart inflammation that was occurring in young people. And then I was attacked on that.
I wrote a document with all the science because, of course, I was not able to deliver all of my scientific arguments in that short interview.
People argued to the public, ‘You realise he only told you half the story.’ And I laugh about that because I say, ‘Well, you’re giving me far too much credit because I didn’t even get to deliver one per cent of the story.’
They’re trying to mean that I didn’t get to the other side of the story. No, there was so much more science, so many more mechanisms of action, of potential harm of these things.
And after I wrote that document, this letter was written by my colleagues. You realise that of those who I was able to get a straight answer from, none of them had even read my science. None of them had even bothered to see what my arguments were for my position. This is what’s happening right now, and the censorship is extreme it’s really unbelievable.
Interviewer: Some of your colleagues, they also said that it doesn’t alter DNA. Would you care to comment on that?
Dr Bridle: Yeah. So when it comes to the DNA, there isn’t sufficient data to … my personal opinion is that it’s not substantially altering the DNA.
All I can tell you is it was thought that human cells did not have a type of protein that’s needed to convert the messenger RNA in the vaccine into DNA. It turns out we do actually have these types of proteins present. So it’s theoretically possible.
Personally, I would think that it’s probably not a substantial issue, but theoretically possible. So as this is theoretically possible, I would argue as a scientist that it would be worthwhile investigating that – doing the research just to alleviate our concerns, people’s concerns, about that.
That’s the thing, people ask these questions and as you see that there’s theoretical possibilities for these happening, that used to be the scientific basis for then conducting the research and definitively answering people’s questions. So many of the questions that you have, I can’t definitively answer because we’ve lost this whole concept of conducting research to address the tough questions.
Interviewer: What I find interesting with what you’re saying is what I’m seeing, very clearly, is you’re confronting a talking point, not a science. And let me illustrate what I mean by that.
You ask a doctor about all this and what’s their answer if you really push them? ‘Well, we’re following the advice of x, y, z and they’re following the science that we trusted?’ Right? You go to the level above them, same thing. You go to the level above them, same thing.
Dr Bridle: We’ve tried, as scientists …
Interviewer: I understand that. You guys will talk to science because you’re working with it. The other side is purposely convoluting science from a talking point.
Dr Bridle: Yes.
Interviewer: I honestly wonder if they have a science. My wife and I survived …
Dr Bridle: Well, at this point I can tell you, as a scientist – that’s why I’m willing to debate anybody on it – they don’t have the science on their side. That’s very clear. And in fact, you no longer need to understand the science, you just need to understand the contradictions that are coming.
Because, this is the thing, the reason why people like Dr Palmer and myself can stand up and talk off the cuff without any script here is because we’re speaking the truth. We’re speaking based on our knowledge, and we don’t have to keep track of a story when we’re speaking the truth.
We don’t have to make sure that what we’re saying today matches what we said at last week’s rally or the one before that. But the public health narrative has become so discombobulated now that they’re constantly contradicting themselves.
And there’s so many examples that I could give you. But let’s take one, for example. I encourage people now to start taking headlines from the mainstream media from months ago, which had people like myself censored, and line them up side-by-side with headlines that they have today.
‘So a great example is this whole issue of the vaccine mandate and the fact that, you know, what are we telling people right now? If you have one dose of the vaccine, you’re lumped in with the unvaccinated. You’re dangerous, you’re the same as somebody who has been unvaccinated, you’re unprotected and you’re going to kill everybody else, right?
We know from the very get-go, the two-dose regimen was proclaimed to have 95 per cent effectiveness. So, this is the thing, a lot of people who are accepting this current messaging about the ‘one dose doesn’t count’ have forgotten about the one-dose summer.
Remember when Trudeau (the Canadian Prime Minister) was pushing and all we were hearing about was the one-dose summer? So in Canada, the world was watching us in bewilderment and wondering what the basis was for us going from the approved three or four-week interval, depending on whether it was the Pfizer or Moderna vaccine, to a four-month interval.
And if you recall, the reason why we could go for the one-dose summer and not worry about getting people two doses is because we were told one dose was 95 per cent effective.
‘A lot of you don’t realise this. If you don’t believe me, you can go on the Health Canada website right now and look. They will have on there that the one dose of the Pfizer vaccine is 95 per cent effective.
So now you have to start asking yourself, using their own messaging: If one dose is 95 per cent effective and two doses is 95 per cent effective, then why are the people with one dose being lumped in with those who are unvaccinated? Why was that OK then, when trying to justify going to a four-month interval, which had no scientific basis?
But now those same people who are sitting with one dose are told, ‘No, no, no. It’s not 95 per cent effective, it’s the equivalent of being unvaccinated altogether.’
This is where we’re getting to. So on that basis alone, that’s what I’m saying is, it’s become blatantly obvious. You don’t have to understand the science. They are not following the science, they’re contradicting themselves over and over and over again.
…
DR BYRAM BRIDLE: There’s been a remarkable number of young people who have died for no apparent reason. And in many cases, we can’t confirm their vaccination status. But I’ve been particularly concerned about the number of varsity athletes at our universities who have been dying completely unexpectedly and suddenly. And the only thing that I can tell you – and I don’t know whether they were or were not vaccinated – well, actually, I can’t tell you when they were vaccinated. What I can tell you is that no varsity athlete in Ontario can participate in a varsity team without being vaccinated. They weren’t allowed exemptions.
INTERVIEWER: My point on that example was simply this: if you’re following the science, that first statement that that head doc released would never be said.
BRIDLE: Yes.
INTERVIEWER: You would say, ‘We don’t know.’
BRIDLE: Exactly. That’s exactly, yes.
INTERVIEWER: But that’s the way they’re reporting it tells you . . .
BRIDLE: As you heard from me, yeah.
INTERVIEWER: . . . their complete agenda.
BRIDLE: As you heard from me. I won’t say definitively that it’s because of the vaccine. I’m a scientist, I’m open to that possibility that there is some other underlying condition with any individual case. But there’s too many of these to not investigate properly. Absolutely.
INTERVIEWER: And if anybody’s paying attention, that whole approach should really put your guard up.
BRIDLE: Yes.
INTERVIEWER: You should realise there’s something drastically wrong with public health officials who would talk with that kind of language.
BRIDLE: Yeah, well, look at the language. So, another contradiction is . . . so, for example, at my university, our president hosted the local Medical Officer of Health who declared the whole reason why the vaccine mandate made so much sense is that there is essentially no such thing as a breakthrough infection. And that’s still being claimed by many, although their ability to claim that continues to be eroded. But that was the idea, and they cited like a 0.003 per cent breakthrough infection rate, so essentially zero, meaning you’re completely protected.
And when our President was asked about that recently, she actually created quite a furore on our campus, because she completely contradicted the messaging that they had just given. Well, the reason why, of course, they still have to mask and physically distance is because, hey, you know, it’s well known that people who are vaccinated can still get infected, still get Covid and transmit the virus. And in fact, there’s very good immunological reasons why people who are vaccinated can still transmit the virus and the scientific data that is emerging is showing that they can transmit at least as efficiently as somebody who has no immunity whatsoever.
And the reason is, is because when we put the vaccine in the shoulder, we’re tricking our bodies into thinking that it’s what we call systemic infection. And so, the problem is that is where your body wants to protect the most is the blood, because if a pathogen gets into the blood it can disseminate throughout the whole body. And so we got all these antibodies in the blood.
So, the one place in our respiratory system where these antibodies will spill over into, if you’re trying to protect against a systemic infection, are the lower airways. And that’s because you just think about gas exchange. There’s barely a physical barrier between the alveolar space and the blood vessels to allow that ready air exchange, which also means it’s very easy for a pathogen that gets deep into the lungs – so that would be what we call pneumonia – for that pathogen to get into the blood. So we put antibodies in the lower airways if we think we have a systemic infection. But we aren’t getting proper antibody protection in the upper airways like we would if we were naturally infected. So these people that have the vaccine, yeah, remember all the antibody titers they’re showing, that’s in the blood. But these people, on average, are quite poorly protected in their upper airways. And it’s not the virus that’s deep down the alveoli that gets transmitted to other people, because of the dead airspace when we exhale, it’s the viral particles that are in the upper airways. So that’s why the vaccinated can spread this just as efficiently as somebody who’s completely unprotected.
And so these vaccines, on that basis, because they don’t come close to conferring sterilising immunity, they don’t properly protect the upper respiratory tract. They only confer about four and a half months of immunity. It’s absolutely 100 per cent impossible to achieve the goal of herd immunity with these vaccines. 100 per cent impossible. For these companies it would be such a quick and easy and cheap study to do, and they could definitively rule this problem in or out. And whenever there’s such easy to do research to be done and they won’t do it, that for me is always a red flag.
INTERVIEWER: Yeah, exactly why isn’t that happening?
DR BYRAM BRIDLE: Yes. All I can say is, again, we’re not being provided with accurate data. So it’s hard to answer any of these questions to do with, you know, what’s actually due to COVID, what’s due to other things? And how we’re defining these things is crazy. Like I said, we’re not even defining somebody who’s vaccinated until they’re 14 days out from their second dose. The second dose is serving as a booster, right? And so typically, the immune response would be peaking actually about five to ten days after receiving that. So we’re actually taking people who would theoretically be at the absolute peak of a vaccine-induced immunity, and we’re calling them not fully vaccinated, for example.
And so for example, if people were to die in that time frame, even if it was linked to the vaccine, it’d be linked as somebody who was not fully vaccinated having died. So it’s very difficult with all these kind of nuances that are going on. All I can say really is what we do know is that the problem of Covid, the number of cases has been dramatically overestimated, but to an unknown degree, because of the way we’ve misused the PCR test. And we know that the problems associate with the vaccines have been grossly underestimated, but to an unknown degree.
And so until we have accurate numbers for these – which I can’t see we’re going to have at any time soon unless we completely change the way we’re monitoring these things – we’re not going to be able to come up with accurate assessments as scientists of . . . you know, with these kind of questions. But the issue was at the beginning, or the problem was, people kept arguing that this could have between a 1 and 10 per cent fatality rate, infection fatality rate, meaning for every 100 people who were infected with the virus between 1 and 10 would die. But the thing is, as we never knew what the proper denominator was, how many people were getting infected – we still don’t know, because again, like I mentioned, there’s many of us . . . well, in fact, just right here, there was an individual who has gone now, but showed me his test result. He had had a positive Covid test result almost a year and a half ago, when he showed me his antibody response for the spike protein, it’s higher, way higher than the average person who’s been vaccinated at the peak, at the peak of their antibody response. So there’s somebody who clearly acquired immunity naturally. And we’re not tracking these people at all, because in many cases where people have actually been infected they didn’t even know it and have natural immunity.
We’re running this clinical trial where we’re evaluating natural acquisition of immunity. We’re finding a huge number of people who never realised that they were sick have clear evidence of immunity against this virus. So that means that for those individuals they were infected but this was not a pathogen for them and they recovered without, you know, without developing disease. And so we have no idea – and we now know this is much more common than we accepted at the beginning – but we have no idea just how common, right?
So the point is, we still don’t know the full extent of the denominator. But when it was updated in February, what was published at that time was that the infection fatality rate was 0.15 – so not even 1 per cent like we were being told, but 0.15 per cent – and that was for the entire population. And if you took out those who were 70 years and older, it dropped to 0.05 per cent. So, just to put that into perspective, a bad flu season would be at 0.1 per cent.
So again, if you go out of the high risk, the highest risk demographic, those over 70. And we’re actually dealing with a problem that is less fatal than the annual flu. And especially when we start talking about children – we’ve had one infant in BC who died. We’re, you’re talking about taking these vaccines down now, in the next phase, to five-year-olds and then all the way down to six months of age. And when you start getting down to under ten years of age, virtually nobody has died. And when you look at the flu, it’s far more dangerous for these individuals.
And if you want to look at another one, respiratory syncytial virus, which we live with – far more dangerous to young people. And this is where even pregnant or breastfeeding women are being told, encouraged, to get vaccinated to protect their infants. It’s crazy. It’s all based on this . . . it’s easy to make people feel that infants are very fragile, very fragile human beings, which in some ways they are. But when it comes to SARS-CoV-2, this was presented today: the younger you are, the fewer receptors you express in your respiratory system that this virus can use to latch on to your cells. And in fact, when you get down into the infants, they’re quite resistant to infection with this virus. And that’s why we haven’t been seeing deaths among that population.
So it’s very unusual, with any other infectious disease you always have two peaks: the frail elderly and the very young. And it’s very clear why, because the frail elderly . . . well, as we get older, our immunological function declines so we in essence become somewhat immunosuppressed as we get older. And then on the very young side, our immune systems don’t fully mature until we’re 16 years old. Still, some components of the immune system maturing as young teenagers. So we’re dealing with less mature immune systems, immune systems that aren’t fully mature as we get into the youngest population. So that’s why we usually see these peaks in the oldest and the youngest. But SARS-CoV-2 is not like that, it’s very unusual in the sense that, yes, infants are relatively immature in terms of their immunological functioning, but they’re physically very resistant to infection with this virus.
So this is all crazy to be encouraging breastfeeding women to be vaccinated, to protect their infants. Their infants are already naturally protected. And as we go down and we start vaccinating six-month-old breastfeeding infants, what we’re doing is we’re bypassing the natural protection they have from the virus when we inject these vaccines, where we start getting their body to manufacture the spike protein. And again, I can’t emphasise enough. The spike protein is not the inert target that we were hoping it would be for the immune system. It has all kinds of biological activities in our bodies that can potentially be harmful.
And what people have to understand is that the receptor that that spike protein can bind to in our children and infants is expressed at the same concentration internally as in adults. And that’s because that protein doesn’t exist to serve as a receptor for the virus, it actually exists to serve basic physiological processes such as regulating blood pressure and so on. So, they’re naturally protected from infection from SARS-CoV-2, but when we put the vaccines in, they’re at least as susceptible as adults to all the harms.
November 28, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular, Video | Canada, Covid-19, COVID-19 Vaccine |
Leave a comment
BMJ notes we will NEVER have the evidence, vaccine makers structured the trials to avoid proving an all-cause mortality benefit since they know it’s negative
If you are are still in doubt as to whether we are being hoodwinked on the safety and efficacy of the COVID vaccines, this Editorial in the BMJ today should remove all doubt. We are being hoodwinked. And it’s not going to get better. Ever. So we are stuck with a vaccine that is being mandated where most people have no fu*&($#ing clue as to whether it works or not.
Why? It’s simple. They know full well from the VAERS data that the vaccine kills far more people than it saves (regardless of age) and they want to make sure you will never find out.
Get it?
Those of us who know how to interpret the safety data from VAERS and other similar systems know full well what is going on, but when we try to warn people, we are being marginalized as spreaders of misinformation. Who’s lying? Well, suffice it to say that no self-proclaimed VAERS expert will agree to a debate.
Note: For those of you upset about the headline, sure, they can argue that the COVID vaccines saved people from dying from COVID. I concede that. But the all-cause mortality (ACM) rate (which nobody is looking at), has always been far greater than the COVID lives saved.
And that my friends is the inconvenient truth.

November 27, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | COVID-19 Vaccine |
Leave a comment
Strategic Group, a major rental housing provider in Alberta, Canada, announced that all new tenants need to show a vaccine passport to live in its properties. Critics claim the renter’s vaccine mandate sets a dangerous precedent.
“Vaccination of everyone in our community is the only way we are going to get through this pandemic and back to a sense of normalcy,” said Riaz Mamdani, founder and CEO of Strategic Group, in an October 28 press release.
“The safety of our team and our residents is a top priority, so ensuring full vaccination across the board is the least we can do.”
The press release said that “all employees, residents, and prospective residents” have to be vaccinated. Existing tenants will have to show proof of vaccination. Anyone “unable to be vaccinated (i.e., children under the age of 12) is exempt until able to receive the vaccine.”
“These rules apply to all of Strategic Group’s residential communities in Alberta.”
The renter owns more than 100 1 and 2-bedroom units in Edmonton and Calgary.
The Canadian Press reported that the Strategic Group COO Tracey Steman said that the company was “very proud” of the mandatory vaccination policy.
“And we’d like to see other landlords implement the same policy… It will help to end this pandemic,” Steman continued. “We’ve had really good feedback from our tenants.”
According to the company’s CEO, residents inspired the new policy as they were saying that “they value knowing that all their neighbors are vaccinated – they feel even safer in their own homes.”
Eva Chipiuk of the Justice Center for Constitutional Freedoms (JCCF) told LifeSiteNews that Strategic Group’s vaccine mandate for tenants “sets a dangerous precedent in Alberta and in Canada.”
“According to this renter’s policy, you do not deserve a roof over your head unless you have taken an experimental injection,” said Chipiuk.
“Such a policy, utterly unthinkable two years ago, is now frighteningly announced with pride,” she added.
“Under what authority is this policy being made?”
Chipiuk noted that the laws banning smoking indoors were discussed in “government housing.”
“This is not the same. These rental companies are taking the law into their own hands. If we allow this to happen, what will be next and who will find themselves without a place to live?” the lawyer asked.
In an article on The Lawyers Daily, landlord-tenant lawyer Caryma Sa’d explained why it is illegal for landlords to enforce vaccine passport mandates for tenants. Sa’d noted that refusing a potential client because of their vaccination status is discrimination.
Also, “landlords cannot simply make unilateral changes to the terms of the agreement, which would include imposing proof of vaccination as a condition of the tenancy.”
“This would prevent a landlord from attempting to evict a tenant based on vaccination status, unless it can be established that the tenant is substantially interfering with the reasonable enjoyment of others within the unit or otherwise causing serious problems at the residential complex because of their vaccination status,” the lawyer continued.
The president of the Canadian Federation of Apartment Associations John Dickie told the Canadian Press that it was “possible” for some landlords to follow Strategic Group’s lead and implement a vaccine passport mandate, but that was not likely to be “very widespread.”
“We’re not the health police,” said Dickie.
“Rental housing providers realize people need housing. We’re not in the habit of inquiring into people’s political views.”
November 27, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science | Canada, COVID-19 Vaccine, Human rights |
Leave a comment
In case you were beginning to feel like your world was becoming a cliché dystopian movie script, don’t feel bad. It appears that at least some of the villains agree with you.
Not happy with unsatisfying stories, scripts and narratives that shape our disorganized zeitgeist, Klaus Schwab and other creepy dungeon masters trying to manage the post-covid world have called for a ‘New Narrative’ to shape our 21st century and beyond. Schwab described the World Economic Forum’s Great Narrative Initiative announced on November 11 as a “collaborative effort of the world’s leading thinkers to fashion longer-term perspectives and co-create a narrative that can help guide the creation of a more resilient, inclusive and sustainable vision for our collective future.”
It is no question that this new project is bone chilling, but can it work? Does it have any basis in reality or is the oligarchical high priesthood stage managing this shit show intoxicated by their own self-induced narratives and completely incapable of seeing the seeds of self-destruction they have created for themselves?
Let’s examine this question in a bit of detail.
As far back as we look, recorded history demonstrates myths and stories that shape each culture’s subjective experience trying to make sense of the objective world and the many tenuous challenges that are tossed into our path.
Deep Structure Narratives
An ice age comes to an end and sea levels rise hundreds of feet drowning millions while wiping out coastal cities. As a consequence, flood myths appear across various cultures of the world.
Fires from the sky reflect terrible asteroids striking the earth wrecking havoc on ecosystems and perhaps even inducing volcanism and vast weather anomalies. As a consequence, more myths are created featuring heroes, villains, angels and Gods punishing sinners and rewarding those with virtue.
Throughout history, countless stories have been created by shamans, priests, and poets which have attempted to infuse meaning onto traumatic events induced by either nature or geopolitical strategies. Some classical stories may have even exposed geopolitical evils under the safer terrain of fiction when literal truths were impossible. One instance of this latter case can be found in the Olympian Gods of Homer’s stories who were in all likelihood representative of actual oligarchical families who manipulated never ending wars and exploited the folly and corruption of their chosen chess pieces on the Great Game of ancient Greece.
These stories are a part of the human condition and for the most part, perfectly natural.
However, in our supposedly enlightened secular era, these forms of myths are discarded as the foolish practices of simpler unscientific times.
Science has taught us to believe in logic. Not faith in God or the health of our immaterial souls.
The medieval myths of sea monsters and flat earths beyond which unsuspecting voyagers would meet a terrible fate were superseded for a new set of narratives during the enlightenment period. During this period, pure logic and empiricism were placed upon the new altars where religion once stood and we were told to worship new godheads by the names such as Kant, Locke, Hegel, Bacon and Newton. When Nietzsche proclaimed God to be dead, this was the current of thinkers that supposedly killed him.
The Indian poet Rabindranath Tagore referred to those suffering from this disease of metastasized logic saying: “A mind all logic is like a knife all blade. It makes the hand bleed that uses it.”
When the foundation of enlightenment logic began to break down under the pressure of reality over a century ago, new narratives taking the form of the Standard Model quantum mechanics began teaching modern man that what appears to be living is in truth, just made up of non living atoms and chemical interactions… and what appears to be ordered form operating with purpose is merely the stochastic motion of atoms devoid of purpose, beauty or even objective truth. We were told that all of this was held together only by a mix of luck (statistical probability) and four fundamental forces created 13.7 billion years ago. All behavior in human life or in nature thus explained away by Darwinian models of survival of the fittest and random mutations. The rise of modern monstrosities like eugenics, and neo-Malthusianism were the sick children of these ghoulish assumptions.
The more we probe behind the impressive veneer of these popular narratives, the more we discover that myths spun by modern day high priests on behalf of political interests have not only continued into our present age, but have continuously adopted new costumes to adapt to our changing world. Those brilliant minds whose discoveries actually overturned old narratives by leaping beyond the domains of inductive/deductive thinking are carefully obscured under mathematical formulas devoid of the spirit and personality of these exceptional individuals (1).
The Political Consequences of False Macro-Narratives
Some political expressions of today’s secular narratives were seen as neocons trotted out in front of cameras broadcasting the message that the two hijacked planes which destroyed three towers on 9/11 was orchestrated by angry Muslims in caves who hated our freedom.
We were told that covid-19 arose from a badly cooked mammal that kissed a bat requiring a total abolition of our constitutional freedoms.
We were told that the protest on January 6, 2021 in Washington D.C. was an insurrection worse than anything the U.S. had seen since the Civil War when 500,000 Americans slaughtered each other for four years.
We are continuously told that Russia has ambitions to undermine democratic elections across the entire free world while China is aiming to subvert western values and impose a global communist government through its imperial New Silk Road.
I could obviously go on for quite some time here, but needless to say, political myth making is an ugly part of life. But while each lie certainly does grave damage, our susceptibility to falling for these falsities is in no way disconnected from our acceptance of those higher meta narratives embedded in those scientific myths that shape HOW our minds move. Every high priest knows that controlling HOW people think is always infinitely more powerful than controlling WHAT they think about any particular thing. This is how the neocon rot grew in the U.S.A over a few generations leading us to today’s multifaceted systemic breakdown crisis.
One of the fathers of the mutant that became neoconservatism was a narrative-building master named Leo Strauss.
Leo Strauss’ Neocon Monstrosity
Working closely with Fabian Society and Frankfurt School agents throughout his career as a teacher in Columbia, New School and the University of Chicago, Strauss preached a perverse interpretation of Plato’s Republic to tens of thousands of devoted students spread across several decades.
Among the highest lessons contained in Strauss’s teachings (at least for a select few among his students) was the idea of the Noble Lie developed by Plato in Book 3 of the Republic. Strauss taught his students that this Noble Lie was the greatest weapon and rightful tool of anyone who found themselves in a position of power to rule over the weak at any time in history.
In true Nietzschean fashion, the narrow definition of “power” as the subordination of the weak to the strong was the only definition permitted by Strauss who taught his students that while Plato preached love of wisdom to the masses, he secretly held a different teaching for those elite among his Academy who would control political power. To these elite few, he gave the name ‘gentlemen’ and ‘Guardians’.
Strauss taught that Plato’s Guardians would control the shadows cast on the cave wall which the plebs shackled to their senses, would believe were the only reality possible. The mandate of these perverse neo-Platonists was to live the ideal not of Socrates, but rather of Thrasymachus whose immoral doctrine Socrates annihilated in the first book of the Republic. Those young neocons learning from their master were taught that the true ‘secret Socrates’ believed, like Thrasymachus, or Callicles (student of Gorgias), was that the highest purpose in life is to attain power, satisfy our lusts and control the shadows in the cave.
As many of Strauss’ own students (like Shadia Drury) came to realize over the years, the old master was himself guilty of projecting his own perverse penchant for fascism onto Plato as he himself maintained secret teachings for his chosen elite students as all good oligarchical head-hunters must.
Cleansing Plato of Strauss
While I adore Plato, I would never deny that he was a myth maker.
The stories showcased in his dialogues from the Timaeus, Critias, Theaetetus, Sophist, Statesman, Meno, Laws, Phaedo, Apology, Gorgias, Republic etc… have shaped the minds of some of the greatest historic figures across 2400 years of world history. Renaissance figures like St. Augustine, Ibn Sina, Erasmus, Shakespeare, Benjamin Franklin, Lincoln, Moses Mendelsohn, Pushkin, Martin Luther King Jr., and countless other brilliant souls had their wits sharpened on the stories and lessons contained in Plato’s writings.
But was Plato truly the tyrannical double-speaker portrayed by Strauss and his followers who preached morality for the weak and vice for those who would control the shadows?
To be a true Guardian in Plato’s world meant more than simply getting out of the cave to see with the light of the sun (symbolic for creative reason) and then lord over the masses.
While Nietzscheans like Strauss stop reading at this moment and choose to dominate the slaves using a higher power of thinking reserved only for a select few of the golden collar elite… Plato made it very clear in his Republic and other writings, that the TRUE philosopher (and implicitly true guardian) was obliged to return back into the cave at risk of his or her life in order to help liberate their fellow captives.
Narratives for Freedom or Slavery?
“Every artist, every scientist, every writer must decide now where he stands. The artist must take sides. He must elect to fight for freedom or for slavery. I have made my choice”
-Paul Robeson, 1937
The question can now be posed: how do we know which narratives are designed to enslave us, which empower us, and which are benign (like a child’s belief in the tooth fairy or the toy-bearing fat guy who trades gifts for good behavior)?
Since each person’s internal universe interfaces with the external reality through the filter of both logic, senses, imagination, and free will, is it possible that some narratives can uplift and inspire us to be more than we are in the face of impossible odds? Can certain stories sharpen our wisdom and free us from the shackles of sense perception as we are taught to see ever more through the eye of reason and a developed imagination?
When George Washington led a small force of farmers against the world’s largest mercenary force in 1776, was it purely logic that guided them in this statistically impossible fight, or were stories of Christ’s passion animating this seeming irrational drive for freedom? When Syria was beset with foreign sponsored Jihadists and teetered on the brink of the abyss, did stories of the Prophet Mohammed animate their hearts to do the impossible when an easier albeit more slavish road awaited their surrender?
Certainly, history has proven time and again, that a certain type of poetic story can empower us to leap beyond our limitations and gain insights into the deeper truths of the human condition and universal reality itself. Even Shakespeare’s “fictional” stories offer the sensitive soul great universal lessons into humanity and real politic which has served great statesmen for centuries.
A Last Look at Today’s Oligarchical Narrative Builders
Although we can affirm with certainty that some narratives can be good and others evil, is it possible that the oligarchs managing today’s Great Narrative project wish humanity no harm?
Perhaps Lynn Forrester de Rothschild is completely genuine when she launched the Council for Inclusive Capitalism alongside Prince Charles, Mark Carney and a handful of Davos Billionaires representing tens of trillions of dollars of capital in 2014. Helping to transform capitalism into a green, eco friendly, more inclusive system that treats everyone equally is a good thing isn’t it?
When this Council merged with the Vatican in December 2020, Lynn de Rothschild described the event as “a historic new partnership between some of the world’s largest investment and business leaders and the Vatican… joining moral and market imperatives to reform capitalism into a powerful force for the good of humanity.”
This council is even led by “a core group of world leaders” who even call themselves “Guardians” following the title used by Plato 2400 years ago.
These guardians include the CEOs of powerful organizations as State Street, Bank of America, Johnson and Johnson, Rockefeller Foundation, Ford Foundation, Merck, British Petroleum, and the Rothschild banking houses. Not exactly the most morally advanced coterie of political heavy weights one could imagine, but still maybe the evil that they have been a part for decades has all been arranged for the sake of a higher good that only the elite may be permitted to know…
Unfortunately for the Davos Guardians, the reality of the New Great Narrative is a world devoid of those very principles that humanity requires to survive and thrive within our creative, reasonable universe. Wielding the power to control a shadow land of dumbed down slaves within a cave might seem impressive for some, but when juxtaposed with the active, creative multipolar paradigm now rising to become a global force for scientific and technological progress, controlling cave dwellers becomes little more than a bleak and pitiful ambition.
And like any parasite which can do naught but kill the very host it needs to suckle on for its very survival, those Davos guardians are likely to meet the same fate as that encountered by Edgar Poe’s impotent, nihilistic oligarch Roderick Usher as his castle crumbled into an abyss.
Note
(1) Some exemplary names of these exceptional individuals include Leonardo Da Vinci, Luca Pacioli, Pierre Fermat, Christian Huygens, Johannes Kepler, Gottfried Leibniz, Max Planck, and Dimitry Mendeleyev (to name but a few).
Matthew Ehret is the Editor-in-Chief of the Canadian Patriot Review , and Senior Fellow at the American University in Moscow. He is author of the ‘Untold History of Canada’ book series and Clash of the Two Americas. In 2019 he co-founded the Montreal-based Rising Tide Foundation .
November 27, 2021
Posted by aletho |
Civil Liberties, Full Spectrum Dominance, Malthusian Ideology, Phony Scarcity, Science and Pseudo-Science, Timeless or most popular |
Leave a comment
Twitter suspended my account (likely forever since there is no appeal) due to one post on prion diseases. Here’s the information they wanted to make sure you NEVER find out.
Summary
There is no doubt the mRNA vaccines are causing prion diseases. People didn’t have these diseases before the shot and suddenly they develop them after the shot. There is no other explanation for this. None of the “fact checkers” can explain the cause of the excess rates. Prion diseases are incurable and always fatal. You can die as soon as 6 weeks after COVID vaccination (see within 6 weeks and within 6 months examples).
However, Twitter believes this is not true, but they refuse to tell anyone why they think that. Other fact checkers who have checked this out never did a VAERS query and are unable to explain away the “excess” number of reports other than doing a blanket dismissal that everything in VAERS is fraudulent without providing any evidence of that claim (other than one report out of 1.6M reports).
None of the fact checkers will debate on this to set the record straight.
On November 24, 2021 I posted the following message on Twitter:

Twitter suspended my account hours later. There is no appeal available. All content over the last 12 years was removed. All my 75K followers were zeroed. My messages were removed. There was no opportunity to download my content.
The only thing left: that my Twitter ID was @stkirsch.
Twitter refuses to tell us what I said that was misleading?
Twitter won’t tell me that!!! They are deliberately withholding their definitive analysis on this extremely important scientific issue. Why???
I really want to know. Obviously, Twitter fact-checkers (all of whom I presume must have PhD degrees or MD degrees to be able to assess my claims) were able to quickly read all the medical literature and determine without a doubt I made an error and should be terminated for making a mistake. But they won’t tell me the mistake!!
If they want to fight misinformation, why aren’t they posting a link to their research proving me wrong when they terminate the account. They obviously invested hours of time in the research before they terminated me. Why not provide a link to that research so everyone can learn from it including me??
Here’s the evidence for my claim
Back in May 2021 when Professor Byram Bridle was disclosing the FOIA request on the Pfizer vaccine bio-distribution data he mentioned that the spike protein was associated with Lewy body formation which is linked to prion diseases. He expressed concern that the vaccines could cause prion diseases like dementia, Alzheimer’s, and Creutzfeldt-Jakob disease (CJD).
What do you know. He was right. Now we have proof.
Check out these VAERS query results. These searches are over all 30 years of VAERS and all 70+ vaccines. See anything unusual? Yeah, for less than 1 year of the COVID vaccines, the results are off the charts.
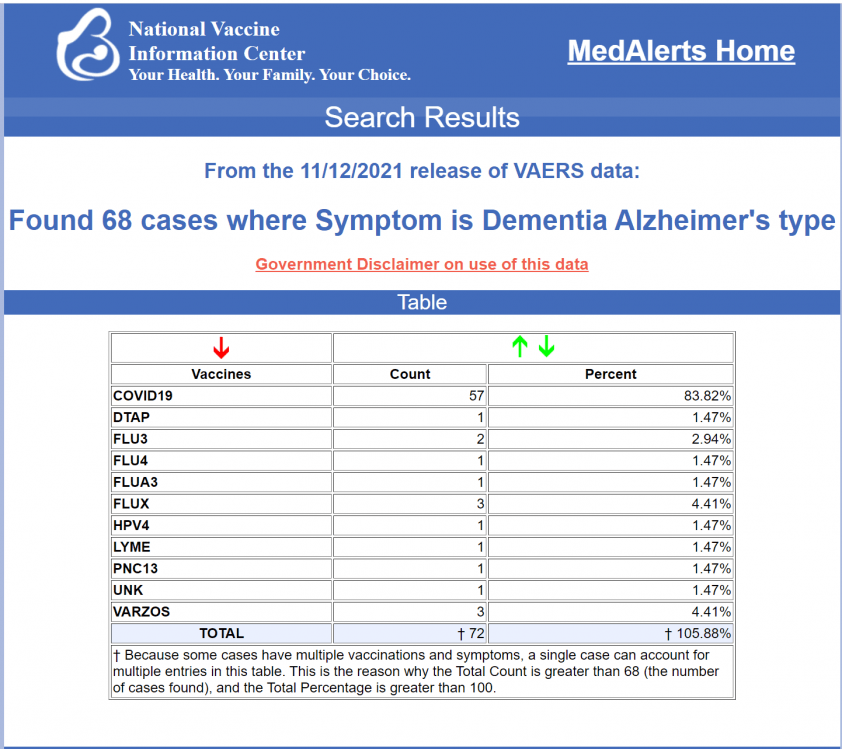
And for CJD which is extremely rare:

Remember, these are 30 year searches for all vaccines. Clearly there are excess reports. And we know VAERS isn’t being “over-reported” this year which I’ve shown many times before (events not caused by the vaccine are reported at rates comparable to other vaccines).
If it wasn’t the COVID vaccines causing this, what was the cause?
Nobody can answer that question, not even the Twitter fact checkers!
For further reading, check out these articles:
- Jessica Rose’s article on COVID vaccines and prion diseases
- Stephanie Seneff’s paper on prion disease and the COVID vaccines
- Bart Classen’s paper linking the vaccines and prion diseases
- SARS-CoV-2 causes brain inflammation and induces Lewy body formation in macaques
- SARS-CoV-2 Prion-Like Domains in Spike Proteins Enable Higher Affinity to ACE2
And compare them to some of the “fact checks” which claim there are no instances in VAERS which as you can see from the queries above (which you can replicate yourself):
- USA Today fact check on prion disease
- Politifact “fact check” on prion diseases
You decide who is telling the truth.
And note that the “fact checkers” never did a single VAERS query. Wow. That’s the first place you’d look to prove the claim is false.
November 27, 2021
Posted by aletho |
Full Spectrum Dominance, Science and Pseudo-Science | CJD, COVID-19 Vaccine |
Leave a comment



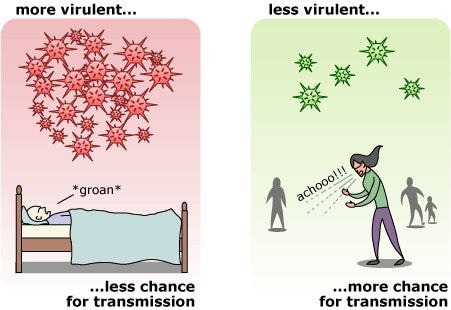

 The label for Humira, once the best-selling drug in the world, lists its risks in plain print. One of them, in the label’s own words, is new “autoimmune” disease.
 Aletho News

