The Magical Thinking and Dangers of Masks
By Dr. Joseph Mercola | November 24, 2021
Are you prepared to wear masks forever? Some are, but their positive attitude toward masks is a likely result of deceptive and misleading information. The resulting magical thinking relating to masks has created one of the most polarized debates in U.S. history and led to anti-maskers being labeled as “grandma killers.”1
To be clear, the U.S. Centers for Disease Control and Prevention (CDC) has blatantly lied about masks’ effectiveness. November 5, 2021, CDC director Dr. Rochelle Walensky tweeted, “Masks can help reduce your chance of #COVID19 infection by more than 80%.”2
But as Dr. Vinay Rasad, MPH, a hematologist-oncologist and associate professor in the department of epidemiology and biostatistics at the University of California San Francisco, put it in the Brownstone Institute, “I don’t know how to put this politely, but it is a lie, and a truly unbelievable one at that … The idea that masks could reduce the chance of infection by 80% is simply untrue, implausible and cannot be supported by any reliable data.”3
Masks Have Meager Effectiveness, if Any
Walensky didn’t give a reference for her claim that masks reduce COVID-19 infection by 80%, but a large study4 from researchers at Yale, Stanford and the University of California Berkeley found much less impressive results from masks.
The trial involved 342,183 people from 600 villages in rural Bangladesh from November 2020 to April 2021. In villages that received masks, the number of symptomatic COVID-19 infections were 9.3% lower compared to villages without masks, or 11% lower in villages that received surgical masks instead of cloth masks.5
Why, then, hasn’t Walensky’s tweet been flagged for misinformation and targeted by “fact checkers” calling out the blatant lie? Rasad featured a tweet6 by Carnegie Mellon University mathematician Wesley Pegden, who said:7
“The head of the agency responsible for providing Americans with accurate and trustworthy information about interventions (like vaccines) that we actually know are really effective should not also be making fabricated quantitative statements in support of poorly evidenced ones.”
Antibiotic-Resistant Pathogens Live on Face Masks
While face masks continue to be recommended or mandated, little has been said about the risks inherent to covering your mouth and nose with fabric or other materials. Both cotton and surgical masks collect pathogens that may increase your risk of infectious illness — a factor that’s rarely taken into account when discussing their merits.
When researchers from the University of Antwerp, Belgium, analyzed the microbial community on surgical and cotton face masks from 13 healthy volunteers after being worn for four hours, bacteria including Bacillus, Staphylococcus and Acinetobacter were found — 43% of which were antibiotic-resistant.8
In order to best clean masks to remove the bacteria, the study found boiling at 100 degrees Celsius (212 degrees F), washing at 60 degrees Celsius (140 degrees F) with detergent or ironing with a steam iron worked best, but only 21% of survey respondents said they cleaned their cotton face masks daily.9 According to the researchers:
“Taken together, this study suggests that a considerable number of bacteria, including pathobionts and antibiotic resistant bacteria, accumulate on surgical and even more on cotton face masks after use. Based on our results, face masks should be properly disposed of or sterilized after intensive use. Clear guidelines for the general population are crucial to reduce the bacteria-related biosafety risk of face masks …”
Researchers from Germany similarly questioned whether a mask that covers your nose and mouth is “free from undesirable side effects” and potential hazards in everyday use.10 It turned out they were not and instead posed significant adverse effects and pathophysiological changes, including the following, which often occur in combination:11
- Increase in dead space volume
- Increase in breathing resistance
- Increase in blood carbon dioxide
- Decrease in blood oxygen saturation
- Increase in heart rate
- Decrease in cardiopulmonary capacity
- Feeling of exhaustion
- Increase in respiratory rate
- Difficulty breathing and shortness of breath
- Headache
- Dizziness
- Feeling of dampness and heat
- Drowsiness
- Decrease in empathy perception
- Impaired skin barrier function with acne, itching and skin lesions
Mask-Induced Exhaustion Syndrome Is Prevalent
The study referred to this cluster of symptoms as mask-induced exhaustion syndrome (MIES) and warned that children, pregnant women and those who are sick or suffering from certain chronic conditions may be particularly at risk from extended masking. While short-term effects include microbiological contamination, headaches, exhaustion, carbon dioxide retention and skin irritation, the long-term effects may lead to chronic issues:12
“Extended mask-wearing would have the potential, according to the facts and correlations we have found, to cause a chronic sympathetic stress response induced by blood gas modifications and controlled by brain centers. This in turn induces and triggers immune suppression and metabolic syndrome with cardiovascular and neurological diseases.”
Further, “it can be assumed,” they wrote, “that the potential adverse mask effects described for adults are all the more valid for children: … physiological internal, neurological, psychological, psychiatric, dermatological, ENT, dental, sociological, occupational and social medical, microbiological and epidemiological impairments …
The masks currently used for children are exclusively adult masks manufactured in smaller geometric dimensions and had neither been specially tested nor approved for this purpose.”13
Again, in taking on these unknown risks — both short- and long-term — to wear masks, the benefits are highly questionable and intended to thwart a pathogen with a low death rate for most populations:14
“[R]ecent studies on SARS-CoV-2 show both a significantly lower infectivity and a significantly lower case mortality than previously assumed, as it could be calculated that the median corrected infection fatality rate (IFR) was 0.10% in locations with a lower than average global COVID-19 population mortality rate.
In early October 2020, the WHO also publicly announced that projections show COVID-19 to be fatal for approximately 0.14% of those who become ill — compared to 0.10% for endemic influenza — again a figure far lower than expected. On the other hand, the side effects of masks are clinically relevant.”
‘The Mask of Your Enslavement’
 It’s clear that the evidence in support of masks for physical protection against disease is lacking, while their potential for psychological harm is immense. Brownstone Institute highlighted the story of folk saint Escrava Anastácia, a slave of African descent who lived in Brazil during the 19th century.15
She was forced to wear a metal, muzzle-like mask during her lifetime in order to silence her from speaking out about the oppression and injustice she was facing. As written by Roberto Strongman, associate professor in the department of black studies at the University of California, Santa Barbara:16
“The apparition of Anastásia at anti-lockdown rallies represents an opportunity to understand the current medical tyranny as a form of enslavement and to forge links of solidarity between communities whose freedom is threatened across all racial groups. The claim of cooptation deserves to be unpacked for a valid claim of cultural usurpation could easily work towards severing important alliances in a divide-and-conquer model.
While there are clear specificities between the suffering of Africans under the system of chattel slavery and the deprivation of civil liberties endured by most citizens around the world during the current pandemic panic, Anastásia reminds us of certain transhistorical constants in the process of dehumanization and subjugation of populations through the gagging and muzzling of their bodies to quell their protestations.”
Strongman pointed out several undeniable reasons why face mask mandates “fashion the citizenry as slaves” and act as symbols of enslavement. Among them, they:17
- Lead to oxygen deprivation, promoting a state of physical and mental weakness
- Are symbols of submission and used as part of master-slave dynamics
- Enforce the creation of a carceral culture
- Erase personhood and homogenize the masses — “The collectivized wearing of masks results in an enforced uniformity in which the individual cedes way to the nameless collectivity as the neo-meta citizen.”18
- Are theatrical and act to conceal identities, rendering us alien to others and ourselves
- Delete facial expressions and inhibit nonverbal communication, including that necessary for social organization that can lead to revolution
- Reduce verbal output
- Are visible displays of allegiance to the “system of medicalizing technocratic control”
- Are part of preparing individuals for new societal roles — “However transitory the current regime of face masking might be, the population must face that we are beingforced to undergo a rite of passage, a process of resocialization into the new normal.”
- Promote a culture of fear
- Act as deterrents of solidarity by making your neighbor into a “nameless pathogenic vector instead of your ally”
Magical Thinking on Masks
In addition to flat-out lies, the CDC also makes nonsensical statements, like this: “Cloth masks will not protect you from wildfire smoke … They might not catch small, harmful particles in smoke that can harm your health.”19
But we are to believe that they will protect us from an aerosolized virus? “The virus is 25X smaller than a smoke particle,” wrote Steve Kirsch, executive director of the Vaccine Safety Research Foundation. “So it’s like trying to stop a mosquito with a chain link fence.”20
Yet magical thinking — the belief that you can influence outcomes by doing something that has no causal connection to them — persists. Robert Dingwall, a consulting sociologist, questioned why the U.K.’s Health Security Agency expert panel used only a second-class evidence base that failed to demonstrate clear benefits on which to base their conclusion that face masks in the community help reduce transmission. He wrote:21
“The state of the face mask debate is rather as if Galileo had published his account of the heliocentric universe and then included a paragraph at the end telling the reader to ignore all the evidence because the Church had declared that everything revolved around the Earth.
In the absence of better-quality work — and we must ask why that research has not been done — some of the claims for face masks look much more like magical thinking than anything that demonstrates the sort of casual connection that might be recognizable as science.”
As the pandemic stretches on, science continues to be ignored and recommendations are primarily pushed based on emotional justifications and triggers. If science were actually followed, universal mask wearing by healthy people would not — indeed could not — be recommended.
In the beginning, health officials did, in fact, advise against masks for healthy people,22 but somewhere along the way — early on — they flip-flopped. Why? According to Strongman:23
“Just as masks function as liminal artifacts in rites of passage and as part of animal training, these covid mask are harbingers of further intrusions to our integrity.
Wearing the masks is just one step away from receiving the shots, then accepting the vaccine passports and the implantable neural links until one’s original persona is buried by a cyborg. The masks function as an empirical compliance test for the projected acceptability of future corporeal technologies of control. Where will you draw the line?”
Sources and References
- 1, 20 Steve Kirsch Newsletter November 7, 2021
- 2 Twitter, Rochelle Walensky November 5, 2021
- 3, 6 Brownstone Institute November 7, 2021
- 4 The Impact of Community Masking on COVID-19: A Cluster-Randomized Trial in Bangladesh November 8, 2021
- 5 ABC Action News September 1, 2021
- 7 Twitter, Wes Pegden November 5, 2021
- 8, 9 Frontiers in Medicine September 3, 2021
- 10, 11, 12, 13, 14 Int J Environ Res Public Health. 2021 Apr; 18(8): 4344
- 15 History Collection December 13, 2018
- 16, 17, 18, 23 Brownstone Institute November 4, 2021
- 19 U.S. CDC, Wildfire Smoke and COVID-19
- 21 Social Science Space October 25, 2021
- 22 Life Site News July 31, 2020
Why another lockdown would be met with mass non-compliance
By Andrew Devine | TCW Defending Freedom | November 25, 2021
LIKE many people, I went along with the first lockdown. I wasn’t very keen, and I was somewhat critical of it, but I believed the lie that it would be a temporary one-off measure. From the time of the second lockdown, I have been vehemently opposed to the policy. While I have never denied that Covid can be a nasty life-threatening illness for some people, I am critical of the way that governments have manipulated data to exaggerate the extent of the threat.
When Covid 19 vaccines were first rolled out in the UK and around the world in late 2020, we were promised by Western governments and their teams of scientific ‘experts’ who wield enormous, unaccountable power, the media and Big Pharma that the vaccines were a game-changer and that mass vaccination would lead us back to some kind of normality. I was initially very resistant to take the vaccine because it is a new drug with no long-term data regarding side effects and risks. I also have two autoimmune conditions, and while they are easily treated, I am genetically predisposed to a third one that can be quite serious.
However, in the end, and with much hesitation due to the already known side effects and autoimmune risks, I took the Pfizer vaccine. I did so for several reasons. Firstly, I am around my elderly parents a lot, and I thought I would be protecting them as I believed the ‘experts’ that the vaccines would significantly reduce transmission.
This has turned out to be false.
Secondly, I was convinced by the data that seems to show that getting vaccinated almost entirely eradicates the chances of someone my age ending up in hospital with a severe case of Covid. Due to fitness and age, my risk of serious illness was already low, but as a neurotic who is sometimes prone to viewing the glass half empty, I admit to having moments when I worried that I might be one of those outliers for my age group cut down prematurely by Covid and so this was an added factor, but not the main one, in my capitulation. The final reason was because I currently reside in the Republic of Ireland where the government have been very keen to enforce some of the harshest lockdowns globally with draconian rules on both inward and outward travel as well as compulsory vaccine certificates for access to various sectors. Therefore, one of my main reasons for getting jabbed, while I still defended vehemently the rights of others not to do so, was that I thought I would be doing my bit to put an end to these hideous lockdowns and other excessive restrictions once and for all. Looking at what has happened in Austria and Holland and the refusal of both the UK and Irish governments to rule out more lockdowns, it is now clear how very wrong I was. Another way of putting it is that I’ve realised how easily I have been duped.
In recent weeks, I have become even more sceptical of everything that the UK and Irish governments and their appointed health experts tell me with regard to Covid-19. For a start, if they were wrong about the effectiveness of the vaccines with regards to transmission, why would I trust them with regards to how rarely serious side effects occur? There would be far more political and career capital at stake to motivate suppression of this data. I’m not accusing governments, scientific ‘experts’ or Big Pharma of doing so, merely noting that there is a much bigger price for them to pay if they didn’t.
With regards to coercive measures and the removal of rights from the unvaccinated, governments don’t even have recourse to the dubious argument that it’s for the greater good as we now know that the vaccinated can also transmit the virus. I keep making the argument to vaccine zealots that people can exercise their right to abstain from taking any medications due to the risks of side effects, but that many governments now believe this right should be removed solely with regard to Covid vaccines. There is no compelling moral argument for why Covid vaccines fall into an exceptional category that warrants the state using coercion whether it be direct (vaccine mandates) or indirect (segregation and removal of rights) to force its citizens to reluctantly take a medicine they would otherwise refuse.
The enthusiasm for vaccines and excessive restrictions are now articles of faith for their proponents. It has become an ideological stance that no amount of reasoned scrutiny can alter. Rational analysis of the extent of the threat from Covid and strategies to deal with it have been abandoned for the simplistic dogma of ‘vaccines good’ and ‘lockdowns and restrictions good’. The truth is much more nuanced than the doom-mongering analysis which permeates the mainstream media. Lockdown enthusiasts and vaccine zealots, like all ideologues, have opponents whom they despise and whom they seek to demonise. This is why only ‘far Right conspiracy theorists’ and ‘anti-vaxxers’ would have an issue with mandatory vaccines which can have serious side effects being given to children to protect them from a virus that rarely makes children very ill.
How have we reached a stage in Western liberal democracies when those of us questioning and disagreeing with extreme public health policies that strip individual citizens of their inalienable rights under false pretences are the ones deemed to be the extremists? Asking questions and being critical of government policy is now viewed by the obedient media class and the political elites and partisan scientific ‘experts’ they serve as being synonymous with the far Right. In truth, it is your democratic duty to question all government policies and especially more so those that would remove your fundamental freedoms. For any government to wish to suspend the rights of its citizenry on a temporary basis, it must first seek consent from the people after explaining the exceptional circumstances in which they seek to do so. There has been no public debate and little media scrutiny across the English-speaking world about whether the threat posed by Covid-19 meets the very high threshold that could justify temporary lockdowns and other extreme restrictions imposed on the citizenry.
If the UK or Irish government or any of the devolved administrations try to impose another lockdown, I predict there will be mass non-compliance. It is very likely that much of the population of these islands will conclude that if several lockdowns, mask mandates and ‘game changing’ vaccines have not eradicated transmission, why comply with another lockdown, possible financial ruin and separation from loved ones? What would be the purpose? As someone once said (it wasn’t actually Einstein): ‘Insanity is doing the same thing over and over and expecting different results.’
Guardian Claims Covid in Hospitals Has “Largely Become a Disease of the Unvaccinated” – Data Shows Opposite
By Will Jones • The Daily Sceptic • November 23, 2021
An article appeared in the Guardian this week written by an anonymous NHS respiratory consultant claiming that “in hospital, COVID-19 has largely become a disease of the unvaccinated”.
Of course, there are people who have their vaccinations but still get sick. These people may be elderly or frail, or have underlying health problems. Those with illnesses affecting the immune system, particularly patients who have had chemotherapy for blood cancers, are especially vulnerable. Some unlucky healthy people will also end up on our general wards with Covid after being vaccinated, usually needing a modest amount of oxygen for a few days.
But the story is different on our intensive care unit. Here, the patient population consists of a few vulnerable people with severe underlying health problems and a majority of fit, healthy, younger people unvaccinated by choice. … If everyone got vaccinated, hospitals would be under much less pressure; this is beyond debate. Your wait for your clinic appointment/operation/diagnostic test/A&E department would be shorter. Your ambulance would arrive sooner. Reports of the pressure on the NHS are not exaggerated, I promise you. … Most of the resources that we are devoting to Covid in hospital are now being spent on the unvaccinated.
This reads to me like a blatant attempt to stigmatise the unvaccinated as selfish, a burden on society and a threat to the vaccinated. (The clue is in the headline: “ICU is full of the unvaccinated – my patience with them is wearing thin.”) Given the polling (which may not be very reliable of course) showing that 45% of U.K. adults would support an indefinite lockdown of the unvaccinated, this is all starting to look and sound rather ugly.
The most frustrating thing about this anonymously written article is it doesn’t cite any data even though its arguments are based on claims which only data can validate. It consists instead only of a single medic’s subjective impressions, with no sources provided to see if his claims holds water.
Are the hospitalised mostly unvaccinated? Not according to Government data from the UKHSA. Here is the breakdown of hospitalisations by vaccination status in England for the four weeks up to November 14th from the latest Vaccine Surveillance report.
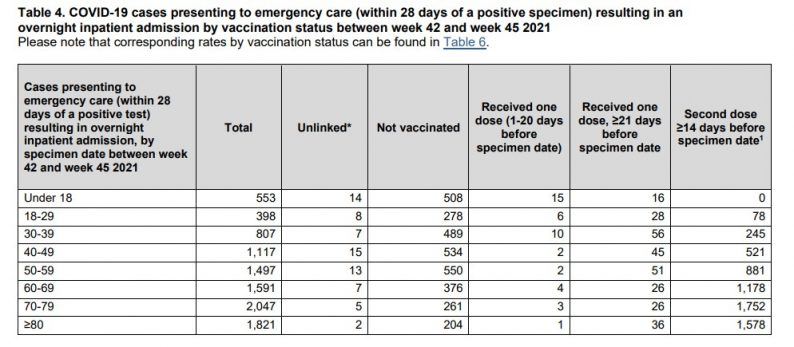
Adding these figures up we find that 3,200 of 9,831 or 33% of Covid hospitalisations are of unvaccinated people, leaving 67% of Covid hospital patients in the vaccinated category, most of them with two doses. Focusing just on adults, we find 2,692 of 9,278 or 29% of Covid hospitalisations are unvaccinated, leaving 71% vaccinated. Seeing as just 68% of the U.K. population is double vaccinated, 67% of Covid hospital patients having received at least one dose hardly seems like a strong result. Indeed, it suggests the unvaccinated are barely over-represented in hospitals at all.
What about Covid deaths – are the unvaccinated over-represented there? Here’s the table from the same report.
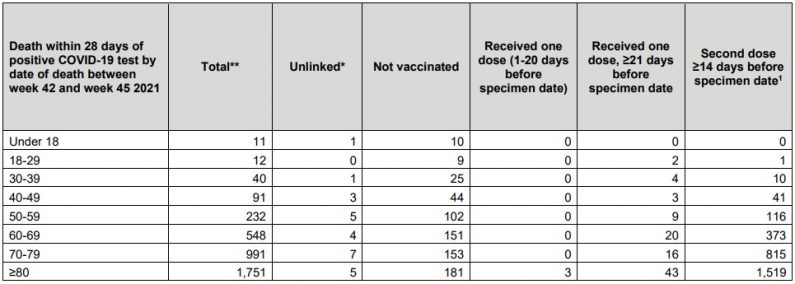
Adding them up we find that 675 of 3,676 or 18% of Covid deaths in the month up to November 14th are in unvaccinated people, leaving 82% in the vaccinated, most with two doses. Only in the under-40s do deaths in the unvaccinated outnumber those in the vaccinated.
It’s hard to square this data with the picture painted by the anonymous medic. Far from COVID-19 having “largely become a disease of the unvaccinated”, with most Covid hospital resources “now being spent on the unvaccinated”, a large majority of hospitalisations and deaths are occurring in the vaccinated, not the unvaccinated.
But what about ICU admissions? And is it true that the vaccinated-sick all have underlying health issues whereas the unvaccinated-sick are all healthy?
The problem with addressing these claims is that we don’t have the data to check them out. The data on ICU admissions by vaccination status has not been updated since July as far as I can see (if you are aware of a more recent update do let me know), and I am not aware of any data on co-morbidities (again, if you are aware of any please drop me a line).
The anonymous writer states: “I can’t think of a single case offhand of a person who was previously fit and healthy who has ended up needing intensive care after being fully vaccinated. It may not stop you from catching Covid. But it can save your life when you do.” But again, this is anecdotal and therefore not terribly helpful.
It’s fair to note that much data does appear to show that the vaccines protect people well against severe disease and death, at least for several months, though some recent analysis has questioned whether such efficacy has been overestimated.
But however well the vaccines protect against severe disease, that is no excuse for turning the unvaccinated into pariahs or scapegoats and blaming them for the strains on the health service. Such moralised blaming of a minority for supposedly disadvantaging the majority (‘Can’t get a doctor’s appointment? Surgery been cancelled again? The unvaccinated are to blame!’) has a very ugly history and rarely ends well. It’s particularly odd to see this scapegoating in a supposedly liberal newspaper. It needs to stop now.
Why aren’t healthcare workers speaking out about the catastrophe caused by the vaccines?
Everyone thinks that if the jabs were really dangerous, doctors and other healthcare workers would be speaking out. They are wrong.
By Steve Kirsch | November 23, 2021
It’s too hard to ignore all the vaccine injured kids showing up in the ER nowadays.
I just heard a story from a friend who went to the lab for a stress echocardiagram.
In the waiting room with her are 4 kids aged 7 to 10 years old with their moms. She talked to the moms. The kids were all suffering from tachycardia (heart rate that beats way too fast) and waiting to be tested.
Two important things you need to know:
- All the kids were recently vaccinated.
- Kids that age NEVER get tachycardia (i.e., the medical experts I’ve talked to have never seen it before in their careers).
There are close to 10,000 adverse event types elevated by the COVID vaccines. Here’s a list of the adverse events most elevated compared to “normal.” In the #2 position: heart rate, elevated by nearly 8,000 times normal.

So why aren’t we hearing about these stories from mainstream doctors?
Here are nine reasons very few people are speaking out:
- Fear of job loss. Nobody wants to lose their job. Look what happened to Deborah Conrad and others who speak out. Fired within hours after speaking out. So the lab technicians who are now seeing kids with tachycardia just keep their mouth shut. They know something is very wrong, but their job is more important. Besides, if they spoke out, it wouldn’t make any difference since they are just a lab technician.
- Belief that COVID is even worse than the vaccine injuries. Many people are deceived by erroneous reports that the number of vaccine cases (e.g., of myocarditis) are occurring far less often now that the vaccines have been rolled out. Dr. John Su is the big culprit here because he’s never told the world that VAERS is under-reported. The pediatric cardiologists know what is going on, but they aren’t going to say anything due to #1. So I see doctors tweeting the myth that “sure, there is myo after the vaccine, but the rates due to COVID are worse so the vaccine is the better of the two options.”
- Belief that the injuries are really rare. I know a doctor who treats vaccine injured patients. He has no clue whether these are every single vaccine injured patient in the US or he’s only seeing a tiny fraction of the injuries. He believes he’s seeing them all so writes it off as just “coincidence” and “bad luck” since if it was the vaccine, the CDC would have spotted it.
- Cognitive dissonance. They are so convinced the vaccines are safe (since nobody else is speaking out), that any adverse events that happen must be due to something else.
- Belief that they can treat you for your vaccine side effects, but that they can’t treat you if you have COVID. So lesser of two evils. And of course, they think no early treatments work, so they think they are doing you a favor by telling you to get the vaccine.
- Belief that there is no viable alternative for treating COVID and that the vaccines work. So even 100,000 dead or injured people is better than 750,000 dead people from COVID.
- Trust in the NIH and CDC. If it was a problem, the CDC would tell people. Telling people isn’t their job. Their job is to follow the direction set by the experts.
- Fear of being ostracized. People who do research fear if they speak out they would be labelled as anti-vaxers and their research would thus be discredited.
- Critical thinkers have been fired. Hospitals and medical facilities have already fired vaccine hesitant employees per vaccine mandates thereby self selecting for vax believers.
The courageous people who dare to speak out
Some are speaking out. Here are some links of people who are speaking out:
Lethal Injection; Frontline E.R. Doctor Gives Chilling Account of Unusual Vaccine-Induced Illness
BY MIKE WHITNEY • UNZ REVIEW • NOVEMBER 20, 2021
“Americans are scared to death… People are walking off the job, not because they want to lose their jobs, but they don’t want to die from the vaccine! … They say, ‘Listen, I don’t want to die. That’s the reason I’m not taking the vaccine.’ It’s that clear.” Dr. Peter McCullough
A report in the U.K. Telegraph explains how the Covid-19 vaccine has led to a sharp rise in excess deaths. Here’s an excerpt from the article:
“Nearly 10,000 more people than usual have died in the past four months from non-Covid reasons, as experts called for an urgent government inquiry into whether the deaths were preventable…
Latest figures from the Office for National Statistics showed that England and Wales registered 20,823 more deaths than the five-year average in the past 18 weeks. Only 11,531 deaths involved Covid.” (“Alarm grows as mortuaries fill with thousands of extra non-Covid deaths,” UK Telegraph )
Mortality is rising because more people are dying. And more people are dying because more people have been vaccinated. There’s a link between rising mortality and the Covid-19 vaccine. Naturally, the media wants to shift responsibility for the fatalities to “delayed treatments” and “the lack of preventable care”. But this is just a diversion. The primary cause of death is the injection of a toxic pathogen into the bloodstreams of roughly 70% of the population. That’s what’s causing the clotting, the bleeding, the pulmonary embolisms, the heart attacks, the strokes, and the premature deaths. It’s the vaccine. Here’s more
“Weekly figures for the week ending November 5 showed that there were 1,659 more deaths than would normally be expected at this time of year. Of those, 700 were not caused by Covid.
The excess is likely to grow as more deaths are registered in the coming weeks.
Data from the UK Health Security Agency show there have been thousands more deaths than the five-year average in heart failure, heart disease, circulatory conditions and diabetes since the summer.
The number of deaths in private homes is also 40.9 per cent above the five-year average, with 964 excess deaths recorded in the most recent week, which runs up to November 5.” (“Alarm grows as mortuaries fill with thousands of extra non-Covid deaths“, UK Telegraph )
The sudden surge in mortality is not a meaningless blip on the radar. It’s a red flag indicating a significant break in the five-year trend. Something has gone terribly wrong. Mass vaccination was supposed to reduce the number of cases, hospitalizations and deaths. Instead, the fatalities continue to rise.
Why?
The answer to that question can be found in the data itself. As the author admits, there has been a sharp uptick in heart failure, heart disease, circulatory conditions and strokes. (Diabetes is the outlier) These are precisely the ailments one would expect to see if one had just injected millions of people with a clot-generating biologic that triggers a violent immune response that attacks the inner lining of the blood vessels inflicting severe damage to the body’s critical infrastructure. So, yes, all-cause mortality is up, and it is certain to climb even higher as more people are vaccinated and gradually succumb to the (frequently) delayed effects of a hybrid concoction that is the cornerstone of a malign plan to dramatically reduce global population. Check out this chart followed by a brief comment by diagnostic pathologist, Dr Claire Craig:
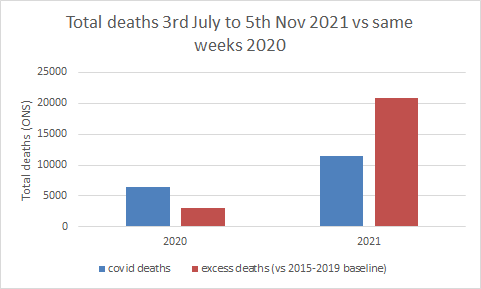
Dr Clare Craig @ClareCraigPath
“Since summer there have been twice as many covid deaths, but seven times as many excess deaths as last year.” (Twitter)
And here’s another blurb from Craig:
“If you start at week 22 and add up all the deaths since for each year, then something very abnormal is happening this year among 15-19 yr old males.”
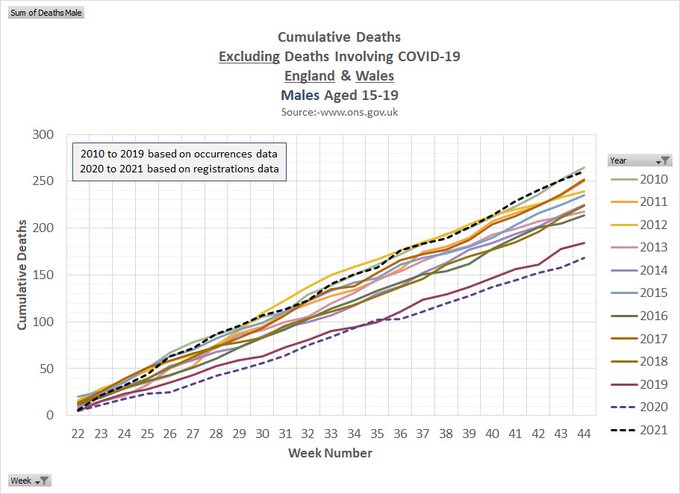
So, not only are more people dying, but the demographic has shifted downwards as younger and younger people are drawn into the vaccine vortex. Simply put, the number of young people dying from vaccine-inflicted cardiac arrest and myocarditis continues to increase with no end in sight.
Not surprisingly, all-cause mortality is higher among the vaccinated than the unvaccinated which, again, makes it easier to trace the problem back to its root, a cytotoxic “poison-death shot” that suppresses the innate immune system, damages vital organs and shaves years off the lives of normal, healthy people.
Perhaps, you’ve seen one of the many short videos of fit, young athletes who suddenly have dropped dead on the field of play or been rushed to hospital shortly after getting injected. If not, here’s a link to two of them. (Athletes collapse following vaccination: See here and here)
According to Israeli Real-Time News, there has been a “500% increase in deaths of players in 2021… Since December, 183 professional athletes and coaches have suddenly collapsed! 108 of them died!”
“500% increase in the deaths” of athletes?!? What are we to make of this?
For starters; the Covid-19 vaccine is not a medication. It is the essential component in the elitist plan for industrial-scale extermination. It is designed to inflict severe physical injury on the people who take it. It’s shocking that people are so deep in denial that they can’t see what’s going on right before their eyes. (Please, watch the video clips of the athletes. These are the fittest people on the planet and, yet, they are being struck down by the mystery substance in the vaccine.) Here’s how South African doctor Shankara Chetty summed it up in a recent video posted on Bitchute:
“The pathogen that is causing all the deaths from the illness is the spike protein. And the spike protein is what the vaccine is supposed to make in your body. … Spike protein is one of the most contrived poisons that man has ever made. And, the aim of this toxin, is to kill billions of people without anyone noticing it. So it is a poison with an agenda.” (“South African Physician Dr. Shankara Chetty Talks about “The Bigger Plan”, Bitchute)
There it is in a nutshell. And Chetty is not alone in linking the vaccine to the agenda of the globalist elites who plan to use the cover of a pandemic to implement their “population management” scheme. Former Pfizer vice president, Mike Yeadon, offered a similar view just days ago on his website. He said:
“We are in the midst of the biggest depopulation program the world has ever seen, where most of humanity are acting as useful idiots to it and to their own demise.”
Indeed, and we have tried to provide as much information as possible on the biologic agent that is being used to pursue this malign agenda, the spike protein. In early reports we passed along the research of Dr. Patrick Whelan who grasped the danger of the spike protein before anyone else. Here’s a brief recap of his analysis from a letter he submitted to the FDA on December 8, 2020:
“I am concerned about the possibility that the new vaccines aimed at creating immunity against the SARS-CoV-2 spike protein have the potential to cause microvascular injury to the brain, heart, liver, and kidneys in a way that does not currently appear to be assessed in safety trials of these potential drugs.
… Meinhardt et al…. show that the spike protein in brain endothelial cells is associated with formation of microthrombi (clots)… In other words, viral proteins appear to cause tissue damage without actively replicating virus…. The Pfizer/BioNTech vaccine (BNT162b2) is composed of an mRNA that produces a membrane-anchored full-length spike protein. The mouse studies suggest that an untruncated form of the S1 protein like this may cause a microvasculopathy in tissues that express much ACE2 receptor.
… it appears that the viral spike protein… is also one of the key agents causing the damage to distant organs that may include the brain, heart, lung, and kidney. Before any of these vaccines are approved for widespread use in humans, it is important to assess in vaccinated subjects the effects of vaccination on the heart…. As important as it is to quickly arrest the spread of the virus by immunizing the population, it would be vastly worse if hundreds of millions of people were to suffer long-lasting or even permanent damage to their brain or heart microvasculature as a result of failing to appreciate in the short-term an unintended effect of full-length spike protein-based vaccines on these other organs. (“FDA shrugs off dire warning about lethal spike protein“, Truth in the Age of Covid)
From the very beginning, government regulators and their allies in the public health establishment have ignored (or censored) the warnings of capable physicians and researchers. They also waved-off career immunologist and vaccinologist, Dr Byram Bridle who was the first in his profession to identify the spike protein as “a specific causative agent of disease”; aka–“a pathogen”. Here’s Bridle:
“‘We have known for a long time that the spike protein is pathogenic… It is a toxin. It can cause damage in our body if it’s in circulation. Now, we have clear-cut evidence that . . . the vaccine itself, plus the protein, gets into blood circulation.’”
Once that happens, the spike protein can combine with receptors on blood platelets and with cells that line our blood vessels. This is why, paradoxically, it can cause both blood clotting and bleeding. ‘And of course the heart is involved, as part of the cardiovascular system… That’s why we’re seeing heart problems. The protein can also cross the blood-brain barrier and cause neurological damage…
‘In short,… we made a big mistake. We didn’t realize it until now. We didn’t realize that by vaccinating people we are inadvertently inoculating them with a toxin.”… (“Vaccine scientist: ‘We’ve made a big mistake’“, TCW Defending Freedom )
Here again, we have a highly-regarded immunologist, with more than 3 decades of experience under his belt, who offered his informed and evidence-based research on an issue that should have been of great interest to the regulators that were making decisions about the long-term safety of the experimental drug they were foisting on millions of people across the country. But there was no interest at all. Despite the fact that the science supported his conclusions, Bridle was viciously attacked, censored, dragged through the mud, and forced to leave his place of employment.
Why?
Because he drew the same conclusions as Dr. Patrick Whelan. There’s really no substantive difference between the two except that Bridle’s comments attracted more attention in the media which made him a greater threat to the “universal vaccination” strategy. That was his real crime; he discovered the truth and made his findings available to the public, basically alerting them to the dangers of the “poison-death shot”. For that he was crushed.
Bridle has since made other claims that should concern anyone whose cancer might be in remission. Here’s what he said in a recent interview:
“What I’ve seen way too much of is people who had cancers that were in remission, or that were being well controlled; their cancers have gone completely out of control after getting this vaccine. And we know the vaccine causes a drop in T-cell numbers, and those T-cells are part of our immune system and they are part of the critical weapons our immune system has to fight off cancer cells; so there’s a potential mechanism there. All I can say, is I’ve had way too many people contact me with these reports for me to feel comfortable. I would say that is my newest major safety concern, and it’s also the one that’s going to be the most under-reported in the adverse data base, because if someone has had cancer before the vaccine, there’s no way public health officials will ever link it to the vaccine.” (“Dr Byram Bridle speaks”, Bitchute, :55 second-mark)
So, the vaccine suppresses the immune system?
Yes, it does, and author Alex Berenson provided evidence of this just recently in an article he posted on Substack. Here’s an excerpt:
“… the British government… admitted today, in its newest vaccine surveillance report, that:
“N antibody levels appear to be lower in people who acquire infection following two doses of vaccination.” (Page 23)
What’s this mean?…
What the British are saying is they are now finding the vaccine interferes with your body’s innate ability after infection to produce antibodies against not just the spike protein but other pieces of the virus…
This means vaccinated people will be far more vulnerable to mutations in the spike protein EVEN AFTER THEY HAVE BEEN INFECTED AND RECOVERED ONCE…
… it probably is still more evidence the vaccines may interfere with the development of robust long-term immunity post-infection.” (“URGENT: Covid vaccines will keep you from acquiring full immunity EVEN IF YOU ARE INFECTED AND RECOVER”, Alex Berenson, Substack)
Berenson’s observations square with research that was compiled earlier in the year by scientists in The Netherlands and Germany who:
“… warned that the … (COVID-19) vaccine induces complex reprogramming of innate immune responses that should be considered in the development and use of mRNA-based vaccines… the research team from Radboud University Medical Center and Erasmus MC in the Netherlands… showed that the vaccine altered the production of inflammatory cytokines by innate immune cells following stimulation with both specific (SARS-CoV-2) and non-specific stimuli.
Following vaccination, innate immune cells had a reduced response to toll-like receptor 4 (TLR4), TLR7 and TLR8 – all ligands that play an important role in the immune response to viral infection…. an unexplored area is whether BNT162b2 vaccination has long-term effects on innate immune responses …
This could be very relevant in COVID-19, in which dysregulated inflammation plays an important role in the pathogenesis and severity of the disease,” writes the team. “Multiple studies have shown that long-term innate immune responses can be either increased (trained immunity) or down-regulated (innate immune tolerance) after certain vaccines or infections.” (Research suggests Pfizer-BioNTech COVID-19 vaccine reprograms innate immune responses, new-medical-net)
Berenson’s finding also align with with cutting-edge research showing that the spike protein greatly “impedes adaptive immunity” by preventing DNA from repairing damaged cells. The paper suggests that the spike protein does in fact “impact on the nucleus of the cell, where we store our DNA, our core genetic material.” Here’s more from Berenson’s breakdown of the paper:
“… our cells have mechanisms to repair their own DNA.
But – at least in the experiments these two scientists ran – the spike protein appeared to interfere with our own DNA repair proteins: “Mechanistically, we found that the spike protein localizes in the nucleus and inhibits DNA damage repair by impeding key DNA repair protein BRCA1 and 53BP1 recruitment to the damage site.”
To be clear, the scientists did NOT prove the spike protein was causing these problems in people, or even animals… Nonetheless, at a time when advanced countries that have high mRNA (and DNA/AAV) vaccination rates are seeing unusually full hospitals and higher-than-normal death rates, they are yet more cause for concern. As the authors explained:
“Our findings reveal a potential molecular mechanism by which the spike protein might impede adaptive immunity and underscore the potential side effects of full-length spike-based vaccines.” (“URGENT: Worrisome paper about the spike protein’s impact on DNA and DNA repair”, Alex Berenson, Substack)
Bottom line: If the vaccine does in fact inhibit the body’s innate immune response, then people are going to get alot sicker from seasonal infections that routinely spread through the population. Their path to recovery will also be alot more difficult.
But rather than belabor the immunity angle, let’s move on to the research of Dr Charles Hoffe who was the first physician to provide hard evidence that the vaccines generate blood clots by triggering an immune response in which the body attacks the thin layer of cells lining the walls of the blood vessels. Hoffe found that 62% of his patients that had been vaccinated tested positive for blood clots on a D-dimer test. Naturally, he was alarmed by what he found, particularly since the vaccine “was causing serious neurological events, and even death. When he raised his concerns with the BC College of Physicians, they immediately implemented a gag order, and reprimanded him in an attempt to intimidate, and silence him.”
Hoffe has been interviewed a number of times and always provides a detailed and riveting account of his findings. In a recent interview, he predicted that some vaccinees suffering from clot-related issues would likely die in just three years. Here’s what he said:
“… once you block off a significant number of blood vessels to your lungs, your heart must pump at a much greater resistance to get the blood through your lungs. That causes a condition called pulmonary artery hypertension, which is high blood pressure in your lungs because so many of the blood vessels in your lungs are blocked. And the terrifying thing about this is that people with pulmonary artery hypertension usually die of right-sided heart failure in three years… And not only is the long-term outlook very grim, but with each successive shot, the damage will add and add and add. It’s going to be cumulative because you are getting more and more damaged capillaries.” (“Shock: Doctor Warns That Majority Of Vaccinated Patients Could HavePermanent Heart Damage, Some May Die Within Three Years”Permanent Heart Damage, Some May Die Within Three Years”, Infowars; Minute 6:10)
Once again, there is no discrepancy between the analysis of Whelan, Bridle and Hoffe. And while the focus of their attention might vary slightly, their conclusions are the same. These experimental injections pose serious risks for anyone who allows himself to be inoculated.
Now check out how similar Hoffe’s analysis is to Dr. Rochagne Kilian who was an Emergency Room physician at the GBHS hospital until she resigned in protest. This is a particularly important video as it describes the “oddball” symptoms and exceedingly rare conditions that are now presenting in emergency rooms everywhere following the mass vaccination of millions of people with the “poison-death shot”. (I transcribed the video myself, so there could be errors.)
Dr Rochagné Kilian – Blows the Whistle on Covid-19 Vaccines and D-Dimer Levels
“What I was seeing in my ER department especially in the last 8 to 9 months is related to the D-Dimer levels. We use D-Dimers specifically related to pulmonary embolisms as well as Deep Vein Thrombosis. D-Dimer detects any thrombosis (clots) in the body but it doesn’t give you a diagnosis it gives you a basis for going further and doing an ultrasound and CT scan to either confirm or deny the presence of a pulmonary embolism or Deep Vein Thrombosis.
The first part of 2020 was probably the slowest ever in the emergency department, but when we went into 2021 and the vaccination rollout started, we ended up seeing an increase in stroke, transient ischemic attacks and stroke like presentations. (There were) definitely significant larger numbers of those people coming in. I ended up doing D-dimer tests on these people and never before in my clinical experience had I seen D-dimers and the amount of people with positive D-dimers higher than 2,000, higher than 3,000 and higher than 5,000. My clinical experience told me a needed to go look for a large clot either in their legs or their lungs. And I ended up doing a CT scan on these people. Most of them, and I will say almost all of them, had negative scans which started making me think that if there was not a significant clot in their lungs, but my D-dimer was so much higher than what I was usually seeing, it might not be concentrated in one clot. But that it is multiple micro-thrombi extended throughout the body, and that is so easy to miss because the CT scan is not going to pick it up.
“These people coming into the ER were all people anywhere from about a week to four months after receiving their 2nd injections. There are certain factors that can influence a D-dimer test that can give you a sense of a higher level than would be expected in the body. That said, the patients I was doing D-Dimer tests on did not have a level of maybe a positive 500 or 400 reading. It was more than 3500, more than 5000 ng/ml. So those are significantly positive without any proof of having a pulmonary embolism. If I was seeing high levels of D-dimer without a definite diagnosis, I needed to ask more questions.
One study said, never ignore extremely elevated D-dimer levels. They are specific for serious illness, including venous thrombosis, sepsis, and/or cancer. Even if sharply elevated D-dimer are a seemingly solitary finding, clinical suspicion of severe underlying disease should be maintained.
There were two conditions that stood out and the first one was disseminated intravascular coagulation also known as DIC. The second one is antiphosphlipid syndrome. Both of these conditions are related to an abnormality in either the initiation or the feedback of the coagulation pathway as well as thrombosis or the thrombosis cycle where clots are being broken down. DIC is a serious sometimes life threatening situation in which the proteins in the blood involved in blood clotting become overactive. It’s a cascade that’s difficult to stop once it’s reached a certain level. There are certain conditions that trigger DIC; significant sepsis, underlying viruses, trauma, major surgery, pregnancy and childbirth. And less common causes toxic drug reaction, blood transfusion reaction, and organ transplants. So there was a connection with intravascular products and a possible DIC.
Most cases of DIC are diagnosed rapidly and suddenly which is the acute presentation. But there are cases where it develops gradually, occurring over a longer period of time. This is known as a chronic form of DIC and I would go as far to say a subacute form of DIC that is very easy to miss. Simultaneous clotting and bleeding can occur with chronic DIC. The bleeding part comes in blood in the urine, headaches and other symptoms associated with brain bleeds, bruising, inflammation of red, small dots on the limbs, bleeding at sites of wounds and mucosal bleeding. which means bleeding out of the gums and nose. I definitely saw an increase in nose bleeds and bleeding from previous wound sites. ulcers, as well as rashes that couldn’t be explained. Blood clotting symptoms and signs were symptoms like chest pains, heart attacks, strokes, TIAs, and headaches either related to bleeding or not. As well as symptoms related to kidney failure, because of the clotting of those smaller blood vessels that go to the kidneys. Antiphosphlipid syndrome is a very similar type of condition. But the basis of the antiphosphlipid syndrome is an autoimmune disorder meaning that the body’s immune system makes proteins–known as antibodies–that mistakenly attacks its own body or tissues. That gives the skin the cascading effect of clotting disorder but it is linked to an autoimmune trigger. Basically, it presented in exactly the same way; high blood pressure which I was seeing alot of; first diagnosis of high blood pressure, heart attacks, strokes, TIAs, heart valve problems, repeated headaches or migraines, vision loss, balance and mobility problems, difficulty concentrating or thinking clearly,
The astute listener would start forming a picture of what we’ve been told about Covid-19, and there are research papers connecting Covid 19 with an underlying vascular disease. One of these was a study called “Covid 19; unraveling the clinical progression of Nature’s Virtually perfect Biological weapon.”
“SARS-Cov-2, presenting as Covid-19 syndrome, was not a respiratory basis, but an underlying vascular basis. which had certain phases of incubation, pulmonary phase, pro inflammatory phase, (which once again comes into a cytotoxic inflammation process) then moves into a protothrombic phase . Covid-19 is a thrombotic disease. implications for prevention, antithrombotic therapy and follow up…
This picture shows us certain risk factors, Homeostatic Abnormalities, as well as clinical outcomes. It indicates increased D-dimer levels. It also mentions Venous Thromboembolism, Myocardial Infarction, and Disseminated Intravascular Coagulation that is connected to postulated mechanisms of coagulathopy as well as parthenogenesis of thrombosis in Covid-19…
I started asking the question, if we are able to detect certain connections between vascular abnormalities and Covid-19, and we based our proposed treatment on the spike protein, which includes the Pfizer and Moderna injections, shouldn’t we be looking for similar side effects or complications from that same injection?
If we are mandating certain treatments, we do need to do the due diligence to make sure what the side effects and complications especially in a time where there has not been long term studies.”And that’s what led me to focusing on D-dimers.” (“Dr Rochagné Kilian – Blows the Whistle on Covid-19 Vaccines and D-Dimer Levels“, Bitchute)
Kilian’s statement should be read over and over again. It is the most detailed description we have of the mysterious and deeply sinister machinations of a laboratory-engineered bioweapon that, in effect, turns the vascular and immune systems against the person who was vaccinated. Disseminated intravascular coagulation and antiphosphlipid syndrome are names that are entirely unknown to the American people, and yet, these freakish conditions are now responsible for a growing number of patients that are experiencing bleeding, clotting, headaches, rashes, bruising, high blood pressure, and inflammation . And– in more extreme cases– chest pains, heart attacks, strokes, heart-valve problems, and brain bleeds. One can only guess how the media will try to cover-up these extraordinarily-rare and potentially life-threatening conditions??
When Kilian asks:
“If we are able to detect certain connections between vascular abnormalities and Covid-19… shouldn’t we be looking for similar side effects or complications from that same injection?”
Bingo! If the spike protein produced by the vaccines, inflicts the same internal damage as Covid-19, then shouldn’t doctors expect to see the same symptoms?
Yes, they should. And if the symptoms are the same, then there’s a good chance that vaccine-induced injuries are being misdiagnosed as Covid-19.
Think about that for a minute. That would be the perfect scenario for the pandemic managers and their billionaire backers who’d love to see the impending mountain of carnage blamed on the waning virus instead of on their own poison-death shot.
And that is the evil-genius of the globalist strategy; to remove the fingerprints from the smoking gun before the investigators even arrive at the scene of the crime.
The amount of planning that must have gone into this scam, is simply breathtaking.

This perverse ban on ivermectin, cheap and proven to work
By Kathy Gyngell | TCW Defending Freedom | November 23, 2021
GIVEN the feared winter resurgence of Covid infection despite, or because of, the government’s mass vaccination programme, the continued ban on ivermectin in this country becomes ever more perverse.
It beggars belief that the British public is still denied access to this proven prophylactic and treatment. If the public health authorities are genuinely worried about pressure on hospitals, why have not the Medicines and Health products Regulatory Agency (MHRA), Public Health England, the NHS and Department of Health all gone flat out over this last year to approve ivermectin with the same zeal they gave emergency authorisation to the limited trialled, novel gene therapy, Covid vaccines?
The answer is widespread misinformation from the top down. Put ‘ivermectin’ into the Google search box and what do you come up with? Topping the list is a warning from the US Food and Drug Administration (FDA) why it should NOT be used to treat or prevent Covid-19. Their reason? It’s as simple as the fact that they have not approved it and, because they have not approved, it cannot be used. Trials are ongoing they say. Maybe some are. But plenty have been completed, as Dr Pierre Kory’s paper (he was the lead author) ‘Review of the Emerging Evidence Demonstrating the Efficacy of Ivermectin in the Prophylaxis and Treatment of Covid-19’, published by the American Journal of Therapeutics earlier this year, made quite clear.
By contrast with this detailed review of the evidence the FDA’s substantive concern appears to rest on random reports of harms deriving from self-medication with ivermectin.
The BBC not to be behindhand entered the fray with its customary selective and biased take on ‘the science’. Its recent report entitled ‘How false science created a Covid ‘miracle’ drug‘ made not even the most minimal of checks on the veracity of their assertions, which are pulled apart here. A letter sent to a programme journalist in response to their request for information (in advance of transmission) by Dr Tess Lawrie, the Director of the British Ivermectin Recommendation Development Group (BIRD), an advocacy group of clinicians and scientists from around the world, setting out the science behind the case for authorising it, was completely ignored. Her letter can be found here.
How the BBC came not to ask how it was that remdesivir – a standard medication for Covid in the UK – was approved on the basis of one study when ivermectin, with 63 studies, of them 31 Randomised Controlled Trials (RCT), 7 meta-analyses, 32 Observational Controlled Trials (OCT), multiple country case studies, expert opinion, patient testimony ALL pointing in favour of the medication, was not, is inexplicable.
This is the news source the public is still told to trust.
A blog posted on BIRD last week asked whether there are indeed any genuine gripes about the quality of the evidence, as the FDA and others suggest?
No, there are not. The author argues it is down to a misinformation campaign based on misleading information produced by high profile public health agencies, like the World Health Organisation, itself a victim of disinformation tactics, that has been ‘perpetrated by a minority of corporations to manipulate and delay government action on matters that would adversely affect their income and profit’. Speculation of course. But every indication points that way.
As reported extensively in TCW Defending Freedom, for example here, the WHO is subject to the huge financial influence of the Bill and Melinda Gates Foundation, the organisation’s second biggest donor. Since one of the BMGF’s long-term interest is in delivering vaccines, why would they show any interest in promoting the use of cheap, old repurposed medications in the treatment and prevention of Covid-19? It’s for the very same reason that ivermectin has proved of so little interest to Big Pharma -it’s hardly the money spinner that indemnified world-wide vaccination is.
Worse perhaps than what these big interests have not done is what they have actively done to discredit ivermectin. The BIRD blog relays an analysis by Dr Kory setting out what the WHO ‘did’ with the ivermectin evidence. He says it:
· Failed to publish a pre-established protocol for data exclusion
· Excluded two ‘quasi-randomised’ controlled trials (RCTs) with lower mortality
· Excluded two RCTs that compared ivermectin to or gave it together with other medications, all reporting lower mortality
· Excluded seven other available ivermectin RCT results
· Excluded all RCTs and observational controlled trials (OCTs) investigating ivermectin in the prevention of Covid-19
· Excluded 13 OCTs, more than 5,500 patients, that showed reductions in mortality
· Excluded numerous published and pre-print epidemiologic studies.
The bottom line, however, remains – if ivermectin is good enough and provenly effective for the more than 20 lower-income countries which do distribute it and also benefit from lower Covid rates, why are the populations of wealthier nations and individuals still being denied?
It’s a point that clearly has bothered the chairman of the Tokyo Medical Association, Dr Haruo Ozaki, who would recommend ivermectin for Covid patients, noting that the parts of Africa that use ivermectin to control parasites have a Covid death rate of just 2.2 per 100,000 population, compared with 13 times that death rate among African countries that do not use ivermectin.
‘I would like,’ said Dr Ozaki, ‘the government to consider treatment at the level of the family doctor’ with the informed consent of the patient. So would we.
Featured Video

EUROPE FEARS RUSSIA’S NEXT MOVE / Ian Proud
or go to
Aletho News Archives – Video-Images
New Book
New Book: No Autoimmunity The Body Doesn’t Attack Itself
Lies are Unbekoming | September 24, 2026
 The label for Humira, once the best-selling drug in the world, lists its risks in plain print. One of them, in the label’s own words, is new “autoimmune” disease.
A drug prescribed for a condition labelled autoimmune carries a warning that it can cause a condition labelled autoimmune. That contradiction sits in every box, on a folded paper almost nobody reads.
My new book starts there.
No Autoimmunity: The Body Doesn’t Attack Itself
For seventy years, “your body is attacking itself, and we don’t know why” has ended the conversation for people diagnosed with multiple sclerosis, lupus, rheumatoid arthritis, Hashimoto’s, Type 1 diabetes, Crohn’s and psoriasis. More than eighty conditions now carry the autoimmune label. The diagnosis comes with a prescription for life. It almost never comes with a question about cause.
This book asks the question and answers it from the framework’s own records: its drug labels, its journals, its regulatory filings, and its own experiments. … continue
Blog Roll
 Aletho News
- Turkish parliament to review Saudi-Pakistan defense pact next month
- DEATH SPIKES & RISING CANCER IN OUR YOUTH EXPLAINED
- Iran offers Trump deal before US election
- Merz regime wants ‘secret police’ – opposition
- Israeli settlers terrorize West Bank Palestinians with state-provided drones: Report
- They see them, then kill them: Israeli quadcopters track, deliberately target civilians in Gaza
- Debunked: Trump’s egregious UNGA claims on war against Iran crumble under scrutiny
- Europe was part of the infrastructure of US aggression against Iran: Deputy FM
- New evidence on the Bucha Massacre
- Italy and France debunk reports CIA issued ‘Russian drone threat’ warning
- If Americans Knew
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- In UN Speech, Iran’s President Displays Pictures of Children Killed by US, Brings Attention to Israel’s Nuclear Arsenal
- Israel displaces hundreds of Palestinians amid wave of demolitions in West Bank
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

