Unassailable proof that the COVID vaccines are the most deadly vaccines in human history
By Steve Kirsch | November 16, 2021
Just because the FDA, CDC and the Public Health Agency of Canada have found no issues with the vaccines, doesn’t mean they are safe. Here’s unassailable proof they aren’t.
We have to stop blindly trusting our trusted authorities that they are giving us good information. It isn’t warranted. We should always insist on hearing both sides of the story.
We should be extremely suspicious when not a single leading medical advocate of the vaccine is willing to debate a team of qualified scientists who disagree with the narrative.
For example, it is well known that Merck received approval from the FDA to give Vioxx to 2 year old children just 3 weeks before Merck pulled the drug for safety issues.
We’re doing it again now with our kids and this time the drug companies aren’t going to pull it even though there is compelling evidence in plain sight of everyone.

Here are three pieces of unassailable proof that the COVID vaccines are the most dangerous in history and should be immediately pulled:
- The VAERS data shows 8,456 deaths in the US (note: if you are using openvaers, be sure to “flip the switch” to show domestic only). Even using the most conservative assumptions of 223 background deaths (the highest annual death toll in VAERS history for domestic deaths), this is 8,233 “excess” deaths. Something caused those deaths. That’s a HUGE number. It’s a public health disaster. If it wasn’t the vaccine, then what did the CDC find caused all these excess deaths? Nothing! Absolutely nothing! Note that I didn’t even have to multiply by the VAERS under-reporting factor (URF) of 41 (calculated via the CDC’s own methodology). There are only 226M vaccinated people. That’s a death rate from the vaccine of at least 36 deaths per million vaccinated (assuming the most conservative possible URF of 1). That’s 36 times more deadly than the deadliest vaccine in human history, a vaccine that is too unsafe to use. It has no business being on the market. Note that all reports in VAERS are validated by HHS before they are allowed to appear in VAERS. Mistakes do happen. There are at least 2 records of the 1.6M in VAERS that were gamed, one by Dr. David Gorski (who is proud of breaking Federal law to do that).
- A prominent group of neurologists with 20,000 patients has had around 2,000 patients with vaccine-related adverse reactions. In the 11 year history of the practice, they’ve never had a patient with a vaccine-related adverse reaction. While this could happen just by bad luck, the chance of it happening by “bad luck” is less than 1 in 10**100, i.e., impossible. This is a huge increase in significant neurological events that is inexplicable if the vaccines are safe. This is further evidence that the increase in the events reported in VAERS is not “stimulated reporting.” NOTE: The doctors won’t come forward publicly for fear of retribution (loss of medical license). That’s why nobody knows. With the doctors’ permission, I’m happy to disclose it to the NY Times or other allegedly reputable news source under NDA if they want to do a story on it.
- And then there is the 60-fold increase in the rates of adverse events happening in front of our eyes. Hard to explain since it never happened before the vaccines rolled out.
When I say unassailable, I mean that nobody can argue using evidence that these happened due to something other than the vaccine as the primary cause. The “using evidence” is key. People make hand-waving arguments all the time to dispute hypotheses. What matters is arguments with supporting evidence. That appears to be non-existent in all three cases.
Extra credit
And then I got this which matches what I’ve heard from others. It’s a bit hard to explain if the vaccines are safe. Check with your own neurologist if you don’t believe me.

Europe heads the stampede to medical apartheid
By Tom Penn | TCW Defending Freedom | November 16, 2021
WHILE the media engaged in a classic diversionary tactic – chortling over reports that former Health Secretary Matt Hancock was to write a book about how he won the Covid war – they virtually ignored perhaps the most concerning pandemic news out of Western Europe so far.
The Netherlands entered a three-week partial lockdown, the news of Austria’s lockdown for the unvaccinated was ‘officially announced’, and Germany’s health agencies began clamouring for tougher restrictions.
Segregation on so-called medical grounds is finding ever firmer footing in Europe – no doubt spurred on by its increasingly successful introduction in Australia and New Zealand even in the face of huge, impassioned protests.
This is the hyper-normalisation of medical apartheid at work, and one day soon the witless masses who permit this process to erode unchallenged the moral bedrock of their societies, will wake up to find that it was they, not their governments, who were the engineers of an all-encompassing punitive style of governance whose dystopian interventions not even the quadruple-jabbed will ultimately be able to evade.
On home soil the supposed leak of the UKHSA’s plan to abandon attempts at stopping the spread of SARS-CoV-2 ‘at all costs’ come springtime, using their exit-strategy named ‘Operation Rampdown’, should come as highly disconcerting and not optimistic news in light of the madness playing out across the Channel right now.
Quite aside from the fact that we have heard all this tosh about promised freedom numerous times before and yet here we are still stuck waist-deep in the bog of Covid-19 interventions, from what we know of the 160-page dossier so far, the scaling-back of spread-control measures is limp to the point of portentous: the real question being just what will such controls be replaced with?
The last 20 months has shown that when the State give with one hand, they use the other to put more shackles on the recipient – we, the people – and Operation Rampdown already sounds not like the Yellow Brick Road to freedom but the paving of the way for medical apartheid.
Ten-day self-isolation is supposedly to be entirely done away with: however, in all likelihood only for those vaccinated and with up-to-date boosters. Free Covid testing is supposedly to end: a move designed to impose a Macron-style financial burden on the unvaccinated, as private testing firms with ties to Government break free of the pricing limitations never enforced in the first place, and the national ‘Test and Trace’ system is purportedly to be scrapped, the billions invested set only to reveal the software’s original design-objective: universal health passports.
When Johnson talks about the ‘storm clouds gathering over Europe’ I don’t envisage the DHSC’s Covid-smoke wafting our way, I see instead scope for ‘circuit-breaker’ lockdowns for the unvaccinated; given succour via the majority of people’s inability to heed the deafening alarms currently being sounded by various neighbouring EU Governments.
At present the UK population is like an infant flat on its back, staring beguiled at a revolving cot-mobile, off which dangles the likes of Matt Hancock, dog coronavirus, and a Harry Kane international hat-trick; whilst Papa Johnson is busy disabling the home’s smoke alarms and opening all the windows in an attempt not to let Covid-19 out, but the far more noxious smoke of apartheid in.
Matt Hancock, I suggest not the working title ‘How I Won the Covid War’, but ‘How I Started the Covid War Engineered Never To Be Won’, alongside the quote from yourself, dated March 16 2020:
‘We should only use the NHS when we really need to.’
You say the war is won, Mr Hancock, yet we still can’t use the NHS. Write a book about that, why don’t you, then you’ll finally find yourself on the same page as the six million poor sods awaiting treatment.
IMF Correctly Predicts Arrival of Compulsory Vaccination Across Russia After Gifting Kremlin $18 Billion
By Edward Slavsquat | Anti-Empire | November 16, 2021
Before October, most of Russia’s 85 regions had few (if any) COVID-related restrictions; mandates requiring businesses to vaccinate the majority of their employees—introduced in Moscow and several other regions in June—had not yet become the norm.
This all changed after the State Duma elections in late September. Speaking a day before the election results were announced, Annette Kyobe, IMF Representative in Russia, made a prophetic observation. As TASS reported at the time:
“There is no appetite [in Russia] for restrictive measures, lockdown, at least on the part of state authorities. <…> After the parliamentary elections, perhaps a more unpopular measure, like mandatory vaccination, can be initiated as early as October-November. “
What an incredible prediction! As it just so happens, COVID “cases” and “deaths” inexplicably began to skyrocket immediately after the Duma elections, forcing Russian authorities to introduce mandates and QR codes across the country.
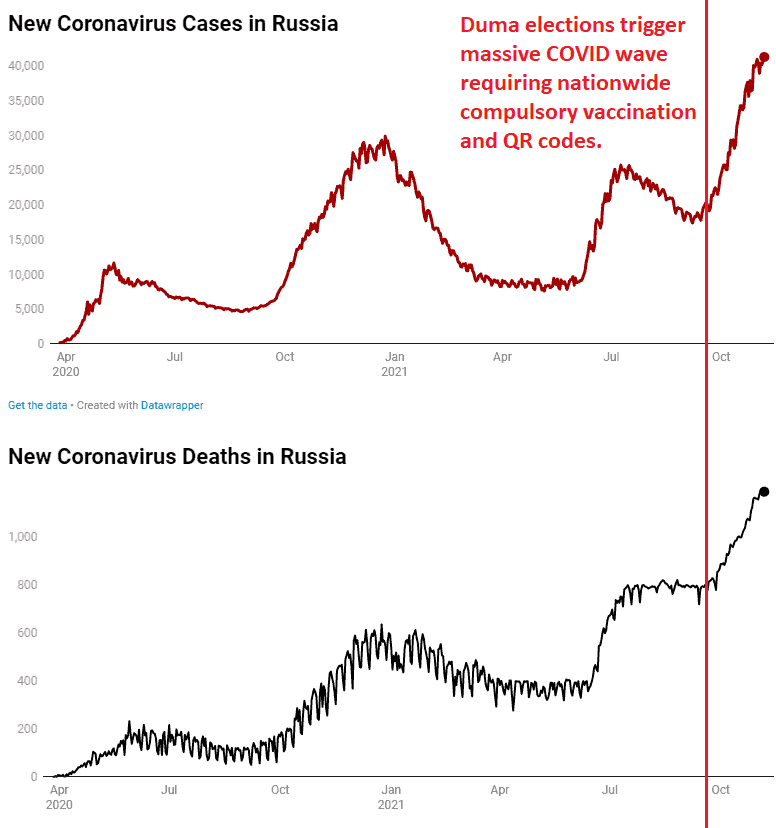
IMF totally called it!
Starting in October, Russian regions began the mass adoption of vaccine mandates and digital “health” passes. On October 14, Deputy Finance Minister Timur Maksimov told the IMF and World Bank that Russia’s government understood how important it was to shove a needle into every arm:
Participants in the autumn session of the IMF and the World Bank on Wednesday came to the conclusion that the problem of the crisis in the global economy cannot be solved until the population of all countries is vaccinated in the required proportion, Russian Deputy Finance Minister Timur Maksimov told reporters following these meetings.
“Until all countries are vaccinated in the required proportion, the world will not return to the old normality. Therefore, the question was raised that it is necessary to increase efforts to produce, to ensure access to vaccines. more and more waves of COVID cover different countries, “Maksimov said.
But wait… how was the IMF—an organ of Western Financial Extortion—able to so accurately predict Russia’s warm embrace of the global Vax Caste System?
Just a lucky guess. Obviously it had nothing to do with the 18 billion United States Dollars that the IMF shoveled into the Kremlin’s coffers back in August. The head of the IMF described the generous cash-injection as part of a “vaccination for the world economy during an unprecedented crisis.” (We should note for the sake of accuracy that the $18 billion was awarded in the form of “special drawing rights.” SDRs are units of account for the IMF and represent a claim to currency held by IMF member countries for which they may be exchanged.)
Outrageously, some Russian analysts and media outlets have suggested that something is slightly suspicious about all this—but why would they suggest something so silly? Anyway:
“There is no appetite for restrictive measures, lockdown, at least on the part of the state authorities. After the parliamentary elections, perhaps a more unpopular measure, such as compulsory vaccination, can be initiated as early as October-November.”
This is an excerpt from the speech of the IMF Resident Representative in Russia Annette Kyobe during the Fitch Ratings webinar “Russia – Macroeconomic Forecast 2021”.
On the air on the Tsargrad TV channel, Alexander Losev, a member of the Presidium of the Council on Foreign and Defense Policy, explained why our country continues to cooperate with discredited organizations and why the IMF wants to vaccinate all of Russia:
“The IMF and the World Bank are two organizations that have introduced such a concept as the Washington Consensus.
Adherence to this Washington Consensus is written for all developing countries.
First of all, this is a limitation of state sovereignty, less support for business, more – the market, invisible hands of the market, there are many of them, and some requirements for budgets and budgetary policy.
All countries that followed the Washington Consensus ended up poorly, with crises.
The second point is why the IMF says it.
At the end of August, the Bank of Russia received $ 18 billion from the IMF in the form of special drawing rights, that is, it received money. I’m not hinting at anything, I’m just stating: was the money accepted? Accepted.
These are the institutes of world governance created by the United States. And now the activity of these institutions is an attempt by the United States to preserve its hegemony, to preserve its power over the world.
They are tools. Behind them is the United States and their establishment, those who manage capital, world politics – or think they do.
[…]
The main beneficiaries of the pandemic are, of course, financiers. Because all the money that governments and central banks sent to help the economy, they basically all went through the banking system. The American banking system is $ 90 trillion in assets. All the money that the government allocated went there too.
The estimate is how much money was allocated and how much got into the banking system, from 24 to 27 trillion dollars. Equivalent. In different countries, including developing countries.
Utter nonsense! Russia adopted nationwide compulsory vaccination policies because there was a huge, dangerous wave of COVID that emerged immediately after Duma elections, which required more Sputnik V, everywhere and for everyone. If Russians don’t like it, they will have a chance to vote again, in the next Duma elections, in 2026.
Public health is a funny thing.
False imagery and data hallmarks of COP26

By Vijay Jayaraj | CNS News | November 12, 2021
Mainstream media is infamous for its exaggeration of everyday events. When it comes to the issue of climate change, it rarely misses an opportunity to promote fear. True to form, during the COP26 climate conference in Glasgow, media promoted incorrect information spewed by politicians and famous personalities.
Special attention was drawn to the assertion that rising sea levels are threatening island nations by none other than Barack Obama, who incongruously has purchased a multi-million-dollar ocean front property on the New England coast.
Catching the attention of millions was the image of a Tuvalu minister standing in knee-high sea water. But there is a problem with this: Most islands in the South Pacific nation of Tuvalu have gained surface area and are in no danger of being inundated.
Despite sea-level rise that has been underway since the end of the last ice age, Tuvalu’s land area has increased recently by 2.9 percent. A peer-reviewed research paper which studied four decades of shoreline change in all 101 islands in theTuvalu atolls categorically proves this. The paper notes that “…change is analyzed over the past four decades, a period when local sea level has risen at twice the global average (~3.90 ± 0.4 mm.yr−1). Results highlight a net increase in land area in Tuvalu of 73.5 hectares (2.9%) despite sea-level rise and land area increase in eight of nine atolls.”
The case of Tuvalu is not unique. Various island nations have gained landmass in recent decades, including Maldives which increased by 37 square kilometers since 2000.

(Getty Images)
The climate doomsday machine has been using this image-based propaganda for a while now. National Geographic circulated an image of a starving polar bear and falsely claimed that the bear’s condition was a direct result of man-made climate change. However, polar bear populations are relatively healthy and have increased in recent decades. When exposed, the famous media channel issued a statement saying that the reason for the dismal condition of the bear is unknown and that it had exaggerated the climate impact.
At COP26, Bill Gates joined climate elites who resorted to a false representation of reality to promote climate fear. “Farmers in low-income countries are at high risk from the impacts of climate change,” said Gates. But a closer look at weather data and the state of global agriculture reveals a different picture.
The United Nations makes clear that there is no strong evidence that climate change is having a significant influence on the frequency of extreme weather events. IPCC AR5 WGI Chapter 2 states, “In summary, there continues to be a lack of evidence and thus low confidence regarding the sign of trend in the magnitude and/or frequency of floods on a global scale.” When it comes to droughts, the report states that “… there is not enough evidence at present to suggest more than low confidence in a global-scale observed trend in drought or dryness (lack of rainfall) since the middle of the 20th century.”
Consider India, a country with world’s largest number of low-income farmers. More than 500 million people depend either on agriculture or allied products. Of that total, 150 million depend only on agriculture — the equivalent of 40 percent of the U.S. population.
These farmers — with an average monthly income of less of $120 — depend on monsoon rainfall and there has been no climate signature on the monsoon rainfall trend. Nor has there been any increase in cyclones. In other words, there has not been any increased risk from climate change for India’s farmers. Another indicator of the absence of heightened risk is crop production. For four consecutive years, India has produced record food crops, higher than ever before in its history.
You would think that Gates would know something about agriculture and climate given that he owns 242,000 acres of U.S.farmland and said to be the largest private owner of such acreage. However, it appears that the billionaire is at best ill-informed.
Though fancying themselves to be noble defenders of nature, these purveyors of doomsday scenarios are more akin to a cult’s priesthood offering commoners salvation in exchange for prosperity and freedom.
Vijay Jayaraj is a Research Associate at the CO2 Coalition, Arlington, Va., and holds a Master’s degree in environmental sciences from the University of East Anglia, England. He resides in Bengaluru, India.
Why have we doctors been silent?

By Lucie Wilk | TCW Defending Freedom | November 15, 2021
AS an NHS hospital doctor, I have had a front-row seat as the drama of the coronavirus pandemic has unfolded. It has been a year and a half of confusion, frustration and anger for me as I’ve watched our profession drawn into complicity with what I anticipate will be regarded as one of the most egregious public health disasters in history.
I have watched as ‘the science’ has been presented on the national stage flanked by Union Jack flags as an unassailable truth. For something so apparently inviolable, it seems to shift and change disconcertingly from week to week, and for those of us looking beneath the pomp to the plain data, we see the rather unexciting (and unchanging) truth: the novel coronavirus SARS-CoV-2, as it turns out, has a much lower infection fatality rate than early predictions. It is less deadly than the seasonal flu in children. The Office for National Statistics has reported the mean age of a Covid-attributed death in the UK to be 80.3 years, slightly older than deaths from other causes (78.2 years over the comparable time period).
What has been most upsetting for me has been the unquestioning compliance from the medical community as increasingly draconian, non-evidence-based and destructive virus control measures have been implemented. Some of the overt corruption, financial conflict of interests and politicisation has been laid bare in editorials in prominent medical journals such as the BMJ. But the vast majority of doctors have had no interest in asking questions or looking further.
My concern over our professional passivity turned to alarm as our compliance required us to support the roll-out of an experimental vaccine to a trusting population.
Contrary to the basic tenets of evidence-based medicine, pronouncing an experimental medical intervention ‘safe and effective’ now does not seem to require any peer-reviewed evidence of safety or clinically meaningful efficacy. The vaccines have not been shown in clinical trials to reduce transmission, hospitalisation or death. The phase 3 trials are not over and the safety data is not complete; the earliest trials will run into 2023.
The consent form for the Covid-19 vaccine does not disclose its status as an unlicensed experimental product. The risks remain largely unknown, although it is becoming clear that the vaccine has resulted in death or injury in a rising number of healthy people. A growing number of vaccine-induced syndromes are being recognised, including immune thrombotic thrombocytopaenia, myocarditis and menstrual irregularities, among many others being published in the literature. At the time of writing, there have been more than 380,000 reports, 1.2million injuries and 1,700 fatalities submitted under the MHRA Yellow Card scheme.
The Prime Minister himself has communicated the latest evidence, that two doses of the vaccine do not stop one contracting the virus, nor do they stop person-to-person transmission, they merely reduce the severity of symptoms. Despite this, it is clear the public are being subjected to a relentless media campaign of shame and coercion, that they must take this experimental product ‘for the greater good’ lest they be viewed as selfish cowards. A vaccine passport is now likely to be rolled out under ‘Plan B’, which proposes to return unlawfully usurped fundamental human rights and freedoms to only the vaccinated. Workers in the care home sector have had their livelihoods tethered to their compliance with the vaccine mandates, and a recent announcement confirms that this will soon include NHS employees. Not only is there no scientific basis for these mandates, these coercive actions breach the Nuremberg Code, as does the unprecedented lack of animal safety data for a novel medical product. A betrayal of the Nuremberg Code constitutes a crime against humanity.
It does not end there. The campaign marches on, and now includes the vaccination of children against a disease that has a statistically negligible chance of harming them. In the world of evidence-based medicine we doctors must weigh risks and benefits, we must ensure the risk of harm is far exceeded by the potential for protection or cure. In this case, with no real risk to healthy children from the infection, any harm is utterly unjustifiable. And the risk of harm is very real and measurable. Vaccine-related myocarditis is now a recognised injury, the risk inversely proportionate to age. Although rare, myocarditis can be fatal, and fatality is more common in the younger population. For reasons that have nothing to do with health, and despite the JCVI advisory board concluding that the health benefits do not outweigh the risks to children, the government is advising that we administer a medicine that carries a risk of serious injury to children who are healthy and who have no significant risk from the disease it purports to protect them against.
Despite all this, and despite our training to look at scientific literature and data with a critical eye, the silence from the medical community in the UK has been deafening. Yet we are the ones who should be shouting all of this from the rooftops. This is a duty of care and an oath we have forgotten.
It is typically those of us most conditioned by the expectations of society, utterly obedient and deferent to authority, who gain entry to medicine. One can see the path: we were good, compliant children and then good, compliant students. Now we are good, compliant doctors. I’m beginning to understand that goodness is measured in a different way, and obedience is not a virtue.
Obedience is learned through fear, threat and intimidation; it is in fact trauma programming and achieved through small control gestures when we were young and helpless. Now we are adults but still operating under these childhood programmes of beliefs and fears. We still feel helpless and beholden to a higher authority. We still submit to an authoritative decree even when it overrides our inherent moral compass.
The horrors of the classic Milgram experiment demonstrated that we live in a deeply traumatised culture, and the same conditioning, in my view, has shaped the medical community and its silence.
Even on the occasion when my counter-narrative evidence cannot be denied by a colleague, the usual response is: ‘It’s coming from the government; our hands are tied.’ But the truth is that most of the time doctors don’t want to see the evidence; their subconscious has prevented them seeing that the parent-like authorities of government, Sage and the MHRA, upon which we project a childlike trust, might be misguided, corrupted or dishonest.
And so we comment to each other on all the changes we are witnessing months into the vaccine roll-out: the unseasonal surge in hospital admissions, the post-jab autoimmune conditions and coagulation disorders, the numbers of ‘double-jabbed’ patients admitted with severe Covid infection, the numbers of lives ruined by lockdown and other Covid control policies. I challenge any doctor to deny that all of this simply feels wrong. To avoid this uncomfortable, authentic, human feeling – important information that should be acted upon – we will reach for something rote. ‘Anecdote is not evidence’ and ‘association is not causation’ will be the justification for carrying on, no questions asked, even though most of the damaging control measures implemented from on high were not based on any evidence at all. Meanwhile, an already struggling NHS has been damaged beyond repair by many of these policies. We are overwhelmed by the demand that we cannot meet, and the complexity of the crisis feels far beyond just one hospital Trust. The locus of responsibility to investigate remains above us and we wait for someone with more authority to come round and make sense of it.
And as we remain silent, the destruction continues.
Most of us went into medicine for the right reasons: to help the vulnerable, to reduce suffering. I know my colleagues are kind and well-intentioned and that their faith in our unelected public health policymakers is the result of a lifetime of conditioning. For those of us who have looked at the data and see the truth, I understand the fear: the risk of non-conformity is immense; careers, reputations and livelihoods are at stake. I recognise an even larger threat: a threat to our chosen profession, our life purpose, the possibility that we have been following a false god in our honest intentions to help the ill. We are at a difficult crossroads, but the choice for me is clear.
Although I am not on the front line in the ‘fight’ against coronavirus, and have had nothing to do with the vaccine campaign, I feel complicit in this public deception. I can no longer hide within a system that has proved itself to be weak-willed and unwilling to stand against the irrevocable erosion of inalienable human rights and freedoms in the name of public health safety. It is past the time for us to grow up, stand up and speak out.
Here’s the real reason Comirnaty is not available
It’s all about liability. It will magically become available when the vaccine for children is fully approved, not before.
By Steve Kirsch | November 3, 2021
The reason Comirnaty isn’t available is because those shots would expose the company to liability since the fully-licensed product doesn’t have the liability waiver of the EUA product.
But once the Pfizer vaccine is fully approved in kids, then Pfizer gets liability waiver on all age groups due to a “feature” in federal law for child vaccines (NCVIA). At that time, they are done. They can market the COVID vaccine products under full approval for all age groups and face no liability when it kills or disables you.
This is why they are focused on the kids. This is why there is a reformulation at a 1/3 dose and they changed the buffer and the storage conditions (low temperatures not required). All of these will weaken the protection, but result in a safer vaccine (since it is ineffective).
But for the clinical trials on the 5-11 year olds, they did not use the formulation they approved in the meeting. This is known as bait and switch. So they used a more effective vaccine to show efficacy (in the trials they completed), then they get the FDA to approve the drug but with a change in formulation, then the product with the new buffer will go out to the public with the lower efficacy, but better safety. This is because they don’t want to jeopardize any adverse events happening until they are fully approved. So they basically use formula 1 for safety, get approval for formula 2 (safer, less effective), then roll out formula 2 under EUA.
They also arrange with the FDA and CDC to make sure no early treatment drugs get approved or recommended. This is why there is no movement on fluvoxamine, ivermectin, etc. since that would blow the EUA. Fluvoxamine is the best drug ever for COVID with a mortality reduction of 12X when taken early. It’s the best drug to date for COVID, but the CDC and NIH are deliberately burying it until the vaccines are fully approved. Then they’ll say, “ok, we have all the data.”
So at the end, Pfizer gets a fully approved vaccine with full liability protection. At that time, then the NIH can recognize other treatments.
This is how it is wired to go. Let’s be honest about it.
This is why nobody wants to debate our team about what is going on.
The Geniuses Are Locking Down Again
By Tom Woods | Principia Scientific International | November 15, 2021
Today someone shared the chart below, generated by the Financial Times. Try to pick out which one of these countries hasn’t implemented a vaccine passport system:

I’ll bet you know which one it is.
Meanwhile, parts of Europe are going back into lockdown.
Austria is locking down the one-third of the population that is unvaccinated.
The Netherlands is 72 percent fully vaccinated and is going into lockdown for everyone, vaccinated and unvaccinated.
Wouldn’t it be nice if, instead of inanely blaming “the unvaccinated” for this, the robots on social media would at least admit that this isn’t how they expected it to go, and that there shouldn’t be this level of cases and deaths after the introduction of vaccines?
It’s like Sweden: we were supposed to believe that Sweden would have one of the worst death rates in the world because it ignored the so-called experts demanding lockdown.
Well, Sweden is currently #53 in the world for COVID death rate. Number fifty-three. Not one. Not two. Not ten. Not twenty. Fifty-three.
The crazies are still criticizing Sweden, naturally.
But my question is: when you were screaming hysterically at Sweden to lock down, did you think they’d end up all the way down at number 53 in the world in death rate?
Aren’t you the least bit curious about that? Is there a chance that if we hadn’t wrecked societies it wouldn’t have made any difference anyway?
Same with Florida: did the hysterics expect them to have one of the better rates of age-adjusted COVID mortality in the United States?
Of course not. They were warning that Florida would be one of the worst.
And yet in none of these cases can they bring themselves to say: thank goodness things turned out better than we predicted!
Instead, they just double down.
Long Covid doesn’t exist, volume one zillion
By Alex Berenson | November 10, 2021
The Journal of the American Medical Association has another stunning paper out, this one on post-Covid symptoms in almost 27,000 French adults.
Researchers asked people to report whether they had had Covid and whether they had any of 18 lasting symptoms like insomnia, fatigue, or cough. They found that self-reported Covid was very strongly associated with nearly every symptom.
But the scientists then went a step further.
They also had Sars-Cov-2 antibody test results for the people they had surveyed, so they didn’t have to depend on self-reported Covid. They knew who really had had Covid and who had not.
They then compared self-reported symptoms in people with antibodies – that is, people who had actually been infected and recovered from Covid – to the general population. And they found no difference in almost any symptom.
Covid was not a risk factor for chest pain, or breathing difficulties, or trouble focusing, or stomach pain, or any of the many, many other complaints that long Covid “patients” and interest groups say are real. There was one interesting exception; people with Covid antibodies did have a much higher rate of anosmia, losing one’s sense of smell. Because anosmia is a known and lasting side effect, it serves as a useful control of sorts.

The researchers also found that almost 60 percent of the people with antibodies HAD NO IDEA THEY HAD EVEN HAD COVID AT ALL. Meanwhile, while more than half the people who said they had had Covid had no antibodies. (Welcome to the plague so severe most halfway healthy adults don’t even know they’ve had it.)
The study strongly suggests that many people are using previous Covid diagnoses – either real or imagined – to help explain away common physical symptoms such as joint pain or cough. It also suggests that actually being infected Covid is far less risky than thinking you have been infected with Covid for many people.
The researchers concluded by explaining that people who claim they have long Covid may need help “to identify cognitive and behavioral mechanisms that may be targeted to relieve the symptoms.” Which is a very polite way of putting the truth.
This study should slow, if not stop, the rush to medicalize long Covid. It is yet more proof that the illness is a group of squishy (if painful and difficult) symptoms looking for a name – and more importantly a billing code.
But so many patients and physicians and public health experts are now invested (in some cases literally) in making long Covid real that the gravy train will likely roll on.
SOURCE: https://jamanetwork.com/journals/jamainternalmedicine/fullarticle/2785832
NIH Conflicted Internally Over Vaccine Mandates
By Dr. Joseph Mercola | November 14, 2021
Preliminary talk leading up to a live-streamed roundtable the National Institutes of Health has planned for December 1, 2021, indicates that the science isn’t settled within the agency itself when it comes to COVID-19 vaccine mandates.
According to The Wall Street Journal, a request for an ethics review by one of the NIH senior infectious disease researchers triggered the scheduling of four seminars on the issue, beginning with the December one.
“There’s a lot of debate within the NIH about whether [a vaccine mandate] is appropriate,” David Wendler, the senior NIH bioethicist who is in charge of planning the session, told The Wall Street Journal. “It’s an important, hot topic.”
One specialist who plans to argue against mandates is Dr. Matthew Memoli, who works with clinical studies in the NIH’s National Institute of Allergy and Infectious Diseases (NIAID). Memoli is not vaccinated for COVID-19. Memoli said his children have received their regular childhood vaccines — he simply thinks “the way we are using the [COVID] vaccines is wrong” and that the COVID-19 vaccine mandates are “extraordinarily problematic.”
His views are concerning for people like Timothy Schacker, vice dean for research and infectious-disease physician at the University of Minnesota Medical School. Schacker believes that bypassing the vaccine and trusting natural infection to be enough to prevent a COVID case is “a terrible idea.”
Coincidentally, the person who signed off for the seminar is Christine Grady, wife of the NIAID’s director, Dr. Anthony Fauci. Wendler reports to her.
How much does vaccine efficacy drop over 6 months? The VA and CDC duke it out
Whose data are better? Whose study was peer-reviewed? Who got published in Science magazine?
By Meryl Nass, MD | November 13, 2021
CDC is always finding ways to massage their data or use estimates instead of real numbers to “prove” the veracity of whatever narrative it is currently pushing. But I think CDC did not reckon with the VA system fighting back with the truth.
Here is the conclusion of CDC’s study of (selected) VA data regarding COVID vaccine efficacy over six months:
During February 1–August 6, 2021, vaccine effectiveness among U.S. veterans hospitalized at five Veterans Affairs Medical Centers was 87%. mRNA COVID-19 vaccines remain highly effective, including during periods of widespread circulation of the SARS-CoV-2 B.1.617.2 (Delta) variant. Vaccine effectiveness in preventing COVID-19–related hospitalization was 80% among adults aged ≥65 years compared with 95% among adults aged 18–64 years.
VA scientists pushed ahead and studied the entire VA database of 780,000 vaccinated beneficiaries from February to October, and published it in the US’ premier science journal, Science.
Their conclusions, drawn with only a few more weeks of data than CDC had, but using a more complete dataset that had not been cherrypicked, were shockingly different than what CDC’s braintrust had reported.
Here is how the VA authors characterized CDC’s overall COVID data collection:
The debate over boosters in the U.S. (24) has laid bare the limitations of its public health infrastructure: national data on vaccine breakthrough are inadequate. The CDC transitioned in May 2021 from monitoring all breakthrough infections to focus on identifying and investigating only hospitalized or fatal cases due to any cause, including causes not related to COVID-19 (25). Some data on vaccinations, infections, and deaths are collected through a patchwork of local health departments (10), but these data are frequently out of date and difficult to aggregate at the national level. Here, we address this gap and examine SARS-CoV-2 infection and deaths by vaccination status in 780,225 Veterans during the period February 1, 2021 to October 1, 2021, encompassing the emergence and dominance of the Delta variant in the U.S.
And their results?
“26,114 positive PCR tests occurred in 498,148 fully vaccinated Veterans–over 5% of vaccinated veterans got COVID despite their vaccinations.”
There are probably considerably more than 5% of vaccinated veterans who came down with COVID: those who chose to be tested closer to home than in a VA facility were not included.
In March, VE-I (vaccine efficacy against infection) was 86.4% for Janssen; 89.2% for Moderna; and 86.9% for Pfizer-BioNTech.
But six months later…
By September, VE-I had declined to 13.1% for Janssen; 58.0% for Moderna; and 43.3% for Pfizer-BioNTech.
This is consistent with Israel’s report in August that Pfizer vaccine efficacy had dropped to 39%. Israel vaccinated its population more speedily than the US and all other countries.
The VA found that protection against death was better than protection against infection, but also waned over time. And the VA authors then cited ten other studies who data were consistent with what the VA found:
Other U.S. studies (29–31), many conducted in large healthcare systems, similarly show declining VE-I as the Delta variant rose to dominance, with notable declines in older adults. For example, two studies conducted in Kaiser Permanente Southern California show VE-I decreased from 95% at 14-60 days to 79% at 151-180 days after vaccination for ages 18-64 years (29), and from 80% at 1 month to 43% at 5 months after vaccination for ages ≥65 years (31). Declines in protection against infection with Delta have been observed in Israel (16), the UK (20, 21), and Qatar (32, 33)…
It is not yet known whether breakthrough infections increase risk of long COVID (otherwise known as post-acute sequelae of COVID-19 or PASC), a constellation of debilitating and lingering symptoms following infection.
It seems we ought to know whether the vaccinated COVID patients are at higher risk, lower risk or the same risk of long COVID by now. But CDC isn’t telling.
It is remarkable that the VA was allowed to publish these honest data. Perhaps all those vaccine mandates for federal employees had something to do with it?
CDC Redefined Vaccine to Support Deficient Fake Vaccines Sold by Drug Companies
By Joel S. Hirschhorn | November 14, 2021
The CDC once was a federal agency that nearly everyone respected. That no longer is the case. Now there are many reasons why the CDC should be widely disrespected. Its latest debacle is how it changed the definition of vaccine.
Just imagine this: The entire push for COVID “vaccines” was based on a lie – they did not meet the official CDC definition of a vaccine. By doing this, the government could coerce the entire population to get the shot. Calling them “vaccines” was the biggest lie from Fauci and the key to drug companies making many billions of dollars.
Why would the government’s key public health agency change the definition of what a vaccine is in the midst of a pandemic? After millions of Americans have taken the shot? And millions more are being beaten into taking it for the first time and others to get booster shots.
Words matter
Here is the key point. It became widely recognized by medical experts and informed citizens that COVID vaccines clearly did not fit the official CDC vaccine definition. The CDC thought the answer was not to fix what was deficient with the COVID vaccines or stop their use by most people as so many medical experts advised. Their response was to change the vaccine definition to fit the so-called vaccines.
This was done so that vaccine mandates could keep getting pushed by the government. Of course, the COVID “vaccines” should be referred to as gene therapy products, even better than calling them experimental vaccines.
To see how corrupt this action by the CDC was, it is necessary to examine the details of the vaccine definition debacle.
Prior to September 1, 2021 here is how CDC defined vaccine:
A product that stimulates a person’s immune system to produce immunity to a specific disease, protecting the person from that disease. Vaccines are usually administered through needle injections, but can also be administered by mouth or sprayed into the nose.
This definition had been used for years and it makes sense. No expert or sensible citizen would find fault with it. But did it honestly apply to the COVID vaccines?
Then this is what the CDC concocted:
A preparation that is used to stimulate the body’s immune response against diseases. Vaccines are usually administered through needle injections, but some can be administered by mouth or sprayed into the nose.
Here is what the CDC also said:
Immunity: Protection from an infectious disease. If you are immune to a disease, you can be exposed to it without becoming infected.
Think about that last sentence: You can be exposed to COVID without being infected; but we know that is not true for fully vaccinated people who still get infected.
This is the key language in the original definition:
“stimulates a person’s immune system to produce immunity to a specific disease, protecting the person from that disease.”
How rational to invoke the purpose of a vaccine to stimulate an immune system to produce immunity to a specific disease that protects the recipient from that disease. Exactly what everyone for years thought was the correct way to think about a vaccine. People want permanent protection from the COVID infection disease.
But now the CDC has taken out the language referring to getting immunity for a specific disease and getting protection from that disease.
Now, COVID vaccines do not have to directly produce immunity. No, now they only have to stimulate the body’s immune system.
You don’t get immunity because COVID vaccines do not directly produce immunity. They do not directly kill the COVID virus. Vaccinated people can still have high viral loads and also transmit the virus to others. While some individuals may get some health benefits from COVID shots, they do not necessarily protect the entire population. This is why mandates to get everyone the shots really do not make sense from a public health perspective, that Dr. Paul Alexander has well substantiated.
Apparently, the only logical way to understand what the CDC has done is to accept the truth belatedly seen by the CDC that COVID vaccines do not, in fact, produce effective immunity for COVID infection and do not provide effective protection, once vaccinated, from that infection.
Much of the public surely does not yet know what the CDC has acknowledged for the COVID vaccines. Odds are that everyone who depends on mainstream media for good information about the pandemic has not been informed about what the CDC has done and its implications.
The new vaccine definition, if publicly known, would reduce public confidence in current COVID vaccines. You don’t have to be a medical expert to see how the new definition has been created to accommodate COVID shots.
In fact, these definition changes reflect what is now known about the limitations of the COVID vaccines.
Fully vaccinated people can still get COVID disease, referred to as breakthrough infections that, contrary to what the government says, can be very serious, often requiring hospitalization and sometimes causing death, as was the case for Colin Powell. Such serious effects have been well discussed by Dr. Günter Kampf. Other times, breakthrough infections greatly disrupt lives, as recently described by Madrigal, a strong proponent of COVID shots.
Moreover, the COVID vaccines are now widely known from considerable clinical evidence to lose their effectiveness typically in about six months. And even worse, they do not provide hardly any protection against variants like the delta variant. Same disease but from a different virus in terms of its complex genetic makeup. So, befitting the new CDC definition the COVID shots really do not have long lasting effective immunity to the specific COVID infection caused by all variants.
Elsewhere on the CDC website is a glossary of many terms; here is what is especially relevant to the debate about COVID vaccines:
Attenuated vaccine: A vaccine in which a live microbe is weakened (attenuated) through chemical or physical processes in order to produce an immune response without causing the severe effects of the disease. Attenuated vaccines currently licensed in the United States include measles, mumps, rubella, varicella, rotavirus, yellow fever, smallpox, and some formulations of influenza, and typhoid vaccines.
Most people would read this and find that it fits with what they think of as vaccines that have been routinely taken by most people, especially children. Clearly, COVID vaccines do not fit this definition. But seeing this established view of vaccines helps explain why so many people resist and reject the COVID shots. They are so fundamentally different than long accepted and used vaccines.
Natural immunity
One of the biggest pandemic scandals is that the government refuses to give full credit to natural immunity that people get from once being infected by the COVID virus. It should be officially recognized as equivalent to “vaccine” immunity.
The following CDC glossary definition is especially relevant:
Active immunity: The production of antibodies against a specific disease by the immune system. Active immunity can be acquired in two ways, either by contracting the disease or through vaccination. Active immunity is usually permanent, meaning an individual is protected from the disease for the duration of their lives.
This CDC definition of active immunity recognizes that you can get it by contracting the disease versus through vaccination. In other words, it recognizes what today is commonly called natural immunity achieved by once being infected by the COVID virus. And that such immunity is likely permanent and better than vaccine immunity, as recent clinical studies substantiate. But it also infers that active immunity obtained through vaccination is also permanent, which clearly is not the case for COVID shots, as evidenced by breakthrough infections.
Also note that it has recently been revealed that the CDC has not been able to provide any proof of at least one instance of an unvaccinated, naturally immune individual transmitting the COVID-19 virus to another individual.
And a new study found that almost 60 percent of the people with antibodies had no idea they had even had COVID at all. But they would have natural immunity. Quite consistent with the reality that most people suffer no significant health impacts from being infected with the COVID virus, regardless of all the fear mongering by Fauci and others.
Conclusions
To sum up, a close look at what the CDC has done lately reinforces the thinking of millions of people who have reservations and concerns about getting COVID genetic therapy shots that pose myriad adverse impacts and sometimes death.
There is a rational, science basis for thinking that the limited benefits of those shots do not adequately offset their risks. This is true for the vast majority of healthy people, especially children, who have extremely low risk from COVID infection for serious illness, hospitalization or death.
Mandates that do not recognize natural immunity are merely a sham tactic to make money for drug companies.
How interesting it would be, in the context of informed consent, if people were shown the original and new CDC vaccine definitions as a means to stimulate productive discussion with medical providers of COVID shots.
Dr. Joel S. Hirschhorn, author of Pandemic Blunder and many articles, podcasts and radio shows on the pandemic, worked on health issues for decades. As a full professor at the University of Wisconsin, Madison, he directed a medical research program between the colleges of engineering and medicine. As a senior official at the Congressional Office of Technology Assessment and the National Governors Association, he directed major studies on health-related subjects; he testified at over 50 US Senate and House hearings and authored hundreds of articles and op-ed articles in major newspapers. He has served as an executive volunteer at a major hospital for more than 10 years. He is a member of the Association of American Physicians and Surgeons, and America’s Frontline Doctors.
Featured Video

Broke Princes: Saudi Arabia’s Powder Keg
or go to
Aletho News Archives – Video-Images
From the Archives
Registered Israeli foreign agent driving contrived campus antisemitism crisis
By Wyatt Reed | The Grayzone | December 17, 2023
Lawsuits accusing top US universities of harboring antisemitism all originate from one source: a corporate law firm that fielded the pro-settler ex-US ambassador to Israel, and which was registered as a foreign agent of an Israeli principal as recently as 2021.
The firm now represents professional Israel lobby activists posing as victimized “Jewish students” and seeking to crush the free speech rights of Palestine solidarity activists. … continue
Blog Roll
 Aletho News
- Did Israel lose the midterms?
- How Iran defeated Trump’s Israel First GOP
- De-escalating the conflict: What the OSCE, the UN, and Europe are (not) doing to prevent war
- Desperate For A Renewed Iran War, Israel Dusts Off The WMD Deception.
- US Elections Offer Choice Between ‘Bad and Worse’ as Both Parties Serve War Lobby – ex-UN Expert
- Ghalibaf warns US government not to betray voters who rejected war
- Broke Princes: Saudi Arabia’s Powder Keg
- Albania’s Crisis: Rama, Israeli Investments and the Demand for Accountability
- Hezbollah Categorically Denies Syrian Accusations: We Aim at Confronting Israeli Enemy, Not Undermining Syria’s Stability
- Trump claims funding to Israel ending in 2026 as merger of Israeli–US armies looms
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago

