Preventing Covid Infections Among Healthy Children Is Pointless
By Noah Carl • The Daily Sceptic • October 12, 2021
Thanks to school closures, children missed out on in-person teaching, as well as regular face-to-face interaction with their friends, for the best part of a year.
The main rationale for closing schools was to help ‘flatten the curve’ of total infections, and thereby prevent the NHS from being overwhelmed. (We’ve known since early on in the pandemic that children’s risk of death from Covid is vanishingly small – lower even than their chance of dying from seasonal flu.)
However, evidence suggests that neither lockdowns in general, nor school closures in particular, were necessary to prevent healthcare systems from being overwhelmed; and the harms from school closures were substantial.
Once the Government conceded it was time for schools to reopen, there came a new justification to keep them closed: protecting teachers. Yet studies have repeatedly shown that teachers are not at elevated risk of death from Covid.
Even after schools finally did open up, pupils faced a rigamarole of mask mandates, regular testing and stints of mandatory self-isolation. Since the vast majority of vulnerable people (and most teachers) had been vaccinated by this point, it’s unclear exactly why things couldn’t just return to normal.
As far as one can discern, the specific rationale seems to be: ‘something to do with case numbers and/or long Covid’. Why we should care about case numbers in an age-group that faces a higher risk of death from season flu has not been explained.
As to long Covid, the latest data suggest that only a tiny number of children (less than 2%) continue to report symptoms 12 weeks after infection. One study found that symptoms were no more common among children who’d had the virus than among those who’d never been infected.
Despite all this, demands for more restrictions in schools can still be heard. On 3rd September, scientists associated with Independent SAGE, as well as various other individuals and organisations, co-signed a letter in The BMJ Opinion calling for the Government “to protect children, our wider communities, and the NHS”.
Their “nine point plan” includes such measures as: reinstating face coverings; offering vaccines to all 12–15 year-olds; and reinstating contact tracing “with a strict policy on mandatory isolation”.
But according to Chris Whitty, “roughly half” of children have already have Covid, and it’s reasonable to assume that “the great majority” are “going to get it at some point” because “this is incredibly infectious”.
Now that almost all vulnerable people have been vaccinated, why are we trying to stop children getting the virus if “the great majority” of them are going to get it at some point anyway? Offering the vaccine to those with an underlying health condition makes sense, but apart from that, why do anything at all?
In fact, shouldn’t we actively encourage young people to get the virus, so as to build up more population immunity before the winter?
Ex-Pfizer Employee Warns Vaccine Increases COVID By Over 300%
By Lance D Johnson | Humans Are Free | October 1, 2021
The fraudulence of covid-19 vaccines is on full display, and the evidence is sitting right out in the open. The full FDA approval for Pfizer’s COMIRNATY vaccine contained clinical proof that the inoculation increases COVID infection by over 300 percent!

Varitage.com
A former Pfizer employee named Karen Kingston is blowing the whistle on her former employer. Kingston is currently a pharmaceutical marketing expert and biotech analyst. When she scrutinized the full FDA approval for COMIRNATY, she found blatant fraud in Pfizer’s clinical studies.
FDA Approves Pfizer’s Covid-19 Vaccine, Even Though It Increases Infection By 300 Percent
Kingston brought forth a Briefing Document from the FDA’s advisory committee meeting that took place on September 17, 2021. The title of the document is, “Application for licensure of a booster dose for COMIRNATY (COVID-19 Vaccine, mRNA).” The document includes clinical studies conducted by Pfizer. These studies track the durability of immunity offered by the COMIRNATY vaccine and compare it to immunity observed in unvaccinated people.
“If you get the Pfizer vax, you’re more likely to get COVID” said Kingston, “So, when they weren’t injected, their infection rate was 1.3% and when they got injected, it was 4.34%. It went up by over 300%.” How could the FDA have glossed over this evidence and approved blatant fraud?
Since the vaccine was officially approved, the federal government started applying pressure on businesses across the US, threatening them with extortion and fines if they do not impose vaccine mandates on their employees.
The covid-19 vaccines have been injected almost 225 million times into the arms of Americans, causing severe injury and death along the way. Real world observations also support clinical data showing that the vaccines increase one’s susceptibility to covid-19.
In fact, the vaccines increase viral load in the nostrils of the vaccinated. An August 26 article by Dr. Peter McCullough shows that the covid vaccines allow the vaccinated to carry 251 times the viral load of covid-19 in their nostrils, turning them into the asymptomatic super spreaders they once feared.
Pfizer Studies Show That Being Unvaccinated Offers Greater Protection
Medical freedom rights attorney, Thomas Renz, went public with the Pfizer fraud. The Pfizer study involved over 36,000 people. Those who were injected earlier in the study were more likely to come down with covid infections later on, showing a clear trend of waning immunity. Those put in “high priority” groups, who were vaccinated earlier on, have a 36 percent greater chance of infection, compared to the group that vaccinated later on.
The group that vaccinated later on went unvaccinated for 5.1 months longer than the group that got vaccinated early on. This placebo group did not have high rates of infection while they were unvaccinated, even though they went longer without any “protection.”
Because of this, Kingston stated that the vaccinated group “have an even higher chance of being infected with COVID-19 than the 36 percent difference indicated by this portion of the study.”
The study even admitted in its conclusion: “An additional analysis appears to indicate that incidence of COVID-19 generally increased in each group of study participants with increasing time post-Dose 2.” Kingston clarified that infection rates “increase over time” when people get two doses of Pfizer mRNA.
Most shocking was the data on the placebo group. In the first four months, the placebo group had “no vaccine protection” and recorded an infection rate of 12.6 cases per 1,000 person-years. The infection rate for the unvaccinated was a meager 1.3 percent.
After their placebo period, the group got “fully vaccinated.” In just a few months, this group became more infectious and showed 43.4 cases per 1,000 person-years. Their infection rate went UP by over 300 percent to a 4.34% infection rate. Mrs. Kingston called this “super alarming.”
“They had less infection when they had no protection. So, that’s a problem,” she said.
References:
Are leaky vaccines driving delta variant evolution and making it more deadly?
by el gato malo – bad cattitude – october 10, 2021
one of the great fears in any vaccination campaign is that the vaccine can wind up becoming the driver viral evolution and making the virus more dangerous. this is a special concern around imperfect (so called “leaky”) vaccines that are non-sterilizing. such vaccines do not stop spread or contagion of the virus. this means the virus will have lots of chances to replicate.
when you combine this with a vaccine that reduces severity of cases and prevents deaths in the vaccinated, it’s a bit of a perfect storm. you get full spread but break the evolutionary gradient towards mildness that viruses tend to follow (and that protects humanity from them).
all a virus wants is to replicate. “make a copy of me and pass it on.” that’s the biological imperative of the selfish gene. excel at it, you win. fail, you disappear. simple as that.
killing or harming the host is maladaptive to viral spread. it’s like burning down your own house with your car in the garage. now you have nowhere to live and no way to get around. that’s not a recipe for reproductive fitness.
this is a property of the world, not of the viruses themselves. so it applies to all of them, evolved and lab hotwired alike.
so viruses evolve to become less, not more virulent. they do not want to kill you. ideally, they’d like to help you. figure out how to be a useful symbiote, and you get a huge boost in propagation. (mitochondria were probably bacteria that were so useful, all our cells incorporated them.) so seeing case fatality rate (CFR) rise in a variant of a virus is like watching water flow uphill. it’s not supposed to do that and when it does, you need to suspect some external force acting on it.
and we’re seeing water flow uphill here.
i started with the england variants of concern (VoC) data. it’s the best quality and the best broken out. (the US data is just plain broken. it’s being deliberately scrubbed to prevent analysis like this.) because this data is always aggregated from feb to current period, it does not provide good temporal snapshots, but this can be fixed by subtracting the penultimate report from the current one etc. you subtract report 22’s totals from report 23 and you get just what happened in the last 2 weeks (it used to be a weekly report, now it’s bi-weekly)
what we see is not what one would expect from a virus. none of the other variants (pre vaccine) worked like this. none saw CFR rise like this. and no jump from major variant to variant saw a statistically significant rise in deadliness.
this IS however what one would expect if a virus were undergoing vaccine mediated evolution (as mareks disease did in chickens) and selecting for hotter strains because vaccinated people can carry and spread them and not die.
experienced CFR on delta is nearly 7X what it was in the beginning of june and has been galloping since the middle of july.
(note that pretty much all this data has a large artifact in it from the 21 june report (VoC 17). there was a “data-dump” in it where they caught up on a bolus of past data. it’s an artifact, not a signal. best to ignore it. i suspect the curve from mid june to mid july was smooth.)
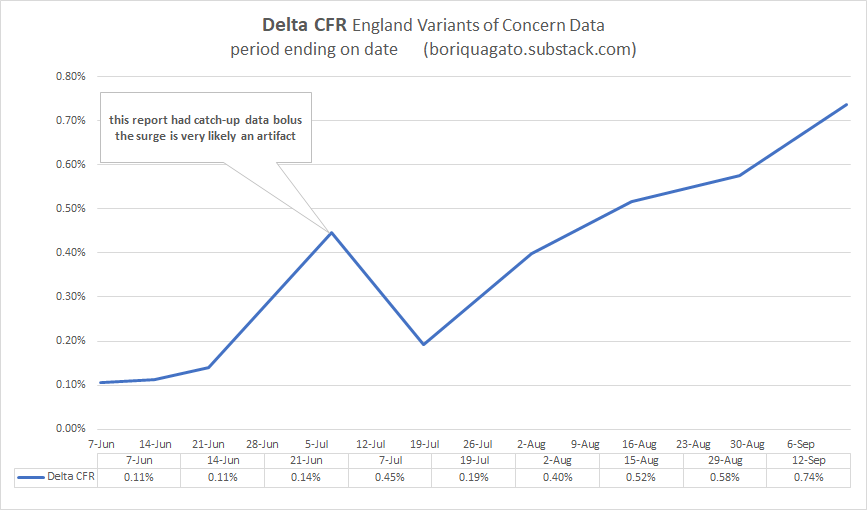
put simply: this is not good.
delta is rapidly approaching alpha (1.1%) in terms of CFR whereas it used to be 90% lower. (it also means that the reports on delta CFR in these VoC updates are FAR too low because they are a blend of all cases and deaths back to feb, so they are averaging in the low CFR past and are slow to respond to current dynamics)
this is consistent with, but not proof of vaccines mediated evolution. to get there, we need to do better.
so now we need to start ruling things out and validating this claim to see if it’s meaningful.
first, it’s not a simpson’s paradox in age data. CFR is rising in over and under 50’s. it’s not mix shift alone. CFR in over 50’s is up 2.5X. it’s up 4-7X in under 50’s.
we’re at about a 3X rise in CFR overall in delta since the summer once we adjust for shifts in age. not as worrying as 7, but still worrying.
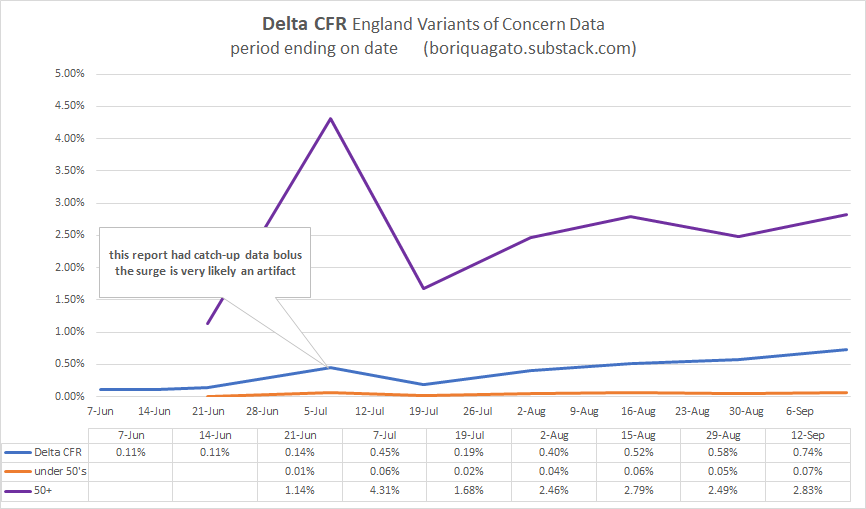
and the deaths are real. it’s not made up counting. this can be clearly seen when we comp CFR to the euro-momo Z scores (thoughtfully provided by frequent gato collaborator ben m at USmortality.com. z score is just a measure of deviation from expected all cause deaths. (explained HERE)
alignment is quite strong.
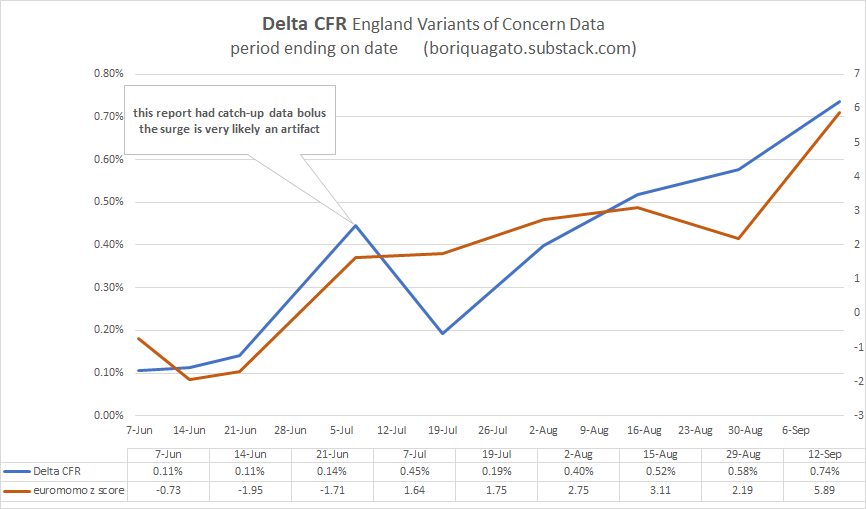
z score was trending negative and spiked to high levels just as CFR really started to ramp up.
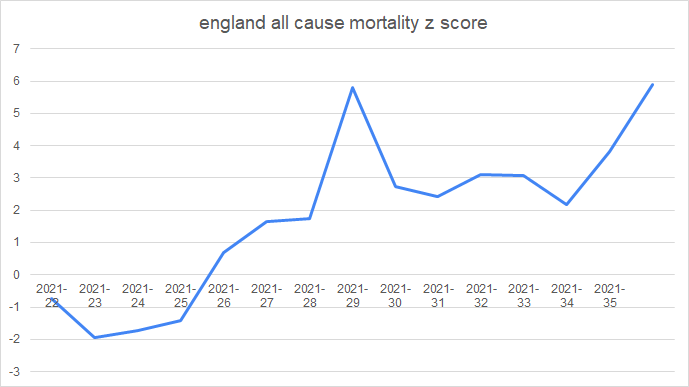
z score for the year can be seen here. starting in wk 22 (may 31) (numbers after the year are weeks)
and given that we know that vaccines DO work to stop deaths in the UK (seemingly in the 50-60% range) it’s even more unexpected that CFR would be rising like this. but it is and the rise in the vaxx rate is not hampering it.
(the precise alignment here is more chart crime than signal, so i’d caution against inferring too much from it)
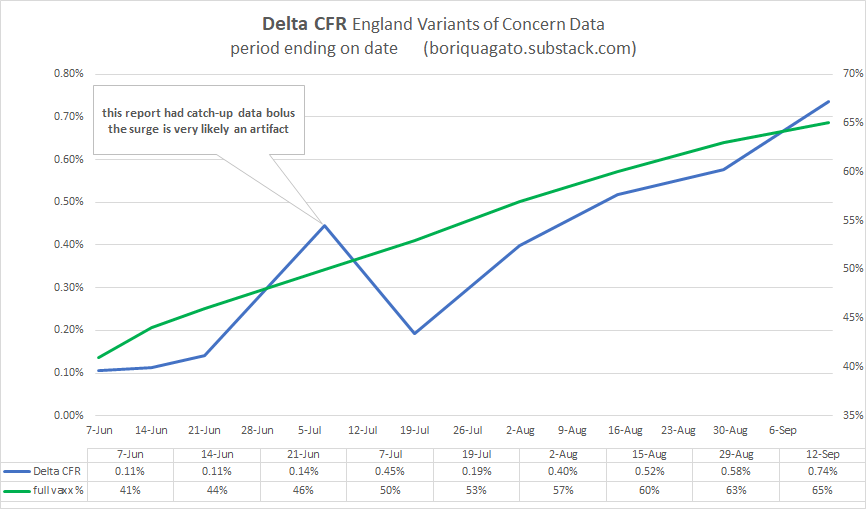
none of this is what one would expect. not remotely. it bucks evolution, it bucks the other variants, and it flies in the face of late stage pandemic dynamics like increase in acquired immunity (which IS sterilizing), depletion of high risk cohorts, improvements in treatment, etc. all these should be pushing CFR down.
instead, water is flowing uphill.
the question is “why?”
the other day, i discussed ADE (antibody dependent enhancement) where antibodies wind up acting as passkeys for a virus to enter cells and also the fetchingly biblically named OAS (original antigenic sin) whereby preferential training to one antibody response leads to its use against new variants of a pathogen and thereby prevents adaptation to more effective modalities.
note that these two phenomena are by no means mutually exclusive and are actually strongly synergistic.
but are they driving this issue?
i do not not think so.
- if they were, we’d be seeing the CFR rise in the vaccinated but not in the unvaccinated and if it were ALL antibodies, we’d be seeing the previously infected getting hit too. but they are not.
- we’d also likely be seeing low or negative vaccine efficacy (VE) for deaths. but we aren’t. it’s clear the vaccinated are doing better.
CFR is (and has been) much better in the vaccinated than the unvaxxed in UK over 50’s (the highest risk category). trends are similar, but absolute values durably disparate.
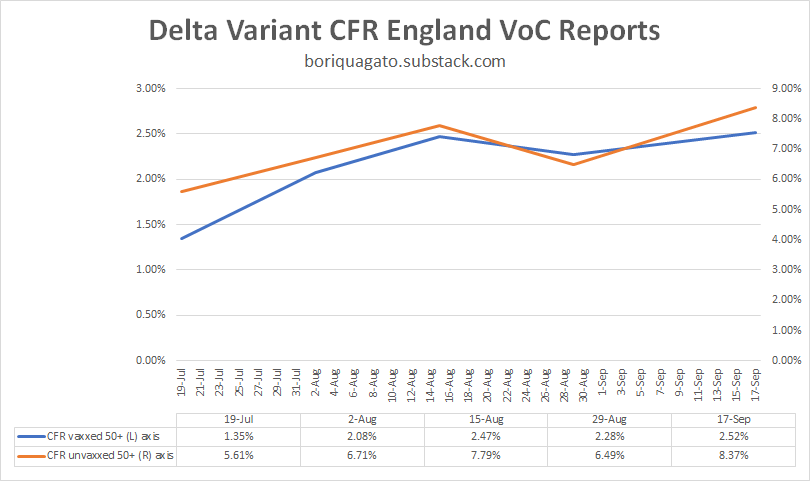
whether and to what extent this is real vaccine efficacy vs cohort bias in a place where 90% of this demographic is vaccinated remains an open issue. it may simply be that only those with the weakest/most compromised immunes systems have not gotten the jab. but this is not really material here.
what IS material is the fact that CFR in the unvaxxed is trending up significantly and so is CFR in the vaxxed. but we’re not seeing many cases of re-infection and almost none of those are serious. this does not look like ADE or OAS as a major driver. if it were, there’s no reason the CFR in the unvaccinated would be rising too.
what this IS consistent with is a variant heating up and getting more and more deadly because it is not checked by normal biological limitations. vaccine mediated evolution (VME) would be very bad news for us.
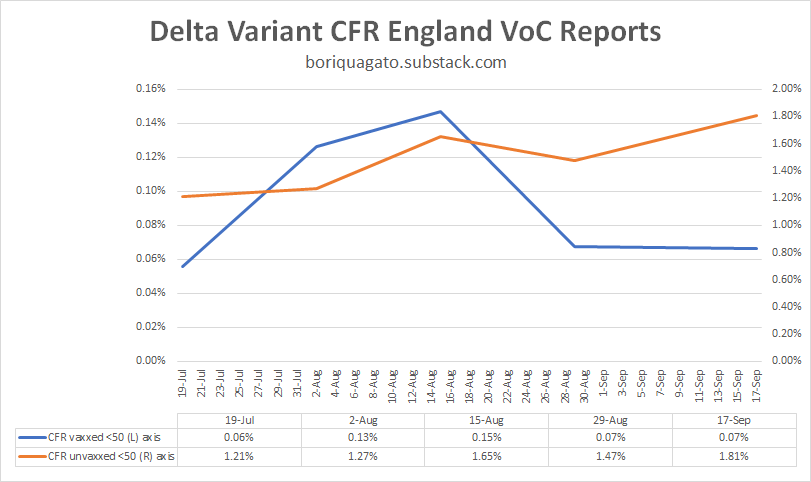
we can see similar in the under 50’s, though the data here is a bit of a mess as during this period, so many very low risk under 50’s (those under 18) got vaccinated that it moved a material risk profile reduction from unvaxxed to vaxxed. i suspect that is why “CFR vaxxed” dropped. it was not vaccines working, it was the vaccinated category being “salted” with large number of the lowest risk folks around. (it also means that group left the unvaxxed, so you get an effect on both)
so i view this data as much lower quality than over 50’s, but it still looks like VME, not ADE or OAS.
this is EXACTLY what leaky vaccines did in chickens.
(read these links. THIS in particular. it’s important.)
such vaccines change the evolutionary gradient for a virus. instead of becoming less virulent/deadly, they can tend the other way because the maladaptiveness of killing the host is mitigated in the vaccinated population. this is what happened with marek’s disease in chickens.
not only is it now more lethal to them than ebola is to humans, making it one of if not THE hottest persistent disease known (killing 100% of unvaxxed birds in 10 days), but, it’s now a disease so hot that an unvaccinated chicken cannot spread it. they die too quickly. only the vaccinated birds spread the nasty strains of mareks. they’re the only ones who live long enough to shed virus.
“Previously, a hot strain was so nasty, it wiped itself out. Now, you keep its host alive with a vaccine, then it can transmit and spread in the world,” Read said. “So it’s got an evolutionary future, which it didn’t have before.”

this is an awful lot of puzzle pieces snapping together and i think we’re really starting to see what this is a picture of.
leaky vaccines that stop severe illness and death but not spread look to be affecting the evolution of the covid 19 virus.
this is an established, predictable, and well supported risk from such vaccines.
this has become my leading hypothesis.
it also explains why we’re seeing such a large rise in deaths relative to cases and deaths and hospitalization overall in so many places. it’s the virus adapting to a stressor we put on it and becoming much more dangerous as a result.
the CFR is a function of the virus, but the virus has become a function of the leaky vaccines.
and it also means the vaccine is protecting no one. yes, it seems to have 50-60% protection against death. but what good is that against a CFR that’s up 300% or more (and rising)? everyone is worse off.

negative VE’s on spread are accelerating cases and this is multiplicative with higher CFR. this is the nightmare scenario and no one is left better off as a result. the CFR among the high risk vaccinated groups is way up too.
everyone is harmed but the brunt is borne by the unvaccinated which perversely winds up looking like better vaccine efficacy. the very fact that vaccines made everyone worse off but spread the misery unevenly makes it look like vaccines are a good idea.
it’s just simple math. if we do something to one group that makes their death rate rise from 1 to 2 per 100 but that also makes the death rate in another group rise from 1 to 4 per 100, that looks like a VE of 50%. in reality, it’s killing 100% more vaxxed people and 300% more of the unvaxxed.
mistaking that gas pedal for the brake and pushing ever harder when you fail to slow would represent an accelerating disaster curve.
that’s the problem with relative measures that ignore absolute changes. you can hide all manner of calamity in such analyses.
it’s still, of course, possible that i’m wrong, but this is looking more and more like it has to be the answer. i can find nothing else fits the facts and the facts themselves are weird enough that “it’s just normal” does not look like a satisfying explanation either and we have enough features here that we can really start testing our puzzle pieces. this one aligns in an AWFUL lot of places.
for something this odd to happen, it takes a truly uncommon exogenous stressor.
i’m just not seeing what else it could be than vaccine mediated selection for hotter variants driving pernicious delta evolution.
so, i’m putting this out to you all to see if you can find some other explanation for what’s going on that fits these facts.
looking forward to the peer review as, honestly, i hope i’m wrong here. this is not an outcome that anyone wants. it’s the nightmare scenario both as a pandemic and as a political horror in the making as if this was an “own-goal”, what would the experts and politicians that pushed this plan not be willing to do to avoid accepting the blame?
because this is career or pharma franchise polonium, and that’s if you’re lucky.
let’s keep at this. one way or the other, we need to know.
the facts do not care about our feelings and epidemiology data is a lousy fabric from which to spin a wubbie to hide under.
we need to get at the truth.
(even if it makes us make a face like this)
Sen. Ron Johnson Shares COVID-19 Data from Public Health England, Refutes “Pandemic of The Unvaccinated” Narrative
The Last Refuge | October 3, 2021
Senator Ron Johnson (R-Wisconsin) used his time on the Senate floor to discuss recently released COVID-19 data from Public Health England in the U.K. [DATA pdf Here]
Ironically, Senator Johnson is forced to use the Senate floor to share the information in an effort to stop government and Big Tech censorship of the discussion. Unlike the rest of the nation, the House and Senate chamber rules create a free speech zone that prohibits anyone from censoring congressional debate and discussion.
Senator Johnson outlines data from the U.K. clearly showing the vaccines offer no protection from the claimed Delta variant. COVID-19 is carried and shed by vaccinated individuals. The subsequent rate of COVID-19 hospitalization and COVID-19 death appears unaffected by the vaccine itself. WATCH:
As Senator Johnson notes: 63% of the deaths in the U.K. during the 7 month period being discussed were among the vaccinated population.
The data Ron Johnson is sharing is available HERE in pdf form
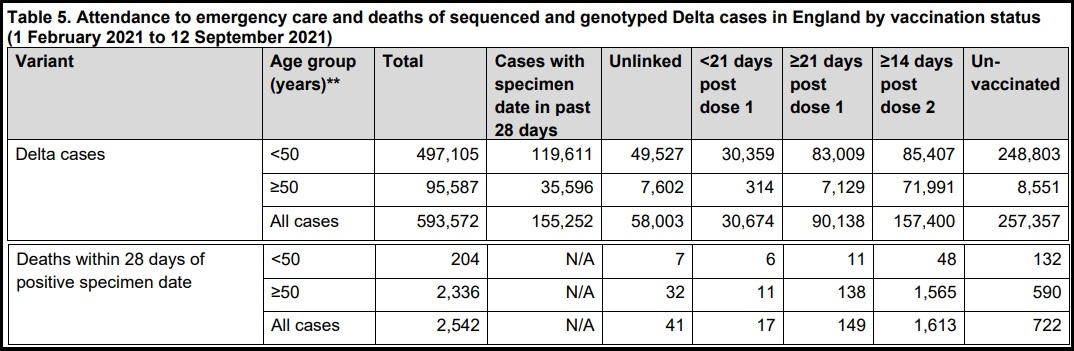
SOURCE: Page 19, 20 – Table 5

Natural Immunity and Covid-19: Twenty-Nine Scientific Studies to Share with Employers, Health Officials, and Politicians
BROWNSTONE INSTITUTE | OCTOBER 10, 2021
From the beginning of the March 2020 lockdowns for the SARS-CoV-2 virus, the subject of natural immunity (also called post-infection immunity) has been neglected. Once the vaccination became widely available, what began with near silence at the beginning turned nearly into a complete blackout of the topic.
Even now, there is an absence of open discussion, presumably in the interests of promoting universal vaccination and required documentation of such vaccination as a condition of participating in public life and even the jobs marketplace. Still, the science exists. Many studies exist. Their authors deserve credit, recognition, and to have their voices heard.
These studies demonstrate what was and is already known: natural immunity for a SARS-type virus is robust, long-lasting, and broadly effective even in the case of mutations, generally more so than vaccines. In fact, a major contribution of 20th-century science has been to expand upon and further elucidate this principle that has been known since the ancient world. Every expert presumably knew this long before the current debates. The effort to pretend otherwise is a scientific scandal of the highest order, especially because the continued neglect of the topic is affecting the rights and freedoms of billions of people.
People who have contracted the virus and recovered deserve recognition. For that matter, people who prefer an exposure risk to the virus in order to gain robust immunity deserve the freedom to make that choice. The realization that natural immunity – which pertains now to perhaps half of the US population and billions around the world – is effective in providing protection should have a dramatic effect on vaccine mandates.
Individuals whose livelihoods and liberties are being deprecated and deleted need access to the scientific literature as it pertains to this virus. They should send a link to this page far and wide. The scientists have not been silent; they just haven’t received the public attention they deserve. The preparation of this list was assisted by links provided by Paul Elias Alexander and Rational Ground’s own cheat sheet on natural immunity, which also includes links to popular articles on the topic.
1. One-year sustained cellular and humoral immunities of COVID-19 convalescents, by Jie Zhang, Hao Lin, Beiwei Ye, Min Zhao, Jianbo Zhan, et al. Clinical Infectious Diseases, October 5, 2021. “SARS-CoV-2-specific IgG antibodies, and also NAb can persist among over 95% COVID-19 convalescents from 6 months to 12 months after disease onset. At least 19/71 (26%) of COVID-19 convalescents (double positive in ELISA and MCLIA) had detectable circulating IgM antibody against SARS-CoV-2 at 12m post-disease onset. Notably, the percentages of convalescents with positive SARS-CoV-2-specific T-cell responses (at least one of the SARS-CoV-2 antigen S1, S2, M and N protein) were 71/76 (93%) and 67/73 (92%) at 6m and 12m, respectively. Furthermore, both antibody and T-cell memory levels of the convalescents were positively associated with their disease severity.”
2. Comparing SARS-CoV-2 natural immunity to vaccine-induced immunity: reinfections versus breakthrough infections, by Sivan Gazit, Roei Shlezinger, Galit Perez, Roni Lotan, Asaf Peretz, Amir Ben-Tov, Dani Cohen, Khitam Muhsen, Gabriel Chodick, Tal Patalon. MedRxiv, August 25, 2021. “Our analysis demonstrates that SARS-CoV-2-naïve vaccinees had a 13.06-fold increased risk for breakthrough infection with the Delta variant compared to those previously infected, when the first event (infection or vaccination) occurred during January and February of 2021. The increased risk was significant for a symptomatic disease as well…. This analysis demonstrated that natural immunity affords longer lasting and stronger protection against infection, symptomatic disease and hospitalization due to the Delta variant of SARS-CoV-2, compared to the BNT162b2 two-dose vaccine-induced immunity.”
3. Shedding of Infectious SARS-CoV-2 Despite Vaccination, by Kasen K. Riemersma, Brittany E. Grogan, Amanda Kita-Yarbro, Gunnar E. Jeppson, David H. O’Connor, Thomas C. Friedrich, Katarina M. Grande, MedRxiv, August 24, 2021. “The SARS-CoV-2 Delta variant might cause high viral loads, is highly transmissible, and contains mutations that confer partial immune escape. Outbreak investigations suggest that vaccinated persons can spread Delta. We compared RT-PCR cycle threshold (Ct) data from 699 swab specimens collected in Wisconsin 29 June through 31 July 2021 and tested with a qualitative assay by a single contract laboratory. Specimens came from residents of 36 counties, most in southern and southeastern Wisconsin, and 81% of cases were not associated with an outbreak. During this time, estimated prevalence of Delta variants in Wisconsin increased from 69% to over 95%. Vaccination status was determined via self-reporting and state immunization records.”
4. Necessity of COVID-19 vaccination in previously infected individuals, by Nabin K. Shrestha, Patrick C. Burke, Amy S. Nowacki, Paul Terpeluk, Steven M. Gordon, MedRxiv, June 5, 2021. “Individuals who have had SARS-CoV-2 infection are unlikely to benefit from COVID-19 vaccination, and vaccines can be safely prioritized to those who have not been infected before.”
5. Large-scale study of antibody titer decay following BNT162b2 mRNA vaccine or SARS-CoV-2 infection, by Ariel Israel, Yotam Shenhar, Ilan Green, Eugene Merzon, Avivit Golan-Cohen, Alejandro A Schäffer, Eytan Ruppin, Shlomo Vinker, Eli Magen. MedRxiv, August 22, 2021. “This study demonstrates individuals who received the Pfizer-BioNTech mRNA vaccine have different kinetics of antibody levels compared to patients who had been infected with the SARS-CoV-2 virus, with higher initial levels but a much faster exponential decrease in the first group.”
6. Discrete Immune Response Signature to SARS-CoV-2 mRNA Vaccination Versus Infection, by Ellie Ivanova, Joseph Devlin, et al. Cell, May 2021. “While both infection and vaccination induced robust innate and adaptive immune responses, our analysis revealed significant qualitative differences between the two types of immune challenges. In COVID-19 patients, immune responses were characterized by a highly augmented interferon response which was largely absent in vaccine recipients.”
7. SARS-CoV-2 infection induces long-lived bone marrow plasma cells in humans, by Jackson S. Turner, Wooseob Kim, Elizaveta Kalaidina, Charles W. Goss, Adriana M. Rauseo, Aaron J. Schmitz, Lena Hansen, Alem Haile, Michael K. Klebert, Iskra Pusic, Jane A. O’Halloran, Rachel M. Presti, Ali H. Ellebedy. Nature, May 24, 2021. “This study sought to determine whether infection with SARS-CoV-2 induces antigen-specific long-lived BMPCs in humans. We detected SARS-CoV-2 S-specific BMPCs in bone marrow aspirates from 15 out of 19 convalescent individuals, and in none from the 11 control participants…. Overall, our results are consistent with SARS-CoV-2 infection eliciting a canonical T-cell-dependent B cell response, in which an early transient burst of extrafollicular plasmablasts generates a wave of serum antibodies that decline relatively quickly. This is followed by more stably maintained levels of serum antibodies that are supported by long-lived BMPCs.”
8. Longitudinal analysis shows durable and broad immune memory after SARS-CoV-2 infection with persisting antibody responses and memory B and T cells, by Kristen W. Cohen, Susanne L. Linderman, Zoe Moodie, Julie Czartoski, Lilin Lai, Grace Mantus, Carson Norwood, Lindsay E. Nyhoff, Venkata Viswanadh Edara, et al. MedRxiv, April 27, 2021. “Ending the COVID-19 pandemic will require long-lived immunity to SARS-CoV-2. We evaluated 254 COVID-19 patients longitudinally from early infection and for eight months thereafter and found a predominant broad-based immune memory response. SARS-CoV-2 spike binding and neutralizing antibodies exhibited a bi-phasic decay with an extended half-life of >200 days suggesting the generation of longer-lived plasma cells. In addition, there was a sustained IgG+ memory B cell response, which bodes well for a rapid antibody response upon virus re-exposure.”
9. Incidence of Severe Acute Respiratory Syndrome Coronavirus-2 infection among previously infected or vaccinated employees, by N Kojima, A Roshani, M Brobeck, A Baca, JD Klausner. MedRxiv, July 8, 2021. “Previous SARS-CoV-2 infection and vaccination for SARS-CoV-2 were associated with decreased risk for infection or re-infection with SARS-CoV-2 in a routinely screened workforce. The was no difference in the infection incidence between vaccinated individuals and individuals with previous infection. Further research is needed to determine whether our results are consistent with the emergence of new SARS-CoV-2 variants.”
10. Single cell profiling of T and B cell repertoires following SARS-CoV-2 mRNA vaccine, by Suhas Sureshchandra, Sloan A. Lewis, Brianna Doratt, Allen Jankeel, Izabela Ibraim, Ilhem Messaoudi. BioRxiv, July 15, 2021. “Interestingly, clonally expanded CD8 T cells were observed in every vaccinee, as observed following natural infection. TCR gene usage, however, was variable, reflecting the diversity of repertoires and MHC polymorphism in the human population. Natural infection induced expansion of larger CD8 T cell clones occupied distinct clusters, likely due to the recognition of a broader set of viral epitopes presented by the virus not seen in the mRNA vaccine. Our study highlights a coordinated adaptive immune response where early CD4 T cell responses facilitate the development of the B cell response and substantial expansion of effector CD8 T cells, together capable of contributing to future recall responses.”
11. mRNA vaccine-induced T cells respond identically to SARS-CoV-2 variants of concern but differ in longevity and homing properties depending on prior infection status, Jason Neidleman, Xiaoyu Luo, Matthew McGregor, Guorui Xie, Victoria Murray, Warner C. Greene, Sulggi A. Lee, Nadia R. Roan. BioRxiv, July 29, 2021. “In infection-naïve individuals, the second dose boosted the quantity and altered the phenotypic properties of SARS-CoV-2-specific T cells, while in convalescents the second dose changed neither. Spike-specific T cells from convalescent vaccinees differed strikingly from those of infection-naïve vaccinees, with phenotypic features suggesting superior long-term persistence and ability to home to the respiratory tract including the nasopharynx. These results provide reassurance that vaccine-elicited T cells respond robustly to emerging viral variants, confirm that convalescents may not need a second vaccine dose, and suggest that vaccinated convalescents may have more persistent nasopharynx-homing SARS-CoV-2-specific T cells compared to their infection-naïve counterparts.”
12. Immunological memory to SARS-CoV-2 assessed for up to 8 months after infection, Jennifer M. Dan, Jose Mateus, Yu Kato, Kathryn M. Hastie, et al., Science, January 6, 2021. “Understanding immune memory to SARS-CoV-2 is critical for improving diagnostics and vaccines, and for assessing the likely future course of the COVID-19 pandemic. We analyzed multiple compartments of circulating immune memory to SARS-CoV-2 in 254 samples from 188 COVID-19 cases, including 43 samples at ≥ 6 months post-infection. IgG to the Spike protein was relatively stable over 6+ months. Spike-specific memory B cells were more abundant at 6 months than at 1 month post symptom onset. SARS-CoV-2-specific CD4+ T cells and CD8+ T cells declined with a half-life of 3-5 months. By studying antibody, memory B cell, CD4+ T cell, and CD8+ T cell memory to SARS-CoV-2 in an integrated manner, we observed that each component of SARS-CoV-2 immune memory exhibited distinct kinetics.”
13. Persistence of neutralizing antibodies a year after SARS-CoV-2 infection, by Anu Haveri, Nina Ekström, Anna Solastie, Camilla Virta, Pamela Österlund, Elina Isosaari, Hanna Nohynek, Arto A. Palmu, Merit Melin. MedRxiv, July 16, 2021. “We assessed the persistence of serum antibodies following wild-type SARS-CoV-2 infection six and twelve months after diagnosis in 367 individuals of whom 13% had severe disease requiring hospitalization. We determined the SARS-CoV-2 spike (S-IgG) and nucleoprotein IgG concentrations and the proportion of subjects with neutralizing antibodies (NAb).”
14. Quantifying the risk of SARS‐CoV‐2 reinfection over time, by Eamon O Murchu, Paula Byrne, Paul G. Carty, et al. Rev Med Virol. 2021. “Reinfection was an uncommon event (absolute rate 0%–1.1%), with no study reporting an increase in the risk of reinfection over time. Only one study esti- mated the population‐level risk of reinfection based on whole genome sequencing in a subset of patients; the estimated risk was low (0.1% [95% CI: 0.08–0.11%]) with no evidence of waning immunity for up to 7 months following primary infection. These data suggest that naturally acquired SARS‐CoV‐2 immunity does not wane for at least 10 months post‐infection. However, the applicability of these studies to new variants or to vaccine‐induced immunity remains uncertain.”
15. SARS-CoV-2 antibody-positivity protects against reinfection for at least seven months with 95% efficacy, by Laith J. Abu-Raddad, Hiam Chemaitelly, Peter Coyle, Joel A. Malek. The Lancet, July 27, 2021. “Reinfection is rare in the young and international population of Qatar. Natural infection appears to elicit strong protection against reinfection with an efficacy ~95% for at least seven months.”
16. Natural immunity against COVID-19 significantly reduces the risk of reinfection: findings from a cohort of sero-survey participants, by Bijaya Kumar Mishra, Debdutta Bhattacharya, Jaya Singh Kshatri, Sanghamitra Pati. MedRxiv, July 19, 2021. “These findings reinforce the strong plausibility that development of antibody following natural infection not only protects against re-infection by the virus to a great extent, but also safeguards against progression to severe COVID-19 disease.”
17. Protection of previous SARS-CoV-2 infection is similar to that of BNT162b2 vaccine protection: A three-month nationwide experience from Israel, by Yair Goldberg, Micha Mandel, Yonatan Woodbridge, Ronen Fluss, Ilya Novikov, Rami Yaari, Arnona Ziv, Laurence Freedman, Amit Huppert, et al.. MedRxiv, April 24, 2021. “Similarly, the overall estimated level of protection from prior SARS-CoV-2 infection for documented infection is 94·8% (CI:[94·4, 95·1]); hospitalization 94·1% (CI:[91·9, 95·7]); and severe illness 96·4% (CI:[92·5, 98·3]). Our results question the need to vaccinate previously-infected individuals.”
18. Immune Memory in Mild COVID-19 Patients and Unexposed Donors Reveals Persistent T Cell Responses After SARS-CoV-2 Infection, by Asgar Ansari, Rakesh Arya, Shilpa Sachan, Someshwar Nath Jha, Anurag Kalia, Anupam Lall, Alessandro Sette, et al. Front Immunol. March 11, 2021. “Using HLA class II predicted peptide megapools, we identified SARS-CoV-2 cross-reactive CD4+ T cells in around 66% of the unexposed individuals. Moreover, we found detectable immune memory in mild COVID-19 patients several months after recovery in the crucial arms of protective adaptive immunity; CD4+ T cells and B cells, with a minimal contribution from CD8+ T cells. Interestingly, the persistent immune memory in COVID-19 patients is predominantly targeted towards the Spike glycoprotein of the SARS-CoV-2. This study provides the evidence of both high magnitude pre-existing and persistent immune memory in Indian population.”
19. Live virus neutralisation testing in convalescent patients and subjects vaccinated against 19A, 20B, 20I/501Y.V1 and 20H/501Y.V2 isolates of SARS-CoV-2, by Claudia Gonzalez, Carla Saade, Antonin Bal, Martine Valette, et al, MedRxiv, May 11, 2021. “ No significant difference was observed between the 20B and 19A isolates for HCWs with mild COVID-19 and critical patients. However, a significant decrease in neutralisation ability was found for 20I/501Y.V1 in comparison with 19A isolate for critical patients and HCWs 6-months post infection. Concerning 20H/501Y.V2, all populations had a significant reduction in neutralising antibody titres in comparison with the 19A isolate. Interestingly, a significant difference in neutralisation capacity was observed for vaccinated HCWs between the two variants whereas it was not significant for the convalescent groups.”
20. Highly functional virus-specific cellular immune response in asymptomatic SARS-CoV-2 infection, by Nina Le Bert, Hannah E. Clapham, Anthony T. Tan, Wan Ni Chia, et al, Journal of Experimental Medicine, March 1, 2021. “Thus, asymptomatic SARS-CoV-2–infected individuals are not characterized by weak antiviral immunity; on the contrary, they mount a highly functional virus-specific cellular immune response.”
21. SARS-CoV-2-specific T cell memory is sustained in COVID-19 convalescent patients for 10 months with successful development of stem cell-like memory T cells, Jae Hyung Jung, Min-Seok Rha, Moa Sa, Hee Kyoung Choi, Ji Hoon Jeon, et al, Nature Communications, June 30, 2021. “In particular, we observe sustained polyfunctionality and proliferation capacity of SARS-CoV-2-specific T cells. Among SARS-CoV-2-specific CD4+ and CD8+ T cells detected by activation-induced markers, the proportion of stem cell-like memory T (TSCM) cells is increased, peaking at approximately 120 DPSO. Development of TSCM cells is confirmed by SARS-CoV-2-specific MHC-I multimer staining. Considering the self-renewal capacity and multipotency of TSCM cells, our data suggest that SARS-CoV-2-specific T cells are long-lasting after recovery from COVID-19, thus support the feasibility of effective vaccination programs as a measure for COVID-19 control.”
22. Antibody Evolution after SARS-CoV-2 mRNA Vaccination, by Alice Cho, Frauke Muecksch, Dennis Schaefer-Babajew, Zijun Wang, et al, BioRxiv, et al, BioRxiv, July 29, 2021. “We conclude that memory antibodies selected over time by natural infection have greater potency and breadth than antibodies elicited by vaccination. These results suggest that boosting vaccinated individuals with currently available mRNA vaccines would produce a quantitative increase in plasma neutralizing activity but not the qualitative advantage against variants obtained by vaccinating convalescent individuals.” Newer version reads: “These results suggest that boosting vaccinated individuals with currently available mRNA vaccines will increase plasma neutralizing activity but may not produce antibodies with breadth equivalent to those obtained by vaccinating convalescent individuals.”
23. Differential effects of the second SARS-CoV-2 mRNA vaccine dose on T cell immunity in naïve and COVID-19 recovered individuals, by Carmen Camara, Daniel Lozano-Ojalvo, Eduardo Lopez-Granados. Et al., BioRxiv, March 27, 2021. “While a two-dose immunization regimen with the BNT162b2 vaccine has been demonstrated to provide a 95% efficacy in naïve individuals, the effects of the second vaccine dose in individuals who have previously recovered from natural SARS-CoV-2 infection has been questioned. Here we characterized SARS-CoV-2 spike-specific humoral and cellular immunity in naïve and previously infected individuals during full BNT162b2 vaccination. Our results demonstrate that the second dose increases both the humoral and cellular immunity in naïve individuals. On the contrary, the second BNT162b2 vaccine dose results in a reduction of cellular immunity in COVID-19 recovered individuals, which suggests that a second dose, according to the current standard regimen of vaccination, may be not necessary in individuals previously infected with SARS-CoV-2.”
24. COVID-19 natural immunity: Scientific Brief. World Health Organization. May 10, 2021. “Available scientific data suggests that in most people immune responses remain robust and protective against reinfection for at least 6-8 months after infection (the longest follow up with strong scientific evidence is currently approximately 8 months). Some variant SARS-CoV-2 viruses with key changes in the spike protein have a reduced susceptibility to neutralization by antibodies in the blood. While neutralizing antibodies mainly target the spike protein, cellular immunity elicited by natural infection also target other viral proteins, which tend to be more conserved across variants than the spike protein.”
25. SARS-CoV-2 re-infection risk in Austria, by Stefan Pilz, Ali Chakeri, John Pa Ioannidis, et al. Eur J Clin Invest. April 2021. “We recorded 40 tentative re-infections in 14 840 COVID-19 survivors of the first wave (0.27%) and 253 581 infections in 8 885 640 individuals of the remaining general population (2.85%) translating into an odds ratio (95% confidence interval) of 0.09 (0.07 to 0.13). We observed a relatively low re-infection rate of SARS-CoV-2 in Austria. Protection against SARS-CoV-2 after natural infection is comparable with the highest available estimates on vaccine efficacies. Further well-designed research on this issue is urgently needed for improving evidence-based decisions on public health measures and vaccination strategies.”
26. Anti-spike antibody response to natural SARS-CoV-2 infection in the general population, by Jia Wei, Philippa C. Matthews, Nicole Stoesser, et al, MedRxiv, July 5, 2021. “We estimated antibody levels associated with protection against reinfection likely last 1.5-2 years on average, with levels associated with protection from severe infection present for several years. These estimates could inform planning for vaccination booster strategies.”
27. SARS-CoV-2 infection rates of antibody-positive compared with antibody-negative health-care workers in England: a large, multicentre, prospective cohort study (SIREN), by Victoria Jane Hall, FFPH, Sarah Foulkes, MSc, Andre Charlett, PhD, Ana Atti, MSc, et al. The Lancet, April 29, 2021. “A previous history of SARS-CoV-2 infection was associated with an 84% lower risk of infection, with median protective effect observed 7 months following primary infection. This time period is the minimum probable effect because seroconversions were not included. This study shows that previous infection with SARS-CoV-2 induces effective immunity to future infections in most individuals.”
28. SARS-CoV-2 Natural Antibody Response Persists for at Least 12 Months in a Nationwide Study From the Faroe Islands, by Maria Skaalum Petersen, Cecilie Bo Hansen, Marnar Fríheim Kristiansen, et al, Open Forum Infectious Diseases, Volume 8, Issue 8, August 2021. “Although the protective role of antibodies is currently unknown, our results show that SARS-CoV-2 antibodies persisted at least 12 months after symptom onset and maybe even longer, indicating that COVID-19-convalescent individuals may be protected from reinfection. Our results represent SARS-CoV-2 antibody immunity in nationwide cohorts in a setting with few undetected cases, and we believe that our results add to the understanding of natural immunity and the expected durability of SARS-CoV-2 vaccine immune responses. Moreover, they can help with public health policy and ongoing strategies for vaccine delivery.
29. Associations of Vaccination and of Prior Infection With Positive PCR Test Results for SARS-CoV-2 in Airline Passengers Arriving in Qatar, by Roberto Bertollini, MD, MPH1; Hiam Chemaitelly, MSc2; Hadi M. Yassine. JAMA Research Letter, June 9, 2021. “Of 9180 individuals with no record of vaccination but with a record of prior infection at least 90 days before the PCR test (group 3), 7694 could be matched to individuals with no record of vaccination or prior infection (group 2), among whom PCR positivity was 1.01% (95% CI, 0.80%-1.26%) and 3.81% (95% CI, 3.39%-4.26%), respectively. The relative risk for PCR positivity was 0.22 (95% CI, 0.17-0.28) for vaccinated individuals and 0.26 (95% CI, 0.21-0.34) for individuals with prior infection compared with no record of vaccination or prior infection.”
Articles in the popular media
Why COVID-19 Vaccines Should Not Be Required for All Americans, by Marty Makary, US News, August 21, 2021
Having SARS-CoV-2 once confers much greater immunity than a vaccine—but vaccination remains vital, by Meredith Wadson, Science, August 26, 2021
Natural infection vs vaccination: Which gives more protection? By David Rosenberg, Israeli National News, July 13, 2021.
Flu survivors still immune after 90 years, by Ed Yong, National Geographic, August 17, 2008.
Rescind Vaccine Mandates: Open Letter to Medical Societies, Hospitals, Clinics, and Other Healthcare Facilities, Association of American Physicians and Surgeons, August 31, 2021.
University Vaccine Mandates Violate Medical Ethics, By Aaron Kheriaty and Gerard V. Bradley, Wall Street Journal, June 14, 2021.
Immunity to the Coronavirus May Last Years, New Data Hint, by Apoorva Mandavilli, New York Times, November 17, 2020.
COVID-19 induces lasting antibody protection, Tamari Bhandara, Washington University School of Medicine, May 24, 2021.
The World Health Organization Oversold the Vaccine and Deprecated Natural Immunity, by Jeffrey Tucker, Brownstone Institute, August 29, 2021.
Why Does the CDC Recognize Natural Immunity for Chicken Pox but Not Covid? By Paul Elias Alexander, Brownstone Institute, September 17, 2021.
Rand Paul and Xavier Becerra Square Off on Natural Immunity, with Devastating Results, by Brownstone Institute, October 2, 2021.
Lockdowns, Mandates, and Natural Immunity: Kulldorff vs. Offit, by Brownstone Institute, October 6, 2021.
Hospitals Should Hire, Not Fire, Nurses with Natural Immunity, by Martin Kulldorff, October 1, 2021.
The Strange Neglect of Natural Immunity, by Jayanta Bhattacharya, Brownstone Institute, July 28, 2021.
The Brownstone Institute for Social and Economic Research is a nonprofit organization conceived of in May 2021 in support of a society that minimizes the role of violence in public life.
Critics love Fauci’s new documentary, but audience hate it and accuse Rotten Tomatoes of ‘hiding’ low score

RT | October 11, 2021
Critics have almost universally praised the new documentary on Dr. Anthony Fauci, but audiences have seemingly hated it, even accusing review aggregator Rotten Tomatoes of trying to hide the movie’s unpopularity.
National Geographic’s ‘Fauci’ has been playing in select cinemas since September 10 and premiered on the Disney Plus streaming service last week. Trailers for the film focus heavily on Fauci and his work combating Covid-19, during which time he has become one of the more controversial figures in American politics.
The film, however, takes a positive look at Fauci and focuses more on tales about the health figure from his family, as well as public figures the infectious disease expert has worked with in the past, such as U2 frontman Bono and former President George W. Bush.
On Rotten Tomatoes, which aggregates reviews from selected critics and then gives a ‘rotten’ or ‘fresh’ score, the film holds a 91% positive rating, based on 30 positive reviews and three negative. The rating from audience members, however, was conspicuously missing from the website until Monday. As of Sunday, only one review, which was negative, had been posted despite the film being out for weeks.
The site was accused of ‘hiding’ the audience score in an effort to spin the movie’s increasingly negative coverage.
On Monday, an audience score did appear, and it showed valleys of difference in opinion from critics to the audience, with users awarding the film a 2% average from over 250 ratings (though it began with a 4% rating that has continually dropped). Despite the average now showing, there is still a lack of actual user reviews on the site, though many users may have chosen to simply drop a rating instead of writing a review.
“Two Americas,” writer Josh Jordan tweeted, including a screenshot of the ‘Tomatometer’ for ‘Fauci’ along with the recently-released comedy special from Dave Chappelle, which has been labeled transphobic by critics, but has been a popular title on Netflix. Critics on Rotten Tomatoes gave the movie a ‘rotten’ score of 33% while audiences awarded a near perfect score.
Fauci critics were quick to mock the film’s near-universal panning from audience members.
The Rotten Tomatoes score for ‘Fauci’ is just the tip of the iceberg when it comes to negative reviews. On IMDB, the movie has a 1.5 rating from over 6000 users.
Trailers for the movie on YouTube haven’t fared much better. One posted by National Geographic has over 100,000 ‘dislikes’ and less than 8000 ‘likes’, as of this writing.
A Disney Plus trailer, on the other hand, has just over 1000 ‘likes’ and over 20,000 ‘dislikes’.
Rotten Tomatoes has been accused of bias in the past, and the company has often chalked up near-universal negative reactions from audiences to trolls’ review-bombing.
In 2019, the company disabled pre-release comments and removed their ‘Want to See’ function – which allowed ratings based on how excited users were for a film – in response to early backlash against franchise pictures accused by critics of going ‘woke’, such as ‘Star Wars: The Last Jedi’ and ‘Captain Marvel’.
Two years before that decision, debate around Rotten Tomatoes and the political influence the audience can have was still a heated debate. Outspoken liberal and comedian Amy Schumer claimed in 2017 that her comedy special ‘The Leather Special’ was review-bombed by the “alt-right” over her comments on Donald Trump and other Republicans (50% critic rating/4% audience). At the time, the site responded again by limiting user functions by removing a five-star system in favor of a positive or negative rating from audiences.
On the opposite end of the spectrum, conservative artists have often pointed to the fact that films aimed at right-leaning audiences often score much lower with critics than audiences as proof the company is more open to ‘certifying’ liberal critics than right-of-center or conservative ones.
Producer John Aglialoro blamed near-universal bad reviews from “hateful” critics on Rotten Tomatoes for his 2011 film ‘Atlas Shrugged: Part I’ struggling to find an audience in theaters (he would go on to produce two sequels covering the last two thirds of Ayn Rand’s influential novel).
Trudeau Bans the Unvaccinated from Leaving the Country and from Earning a Living
The Justice Centre – October 7, 2021
CALGARY: The Justice Centre today responded to the federal government announcement that unvaccinated Canadians will lose their right to move and travel freely within Canada, their right to leave Canada, and their right to earn a living and participate in society without discrimination.
“The government is seeking to have 100% of Canadians injected with the experimental mRNA vaccine, which has not been subjected to any long-term testing on humans,” states lawyer John Carpay, President of the Justice Centre.
With the Canada-U.S. land border closed to non-essential travel, this Covid-19 vaccine travel mandate will effectively prevent unvaccinated people from leaving Canada in any way. In addition to denying unvaccinated Canadians the right to travel by plane or train, the federal government has also announced that federal employees and contractors will lose their jobs unless they participate in the world-wide experiment with new mRNA vaccines.
“We were recently promised, this past summer, that life would go back to normal once 70% of Canadians were injected with mRNA. This high vaccination rate has been achieved but has not stopped the spread of the virus. The new mRNA vaccine also provides no guarantee against the Delta variant,” continues Mr. Carpay.
According to media reports, Prime Minister Trudeau declared that these discriminatory measures against unvaccinated Canadians are needed to keep people “safe,” including children.
“Government data and statistics from every Canadian province, and from countries around the world, tell us that children, teenagers and young adults face no serious threat from Covid, which makes the Prime Minister’s rhetoric about saving children highly misleading,” continues Mr. Carpay.
“Medical reports and scientific studies make it clear that both vaccinated and unvaccinated people spread Covid-19. There is no scientific basis for turning unvaccinated Canadians into second-class citizens,” stated Allison Pejovic, Justice Centre Staff Lawyer.
Currently, Canada’s provincial and federal governments accept two injections as enough to qualify for “full” vaccination. But this may soon change to requiring three, four and more injections to maintain one’s legal status as “fully” vaccinated, as has been demonstrated in Israel and the Netherlands.
“Governments throughout history have used the notion of ‘science’ to support their policies, along with various appeals to public health, safety, security, morality, and so on. No government will violate human rights without putting forward a good-sounding justification, such as the war on terrorism, communism, online hate, drugs, or a nasty virus,” continues Mr. Carpay.
The government’s own data and statistics tell us that Covid is much closer to the annual flu than to the Spanish Flu of 1918. This matters because the entire world was put into a state of panic by the dire predictions of Dr. Neil Ferguson of Imperial College, who claimed in March of 2020 that Covid would be like the Spanish Flu of 1918, killing tens of millions of people.
“Canada’s vaccine passports, and the creation of first-class and second-class citizenship, are founded on Neil Ferguson’s demonstrably false claim that Covid is an unusually deadly killer,” states Mr. Carpay.
“Covid is real. Fear of Covid is wildly exaggerated. Over the past 18 months, government-funded media have been very successful in persuading the majority that vaccine passports (and lockdown policies preceding them) are based on science. When people hear a message thousands of times, they believe it to be true,” continues Mr. Carpay.
“The Justice Centre is profoundly disturbed that these federal mandates will prevent unvaccinated Canadians from leaving the country. Such a mandate is an egregious and unacceptable infringement of Canadians’ constitutionally protected mobility rights. There is no scientific justification for this,” concludes Ms. Pejovic.
These new government restrictions on civil liberties are still announcements at this stage, and no law has been passed by Parliament or by way of cabinet regulation (Order-in-Council). So, no legal challenge is possible at this time. If the government intends to implement these vaccine travel mandates and give them the force of law, these policies can then be challenged in court.
Doctor Says Physicians Are Being “Hunted” For Speaking Out by Press & Medical Boards
Dr Robert Malone branded a “terrorist” by Italian media

By Paul Joseph Watson | Summit News | October 7, 2021
Dr Robert Malone, the inventor of mRNA vaccines, says he was branded a “terrorist” by the media in Italy and warns that physicians who speak out are being “hunted via medical boards and the press.”
“I am going to speak bluntly,” tweeted Malone. “Physicians who speak out are being actively hunted via medical boards and the press. They are trying to deligitimize and pick us off one by one. This is not a conspiracy theory – this is a fact. Please wake up. This is happening globally.”
“I was labeled as a ‘terrorist’ in the Italian press when I was in Rome for the International COVID Summit. My crime? Advocating for early treatment of COVID-19 disease. I suggest that merits a bit of meditation,” he added.
Malone is one of many doctors who have been completely persecuted merely for discussing issues relating to COVID treatments and vaccine side-effects.
He has faced fierce opposition for his assertion that children shouldn’t be given COVID-19 vaccines and has also consistently highlighted concerns over links to myocarditis risk.
Those concerns are now being justified by Finland, Denmark and Sweden halting the Moderna jab for for younger males after reports of cardiovascular side effects.
Despite such concerns being regularly voiced by doctors, the Federation of State Medical Boards announced back in July that it would consider pulling medical licenses of doctors who traffic in “misinformation” about COVID.
In another stunning development, Malone’s IP address was blocked by the New England Journal of Medicine so he couldn’t read studies on their website.
The doctor said he was aware of how to get around the IP block, but called the move a “petty act.”
The War Against Ivermectin Intensifies
By Joel S. Hirschhorn | Principia Scientific | October 11, 2021
The unrelenting opposition to using ivermectin to treat and prevent COVID-19 is stronger than ever. This has resulted from a gigantic increase in demand for IVM by much of the public.
Despite big media tirades against IVM, the truth about its effectiveness (together with failure of COVID vaccines) has reached the public through many articles on alternative news websites and truth-tellers on countless podcasts. Its success has forced Big Pharma to create expensive copies of it.
And in my book Pandemic Blunder I made the case with data that using cheap, safe and effective generics like IVM and hydroxychloroquine would save 80 percent or more of COVID deaths. Esteemed physician Peter McCollough later said 85 percent. For the US, that means over 500,000 lives could have been saved, and globally over four million lives.
Meanwhile, hundreds of thousands of people worldwide have died from COVID vaccines, the failed solution to the pandemic.
Merck, a maker of IVM, is getting much positive press coverage for its forthcoming prescription oral antiviral (molnupiravir). It is designed to replace IVM that they cannot make big money from. FDA will soon give it emergency use authorization because of the emerging clarity that COVID vaccines do NOT work effectively or safely.
That the Washington Post says that what Merck has created is the “first covid-fighting pill” illustrates how awful big media has been in ignoring the proven benefits of the IVM and HCQ generics. And ignoring the many failures of COVID vaccines. In its October 2 front-page story on the new Merck pill, it did not even mention IVM or present any data showing IVM as proven even more effective than the new expensive drug tested on only hundreds of people for a short period.
In contrast, IVM has been used successfully on hundreds of thousands of people to treat and prevent COVID.
Speaking as someone who is using IVM as a prophylactic, here is what I have seen in recent times. Though getting a prescription for it is very difficult and stressful it can be done through a number of websites. But then the battle just begins. Many pharmacies, especially big chain ones, will not fill IVM prescriptions if there is any evidence that it is being used to fight COVID.
And then you will likely discover, as I did, that virtually no pharmacy (typically small community ones) that will fill such prescriptions has any IVM. That’s right. There is a national shortage of IVM because of huge demand in recent months and because US makers have not escalated production.
Probably, millions of vaccine resisters are using IVM, especially those resisting booster shots.
Can you still get it? Yes, and even without a prescription. It will have to come from India, with many makers of IVM. It can take many weeks to get it. But the cost is a tiny fraction of what US pharmacies have been charging when they did have it in stock. Rather than $4 or $5 for a 3 mg pill, you can buy 12 mg pills for way under $1 a pill.
But there is more to the IVM story.
There is absolutely no doubt whatsoever that there is massive medical science data showing absolute reliable data that IVM is safe and effective for both treating and preventing COVID. This is what should be a bold large headline in newspapers if we had honest big media: IVM SAFE AND EFFECTIVE ALTERNATIVE TO COVID VACCINES.
But instead, there is a constant barrage of articles and statements from government agencies asserting IVM should not be used to fight COVID. They argue it is unsafe and ineffective. Both are lies aimed solely at protecting the mass vaccination effort and the profits of big drug companies. And now protecting the new Big Pharma market for antiviral pills.
FDA has issued very strong warnings against using IVM for COVID. Nothing it has said follows the true science and mountains of data supporting safe and effective IVM use. Like other IVM opponents, it has conflated personal IVM use with the use of IVM products designed for animals.
This is even more infuriating. Merck, despite being a maker of IVM discredited its use for COVID by irresponsibly stating, “We do not believe that the data available support the safety and efficacy of ivermectin beyond the doses and populations indicated in the regulatory agency-approved prescribing information.”
Clearly, Merck, Pfizer and other vaccine makers are developing their own oral antivirals to directly compete with the cheap and effective IVM. These antivirals, unlike cheap generic IVM, would be patented so expensive pills could be sold worldwide. They will find some ingenious ways to copy IVM but make enough changes to get patents.
Already, Merck has begun production of its new pill to be taken twice daily for five days. Even more significant: The US government has made an advance purchase of 1.7 million treatment courses for $1.2 billion! That is over $700 per treatment. So much more profitable than making IVM. Forget the billions of dollars spent on vaccines that are injuring and killing many people.
I am confident in predicting that as more and more bad news about the ineffectiveness and dangerous side effects of COVID vaccines become increasingly known to more of the public, the big drug companies will increasingly switch from vaccines to prescription antiviral medicines.
This is what smart corporate business strategic planning is all about. With Merck, it has already started. And FDA, CDC and NIH will go along with this strategic switch.
This will preserve a trillion-dollar market for pharmaceutical companies. How the government and public health establishment weasel word their switch from COVID vaccines to antiviral pills will be a marvelous magical trick to watch. Do you think that they will admit that millions of people worldwide have lost their health and lives from vaccine use? Of course not. Expensive antiviral pills will simply be sold as a better solution.
Be clear about the science explaining why IVM and HCQ have worked. They both (along with zinc) interfere at the earliest stage of COVID infection with viral replication. Stop infection in its tracks. They work as prophylactics for the same reason.
If you keep a modest amount of IVM and HCQ in your body (and take zinc, vitamins C and D, and quercetin) any virus that enters your body can be stopped before major viral replication. The new prescription medicines coming from Merck and other Big Pharma are designed to serve the same function as the cheap generics.
This is the big truth coming to fruition: All the emerging information on COVID vaccine ineffectiveness and dangerous and often lethal side effects is forcing a major strategic shift to antivirals.
Congressman Louie Gohmert has recently made a number of solid observations about IVM:
“Almost 4 billion doses of ivermectin have been prescribed for humans, not horses, over the past 40 years. In fact, the CDC recommends all refugees coming to the U.S. from the Middle East, Asia, North Africa, Latin America, and the Caribbean receive this so-called dangerous horse medicine as a preemptive therapy.
Ivermectin is considered by the World Health Organization (WHO) to be an ‘essential medicine.’
The Department of Homeland Security’s ‘quick reference’ tool on COVID-19 mentioned how this life-saving drug reduced viral shedding duration in a clinical trial.”
“To date, there are at least 63 trials and 31 randomized controlled trials showing benefits to the use of ivermectin to fight COVID-19 prophylactically as well as for early and late-stage treatment. Ivermectin has been shown to inhibit the replication of many viruses, including SARS-CoV-2. It has strong anti-inflammatory properties and prevents transmission of COVID-19 when taken either before or after exposure to the virus.”
“Ivermectin also speeds up recovery and decreases hospitalization and mortality in COVID-19 patients. It has been FDA approved for decades and has very few and mild side effects. It has an average of 160 adverse events reported every year, which indicates ivermectin has a better safety record than several vitamins. In short, there is no humane, logical reason why it should not be widely used to fight against the China Virus should a patient and doctor decide it is appropriate to try in that patient’s case.”
And that small number of adverse events pales in comparison to hundreds of thousands for COVID vaccines.
A new, comprehensive report noted that 63 studies have confirmed the effectiveness of IVM in treating COVID-19. This is a great website to see positive IVM data.
And consider what former Director of Intellectual Property at Gilead Pharmaceuticals, Brian Remy, said about the necessity of implementing Ivermectin. “It is simple – use what works and is most effective – period. Ivermectin used in combination with other therapeutics is a no-brainer and should be the standard of care for COVID-19. Not only would this be good for business and help avoid the criticism and bad PR, and potential civil/criminal liability for censorship, scientific misconduct, etc. for misrepresentation of Ivermectin and other generics, but most importantly it would save countless lives and end the pandemic for good.” Amen.
Want even more positive facts? Consider the India experience. In India’s deadly second pandemic surge, Ivermectin obliterated their crisis. Within weeks after adopting IVM cases were down 90 percent. Those states with more aggressive IVM use were down more dramatically. Daily cases in Goa, Uttarakhand, Uttar Pradesh, and Delhi were down 95, 98, 99, and 99 percent, respectively.
And appreciate this: Dr. Kory and the FLCCC published a narrative review in May 2021, showing the massive effectiveness of IVM against COVID-19 in reducing death and cases. They concluded that it must be adopted globally immediately. Yet big media without respect for public health waged war against IVM. Now it is going crazy in support of the expensive Merck antiviral pill.
To sum up: The IVM story is far from over. We now have a pandemic of the vaccinated. From all over the world the fractions of people said to have died from COVID who were fully vaccinated are very high, often 80 percent. Many people with breakthrough COVID infections die.
Blame those deaths on the vaccines. Big media suppresses all the negative information on the vaccines and all the positive information on IVM.
This double whammy is pure evil. It is designed to pave the way for the new, expensive generation of antiviral pills once the medical and public health establishments backtrack from their vaccine advocacy and coercion.
About the author: Dr. Joel S. Hirschhorn, author of Pandemic Blunder and many articles on the pandemic, worked on health issues for decades. As a full professor at the University of Wisconsin, Madison, he directed a medical research program between the colleges of engineering and medicine. As a senior official at the Congressional Office of Technology Assessment and the National Governors Association, he directed major studies on health-related subjects; he testified at over 50 US Senate and House hearings and authored hundreds of articles and op-ed articles in major newspapers. He has served as an executive volunteer at a major hospital for more than 10 years. He is a member of the Association of American Physicians and Surgeons, and America’s Frontline Doctors.
Cultural Warfare in the 20th Century: How Western Civilization Came Undone
By Matthew Ehret | Strategic Culture Foundation | October 9, 2021
In my last article “Guterres and the Great Reset: How Capitalism Became a Time Bomb”, I made the case that the time bomb justifying a Great Reset of civilization was set into motion over 50 years ago. In that location, we were introduced to a cast of characters surrounding the World Economic Forum and Trilateral Commission who played instrumental roles in bringing about a controlled disintegration of western civilization.
Despite the fact that this un-natural transformation occurred over the dead bodies of great statesmen of the 1960s, a question still lingers: HOW did the western nations… especially the United States, so deeply shaped by a love of freedom, wilfully relinquish its democratic institutions in favor of a new system of supranational governance and de-growth? How did the very people who were targeted for destruction not only let this happen but in some cases even aide and abet the perpetrators?
Epistemological Warfare in America
Here it helps to look to the writings of an imperial grand strategist who is too often championed as a defender of freedom: Aldous Huxley.
While Aldous’ brother Julian was reshaping the global paradigm by re-packaging eugenics under several new costumes post-1945, Aldous’ creative juices were driven entirely by his role as a cultural warrior.
Grand children of Thomas Huxley who was commissioned to re-organize the British Empire in the late 1850s, both grandchildren vigorously embraced the family business working closely with the elite Bloomsbury Group of Bertrand Russell, and John Maynard Keynes between 1914-1937.
Among these creative misanthropes, Lord Bertrand Russell (another celebrated pacifist) had gone far in outlining the sort of bone chilling ideal that Darwinian laws of evolution demanded be humanity’s destiny under a scientifically managed priesthood. In his 1930 Scientific Outlook, Russell stated:
“The scientific rulers will provide one kind of education for ordinary men and women, and another for those who are to become holders of scientific power. Ordinary men and women will be expected to be docile, industrious, punctual, thoughtless, and contented. Of these qualities probably contentment will be considered the most important. In order to produce it, all the researchers of psycho-analysis, behaviourism, and biochemistry will be brought into play…. All the boys and girls will learn from an early age to be what is called `co-operative,’ i.e., to do exactly what everybody is doing. Initiative will be discouraged in these children, and insubordination, without being punished, will be scientifically trained out of them.”
“Except for the one matter of loyalty to the world state and to their own order, members of the governing class will be encouraged to be adventurous, and full of initiative. It will be recognized that it is their business to improve scientific techniques and to keep the manual workers contented by means of continual new amusements”.
Huxley would have Russell’s thesis firmly in mind when he began writing his Brave New World in 1931.
Aldous Goes to Work
Having set up his base of operations in Hollywood in 1937, Aldous lived out his days in the USA writing scripts for Hollywood, exploring psychotropic drugs and coordinating a new cultural movement that would soon overtake the youth growing up amidst the insanity of the Cold War.
In an infamous 1962 speech titled “The Ultimate Revolution”, Aldous Huxley outlined the principles of this new science of governance telling adoring fans amidst the wannabe alphas in the Berkeley auditorium:
“If you are going to control any population for any length of time, you must have some measure of consent. It’s exceedingly difficult to see how pure terrorism can function indefinitely. It can function for a fairly long time, but I think sooner or later you have to bring in an element of persuasion, an element of getting people to consent to what is happening to them. Well, it seems to me that the nature of The Ultimate Revolution with which we are now faced is precisely this: That we are in process of developing a whole series of techniques, which will enable the controlling oligarchy who have always existed and presumably always will exist, to get people, actually, to love their servitude.”
Getting people to love their servitude would be made possible by an array of new techniques outlined in both Huxley’s fiction and non-fiction writings and put into motion by the hard work of CIA-funded laboratories working under secretive umbrella of Allan Dulles’ MK Ultra. Utilizing many techniques pioneered by Nazi psychiatrists in WWII, one of the primary objectives of MK Ultra was to deconstruct the human psyche using a mix of electroshock therapy, psychotropic drugs and other conditioning in order to reconstruct personalities from scratch by professional psychiatrists. As Naomi Klein demonstrated in her famous book The Shock Doctrine, the idea behind MK Ultra was always to extend these behavioral techniques to reprogramming entire groups, societies and nations.
Within Huxley’s Brave New World, psychotropic drugs (soma), cultural norms driven by pre-adolescent sensualism, constant Tinder-esque sexual escapades, the disintegration of family units and hyper-sensualized entertainment (dubbed “feelies”) did the job nicely. Huxley’s dystopia featured a society which had successfully evolved to become a total oligarchy with a scientific priesthood managing the test tube babies bio engineered to become alphas, betas, gammas or the lowly toilet cleaning epsilons reminiscent of the sub-human Morlocks described in H.G. Wells’ earlier Time Machine. In Huxley’s world, family units have long since disintegrated with the nation state and any belief in God.
In his 1958 Brave New World Revisited, Aldous decries the ultimate evil caused by faith in scientific and technological progress as an illusion which cannot provide an escape from the ultimate determining law of humanity: overpopulation. Citing creative breakthroughs in atomic power, space exploration and medicine, Huxley bemoans how each time humanity solves a problem that allows us to save more lives, the species replicates at faster rates bringing about the inevitable Malthusian problems of future wars for resources, diseases and the breeding of the inferior races.
Huxley writes:
“In this second half of the twentieth century we do nothing systematic about our breeding; but in our random and unregulated way we are not only over-populating our planet, we are also, it would seem, making sure that these greater numbers shall be of biologically poorer quality. In the bad old days children with considerable, or even with slight, hereditary defects rarely survived. Today, thanks to sanitation, modern pharmacology and the social conscience, most of the children born with hereditary defects reach maturity and multiply their kind.”
In another speech delivered to the University of California in 1961, Huxley elaborated on this bone chilling plan saying:
“There will be in the next generation or so a pharmacological method of making people love their servitude and producing dictatorship without tears, so to speak. Producing a kind of painless concentration camp for entire societies, so that people will in fact have their liberties taken away from them but will rather enjoy it, because they will be distracted from any desire to rebel – by propaganda, or brainwashing, or brainwashing enhanced by pharmacological methods. And this seems to be the final revolution.”
Huxley knew that if this sort of brainwashing were successfully induced, the ruling oligarchy could ensure that the hedonistic identities of those coming of age within this controlled environment would detach themselves from outdated concepts like nationalism, love of family, or religion, in order to create LSD-driven personal “micro-realities”. Honoring the past and sacrificing for the future became replaced with a new wisdom of “living in the now”.
Huxley was happy to discover that LSD-25 mixed with cannabis, hashish and mescaline was a perfect supplement for soma writing in his 1958 Revisited:
“In LSD-25 (lysergic acid diethylamide) the pharmacologists have recently created another aspect of soma – a perception-improver and vision-producer that is, physiologically speaking, almost costless. This extraordinary drug, which is effective in doses as small as fifty or even twenty-five millionths of a gram, has power (like peyote) to transport people into the other world. In the majority of cases, the other world to which LSD-25 gives access is heavenly; alternatively it may be purgatorial or even infernal. But, positive, or negative, the lysergic acid experience is felt by almost everyone who undergoes it to be profoundly significant and enlightening. In any event, the fact that minds can be changed so radically at so little cost to the body is altogether astonishing.”
During his time in the United States coordinating this new countercultural insurgency, Aldous recruited a young professor of psychiatry named Timothy Leary to his cause. Describing his interaction with Huxley as the two planned this final revolution, Leary wrote in 1983:
“We had run up against the Judeo-Christian commitment to one God, one religion, one reality, that has cursed Europe for centuries and America since our founding days. Drugs that open the mind to multiple realities inevitably lead to a polytheistic view of the universe. We sensed that the time for a new humanist religion based on intelligence, good natured pluralism and scientific paganism had arrived.”
The Creation of Organized Schizophrenia
How the counter-culture was formed in the bowels of such oligarchical psychiatric mental meatgrinders like London’s Tavistock Institute and was applied by psychiatric shock troops strategically placed across all schools, military, unions, corporate boards and government bureaucracies throughout the years is beyond the scope of this present article, although it was explored in a recent video by this author.
What must be kept in mind for our present purposes is that cultural warfare during this intense post WW2 period was full spectrum in nature- taking every major branch of human life into account and extracting all traces of creative reason, universality, Freedom, and Truth anywhere it could be found.
Whether it was in the fine arts and music or whether it was in scientific practice, new dualisms were imposed severing logical thinking from the “pollution” of subjective emotions. Where the arts became shaped increasingly by hedonism liberated from reason (with a “high” post-modern art for the elites and a “low” populist art for the dumb masses), the sciences became governed by the dogmatic faith in cold mathematical sterility governed by “statistics”, entropy, and blind fatalism.
Random paint splashes of CIA-funded artists like Jackson Pollock or the fuzzy squares of Mark Rothko became the new artistic ideal while scientists found themselves trained to think like computers modelling their minds of the methods of Bertrand Russell’s Principia, Norbert Weiner’s Cybernetics and John von Neumann’s Information Theory. Bertrand Russell’s role coordinating the CIA’s Congress for Cultural Freedom should not be lost on anyone.
With the severing of creativity from reason, the minds of those processed by this new cultural field was increasingly shaped by blind rules and axioms enforced by expert consensus rather than personal acts of discovery. Computer modelling thus found itself replacing acts of genuine human thought and within this sterile intellectual climate, a new cult of artificial intelligence began to find fertile soil to grow its perverse roots.
When mixed with heavy doses of imperial wars, assassinations, coups, and the looming threat of nuclear annihilation, the parents of the baby boomers had no clue what evil they were dealing with as their children were absorbed into a new drug/sex-ridden cultural field that no one had ever experienced before. Schizophrenic chaos in the world bred schizophrenic chaos in the culture as increasingly large arrays of youth gave up on reality in order to “tune in, turn on and drop out”.
Throughout the 1960s, patriotic forces around the world rallied to revive the spirit of scientific and technological progress which these neo-Malthusians despised so much. President John F Kennedy attempted to amplify Eisenhower’s Atoms for Peace along with large scale investments into Africa, Asia and Ibero America alongside leaders of the Pan African and Pan Arab world who were committed to ending colonialism and bringing their people into the 21st century.
After Kennedy’s murder, Charles de Gaulle worked with international co-thinkers like Quebec Premier Daniel Johnson, Canadian Prime Minister John Diefenbaker and German Chancellor Adenauer to bring about a coalition of progress which peaked in 1968 with Bobby Kennedy’s inevitable leadership of the United States.
Just as in the period of the late 19th century when a win-win system of international cooperation was threatening to replace the dying Hobbesian system of the British Empire, a dense string of coups, color revolutions and assassinations ensured the crushing of this dynamic as a new age of post-industrialism, Anglo-American imperialism and monetarism was unleashed onto an unsuspecting society.
The Club of Rome Takes the Stage
In this new post-1968 political climate, new scientific conferences were organized in an attempt to impose statistic modelling premised on systems analysis onto biological, economic and especially ecological systems. Extrapolating present trends into the future and disregarding the sorts of non-linear qualitative leaps caused by creative thought allowed this new breed of scientist to “predict” the inevitable crises caused by population growth and the diminishing returns on finite resources.
The iconic study for this new scientific movement was the Club of Rome-commission MIT report Limits to Growth that “predicted”, as Malthus had done two centuries earlier, the point of crisis when population pressures would outstrip nature’s bounty- giving technocrats managing humanity the tools needed to make the proper sacrifices in the present.
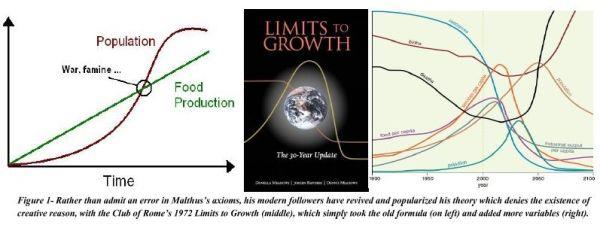
When figures like Mark Carney discuss the “greening of global finance” and placing monetary values upon the reduction of carbon footprints, this is the sick and unscientific foundation of their thinking. Where formerly, humanity valued economic growth via scientific and technological progress (and implicitly the support of increased numbers of people at higher standards of life), the new system of “values” promoted by these misanthropes demanded that profit be tied to the reduction of human activity on the earth.
Club of Rome co-founder Aurelio Peccei, who presented at the inaugural World Economic Forum meetings in Davos, stated:
“The economy and the ecology are inextricably united… A strategy of generating wealth and one of safeguarding this patrimony are opposed. Activities that generate wealth but destroy the natural patrimony even more, create negative value”.
Former President of the World Federation of Mental Health during the high point of MK Ultra, Margaret Mead (wife of MK Ultra controller Gregory Bateson) presided over one such 1975 conference on the environment and atmosphere sponsored by the Club of Rome (this club also being an early sponsor of the World Economic Forum in 1971). Echoing the spirit of Russell and Huxley earlier, Mead called for the creation of a new science of statistics premised on equating pollution to climate change that would become internally consistent and shape the behavior of humanity going into the 21st century. The focus was always population control. In her speech Mead said:
“The unparalleled increase in the human population and its demands for food, energy, and resources is clearly the most important destabilizing influences in the biosphere. We are facing a period when society must make decisions on a planetary scale.”
“What we need from scientists are estimates, presented with sufficient conservatism and plausibility but at the same time as free as possible from internal disagreements that can be exploited by political interests, that will allow us to start building a system of artificial but effective warnings, warnings which will parallel the instincts of animals who flee before the hurricane. [We must] draw from the necessary capacity for sacrifice. It is therefore a statement of major possibilities of danger, which may overtake humankind, on which it is important to concentrate attention”.
Rather than seeing science as a field for optimistic problem solving, this misanthropic cult of elitists demanded that science be redefined around a “new wisdom” of adapting to problems real or imagined. This cynical science of “problematique” (the science of problems) assumed that since all creative discovery caused population growth, the real enemy was found in the naïve optimists who believe it good to promote discoveries. Mead ridiculed those cultural optimists who rejected this cynical view of science saying:
“Those who react against prophets of doom, believing that there is not adequate scientific basis for their melancholy prophecies, [for they] tend to become in turn prophets of paradisiacal impossibilities, guaranteed utopias of technological bliss, or benign interventions on behalf of mankind that are none the less irrational just because they are couched as ‘rational.’ They express a kind of faith in the built-in human instinct for survival, or a faith in some magical technological panacea.”
Using more truthful language, Club of Rome co-founder Sir Alexander King stated in the preface of The First Global Revolution (1991):
“In searching for a common enemy against whom we can unite, we came up with the idea that pollution, the threat of global warming, water shortages, famine and the like, would fit the bill. In their totality and their interactions these phenomena do constitute a common threat which must be confronted by everyone together. But in designating these dangers as the enemy, we fall into the trap, which we have already warned readers about, namely mistaking symptoms for causes. All these dangers are caused by human intervention in natural processes, and it is only through changed attitudes and behaviour that they can be overcome. The real enemy then is humanity itself.”
Today’s world is being pulled by two opposing dynamics.
The prophets of doom who set the time bomb in place half a century ago giddily prepare their utopian Great Reset which demands vast bloodletting as an overpopulated humanity is to be sacrificed by a modern pagan scientific priesthood devoted to Gaia and computer models. On the other hand, the spirit of progress and open system thinking has come alive in the form of the multipolar alliance which premises its planning on an opposing set of assumptions about the nature of humanity, creative thought, value, economics, progress and natural law.
Which future wins out in this battle over humanity will be shaped by the decisions and discoveries we make (or fail to make) in the days ahead.
Featured Video

Death Spikes & Rising Cancer In Our Youth Explained
or go to
Aletho News Archives – Video-Images
From the Archives
Politicians lie
By Mazin Qumsiyeh | Popular Resistance | August 18, 2013
There is no way to say this truth nicely: Politicians lie. That includes Japanese, American, Egyptian, Israeli, and Palestinian politicians! Is there something more common sense than that? Yet, so many citizens around the world believe their own politicians or wistfully acknowledge lies but think it is part of the job needed to run things. They believe even when politicians contradict themselves blatantly. This phenomenon is rather remarkable. It is a dissonance and disconnect from reality that many seem oblivious to. It is very dangerous because it can lead to accepting rationales for going to war. These can be deadly wars that lead to millions of lives lost as happened in what was called World War 1 and WW2. Even when incredible and declassified evidence abound, politicians continue to lie and old mythologies refuse to die. Here are just a few of the countless lies told to us over the past few decades… continue
Blog Roll
 Aletho News
- Ukrainian Soldiers, Potential Mercenaries: Have Gun, Will Travel!
- Burnham’s UN debut… A masterclass in British disinformation
- Iran flights continue despite US aviation sanctions
- Global Tipping Points Lead the World Into a State of Entropy
- The day-after at the White House: USA and Xi Jinping
- The Geopolitical Balance in the Red Sea: The UAE Being Displaced by New Players
- Iraqi resistance group vows to stage airport sit-ins over Iran aerial blockade
- Turkish parliament to review Saudi-Pakistan defense pact next month
- DEATH SPIKES & RISING CANCER IN OUR YOUTH EXPLAINED
- Iran offers Trump deal before US election
- If Americans Knew
- Deconstructing Netanyahu’s pants-on-fire UN rant – Daily Update
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- In UN Speech, Iran’s President Displays Pictures of Children Killed by US, Brings Attention to Israel’s Nuclear Arsenal
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

