Have 1,200 Experts Ever Been Proved Wrong So Quickly?
By Toby Young • The daily Sceptic • August 3, 2021
Guido Fawkes reminds us today that over 1,200 so-called experts signed ‘the Declaration’ – cooked up by the same people behind the John Snow Memorandum – warning of the terrible effect easing coronavirus restrictions on July 19th would have. The Declaration originally took the form of a letter in the Lancet, published on July 7th, in which 120 self-described ‘scientists’, many of them members of Independent SAGE, described ‘Freedom Day’ as “dangerous and premature”. They cited the SAGE modelling showing there would be 100,000 new Covid cases a day if the Government went ahead its plans and set out the dire consequences for Britain and the rest of the world. “We believe the Government is embarking on a dangerous and unethical experiment, and we call on it to pause plans to abandon mitigations on July 19th, 2021,” they wrote.
Two weeks on from ‘Freedom Day’, their predictions aren’t holding up terribly well.
According to Public Health England, the number of new daily cases fell to 21,691 today, another five-week low. So the 1,200 signatories of the Declaration exaggerated the number of daily cases that would follow ‘Freedom Day’ by 500%.
The Lancet letter also predicted that hospital admissions would soar as a result of Boris’s recklessness:
The link between cases and hospital admissions has not been broken, and rising case numbers will inevitably lead to increased hospital admissions, applying further pressure at a time when millions of people are waiting for medical procedures and routine care.
Perhaps they should have thought twice before inserting that word “inevitably” because the latest data shows hospital admissions falling. “Another 731 admissions were recorded by officials on July 30th, the latest date available – down 15% on the week before,” reports MailOnline.
And it wasn’t just these 1,200 ‘experts’ who were sounding the alarm. Let’s not forget that Keir Starmer also described Boris’s plan to ease restrictions as “reckless”.
And, of course, our old friend Neil Ferguson said on July 18th that it was “almost inevitable” that daily cases would climb to 100,000 a day if Boris went ahead with the unlocking the following day and added that “the real question” was whether they would reach 200,000 a day or more and warned of a “significant burden on the healthcare system”. Out by 1000% – which is actually pretty modest by Ferguson’s standards.
As Guido Fawkes says: “Guido can’t remember a time 1,200 so-called experts were proven so wrong in one fell swoop…”
Boris’s decision to go ahead with ‘Freedom Day’ is the first time I can think of in the past 16 months when he’s stuck to his guns in the face of wildly apocalyptic claims from various ‘experts’ about the consequences of “letting it rip” (their phrase for giving us our freedoms back). On every previous occasion, because he’s done exactly as these gloomsters have asked, they haven’t been proved wrong. Admittedly, locking down three times hasn’t stopped the U.K. from having one of the worst Covid death tolls in Europe, and Sweden’s excess deaths in 2020 were lower than ours in spite of not locking down. But the crystal ball gazers have always been able to argue that things would have been so much worse if we hadn’t locked down. Yet this time – finally – Boris ignored their doom-mongering and, as a result, they have been proved spectacularly – and humiliatingly – wrong.
Will this experience stiffen Boris’s backbone the next time he’s prevailed upon by the Government’s scientific advisers, sundry public health experts and the chin-wobblers in the Cabinet to lock down again, which really is inevitable? We can but hope.
Lockdowns, science or voodoo magic? An Interview With Philippe Lemoine
By Noah Carl • The Daily Sceptic • August 3, 2021
Philippe Lemoine is a PhD candidate in philosophy at Cornell University, with a background in computer science. He’s also a blogger, a research fellow at the Centre for the Study of Partisanship and Ideology, and a lockdown sceptic. During the pandemic, he’s written several detailed articles about the efficacy of lockdowns. I interviewed him via email.
On December 4th, you published an article on your blog titled ‘Lockdowns, science and voodoo magic’, which criticised the well-known paper by Flaxman et al. That paper (which has been cited more than 1,300 times) concluded, “major non-pharmaceutical interventions—and lockdowns in particular—have had a large effect on reducing transmission”. Could you briefly summarise your criticisms?
I made two main points against that paper. First, the model assumed that only non-pharmaceutical interventions affected transmission, so any observed reduction in transmission could only be ascribed by the model to non-pharmaceutical interventions. Since in fact transmission went down quickly everywhere during the first wave, the only question was how much of that reduction would the model attribute to each intervention. But the fact that non-pharmaceutical interventions were jointly responsible for the entire reduction in transmission was not something the model inferred from the data, it was assumed at the outset by the authors when they defined the model. A consequence of this fact is that, when they compute a counterfactual scenario in which there weren’t any non-pharmaceutical interventions to estimate how many lives were saved by lockdowns and other restrictions, the authors just assume that cases would have continued to rise until the herd immunity threshold was reached and would only start to go down then. Although the authors did not deem it necessary to reveal this small detail, this meant that, in their counterfactual, more than 95% of the population was already infected by May 3, which is preposterous. Even one year and a half after the beginning of the pandemic, there isn’t a single country where the proportion of the population that has been infected even comes close to such a figure, not even in countries where restrictions were extremely limited. So when the paper finds that non-pharmaceutical interventions in general and lockdowns in particular saved 3 million lives in Europe alone during the first wave, they only reach that conclusion by comparing the actual number of COVID-19 deaths to the number of deaths in a ridiculous scenario where essentially everyone had been infected. Yet this preposterous estimate was taken seriously by the entire scientific establishment and, as you noted, the paper became of the most cited studies on the COVID-19 pandemic.
The second point I made is that, not only was this result based on totally unrealistic assumptions, but the authors failed to disclose a key result that completely undermined their conclusion. As I explained above, the model was bound to attribute the entire reduction in transmission that was observed in Europe during the first wave to non-pharmaceutical interventions, the only question was how much of it would be attributed to each intervention. Their headline result was that, apart from lockdowns, nothing else had any clear effect, which meant that lockdowns were responsible for the overwhelming majority of the 3 million lives that, according to this study, non-pharmaceutical had collectively saved. However, Sweden was included in the study and never locked down, yet only a tiny fraction of its population was infected during the first wave. How is that possible if only lockdowns have a substantial effect on transmission? I knew this made no sense, so I downloaded the code of the paper to reproduce their analysis on my computer and take a closer look at the results. Their model allowed the effect of the last intervention, which happened to be a lockdown everywhere except in Sweden, where it was a ban on public events, in each country to vary. What my analysis of their results showed is that, in order to fit the data, the model had to find that banning public events reduced transmission by ~72.2% in Sweden but only by ~1.6% elsewhere. In other words, according to the model, banning public events had somehow been 45 times more effective in Sweden than anywhere else. Now, unless you believe there are magical anti-pandemic faeries in Sweden that somehow made banning public events 45 times more effective than elsewhere, this obviously never happened. Rather, what this means is that the model was garbage, which in turn means that we have no reason to believe the paper’s headline result that lockdown had a huge effect on transmission. There is a lot more in my piece about that paper, which I methodically demolish, but those are the main points.
Then on March 4th, you published a report for the Centre for the Study of Partisanship and Ideology titled ‘The Case against Lockdowns’. This was followed by an op-ed in the Wall Street Journal titled ‘The Lockdowns Weren’t Worth It’. Could you briefly summarise the case against lockdowns, as you see it?
First, I think it’s impossible to estimate precisely the effects of non-pharmaceutical interventions because too many factors contribute to transmission, and we lack the kind of background knowledge we’d need to be confident that the statistical techniques people use to estimate those effects are reliable, so people who claim to be able to do that are full of it. I just published another piece in which I take a very close look at a study which found that non-pharmaceutical interventions had a substantial effect on the number of cases and deaths in the US during the first wave. This study is far more sophisticated than Flaxman et al.’s paper and, in particular, the authors did not assume that only non-pharmaceutical interventions affect transmission, and tried to model the effect of voluntary behavioral changes. Nevertheless, as I show in my article, when you look at it closely and perform various sensitivity analysis, the conclusions no longer hold. So we have no way to estimate precisely the effects of non-pharmaceutical interventions and we should be honest about this. However, whatever their precise effects, they can’t be huge because otherwise they would be much easier to detect. The contrast with the effect of vaccination is particularly striking in that respect. In the case of vaccination, the effect is so obvious that you can see it on a simple chart, whereas in the case of non-pharmaceutical interventions you have to squint and use very complicated statistical techniques that, although they impress people because they look scientific, we have no reason to think are reliable in this context. Now, if you do a cost-benefit analysis, even if the only costs of lockdowns you take into account is the immediate effect they have on people’s well-being and you make ridiculously optimistic assumptions about how much stringent restrictions reduce transmission, they don’t pass a cost-benefit test. In fact, not only do they fail to pass a cost-benefit test, but it’s not even close. The costs of lockdowns, by which I mean just their immediate effect on well-being, so far outweigh their benefits that one cannot reasonably doubt a more rigorous cost-benefit analysis would reach a different conclusion.
According to some people, claiming that lockdowns don’t have a large effect on the spread of COVID-19 is tantamount to “denying germ theory”. What do you say to those people?
Nobody is denying that transmission occurs during physical interactions, but it doesn’t follow that lockdowns have a large effect on transmission, so people who make this argument simply haven’t thought things through. In theory, lockdowns could even increase transmission, so this argument is very confused. For instance, it could be that, although lockdowns decrease between-household contacts, the effect on transmission at the aggregate level is more than compensated by the increase in within-household contacts they produce. To be clear, I don’t believe this is the case, I’m just saying that it’s a theoretical possibility that obtains in some models, even though nobody denies the germ theory of diseases. There are many possible explanations for why lockdowns don’t result in the very large reduction in transmission that one might have expected. For instance, we don’t expect lockdowns to be equally effective at reducing all types of contacts and, as I just noted, they even increase the frequency of some types of contacts, such as within-household contacts. So it could be that the types of contacts that lockdowns manage to reduce a lot don’t contribute a lot to transmission, while the types of contacts they aren’t very useful for preventing contribute a lot to it. Another important point is that, even in the absence of a lockdown, people change their behavior in response to the pandemic. So it could be that the types of contacts that contribute the most to transmission are the same types of contacts that people tend to reduce voluntarily even in the absence of a lockdown. Anyway, whatever the explanation, it’s pretty clear that lockdowns don’t have a very large effect. It would be very surprising if such a fact were inconsistent with the germ theory of diseases, but fortunately it isn’t. It’s just that people who make this argument are confused. The effectiveness of lockdowns and restrictions in general is an empirical question that cannot be solved by theorizing from the armchair.
Much of your writing about lockdowns has dealt with the deficiencies of epidemiological models. Why have most models done so poorly at predicting the epidemic’s trajectory?
This is a difficult question and I’m not sure what the answer is. I’m very confident that part of the story is that most of those models don’t take into account the kind of voluntary changes of behavior I was just talking about. If your model is based on the assumption that people’s behavior only changes in response to government interventions, it should be no surprise that it performs terribly. But I don’t think it’s the whole story and I increasingly suspect that the fact that models don’t adequately model population structure is another factor. Most epidemiological models that have been used to make projections assume that, withing large age groups, people mix homogeneously. But this is totally unrealistic since, for instance, a 55-year-old is not equally likely to run into any other person in the 50 to 59 age group. Rather, a particular 55-year-old is very likely to have contacts with some people in that age group (such as friends and family), but very unlikely to meet many other people in that age group and has essentially no chance of running into the vast majority of people in that age group. Anyway, nobody really knows why those models perform so terribly at larger scales, but in order to investigate the problem epidemiologists would first have to acknowledge it. Unfortunately, they mostly ignore it and act as if their models had not proven incapable of explaining the data, except in the sense that you can always “explain” any data if you are willing to make enough purely ad hoc hypotheses, so they don’t even get started.
As far as I’m aware, no Western government has published a cost-benefit analysis of lockdowns. Why were these far-reaching policies implemented with so little regard for costs?
As I noted above, any serious cost-benefit analysis would immediately show that lockdowns are not worth it. Yet as you say no Western government has published any to justify their policy. This is particularly surprising when you know that, in most Western governments, the use of cost-benefit analyses is largely institutionalized and the authorities are often required to make one before they can embark on projects as banal as building a bridge. Yet they apparently didn’t feel the need to publish a cost-benefit analysis to justify what are effectively the largest attacks on individual freedoms in the West since the end of World War 2. One interpretation is they realize that, as I noted above, no cost-benefit analysis would ever vindicate lockdowns. But this wouldn’t explain why they are pursuing lockdowns and I don’t believe in that explanation for a second anyway. In a way, if that were really the explanation, I would almost find that reassuring because it would at least imply a level of competence and understanding which I think is entirely lacking from our political leaders. Rather, I think their decisions are the result of a combination of cluelessness not just on their part but also on the part of their advisors and a variety of bad incentives that conspire to create absurd policies, such as the desire not to leave themselves open to the accusation of not having done anything to curb the epidemic. This desire must be strong as they are constantly under pressure from the largely pro-lockdown media to enact more restrictions. In order to answer this unremitting call to “do something”, they do something, even if that’s completely absurd, as long as they have something to show to the people who constantly ask them to “do something”. The idea of measuring the costs of their decisions against their supposed benefits often doesn’t even enter their heads because their decision-process is not governed by rational considerations, but rather by this ungodly combination of emotion, illusion of control, bad incentives and even worse advice.
You’re a Frenchman. Given what we know now, what should Emmanuel Macron have done in March of 2020?
With the benefit of hindsight, I think he should have just told people to try to limit their contacts to reduce the amount of stress on hospitals, but leave them free to make their own choices and focus his efforts on preparing government services to respond as best as possible. I think there are lots of reasons to blame Macron and French officials for their conduct at the beginning of the pandemic, especially for their lack of preparation and their carelessness in the weeks leading up to the explosion of cases in the country, but if we put aside the lies they told repeatedly during that period and since then, they at least had the excuse that we didn’t know much about the virus and how different policies would affect spread. I was in favor of the first lockdown and, while I now think that I was wrong and that I should have predicted lockdowns would become entrenched after we had used them once, it was a genuinely difficult decision because we didn’t know much. But after the first wave there was no longer any excuse and Macron should be judged harshly for keeping us more or less locked down for months after the first wave, even though it was already very clear by that point that restrictions did not make a very large difference to transmission, yet had a very negative impact on the population’s well-being.
The Delta Helter Skelter. When Dire Delta is the excuse for new lockdowns and vaccine mandates, but the truth keeps dribbling out.
Today more news from Israel
By Meryl Nass, MD | August 3, 2021
‘Helter-skelter’ means ‘in chaotic and disorderly haste’.
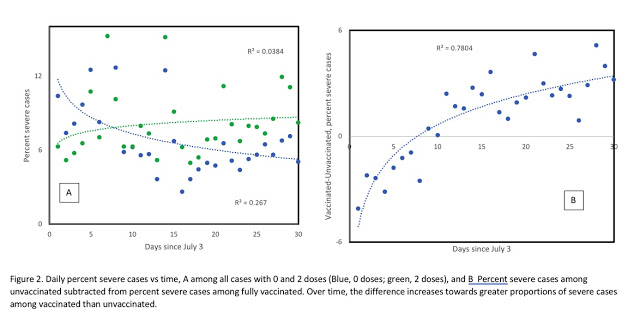
It seems a good descriptor of how public health mouthpieces are dealing with the facts oozing out of the public health muck regarding the Delta variant. Considering their strategy has been to use Delta to impose ever more harsh and unjustifiable Great Reset measures. Not to mention vaccine mandates. But now things look a lot worse than they did in that CDC slide deck. Check out these official graphs from Israel: not only are cases rising equally in the vaccinated as the unvaccinated, but the vaccinated are not being spared severe illness, as claimed by our plucky CDC director.
If nearly all the elderly and high risk Israelis have been vaccinated, then there would be some benefit of vaccination in warding off severe illness… but still, 2/3 of those with severe illness have been doubly vaccinated.
How can you spin this into a justification for vaccine mandates? You can’t. And unless the authorities can prove there is no ADE [antibody-dependent enhancement], getting a booster could just make things a whole lot worse.

[I think we should stop talking about this as a pandemic response. It is a coup, a Reset of the world as we knew it. The so-called responses simply served to terrorize the public and prolong the illness. ]
Med Schools Are Now Denying Biological Sex

By Katie Herzog | Bari Weiss’ Substack | July 27, 2021
During a recent endocrinology course at a top medical school in the University of California system, a professor stopped mid-lecture to apologize for something he’d said at the beginning of class.
“I don’t want you to think that I am in any way trying to imply anything, and if you can summon some generosity to forgive me, I would really appreciate it,” the physician says in a recording provided by a student in the class (whom I’ll call Lauren). “Again, I’m very sorry for that. It was certainly not my intention to offend anyone. The worst thing that I can do as a human being is be offensive.”
His offense: using the term “pregnant women.”
“I said ‘when a woman is pregnant,’ which implies that only women can get pregnant and I most sincerely apologize to all of you.”
It wasn’t the first time Lauren had heard an instructor apologize for using language that, to most Americans, would seem utterly inoffensive. Words like “male” and “female.”
Why would medical school professors apologize for referring to a patient’s biological sex? Because, Lauren explains, in the context of her medical school “acknowledging biological sex can be considered transphobic.”
When sex is acknowledged by her instructors, it’s sometimes portrayed as a social construct, not a biological reality, she says. In a lecture on transgender health, an instructor declared: “Biological sex, sexual orientation, and gender are all constructs. These are all constructs that we have created.”
In other words, some of the country’s top medical students are being taught that humans are not, like other mammals, a species comprising two sexes. The notion of sex, they are learning, is just a man-made creation.
The idea that sex is a social construct may be interesting debate fodder in an anthropology class. But in medicine, the material reality of sex really matters, in part because the refusal to acknowledge sex can have devastating effects on patient outcomes.
In 2019, the New England Journal of Medicine reported the case of a 32-year-old transgender man who went to an ER complaining of abdominal pain. While the patient disclosed he was transgender, his medical records did not. He was simply a man. The triage nurse determined that the patient, who was obese, was in pain because he’d stopped taking a medication meant to relieve hypertension. This was no emergency, she decided. She was wrong: The patient was, in fact, pregnant and in labor. By the time hospital staff realized that, it was too late. The baby was dead. And the patient, despite his own shock at being pregnant, was shattered.
Professors Running Scared of Students
To Dana Beyer, a trans activist in Maryland who is also a retired surgeon, such stories illustrate how vital it is that sex, not just gender identity — how someone perceives their gender — is taken into consideration in medicine. “The practice of medicine is based in scientific reality, which includes sex, but not gender,” Beyer says. “The more honest a patient is with their physician, the better the odds for a positive outcome.”
The denial of sex doesn’t help anyone, perhaps least of all transgender patients who require special treatment. But, Lauren says, instructors who discuss sex risk complaints from their students — which is why, she thinks, many don’t. “I think there’s a small percentage of instructors who are true believers. But most of them are probably just scared of their students,” she says.
And for good reason. Her medical school hosts an online forum in which students correct their instructors for using terms like “male” and “female” or “breastfeed” instead of “chestfeed.” Students can lodge their complaints in real time during lectures. After one class, Lauren says, she heard that a professor was so upset by students calling her out for using “male” and “female” that she started crying.
Then there are the petitions. At the beginning of the year, students circulated a number of petitions designed to, as Lauren puts it, “name and shame” instructors for “wrongspeak.”
One was delivered after a lecture on chromosomal disorders in which the professor used the pronouns “she” and “her” as well as the terms “father” and “son,” all of which, according to the students, are “cisnormative.” After the petition was delivered, the instructor emailed the class, noting that while she had consulted with a member of the school’s LGBTQ Committee prior to the lecture, she was sorry for using such “binary” language. Another petition was delivered after an instructor referred to “a man changing into a woman,” which, according to the students, incorrectly assumed that the trans woman wasn’t always a woman. But, as Lauren points out, “if trans women were born women, why would they need to transition?”
This phenomenon — of students policing teachers; of students being treated as the authorities over and above their teachers — has had consequences.
“Since the petitions were sent out, instructors have been far more proactive about ‘correcting’ their slides in advance or sending out emails to the school listserv if any upcoming material has ‘outdated’ terminology,” Lauren tells me. “At first, compliance is demanded from outside, and eventually the instructors become trained to police their own language proactively.”
In one point in the semester, a faculty member sent out a preemptive email warning students about forthcoming lectures containing language that doesn’t align with the school’s “approach to gender inclusivity and gender/sex antioppression.” That language included the term “premenopausal women.” In the future, the professor promised, this would be updated to “premenopausal people.”
Lauren also says young doctors are being taught to declare their pronouns upon meeting patients and ask for patients’ pronouns in return. This was echoed by a recent graduate of Mount Sinai Medical School in New York. “Everything was about pronouns,” the student said. The student objected to this, thinking most patients would be confused or offended by a doctor asking them what their pronouns were, but she never said so — at least not publicly. “It was impossible to push back without worrying about getting expelled,” she told me.
This hypersensitivity is undermining medical training. And many of these students are likely not even aware that their education is being informed by ideology.
“Take abdominal aortic aneurysms,” Lauren says. “These are four times as likely to occur in males than females, but this very significant difference wasn’t emphasized. I had to look it up, and I don’t have the time to look up the sex predominance for the hundreds of diseases I’m expected to know. I’m not even sure what I’m not being taught, and unless my classmates are as skeptical as I am, they probably aren’t aware either.”
Other conditions that present differently and at different rates in males and females include hernias, rheumatoid arthritis, lupus, multiple sclerosis, and asthma, among many others. Males and females also have different normal ranges for kidney function, which impacts drug dosage. They have different symptoms during heart attacks: males complain of chest pain, while women experience fatigue, dizziness, and indigestion. In other words: biological sex is a hugely important factor in knowing what ails patients and how to properly treat them.
Carole Hooven is the author of T: The Story of Testosterone, the Hormone that Dominates and Divides Us and a professor at Harvard who focuses on behavioral endocrinology. I discussed Lauren’s story with her and Hooven found it deeply troubling. “Today’s students will go on to hold professional positions that give them a great deal of power over others’ bodies and minds. These young people are our future doctors, educators, researchers, statisticians, psychologists. To ignore or downplay the reality of sex and sex-based differences is to perversely handicap our understanding and our ability to increase human health and thriving.”
A former dean of a leading medical school agrees: “I don’t know the extent to which the stories you relate are now widespread in medical education, but to the extent that they are — and I hear some of this is popping up at my own institution — they are a serious departure from the expectation that medical education and practice should be based on science and be free from imposition of ideology and ideology-based intimidation.”
He added: “How male and female members of our species develop, how they differ genetically, anatomically, physiologically, and with respect to diseases and their treatment are foundational to clinical medicine and research. Efforts to erase or diminish these foundations should be unacceptable to responsible professional leaders.”
There is no doubt the rules are changing. According to the American Psychological Association, the terms “natal sex” and “birth sex,” for example, are now considered “disparaging”; the preferred term is “assigned sex at birth.” The National Institutes of Health, the CDC, and Harvard Medical School have all made efforts to divorce sex from medicine and emphasize gender identity.
When Asking Questions Can Destroy Your Career
While it’s unclear if this trend will remain limited to some medical schools, what is perfectly clear is that activism, specifically around issues of sex, gender, and race, is impacting scientific research and progress.
One of the most notorious examples is that of a physician and former associate professor at Brown University, Lisa Littman.
Around 2014, Littman began to notice a sudden uptick in female adolescents in her social network who were coming out as transgender boys. Until recently, the incidence of gender dysphoria was thought to be rare, affecting an estimated one in 10,000 people in the U.S. While the exact number of trans-identifying adolescents (or adults, for that matter) is unknown, in the last decade or so, the number of youth seeking treatment for gender dysphoria has spiked by over 1,000 percent in the U.S.; in the U.K., it’s jumped by 4,000 percent. The largest youth gender clinic in Los Angeles reportedly saw 1,000 patients in 2019. That same clinic, in 2009, saw about 80.
Curious about what was happening, Littman surveyed about 250 parents whose adolescent children had announced they were transgender — after never before exhibiting the symptoms of gender dysphoria. Over 80 percent of cases involved girls; many were part of friend groups in which half or more of the members had come out as trans. Littman coined the term “rapid-onset gender dysphoria” to describe this phenomenon. She posited that it might be a sort of social contagion, not unlike cutting or anorexia, both of which were endemic among teenage girls when I was in high school in the ’90s.
In August 2018, Littman published her results in a paper called “Rapid-Onset Gender Dysphoria in Adolescents and Young Adults: A Study of Parental Reports” in the journal PLOS One. Littman, the journal, and Brown University were pummeled with accusations of transphobia in the press and on social media. In response, the journal announced an investigation into Littman’s work. Several hours later, Brown University issued a press release denouncing the professor’s paper.
Littman’s paper was republished in March 2019 with an amended title and other minor, mostly cosmetic changes. The journal has since confirmed that, while the paper was “corrected,” the original version contained no false information.
But Littman’s career was forever altered. She no longer teaches at Brown. And her contract at the Rhode Island State Health Department wasn’t renewed.
Littman is hardly alone. Trans activists have also targeted Ray Blanchard and Ken Zucker in Toronto, Michael Bailey at Northwestern, and Stephen Gliske at the University of Michigan for publishing findings they deemed transphobic. In a recent case, trans activists shut down research that was to be conducted by UCLA psychiatrist Jamie Feusner, who had hoped to explore the physiological underpinnings of gender dysphoria.
Nor is this limited to academia. Journalists who question the new ideological orthodoxy, like Abigail Shrier and Jesse Singal (with whom I co-host a podcast), have also been smeared for their work. After the American Booksellers Association included Shrier’s book, Irreversible Damage, in a promotional mailing to bookstores, activists went ballistic, prompting the ABA’s CEO to apologize for having done “horrific harm” that “traumatized and endangered members of the trans community” and “caused violence and pain.”
I had a similar experience in 2017 after writing about de-transitioners — people who transition to a different gender and then transition back — for the Seattle alt-weekly The Stranger. After the piece came out, people put up flyers and stickers around Seattle calling me transphobic; someone burned stacks of the newspaper and sent me a video of it. I lost many friends, and later ended up moving out of the city in part because of the turmoil.
But far more concerning than the treatment of journalists chronicling this story is the treatment of patients themselves.
Patients Are Suffering
Julia Mason is a pediatrician in the Portland suburbs who, unlike most doctors I spoke to, allowed me to use her name. Mason explained that she works at a small private practice and her boss is a libertarian. In other words: she won’t get fired for being honest.
Mason has been practicing for over 25 years, but it wasn’t until 2015 that she saw her first transgender patient: a 15-year-old trans boy who Mason referred to a gender clinic, where the patient was prescribed testosterone.
Since that first patient, she says there have been about 10 more requests for referrals to gender clinics. As this number increased, Mason started wondering about the advice her patients are getting at these clinics.
“A 12-year-old female came to see me, and the dad told me that they went to a therapist, and in the first five minutes, the therapist was like, ‘Yep. He’s trans,’” she told me. “And then they went to a pediatric endocrinologist who recommended puberty blockers on the first visit.”
Mason generally avoids prescribing puberty blockers, which inhibit the development of secondary sex characteristics like breasts or facial hair. The reason, she says, is that because there have been no controlled studies on the use of puberty blockers for gender dysphoric youth, the long term effects are still unknown. (In the U.K., a recent review of existing studies found that the quality of the evidence that puberty blockers are effective in relieving gender dysphoria and improving mental health is “very low.”)
In girls, Mason says, blockers inhibit breast development, but “you end up shorter, and the last thing a female who wants to look male needs is to be shorter.” Other side effects may include a loss of bone density, headache, fatigue, joint pain, hot flashes, mood swings and something called “brain fog.” In boys, blockers inhibit penis growth, which can make it harder for them to achieve orgasm and for surgeons to later construct those penises into “neo-vaginas,” a procedure known as vaginoplasty.
Trans activists often claim the effects of puberty blockers are fully reversible, but this remains unproven, and studies show that the overwhelming majority of teens who start on puberty blockers later take cross-sex hormones (testosterone for females and estrogen for males) to complete their transition. The combination of puberty blockers followed by hormones can cause sterility and other health problems, including sexual dysfunction, and the hormones must be taken for life — or until detransition. Little is known about their long-term effects. While the line that blockers are “fully reversible” is oft-repeated by activists and the media, last year, England’s National Health Service back-tracked this unsubstantiated claim on its website.
Mason is one of several doctors who voiced concerns about the fast-tracking of adolescents seeking to transition — and the new normal in the medical establishment, which seems to encourage that fast-tracking.
In 2018, the American Academy of Pediatrics recommended that pediatricians “affirm” their patients’ chosen gender without taking into account mental health, family history, trauma, or fears of puberty. The AAP recommendations say nothing about the many consequences, physical and psychological, of transitioning. So perhaps it is not surprising that surgeons are performing double mastectomies, or “top surgery,” on patients as young as 13.
One leading clinician, Diane Ehrensaft, has said that children as young as three have the cognitive ability to come out as transgender. And the University of California San Francisco Child and Adolescent Gender Center Clinic, where Ehrensaft is the mental health director, has helped kids of that age transition socially.
But not all clinicians have cheered these developments. In a paper responding to the AAP guidelines, James Cantor, a clinical psychologist in Toronto, noted that “every follow-up study of [gender dysphoric] children, without exception, found the same thing: By puberty, the majority of GD children ceased to want to transition.” Other studies of gender-clinic patients, stretching back to the 1970s, have found that 60 to 90 percent of patients eventually grow out of their gender dysphoria; most come out as gay or lesbian.
In an email to me, Cantor said: “The deafening silence from AAP when asked about the evidence allegedly supporting their trans policy is hard to interpret as anything other than their ‘pleading the 5th,’ as you in the U.S. put it.”
Erica Anderson, a clinical psychologist at the UCSF Child and Adolescent Gender Center Clinic and a trans woman herself, also voiced skepticism about the AAP’s approach to would-be transitioners. Unlike Mason, Anderson says withholding puberty blockers from dysphoric children is “cruel.” But she is suspicious of the sharp spike in young people, and especially young women. While she doesn’t like phrases like “rapid-onset gender dysphoria” or “social contagion,” she said something is definitely going on.
“What makes us think that gender is the one exception to peer influence?” she told me. “For 100 years, psychology has acknowledged that adolescence is a time of experimentation and exploration. It’s normal. I’m not alarmed by that. What I’m alarmed by is some medical and psychological professionals rushing kids into taking blockers or hormones.”
Because Anderson has been so vocal, including a recent 60 Minutes appearance in which she discussed detransitioners, she regularly gets calls from frantic parents. She told me she’d gotten off the phone with the parents of a 17-year-old who had announced that they were trans and wanted hormones. “It’s alarming to these parents,” Anderson said.
Anderson isn’t opposed to pediatric transition when patients are properly diagnosed, but she wants to see more individualized care rather than the activist-driven, one-size-fits-all approach. That, however, goes against current AAP guidelines.
Will Science Prevail?
Medicine is not impervious to trends.
“In the 90s, when I was training, everything was about controlling pain,” said a pediatrician in the Midwest who declined to be named for fear of repercussions. “We were taught that it was really hard to become addicted to narcotics. Look where that got us.”
Around the same time, she says, there was a rash of kids being diagnosed with bipolar disorder, something we now know is exceedingly rare in children. Before that, there was the recovered memory craze, multiple personality disorder, and rebirthing therapy, a bizarre treatment for attachment disorders that lead to the deaths of several children in the U.S. So how does this happen?
“Some idea will get picked up by major medical associations that put out reports and their members turn to those instead of the actual literature,” this pediatrician said. “And when you get too far ahead of the research, that’s when you get into trouble. That’s what’s happening now.”
For her part, Lauren, the medical student in California, is both hopeful for the future — and not. “On the one hand, I have this idea that the truth will eventually come out and science will ultimately prevail,” she said.
But the difference between things like rebirthing therapy or multiple personality disorder and the new gender ideology is that the latter is portrayed as a civil rights movement. “It seems virtuous. It seems like the right thing to do,” she said. “So how can you fight against something that’s being marketed as a fight for human rights?”
Why would you institute get tough policies and mandates exactly when the data show the vaccines are very leaky?
By Meryl Nass, MD | August 1, 2021
If your vaccine doesn’t necessarily protect you or me very well, you can’t achieve herd immunity and there is no societal justification to mandate the shot, or squeeze the unvaccinated.
Supposedly, CDC just figured this out. More to the point, the media just started reporting on it, mostly because of a leaked set of CDC slides.
So, it would appear that the only reason to get tough about the shots right now, would be to get them into arms before the public realizes the benefits are rapidly shrinking.
Pfizer applied for a full license, which would be the necessary condition to legally mandate the shots. But a poorly conceived and argued Office of Legal Counsel “opinion” was issued last week. It argues that mandates could be imposed under EUA.
It is unlikely that the feds would issue such a charged and difficult-to-defend document unless they needed it. They only need it if a license is not coming soon. Which suggests FDA has cold feet. Which is something new, considering how they licensed remdesivir. The data they have must be pretty bad. Maybe they are waiting for more data that will look better?
Just speculating…
Booster Jabs To Be Offered To 32 Million Brits From September
By Richie Allen | August 2, 2021
It is being reported this morning that booster jabs will be offered to 32 million Britons from next month. Pharmacies will play a key role in delivering 2.5 million doses a week.
It is hoped that while pharmacies administer the booster jabs, GP surgeries and hospitals can tackle the backlog of patients who are waiting for other treatments. According to The Telegraph :
All adults aged 50 and over, as well as the immuno-suppressed, will be offered the booster jabs.
The campaign could start as soon as Sept 6, which would see the rollout completed by early December if it goes to plan. It is hoped the timetable will leave at least a fortnight for the final people vaccinated to benefit from the jab’s effect before Christmas.
Proposals have been drawn up for the covid-19 vaccine to be co-administered alongside the flu jab with one injection in each arm mooted.
Apparently, ministers are considering giving people a different booster shot to the one they got for their first and second dose. Nobody in the mainstream media is asking any questions about the dangers of giving people two vaccines at once.
Nor is anyone questioning the need for booster jabs. As the flu jab rarely works (Google that statement if you don’t believe me) and they claimed that flu disappeared last year, how can they possibly prepare a jab for it?
As usual, the MSM is deaf dumb and blind. Nothing to see here. I’m beginning to get fairly alarmed. What sort of pressure will be brought to bear on people like me who will continue to tell them to stick their jabs where the sun doesn’t shine?
I don’t expect to travel internationally ever again. My days of going to concerts, the theatre, the cinema and restaurants are over. It’s devastating, but I can cope. However, they won’t stop there. They’ll do everything in their power, short of mandating the jabs, to coerce the rest of us to give in. It’s going to be a long Winter.
Does This Data From Public Health Scotland Show that Vaccine Effectiveness Against Death is Just 46%?
By Will Jones | The Daily Sceptic | August 2, 2021
How well do the vaccines protect from death? The two most recent weekly reports from Public Health Scotland give us death data by vaccination status, and by subtracting one from the other we can work out how many Covid patients died in the week July 9th-15th. The results are shown below.
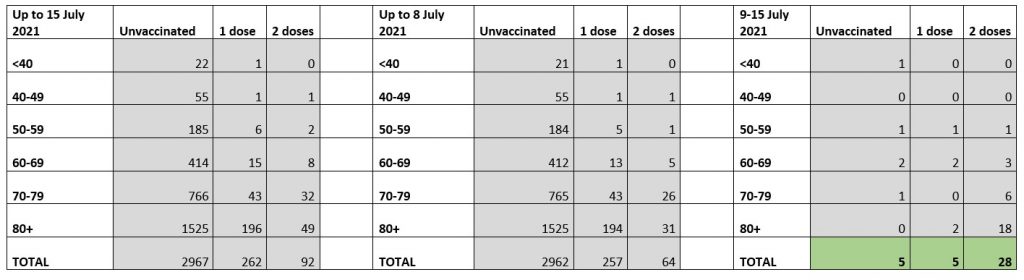
We see that 38 people died with Covid that week, 37 of whom were over 50. Twenty-eight (74%) were fully vaccinated (18 of whom were over 80 and 24 were over 70). Thirty-three (87%) had had at least one dose. Just five (13%) were unvaccinated.
To fully interpret these we need to know how many people were vaccinated in each age group. The problem with obtaining this information is that the official Scottish statistics appear to use the same method as the NHS for estimating vaccine coverage, which gives figures which exceed the likely more accurate estimates of Public Health England by around 5%.
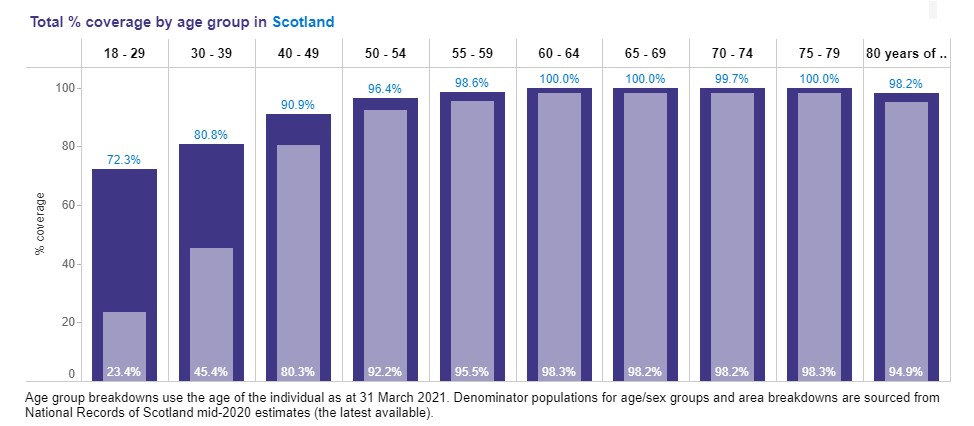
This means the official Scottish figures show extremely high coverage in the over-60s, implausibly hitting 100% in three of the age bands. If we compare this to the latest PHE figures we can see that the corresponding figures in England, taken from the NIMS database, are more like 90-95% than 100%. In fact, the PHE figures are generally around 10 percentage points lower than the PHS figures for the under-70s. That’s a lot.
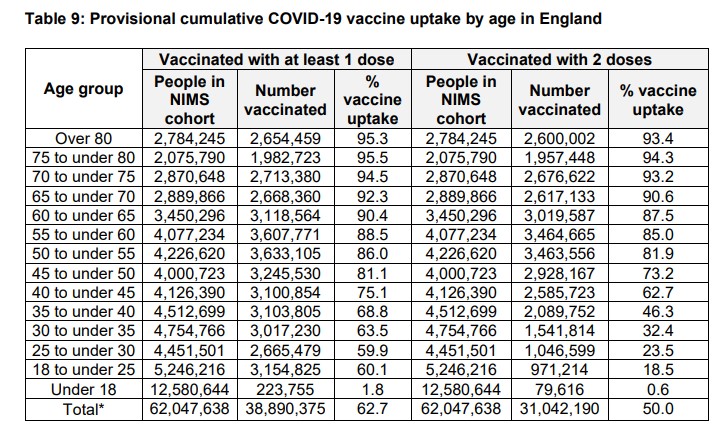
Even if the Scottish really are more keen on vaccination than the English (not unlikely, if only because of the smaller minority ethnic population), we know from the English figures that the NHS estimates appear, as mentioned, to overestimate vaccine coverage by around 5%. I’m going to use a very rough estimate then that around 93% of the over-50s in Scotland have had at least one dose (compared to around 90% in England) and around 91% are fully vaccinated (compared to around 88% in England).
Looking at just the deaths in the over 50s now (so dropping the one in the under 50s), this means that 89% of the deaths in the week 9th-15th July were in the 93% who were vaccinated with at least one dose; 76% of the deaths were in the 91% who were fully vaccinated; and 11% of the deaths were in the 7% who were unvaccinated. This does imply that the vaccines are having some protective effect, but not as much as we might have expected from other sources such as PHE which claim the vaccines are 75-99% effective against death.
Note that these figures suggest that those who had received only one dose were particularly vulnerable to death, as they made up only around 2% of the over-50s population but accounted for 14% of the deaths. Since almost all the over-50s had been offered two doses by this point, this means those who had only one may have had particular reason to avoid the second, such as a bad reaction to the first, or simply being otherwise more vulnerable.
We can use these figures to do a crude estimate of the vaccine effectiveness against death. The four deaths in the seven percent who were unvaccinated imply that if the vaccines have no effect there would have been 57 deaths in total (4/0.07), or 52 deaths in the 91% who were fully vaccinated. There were 28 deaths in the fully vaccinated, meaning the vaccines reduced the expected deaths among the over-50s by 46%. This is 46% overall protection, not protection in addition to protection from infection and hospitalisation, and is considerably below the 75-99% PHE estimate.
This is a very crude estimate, however, as 20 of the deaths were in the over-80s. Once we have more data from the recent surge we may be able to get a better estimate.
That big lie from last week – that 97% of hospitalized and 99.5% of deaths occur in the unvaccinated…
… Proven a lie by CDC’s own slide deck
By Meryl Nass, MD | August 1, 2021
This is from the slide deck leaked a few days ago from CDC:

2020 Was Another Quiet Tornado Season
By Paul Homewood | Not A Lot Of People Know That | August 1, 2021
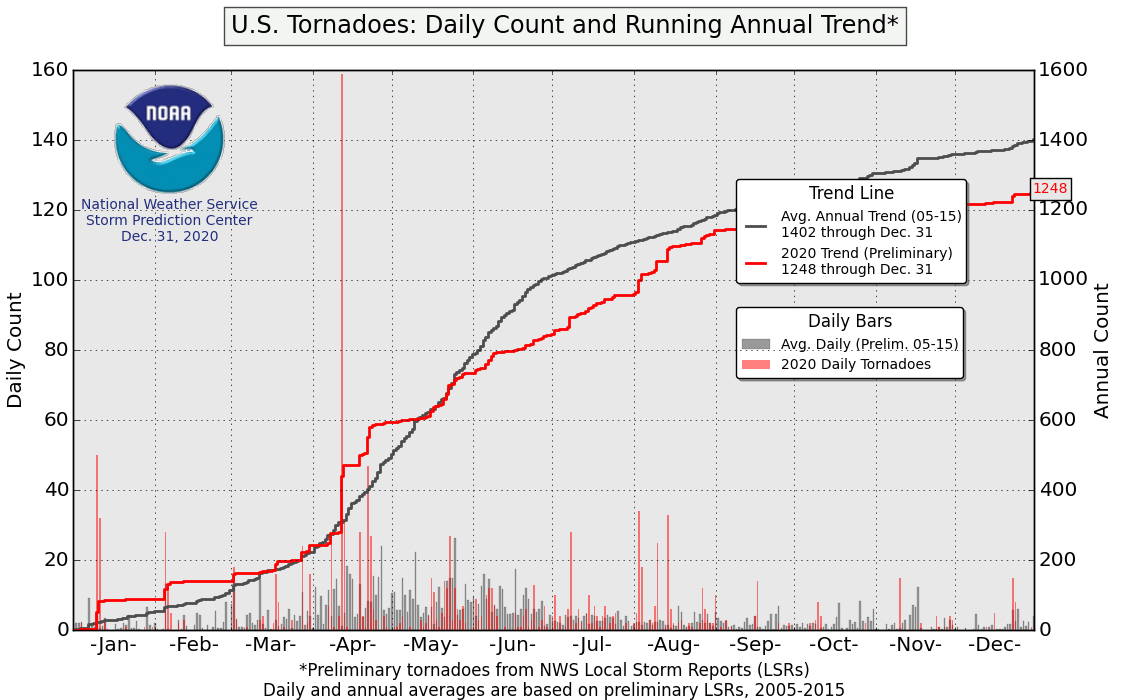
https://www.spc.noaa.gov/wcm/2020/ptorngraph-big.png
According to NOAA’s preliminary data, the number of tornadoes in the US last year was below average.
The full, finalised data has now been released, and it shows another very quiet year for the stronger tornadoes, EF-3s and greater:

Source: NOAA
There were twelve EF-3s, six EF-4s and no EF-5s at all. The number of these violent tornadoes shows a clear and continuing decline since the 1970s.
Particularly significant is the lack of EF-5s, the most powerful tornadoes, packing winds of over 200 mph. The most recent EF-5 was the Moore tornado in May 2013. As there have been none this year so far either, it means that we have now gone more than eight years without an EF-5. This is the longest such period on record, tied with 1999 to 2007.
With the introduction of Doppler radar in the 1990s, increased population, mobile phones and better monitoring systems generally, many tornadoes are now spotted and counted which would have been missed in the past. For that reason, NOAA advise that trends in stronger tornadoes give a better reflection of tornado activity, as these tornadoes would have likely been reported even during the decades before Doppler radar use became widespread and practices resulted in increasing tornado reports.
DR MIKE YEADON, DOCTORS FOR COVID ETHICS, DAY 2, SESSION 2
ArmerLainie@123 | July 31, 2021
Dr Mike Yeadon speaks with Dr Michael Palmer
Featured Video

False Flags and the Dawn of Bioterrorism
or go to
Aletho News Archives – Video-Images
From the Archives
How 1960’s French Nuclear Tests Are Still Claiming Lives in Algeria
Sputnik – 15.02.2018
On February 13, 1960, France carried out its first nuclear test in Algeria’s southern Reggane region. According to official statistics, 17 nuclear tests were carried out in total over the next 6 years. The area remains affected, and local scientists say that radioactive contamination has caused genetic mutations and irreversibly changed the region.
There are no official statistics on the number of victims. The only figures can be found in the records kept by the French representative of the local church, which lists 42,000 victims of nuclear tests. Three years ago, the French Ministry of Defense issued a statement, putting the number at 27,000 people. The victims include French soldiers as well as local Algerians who lived in the surrounding areas. … continue
Blog Roll
 Aletho News
- Using nuclear weapons, the US-Israeli alliance still can’t beat Iran
- Sunset on the Quality of Western Propaganda: Arrival of the Dr Strangelove Moment
- Ukrainian general accused of protecting crime bosses
- US-‘Israel’ alliance faces growing rupture after midterms
- GOP’s Crushing Midterm Loss Could Reshape US Political Landscape – Analyst
- Midterm loss gives Congress power to rein in US war on Iran
- Midterms Were ‘Vote of No Confidence’ in GOP, But Iran Has No Illusions About Democrats – Marandi
- Israeli Soldiers Inadvertently Prove Their Own Genocidal Guilt
- Ukraine arrests woman who exposed Azov battalion’s ‘torture chamber’
- Did Israel lose the midterms?
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago

