Poll: Vaccinated People Far More Likely to Support Risking WWIII Over Ukraine
By Paul Joseph Watson | Summit News | March 22, 2022
A new poll finds that vaccinated people are far more likely to risk World War III over Ukraine by supporting aggressive measures against Russia, while unvaccinated people are more likely to support diplomatic measures.
The revealing results of the survey, which was conducted by EKOS, were published by the Toronto Star.
Canadians who have received “three or more shots” massively supported expanding sanctions (86%), seizing Russians assets (85%), cutting off shipments of Russian oil (81%) and sending additional military equipment to Ukraine (82%). Over half (52%) supported providing Ukraine with fighter jets.
On the flip side, unvaccinated Canadians were far less likely to support measures that would serve to escalate the conflict.
Indeed, a majority of unvaccinated (52%) don’t support any of the measures listed at all.

“The overwhelming majority probably would have said “use diplomacy” if it was an option but the warhawks behind the poll left it off the list,” comments Chris Menahan.
The insightful poll results back up the claims of many, that the COVID narrative was switched for ‘support Ukraine’ virtually overnight by the media and the unthinking masses immediately displayed their ideological subservience.
NPCs were able to seamlessly transfer from zealous support for vaccines and vitriolic denunciations of anyone who didn’t get one, to zealous support for Ukraine and vitriolic denunciations of anyone who didn’t fully swallow the war narrative.
It seems that mass support for whatever ‘current thing’ the political class and culture demands has become a form of cognitive addiction.
Humanity is seemingly dependent on defining itself by lurching from one crisis to another and weaponizing it to ostracize, publicly shame and deplatform dissidents who suggest all may not be as it seems.
Samizdat adds:
The poll also revealed how the two groups feel about the reasons for the conflict, with 88% of vaccinated respondents saying the repression of Russian speakers in the Donbass region does not justify Russia’s actions in Ukraine. The unvaccinated, however, are more split on the question, with 26% saying Russia’s military operation is justified, 27% saying it isn’t, and 35% saying they neither agree nor disagree with it.
The vaccinated also say, almost unanimously (88%), that Russia is guilty of war crimes in Ukraine, while only 32% of unvaxxed respondents agree, and 42% say they don’t believe it is happening at all.
EKOS President Frank Graves said he found the poll results alarming, suggesting that vaccine refusers were “much more sympathetic to Russia,” and that it showcased the “highly corrosive influences of disinformation.”
“This is definitely a new and bluntly insidious force that’s contributing to polarization and disinformation and poor decision-making. And it doesn’t seem to be going away. Things are getting worse,” Graves said, as reported by the Toronto Star.
“I don’t think this is because those people had an ingrained sympathy to the Russians. They’re reading this online, they’re consuming this from the same sources that were giving them the anti-vax stuff.”
CHD Wins Federal District Court Injunction On DC’s Minor Consent for Vaccinations Act
Children’s Health Defense | March 21, 2022
Washington, DC – On March 18, the United States District Court for the District of Columbia issued an order granting a preliminary injunction to prohibit the mayor of the District of Columbia, the D.C. Department of Health and D.C. public schools from enforcing the D.C. Minor Consent for Vaccination Act of 2020 until further order of the court.
“This is a major legal victory for children, parental rights, and informed consent,” said Rolf Hazlehurst, senior staff attorney for Children’s Health Defense (CHD) who argued the case. “Government overreach such as this has dire implications for children’s health and the constitutional rights of citizens.”
The D.C. Minor Consent for Vaccination Act of 2020, allows children eleven years of age and older to consent to vaccinations without their parents’ knowledge or consent. The law specifically targets children whose parents have religious exemptions for their children. The D.C. Act contains several provisions designed to deceive parents and hide the fact that their children have been vaccinated against their parental judgment, authority or religious convictions.
The court order states that the parents “have shown they are likely to succeed on the merits because the District’s law requires providers to hide children’s vaccination status from parents who invoke their religious exemption rights…”
The D.C. Minor Consent Act requires health care providers to falsify records by leaving the child’s school vaccination records “blank.” The doctors may bill the parents’ insurance companies for the vaccines administered to the children against the parents’ written directive. However, to deceive the parents, insurance companies may not send the parents an Explanation of Benefits (EOB).
CHD and Parental Rights Foundation filed a lawsuit in the U.S. District Court for the District of Columbia, seeking a court order to declare the D.C. Minor Consent for Vaccinations Amendment Act of 2020 unconstitutional. Plaintiffs, (Booth, et al.) are four parents of minor children who attend public school in Washington, D.C. Oral arguments were heard on March 3, 2022.
 In the opinion issued on Friday, March 18, the court found the parents likely to succeed on the merits in their arguments that the D.C. Act is unconstitutional for two reasons. First, the D.C. Act is preempted by federal law because it directly contradicts the National Childhood Vaccine Injury Act of 1986. The D.C. Act also violates the right to free exercise of religion guaranteed by the First Amendment to the Constitution.
Hazlehurst argued that the District has created a “pressure-cooker environment, enticing and psychologically manipulating [minor children] to defy their parents and take vaccinations against their parents’ will.”
The Plaintiffs overcame a high legal hurdle that “threatened injury must be certainly impending” as established by the U.S. Supreme Court precedent Clapper v. Amnesty Int’l., in part by the use of a drawing entitled “Peer Pressure,” drawn by one of the plaintiff’s children. The drawing depicts the dilemma children face at school when they do not want to get the COVID vaccine or have been advised by their parents not to take the shot.
“This preliminary injunction is part of ongoing litigation in an extremely important national precedent-setting case,” said Hazlehurst. “The rights of parents to decide what is best for their children’s health is at stake. Government can’t be allowed to make such decisions for minor children.”
Two similar but separate lawsuits, Booth (argued by CHD/Parental Rights Foundation) and Mazer (supported by Informed Consent Action Network), were filed against the D.C. Minor Consent Act. In both Booth and Mazer, the court ruled the plaintiffs have “standing” based on preemption because the D.C. Minor Consent Act conflicts with Congress’ National Childhood Vaccine Injury Act of 1986. In CHD’s Booth case, the court made the additional finding that the plaintiffs are likely to succeed on the merits that the D.C. Minor Consent Act violates the free exercise of religion clause in the First Amendment of the Constitution.
In his ruling, U.S. District Judge Trevor N. McFadden stated, “Removing the law would revert the District to the standard age of consent of 18.” Although the case is not yet final, the preliminary injunction reverts D.C. to the standard age of consent of 18.
###
Children’s Health Defense is a 501(c)(3) non-profit organization. Its mission is to end childhood health epidemics by working aggressively to eliminate harmful exposures, hold those responsible accountable, and establish safeguards to prevent future harm. For more information, visit ChildrensHealthDefense.org.
CHD Links:
a) 1 of 38-page document- PI Memo Opinion DC Minor Case:
https://childrenshealthdefense.org/wp-content/uploads/PI-memo-opinion-DC-minor-case.pdf
b) 1 of 2-page document- Booth Preliminary Injunction Order:
https://childrenshealthdefense.org/wp-content/uploads/Booth-Preliminary-Injunction-Order.pdf
c) 1 of 88-page document- #31 Amended Complaint:
https://childrenshealthdefense.org/wp-content/uploads/31-AMENDED-COMPLAINT-against-All-Defendants-filed-by-SHANITA-WILLIAMS-SHAMEKA-WILLIAMS-VICTOR-M.-BOOTH-JANE-HELLEWELL.-AttachmentsHazlehurst-Rolf.pdf
d) 1 of 131-page document- #31 Appendix:
https://childrenshealthdefense.org/wp-content/uploads/31-1-Appendix.pdf
e) DC Plaintiff Drawing (Exhibit 11 & timestamp included):
https://childrenshealthdefense.org/wp-content/uploads/Exhibit-11-DC-plaintiff-drawing-.png
The Legal Right to Refuse Medical Treatment in the U.S.A.
Ronald B. Standler, Esq. has produced an extraordinary resource that summarizes key legal precedents
By Toby Rogers | March 20, 2022
I want to draw your attention to an extraordinary legal resource that I just discovered (hat tip to the brilliant @blueivyrose_ on Instagram). It’s a document prepared by Massachusetts lawyer Ronald B. Standler titled Legal Right to Refuse Medical Treatment in the U.S.A.
It summarizes all of the key court cases (up until 2012 when it was published) that establish the legal right to refuse medical treatment. He writes,
This essay discusses the history of judicial opinions that hold a mentally competent adult patient has the legal right in the USA to refuse continuing medical treatment for any reason, even if that refusal will hasten his/her death.
His summaries are excellent and really zoom in on the key quotes from the decisions:
Basis for Right to Refuse Treatment
History
The history of the right to refuse medical treatment in the USA is often traced back to two judicial opinions:
• Union Pacific Railway Co. v. Botsford, 141 U.S. 250, 251 (1891) Botsford sued railroad for concussion resulting from alleged negligence of railroad. Railroad wanted surgical examination of her injuries. Request of railroad denied. “No right is held more sacred, or is more carefully guarded by the common law, than the right of every individual to the possession and control of his own person, free from all restraint or interference of others, unless by clear and unquestionable authority of law.”
• Schloendorff v. Society of New York Hospital, 105 N.E. 92, 93 (N.Y. 1914) “Every human being of adult years and sound mind has a right to determine what shall be done with his own body; and a surgeon who performs an operation without his patient’s consent commits an assault, for which he is liable in damages.”
It goes on like this for 57 pages with summaries of key cases, discussion of the major issues raised by each case, and important insights into how the courts have interpreted these precedents over the years.
I imagine this will be a helpful resource for warrior mamas in child custody cases trying to keep their kids from being poisoned by vengeful spouses. I also think it may be helpful for our warrior litigators fighting against a wide range of Pharma fascist policies at the federal, state, and local level.
One bummer about the document is that it is a locked PDF — which makes it difficult to copy and paste. I imagine that clever people will find a way around that.
To recap where we are at in the legal fight against vaccine mandates:
There are four broad sets of legal doctrines that clearly support bodily autonomy:
1. The U.S. Constitution, including the right to freedom of speech and freedom of religion (1st Amendment), the right of people to be secure in their person (4th Amendment), the prohibition on involuntary servitude (13th Amendment), and the right to equal protection under the law (14th Amendment) — all support personal sovereignty.
2. International law and medical norms including:
• The Universal Declaration of Human Rights
• The Nuremberg Code and
• The Declaration of Helsinki
support the absolute right to refuse medical treatment.
3. The mountain of case law cited in Legal Right to Refuse Medical Treatment in the USA shows that the courts have long-supported medical autonomy.
4. The recent Supreme Court decision in the OSHA case and 5 other federal cases establish that federal agencies do not have the power to mandate a medical product.
Meanwhile, all that Team Pharma has going for it is the wrongly decided 1905 Jacobson v. Massachusetts case that is now completely discredited because it was used as a justification for forced sterilization in the Buck v. Bell case in 1927 that was struck down as unconstitutional in 1978 (see Holland, 2010, p. 42, footnote 300). Jacobson is a product of eugenic thinking and it must be repudiated as such and permanently relegated to the dustbin of history.
Were it not for that fact that Pharma pumps billions of dollars into our political and regulatory system every year we would not even be having this conversation because the courts have been clear at least since World War II that bodily autonomy is sacrosanct and that all medical decision reside with the individual — not the state, not doctors, and not the public health system.
The real story here is that progressives just cannot seem to quit eugenics. They loved eugenics in the 1900s when Jacobson was decided. They loved eugenics in the 1920s when Buck v. Bell was decided. And now progressives have once again embraced eugenics with their fanatical support for junk science mRNA shots that are killing and maiming hundreds of thousands of people in the U.S. and around the world.
All decent and sane people must reject eugenics and reject Pharma junk science and return to the bedrock legal principles of individual autonomy and personal sovereignty.
CDC massages its data in order to terrify parents into vaccinating their babies and preschoolers
By Meryl Nass, MD | March 19, 2022
This story is about a particularly vile piece of disinformation CDC issued today to push vaccines on the most vulnerable, those humans who are too tiny to say no.
As I have noted periodically for twenty years, and it was roundly confirmed 4 weeks ago in the NY Times, CDC cherry-picks the data it presents to the public, hiding most of what it has. Then it blames its ‘outdated’ IT systems for the problems. As the NYT noted,
The CDC has received more than $1 billion to modernize its systems, which may help pick up the pace, [CDC spokesperson] Ms. Nordlund said. “We’re working on that,” she said.
CDC is not a public health agency. It is a public propaganda agency that collects a massive amount of data. CDC marshals its massive data library to create presentations to support the current administration’s desired public health policies. CDC also has state of the art PR staff, as well as TV studios, and produces videos, radio spots and a massive number of press releases which are distributed to the media. CDC pays for getting its messages out. As we learned last year, it paid Facebook for messaging, while Facebook donated $millions in advertising back to CDC. Last March, Mark Zuckerberg stated,
We’ve already connected over 2 billion people to authoritative COVID-19 information, and today as access to COVID-19 vaccines expands, we’re going even further and aiming to help bring 50 million people one step closer to getting vaccinated.
While CDC collects data from a much larger sample size, it often, as in this case, only presents part of its dataset, and/or (as in this case) CDC chooses a specific, limited timeframe from which to select its data.
The story that CDC is crafting today is that tiny children, under the age of 5, have been recently hospitalized at extremely high rates due to COVID, and therefore need to be vaccinated as soon as the vaccine is authorized for them.
- Whereas, the true story is that most children have now been exposed to COVID and are therefore already immunized. Multiple studies have revealed that you are at higher risk of a vaccine-induced adverse reaction if you are already immune–but CDC cleverly never mentions that to parents.
- Many other studies show the immunity derived from exposure is much stronger and long-lasting than from vaccination.
- While a new theory gaining ground is that vaccination after infection may actually narrow and weaken the protection derived from COVID immunity.
Pediatric hospitalizations are now CDC’s golden metric, because, since it has been shown the vaccines do not prevent infection or viral transmission, CDC had to stop saying getting vaccinated protects granny, because it doesn’t. But CDC didn’t let that slow them down. They immediately pivoted to creating stories about preschooler hospitalizations, even though they are rare. Let’s see how this is done.
This current issue of the CDC’s in-house journal, the MMWR, not only discusses hospitalization rates, but provides a downloadable poster that it hopes will be placed in pediatric clinics throughout the country. Here it is:

Hospitalizations five times as high! That’s terrible! Omicron must be much more severe for preschoolers than we were led to believe!
But wait a sec. Let’s compare the pediatric Delta wave with the Omicron wave using the data CDC provides.
The Delta wave lasted longer than Omicron but had fewer cases at any one time. Delta’s wave looked those old graphs of ‘flattening the curve,’ while Omicron, being much more contagious, had a much taller peak while its wave ended much more quickly (what you would supposedly see if you didn’t flatten the curve). Actually, Omicron proved that all the gibberish about vaccines and masks and distancing couldn’t flatten Omicron’s curve at all. But I digress. The Delta wave led to about a third more pediatric hospitalizations overall than Omicron in CDC’s dataset (790 vs 572), but they occurred over a longer time frame.
CDC selected their best data for the age group that they hope to immunize soon, as soon as possible after an EUA is issued for them. Here is how CDC attempts to explain its cherrypicking in its article. While all hospitalizations were reviewed up until December 2021, for December and January 2022:
“some sites examined clinical data on a representative sample of hospitalized infants and children.”
Oh, really? You mean CDC pays hospitals to send all their data to COVID-Net, then CDC lets them choose only a ‘representative sample’ during Omicron’s peak to send? I don’t think so. If CDC contracted and paid for a full dataset, believe me it is getting a full dataset. No self-respecting journal editor would let CDC get away with this.
In fact, the CDC had already planned the baby-toddler vaccine campaign for February, but had to postpone it when FDA delayed the authorization process on February 10. It turned out the Pfizer trial supported neither a reduction in cases nor sufficiently high antibody levels in the 2 through 4 year olds to meet the pre-specified titer required.
FDA was probably hoping to issue an EUA anyway. It had an advisory committee meeting scheduled for February 15 to vote on the proposal–until data from vaccinated 5-11 year olds in NY state (about 365,000 of them) showed the vaccine didn’t work, after only a few weeks. Somehow, some way, the lid was kept on this information after it had been presented to FDA and CDC in early February. But the story got out in a preprint and in the NY Times on February 28, which wrote:
The coronavirus vaccine made by Pfizer-BioNTech is much less effective in preventing infection in children ages 5 to 11 years than in older adolescents or adults, according to a large new set of data collected by health officials in New York State — a finding that has deep ramifications for these children and their parents.
After about 6 weeks, protection against hospitalization dropped from a purported 100% to 48% in the 5-11 year olds, and protection against infection had dropped to a miserable 12%.
I don’t think FDA could then deal with pushing vaccine on preschoolers when it wasn’t working in the elementary school kids, whose dose was over 3 times higher. FDA decided to wait until Pfizer waved its magic wand and produced better data. Brook Jackson can explain how that happens.
I’m guessing that in response to the abominable data, CDC spun up its spin doctors, resulting in this March 18, 2022 publication and poster.
Below is Table 1 from CDC’s March 18 paper, published in its very own, non-peer-reviewed journal, the MMWR. Publishing in its own journal lets CDC get its messages out quickly, and protects CDC’s “science” from external reviewers’ criticisms and comments.
Since the beginning of the pandemic, there were a total of 2,562 children aged under 5 years who were hospitalized with COVID in CDC’s COVID-Net catchment groups in 14 states. They comprised CDC’s data collection. Nearly half (44%) of the hospitalized children were under 6 months of age, and would be too young to be vaccinated under the proposed EUA anyway.
The average length of their hospitalizations was 2 days during the Delta wave and 1.5 days during the Omicron wave. Sounds like most kids were not that sick. The deaths were the same for both Delta and Omicron: 0.5% of the children who required hospitalization died during each wave, although CDC carefully fails to tell us about comorbidities in the children who died or required ICU care. While it is true that there were more hospitalizations per week during the omicron peak than during the delta peak, this happened because cases were compressed into a smaller time period for Omicron, since the virus whizzed rapidly through the population. It took longer for Delta to reach its peak and trough, though there were, in total, more pediatric hospitalizations due to Delta than to Omicron.
CDC managed to spin these data into an appearance of terrible danger for little kids: 5 times as many hospitalizations for Omicron than Delta–but only if you parse the data by week rather than by wave. And if you parse the data by total number of cases (the area under the curve for each wave) there were many fewer hospitalizations per the number of cases for Omicron than for Delta. (I have posted a NY Times graph, which uses CDC data for cases, at the bottom of this article.)
Now that the Omicron wave is over, hospitalizations are way way down. CDC isn’t making that part of its message, even though its article came out today and the data have been available for several weeks. Telling us the current risk for kids is close to zero would ruin the narrative.
I have to vent about one more thing. I am really angry about a lie that CDC placed in its blue poster above. It says, “Get vaccinated to help protect yourself and those too young to be vaccinated.” Except, since the vaccine does not prevent you catching the disease nor spreading it, how could vaccination protect those too young to be vaccinated? It doesn’t, and we have known that since at least last October, when Boris Johnson and Rochelle Walensky started to admit it.
Grasping for talking points, despite being able to spin the data however it pleased, I guess CDC just could not shake itself loose from all its lies…
The bottom line is that the vaccine, designed for the original Wuhan virus, doesn’t do the job—and does it even less well in children. Although the safety data in children are very limited due to the tiny numbers enrolled in Pfizer’s trials, we know from older children and adults, using the Vaccine Adverse Event Reporting System, managed by CDC and FDA, that COVID vaccines are the most dangerous vaccines ever used on a mass scale.
By giving manufacturers a vast liability shield, the federal government has incentivized them to rush out their products and provide only the most minimal safety testing—because the way the law is writtten, they can only be charged with willful misconduct if they knew in advance of their products’ flaws.
Parents whose children are injured by experimental COVID vaccines will never forgive themselves. Please don’t be one of them.


More evidence on Covid vaccine deaths
By Guy Hatchard | TCW Defending Freedom | March 20, 2022
The writer is in New Zealand
A NEW paper at an open access platform (OSF) about German excess all-cause deaths adds significantly to the growing body of evidence being reported around the world.
There are a number of interesting points in the German data which is broken down by age. During 2020, Covid infections peaked but all-cause mortality was not seriously elevated, whereas during 2021 while the mRNA vaccine was being rolled out, German all-cause deaths were elevated for the 15-79 age range.

This is not an isolated statistic. All-cause deaths among working age populations are increasing. Official US all-cause death data paints a depressingly similar picture to the German and New Zealand stats. Commercial insurance data confirms this.
A comparison of 15-79 German all-cause deaths with vaccinations by month shows how vaccination numbers mirrored deaths. It also shows how an increase in all-cause deaths occurred when boosters were rolled out. The relationship is similar to the observed excess all-cause deaths in NZ.

The significance of this data cannot be overestimated. UKHSA reports that the average age of people dying from Covid is 82.9 years, higher than the average UK life expectancy. Therefore all-cause deaths among the 15-79 year age bracket are not expected to increase significantly as a result of Covid infections. The implications of the observed rises across multiple countries are very disturbing. Most studies of long-term outcomes following Covid infection are not differentiating between subjects who have been vaccinated and those who are not. This allows vaccine advocates, pharmaceutical manufacturers, and governments to continue to blame adverse outcomes including deaths on Covid infection alone or chance events without considering the adverse effect of mRNA vaccination, whose long-term impacts may be even larger. The German data supports causal attribution of increases in all-cause deaths to the effects of mRNA Covid vaccination.
Some are beginning to see the light. Last week John Campbell, respected provaxx YouTube Covid commentator from the UK with 2million followers, changed sides. He read out the key points from the court-ordered Pfizer release of adverse effects documents, threw up his hands in despair, and expressed anger at how we have all been misled from the start. A list of 1,223 deaths and 42,086 adverse events across broad categories of serious illness led to his censure.
New Zealand carries on regardless
At a press conference on Thursday, Northern Region Health Coordination Centre (NRHCC) chief clinical officer Dr Andrew Old said only a third of the 1,000 people currently in hospital with Covid-19 were there due to the effects of the virus. He did not provide any details about how many of this third were vaccinated and how many unvaccinated. He didn’t provide any data on how many of the modest number of deaths were ‘with Covid’ and how many were ‘because of Covid’. So all bets are off when it comes to analysing NZ data. Yet Dr Ashley Bloomfield, the NZ Director General of Health, who was interviewed by Mike Hosking yesterday morning, said the 1,000 people in hospital would not be there if it wasn’t for Covid. Hosking had to correct him.
This means for the last few weeks we have been subjected to a meaningless psychobabble of palpably false Covid statistics designed by the Ministry of Health to contain us in a state of constant fear. What the government hasn’t really talked about is their failure to upgrade the emergency departments of NZ hospitals (they’ve had two years to prepare), instead spending 64billion dollars of borrowed money promoting an ineffective Covid vaccination programme. The NZ Herald reports our hospital system is in crisis, strained to breaking point. The statistics show that the hospitals are overwhelmed with vaccinated Covid patients, but you wouldn’t know it unless you moved beyond government propaganda.
Despite the mounting evidence of ineffectiveness and serious harm, the focus of government and the health system is still saturation advertising proclaiming the safety and effectiveness of mRNA vaccination. Meanwhile thousands of people in and out of hospital with serious illness continue to be under-resourced and in some cases neglected.
Excess all-cause death is not a statistic that can be ignored. Dr Ashley Bloomfield says it is not necessary to institute mandatory reporting of adverse events following vaccination. What planet is he on? We need an immediate end to mandates, proper assessment of adverse effects, and adequate compensation and treatment for those affected.
Guy Hatchard PhD is a former senior manager at Genetic ID, a global food testing and certification company. He lives in New Zealand.
483 More Deaths After COVID Vaccines Reported to VAERS, as Pfizer and Moderna Push for More Boosters
By Megan Redshaw | The Defender | March 18, 2022
The Centers for Disease Control and Prevention (CDC) today released new data showing a total of 1,183,495 reports of adverse events following COVID-19 vaccines were submitted between Dec. 14, 2020, and March 11, 2022, to the Vaccine Adverse Event Reporting System (VAERS). VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S.
The data included a total of 25,641 reports of deaths — an increase of 483 over the previous week — and 208,209 reports of serious injuries, including deaths, during the same time period — up 4,321 compared with the previous week.
Excluding “foreign reports” to VAERS, 788,624 adverse events, including 11,728 deaths and 76,231 serious injuries, were reported in the U.S. between Dec. 14, 2020, and March 11, 2022.
Foreign reports are reports foreign subsidiaries send to U.S. vaccine manufacturers. Under U.S. Food and Drug Administration (FDA) regulations, if a manufacturer is notified of a foreign case report that describes an event that is both serious and does not appear on the product’s labeling, the manufacturer is required to submit the report to VAERS.
Of the 11,728 U.S. deaths reported as of March 11, 17% occurred within 24 hours of vaccination, 22% occurred within 48 hours of vaccination and 60% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 556 million COVID vaccine doses had been administered as of March 11, including 328 million doses of Pfizer, 209 million doses of Moderna and 19 million doses of Johnson & Johnson (J&J).
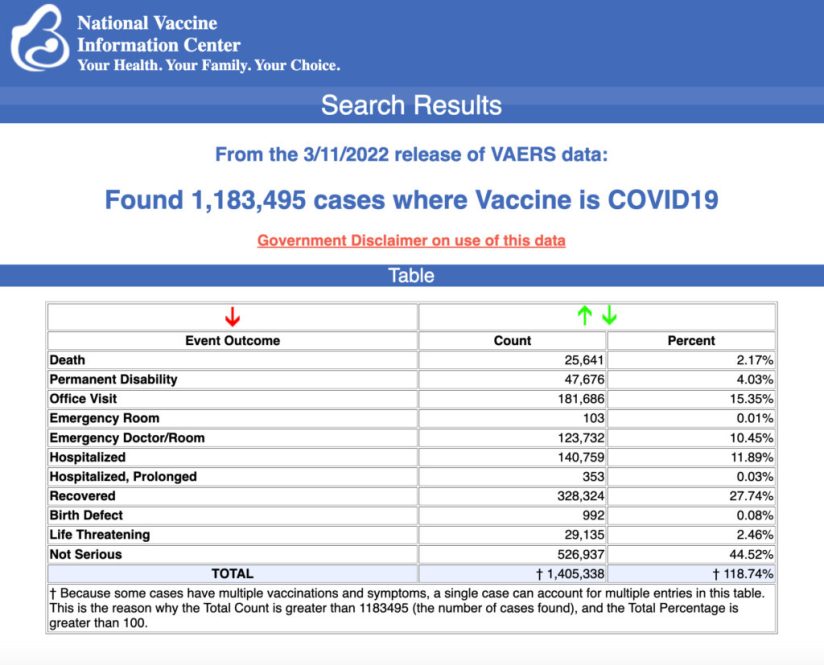
Every Friday, VAERS publishes vaccine injury reports received as of a specified date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed.
Historically, VAERS has been shown to report only 1% of actual vaccine adverse events.
U.S. VAERS data from Dec. 14, 2020, to March 11, 2022, for 5- to 11-year-olds show:
- 9,161 adverse events, including 217 rated as serious and 5 reported deaths.
The most recent death involves a 7-year-old boy (VAERS I.D. 2152560) from Washington who died 13 days after receiving his first dose of Pfizer’s COVID vaccine when he went into shock and suffered cardiac arrest. He was unable to be resuscitated and died in the emergency department.
- 17 reports of myocarditis and pericarditis (heart inflammation).
The CDC uses a narrowed case definition of “myocarditis,” which excludes cases of cardiac arrest, ischemic strokes and deaths due to heart problems that occur before one has the chance to go to the emergency department.
- 34 reports of blood clotting disorders.
U.S. VAERS data from Dec. 14, 2020, to March 11, 2022, for 12- to 17-year-olds show:
- 30,295 adverse events, including 1,744 rated as serious and 42 reported deaths.
The most recent deaths involve a 17-year-old boy (VAERS I.D. 2171083) from Illinois with Duchenne muscular dystrophy who died from cardiac arrest after receiving his second dose of Pfizer’s COVID vaccine, and 14-year-old boy from Guam (VAERS I.D. 2157944) who died one week after his first dose of Pfizer when he suddenly committed suicide.
The boy’s VAERS report states:
“Sudden suicide one week after the vaccine. Patient was a perfectly happy child. After the vaccine, he became much more tired and achy and lost interest in doing his sports. One week later, without any warning, he hung himself.”
- 68 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 96% of cases attributed to Pfizer’s vaccine.
- 646 reports of myocarditis and pericarditis, with 634 cases attributed to Pfizer’s vaccine.
- 162 reports of blood clotting disorders, with all cases attributed to Pfizer.
U.S. VAERS data from Dec. 14, 2020, to March 11, 2022, for all age groups combined, show:
- 20% of deaths were related to cardiac disorders.
- 54% of those who died were male, 41% were female and the remaining death reports did not include the gender of the deceased.
- The average age of death was 72.7.
- As of March 11, 5,250 pregnant women reported adverse events related to COVID vaccines, including 1,668 reports of miscarriage or premature birth.
- Of the 3,613 cases of Bell’s Palsy reported, 51% were attributed to Pfizer vaccinations, 40% to Moderna and 8% to J&J.
- 863 reports of Guillain-Barré syndrome, with 41% of cases attributed to Pfizer, 30% to Moderna and 28% to J&J.
- 2,363 reports of anaphylaxis where the reaction was life-threatening, required treatment or resulted in death.
- 1,683 reports of myocardial infarction.
- 13,512 reports of blood-clotting disorders in the U.S. Of those, 6,034 reports were attributed to Pfizer, 4,818 reports to Moderna and 2,617 reports to J&J.
- 4,045 cases of myocarditis and pericarditis with 2,483 cases attributed to Pfizer, 1,377 cases to Moderna and 175 cases to J&J’s COVID vaccine.
Moderna asks FDA to authorize 4th dose for adults 18 and up
Moderna on Thursday asked the FDA to amend Emergency Use Authorization (EUA) of its COVID vaccine to include a fourth dose for adults 18 and older.
According to The Associated Press, the request is broader than Pfizer’s. Pfizer earlier this week asked the agency to authorize a fourth dose of its COVID vaccine for adults 65 and older.
In a press release, Moderna said the request to include adults over 18 was made “to provide flexibility for the U.S. Centers for Disease Control and Prevention and healthcare providers to determine the appropriate use of an additional booster dose of mRNA-1273, including for those at higher risk of COVID-19 due to age or comorbidities.”
Moderna said its decision to seek FDA approval was based on studies from the U.S. and Israel about the Omicron variant, but didn’t provide further information. Booster doses of Moderna are half the dose of the first and second doses.
Pfizer and BioNTech ask FDA to authorize fourth vaccine dose for older adults
Pfizer and BioNTech on Tuesday said they submitted a request to the FDA for EUA of an additional booster dose of their COVID vaccine for adults 65 and older.
The companies’ request was not based on robust, peer-reviewed U.S. data, but on two recent studies from Israel — both published on preprint servers without peer review.
The first study was done in conjunction with Israel’s Ministry of Health and involved a review of 1.1 million health records. The study concluded rates of COVID in those who received a fourth dose of Pfizer’s COVID vaccine were lower compared to those who received only three doses.
According to the preprint published on medRxiv, since Jan. 2 Israel has been administering a fourth dose of the Pfizer vaccine only to people over 60 and at-risk populations.
In the second study of Israeli healthcare workers, results showed a fourth dose of either Pfizer’s or Moderna’s vaccine boosted antibody levels, but neither was effective at preventing infections.
CDC deletes thousands of reported COVID-19 deaths in children
The CDC removed tens of thousands of deaths linked to COVID, including nearly a quarter of deaths it had attributed to those younger than 18, The Epoch Times reported. The change was made on March 15 on its COVID data tracker website.
“Data on deaths were adjusted after resolving a coding logic error. This resulted in decreased death counts across all demographic categories,” the CDC said on the website. The agency also acknowledged COVID death data is not complete.
Before the change, the CDC listed 1,755 deaths in children from COVID, along with 851,000 others, according to Kelley Krohnert, a Georgia resident who tracks the CDC’s updates.
The CDC removed 416 deaths among children and more than 71,000 other reported deaths — arriving at a total of about 780,000.
The CDC’s statistics are frequently cited by physicians and experts when pushing for children to receive COVID vaccines. Dr. Rochelle Walensky, the CDC’s director, referred to the tracker’s death total on November 2021 while pushing for an expert panel to advise her agency to recommend vaccination for all children 5 to 11 years old.
Vaccine researcher develops tinnitus 90 minutes after COVID shot, calls for more research
A vaccinologist at the Mayo Clinic in Minnesota said he developed tinnitus after receiving his second dose of an mRNA COVID vaccine.
Dr. Gregory Poland’s symptoms began 90 minutes after receiving the vaccine. He described the condition as “fairly severe” and “extraordinarily bothersome, interfering with sleep and the ability to concentrate.”
According to the National Institutes of Health, tinnitus is a sign that something is wrong with the auditory system. It is commonly described as a ringing in the ears, but it also can sound like roaring, clicking, hissing, or buzzing that accompanies soft, loud or high pitches.
According to the most recent VAERS data released on March 11, 19,851 people have reported developing tinnitus after a COVID vaccine, with 12,027 cases attributed to Pfizer’s COVID vaccine.
CEO of German health insurer fired after releasing data on underreported COVID vaccine injuries
The CEO of one of Germany’s largest health insurance companies was abruptly fired last month after he released data suggesting German health authorities are significantly underreporting COVID-19 vaccine injuries.
The data, released by Andreas Schofbeck of BKK/ProVita, have since been scrubbed from the company’s website.
Schofbeck, who noticed an unexpected jump in vaccine-related health insurance claims, in February notified the Paul Ehrlich Institute (PEI) — the German equivalent of the CDC — that BKK billing data indicated the PEI was underreporting adverse events to COVID vaccines.
In his letter to the PEI, Schofbeck wrote:
I’m “If these figures are extrapolated to the whole year and to the population in Germany, probably 2.5-3 million people in Germany have received medical treatment for vaccination side effects after Corona vaccination.”
Dr. Dirk Heinrich, chairman of NAV-Virchow Bund, an association of private medical practitioners in Germany, said PEI and BKK would be working closely to examine the billing code data. Heinrich also stated that the conclusions from Schofbeck’s letter are “complete nonsense.”
Children’s Health Defense asks anyone who has experienced an adverse reaction, to any vaccine, to file a report following these three steps.
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Hospital restrictions remain absurd and cruel
Health Advisory & Recovery Team | March 18, 2022
Following our recent article highlighting isolation and neglect in care homes, we are appalled to report that the situation is only slowly improving. What is more, many NHS sites are still imposing draconian and vindictive policies. Children are being separated from parents and dying relatives are being abandoned to a lonely end.
It is beyond comprehension that this situation persists. Three weeks to flatten the curve? More like 24 months to bulldoze the social contract. Here is one quote from a UK hospital this week:
“We know that continuing to extend restrictions on visiting will be disappointing and it is not a decision we have taken lightly. We understand how important the support of family and friends can be for patients in their recovery while they are in hospital, however, our number one priority is to keep everyone safe”.
These silken, virtue-signalling words – keeping “everyone safe” – are not only utterly simplistic, they disguise blanket policies that encourage multiple Milgram-esque acts of cruel depravity. We are hearing horrific stories of desperate children being denied access to their dying parents.
“Everyone” is not safe when a nonagenarian, now in declining health, has to spend their remaining weeks – or even days – in soulless incarceration. These individuals spent their entire working lives rebuilding this country after WW2 and then brought up a subsequent generation of taxpayers. Surely we owe these bastions of society the dignity of choice in their final days.
If this situation was not depressing enough, HART has also been made aware of the most cruel of indignities: patients in their final days of life are being denied palliative care if they refuse a covid injection. It is hard to comprehend the wickedness of foisting this particular medical intervention – with all the known short-term adverse effects – on someone with a severely weakened immune system who is already in their final days. It is hard to see this as anything other than battery.
There is no doubt that the overwhelming majority of people involved in the healthcare services want the best for their patients, so how can these things still be happening? Two years into this depressing saga, perhaps it is too late for those who promote these injustices to take responsibility for the harm caused. However, those that have been ‘going with the flow’, perhaps hoping for an easy life, might want to reconsider whether their consciences can bear any more of this, and whether they want to align themselves with faceless and sadistic despotism.
After all, you cannot comply your way out of tyranny.
In Germany, Corona Limps On
The Bundestag passes a new Infection Protection Act
eugyppius | March 18, 2022
As I wrote a few weeks ago, the legal basis for our current regime of unnecessary restrictions and interference in the everyday lives of German citizens expires after tomorrow, but Corona cannot be allowed to end in Germany. The past few weeks have seen fraught negotiations within the coalition government to draft a new Infection Protection Act and continue the circus.
Today, after acrimonious debate, the Bundestag voted in the new legislation. It provides two tiers of ongoing Corona regulation:
1) Automatically and at all times, “basic protection” measures will be available to the federal states. These allow the state governments to impose mask mandates upon local transit and healthcare facilities, and to impose testing requirements on healthcare facilities and schools. Of course, they will all do so. Mask mandates will also continue in long-distance trains and in aeroplanes.
2) State governments will be allowed to impose additional restrictions, including vaccination and testing requirements for restaurants and public events, in the case of so-called “hotspots.” Anytime you encounter English vocabulary in German law, it is a sign of bad things. A vote of the state parliament is necessary to declare a hotspot and these additional restrictions.
The federal states are allowed a transitional period to continue current rules, but this ends on 2 April.
The press is starting to fill with vile articles about the “freedoms” that will be returning to us. The thing is, that these are not freedoms anymore. They have become temporary, seasonal privileges, which can be removed anytime political pressure builds on the state parliaments. A softening of the rules makes things more comfortable in the shorter term, but it extends the political half-life of the Corona regime substantially.
 Despite all the crazy discussion in the press and from individual politicians, vaccine mandates appear to be dead in Germany; only about a third of the Bundestag support a universal mandate for adults.
That’s not as good as it sounds: A lot of other members of parliament want mandate-adjacent requirements that are also bad. Andrew Ullmann, from the FDP, has gained some support for his scheme of mandatory vaccine information sessions rather than mandatory vaccination. I agree that forced lectures from ignorant low-level bureaucrats are preferable to forced medical procedures, but the whole scheme also makes me find Andrew Ullmann even more loathsome than I did before.
In case you thought Ullmann was just trying to reach a compromise to ward off the vaccinators, he’s also open to mandates for the 50+ crowd, so he’s not your friend.
Meanwhile, the CDU (and CSU), who are not in government, propose setting up a creepy “vaccination register” so the vaccinators know who to pressure. They want vaccine mandates maybe possibly for certain at-risk groups and for certain professions.
Of 736 Bundestag members, a mere 50 support a resolution against mandatory vaccination, primarily from the FDP and the AfD.
Featured Video

When Israel Is Mighty
or go to
Aletho News Archives – Video-Images
From the Archives
US murdering 1 million Iraqis is democracy, Iran giving yogurt to Iraq is “domination”
By Ali Salaam | American Herald Tribune | July 31, 2017
The New York Times, owned by the Zionist Jewish supremacist Ochs-Sulzberger family, has no problem with Iraqi suffering as long as Iran is not the one behind it.
The Iraq War was a genocide of the Iraqi people by Zionist supremacists in the Bush administration. Over 1 million innocent people were killed based on a lie. American soldiers died in an Israeli war and now an average of 22 soldiers commit suicide every day because their consciences cannot cope with the fact they committed crimes in an illegal war that served no purpose other than to benefit Israel, not America.
Benjamin Netanyahu, Prime Minister of the Zionist regime, once said “We are benefiting from one thing, and that is the attack on the Twin Towers and Pentagon, and the American struggle in Iraq.”
Paul Wolfowitz had his sights on Iraq since his time in the first Bush administration. Former Israeli official and Bush administration official Richard Perle had his eyes on Iraq since at least his authorship of the Clean Break white paper. The Zionist regime had their eyes on Iraq since the 1980s when strategist Oded Yinon wrote his white paper in support of dividing the Arab-Muslim world along ethnic and sectarian lines. The global Zionist lobby has had their eyes on Iraq since Theodor Herzl stated that Eretz Israel’s true borders go from the Nile River in Egypt to the Euphrates River in Iraq. … continue
Blog Roll
 Aletho News
- MEP blasts ‘Euro-Gestapo’ for lecturing Russia on democracy
- Syria May Send Troops to Saudi Arabia Amid War with Ansar Allah
- UK whines about losing billions to ‘Putin tax’
- Baghaei to Rubio: Distorted narratives cannot erase US record of broken commitments
- Houthis Don’t Have to Conquer Saudi Arabia to Make It Pay
- MOE: Nearly 22,000 Students and Education Workers Killed
- Guterres in Islamabad: Genocide, cowardice, and the cage of Imran Khan
- Johnson, Marandi say Yemen holds upper hand over Saudi Arabia
- False flags won’t save aggressors, Iran FM spokesman says
- The Makkah Pact Enters Into Force: The End of American Dominance or Its New Form?
- If Americans Knew
- Gaza ceasefire exists in name only, say more than 100 organizations
- Nearly 2 Million in Gaza Need Urgent Shelter Assistance as Winter Looms: IOM Chief Warns
- Suppressing Palestinian resistance: US charity under fire for AI monitoring of Gaza classrooms
- Thousands Are Held in Israeli Torture Camps. This Is What Happens Inside
- Israel puts Gaza’s sick, injured, newborn in peril – Daily Update
- Report claimed Mark Levin used by Israeli government to influence Trump
- Over 2,000 Gazans have died awaiting medical evacuation amid Israel’s continued siege
- How a U.S. Diplomat Suppressed and Altered Reports Critical of Israel
- 5 Palestinians Die from Israeli Strikes in Gaza as Relentless Attacks Continue
- Report: Ceasefire Slows Killing but Leaves Devastation Intact
- No Tricks Zone
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative

