American Truckers are launching The People’s Convoy, a peaceful and unified transcontinental movement

FOR IMMEDIATE RELEASE
For media inquiries contact:
Email: thepeoplesconvoy@protonmail.com
American Truckers are launching The People’s Convoy, a peaceful and unified transcontinental movement, on February 23 from Adelanto Stadium in Southern California
ADELANTO, Calif., (Feb. 20, 2022) American truckers are launching The People’s Convoy, a peaceful and unified transcontinental movement, on Wednesday, February 23, 2022, from the Adelanto Stadium in Southern California. Starting at 10:00 a.m., hundreds of truckers will hear words of encouragement and blessings from a group of speakers including FLCCC President Dr. Pierre Kory and Godspeak Church Pastor Rob McCoy. The truckers and blue-collar workers of the United States will be joined by freedom-loving supporters from all walks of life – frontline doctors, lawyers, first- responders, former military servicemen and women, students, retirees, mothers, fathers and children – on this peaceful and law-abiding transcontinental journey toward the east coast. The truckers encourage one and all to come out to the stadium in the heart of Adelanto, California to wish them well, see them off and join in the journey.
This convoy is about freedom and unity: the truckers are riding unified across party and state lines and with people of all colors and creeds – Christians, Muslims, Sikhs, Mormons, Agnostics, Blacks, Hispanics, Asians, Native Americans, Republican, Democrats. All individuals are welcome to participate by either attending the launch gathering – at 10:00 a.m. on Wednesday February 23, at Adelanto Stadium – or by getting in their own vehicles and following the big rigs from Adelanto toward the east coast!
The message of The People’s Convoy is simple. The last 23 months of the COVID-19 pandemic have been a rough road for all Americans to travel: spiritually, emotionally, physically, and – not least – financially. With the advent of the vaccine and workable therapeutic agents, along with the hard work of so many sectors that contributed to declining COVID-19 cases and severity of illness, it is now time to re-open the country. The average American worker needs to be able to end-run the economic hardships of the last two years, and get back to the business of making bread – so they can pay their rents and mortgages and help jumpstart this economy. To that end, it’s time for elected officials to work with the blue collar and white-collar workers of America and restore accountability and liberty – by lifting all mandates and ending the state of emergency – as COVID is well-in-hand now, and Americans need to get back to work in a free and unrestricted manner.
The People’s Convoy is a non-partisan, trucker-led effort supported by a cross-cultural and multi-faith contingent of supporters including
- Dr. Pierre Kory and the doctors of the Frontline Covid-19 Critical Care Alliance (FLCCC)
- Liberty-minded lawyers such as Tom Renz and Joey Gilbert (Gubernatorial candidate – Nevada)
- Pastors like Rob McCoy and Rick Brown of Godspeak Church
- Transportation workers including rail workers and pilotsA broad consortium of organizations including
- The Unity Project
- The America Project
- Advocates for Citizens’ Rights
- U.S. Freedom Flyers
- The American Foundation for Civil Liberties & Freedom
- Faith groups from every spectrum
Newsmax and Eric Bolling have indicated they will do a ride along and live daily updates from the convoy with Maureen Steele. The Epoch Times and a variety of other journalists, media outlets and podcasters will also be embedding. Children’s Health Defense’s CHD.TV will be covering the convoy – and the activists on the ground and across the country – with live updates every day at 10 am EST at https://live.childrenshealthdefense.org/.
The convoy is being assisted by retired military personnel and security experts, who are spearheading logistics in order to ensure a 100% safe, lawful, and peaceful journey.
The People’s Convoy Route*
*Route subject to change
Day 1: Wednesday, February 23
Morning – Depart Adelanto Stadium, CA
Evening – Arrive in Kingman, AZ for overnight stay
Day 2: Thursday, February 24
Morning – Depart Kingman, AZ head east on I-40, toward Lupton, AZ Evening – Arrive in Lupton, AZ for overnight stay
Day 3: Friday, February 25
Morning – Depart Lupton, AZ on I-40 eastbound thru New Mexico Evening – Arrive in Glenrio, TX for overnight stay
Day 4: Saturday, February 26
Morning – Depart Glenrio, TX
Evening – Arrive in Elk City, OK area for overnight stay
Day 5: Sunday, February 27
Morning – Depart Elk City, OK area
Evening – Arrive in Vinita, OK area for overnight stay
Day 6: Monday, February 28
Morning – Depart Vinita, OK area
Evening – Arrive in Sullivan, MO area for overnight stay
Day 7: Tuesday, March 1
Morning – Depart Sullivan, MO area
Evening – Arrive in Indianapolis, IN area for overnight stay
Day 8: Wednesday, March 2
Morning – Depart Indianapolis, IN area
Evening – Pause for rest in Indianapolis, IN area for overnight stay
Day 9: Thursday, March 3
Morning – Depart Indianapolis, IN area
Evening – Arrive in Cambridge, OH area for overnight stay
Day 10: Friday, March 4
Morning – Depart Cambridge, OH area
Evening – Arrive in Hagerstown, MD area for overnight stay
Day 11: Saturday, March 5
Morning – Depart Hagerstown, MD area Evening – Arrive in the DC Beltway area
The People’s Convoy will abide by agreements with local authorities, and terminate in the vicinity of the DC area, but will NOT be going into DC proper.
Stay tuned for opportunities for elected officials and regular folks to go “Ridin’ Shotgun” with an actual trucker for a day – as well as an opportunity to bid on one seat that will be sold on our Operations Vehicle – for a similar ride-along opportunity. Details will be posted to the website soon.
To support the truckers, see the routes, or find out more, please visit: http://www.ThePeoplesConvoy.org This website and the official social media handles are the ONLY source of accurate data about this
peaceful, law-abiding convoy – we hope to see America there!
Instagram: https://www.instagram.com/thepeoplesconvoyusa/ Twitter: https://twitter.com/peoplesconvoyus
An Open Letter to the Professional Bodies of Counsellors and Psychological Therapists in the UK
Therapists for Medical Freedom | February 17, 2022
We write as a group of registered counsellors, psychotherapists and psychologists in clinical practice in the United Kingdom.
We are contacting you to express our grave concerns around Vaccines as a Condition of Deployment (VCOD) mandates for health and social care professionals, and the implications that these could have for our profession.
Whilst we welcome the recent suspension of the NHS vaccine mandate [1] to allow space for further public consultation, we are also aware that Sajid Javid, the Secretary of State for Health and Social Care, has made it clear that the debate on mandatory vaccination is far from over. He was quoted in The Times on 7th February as demanding that medical regulators send the “clear message” that healthcare workers must be vaccinated against coronavirus. [2]
The implication here is that the onus of enforcing and policing the vaccination status of healthcare workers could be shifted from employers to professional/regulatory bodies. We are concerned about the silence of our professional bodies on this matter and now seek urgent clarification on their positions.
We call upon our professional bodies to publicly reject any policy of mandating COVID-19 vaccines as a condition of registration and/or deployment amongst their membership – either now or at a future point. Furthermore, we urge them to commit to protecting the right to informed consent and bodily autonomy, both for their professional membership and the clients we serve.
In particular, we would like the professional bodies to consider and respond to our professional concerns on the following points:
1. Mandatory vaccination policies conflict with our professional ethics as counsellors and psychological therapists.
One of the core principles common to the Ethical Frameworks of all our professional bodies is that of upholding client autonomy and their right to informed consent to treatment.
As health practitioners, we rightly understand that no medical or clinical intervention can be considered universally safe. We know from our own practice that even authorised, regulated and ethically sound medical treatments can still pose significant risks and have the potential to cause harm at an individual level.
As such, suitability for any medical treatment needs to be assessed on a case-by-case basis and can only be authorised with informed consent from the client (so long as they have the capacity to do so), after they have been given full and accurate information around any potential risks.
This principle of informed consent is not only vital to our ethical practice, it is upheld as a central principle within wider medical ethics and international human rights law. For example, in the UK all medical interventions in the NHS must be fully voluntary and in line with this principle of informed consent:
The decision to either consent or not to consent to treatment must be made by the person, and must not be influenced by pressure from medical staff, friends or family… If an adult has the capacity to make a voluntary and informed decision to consent to or refuse a particular treatment, their decision must be respected. [3]
In March 2015, a significant judgement about the nature of informed medical consent was made in the UK Supreme Court. [4] The court clarified that doctors must: “take reasonable care to ensure that the patient is aware of any material risks involved in any treatment,” in which, “a reasonable person in the patient’s position would be likely to attach significance to the risk, or the doctor is aware that the particular patient would be likely to attach significance to it”.
The court ruled that UK doctors can no longer rely on simply sharing the consensus of a body of medical opinion (‘the Bolam test’) as a basis for a patient’s informed consent, but a personalised risk assessment must be given. In the case of COVID-19 mandates, this means that generic claims that ‘the science is settled’ or ‘vaccines are safe and effective’ – cannot be used to justify their safety for an individual. [5]
The public and professional discourse on COVID-19 vaccination mandates are an example of how social pressure can be exerted on individuals to have a particular health intervention, even without a full individual risk assessment or any long-term safety data. As such, mandates can be considered medically coercive and in direct violation of the legal principle of informed consent.
We call on our professional bodies to recognise that coercion does not equal informed consent.
2. COVID-19 vaccines are far from universally ‘safe and effective’.
COVID-19 vaccinations use novel technologies which have been in widespread use for little more than a year, are still in clinical trials and for which by definition no long-term safety data is available.
Since the start of the vaccine rollout, we have already seen a significant shift from the COVID-19 jabs being promoted as being ‘safe and 100% effective’ [6][7][8][9] – to a recognition that there can be serious, even fatal side effects for a small minority of people. Their overall efficacy, especially in reducing transmission and preventing the spread of Coronavirus, is also far from what was originally hoped for.
Furthermore, since their general release, some COVID-19 injections have now been discontinued for use within certain demographics due to safety concerns. For example, the AZ and Moderna vaccines have been discontinued for young people in several countries after safety concerns arose around the risks of blood clots, following several high-profile deaths. In more recent months there have been emerging scientific studies showing the risks, particularly to younger males, of serious side effects such as myocarditis and pericarditis following vaccination, as well as ongoing concerns about the impact of vaccines on the female menstrual cycle. Both concerns have led to the commissioning of major safety investigations through additional clinical trials.
Whatever the outcome of these investigations, the fact remains that our understanding of these novel COVID-19 vaccines and the risks they pose to human health is far from comprehensive or complete.
Whenever there is risk of significant harm from a medical intervention, especially when the treatment is newly developed and those harms could be life-threatening, it is imperative that there is free choice for the individual to refuse that treatment without fear of negative consequences.
For professional bodies to require mandatory vaccination as a condition of professional registration, for acceptance on professional training courses, or as a condition of employment, would amount to unethical coercion of its professional members. To do so would place the professional bodies in direct violation of the principle of informed consent.
We ask that the professional bodies join us in speaking out against the unethical nature of mandatory vaccination policies, and publicly affirm their commitment to the ethical principle of informed medical consent.
3. Informed consent goes beyond issues of safety and risk.
As counsellors and therapists, we recognise that assessing the safety profile of a specific intervention is only one aspect of the complex decision-making process that informs our consent to medical treatment.
An individual’s moral, spiritual and political beliefs, as well as their cultural practices, life experiences and approach to managing their health, will also have an impact on their willingness to give, or withhold, informed medical consent.
Many of us take a holistic, person-centred approach to working with our clients. As such, we believe in the validity, authority and importance of these broader factors that can be drawn upon to inform medical consent. We see these wider factors as valuable, essential and equal; individuals have a right to refuse a medical treatment on wider grounds than its official safety profile or potential side effects. We are particularly concerned about the impact of mandates on those who have complex health conditions, those who have prior experiences of being harmed by medical treatments, those who favour their natural immunity, and those with religious or ethical concerns about the development process of the vaccines.
Current government guidelines for vaccine mandates only grant ‘medical exemption’ to staff with a tiny number of officially permitted medical conditions [10], with no allowance for many broader concerns that could be central to someone deciding not to consent to a COVID-19 injection. We believe that the government has no lawful right or moral authority to draw up a set of very limited medical criteria and then insist that these are the only permitted circumstances in which someone can be officially ‘exempted’ from vaccine mandates without facing redeployment or job loss.
As counsellors and psychological therapists, we uphold the right of every individual to make an informed choice about whether to take a COVID-19 vaccination, or indeed any other medical intervention, based on their own personal circumstances and medical history. We call on our professional bodies to uphold that right for practitioners and the clients we serve.
4. Professional bodies are failing in their duty of care to members who are affected by NHS vaccination mandates.
It would be incongruent for professional bodies to enshrine the principle of informed consent within their ethical codes of conduct for working with clients, whilst their professional members are not permitted to make autonomous decisions about their own medical treatment.
Mandatory vaccination policies, and the loss of the right to informed medical consent, is causing significant psychological distress to many UK counsellors and therapists, especially those working in the NHS. Many of these affected practitioners have been loyal, paying members of their respective professional bodies for decades. The silence and seeming lack of engagement from our professional bodies around this issue is both disturbing and disappointing given how severe the consequences are for members who face job loss.
The exact number of counsellors and psychological therapists who stand to be affected by NHS vaccine mandates is uncertain, as to our knowledge, there has been no formal consultation process around this issue by any of the professional bodies.
However, Therapists for Medical Freedom have now facilitated numerous free, volunteer-run support workshops for affected therapists, which have often been full to capacity. We have also had hundreds of communications from distressed members who are under significant stress from the vaccine mandate process. Many have complained to us about experiencing an utter lack of clarity, guidance or support from their professional body.
Professional bodies have a duty to represent the interests of their paying members, especially at times where their human and employment rights are under threat in a professional context.
Therapists affected by vaccine mandates deserve better treatment and representation than they are currently getting from professional bodies. This situation must change, and we appeal to professional bodies to address this with the utmost urgency.
5. Vaccine mandates will have negative consequences for clients accessing therapeutic services.
NHS England estimated that had the vaccine mandate policy been implemented in April as planned, this would have left the NHS down by at least 80,000 staff, as many planned to leave the profession rather than comply with the policy. [11]. This number would increase exponentially if vaccines were mandated as part of the professional registration process, thereby affecting health professionals working outside of NHS services, which applies to most therapists and counsellors in the UK.
To lose a significant number of counsellors and therapists at a time of national crisis could pose significant harm to clients. COVID-19 and the wide-ranging impact of restrictions on the population has left a legacy of new and worsening existing mental health problems. The Centre for Mental Health estimates that 8 million adults and 1.5 million children will need mental health support in the years following the pandemic. [12]
Those of us who have worked to provide psychological therapies throughout this challenging time are now seeing an unprecedented rise in demand for NHS and voluntary sector counselling and therapy services, to the point where people in need now face dangerously long waiting times. [13] Across the UK, even private therapy services and individual practitioners are in short supply, with many having to make difficult decisions to turn away people in need because they simply do not have the resources to treat them. At a time of increased mental health need, vaccine mandates would therefore be detrimental for current and future clients.
We call upon the professional bodies to provide reassurance that clients’ access to therapeutic support will not be restricted based on vaccination status, either now or in the future. We also call on them to reject policies that will risk the loss of experienced practitioners, put further strain on existing services and staff, and potentially dissuade others from training to enter the field.
6. It is essential to consider the wider context to mandatory vaccination policies and to remember the lessons of history.
As counsellors and psychological therapists, when faced with an ethical dilemma, we are encouraged to look beyond the issue itself and consider the wider field and context – including any relevant historical, sociological and political factors. Therefore, when considering the ethics of vaccine mandates, we must consider more than just the risk posed by COVID-19 vs the benefits and risks of vaccination.
When we step back and consider the wider socio-political context, we can clearly see that:
- Governments do not always act in the best interests of the public they are appointed to serve, whatever their political rhetoric might be. We are seeing numerous examples of this emerging now, for example the conflicts of interests in the awarding of PPE contracts and the flouting of COVID-19 rules by senior government figures. [14]
- There have been numerous instances in human history, especially at times of ‘national emergency’, where government bodies have actively lied to the population, exploited the situation to further their own aims, or have sought to conceal important information, especially when it could harm their wider political agenda. [15][16][17]
- The health care system has a long history of being vulnerable to exploitation by political lobbyists, corporate donors or becoming compromised by internal pressures from within government or from regulatory bodies. Consider examples from our recent history – public health advice given to reassure the public of the safety of tobacco, pesticides, GMOs – which have later been proven to be manifestly unsafe, despite the proclamations of the government-sanctioned public health experts of the time. [18][19][20]
- Many authorised medical treatments have later been discovered to be causing significant harm to human health and have been withdrawn from public use, despite having passed required safety checks and being widely embraced by the medical orthodoxy of the time. [21][22][23]
- We are being exhorted to “trust the science” when there is no such thing as ‘the’ science. Rather, science has always comprised a breadth of opinions, conclusions, methods and ethical standpoints. History has shown us that public trust has not always been as safe as we would hope for in the hands of scientists and medical professionals, especially when there are financial interests at stake. [24][25]
- Politicians, pharmaceutical companies, peer-reviewed medical research, clinical trials, regulatory bodies and individual expert opinion – all of these are vulnerable to human error, corruption and conflicts of interest which are not always declared or formalised. [26][27][28]
In the context of our collective history, as ethical health practitioners, we have a responsibility to ask difficult questions if we see draconian policies such as vaccination mandates being introduced in our society. We must continue to think critically about who would profit and benefit most from such policies. Might there also be vested interests, whether in government, science and medicine or the pharmaceutical industry, that could stand in the way of open and transparent discussion? [29][30]
It is not the terrain of ‘conspiracy theory’ for therapists and other health professionals to demand that government and medical experts are scrutinised and held to account for the policies they impose upon the public. As a profession, we must make room for alternative perspectives and difficult questions without these legitimate concerns being dismissed or slandered as ‘anti vax’, ‘dangerous disinformation’ or even more alarmingly, as ‘far-right extremism’.
It is not acceptable for our Professional Bodies to simply dismiss or silence any dissenting voices within their membership, or to ignore these difficult questions. Nor is it acceptable for heavy-handed policies such as COVID-19 vaccine mandates to be supported and justified by our professional bodies on the sole basis that they are acting in line with ‘official legislation or government guidance’ without any independent analysis of the actual effectiveness, ethics, or impact of the guidelines – or any acknowledgement that governments do not always act solely in the public interest.
Our professional bodies have a duty to carefully scrutinise any mandated public health measures that compromise our medical autonomy. They must not be accepted on face value as being in the public interest simply based on the assurances of government and its approved health advisors, or pharmaceutical companies with vested interests.
Recommended Actions:
It is time for the professional bodies who represent counsellors and psychological therapists in the UK to show courage and break their collective silence on the issue of mandatory vaccination in our profession.
In light of all the above, we call on our professional bodies to:
- Uphold the values that are written and protected within their own ethical codes by publicly affirming their commitment to protecting the right of therapists and clients to freely give or withhold their consent to medical treatment without fear of coercion or punishment.
- Affirm that their commitment to upholding the right to informed consent will stand regardless of the emergence of new future variants, waves of disease or novel medical treatments.
- Engage with Therapists for Medical Freedom and other groups of concerned professionals in a process of dialogue around the ethics and legality of vaccine mandates in our profession.
- Pledge to protect the rights of therapists and clients who have exercised their lawful right to informed consent to refuse COVID-19 vaccinations.
- Use their authority as professional membership bodies to prohibit the implementation of discriminatory policies around COVID-19 vaccinations within their organisational membership and associated training institutes – and to publicly speak out against such discriminatory practices in the wider field.
- Remind their members that we each have an ethical responsibility to think critically for ourselves when assessing any government health advice, especially when it is mandated. Professional bodies should help facilitate this broader risk assessment process within their membership, especially the potentially negative impact that any existing or future public health advice might have on practitioners and clients.
- Take into account the broader historical, social and political context when assessing the ethics of mandatory health interventions. We cannot forget the harm that has been caused to human health and civil liberties when the right to refuse medical treatment has been denied to populations at other times in history.
We await to hear your considered responses on these important matters of professional ethics, legislation and human rights, and look forward to beginning a process of dialogue with you.
Yours sincerely,
Therapists for Medical Freedom
Principal Signatories:
Jennifer Ayling, Psychotherapeutic Counsellor, UKCP
Clare Beatson, Counsellor, BACP
Elizabeth Bentley, Psychotherapist, BACP
Johann Burton, Counsellor, NCS
Paula Charnley, Counsellor, BACP
Ben Harris, Psychotherapist, MBACP
Julie Horsley, Counsellor, NCS
Frances Kandler-Singer, Psychotherapist, BACP
Naintara Land, Psychotherapist, UKCP
Rachel Maisey, Counsellor, BACP
Kate Morrissey, Psychotherapist, BACP
Melanie Pickles, Counsellor, BACP
Dr. Bruce Scott, Psychoanalyst, UKCP & CP-UK
Dr. Gary Sidley, Clinical Psychologist (Retired)
Deborah Short, Psychotherapist, UKCP
Elizabeth Smith, Psychotherapist, Pre-Accred
Leanne Ward, Clinical Psychologist, HCPC
Sarah Waters, Psychotherapist, MBACP
Supporting Signatories:
Marc Allen, Trainee Therapist, Pre-Accred
John Bates, Psychotherapist, UKCP
Antoine Bowes, Counsellor, BACP
Dr. Faye Bellanca, Clinical Psychologist, HCPC
Caroline Brett, Psychotherapist, BACP
Jacqueline O’Brien, Psychotherapist, (retired)
Sheila Burchell, Clinical Psychologist, HCPC
Dr. Erika Filova, Clinical Psychologist, HCPC
Dr. June Golding, Psychotherapist, UKCP
Andrew Harry, Counsellor, UKPTA
Susan Hayes, Psychotherapist
Jessica Horton, Counsellor, BACP & BPS
Isla Hunter, Psychotherapist, BABCP
Gabrielle Lake Mitchell, Trainee Therapist, BACP
Maggie Leathley, Psychotherapist, BACP
Jane Margerison, Psychotherapist, BACP
Jonathan Martin, Psychotherapist, UKCP
Gary McKeever, Counsellor, BACP
Caroline Montanaro, Psychotherapist, UKCP
Dr. Naomi Murphy, Clinical Psychologist, HCPC & A-CP
Dr. Rachel Newton, Clinical Psychologist, HCPC & BPS
Sue Parker Hall, Psychotherapist, UKCP
Kay Parkinson, Psychotherapist, UKCP
Dr. Helen Payne, Psychotherapist, UKCP & ADMP UK
Carolyn Polunin, Psychotherapist, UKCP
Dr. Kate Porter, Clinical Psychologist, HCPC
Tracy Rees, Trainee Therapist, Pre-Accred
Dr. Helen Ross, Clinical Psychologist, HCPC
David Scott, Clinical Psychologist, HCPC
Patricia Taddei, Psychotherapist, UKCP
Dr. Lucie Turner, Clinical Psychologist, HCPC
Dr. Alice Welham, Clinical Psychologist, HCPC
Tracy Williams, Counsellor, BACP
Dominique Wynn, Psychotherapist, (Retired)
Sign the Open Letter
Are you a Counsellor, Psychotherapist or Clinical Psychologist based in the UK who is concerned about the impact of vaccine mandates on the profession? (whether you are personally vaccinated or not).
If so, please sign the letter.
Most Published Studies Exaggerated the Effects of Ocean Acidification – and Covid, Etc.
By Jennifer Marohasy | February 20, 2022
The concept of ocean acidification, and human-caused global warming more generally, could be described as containing a grain of truth embedded in a mountain of nonsense. Indeed, the projected large increase in atmospheric CO2 will at most cause a small reduction in pH – it will not turn the ocean acidic. Yet this is what is implied by the term ocean acidification. True acidification would require average pH to be reduced below 7.0, at which point seashells would indeed begin to dissolve. This is an impossible scenario, however, because of the ocean’s effectively limitless buffering capacity.
There is a newly published study by Jeff Clements and team that concludes many of the published studies on ocean acidification, especially those studies published in high impact journals and accompanied by sensational media reporting, have turned-out to be wrong, or at least exaggerated.
My colleague Peter Ridd describes the situation:
This problem with exaggeration of threats applies to many areas of science and has a name: The Decline Effect.
The Decline Effect goes like this: an early report, usually attracting huge media interest, predicts some sort of catastrophe. But when follow up work is done, usually with far better experimental procedure and far greater numbers of samples, the original report turns out to be wrong.
Jeff Clements’ team included Timothy Clark, Josefin Sundin and Frederik Jutfelt who were involved in a study last year proving that numerous reports by James Cook University’s coral reef centres on reef fish was totally wrong.
I co-authored a book chapter with John Abbot some years ago that explained:
Initial concerns about ocean acidification focused on organisms that construct their shells or skeletons from calcium carbonate. Such organisms are referred to as marine calcifiers and include not only corals, but also crabs, clams and conchs (sea snails).
Theoretically, and according to popular science magazines, all corals are already severely and negatively affected by ocean acidification. But this is not evident from methodologically sound studies undertaken at the Great Barrier Reef. A review of the growth rates of six, hard coral species at Lord Howe Island (Anderson et al. 2015) found marked variation in the growth rates of branching coral, while growth rates of the massive Porites coral were unchanged. The researchers suggested that a decline in the growth rates of the branching species could be attributable to a reduction in the calcium carbonate saturation state as a consequence of higher summer temperatures. A study measuring calcification rates for 41 long-lived Porites corals from seven reefs from the central Great Barrier Reef (D’Olivio et al. 2009), showed good recovery from the major 1998 bleaching event, with no significant trend in calcification rates for the inner reefs. Corals from the mid-shelf central Great Barrier Reef, however, did show a decline of 3.3%.
While most ocean acidification research has been focused on physiological processes, in particular calcification, there have also been studies on three common hard corals to look at their fertilisation, embryonic development, larval survivorship, and metamorphosis (Chua et al. 2013a; Chua et al. 2013b). These studies have found the early life-history stages were unaffected by reduced pH; there was no consistent effect of elevated CO2 alone, nor in combination with temperature.
Studies of the effect of very high CO2 levels (up to 2,850 ppm) on molluscs – including oysters, clams, scallops and conchs – have shown that these species will generally build their shells more slowly as CO2 levels increase (Ries et al. 2009). This same study showed that crabs and lobsters respond quite differently to the same elevated CO2 levels, showing a general increase in calcification rates.
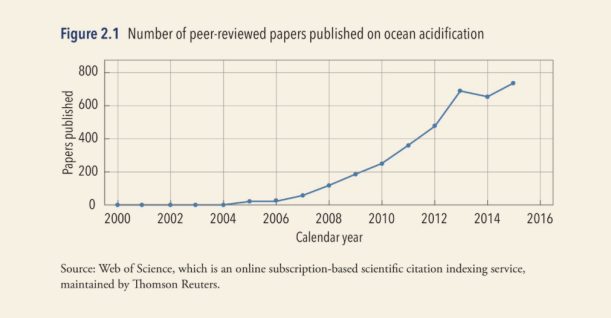
This chart shows how quickly scientists could meet the demand for commentary in the new area of ocean acidification, including to support the theory of human-caused global warming.
The varied responses among different organisms reflect their differing abilities to regulate pH at the site of calcification, and:
- the extent to which their outer shell layer is protected by an organic covering
- the solubility of their shell, or skeletal mineral
- the extent to which they use photosynthesis (Ries et al. 2009).
Of course, many marine organisms are not calcifiers, and some of these organisms have also been tested for a response to ocean acidification.
When seagrasses collected from three locations in the Great Barrier Reef region – Cockle Bay, Magnetic Island, and Green Island – were exposed to four different CO2 concentration levels for two weeks – with water temperature and salinity in the experimental tanks near-constant throughout – all three seagrass species exhibited enhanced photosynthetic responses (Ow et al. 2015). That is growth rates, observed after two weeks of exposure to an enriched CO2 environment in an indoor aquarium, were higher. This suggests that ocean acidification could mean more seagrass, which would be good for large marine mammals like dugongs (dugongs are vulnerable to extinction because of issues unrelated to changing ocean chemistry).
Also, contrary to expectations, laboratory investigations into the effects of three different CO2 treatments on anemonefish (commonly known as the clownfish) found that higher CO2 levels stimulated breeding activity (Miller et al. 2013). The breeding pairs from the fringing reefs of Orpheus Island on the Great Barrier Reef, where they are exposed to the highest CO2 levels, produced double the number of clutches per breeding pair, and 67% more eggs per clutch than the control. However, young anemonefish that were bred in high CO2 levels and high temperatures showed decreases in their length, weight, condition, and survival (Miller et al. 2012). Though these effects were absent or reversed when their parents also experienced the higher concentrations (Miller et al. 2013).
We concluded:
Most studies have been on single species in contrived laboratory conditions. They have been of short duration, and they have not considered the potential for adaptation. In the few instances where adaptation has been considered, it has been shown to significantly modify the impact of varying pH as a consequence of elevated levels of CO2.
All of this needs to be assessed against the reality that along the length and breadth of the Great Barrier Reef there are naturally occurring large daily fluctuations in pH, and that it is unclear as to what extent the current trends of apparent pH decline are part of existing natural cycles.
Most of the articles describe the effects of changes of pH on biological organisms; many of the claims are based exclusively on laboratory experiments (Riebesell & Gattuso 2015). However, a problem with laboratory experiments is that they cannot capture the complexities of the real world, not even the tremendous natural variability in ocean pH – which is a measure of ocean acidification.
Statistician John P.A. Ioannidis published a review of medical research back in 2005 entitled ‘Why most published research findings are false’ (Plos Medicine ). It included a comment that:
The majority of modern biomedical research is operating in areas with very low pre- and post-study probability for true findings.
The review by John Ioannidis is a devastating critic of the sad state of biomedical research. It is this same profession, biomedical research, that concluded we should fear Covid-19 and get vaccinated – with the results from the Pfizer trials withheld while emergency approvals were granted for the mass vaccination of citizens across the world against Covid-19.
We will no doubt have better insights, when studies like those by Jeff Clements into ocean acidification, are undertaken into the recent Covid-19 vaccine research. We may then be in a position to judge whether the apparent ineffectiveness of these particular Covid-19 vaccines, despite all the promises, can be best explained by corporate greed and mendacity, or simply flaws in the scientific method. Certainly there was pressure on medical researchers to find a quick cure, that could be administered as part of a global public health response, to what appeared in the beginning to be a deadly new virus much worse than the seasonal flu.
The British Medical Journal in an editorial dated 19thJanuary includes commentary that we don’t know enough about Covid-19 vaccines.
‘Today, despite the global rollout of Covid-19 vaccines and treatments, the anonymised participant-level data underlying the trials for these new products remain inaccessible to doctors, researchers, and the public—and are likely to remain that way for years to come,’ the editorial states. ‘This is morally indefensible for all trials, but especially for those involving major public health interventions.’
The editorial also accuses pharmaceutical companies of ‘reaping vast profits without adequate independent scrutiny of their scientific claims,’ pointing to Pfizer, whose Covid vaccine trial was ‘funded by the company and designed, run, analysed, and authored by Pfizer employees’.
Of course, Peter Ridd lost his job at James Cook University for speaking truth to power. Those who continue to publish studies on ocean acidification, especially those studies published in high impact journals and accompanied by sensational media reporting, have most recently been rewarded by the Australian government with an additional $1billion in funding. Some of this money will end-up funding more nonsense ocean acidification projects at James Cook University. It is unlikely that any of this grant money will be used to ensure that there is some quality assurance of the same research.
How the Charter of Rights let Canada down
BY YUAN YI ZHU | UNHERD | FEBRUARY 18, 2022
If Canada has a sacred cow, akin to the NHS in the UK, it is the Canadian Charter of Rights and Freedoms — a constitutional bill of rights added to our constitution in 1982. As a national symbol, it is more popular than the national flag, the national anthem, and even hockey. Many Canadians can barely imagine that other, more benighted, lands might also have put some fundamental rights down in writing.
This would normally be harmless enough. Canada is after all a young nation, and nations need symbols. But the Charter, though full of admirable sentiments, has also infantilised Canadian politics and public discourse. A vague document full of broad promises coupled with important qualifications (rights are subject to limits as “can be demonstrably justified in a free and democratic society”) and exceptions (judicial interpretations of rights may be subject to legislative override under s. 33, the notwithstanding clause), it has enabled generations of Canadian judges to act as supreme legislators by interpreting it in all sorts of creative ways, striking down disfavoured legislation at a whim.
Only a few months ago, for instance, a Canadian court ruled that it was unconstitutional to require prospective schoolteachers to pass a basic maths test — the Charter, you see, forbids this, because equality rights something-something. No policy of any importance is implemented without the courts, and usually the Supreme Court of Canada, chiming in, which suits politicians admirably because they can fob awkward issues to the judges in that way.
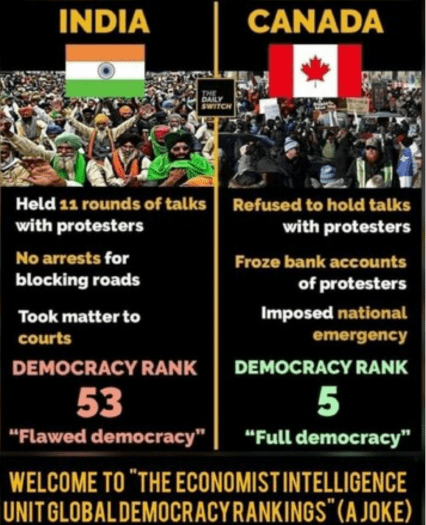
This is where the Canadian trucker protests come in. Earlier this week, the Trudeau government invoked the Emergencies Act to stop these protests, which have now lasted for almost two months. The Emergencies Act, which replaced the bluntly but honestly named War Measures Act in 1988, gives the power to the Governor-in-Council (in practice the Cabinet) to declare an emergency. Once an emergency is declared, the government can impose a host of drastic measures by executive fiat, subject to parliamentary review within seven days.
The measures the Canadian government have imposed make for uneasy reading, whatever your view on the trucker protests. They not only make it illegal to participate in or travel to the protests, but also to give money to any protester or to provide them with car insurance — while making it legal to freeze their bank accounts without a court order. In effect it makes it impossible for many of them to earn their livelihoods, or simply to live (Canada being such a large country, large parts of it are unliveable without an automobile, and driving legally requires car insurance). They also give the government the power to force tow truck drivers to provide their services to the government. Breach of these regulations carries a maximum of five years’ imprisonment.
The international reaction was distinctly queasy. Even outlets such as the New York Times, hardly the natural ally of protesters against Covid restrictions, saw those measures for what they were: a “temporary suspension of civil liberties”. But the Times quickly backed down after being bombarded with tweets by Canadian journalists and politicians angry with that description.
Bob Rae, Canada’s ambassador to the United Nations who was once one of Canada’s leading politicians, tweeted out the following representative gem:
The Preamble to the Emergencies Act states clearly that it is subject to the Charter of Rights. Contrary to what the NY Times has stated, civil liberties have not been suspended in Canada. Get a grip. – BOB RAE, TWITTER
But by any definition, freezing someone’s assets without due process is a violation of civil liberties. Likewise depriving people of their livelihoods or taking away people’s right to refuse to perform work for the government. You may think that these violations are justified, but that doesn’t change the fact that they are violations.
But Canadians’ grasp of the constitutional facts have been so atrophied by decades of unthinking Charter worship that many are no longer able to think about rights independently of it, to see that rights do not begin and end with a piece of paper with an impressive title. Just because the emergency decrees pay lip service to the Charter doesn’t make them any less rights-violating.
Ultimately, the best protection for rights is not any particular piece of legislation, but a robust societal consensus in their favour, as well as active thinking and discussion about their parameters. Through the Charter, Canadians have gained a constitutional guarantee for certain rights formulated in abstract terms, but may have lost much of the cultural wherewithal necessary to sustain a broader culture of rights. Would-be constitutional tinkerers in the United Kingdom and elsewhere might want to take note.
Trevor in Trimley’s letter to PM Justin Trudeau
(Since he claimed the right to freeze everybody’s bank accounts)
February 17, 2022
Dear Justin Trudeau,
How do you do it? It’s like you’re a psychic gifted with an intuitive capacity far beyond the range of normal people. I would never have known the truckers were racist just by looking at them, but apparently you can spot it from a mile away! And how did you know that they have “unacceptable views” without ever talking to them? Genius! Is this the result of special training or were you born this way? I must confess I’m so old-fashioned I still need racists to actually do or say something racist before I know I’m dealing with one. I was singing your praises to Mrs Trevor in Trimley only this morning and she agreed you have special gifts. (Actually she said you have special needs, she gets mixed up sometimes.) My Great Aunt Mabel had the gift too, but sadly those were different times and she was institutionalised. Perhaps when you die you should leave your brain to ‘the science?’
But I know you’re a busy man so I shall get to my point. I should tell you that it is Mrs Trevor in Trimley who prompted me to pen you this letter. She rightly brought to my attention that she has recently sent money (£20 as a birthday gift) to a cousin who emigrated to Canada in 1983, and she is now understandably concerned that Laurence may have gone off the rails since then and joined the ranks of the many hundreds of thousands of Canadians who have become racists, misogynists and terrorists during your premiership. Between you and me, I always had misgivings about “long haired Larry” and would not be the least bit surprised to see him flying a banner inscribed with provocative white supremacist language on it like, ‘freedom!’ (Yeah, sure Larry, freedom for whites like you but what about freedom for people who like to black up on social occasions?)
Mrs Trevor in Trimley’s concern, of course, is that her largesse may be mistaken for funding terrorism and that her bank account could be frozen, or worse, that she might be kicked out of the Women’s Institute if her name emerges on a list of supporters of working class struggles against the powerful, and all as a result of her being thoughtlessly generous to a person without first checking the acceptability of his current views. I offer my sincere apologies for my wife’s generous nature and would like to make a suggestion that I hope makes up for it.
To help us, and other non-Canadians, avoid making similar missteps in future, may I ask that you put in place a clear system that clarifies the views held by Canadian people we may come into contact with. My suggestion is that you ask Canadians to answer a simple “acceptable views” questionnaire, perhaps on a weekly basis? If their answers are published online we’ll be able to see whether or not we’re funding terrorism when we send them money for charitable causes they support, or money at birthdays and Christmas, etc.
My suggested ten questions are:
- Do you like Justin Trudeau?
- Do you admire Justin Trudeau?
- Are you now or have you ever been a member of a political party that opposes Justin Trudeau?
- Do you want Justin Trudeau to utterly destroy the Canadian economy to prevent you from feeling under the weather for a week or two?
- Do you think Justin Trudeau bears a passing resemblance to any notable Cubans?
- Do you think Justin Trudeau is right (they shouldn’t even need to read the rest of this question) that the truckers’ convoy is just as serious an emergency situation as World Wars 1 and 2?
- Do you think Justin Trudeau should stay in hiding for the rest of his life, yes or no? (This is a trick question Justin to confuse anyone who thinks they can cheat the test!)
- Can you, hand on heart, state that Justin Trudeau is right that there are ZERO treatments that work against COVID except for the glorious vaccines that will save the world?
- Would Canada be better off abandoning democracy entirely and installing Justin Trudeau as Supreme Leader?
- Would you like to see Justin Trudeau as President of a one world government?
_____
My grading system would be:
10 pro-Trudeau answers = Acceptable views.
Anything less = A gulag in Saskatchewan, or just Saskatchewan, whichever is harder to escape from.
Once again, please accept our apologies and know that I am fully in support of your stance AGAINST wanting people to die of COVID, and AGAINST racists, misogynists, transphobics, homophobics, terrorists, and everything else that’s impossible for anyone to publicly support, and that you’ve so cleverly founded your political ideology on. Who could ever argue successfully with any of that??!!
Please be assured that any unfortunate error made by Mrs Trimley was just carelessness with her innate human desire to give generously to people less well off than herself and should not be interpreted as a hostile act towards you personally or anyone else lacking those instincts. We’re on your side! To prove it, I have begun a fundraiser with GoFundMe.com to support your campaign to be Dictator of Canada! This is gonna be huge! I’ve kicked it off with a pound. You’re on your way!
Yours sincerely,
PS. I’ve just watched a couple of YouTube videos of the truckers and now you’ve pointed it out, it’s so clear they’re racist! The black racist truckers I saw were obviously the worst. Who are they even racist against??? Is it white people or themselves??? Please advise.
Trevor in Trimley writes open letters to people who should know better. You can read more of his work on his substack.
Nearly 24,000 Deaths After COVID Vaccines Reported to VAERS, Data Show
By Megan Redshaw | The Defender | February 18, 2022
The Centers for Disease Control and Prevention (CDC) today released new data showing a total of 1,119,063 reports of adverse events following COVID vaccines were submitted between Dec. 14, 2020, and Feb. 11, 2022, to the Vaccine Adverse Event Reporting System (VAERS). VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S.
The data included a total of 23,990 reports of deaths — an increase of 375 over the previous week — and 192,517 reports of serious injuries, including deaths, during the same time period — up 4,382 compared with the previous week.
Excluding “foreign reports” to VAERS, 760,102 adverse events, including 10,909 deaths and 79,111 serious injuries, were reported in the U.S. between Dec. 14, 2020, and Feb. 11, 2022.
Foreign reports are reports foreign subsidiaries send to U.S. vaccine manufacturers. Under U.S. Food and Drug Administration (FDA) regulations, if a manufacturer is notified of a foreign case report that describes an event that is both serious and does not appear on the product’s labeling, the manufacturer is required to submit the report to VAERS.
Of the 10,909 U.S. deaths reported as of Feb. 11, 18% occurred within 24 hours of vaccination, 23% occurred within 48 hours of vaccination and 60% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 546 million COVID vaccine doses had been administered as of Feb. 11, including 321 million doses of Pfizer, 206 million doses of Moderna and 18 million doses of Johnson & Johnson (J&J).

Every Friday, VAERS publishes vaccine injury reports received as of a specified date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed. Historically, VAERS has been shown to report only 1% of actual vaccine adverse events.
U.S. VAERS data from Dec. 14, 2020, to Feb. 11, 2022, for 5- to 11-year-olds show:
- 8,173 adverse events, including 179 rated as serious and 3 reported deaths.
The most recent death involves a 7-year-old girl (VAERS I.D. 1975356) from Minnesota who died 11 days after receiving her first dose of Pfizer’s COVID vaccine when she was found unresponsive by her mother. An autopsy is pending.
- 16 reports of myocarditis and pericarditis (heart inflammation).
- 29 reports of blood clotting disorders.
U.S. VAERS data from Dec. 14, 2020, to Feb. 11, 2022, for 12- to 17-year-olds show:
- 29,154 adverse events, including 1,675 rated as serious and 38 reported deaths.
The most recent deaths involve a 13-year-old male (VAERS I.D. 2042005) from an unidentified state who died from a sudden heart attack seven months after receiving his second dose of Moderna, and a 17-year-old female from an unidentified state (VAERS I.D. 2039111) who died after receiving her first dose of Moderna. Medical information was limited and it is unknown if an autopsy was performed in either case.
- 68 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 96% of cases attributed to Pfizer’s vaccine.
- 639 reports of myocarditis and pericarditis with 627 cases attributed to Pfizer’s vaccine.
- 158 reports of blood clotting disorders, with all cases attributed to Pfizer.
U.S. VAERS data from Dec. 14, 2020, to Feb. 11, 2022, for all age groups combined, show:
- 19% of deaths were related to cardiac disorders.
- 54% of those who died were male, 41% were female and the remaining death reports did not include the gender of the deceased.
- The average age of death was 72.7.
- As of Feb. 11, 5,086 pregnant women reported adverse events related to COVID vaccines, including 1,635 reports of miscarriage or premature birth.
- Of the 3,557 cases of Bell’s Palsy reported, 51% were attributed to Pfizer vaccinations, 40% to Moderna and 8% to J&J.
- 851 reports of Guillain-Barré syndrome (GBS), with 40% of cases attributed to Pfizer, 30% to Moderna and 28% to J&J.
- 2,323 reports of anaphylaxis where the reaction was life-threatening, required treatment or resulted in death.
- 1,592 reports of myocardial infarction.
- 13,102 reports of blood clotting disorders in the U.S. Of those, 5,846 reports were attributed to Pfizer, 4,670 reports to Moderna and 2,542 reports to J&J.
- 3,992 cases of myocarditis and pericarditis with 2,456 cases attributed to Pfizer, 1,335 cases to Moderna and 170 cases to J&J’s COVID vaccine.
Pfizer and BioNTech Omicron-targeted COVID vaccine delayed
Pfizer and BioNTech’s new vaccine specific to the Omicron variant was delayed by several weeks due to a “slower-than-expected” data gathering process, Ugur Sahin, BioNTech’s CEO said Thursday.
Once a new vaccine is ready the company said it will consider whether a variant-specific vaccine was still needed, Sahin said.
“If the wave ends, that does not mean it can’t begin again,” he said, adding BioNTech could create new vaccines as variants emerge.
“I really don’t see the situation as dramatic anymore,” Sahin said, referring to how the COVID would develop in future. Pfizer and BioNTech had originally planned to release a new vaccine by the end of March, but said it was dependent on how much clinical data regulators would require.
Autopsies show two teen boys died of heart inflammation caused by Pfizer vaccine
Pathologists who examined the autopsies of two teenage boys who died days after receiving Pfizer’s COVID-19 vaccine concluded the vaccine caused the teens’ deaths.
The three pathologists, two of whom are medical examiners, published their findings Feb. 14 in an early online release article, “Autopsy Histopathologic Cardiac Findings in Two Adolescents Following the Second COVID-19 Vaccine Dose,” in the Archives of Pathology and Laboratory Medicine.
The authors’ findings were conclusive. Two teenage boys were pronounced dead in their homes three and four days after receiving the second Pfizer-BioNTech COVID-19 dose.
There was no evidence of active or previous COVID-19 infection.
The teens had negative toxicology screens (i.e. no drugs or poisons were present in their bodies).
Judge blocks Air Force from punishing officer who refused COVID vaccine for religious reasons
Federal judge Tillman E. Self III issued a preliminary injunction for an Air Force Reserve officer who was denied a religious exemption from the military’s COVID vaccine mandate, calling the military’s process for granting religious exemption “illusory and insincere.”
The judge said the Air Force likely violated the officer’s First Amendment rights when it denied her request for a religious exemption and subsequently appeal, and ordered the branch to refrain from taking “any adverse action” against the officer on the basis of “this lawsuit or her request for religious accommodation, specifically including forcing her to retire.”
As of Feb. 8, the Air Force had only approved 3,313 vaccine exemptions, but they were granted for medical or nonreligious administrative reasons. At the time the unnamed officer filed her lawsuit on Jan. 6, the Air Force had not granted any religious accommodations.
To date, the Air Force has granted only nine religious exemptions, denied 3,665 requests and is still considering 3,288 requests — 142 active-duty airmen have been administratively separated for refusing the vaccine, the branch said in its COVID update last week.
Children’s Health Defense asks anyone who has experienced an adverse reaction, to any vaccine, to file a report following these three steps.
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Oklahoma AG declares medical boards can’t punish doctor for prescribing ivermectin
LifeSiteNews | February 16, 2022
OKLAHOMA CITY – Doctors in Oklahoma are well within their professional rights to prescribe ivermectin (IVM) and hydroxychloroquine (HCQ) to COVID-19 patients, state Attorney General John O’Connor affirmed, despite the drugs’ disfavored status within the federal health bureaucracy.
“The Attorney General’s office finds no legal basis for a state medical licensure board to discipline a licensed physician for exercising sound judgment and safely prescribing an FDA-approved drug – like ivermectin or hydroxychloroquine – for the off-label purpose of treating a patient with COVID-19,” O’Connor’s office concluded in a February 8 statement, declaring that “healthcare professionals should have every tool available to combat COVID-19.”
“The Attorney General’s office neither condones nor condemns a specific course of treatment for COVID-19,” the release added. “Our office maintains that proper healthcare decisions are to be made between a patient and his or her physician, and the government should not interfere with their relationship.”
Despite being misrepresented in the mainstream media as aquarium cleaner and horse dewormer, respectively, hydroxychloroquine and ivermectin are both FDA-approved medications with a range of human applications, such that both are listed on the World Health Organization’s Model List of Essential Medicines. Like many medications, ivermectin is also used for horses, but human dosages of the drug for human ailments were not controversial until IVM started gaining notice in the context of COVID-19.
While experts continue to debate the drugs’ effectiveness at treating COVID-19, promising studies as well as reports of positive results have generated significant interest in them, as has the fact that they have been used and studied for far longer than the COVID-19 vaccines, which were developed and released in record time by the Trump administration’s Operation Warp Speed initiative. Many believe the long-established drugs are safer than relatively new vaccines they believe have been rushed and politicized.
Despite the established safety of IVM and HCQ, and the evolving nature of COVID knowledge, families across the country have had to go to court to force hospitals to let them try the drugs for their loved ones, while doctors have seen their medical licenses threatened for prescribing them – a scenario the Oklahoma Attorney General’s Office indicates will not be tolerated in the Sooner State.
The University of Minnesota, Emory University School of Medicine, Northwestern Medicine, and other medical institutions are currently conducting a major at-home clinical trial to assess ivermectin’s effectiveness at treating COVID-19, as well as that of the drugs metformin and fluvoxamine or any combination of the three.
300 medics demand halt to child vaccination as ‘all risk and no benefit’
TCW Defending Freedom – February 18, 2022
FOLLOWING the decision to roll-out Covid vaccines to healthy children aged 5-11 from April, the Children’s Covid Vaccine Advisory Group (CCVAG), comprising a wide range of senior health professionals, have issued a statement urging an immediate halt to the policy.
Dr Ros Jones, chairwoman of the CCVAG, said: ‘Why are the governments of the four nations announcing a rollout of Covid vaccines to healthy children aged 5-11 when they still have not answered urgent questions about safety in 12-17-year-olds?
‘Presumably this “offer” is being made on a “non-urgent” basis because the government has not finished its investigation into the growing evidence of harms to children.
‘This has never been a more urgent matter. We must halt the vaccine roll out while further investigations take place.’
Since yesterday morning, more than 300 healthcare professionals have co-signed a letter to the government and its advisers, in a growing critique of policy by Britain’s medical establishment.
The letter, which you can read here with the full list of signatories, calls for an immediate halt to the UK Covid vaccine roll-out to children to allow time for a thorough investigation.
Data from Hong Kong shows the myocarditis (heart inflammation) risk to teenage boys as high as 1 in 2,680, and they have ceased giving a 2nd dose. ONS figures for the UK have shown a significant rise in non-Covid deaths, representing at least two young men aged 15-19 dying each week, the cause of which has yet to be investigated and correlating with the vaccine roll-out.
The CCVAG says: ‘Vaccinating children is all risk and no benefit. Yet governments are recommending vaccinating healthy 5-11s, most of whom have already had SARS-CoV-2 infection, providing excellent natural immunity.’
About the CCVAG
The Children’s Covid Vaccine Advisory Group comprises a wide number of health professionals and scientists including several of the country’s leading professors in medicine, microbiology and risk, as well as specialists in public health, emergency medicine, paediatrics, infectious disease and primary care.
DHS says it scans social media for “misinformation” but not “constitutionally protected speech”
But “misinformation” is constitutionally protected speech
By Didi Rankovic | Reclaim The Net | February 18, 2022
The Department of Homeland Security (DHS) is doubling down on a recently revealed policy of tying the issue of domestic terrorism with online “misinformation,” as well as keeping an extra eye on trucker protests.
The document derived from an event that spelled all this out first appeared on February 7 as a bulletin, detailing the allegedly heightened threats the US is facing – not least because of “an online environment filled with false or misleading narratives and conspiracy theories.”
What was until recently typical of media op-eds and Twitter exchanges has evidently seeped into official policy, so the DHS now explicitly fears that “misleading narratives” found on the internet have the power to undermine trust in US government, not to mention branding free expression and political differences as dangerous “discord.”
Meanwhile, what is sowing true discord – Covid mandates – are mentioned not as a problem in and of itself, but simply something that gives rise to said “misleading narratives.”
“For example, there is widespread online proliferation of false or misleading narratives regarding unsubstantiated widespread election fraud and COVID-19. Grievances associated with these themes inspired violent extremist attacks during 2021,” reads the bulletin.
A week later, after this particular take on the situation raised some eyebrows in the Senate, DHS Counter-Terrorism Coordinator John Cohen is defending the document.
Reports, including in the Washington Times, say that Senator Marsha Blackburn described this particular DHS policy as speech policing, while the nonpartisan Center to Advance Security in America (CASA) wants to know more about the department’s “methodology” in coming up with all this.
But according to Cohen “hard analysis” has taken place (he failed to mention whether it produced any “hard evidence”) which he says shows links between “narratives about government’s response to COVID, the 2020 election, immigration, and race.”
And, he continued, the job of the DHS is not to police thought. One would hope the agency does its job, but a question mark lingers over it since Cohen added that the DHS doesn’t monitor individuals who are engaging in constitutionally protected speech.
“Our job’s not to police thought. Our job is to prevent acts of violence. We don’t monitor individuals engaging in constitutionally protected speech,” he said.
“We’ve put in place a series of protections to make sure that as we’re evaluating online content, it’s only relating to threats, and we’re only handling that information in a privacy, civil liberties-protective way.”
Unfortunately for Cohen’s own “narrative” here, in the US, even what passes as “misinformation” is actually constitutionally protected speech.
As for trucker protests, which are treated in Canada as a national security issue, he said the DHS was monitoring them in cooperation with counterparts across the border.
He diminished the number of participants whose goal was “simply” to express opposition to vaccine mandates by saying there were “some people” who were there for that reason.
But, Cohen went on, there are “significant levels of online and physical participation by ideologically motivated violent extremists.”
40,000 Deaths Following COVID Shots in European Database

By Brian Shilhavy | Health Impact News | February 18, 2022
The European (EEA and non-EEA countries) database of suspected drug reaction reports is EudraVigilance, verified by the European Medicines Agency (EMA), and they are now reporting 39,997 fatalities, and 3,666,011 injuries following injections of four experimental COVID-19 shots:
- COVID-19 MRNA VACCINE MODERNA (CX-024414)
- COVID-19 MRNA VACCINE PFIZER-BIONTECH
- COVID-19 VACCINE ASTRAZENECA (CHADOX1 NCOV-19)
- COVID-19 VACCINE JANSSEN (AD26.COV2.S)
From the total of injuries recorded, almost half of them (1,727,226) are serious injuries.
“Seriousness provides information on the suspected undesirable effect; it can be classified as ‘serious’ if it corresponds to a medical occurrence that results in death, is life-threatening, requires inpatient hospitalisation, results in another medically important condition, or prolongation of existing hospitalisation, results in persistent or significant disability or incapacity, or is a congenital anomaly/birth defect.”
A Health Impact News subscriber in Europe ran the reports for each of the four COVID-19 shots we are including here. It is a lot of work to tabulate each reaction with injuries and fatalities, since there is no place on the EudraVigilance system we have found that tabulates all the results.
Since we have started publishing this, others from Europe have also calculated the numbers and confirmed the totals.*
Here is the summary data through February 12, 2022.
Total reactions for the mRNA vaccine Tozinameran (code BNT162b2,Comirnaty) from BioNTech/ Pfizer: 18,185 deaths and 1,791,261 injuries to 12/02/2022
- 50,761 Blood and lymphatic system disorders incl. 254 deaths
- 61,233 Cardiac disorders incl. 2,638 deaths
- 547 Congenital, familial and genetic disorders incl. 55 deaths
- 23,657 Ear and labyrinth disorders incl. 12 deaths
- 2,077 Endocrine disorders incl. 8 deaths
- 27,111 Eye disorders incl. 39 deaths
- 138,253 Gastrointestinal disorders incl. 706 deaths
- 443,764 General disorders and administration site conditions incl. 5,190 deaths
- 2,025 Hepatobiliary disorders incl. 95 deaths
- 19,243 Immune system disorders incl. 99 deaths
- 84,884 Infections and infestations incl. 1,931 deaths
- 35,665 Injury, poisoning and procedural complications incl. 349 deaths
- 44,308 Investigations incl. 520 deaths
- 11,795 Metabolism and nutrition disorders incl. 289 deaths
- 209,669 Musculoskeletal and connective tissue disorders incl. 228 deaths
- 1,744 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 166 deaths
- 290,349 Nervous system disorders incl. 1,926 deaths
- 2,658 Pregnancy, puerperium and perinatal conditions incl. 75 deaths
- 262 Product issues incl. 3 deaths
- 32,195 Psychiatric disorders incl. 216 deaths
- 6,509 Renal and urinary disorders incl. 272 deaths
- 74,588 Reproductive system and breast disorders incl. 6 deaths
- 75,926 Respiratory, thoracic and mediastinal disorders incl. 1,932 deaths
- 81,815 Skin and subcutaneous tissue disorders incl. 146 deaths
- 4,127 Social circumstances incl. 23 deaths
- 21,849 Surgical and medical procedures incl. 208 deaths
- 44,247 Vascular disorders incl. 799 deaths
Total reactions for the mRNA vaccine mRNA-1273 (CX-024414) from Moderna: 11,138 deaths and 573,035 injuries to 12/02/2022
- 13,383 Blood and lymphatic system disorders incl. 120 deaths
- 19,462 Cardiac disorders incl. 1,169 deaths
- 198 Congenital, familial and genetic disorders incl. 12 deaths
- 6,688 Ear and labyrinth disorders incl. 8 deaths
- 533 Endocrine disorders incl. 6 deaths
- 7,856 Eye disorders incl. 35 deaths
- 46,468 Gastrointestinal disorders incl. 416 deaths
- 152,534 General disorders and administration site conditions incl. 3,672 deaths
- 819 Hepatobiliary disorders incl. 55 deaths
- 5,683 Immune system disorders incl. 21 deaths
- 24,462 Infections and infestations incl. 1,051 deaths
- 10,555 Injury, poisoning and procedural complications incl. 211 deaths
- 12,633 Investigations incl. 395 deaths
- 4,996 Metabolism and nutrition disorders incl. 268 deaths
- 70,107 Musculoskeletal and connective tissue disorders incl. 221 deaths
- 700 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 86 deaths
- 95,946 Nervous system disorders incl. 1,040 deaths
- 925 Pregnancy, puerperium and perinatal conditions incl. 10 deaths
- 101 Product issues incl. 4 deaths
- 9,813 Psychiatric disorders incl. 181 deaths
- 3,157 Renal and urinary disorders incl. 218 deaths
- 14,047 Reproductive system and breast disorders incl. 9 deaths
- 24,308 Respiratory, thoracic and mediastinal disorders incl. 1,178 deaths
- 29,172 Skin and subcutaneous tissue disorders incl. 96 deaths
- 2,325 Social circumstances incl. 45 deaths
- 3,585 Surgical and medical procedures incl. 206 deaths
- 12,579 Vascular disorders incl. 405 deaths
Total reactions for the vaccine AZD1222/VAXZEVRIA (CHADOX1 NCOV-19) from Oxford/ AstraZeneca: 8,174 deaths and 1,170,321 injuries to 12/02/2022
- 14,038 Blood and lymphatic system disorders incl. 279 deaths
- 21,330 Cardiac disorders incl. 854 deaths
- 241 Congenital familial and genetic disorders incl. 9 deaths
- 13,580 Ear and labyrinth disorders incl. 7 deaths
- 709 Endocrine disorders incl. 6 deaths
- 20,310 Eye disorders incl. 32 deaths
- 108,425 Gastrointestinal disorders incl. 447 deaths
- 309,230 General disorders and administration site conditions incl. 1,893 deaths
- 1,062 Hepatobiliary disorders incl. 70 deaths
- 5,495 Immune system disorders incl. 40 deaths
- 43,810 Infections and infestations incl. 634 deaths
- 13,918 Injury poisoning and procedural complications incl. 201 deaths
- 26,112 Investigations incl. 206 deaths
- 13,147 Metabolism and nutrition disorders incl. 132 deaths
- 170,055 Musculoskeletal and connective tissue disorders incl. 171 deaths
- 769 Neoplasms benign malignant and unspecified (incl cysts and polyps) incl. 42 deaths
- 236,745 Nervous system disorders incl. 1,199 deaths
- 631 Pregnancy puerperium and perinatal conditions incl. 21 deaths
- 199 Product issues incl. 1 death
- 21,273 Psychiatric disorders incl. 73 deaths
- 4,416 Renal and urinary disorders incl. 82 deaths
- 17,181 Reproductive system and breast disorders incl. 3 deaths
- 42,021 Respiratory thoracic and mediastinal disorders incl. 1,119 deaths
- 52,622 Skin and subcutaneous tissue disorders incl. 69 deaths
- 1,657 Social circumstances incl. 9 deaths
- 2,217 Surgical and medical procedures incl. 33 deaths
- 29,128 Vascular disorders incl. 542 deaths
Total reactions for the COVID-19 vaccine JANSSEN (AD26.COV2.S) from Johnson & Johnson: 2,500 deaths and 131,394 injuries to 12/02/2022
- 1,272 Blood and lymphatic system disorders incl. 54 deaths
- 2,671 Cardiac disorders incl. 211 deaths
- 44 Congenital, familial and genetic disorders incl. 1 death
- 1,382 Ear and labyrinth disorders incl. 3 deaths
- 109 Endocrine disorders incl. 2 deaths
- 1,710 Eye disorders incl. 10 deaths
- 9,791 Gastrointestinal disorders incl. 94 deaths
- 35,428 General disorders and administration site conditions incl. 708 deaths
- 160 Hepatobiliary disorders incl. 15 deaths
- 572 Immune system disorders incl. 10 deaths
- 8,881 Infections and infestations incl. 211 deaths
- 1,230 Injury, poisoning and procedural complications incl. 26 deaths
- 6,393 Investigations incl. 134 deaths
- 793 Metabolism and nutrition disorders incl. 63 deaths
- 17,493 Musculoskeletal and connective tissue disorders incl. 57 deaths
- 95 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 9 deaths
- 23,989 Nervous system disorders incl. 248 deaths
- 61 Pregnancy, puerperium and perinatal conditions incl. 1 death
- 31 Product issues
- 1,844 Psychiatric disorders incl. 24 deaths
- 560 Renal and urinary disorders incl. 32 deaths
- 3,189 Reproductive system and breast disorders incl. 7 deaths
- 4,649 Respiratory, thoracic and mediastinal disorders incl. 314 deaths
- 3,894 Skin and subcutaneous tissue disorders incl. 12 deaths
- 429 Social circumstances incl. 4 deaths
- 932 Surgical and medical procedures incl. 75 deaths
- 3,792 Vascular disorders incl. 175 deaths
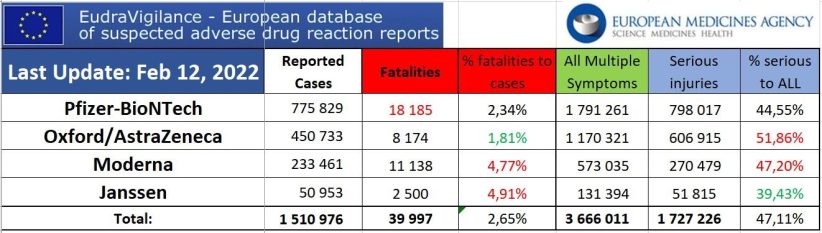
*These totals are estimates based on reports submitted to EudraVigilance. Totals may be much higher based on percentage of adverse reactions that are reported. Some of these reports may also be reported to the individual country’s adverse reaction databases, such as the U.S. VAERS database and the UK Yellow Card system. The fatalities are grouped by symptoms, and some fatalities may have resulted from multiple symptoms.
FDA Executive Officer: “Almost a Billion Dollars a Year Going into FDA’s Budget from the People we Regulate”
Health Impact News | February 17, 2022
Project Veritas published Part Two of its series on the FDA on Wednesday night which featured FDA Executive Officer, Christopher Cole, speaking about the inner workings of the agency including the FDA’s conflicts of interest, overspending, and why it’s hard for those within the agency to speak out on such abuses.
https://www.bitchute.com/video/WT4CuKhKW6N9/
In the footage, Cole talks about the impact that pharmaceutical companies have on the agency including the process for approving drugs.
“A long time ago, Congress approved user fees for [the] FDA. Basically, we charge the industry millions of dollars in order to hire more drug reviewers and vaccine reviewers, which will speed up the approval process, so they make more money,” Cole says in the hidden camera footage.
He then reveals that the FDA tones down the impact that these user fees have on the agency’s operations because, “they’re dependent on the drug companies, and the vaccine companies and these other companies for their agency to operate.”
The incendiary footage, which features Cole talking about how the additional money the FDA brings in “gets banked” to be spent on “whatever you can, whether it’s right or wrong,’’ also features Cole discussing reasons why it’s difficult for anyone in government to speak out about practices he sees as “probably excessive.”
“I don’t think there’s enough people saying they’re, like, ‘Look, that’s fine, but that’s not right. So, we’re not going to charge that.’ You don’t want to be that person. You’re not going to have a long shelf life in the agency if you’re always that person,” Cole said.
“There’s not an incentive to speak out in government, surprisingly. You would think there would be, but there’s not. It’s better just to just not say anything and just ignore it. The whistleblower, well, it’s high-profile whistleblower statutes and everything, that’s kind of ridiculous,” Cole said before adding “it’s better to just stay quiet and accept.”
Cole’s LinkedIn page lists him as an Executive Officer within the agency’s Countermeasures Initiatives, which plays a critical role in ensuring that drugs, vaccines, and other measures to counter infectious diseases and viruses are safe. He made these revelations on a hidden camera to an undercover Project Veritas reporter.
A spokesperson for FDA issued a statement yesterday saying, “The person purportedly in the video does not work on vaccine matters and does not represent the views of the FDA.”
This statement appears to contradict a phone call released Wednesday afternoon by Project Veritas wherein Cole reiterated, during the conversation with Project Veritas Founder and CEO, James O’Keefe, that he is “a manager in the office that helps oversee the approval of the COVID vaccines for emergency approval.”
See also: Part One
Featured Video

The Search for Truth: Charlie Kirk’s Assassination One Year Later
or go to
Aletho News Archives – Video-Images
From the Archives
The 9/11 “Double-Cross” Conspiracy Theory
BY LAURENT GUYÉNOT • UNZ REVIEW • SEPTEMBER 6, 2022
Is it true that “9/11 was an inside job”? Yes, insofar as Israel is “inside” the U.S. But for the 9/11 truthers who have identified Israel as the main perpetrators, “9/11 was an inside job” is at best a half-truth, and at worst an integral part of the Zionist operation, like a secondary flag sewn as a lining under the false flag of Islamism. Victor Thorn (1963-2017) wrote in his book 9/11 made in Israel: The Plot Against America (2011): “In essence, the ‘9-11 truth movement’ was created prior to Sept. 11, 2001 as a means of suppressing news relating to Israeli complicity. . . . The slogan ‘9-11 was an inside job’ was quite possibly the greatest example of Israeli propaganda ever devised.” In milder terms, it is “controlled opposition”.
A genuine truth movement would have pointed to Israel as the prime suspect from the start. From day one, it was obvious who would benefit. … continue
Blog Roll
 Aletho News
- Europe’s mounting social chaos… chickens coming home to roost for proxy war against Russia
- US-Russia Diesel Deal Becomes Massive Defeat for Ukraine
- Hormuz and the Looming Economic Catastrophe
- Dhubab offensive, media blitz and the rapid unraveling of Saudi-backed coalition’s new gambit
- Putin Conveys to Trump Iran’s Vision on Possible Conflict Resolution – Kremlin
- The Search for Truth: Charlie Kirk’s Assassination One Year Later
- ‘Harsh reality’: Iran says France seeks monopoly on power and intimidation, not peace for all
- When Will This White House Madness End?
- Huckabee aide goes to ‘unusual lengths’ to portray ‘Israel’ positively
- Trump Announces Diesel Supply Deal With Putin Following Phone Call
- If Americans Knew
- Israeli forces kill another child in Gaza – Daily Update
- Gaza ceasefire exists in name only, say more than 100 organizations
- Nearly 2 Million in Gaza Need Urgent Shelter Assistance as Winter Looms: IOM Chief Warns
- Suppressing Palestinian resistance: US charity under fire for AI monitoring of Gaza classrooms
- Thousands Are Held in Israeli Torture Camps. This Is What Happens Inside
- Israel puts Gaza’s sick, injured, newborn in peril – Daily Update
- Report claimed Mark Levin used by Israeli government to influence Trump
- Over 2,000 Gazans have died awaiting medical evacuation amid Israel’s continued siege
- How a U.S. Diplomat Suppressed and Altered Reports Critical of Israel
- 5 Palestinians Die from Israeli Strikes in Gaza as Relentless Attacks Continue
- No Tricks Zone
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative

