The U.S. Supreme Court on Jan. 7 will convene a special session to hear oral arguments in two cases related to the Biden administration’s COVID vaccine mandates.
The two cases pertain to the mandates imposed on private businesses with 100 or more employees, and healthcare facilities participating in the Medicare or Medicaid programs.
The Supreme Court announced Dec. 22, 2021, it would hold a special session to hear both cases, following a series of decisions in lower courts that successively implemented and lifted injunctions against the two mandates.
In both disputes, the formal legal question at hand pertains to whether the federal government can continue enforcing the mandates while legal challenges against them work their way through the judicial system.
In the first instance, the 6th Circuit Court of Appeals, in a 2-1 ruling Dec. 17, 2021, lifted an injunction against Biden’s vaccine mandate for private businesses previously issued by the 5th Circuit Court of Appeals.
The mandate is now set to come into force on Jan. 4, though the Occupational Safety and Health Administration (OSHA) announced it will not begin enforcement of the rule until Jan. 10. The mandate, if and when it is enforced, will impact an estimated 84 million U.S. workers.
Two of these requests, one filed by a trade group and the other by a group of states led by Ohio, were formally accepted for oral argument.
These groups were joined by more than 170 Republican lawmakers who on Dec. 30, 2021, jointly filed an amicus brief with the Supreme Court arguing OSHA has no legal authority to impose a vaccine mandate on private businesses.
The Supreme Court, via Justice Brett Kavanaugh — whose jurisdiction includes the 6th Circuit — asked the Biden administration to submit a response to the legal challenges by Dec. 30, 2021.
In its response, Solicitor General Elizabeth B. Prelogar argued the Biden administration possesses the authority, under federal law, to impose the mandate and the Supreme Court should not block a program that will save thousands of lives.
The Supreme Court will also hear arguments pertaining to Biden’s vaccine mandate for healthcare workers at facilities that receive federal Medicare or Medicaid funding. This rule is estimated to impact more than 17 million workers across the U.S.
In this instance, it was the Biden administration that filed an emergency request with the court, requesting it be allowed to temporarily enforce the healthcare worker mandate, which is currently blocked in 24 states following a series of injunctions issued by lower courts.
A brief filed with the Supreme Court by 14 Republican-led states described the mandate as “plainly unlawful.”
The Centers for Medicare & Medicaid Service, which oversees the healthcare mandate, announced Dec. 29, 2021, it will begin enforcing the mandate in the 26 states where it is not blocked.
A modified enforcement timeline accompanied this announcement: Healthcare workers will now be required to receive the first dose of a COVID vaccine by Jan. 27, and the second dose by Feb. 28.
The Supreme Court’s move to hold oral arguments in deciding whether or not to issue an emergency stay is considered unusual. Typically, such cases are placed on the “shadow docket” and are decided without a full briefing or a presentation of oral arguments.
In this instance though, the Supreme Court may seek to alleviate the uncertainty which exists among employers and workers who remain unsure as to whether they are subject to a mandate or not.
It remains unclear whether a decision by the Supreme Court to uphold the injunctions against the healthcare worker mandate will impact all 50 states or only the 24 where the mandate is currently blocked.
Any emergency stay issued by the Supreme Court would not constitute a final ruling regarding either case, but would freeze the enforcement of the two mandates until legal challenges make their way through the federal appeals courts before, most likely, ending up in the Supreme Court for a full hearing.
Separate Biden administration mandates pertaining to such categories as federal contractors and military personnel also have been challenged legally.
In the most recent such example, Judge James “Wesley” Hendrix of the U.S. District Court for the Northern District of Texas ruled against a mask and vaccine mandate for participants in federal Head Start programs. The rules were set to take effect by the end of January.
Texas Attorney General Ken Paxton described the ruling as “a win for the children of Texas.”
However, the Supreme Court will not examine any of these other Biden administration mandates in the Jan. 7 special session.
While the Supreme Court previously rejected requests for emergency stays against state-level vaccine mandates, the court is also viewed as one that is skeptical of the power of federal agencies to issue mandates relating to COVID countermeasures.
This stance was evident, for instance, when the court lifted a moratorium on evictions imposed by the Centers for Disease Control and Prevention, on the basis it was outside the agency’s authority.
Notably, a well-known Supreme Court decision from 1905, Jacobsen v. Massachusetts, which, according to proponents of vaccine mandates, sets a legal precedent for their legality, actually pertains to state-level mandates.
This argument was made by the state of Arizona in its lawsuit against the OSHA mandate, as previously reported by The Defender.
The lack of a federal-level precedent may therefore weigh into the justices’ decision.
Michael Nevradakis, Ph.D., is an independent journalist and researcher based in Athens, Greece.
Back in October, I shared the story of the brave Dr. Patricia Lee, a fully vaccinated intensive care unit physician and surgeon, who stepped forward after witnessing numerous serious injuries in her patients following COVID-19 vaccination.
Since that story was published, Dr. Lee had a Zoom meeting with six federal health officials, including Dr. Peter Marks of the FDA and Dr. Tom Shimabukuro of the CDC. The meeting left Dr. Lee more frustrated than she had been prior to the meeting – the officials had no interest in the specific harms she detailed, even after hearing the heartbreaking and traumatic stories that Dr. Lee shared about her individual patients. Without asking a single question or reviewing any of the relevant medical records, Dr. Lee was effectively told that COVID-19 vaccines did not cause these injuries in her patients.
Given the lack of interest in understanding the harm to her patients, Dr. Lee made only one request. She asked that both the FDA and the CDC publicly announce that physicians should not be retaliated against for advocating for their injured patients, so that they would not fear reporting injuries from COVID-19 vaccinations. The individuals in the meeting indicated that they welcomed those reports and that they view physicians as partners in monitoring safety. However, to date, no such public statement has been made, even after a follow-up letter was sent requesting just that. Nor has any other action been taken.
Dr. Lee is not willing to let this go – as a physician, she has an ethical duty to her patients. And so she has now reached out to the oversight committees in Congress. You can read her letter to these committees below highlighting the federal health authorities’ refusal to even recognize vaccine injuries, let alone address this serious issue and those whose lives have been devastated by these injuries. Hopefully these elected officials do the right thing:
there is some really interesting data coming out of ontario on vaccine efficacy (VE) and vaccine evasion from omicron.
it also seems to be being widely misinterpreted/misread, so i want to put a paw in here and opine.
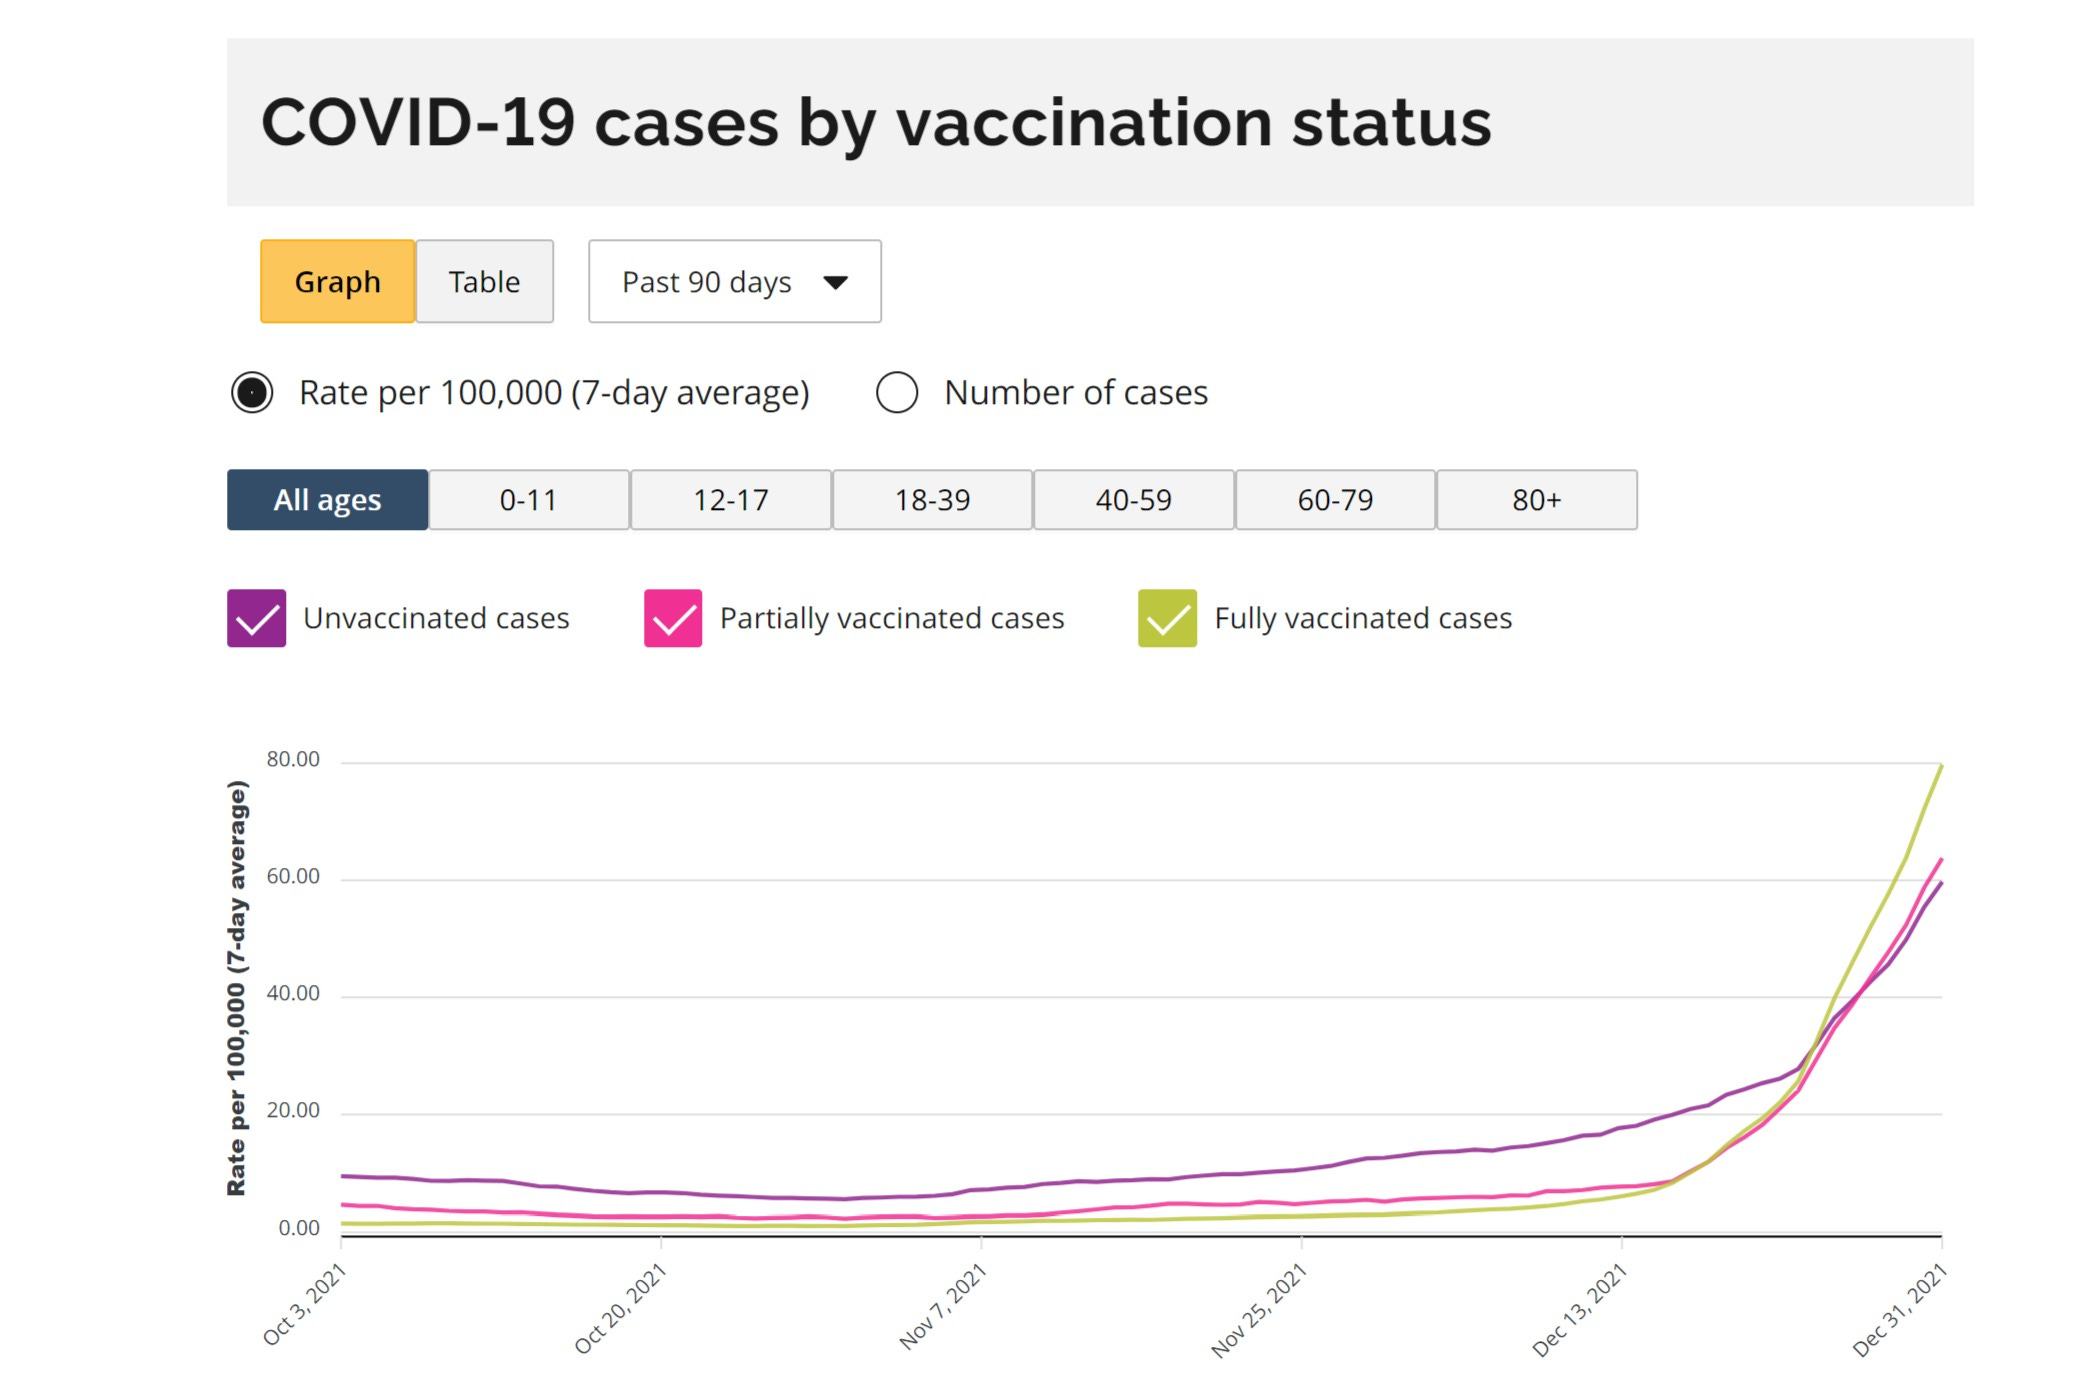
this is the key chart. (generated from the ontario gov’t website HERE)
and it shows something incredibly interesting. it shows vaccines working to stop cases until mid december and then suddenly inverting. this is presumably due to omicron.
vaccination just fell to a -33% VE for cases and this looks to be worsening rapidly, likely because of a rise in omicron prevalence.
this is consistent with not just vaccine escape, but vaccine driven acceleration.
the vaccinated are getting covid at higher rates than the unvaxxed and that rate looks to be increasing rapidly as omi gains viral share.
many are denying this and calling it a simpson’s paradox (SP) where each subgroup is actually showing strong VE but where the way they aggregate causes the net figure to invert and imply an erroneous relationship that does not actually pertain. such things have been common in covid data.
i think this claim is incorrect.
firstly, if this is an SP, then why did that not manifest before? why did the relationship for case reduction invert so suddenly? it was certainly not a massive, sudden change in who was vaccinated.
this confusion has been greatly amplified by the website itself. when you select for any given age cohort, it shows positive VE for cases. this seems to be an open and shut case for this being an SP.
but it’s not. such claims contain a severe error. can you spot it?
look closely at the dates. see where they end?
all the age cohorted data ends in october.
the same is true of the data in the table above. it’s full blown apples and oranges. there seems to be no post october age delineated data in this system at all.
but the change in vaccine efficacy pattern did not occur until mid decemeber. so, this is an irrelevant comparison to the current data and current situation. it actually agrees with the first chart.
whether this is just carelessness or sloth on the part the ontario health agencies or a subtle and cunning manipulation is anyone’s guess and i’m not going to wade into that. but i HAVE seen an awful lot of smart people miss this. (i missed it at first too) you simply do not expect to see the data truncate like that on the same graphing tool.
just one more cautionary tale on data handling…
ADDENDUM OF EXCELLENT GRAPHIC FROM GATOPAL™ ORWELL2024.
and an additional catch:
“The https://covid-19.ontario.ca/data says: “Due to technical difficulties, the case rate by vaccination status by age group is not available”.
We can lockdown the entire economy, but can’t fix a dashboard that would help showing what’s going on?”
this is what team work looks like and it’s how we make progress.
(END ADDENDUM)
but the conclusion here looks to be that this data (along with data from many other places) is consistent with omicron being not just a vaccine escaping variant, but one that is actually vaccine enabled.
if it was just escape, we’d see parity with the unvaxxed. having it go strongly negative is a sign that the vaccine is making it worse either though OAS/antigenic fixation or some other mechanism.
the good news is that omicron looks mild. the bad news is that it increasingly looks like the variant that original antigenic sin (OAS) begot and this means that the vaccinated may be wide open for it in a way they would not have been had these programs not been rolled out. worse, they may NEVER be able to generate sound immunity because that’s what OAS…
this leads me to predict that the curves will continue to separate in ontario as omicron becomes more prevalent and that we’ll start seeing VE’s that look more like denmark.
will keep an eye on it (and hope they keep reporting the data).
A major study from the University of Oxford into risks of myocarditis (heart inflammation) following Covid vaccination has found the risk in males under 40 to be significantly higher than the risk of the condition following Covid infection.
The researchers found that while there were seven additional myocarditis events per million in the 28 days following COVID-19 infection (95% Confidence Interval (CI): 2, 11), there were 14 following an AstraZeneca second dose (CI: 8,17), 12 following a Pfizer second dose (CI: 1,7), 101 following a Moderna second dose (CI: 95,104), and 13 following a Pfizer third dose (CI: 7,15). These findings are depicted above. Most of these figures represent a doubling of the risk compared with infection. However, the Moderna second dose figure is a massive 14.4 times greater. The Moderna vaccine uses a similar mRNA technology to the Pfizer vaccine, but delivers a dose three times as large, which may partly explain the difference.
For females and for males over 40 the study found greater risk of myocarditis following infection than following vaccination. However, some have criticised the study for under-counting Covid infections by using positive tests rather than antibody surveys, which means the risk following infection may be exaggerated. Another criticism was the use of only two age bands – above and below 40 years – which may conceal elevated risks for younger age groups.
The study, which is a pre-print, is an update to an earlier study published in Nature earlier in December which used data up to August 24th. The update brings us up to November 15th, extends the age range down to 13 years from 16 years, and also includes results split by both sex and age (rather than just by sex and age separately) – the original study was especially criticised for omitting this breakdown, leading to allegations of concealing important findings for political purposes.
The authors note: “These findings have important implications for public health and vaccination policy.”
Indeed they do. In particular, given the low risk of Covid to males under 40, the extreme elevated risk of myocarditis from the Moderna vaccine means it ought to be suspended for use in males under 40 with immediate effect.
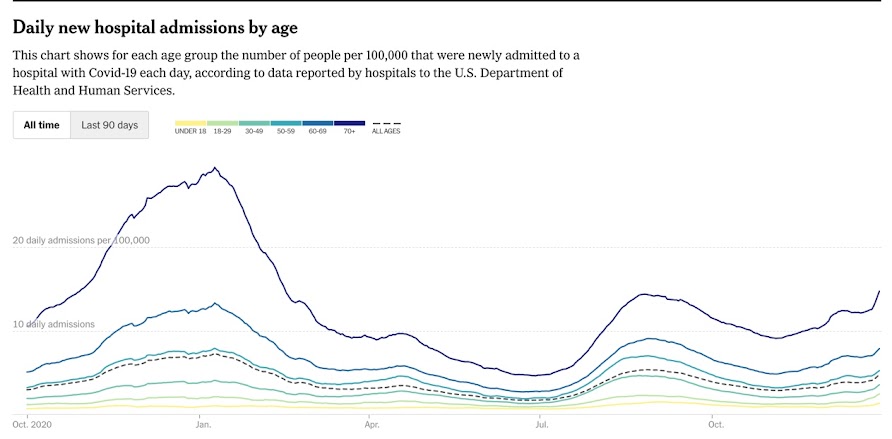
The yellow line represents pediatric hospitalizations over the past 15 months, per the NY Times. Yes, they did increase a bit, just like hospitalizations in every other age group, and the increase was proportional to that of the other age groups.
Cases rose much more dramatically.
Why are the media hollering? Because 80% of parents have been too smart to fall for the vaccinations for their 5-11 year olds. Peer pressure did not work as well on this age group, so parents have to be scared.
Please protect your children from this horribly damaging scam. See Robert Malone about how the benefits are marginal, while the risks are major for children.
As we come to the end of the second year in Covidia, I reflect on just how much the instigators of the entire scam have managed to reshape reality in an amazingly short timeframe, such that what was considered normal 12 months ago is now considered abnormal, and what was considered abnormal 12 months ago is now seen as normal.
For instance, had one predicted 12 months ago that after “vaccinating” the elderly and those considered vulnerable, which was the “route back to freedom”, the Johnson Regime and countless others around the world would:
Proceed to push the injection onto all adults
Move on to getting it into children
Make thousands jobless who do not wish to partake in the experiment
Begin the introduction of Vaccine Passports
Announce that the allegedly 95% effective products wane so quickly they’ll need to be taken every few months
Start talking about the possibility of mandatory jabs
Reintroduce the restrictions that these injections were supposed to do away with
… why such a person would have been called a Conspiracy Nut. Yet a year later the same person is called a Conspiracy Nut for opposing these very things they got called a Conspiracy Nut for predicting, but which are now reality.
There is something horribly ironic, and also deeply chilling about this. For it shows not only how easily manipulated so many people are, but also just how easy it has been for the Covidian Regimes to reshape reality such that millions have come to accept as normal the very things they would have dismissed just months earlier as the product of deranged minds.
The last two years has felt like people are living in parallel universes, so much so that it’s almost tempting to wonder whether Zuckerberg’s hideous Metaverse is already a thing, with millions having unwittingly entered it in early 2020 without noticing.
In the Metaverse, SARS-CoV-2 is a new Black Death that kills indiscriminately no matter what age. In the real world, it is a virus that has a 99.9% Survivability Rate, and there are effective early treatments available to the 0.1% for whom it might potentially be lethal.
In the Metaverse, Lockdowns of healthy people are how we’ve always dealt with outbreaks of transmissible illnesses. In the real world, other than a hastily ended five-day trial in Mexico during the 2009 Swine Flu outbreak, the quarantining of the healthy has never been done before the Chinese Communist Party implemented it in early 2020, to be copied all over the world by Governments ignoring their own long existing pandemic preparedness plans.
In the Metaverse, masks are about loving your neighbour because wearing them stops you passing on the virus you don’t have to others. In the real world, masks do not and cannot stop viral transmission, and thus they are a not a health aid, but a political and psychological tool of subjugation and dehumanisation, designed to humiliate and perpetuate fear.
In the Metaverse, a public health crisis caused by a virus has zero medical advice given out to people, but just a relentless barrage of talk about cases, hospitalisations and deaths, with all knowledge of effective early treatments ruthlessly suppressed. In the real world, a public health crisis caused by a virus would see Governments, health officials, and doctors recommending cheap and effective ways of boosting one’s immune system, such as Vitamin C and D, Zinc, Quercetin, sunshine and plenty of exercise and fresh air.
In the Metaverse, people who aren’t ill can spread the illness they don’t have, and so must take a test which cannot diagnose illness and which gives huge numbers of false positives, after which they must stay in their house for a prolonged period to stop the virus they don’t have from spreading. In the real world, if you’re well, you go about your daily life; if you have what are called “symptoms”, you stay home and rest.
In the Metaverse, the injection of billions of lipid nanoparticles containing mRNA, which has never been injected into people before, which tricks the cells into allowing it to enter, which then causes billions of cytotoxins to be produced in cells throughout every organ, and for which the manufacturers have indemnity but no proper safety data, is hailed as a saviour. In the real world, this is the most dangerous, reckless medical experiment ever performed on masses of people without their knowledge of what they are being given, and the long-term consequences could be unimaginably disastrous, as Professor Sucharit Bhakdi explains in this horrifying warning.
In the Metaverse, a product which doesn’t prevent infection, doesn’t provide immunity, and which requires top-ups every three months, is a vaccine, even if it needs the dictionary definition of what a vaccine is to be changed to accommodate it. In the real world, the Groucho Marx rule about ducks applies — if it looks, walks, and quacks like a duck then it probably is a duck. Thus if it doesn’t stop infection, doesn’t provide immunity, and wanes after 10 weeks, then it probably isn’t a vaccine.
In the Metaverse, willfully going along with abnormal, illegitimate and authoritarian rules & behaviours is the way back to normality and freedom. In the real world, willfully going along with abnormal, illegitimate and authoritarian rules & behaviours is about conditioning us to accept abnormality, the end of a law based society, and the long term loss of freedom.
In the Metaverse, bringing in Vaccine Passports for nightclubs and other large venues is about keeping people safe, and of course won’t be extended to other venues. In the real world, Vaccine Passports are a Trojan Horse, firstly to be extended into other venues of much smaller size (as has been the case in many European countries), but ultimately to facilitate the creation of a Digital ID Social Credit Hellhole where your every move and transaction can be tracked, you have credits not money, and freedom as we knew it is a thing of the past.
In the Metaverse, people who refuse to submit to the mass medical experiment only have themselves to blame if they find themselves excluded by law from entering certain venues, doing certain jobs, buying certain goods, and even being able to avail themselves of the basic necessities of life. In the real world, this unscientific, unholy, sinister apartheid system shows that we are edging eerily close to repeating the ugliness and depravity of certain 20th century regimes that we smugly told ourselves we were not capable of repeating, due to our apparent goodness.
It is baffling that people can view what’s going on so differently, but I would point out that all the views in the real world are derived from facts, data, reason, logic and historical examples, whereas all the views in the Metaverse are taken from Government and media propaganda.
One of the exasperating things in dealing with this is that whilst there are an endless potential number of lies that can be told, there is only one truth. And what the Government and media are very skillful at doing is layering lies upon lies upon lies, such that whilst the critical thinkers and data analysts are busy trying to debunk lie number one, lies number two, three, four and following are already being laid on that foundation so that by the time the original lie has been shown to be false, things have moved on and hardly anyone can remember, let alone care about the original claim.
However, the good news is that this is also the Achilles Heel of the Globalist’s narrative. Firstly, the more lies that are told, the harder it is to sustain the story because it can only be kept going by more lies, each of which tends to become increasingly blatant and absurd, such that even those who have been slumbering for two years begin to stir. For instance, if you try to assure the huge numbers of people that have had adverse events from the injection, or who know others that have suffered, that they must get the next one and it’s perfectly safe, clearly you are going to have your work cut out as stark reality highlights the lie in what is being told.
But the other part of this Achilles Heel is this: The Truth will win because The Truth must win. It is The Truth. It cannot not win. Attempting to suppress it is like trying to hold a cork under water. It will always be wanting to get to the surface, and as soon as you tire of holding it and release your grip, that’s what it will do. And so although these lies will continue, and although they will appear to prevail for some time to come, there is coming a time when they will be defeated because The Truth, not lies, is the ultimate reality:
“Truthful lips endure forever, but a lying tongue is but for a moment.” (Proverbs 12:19)
As we look forward to 2022, although we do not know the details of what is to come, because it is very clear that the goal of the Covidian Regimes is to get everybody injected with their mRNA witches’ brew over and over again by carrot or by stick, by hook or by crook, we can be absolutely sure there will be many more lies, many more difficulties, and much more wickedness. Yet we can also be equally sure that these lies will ultimately be defeated, because he who is The Truth (John 14:6) is guaranteed the victory (Revelation 17:14), and he will suffer their lies only so far, until such time as he destroys their unholy, totalitarian, anti-human agenda. There will be a Reckoning. Just make sure that you are on the right side when it comes.
Researchers working at Belgium’s Princess Elisabeth Polar Station in Antarctica have contracted Covid-19, even though all personnel have been inoculated and any new arrival has to follow rigorous safety protocols.
Two-thirds of the station’s staff of 25 have been infected with the coronavirus, Belgium’s polar secretariat confirmed to local media earlier this week. But how the virus could have reached the remote station, located some 220km (137 miles) from the Antarctic coast, remains a mystery.
“All those present have received two doses of vaccine, and one person has even received a booster shot,” said Alain Hubert, the facility’s executive operator and head of security measures. All staff members also have to undergo a series of PCR tests on their long journey to the station.
Those en route there take one PCR test in Belgium before leaving for South Africa and another five days after their arrival. They self-isolate for 10 days in Cape Town, then undergo two further tests: one before leaving for Antarctica and another five days after arriving at the station.
Nonetheless, even such strict control measures were apparently not stringent enough, as the first Covid-19 case was reported at the station in mid-December among a group of new arrivals. The person in question was immediately placed in isolation, but two others were soon revealed to have contracted the coronavirus as well.
All three infected researchers were evacuated on December 23, but this measure did not stop the virus from spreading further. A virologist contacted by the polar secretariat said the variant that has infected personnel at the station might be Omicron – the highly transmissible strain recently discovered in South Africa.
There are two emergency doctors and all the necessary equipment at the station to treat anyone who falls ill, according to the media. In the meantime, the polar secretariat has placed all personnel under quarantine and put a halt to any new arrivals until the Covid-19 cluster there dissipates. Explorers venturing on two new expeditions had been expected on January 12, but their arrival has now been delayed.
**Displays number of deaths and disabilities associated with each batch/lot number = indication of relative toxicity of one batch/lot compared to another
**No one currently knows the reason why some batches/lots are associated with excessive deaths, disabilities and adverse reactions (up to 50 x). Until we do know, it is best to be cautious
**[“Batch-code” = “Lot Number” = the number they write on your vaccination card.]
All data is sourced from VAERS, a public database of over 700,000 adverse reaction reports for Moderna, Pfizer and Janssen Covid 19 vaccines in the USA.
Our intention is to present the VAERS data in an accessible and unadulterated form, that can be easily verified using the links below
I haven’t written about this because some people who I rely on for advice believe that there are too many unknowns to make a determination as to whether increased adverse event reports are due to a bad “batch” or a bad “vial” or something else.
The unknowns include:
were certain sites just reporting more reliably so any vials sent there would appear more dangerous?
how many vials are in a particular lot?
where did all the vials of a given lot go?
could there have a been a problem in transit?
could there have been a problem with storage?
if a vial is not kept at the proper temperature, could it become dangerous?
…
The inability for anyone to analyze these vials as well as the lack of transparency about each batch makes finding the answer to these questions very difficult.
In this talk delivered in Fresno, California, Dr. McCullough delivers one of his best lectures to date, discussing Covid-19, vaccines, SARS-CoV-2, spike proteins, Covid-19 home treatments, censorship, and Prof. Mattias Desmet’s theories about mass formation psychosis, among many other topics.
Dr. McCullough summarizes the lecture as follows:
* COVID pandemic is a global disaster
* Pathophysiology is complex—not amenable to single-drug treatment
* The prehospital phase is the therapeutic opportunity
* Early ambulatory therapy with a sequenced, multi-drug regimen is supported by available sources of evidence and has a positive benefit-to-risk profile
* Reduces the risk for hospitalization and death
* More safely temporize to close the crisis with herd immunity
* COVID-19 genetic vaccines
* Unfavorable safety profile
* Protection not sufficiently complete or durable
* Censorship and reprisal are working to crush freedom of speech, scientific discourse and medical progress
(no, this has nothing to do with the american koch brothers. it’s a common name and this is a quasi-government health agency.)
data such as this is easy to misinterpret and nearly everyone is doing it incorrectly, so i’d like to walk through why, counter to what many are claiming, this data actually shows that boosters have negative VE (vaccine efficacy).
caveat: this is a small and likely incomplete societal dataset. the sample size is possibly large enough to give us a sense of outcomes, but as with all societal data, it’s difficult to know what bias may be injected by self selection for testing and for vaccination. error bars are likely meaningful.
but we work with what we have, not what we would prefer, so let’s take a look:
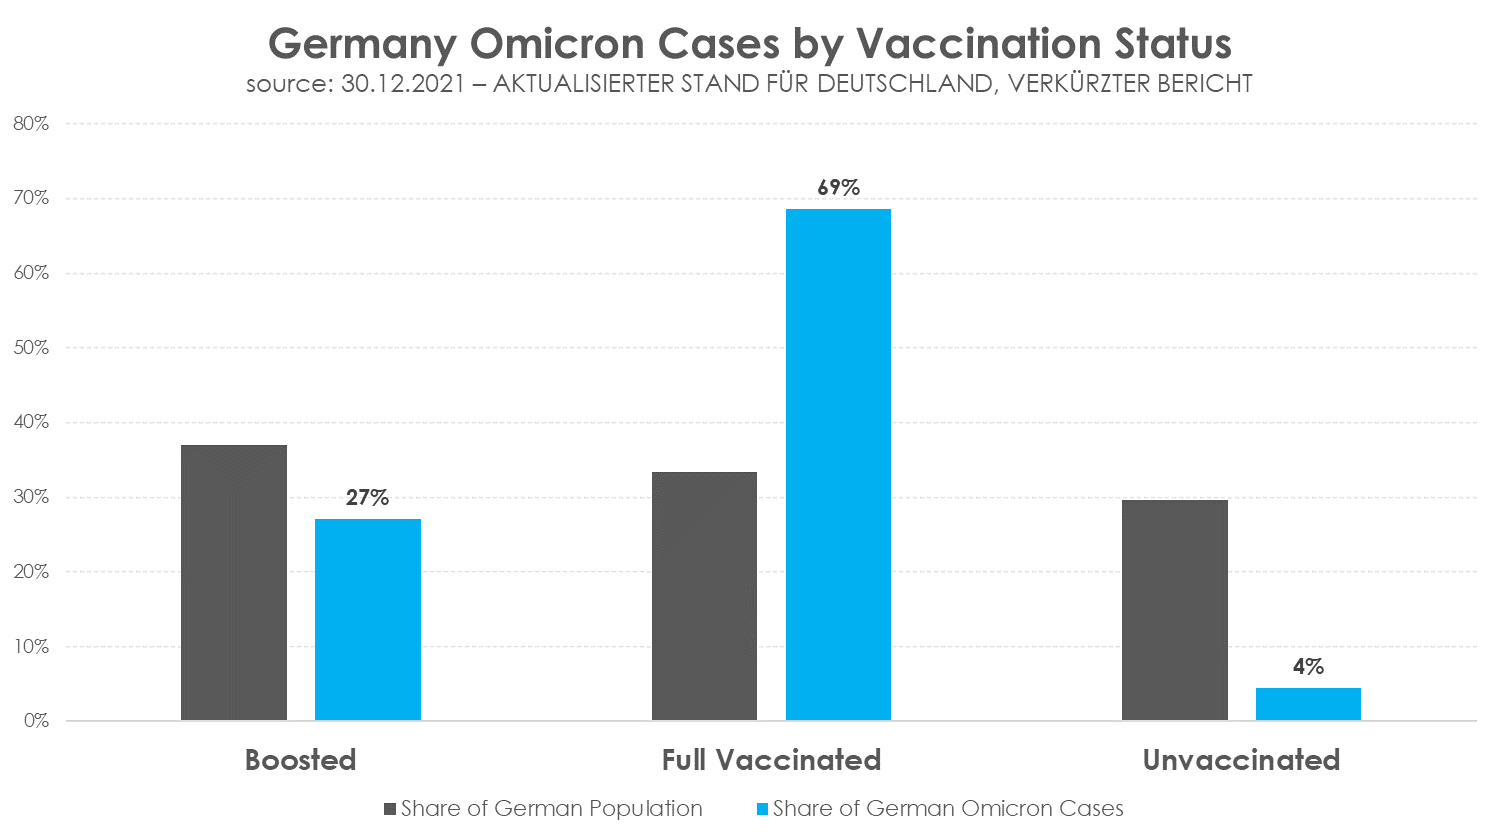
– 4020, ergo 95,58 % vollständig Geimpfte (1137 davon geboostert) – 186 Ungeimpfte (4,42 %)
4020 cases with 2 or more doses of vaccine, 1137 of them with boosters.
186 cases in the unvaccinated.
(unfortunately, there is no breakout for 1 dose only, so i’m presuming that group has been included in “unvaccinated”)
germany is 70.5% “full vaccinated.” (per OWID) thus, by the definitions this report uses, it is 29.5% unvaccinated.
it is 38.2% boosted as of 12/30/21. it’s not clear to me if this study is using that figure or only counting as boosted those who got their booster more than 14 days ago (as many seem to count it). if this is so, the number drops to 29.3%. i will look at it both ways to try to create some bookends for the range. (if anyone can clarify, i’d be grateful)
to see what is happening more granularly, we first need to regroup the terms:
from this one can see that the 3 groups are actually fairly similar in size, but quite divergent in outcomes.
many seem to presume that because cases in the boosted are a lower percentage of overall cases than the boosted are of the overall population that this shows vaccine efficacy.
this is not, however, correct as can be readily seen once we adjust this data to a per capita level.
that data looks like this (using 83.2mm for german population)
and this makes the issue obvious.
to calculate VE, we need to compare the vaccinated cohorts to the unvaccinated. that’s the control group. there are probably some pretty significant error bars here, but this outcome is STARK. the risk ratios for all vaccinated groups are far, far higher than control.
boosting does seem to lead to a 2/3 risk reduction vs just being double vaxxed but still leaves one at 4.7X the risk of the unvaccinated.
this risk ratio leads to VE figures that are, frankly, so bad that i suspect there must be some sort of bias here. this looks too extreme to be entirely plausible and far exceeds all other data i have seen.
one possible source of this issue is definitional. if the german study is using “boosted +14 days” as its definition, then the numbers change quite a bit as the size of the boosted group shrinks and the size of double vaxxed rises causing their risk rates to converge somewhat.
another possible source of contamination is the actual act of running a booster campaign during an outbreak.
the tendency toward transitory immune suppression created by mRNA vaccine administration is well documented.
the danes found it to be on the order of 40-100% increase in the likelihood of infection in the 2 weeks following administration (with 100% likely being a better proxy for genpop as they resemble HCW’s more than NH residents). this study was during a period of relatively low prevalence and with a less contagious variant than omicron. this needle could have moved quite a lot by now.
and all this piles up, so if you are doubling the risk of a group already showing increased risk due to vaccine escape/antigenic fixation/OAS the issue may become multiplicative. […]
Fully referenced facts about covid-19, provided by experts in the field, to help our readers make a realistic risk assessment.
“The only means to fight the plague is honesty.” (Albert Camus, 1947)
Overview
Lethality: According to the latest immunological studies, the overall infection fatality rate (IFR) of covid in the general population is about 0.1% to 0.5% in most countries, which is most closely comparable to the medium influenza pandemics of 1936, 1957 and 1968.
Vaccines: Real-world studies have shown a very high, but rapidly declining covid vaccine effectiveness against severe disease. Vaccination cannot prevent infection and transmission. Various severe and fatal vaccine adverse events have been reported, including in young people. A prior infection generally confers superior immunity compared to vaccination.
Treatment: For people at high risk or high exposure, early or prophylactic treatment is essential to prevent progression of the disease. According to numerous international studies, early outpatient treatment of covid may significantly reduce hospitalizations and deaths.
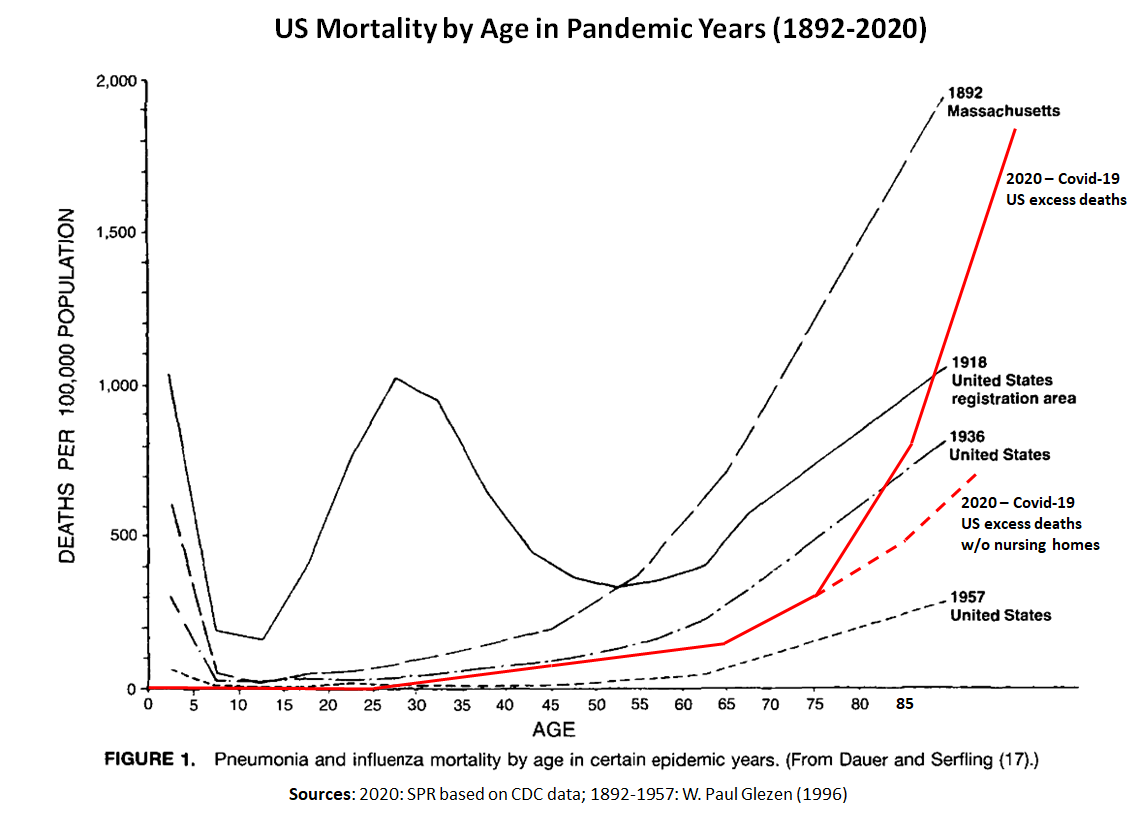
Age profile: The median age of covid deaths is over 80 years in most Western countries (78 in the US) and about 5% of the deceased had no serious preconditions. The age and risk profile of covid mortality is therefore comparable to normal mortality, but increases it proportionally.
Nursing homes: In many Western countries, about 50% of all covid deaths have occurred in nursing homes, which require targeted and humane protection. In some cases, care home residents died not from the coronavirus, but from weeks of stress and isolation.
Excess mortality: Overall, the pandemic has increased mortality by 5% to 25% in most Western countries. In some countries, up to 30% of additional deaths have been caused not by covid, but by indirect effects of the pandemic and lockdowns (including drug overdose deaths).
Antibodies: By the end of 2020, between 10% and 30% of the population in most Western countries had coronavirus antibodies. In India and some Latin American countries, coronavirus infection prevalence reached up to 75% by the summer of 2021.
Symptoms: About 30% of all infected persons show no symptoms. Overall, about 95% of all people develop at most mild or moderate symptoms and do not require hospitalization. Early outpatient treatment may significantly reduce hospitalizations.
Long covid: Up to 10% of symptomatic people experience post-acute or long covid, i.e. covid-related symptoms that last several weeks or months. Long covid may also affect younger and previously healthy people whose initial course of disease was rather mild.
Transmission: Indoor aerosols appear to be the main route of transmission of the coronavirus, while outdoor aerosols, droplets, as well as most object surfaces appear to play a minor role. The coronavirus season in the northern hemisphere usually lasts from November to April.
Masks: There is still little to no scientific evidence for the effectiveness of face masks in the general population, and the introduction of mandatory masks couldn’t contain or slow the epidemic in most countries. If used improperly, masks may increase the risk of infection.
Children and schools: In contrast to influenza, the risk of disease and transmission in children is rather low in the case of covid. There was and is therefore no medical reason for the closure of elementary schools or other measures specifically aimed at children.
Contact tracing: A WHO study of 2019 on measures against influenza pandemics concluded that from a medical perspective, contact tracing is “not recommended in any circumstances”. Contact tracing apps on cell phones have also proven ineffective in most countries.
Virus mutations: Similar to influenza viruses, mutations occur frequently in coronaviruses. Most of these mutations are insignificant, but some of them may increase the transmissibility, virulence or immune evasion of the virus to some extent.
Sweden: In Sweden, covid mortality without lockdown has been comparable to a strong influenza season and somewhat below the EU average. About 50% of Swedish deaths occurred in nursing homes and the median age of Swedish covid deaths was about 84 years.
Virus origin: The origin of the new coronavirus remains unknown, but the best evidence currently points to a covid-like pneumonia incident in a Chinese mine in 2012, whose virus samples were collected, stored and researched by the Wuhan Institute of Virology (WIV). Due to cooperations, some US labs may also have had access to these viruses.
Surveillance: NSA whistleblower Edward Snowden warned that the coronavirus pandemic may be used to expand global surveillance. Many governments have restricted fundamental rights of their citizens and announced plans to introduce digital biometric vaccine passports.
There are certain assumptions that are applied to anyone labelled a “conspiracy theorist”—and all of them are fallacies. Indeed, the term “conspiracy theory” is nothing more than a propaganda construct designed to silence debate and censor opinion on a range of subjects. Most particularly, it is used as a pejorative to marginalise and discredit whoever challenge the pronouncements and edicts of the State and of the Establishment—that is, the public and private entities that control the State and that profit from the State.
Those of us who have legitimate criticisms of government and its institutions and representatives, who are therefore labelled “conspiracy theorists,” face a dilemma. We can embrace the term and attempt to redefine it or we can reject it outright. Either way, it is evident that the people who weaponise the “conspiracy theory” label will continue to use it as long as it serves their propaganda purposes.
One of the most insidious aspects of the “conspiracy theory” fabrication is that the falsehoods associated with the term have been successfully seeded into the public’s consciousness. Often, propagandists need do no more than slap this label on the targeted opinion and the audience will immediately dismiss that viewpoint as a “lunatic conspiracy theory.” Sadly, this knee-jerk reaction is usually made absent any consideration or even familiarity with the evidence presented by that so-called “lunatic conspiracy theorist.”
This was the reason why “conspiracy theorist” label was created. The State and its propagandists do not want the public to even be aware of inconvenient evidence, let alone to examine it. The challenging evidence is buried under the “wild conspiracy theory” label, thereby signalling to the unsuspecting public that they should automatically reject all of the offered facts and evidence.
There are a number of components that collectively form the conspiracy theory canard. Let’s break them down. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.