More bad news on Covid vaccines and myocarditis in men under 40 – even as more colleges require booster shots
By Alex Berenson | Unreported Truths | January 5, 2022
A huge new study has found the risk of serious heart problems called myocarditis in men under 40 soars with each dose of a Covid mRNA vaccine – and is sharply higher than the risk from a coronavirus infection itself.
The findings call into sharp question the efforts by American colleges and universities to make their students receive booster shots before returning to school this January – especially since other studies have shown that the risk of post-vaccine myocarditis is concentrated not merely in men under 40 but in those aged 16-25.
The study, which British researchers released in late December, showed that the risk of myocarditis almost doubled after the first Pfizer shot in men under 40. Then it doubled again after the second and doubled again after the third – to almost eight times the baseline risk.

SOURCE: https://www.medrxiv.org/content/10.1101/2021.12.23.21268276v1.full.pdf
For the Moderna vaccine, the risks were even higher, reaching 16-fold after the second shot. (The risk of a third Moderna shot could not be calculated because too few people received it.)
Because each Moderna shot contains 100 micrograms of mRNA, while each Pfizer shot contains 30, the findings suggest strongly that the heart risks are dose-related and likely to continue to rise with each additional shot.
The study also contained some evidence that post-vaccine myocarditis might be more dangerous than other forms of myocarditis. It showed a trend towards higher death rates in people hospitalized for myocarditis after vaccination compared to other myocarditis cases.
Both myocarditis and pericarditis are forms of heart inflammation that can be very serious, even deadly. In an appendix, the researchers reported that 263 Britons were hospitalized for myocarditis within four weeks of receiving a Pfizer shot; of those, 38, or 14 percent, died. Only about 9 percent of people hospitalized for myocarditis that did not follow an mRNA vaccination died.
The researchers did not look at other potential cardiovascular risks, such as heart attacks or irregular heartbeats, although American and European databases of post-vaccine side effects contain many reports of those as well.
The findings come even as many colleges and universities – including public schools like the University of Massachusetts at Amherst, large private schools such as Syracuse University, and Ivy League institutions such as Princeton University – demand that their students receive a booster Covid shot before returning to campus.
For nearly all these students, an mRNA shot is the only viable option, as the Johnson & Johnson shot is no longer in common use.
These colleges are likely subjecting their male students to a risk of myocarditis and pericarditis, a related illness, that is much higher than the overall risk of Covid, which is vanishingly small for healthy teenagers and young adults. Many larger universities are likely to have multiple cases of male students hospitalized for myocarditis as a result of the mandates.
The massive study was is based on data from 42 million Britons who received at least one Covid vaccine dose, including roughly 22 million who received the mRNA vaccines.
About half were given the mRNA vaccines, while the rest received AstraZeneca’s DNA/AAV vaccine, which is not available in the United States. The AstraZeneca vaccine, which works similarly to the Johnson & Johnson vaccine, had a lower risk of myocarditis than mRNA vaccines.
There are now 4 myocarditis cases at Monte Vista
So it’s likely that 1 in 70 teenage boys are affected. That’s not rare. Why isn’t anyone speaking out about this? Is it fear? Of what?
By Steve Kirsch | January 5, 2022
I’ve written earlier about Monte Vista Christian school.
I just heard that there’s another case of myocarditis at the school, so now there are now 4 cases in 285 vaccinated boys (estimate), bringing the incidence rate to nearly 1 in 70, assuming all the cases are boys (285/4=71.25). This is not rare. This is a disaster.
Furthermore, these are just the cases we know about. There could be other cases that we simply don’t know about because the families decided not to tell anyone. And there could be sub-clinical cases where the damage is being done slowly over time.
Nikki Daniels, MVC’s Head of School, believes it is in the best interest of all parties to keep this information confidential so that nobody outside of the school will know. All the parents agree; they could speak out but choose not to say a word to anyone outside the community.
I disagree with that approach. There is nothing whatsoever to keep them from speaking out. They could save hundreds of thousands of lives worldwide if they spoke out and others followed their lead. It would destroy the credibility of the CDC and break people out of their hypnotic trance doing whatever the CDC says.
Instead, Monte Vista behaves just like every other school: keep your mouth shut and pretend that the kids aren’t being injured by the vaccine. Maybe it will all just go away if we don’t say anything.
This kind of behavior doesn’t save lives. It fuels the false narrative and costs lives.
Monte Vista is setting a horrible role model for students
Students learn that if you see people being injured or killed by your government, the right thing to do is to keep your mouth shut and look the other way.
I guess these are the new Christian values that they are teaching kids today.
Why RFK, Jr.’s Latest Book Didn’t Hit No. 1 on New York Times Best Sellers List
By Tony Lyons | The Defender | January 4, 2022
The New York Times reportedly bases a book’s position on its bestseller list on what they call a proprietary algorithm. Whatever their method, they favor specific books, ignore others, and rankings are often disconnected from how many copies of a book were actually sold to consumers.
You probably thought the New York Times Best Sellers list reflected book sales, but it doesn’t. It’s an engine of censorship, corruption and misinformation.
How do we know this? Follow the numbers.
Can a book outsell every other book in the U.S. and not be the #1 New York Times Bestseller? Sure. Is that perhaps a form of censorship? Yup.
Robert F. Kennedy, Jr.’s latest book, “The Real Anthony Fauci: Bill Gates, Big Pharma, and the Global War on Democracy and Public Health,” was published Nov. 16, 2021, by Skyhorse Publishing, Inc.
The New York Times reportedly bases a book’s position on its bestseller list on what it calls a proprietary algorithm. Whatever the method, the Times favor specific books, ignore others, and rankings are often bizarrely disconnected from how many copies of a book were actually sold to consumers.
As every publisher in America knows, you can’t make the Times’ list without selling a substantial number of books through Barnes & Noble, as well as “the independents.”
But what if Barnes & Noble decides to buy very few copies of a book based on its subject matter? And what if some independents exhibit similar bias by boycotting the book, refusing to carry it and telling customers that they won’t even special order the book?
That’s what happened in the case of Kennedy’s “The Real Anthony Fauci”: Barnes & Noble purchased an unusually small quantity, and they kept the book invisible in most of their stores.
Independent booksellers, such as the San Francisco-based City Lights, don’t list the book on their website, tell customers they “don’t carry the book” and refuse to order it, even upon request. These decisions have nothing to do with customer demand or interest in the book.
Perhaps because of the trend toward politicization by bookstores that report sales to the Times, Amazon now accounts for an increasingly large percentage of book sales in the U.S.
On the one hand, the Times’ list is inaccurate because it applies an outdated, and increasingly irrelevant, view of how books are sold. On the other hand, it appears the Times’ bestseller list intentionally misrepresents actual consumer sales and demand.
Let’s see that in action by using “The Real Anthony Fauci” as a case study. The book boldly challenges mainstream narratives. It’s a serious work that makes legitimate, meticulously researched arguments.
With more than 2,000 citations and references, the book asks readers to engage in dialog and debate. At the end of each chapter, there’s a QR code that links to a website containing updates, critiques and new information.
“The Real Anthony Fauci” was carefully vetted by doctors, scientists and lawyers. It has received substantial support from leading scientists, including at least one Nobel Prize-winning scientist.
This type of book cannot possibly be what any reasonable person has in mind when they seek to protect the public from “misinformation.”
Kennedy’s tour de force resonates so strongly with the American public that, despite epic censorship, “The Real Anthony Fauci” is one of the bestselling books in America.
It has achieved this status despite a total media blackout. There hasn’t been a single review in a major newspaper, online platforms have rejected advertising — some calling it “misinformation” before anyone could actually have read it — and bookstores are boycotting it.
In the past, people perused the New York Times Best Sellers list because they believed it represented an honest account of what people across the country were reading.
Today, alas, the New York Times Best Sellers list represents a political point of view and has become a way to encourage Times readers to buy and read books that the newspaper owners approve of — and to avoid books they don’t approve of.
The playbook from major newspapers and other media outlets is transparent: Attack the author, ignore the book.
In Kennedy’s case, the hit pieces have come from Town & Country, The New York Post, Vanity Fair, The Associated Press and others. (The Times hasn’t reviewed the book, of course, but describes it as a new book by an “anti-vaxxer.”)
Again, despite the epic censorship, there has been enormous grassroots demand for this book, and it’s burst through the blockade to hold the #1 spot on Amazon Charts and also become the #1 USA Today, #1 Publishers Weekly, and #1 Wall Street Journal bestseller.
The New York Times, however, listed it at #7 in the first week and #8 in the second. That must mean the book sold fewer copies than the books with higher rankings on the list, right? Wrong.
Few people ever see the actual numbers of books sold, so let’s break that tradition and share it all: The week Kennedy’s book was ranked #7 by the Times, it sold more than 92,000 hardcover copies.
That’s four-and-a-half times as many copies as two of the books ranked ahead of “The Real Anthony Fauci,” and more than double the average of all the books ranked ahead of it.
The fact is no book anywhere on the list sold more copies than “The Real Anthony Fauci.” (The book that earned the coveted #1 slot was the Times’ own “1619 Project,” which sold thousands fewer copies than Kennedy’s book.)
New York Times Best Sellers List
Nov. 21, 2021 (Reported Dec. 5)
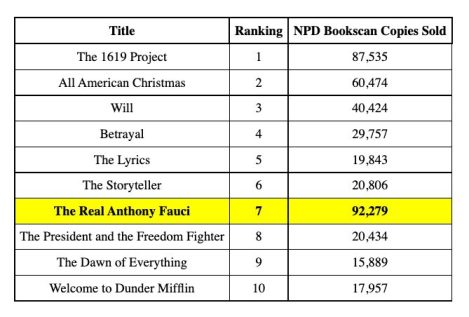
The week after that, the Times again placed the “1619 Project” in the #1 position, as if it had sold the most books, even though it undersold Kennedy’s book by more than 20%.
And they moved “The Real Anthony Fauci” down to the #8 position — even though it outsold every other book on the list. It sold nearly three times as many copies as the book the Times listed as #3.
New York Times Best Sellers List
Nov. 28, 2021 (Reported Dec. 12)
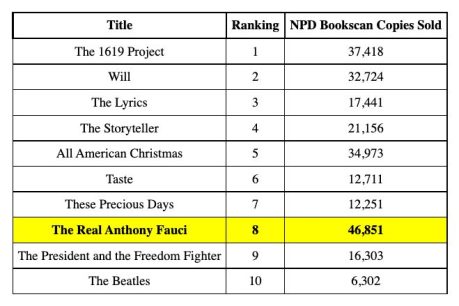
The Times obviously doesn’t want its readers to know how well Kennedy’s book is selling, likely hoping that’ll stymie demand.
But Americans are smarter than the New York Times gives them credit for — in less than four weeks, “The Real Anthony Fauci” sold more than 400,000 copies in all formats.
Americans clearly don’t like to be told what to think or what to read — or what not to read. Buying “The Real Anthony Fauci” has become a vote, sort of like a straw poll, against the increasingly insidious censorship in America.
Tony Lyons, president and publisher at Skyhorse publishing, and an attorney, was publisher at The Lyons Press between 1997 and 2004. He founded Skyhorse Publishing in 2006 and has been involved with every aspect of the book publishing process.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
BUY TODAY: Robert F. Kennedy, Jr.’s New Book — ‘The Real Anthony Fauci’
Reports of COVID Vaccine Injuries Pass 1 Million Mark, FDA Signs Off on Pfizer Booster for Kids 12 and Up
By Megan Redshaw | The Defender | January 3, 2022
The Centers for Disease Control and Prevention on Dec. 31, 2021, released new data showing a total of 1,000,229 reports of adverse events following COVID vaccines were submitted between Dec. 14, 2020, and Dec. 24, 2021, to the Vaccine Adverse Event Reporting System (VAERS). VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S.
The data included a total of 21,002 reports of deaths and 162,506 reports of serious injuries. Excluding “foreign reports” to VAERS, 709,084 adverse events, including 9,623 deaths and 62,069 serious injuries, were reported in the U.S. between Dec. 14, 2020, and Dec. 24, 2021.
Foreign reports are reports received by U.S. manufacturers from their foreign subsidiaries. Under U.S. Food and Drug Administration (FDA) regulations, if a manufacturer is notified of a foreign case report that describes an event that is both serious and does not appear on the product’s labeling, the manufacturer is required to submit the report to VAERS.
Of the 9,623 U.S. deaths reported as of Dec. 24, 20% occurred within 24 hours of vaccination, 25% occurred within 48 hours of vaccination and 61% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 499.7 million COVID vaccine doses had been administered as of Dec. 23. This includes 291 million doses of Pfizer, 190 million doses of Moderna and 18 million doses of Johnson & Johnson (J&J).

Every Friday, VAERS publishes vaccine injury reports received as of a specified date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed. Historically, VAERS has been shown to report only 1% of actual vaccine adverse events.
U.S. VAERS data from Dec. 14, 2020, to Dec. 24, 2021, for 5- to 11-year-olds show:
- 5,706 adverse events, including 114 rated as serious and 2 reported deaths.
- 11 reports of myocarditis and pericarditis (heart inflammation).
- 14 reports of blood clotting disorders.
U.S. VAERS data from Dec. 14, 2020, to Dec. 24, 2021, for 12- to 17-year-olds show:
- 25,802 adverse events, including 1,506 rated as serious and 34 reported deaths.
The most recent death involves a previously healthy 15-year-old girl from Wisconsin (VAERS I.D. 1963633), who experienced a cerebral and intraventricular hemorrhage secondary to a ruptured aneurysm. She also tested positive for SARS-CoV-2 despite having been fully vaccinated.
- 61 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 96% of cases
attributed to Pfizer’s vaccine. - 579 reports of myocarditis and pericarditis with 568 cases attributed to Pfizer’s vaccine.
- 146 reports of blood clotting disorders, with all cases attributed to Pfizer.
U.S. VAERS data from Dec. 14, 2020, to Dec. 10, 2021, for all age groups combined, show:
- 19% of deaths were related to cardiac disorders.
- 54% of those who died were male, 41% were female and the remaining death reports did not include the gender of the deceased.
- The average age of death was 72.3.
- As of Dec. 24, 4,692 pregnant women reported adverse events related to COVID vaccines, including 1,487 reports of miscarriage or premature birth.
- Of the 3,358 cases of Bell’s Palsy reported, 51% were attributed to Pfizer vaccinations, 41% to Moderna and 8% to J&J.
- 815 reports of Guillain-Barré syndrome (GBS), with 41% of cases attributed to Pfizer, 29% to Moderna and 28% to J&J.
- 2,241 reports of anaphylaxis where the reaction was life-threatening, required treatment or resulted in death.
- 12,070 reports of blood clotting disorders in the U.S. Of those, 5,341 reports were attributed to Pfizer, 4,302 reports to Moderna and 2,275 reports to J&J.
- 3,405 cases of myocarditis and pericarditis with 2,379 cases attributed to Pfizer, 1,197 cases to Moderna and 152 cases to J&J’s COVID vaccine.
FDA clears Pfizer boosters for 12- to 15-year-olds, bypasses experts
The FDA today amended Emergency Use Authorization (EUA) for Pfizer’s COVID vaccine expanding eligibility for boosters to children 12 through 15 years of age.
The agency did not consult its expert panel of vaccine advisors, who in September, overwhelmingly rejected boosters for healthy people 16 and older.
The FDA also shortened the time for both adolescents and adults to receive a booster from six months to five months after receiving a second dose and authorized a third shot for immunocompromised children aged 5 to 11.
Dr. Peter Marks, director of the Center for Biologics Evaluation and Research at the FDA, said in a statement the agency made its decision because a third dose “may help provide better protection against both the Delta and Omicron variants.”
The FDA said it reviewed real-world data from Israel of more than 6,300 individuals 12- to 15-years-old who received a booster at least five months after their second Pfizer dose and found no serious safety concerns.
Likewise, additional data showed no problems giving anyone eligible for a Pfizer booster an extra dose at five months instead of six, the Associated Press reported.
The FDA said it will continue to review the information and communicate with the public if data emerges suggesting booster doses are needed for the younger pediatric population.
Pediatrician weighs in on FDA decision: children aren’t ‘mini-adults’
Dr. Michelle Perro, pediatrician and co-author of “What’s Making Our Children Sick,” disagreed with the FDA’s decision, pointing out that “children are not mini-adults.” In an email to The Defender, Perro said children’s rapid growth, quick cellular turnover and less efficient detoxification pathways are factors that must be considered whenever any new therapeutics are being introduced.
Perro said:
“This newest immunomodulating therapy, the mRNA inoculation, has already been shown to have produced multisystem negative health outcomes in children garnered from the CDC’s own database.”
Perro outlined five reasons she believes this “experimental therapy” must be immediately withdrawn:
- Gene-edited injectables have not been adequately studied in children as per Pfizer’s own data, where they meshed childrens’ and adults’ data together.
- The injection utilizes nanotechnology which is now part of the emerging technology in vaccinology research. These nanoparticles are so small in size they can cross the blood-brain barrier which can adversely affect our already fragile population of children.
- The mRNA itself is unstable and is thus encapsulated in a lipid biosphere comprised of a polyethylene glycol shell which in itself is toxic.
- The number of children suffering from already documented irreparable side effects from the inoculations, such as those occurring in their hearts (myocarditis), is not only unacceptable but immoral.
- Children’s healthcare providers are neither educated or proactive in diagnosing and treating the effects from this experimental therapy.
Perro questioned the FDA’s motives, given that children suffer nearly zero morbidity and mortality from COVID infections.
She also said the FDA is “veering from” its own historical stance.
“When previous true vaccines were introduced historically (rotavirus vaccine), after just a few cases of adversity, they were immediately withdrawn,” Perro told The Defender. “The FDA must adhere to its own historical position regarding their assigned task of the protection and oversight of our country’s greatest asset: our children.”
Fauci says hospitalization numbers for kids with COVID are overcounted
Dr. Anthony Fauci, director of the National Institute of Allergy and Infectious Diseases, in an interview on MSNBC, said statistics for hospitalizations among children with COVID are overcounted, making clear the distinction between children hospitalized with COVID and children hospitalized “because of COVID.”
Speaking to MSNBC’s Ayman Mohyeldin, who was filling in for Rachel Maddow on Dec. 29, about the rise in hospitalizations among children amid the Omicron variant, Fauci said the surge is due to two contributing factors — more children getting infected and the way COVID cases are counted.
“And what we mean by that — if a child goes in the hospital, they automatically get tested for COVID. And they get counted as a COVID-hospitalized individual,” Fauci said. “When in fact, they may go in for a broken leg or appendicitis or something like that. So it’s overcounting the number of children who are, quote, ‘hospitalized with COVID,’ as opposed to because of COVID.”
Covid passport microchip developer says chipping humans is happening “whether we like it or not”
By Ken Macon | Reclaim The Net | January 3, 2022
Towards the end of last year, tech start-up Dsruptive Subdermals announced a microchip installed under the skin that can be scanned to reveal Covid vaccination status.
The technology was criticized, with many calling it “invasive.”
In an interview with Express, the company’s managing director doubled down on the technology and told critics the technology was here to stay.
The technology is a pre-programmed and scannable implant about the size of a grain of rice. It stores the vaccination information, displaying a person’s Covid-19 vaccine passport when scanned.
Speaking to Express, Hannes Sjobald, the company’s managing director, said: “This technology exists and is used whether we like it or not.
“I am happy that it is brought into the public conversation.
“New technologies must be broadly debated and understood.
“Smart implants are a powerful health technology.
“That is what we are building at Dsruptive and our goal is to transform healthcare on a global scale.”
Sjobald said the technology makes the vaccine passports more “accessible.”
“This means it is always accessible for me or for anyone else, really, who wants to read me.
“For example, if I go to the movies or go to a shopping center, then people will be able to check my status even if I don’t have my phone.”
Related:
Supreme Court to Hold Special Session on Legal Challenges to Biden Vaccine Mandates
By Michael Nevradakis, Ph.D. | The Defender | January 3, 2022
The U.S. Supreme Court on Jan. 7 will convene a special session to hear oral arguments in two cases related to the Biden administration’s COVID vaccine mandates.
The two cases pertain to the mandates imposed on private businesses with 100 or more employees, and healthcare facilities participating in the Medicare or Medicaid programs.
The Supreme Court announced Dec. 22, 2021, it would hold a special session to hear both cases, following a series of decisions in lower courts that successively implemented and lifted injunctions against the two mandates.
In both disputes, the formal legal question at hand pertains to whether the federal government can continue enforcing the mandates while legal challenges against them work their way through the judicial system.
In the first instance, the 6th Circuit Court of Appeals, in a 2-1 ruling Dec. 17, 2021, lifted an injunction against Biden’s vaccine mandate for private businesses previously issued by the 5th Circuit Court of Appeals.
The mandate is now set to come into force on Jan. 4, though the Occupational Safety and Health Administration (OSHA) announced it will not begin enforcement of the rule until Jan. 10. The mandate, if and when it is enforced, will impact an estimated 84 million U.S. workers.
Immediately following the 6th Circuit Court ruling, 27 states and several business groups, companies and ministries submitted applications to the Supreme Court seeking an emergency stay.
Two of these requests, one filed by a trade group and the other by a group of states led by Ohio, were formally accepted for oral argument.
These groups were joined by more than 170 Republican lawmakers who on Dec. 30, 2021, jointly filed an amicus brief with the Supreme Court arguing OSHA has no legal authority to impose a vaccine mandate on private businesses.
The Supreme Court, via Justice Brett Kavanaugh — whose jurisdiction includes the 6th Circuit — asked the Biden administration to submit a response to the legal challenges by Dec. 30, 2021.
In its response, Solicitor General Elizabeth B. Prelogar argued the Biden administration possesses the authority, under federal law, to impose the mandate and the Supreme Court should not block a program that will save thousands of lives.
The Supreme Court will also hear arguments pertaining to Biden’s vaccine mandate for healthcare workers at facilities that receive federal Medicare or Medicaid funding. This rule is estimated to impact more than 17 million workers across the U.S.
In this instance, it was the Biden administration that filed an emergency request with the court, requesting it be allowed to temporarily enforce the healthcare worker mandate, which is currently blocked in 24 states following a series of injunctions issued by lower courts.
A brief filed with the Supreme Court by 14 Republican-led states described the mandate as “plainly unlawful.”
The Centers for Medicare & Medicaid Service, which oversees the healthcare mandate, announced Dec. 29, 2021, it will begin enforcing the mandate in the 26 states where it is not blocked.
A modified enforcement timeline accompanied this announcement: Healthcare workers will now be required to receive the first dose of a COVID vaccine by Jan. 27, and the second dose by Feb. 28.
The Supreme Court’s move to hold oral arguments in deciding whether or not to issue an emergency stay is considered unusual. Typically, such cases are placed on the “shadow docket” and are decided without a full briefing or a presentation of oral arguments.
In this instance though, the Supreme Court may seek to alleviate the uncertainty which exists among employers and workers who remain unsure as to whether they are subject to a mandate or not.
It remains unclear whether a decision by the Supreme Court to uphold the injunctions against the healthcare worker mandate will impact all 50 states or only the 24 where the mandate is currently blocked.
Any emergency stay issued by the Supreme Court would not constitute a final ruling regarding either case, but would freeze the enforcement of the two mandates until legal challenges make their way through the federal appeals courts before, most likely, ending up in the Supreme Court for a full hearing.
Separate Biden administration mandates pertaining to such categories as federal contractors and military personnel also have been challenged legally.
In the most recent such example, Judge James “Wesley” Hendrix of the U.S. District Court for the Northern District of Texas ruled against a mask and vaccine mandate for participants in federal Head Start programs. The rules were set to take effect by the end of January.
Texas Attorney General Ken Paxton described the ruling as “a win for the children of Texas.”
However, the Supreme Court will not examine any of these other Biden administration mandates in the Jan. 7 special session.
While the Supreme Court previously rejected requests for emergency stays against state-level vaccine mandates, the court is also viewed as one that is skeptical of the power of federal agencies to issue mandates relating to COVID countermeasures.
This stance was evident, for instance, when the court lifted a moratorium on evictions imposed by the Centers for Disease Control and Prevention, on the basis it was outside the agency’s authority.
Notably, a well-known Supreme Court decision from 1905, Jacobsen v. Massachusetts, which, according to proponents of vaccine mandates, sets a legal precedent for their legality, actually pertains to state-level mandates.
This argument was made by the state of Arizona in its lawsuit against the OSHA mandate, as previously reported by The Defender.
The lack of a federal-level precedent may therefore weigh into the justices’ decision.
Michael Nevradakis, Ph.D., is an independent journalist and researcher based in Athens, Greece.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Update On Physician Whistleblower Dr. Patricia Lee
Since pleas to CDC/FDA regarding serious COVID-19 vaccine injuries remain unaddressed, she has escalated her concerns to Congress
By Aaron Siri | Injecting Freedom | January 3, 2022
Back in October, I shared the story of the brave Dr. Patricia Lee, a fully vaccinated intensive care unit physician and surgeon, who stepped forward after witnessing numerous serious injuries in her patients following COVID-19 vaccination.
Since that story was published, Dr. Lee had a Zoom meeting with six federal health officials, including Dr. Peter Marks of the FDA and Dr. Tom Shimabukuro of the CDC. The meeting left Dr. Lee more frustrated than she had been prior to the meeting – the officials had no interest in the specific harms she detailed, even after hearing the heartbreaking and traumatic stories that Dr. Lee shared about her individual patients. Without asking a single question or reviewing any of the relevant medical records, Dr. Lee was effectively told that COVID-19 vaccines did not cause these injuries in her patients.
Given the lack of interest in understanding the harm to her patients, Dr. Lee made only one request. She asked that both the FDA and the CDC publicly announce that physicians should not be retaliated against for advocating for their injured patients, so that they would not fear reporting injuries from COVID-19 vaccinations. The individuals in the meeting indicated that they welcomed those reports and that they view physicians as partners in monitoring safety. However, to date, no such public statement has been made, even after a follow-up letter was sent requesting just that. Nor has any other action been taken.
Dr. Lee is not willing to let this go – as a physician, she has an ethical duty to her patients. And so she has now reached out to the oversight committees in Congress. You can read her letter to these committees below highlighting the federal health authorities’ refusal to even recognize vaccine injuries, let alone address this serious issue and those whose lives have been devastated by these injuries. Hopefully these elected officials do the right thing:

Vaccine evasion and an Original Antigenic Sin signal in Ontario
el gato malo – bad cattitude – january 2, 2022
there is some really interesting data coming out of ontario on vaccine efficacy (VE) and vaccine evasion from omicron.
it also seems to be being widely misinterpreted/misread, so i want to put a paw in here and opine.
this is the key chart. (generated from the ontario gov’t website HERE)
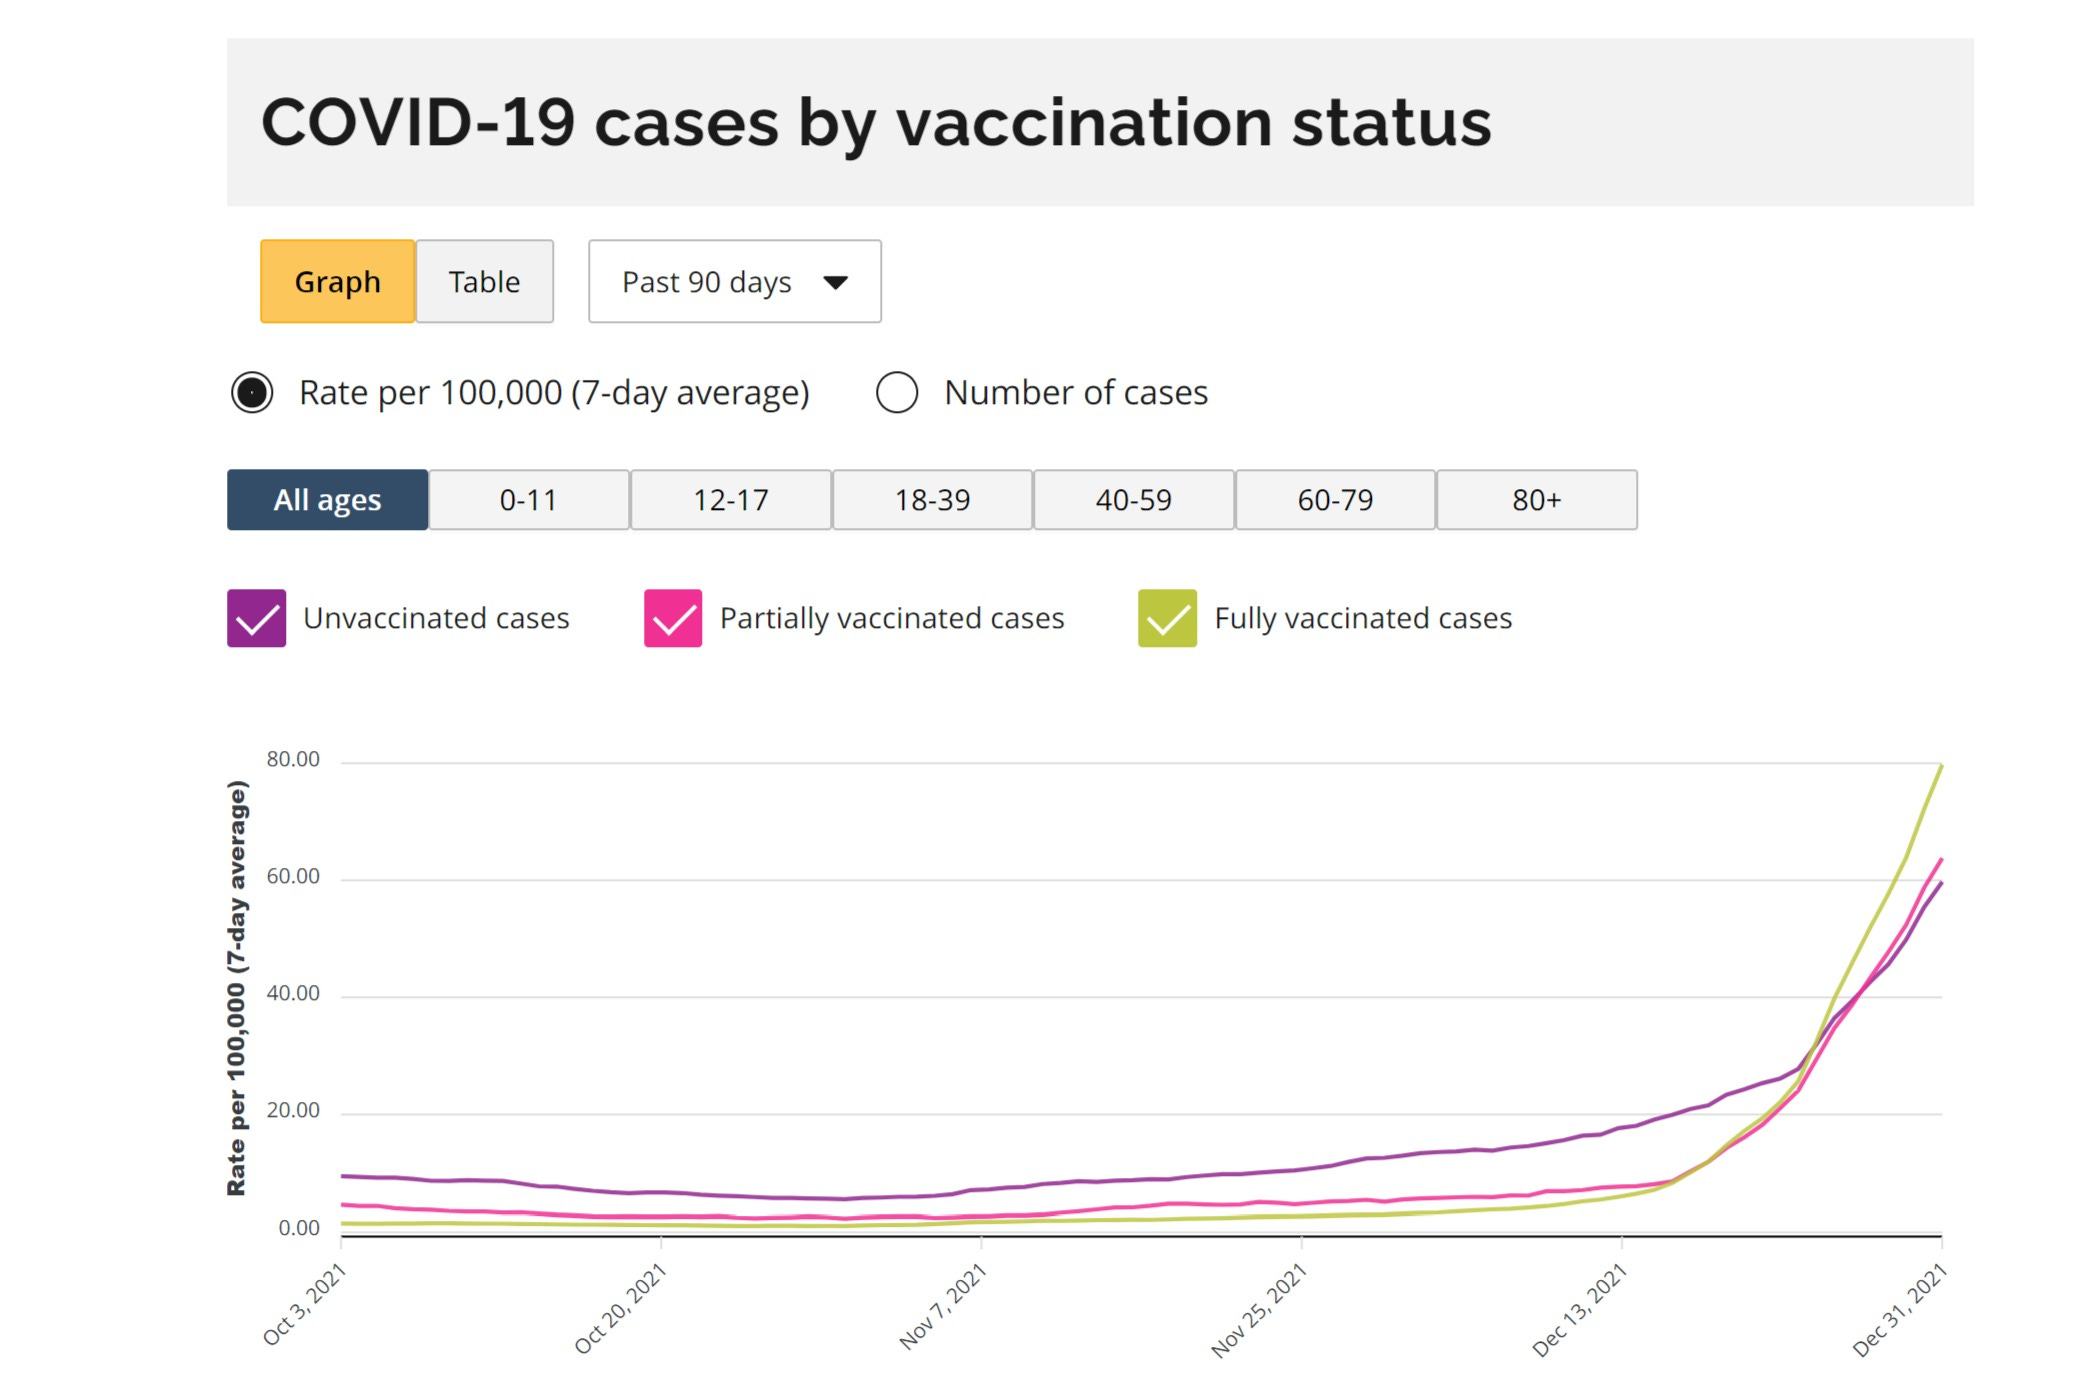
and it shows something incredibly interesting. it shows vaccines working to stop cases until mid december and then suddenly inverting. this is presumably due to omicron.
vaccination just fell to a -33% VE for cases and this looks to be worsening rapidly, likely because of a rise in omicron prevalence.
this is consistent with not just vaccine escape, but vaccine driven acceleration.
the vaccinated are getting covid at higher rates than the unvaxxed and that rate looks to be increasing rapidly as omi gains viral share.

many are denying this and calling it a simpson’s paradox (SP) where each subgroup is actually showing strong VE but where the way they aggregate causes the net figure to invert and imply an erroneous relationship that does not actually pertain. such things have been common in covid data.
i think this claim is incorrect.
firstly, if this is an SP, then why did that not manifest before? why did the relationship for case reduction invert so suddenly? it was certainly not a massive, sudden change in who was vaccinated.
this confusion has been greatly amplified by the website itself. when you select for any given age cohort, it shows positive VE for cases. this seems to be an open and shut case for this being an SP.
but it’s not. such claims contain a severe error. can you spot it?

look closely at the dates. see where they end?
all the age cohorted data ends in october.
the same is true of the data in the table above. it’s full blown apples and oranges. there seems to be no post october age delineated data in this system at all.
but the change in vaccine efficacy pattern did not occur until mid decemeber. so, this is an irrelevant comparison to the current data and current situation. it actually agrees with the first chart.
whether this is just carelessness or sloth on the part the ontario health agencies or a subtle and cunning manipulation is anyone’s guess and i’m not going to wade into that. but i HAVE seen an awful lot of smart people miss this. (i missed it at first too) you simply do not expect to see the data truncate like that on the same graphing tool.
just one more cautionary tale on data handling…
ADDENDUM OF EXCELLENT GRAPHIC FROM GATOPAL™ ORWELL2024.

and an additional catch:
“The https://covid-19.ontario.ca/data says: “Due to technical difficulties, the case rate by vaccination status by age group is not available”.
We can lockdown the entire economy, but can’t fix a dashboard that would help showing what’s going on?”
https://twitter.com/orwell2022/status/1477636960348946436?s=20
this is what team work looks like and it’s how we make progress.
(END ADDENDUM)
but the conclusion here looks to be that this data (along with data from many other places) is consistent with omicron being not just a vaccine escaping variant, but one that is actually vaccine enabled.
if it was just escape, we’d see parity with the unvaxxed. having it go strongly negative is a sign that the vaccine is making it worse either though OAS/antigenic fixation or some other mechanism.
See:
Is original antigenic sin starting to dominate covid?
the good news is that omicron looks mild. the bad news is that it increasingly looks like the variant that original antigenic sin (OAS) begot and this means that the vaccinated may be wide open for it in a way they would not have been had these programs not been rolled out. worse, they may NEVER be able to generate sound immunity because that’s what OAS…
and this data starts to get STARK when you isolate the omi variant alone.
this leads me to predict that the curves will continue to separate in ontario as omicron becomes more prevalent and that we’ll start seeing VE’s that look more like denmark.
will keep an eye on it (and hope they keep reporting the data).
Major Oxford study into vaccine side-effects finds myocarditis risk in younger males up to 14 times higher after vaccination than after infection

By Will Jones | The Daily Sceptic | December 31, 2021
A major study from the University of Oxford into risks of myocarditis (heart inflammation) following Covid vaccination has found the risk in males under 40 to be significantly higher than the risk of the condition following Covid infection.
The researchers found that while there were seven additional myocarditis events per million in the 28 days following COVID-19 infection (95% Confidence Interval (CI): 2, 11), there were 14 following an AstraZeneca second dose (CI: 8,17), 12 following a Pfizer second dose (CI: 1,7), 101 following a Moderna second dose (CI: 95,104), and 13 following a Pfizer third dose (CI: 7,15). These findings are depicted above. Most of these figures represent a doubling of the risk compared with infection. However, the Moderna second dose figure is a massive 14.4 times greater. The Moderna vaccine uses a similar mRNA technology to the Pfizer vaccine, but delivers a dose three times as large, which may partly explain the difference.
For females and for males over 40 the study found greater risk of myocarditis following infection than following vaccination. However, some have criticised the study for under-counting Covid infections by using positive tests rather than antibody surveys, which means the risk following infection may be exaggerated. Another criticism was the use of only two age bands – above and below 40 years – which may conceal elevated risks for younger age groups.
The study, which is a pre-print, is an update to an earlier study published in Nature earlier in December which used data up to August 24th. The update brings us up to November 15th, extends the age range down to 13 years from 16 years, and also includes results split by both sex and age (rather than just by sex and age separately) – the original study was especially criticised for omitting this breakdown, leading to allegations of concealing important findings for political purposes.
The authors note: “These findings have important implications for public health and vaccination policy.”
Indeed they do. In particular, given the low risk of Covid to males under 40, the extreme elevated risk of myocarditis from the Moderna vaccine means it ought to be suspended for use in males under 40 with immediate effect.
Image credit: Dr Tracy Høeg.
The skinny on pediatric hospitalizations
By Meryl Nass, MD | December 31, 2021
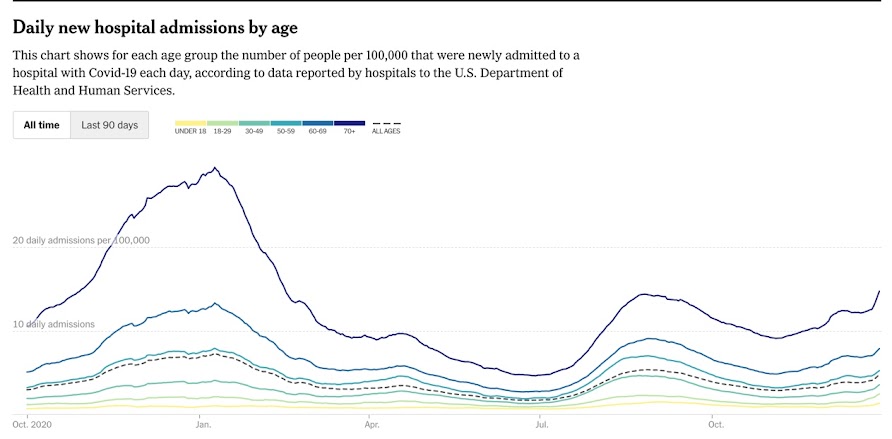
The yellow line represents pediatric hospitalizations over the past 15 months, per the NY Times. Yes, they did increase a bit, just like hospitalizations in every other age group, and the increase was proportional to that of the other age groups.
Cases rose much more dramatically.
Why are the media hollering? Because 80% of parents have been too smart to fall for the vaccinations for their 5-11 year olds. Peer pressure did not work as well on this age group, so parents have to be scared.
Please protect your children from this horribly damaging scam. See Robert Malone about how the benefits are marginal, while the risks are major for children.
Featured Video

The Failed Air War Over Vietnam
or go to
Aletho News Archives – Video-Images
From the Archives
USS Liberty Massacre: A Pivotal Moment in the Hostile Takeover of America
By Kevin Barrett | Crescent | Dhu al-Qa’dah 24, 1445
In corporate America, hostile takeovers are commonplace. They occur when an aggressor—a larger corporation or rich individuals—seizes control of a smaller corporation without asking permission.
What few recognize is that the United States itself has been subjected to a hostile takeover. Since the aggressor, the illegitimate settler colony known as “Israel,” is much smaller than the US, the takeover has necessarily been surreptitious.
As of June, 2024, Israel’s gradual takeover of the US has become obvious and undeniable—a proverbial “elephant in the living room.” … continue
Blog Roll
 Aletho News
- Leaders Condemn Ansarallah Attack on Saudi Arabia While Ignoring Illegal War Against Yemen
- Leaked: Britain’s Covert Iraqi Psyops Network
- Yemeni Armed Forces Warn Airlines Against Using Saudi Airports, Exempt Mecca and Medina
- Iran security chief says powers greater than US tried to conquer Iran but ended in ‘dustbin of history’
- Europe’s mounting social chaos… chickens coming home to roost for proxy war against Russia
- US-Russia Diesel Deal Becomes Massive Defeat for Ukraine
- Hormuz and the Looming Economic Catastrophe
- Dhubab offensive, media blitz and the rapid unraveling of Saudi-backed coalition’s new gambit
- Putin Conveys to Trump Iran’s Vision on Possible Conflict Resolution – Kremlin
- The Search for Truth: Charlie Kirk’s Assassination One Year Later
- If Americans Knew
- For three years, Israel has killed a child in Gaza every 71 minutes – Daily Update
- Israeli forces kill another child in Gaza – Daily Update
- Gaza ceasefire exists in name only, say more than 100 organizations
- Nearly 2 Million in Gaza Need Urgent Shelter Assistance as Winter Looms: IOM Chief Warns
- Suppressing Palestinian resistance: US charity under fire for AI monitoring of Gaza classrooms
- Thousands Are Held in Israeli Torture Camps. This Is What Happens Inside
- Israel puts Gaza’s sick, injured, newborn in peril – Daily Update
- Report claimed Mark Levin used by Israeli government to influence Trump
- Over 2,000 Gazans have died awaiting medical evacuation amid Israel’s continued siege
- How a U.S. Diplomat Suppressed and Altered Reports Critical of Israel
- No Tricks Zone
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI

