Why have we doctors been silent?

By Lucie Wilk | TCW Defending Freedom | November 15, 2021
AS an NHS hospital doctor, I have had a front-row seat as the drama of the coronavirus pandemic has unfolded. It has been a year and a half of confusion, frustration and anger for me as I’ve watched our profession drawn into complicity with what I anticipate will be regarded as one of the most egregious public health disasters in history.
I have watched as ‘the science’ has been presented on the national stage flanked by Union Jack flags as an unassailable truth. For something so apparently inviolable, it seems to shift and change disconcertingly from week to week, and for those of us looking beneath the pomp to the plain data, we see the rather unexciting (and unchanging) truth: the novel coronavirus SARS-CoV-2, as it turns out, has a much lower infection fatality rate than early predictions. It is less deadly than the seasonal flu in children. The Office for National Statistics has reported the mean age of a Covid-attributed death in the UK to be 80.3 years, slightly older than deaths from other causes (78.2 years over the comparable time period).
What has been most upsetting for me has been the unquestioning compliance from the medical community as increasingly draconian, non-evidence-based and destructive virus control measures have been implemented. Some of the overt corruption, financial conflict of interests and politicisation has been laid bare in editorials in prominent medical journals such as the BMJ. But the vast majority of doctors have had no interest in asking questions or looking further.
My concern over our professional passivity turned to alarm as our compliance required us to support the roll-out of an experimental vaccine to a trusting population.
Contrary to the basic tenets of evidence-based medicine, pronouncing an experimental medical intervention ‘safe and effective’ now does not seem to require any peer-reviewed evidence of safety or clinically meaningful efficacy. The vaccines have not been shown in clinical trials to reduce transmission, hospitalisation or death. The phase 3 trials are not over and the safety data is not complete; the earliest trials will run into 2023.
The consent form for the Covid-19 vaccine does not disclose its status as an unlicensed experimental product. The risks remain largely unknown, although it is becoming clear that the vaccine has resulted in death or injury in a rising number of healthy people. A growing number of vaccine-induced syndromes are being recognised, including immune thrombotic thrombocytopaenia, myocarditis and menstrual irregularities, among many others being published in the literature. At the time of writing, there have been more than 380,000 reports, 1.2million injuries and 1,700 fatalities submitted under the MHRA Yellow Card scheme.
The Prime Minister himself has communicated the latest evidence, that two doses of the vaccine do not stop one contracting the virus, nor do they stop person-to-person transmission, they merely reduce the severity of symptoms. Despite this, it is clear the public are being subjected to a relentless media campaign of shame and coercion, that they must take this experimental product ‘for the greater good’ lest they be viewed as selfish cowards. A vaccine passport is now likely to be rolled out under ‘Plan B’, which proposes to return unlawfully usurped fundamental human rights and freedoms to only the vaccinated. Workers in the care home sector have had their livelihoods tethered to their compliance with the vaccine mandates, and a recent announcement confirms that this will soon include NHS employees. Not only is there no scientific basis for these mandates, these coercive actions breach the Nuremberg Code, as does the unprecedented lack of animal safety data for a novel medical product. A betrayal of the Nuremberg Code constitutes a crime against humanity.
It does not end there. The campaign marches on, and now includes the vaccination of children against a disease that has a statistically negligible chance of harming them. In the world of evidence-based medicine we doctors must weigh risks and benefits, we must ensure the risk of harm is far exceeded by the potential for protection or cure. In this case, with no real risk to healthy children from the infection, any harm is utterly unjustifiable. And the risk of harm is very real and measurable. Vaccine-related myocarditis is now a recognised injury, the risk inversely proportionate to age. Although rare, myocarditis can be fatal, and fatality is more common in the younger population. For reasons that have nothing to do with health, and despite the JCVI advisory board concluding that the health benefits do not outweigh the risks to children, the government is advising that we administer a medicine that carries a risk of serious injury to children who are healthy and who have no significant risk from the disease it purports to protect them against.
Despite all this, and despite our training to look at scientific literature and data with a critical eye, the silence from the medical community in the UK has been deafening. Yet we are the ones who should be shouting all of this from the rooftops. This is a duty of care and an oath we have forgotten.
It is typically those of us most conditioned by the expectations of society, utterly obedient and deferent to authority, who gain entry to medicine. One can see the path: we were good, compliant children and then good, compliant students. Now we are good, compliant doctors. I’m beginning to understand that goodness is measured in a different way, and obedience is not a virtue.
Obedience is learned through fear, threat and intimidation; it is in fact trauma programming and achieved through small control gestures when we were young and helpless. Now we are adults but still operating under these childhood programmes of beliefs and fears. We still feel helpless and beholden to a higher authority. We still submit to an authoritative decree even when it overrides our inherent moral compass.
The horrors of the classic Milgram experiment demonstrated that we live in a deeply traumatised culture, and the same conditioning, in my view, has shaped the medical community and its silence.
Even on the occasion when my counter-narrative evidence cannot be denied by a colleague, the usual response is: ‘It’s coming from the government; our hands are tied.’ But the truth is that most of the time doctors don’t want to see the evidence; their subconscious has prevented them seeing that the parent-like authorities of government, Sage and the MHRA, upon which we project a childlike trust, might be misguided, corrupted or dishonest.
And so we comment to each other on all the changes we are witnessing months into the vaccine roll-out: the unseasonal surge in hospital admissions, the post-jab autoimmune conditions and coagulation disorders, the numbers of ‘double-jabbed’ patients admitted with severe Covid infection, the numbers of lives ruined by lockdown and other Covid control policies. I challenge any doctor to deny that all of this simply feels wrong. To avoid this uncomfortable, authentic, human feeling – important information that should be acted upon – we will reach for something rote. ‘Anecdote is not evidence’ and ‘association is not causation’ will be the justification for carrying on, no questions asked, even though most of the damaging control measures implemented from on high were not based on any evidence at all. Meanwhile, an already struggling NHS has been damaged beyond repair by many of these policies. We are overwhelmed by the demand that we cannot meet, and the complexity of the crisis feels far beyond just one hospital Trust. The locus of responsibility to investigate remains above us and we wait for someone with more authority to come round and make sense of it.
And as we remain silent, the destruction continues.
Most of us went into medicine for the right reasons: to help the vulnerable, to reduce suffering. I know my colleagues are kind and well-intentioned and that their faith in our unelected public health policymakers is the result of a lifetime of conditioning. For those of us who have looked at the data and see the truth, I understand the fear: the risk of non-conformity is immense; careers, reputations and livelihoods are at stake. I recognise an even larger threat: a threat to our chosen profession, our life purpose, the possibility that we have been following a false god in our honest intentions to help the ill. We are at a difficult crossroads, but the choice for me is clear.
Although I am not on the front line in the ‘fight’ against coronavirus, and have had nothing to do with the vaccine campaign, I feel complicit in this public deception. I can no longer hide within a system that has proved itself to be weak-willed and unwilling to stand against the irrevocable erosion of inalienable human rights and freedoms in the name of public health safety. It is past the time for us to grow up, stand up and speak out.
Here’s the real reason Comirnaty is not available
It’s all about liability. It will magically become available when the vaccine for children is fully approved, not before.
By Steve Kirsch | November 3, 2021
The reason Comirnaty isn’t available is because those shots would expose the company to liability since the fully-licensed product doesn’t have the liability waiver of the EUA product.
But once the Pfizer vaccine is fully approved in kids, then Pfizer gets liability waiver on all age groups due to a “feature” in federal law for child vaccines (NCVIA). At that time, they are done. They can market the COVID vaccine products under full approval for all age groups and face no liability when it kills or disables you.
This is why they are focused on the kids. This is why there is a reformulation at a 1/3 dose and they changed the buffer and the storage conditions (low temperatures not required). All of these will weaken the protection, but result in a safer vaccine (since it is ineffective).
But for the clinical trials on the 5-11 year olds, they did not use the formulation they approved in the meeting. This is known as bait and switch. So they used a more effective vaccine to show efficacy (in the trials they completed), then they get the FDA to approve the drug but with a change in formulation, then the product with the new buffer will go out to the public with the lower efficacy, but better safety. This is because they don’t want to jeopardize any adverse events happening until they are fully approved. So they basically use formula 1 for safety, get approval for formula 2 (safer, less effective), then roll out formula 2 under EUA.
They also arrange with the FDA and CDC to make sure no early treatment drugs get approved or recommended. This is why there is no movement on fluvoxamine, ivermectin, etc. since that would blow the EUA. Fluvoxamine is the best drug ever for COVID with a mortality reduction of 12X when taken early. It’s the best drug to date for COVID, but the CDC and NIH are deliberately burying it until the vaccines are fully approved. Then they’ll say, “ok, we have all the data.”
So at the end, Pfizer gets a fully approved vaccine with full liability protection. At that time, then the NIH can recognize other treatments.
This is how it is wired to go. Let’s be honest about it.
This is why nobody wants to debate our team about what is going on.
NIH Conflicted Internally Over Vaccine Mandates
By Dr. Joseph Mercola | November 14, 2021
Preliminary talk leading up to a live-streamed roundtable the National Institutes of Health has planned for December 1, 2021, indicates that the science isn’t settled within the agency itself when it comes to COVID-19 vaccine mandates.
According to The Wall Street Journal, a request for an ethics review by one of the NIH senior infectious disease researchers triggered the scheduling of four seminars on the issue, beginning with the December one.
“There’s a lot of debate within the NIH about whether [a vaccine mandate] is appropriate,” David Wendler, the senior NIH bioethicist who is in charge of planning the session, told The Wall Street Journal. “It’s an important, hot topic.”
One specialist who plans to argue against mandates is Dr. Matthew Memoli, who works with clinical studies in the NIH’s National Institute of Allergy and Infectious Diseases (NIAID). Memoli is not vaccinated for COVID-19. Memoli said his children have received their regular childhood vaccines — he simply thinks “the way we are using the [COVID] vaccines is wrong” and that the COVID-19 vaccine mandates are “extraordinarily problematic.”
His views are concerning for people like Timothy Schacker, vice dean for research and infectious-disease physician at the University of Minnesota Medical School. Schacker believes that bypassing the vaccine and trusting natural infection to be enough to prevent a COVID case is “a terrible idea.”
Coincidentally, the person who signed off for the seminar is Christine Grady, wife of the NIAID’s director, Dr. Anthony Fauci. Wendler reports to her.
How much does vaccine efficacy drop over 6 months? The VA and CDC duke it out
Whose data are better? Whose study was peer-reviewed? Who got published in Science magazine?
By Meryl Nass, MD | November 13, 2021
CDC is always finding ways to massage their data or use estimates instead of real numbers to “prove” the veracity of whatever narrative it is currently pushing. But I think CDC did not reckon with the VA system fighting back with the truth.
Here is the conclusion of CDC’s study of (selected) VA data regarding COVID vaccine efficacy over six months:
During February 1–August 6, 2021, vaccine effectiveness among U.S. veterans hospitalized at five Veterans Affairs Medical Centers was 87%. mRNA COVID-19 vaccines remain highly effective, including during periods of widespread circulation of the SARS-CoV-2 B.1.617.2 (Delta) variant. Vaccine effectiveness in preventing COVID-19–related hospitalization was 80% among adults aged ≥65 years compared with 95% among adults aged 18–64 years.
VA scientists pushed ahead and studied the entire VA database of 780,000 vaccinated beneficiaries from February to October, and published it in the US’ premier science journal, Science.
Their conclusions, drawn with only a few more weeks of data than CDC had, but using a more complete dataset that had not been cherrypicked, were shockingly different than what CDC’s braintrust had reported.
Here is how the VA authors characterized CDC’s overall COVID data collection:
The debate over boosters in the U.S. (24) has laid bare the limitations of its public health infrastructure: national data on vaccine breakthrough are inadequate. The CDC transitioned in May 2021 from monitoring all breakthrough infections to focus on identifying and investigating only hospitalized or fatal cases due to any cause, including causes not related to COVID-19 (25). Some data on vaccinations, infections, and deaths are collected through a patchwork of local health departments (10), but these data are frequently out of date and difficult to aggregate at the national level. Here, we address this gap and examine SARS-CoV-2 infection and deaths by vaccination status in 780,225 Veterans during the period February 1, 2021 to October 1, 2021, encompassing the emergence and dominance of the Delta variant in the U.S.
And their results?
“26,114 positive PCR tests occurred in 498,148 fully vaccinated Veterans–over 5% of vaccinated veterans got COVID despite their vaccinations.”
There are probably considerably more than 5% of vaccinated veterans who came down with COVID: those who chose to be tested closer to home than in a VA facility were not included.
In March, VE-I (vaccine efficacy against infection) was 86.4% for Janssen; 89.2% for Moderna; and 86.9% for Pfizer-BioNTech.
But six months later…
By September, VE-I had declined to 13.1% for Janssen; 58.0% for Moderna; and 43.3% for Pfizer-BioNTech.
This is consistent with Israel’s report in August that Pfizer vaccine efficacy had dropped to 39%. Israel vaccinated its population more speedily than the US and all other countries.
The VA found that protection against death was better than protection against infection, but also waned over time. And the VA authors then cited ten other studies who data were consistent with what the VA found:
Other U.S. studies (29–31), many conducted in large healthcare systems, similarly show declining VE-I as the Delta variant rose to dominance, with notable declines in older adults. For example, two studies conducted in Kaiser Permanente Southern California show VE-I decreased from 95% at 14-60 days to 79% at 151-180 days after vaccination for ages 18-64 years (29), and from 80% at 1 month to 43% at 5 months after vaccination for ages ≥65 years (31). Declines in protection against infection with Delta have been observed in Israel (16), the UK (20, 21), and Qatar (32, 33)…
It is not yet known whether breakthrough infections increase risk of long COVID (otherwise known as post-acute sequelae of COVID-19 or PASC), a constellation of debilitating and lingering symptoms following infection.
It seems we ought to know whether the vaccinated COVID patients are at higher risk, lower risk or the same risk of long COVID by now. But CDC isn’t telling.
It is remarkable that the VA was allowed to publish these honest data. Perhaps all those vaccine mandates for federal employees had something to do with it?
CDC Redefined Vaccine to Support Deficient Fake Vaccines Sold by Drug Companies
By Joel S. Hirschhorn | November 14, 2021
The CDC once was a federal agency that nearly everyone respected. That no longer is the case. Now there are many reasons why the CDC should be widely disrespected. Its latest debacle is how it changed the definition of vaccine.
Just imagine this: The entire push for COVID “vaccines” was based on a lie – they did not meet the official CDC definition of a vaccine. By doing this, the government could coerce the entire population to get the shot. Calling them “vaccines” was the biggest lie from Fauci and the key to drug companies making many billions of dollars.
Why would the government’s key public health agency change the definition of what a vaccine is in the midst of a pandemic? After millions of Americans have taken the shot? And millions more are being beaten into taking it for the first time and others to get booster shots.
Words matter
Here is the key point. It became widely recognized by medical experts and informed citizens that COVID vaccines clearly did not fit the official CDC vaccine definition. The CDC thought the answer was not to fix what was deficient with the COVID vaccines or stop their use by most people as so many medical experts advised. Their response was to change the vaccine definition to fit the so-called vaccines.
This was done so that vaccine mandates could keep getting pushed by the government. Of course, the COVID “vaccines” should be referred to as gene therapy products, even better than calling them experimental vaccines.
To see how corrupt this action by the CDC was, it is necessary to examine the details of the vaccine definition debacle.
Prior to September 1, 2021 here is how CDC defined vaccine:
A product that stimulates a person’s immune system to produce immunity to a specific disease, protecting the person from that disease. Vaccines are usually administered through needle injections, but can also be administered by mouth or sprayed into the nose.
This definition had been used for years and it makes sense. No expert or sensible citizen would find fault with it. But did it honestly apply to the COVID vaccines?
Then this is what the CDC concocted:
A preparation that is used to stimulate the body’s immune response against diseases. Vaccines are usually administered through needle injections, but some can be administered by mouth or sprayed into the nose.
Here is what the CDC also said:
Immunity: Protection from an infectious disease. If you are immune to a disease, you can be exposed to it without becoming infected.
Think about that last sentence: You can be exposed to COVID without being infected; but we know that is not true for fully vaccinated people who still get infected.
This is the key language in the original definition:
“stimulates a person’s immune system to produce immunity to a specific disease, protecting the person from that disease.”
How rational to invoke the purpose of a vaccine to stimulate an immune system to produce immunity to a specific disease that protects the recipient from that disease. Exactly what everyone for years thought was the correct way to think about a vaccine. People want permanent protection from the COVID infection disease.
But now the CDC has taken out the language referring to getting immunity for a specific disease and getting protection from that disease.
Now, COVID vaccines do not have to directly produce immunity. No, now they only have to stimulate the body’s immune system.
You don’t get immunity because COVID vaccines do not directly produce immunity. They do not directly kill the COVID virus. Vaccinated people can still have high viral loads and also transmit the virus to others. While some individuals may get some health benefits from COVID shots, they do not necessarily protect the entire population. This is why mandates to get everyone the shots really do not make sense from a public health perspective, that Dr. Paul Alexander has well substantiated.
Apparently, the only logical way to understand what the CDC has done is to accept the truth belatedly seen by the CDC that COVID vaccines do not, in fact, produce effective immunity for COVID infection and do not provide effective protection, once vaccinated, from that infection.
Much of the public surely does not yet know what the CDC has acknowledged for the COVID vaccines. Odds are that everyone who depends on mainstream media for good information about the pandemic has not been informed about what the CDC has done and its implications.
The new vaccine definition, if publicly known, would reduce public confidence in current COVID vaccines. You don’t have to be a medical expert to see how the new definition has been created to accommodate COVID shots.
In fact, these definition changes reflect what is now known about the limitations of the COVID vaccines.
Fully vaccinated people can still get COVID disease, referred to as breakthrough infections that, contrary to what the government says, can be very serious, often requiring hospitalization and sometimes causing death, as was the case for Colin Powell. Such serious effects have been well discussed by Dr. Günter Kampf. Other times, breakthrough infections greatly disrupt lives, as recently described by Madrigal, a strong proponent of COVID shots.
Moreover, the COVID vaccines are now widely known from considerable clinical evidence to lose their effectiveness typically in about six months. And even worse, they do not provide hardly any protection against variants like the delta variant. Same disease but from a different virus in terms of its complex genetic makeup. So, befitting the new CDC definition the COVID shots really do not have long lasting effective immunity to the specific COVID infection caused by all variants.
Elsewhere on the CDC website is a glossary of many terms; here is what is especially relevant to the debate about COVID vaccines:
Attenuated vaccine: A vaccine in which a live microbe is weakened (attenuated) through chemical or physical processes in order to produce an immune response without causing the severe effects of the disease. Attenuated vaccines currently licensed in the United States include measles, mumps, rubella, varicella, rotavirus, yellow fever, smallpox, and some formulations of influenza, and typhoid vaccines.
Most people would read this and find that it fits with what they think of as vaccines that have been routinely taken by most people, especially children. Clearly, COVID vaccines do not fit this definition. But seeing this established view of vaccines helps explain why so many people resist and reject the COVID shots. They are so fundamentally different than long accepted and used vaccines.
Natural immunity
One of the biggest pandemic scandals is that the government refuses to give full credit to natural immunity that people get from once being infected by the COVID virus. It should be officially recognized as equivalent to “vaccine” immunity.
The following CDC glossary definition is especially relevant:
Active immunity: The production of antibodies against a specific disease by the immune system. Active immunity can be acquired in two ways, either by contracting the disease or through vaccination. Active immunity is usually permanent, meaning an individual is protected from the disease for the duration of their lives.
This CDC definition of active immunity recognizes that you can get it by contracting the disease versus through vaccination. In other words, it recognizes what today is commonly called natural immunity achieved by once being infected by the COVID virus. And that such immunity is likely permanent and better than vaccine immunity, as recent clinical studies substantiate. But it also infers that active immunity obtained through vaccination is also permanent, which clearly is not the case for COVID shots, as evidenced by breakthrough infections.
Also note that it has recently been revealed that the CDC has not been able to provide any proof of at least one instance of an unvaccinated, naturally immune individual transmitting the COVID-19 virus to another individual.
And a new study found that almost 60 percent of the people with antibodies had no idea they had even had COVID at all. But they would have natural immunity. Quite consistent with the reality that most people suffer no significant health impacts from being infected with the COVID virus, regardless of all the fear mongering by Fauci and others.
Conclusions
To sum up, a close look at what the CDC has done lately reinforces the thinking of millions of people who have reservations and concerns about getting COVID genetic therapy shots that pose myriad adverse impacts and sometimes death.
There is a rational, science basis for thinking that the limited benefits of those shots do not adequately offset their risks. This is true for the vast majority of healthy people, especially children, who have extremely low risk from COVID infection for serious illness, hospitalization or death.
Mandates that do not recognize natural immunity are merely a sham tactic to make money for drug companies.
How interesting it would be, in the context of informed consent, if people were shown the original and new CDC vaccine definitions as a means to stimulate productive discussion with medical providers of COVID shots.
Dr. Joel S. Hirschhorn, author of Pandemic Blunder and many articles, podcasts and radio shows on the pandemic, worked on health issues for decades. As a full professor at the University of Wisconsin, Madison, he directed a medical research program between the colleges of engineering and medicine. As a senior official at the Congressional Office of Technology Assessment and the National Governors Association, he directed major studies on health-related subjects; he testified at over 50 US Senate and House hearings and authored hundreds of articles and op-ed articles in major newspapers. He has served as an executive volunteer at a major hospital for more than 10 years. He is a member of the Association of American Physicians and Surgeons, and America’s Frontline Doctors.
Biden Regime War on Humanity with Mass Destruction in Mind

By Stephen Lendman | November 14, 2021
If only what’s ongoing would end on awakening from a bad dream.
Horrors unleashed by Biden regime and complicit dark forces are horrifyingly real.
There’s no end of them in prospect without a second US revolution to accomplish what the first one failed to address when everything changed but stayed the same under new management.
If genocidist Bill Gates had dictatorial powers he likely craves, refuseniks unwilling to self-inflict harm through kill shots — and oppose masks that don’t protect and risk respiratory harm — would be criminalized.
Calling for punishing them, he wants truth and full disclosure about all things flu/covid banned by digital censorship, along with medical surveillance, simulated bioterrorism attacks he likely wants rehearsed ahead of launching the real things for greater mass-extermination than already.
Separately, the American Medical Association (AMA) promoter of medical tyranny in support of mandatory kill shots filed an amicus brief on Thursday with the 5th Circuit Court of Appeals in support of the draconian Biden regime mandate from hell.
The brief falsely called seasonal flu — deceptively called covid — a major public health threat, a bald-faced Big Lie.
It backs mandatory kill shots for everyone.
It lied claiming they’ll contain infections and transmission of the viral illness.
It lied saying kill shots will protect the jabbed and unjabbed alike.
It lied claiming they’re essential to protect US workers.
It lied saying they’re safe and effective.
It lied claiming that the vast majority of individuals with flu/covid are unjabbed.
The amicus brief was infested with beginning to end bald-faced Big Lies by an agency hostile to its stated mission of protecting health.
Along with US/Western dark forces, their anti-public health handmaidens, Pharma profiteer-pushers of toxic kill shots and MSM co-conspirators, the AMA is a mortal enemy of protecting and preserving what’s too precious to lose.
It supports policies intended to destroy health with unparalleled genocide in mind.
Flu/covid is easily treated and cured.
Yet the AMA opposes known safe and effective protocols for protection against contraction of flu/covid, along with obliterating outbreaks when occur in a few days.
When taken as directed, jabs irreversibly harm health.
The AMA supports kill shots with that objective in mind.
The pandemic it cited doesn’t exist — except for jabbed individuals.
It wants the health of young kids destroyed by mandatory kill shots.
It also wants US public health wrecked by mandating them for all doctors, nurses and other healthcare staff.
Numerous young/highly conditioned professional athletes in the US/West and elsewhere either collapsed and died from kill shots or became seriously ill and disabled.
Despite numbers continuing to rise, US/Western MSM suppressed what should be headline news.
Most athletes who perished or became seriously ill were diagnosed with heart-related issues.
What’s been unheard of in athletes and other young people pre-2020 is now at epidemic levels worldwide.
Numbers of young kids likely to die or fall seriously ill when mass-jabbing is fully underway should chill parents and others to denounce the practice.
Kill shots are designed to cause maximum destruction of public health.
Shunning them is crucial to protecting it.
SAN DIEGO COUNTY BOARD OF SUPERVISORS MEETING – Dr. Scot Youngblood defends the science
Dr. Scot Youngblood spoke to the San Diego county Board of Supervisors on November 2, using the CDC and Pfizer data to show the vaccine provides no net benefit.
Welsh Government can’t provide any evidence for vaccine passport effectiveness
By Didi Rankovic | Reclaim The Net | November 13, 2021
The Welsh Liberal Democrats continue their campaign against introduction of Covid Passes, calling attention to the fact that not even those in government who are pushing the controversial certificates are able to properly justify them.
On its site, the party noted that the Welsh government has admitted to not having any empirical evidence that introducing Covid passes helped stem the tide of coronavirus transmission in places of mass gatherings of people.
Naturally, the government response to a question on this subject didn’t put the evaluation of the effectiveness of Covid passes in quite so many words, but the opposition interpreted them to mean just that.
The scheme was launched on October 11, and a month later, the Liberal Democrats are quoting a reply they got to their letter about this issue sent to Health Minister Eluned Morgan by party leader Jane Dodd.
In it, Morgan says that too little time had elapsed since the rollout of Covid passes to be able to assess their effectiveness, but that there was “positive feedback” from stakeholders and users of the passes. And it seems the positive feedback has to do with subjective feelings, rather than, as the Liberal Democrats put it, hard evidence.
Covid pass, Morgan writes, has given those holding it “the confidence to attend venues and events, knowing everyone else is either fully vaccinated or has had a very recent negative test result.”
Commenting on this response, Dodd noted that laws with such a strong impact on people’s civil liberties must be justified by strong evidence. She also noted that her party was not opposed to efforts to curb Covid and associated harm, but insists that action taken to this end “must be proportional and based on an evidence-based strategy that has a clear outcome.”
Dodd went on to cite a leaked UK government document that showed Covid passes might even be harmful in terms of producing more infections as more people are gathering in smaller spaces – possibly under a false sense of security.
And even though Morgan cited positive feedback from “stakeholders,” the businesses affected by Covid passes continue to feel increased burden from the scheme, while not receiving financial aid to help them cope.
Lastly, Dodd urged the government to state a precise date when this policy, which she said was “introduced without sufficient evidence,” will come to an end.
New VAERS analysis reveals hundreds of serious adverse events that the CDC and FDA never told us about
Serious adverse events that are more elevated than myocarditis. New VAERS analysis by Albert Benavides blows the “safe and effective” narrative away.
By Steve Kirsch | November 9, 2021
The CDC and FDA have said the vaccines are “safe and effective.” They haven’t found any serious issues with the COVID vaccines. Zero. Zip. Nada. It was the DoD that found myocarditis.
The evidence in plain sight shows that they are either lying or incompetent. Or both. But of course, the medical community is never going to call them on this.
So that’s where our team of vaccine safety experts comes in; to reveal the truth about what is really going on.
In a brand new VAERS data analysis performed by our friend Albert Benavides (aka WelcomeTheEagle88), we found hundreds of serious adverse events that were completely missed by the CDC that should have been mentioned in the informed consent document that are given to patients. And we found over 200 symptoms that occur at a higher relative rate than myocarditis (relative to all previous vaccines over the last 5 years). All together, there were over 4,000 VAERS adverse event codes that were elevated by these vaccines by a factor of 10 or more over baseline that the CDC should have warned people about.
As of November 1, 2021, there have been more adverse events reported for the COVID vaccines than for all 70+ vaccines combined since they started tracking adverse events 30 years ago. That’s a stunning statistic, nobody can deny it, but nobody in the mainstream medical community (or mainstream media) seems to care much. It’s not even worth noting in passing. Wow.
Here’s what the evidence shows:
- The COVID vaccines are the most dangerous vaccines in human history. They are 800 times more deadly than the smallpox vaccine which was the previous record holder. The vaccines have killed over 150,000 Americans and permanently disabled even more. They don’t make sense for anyone of any age. The younger you are, the worse it gets. For kids, it is estimated that we kill 117 kids for every COVID death we prevent.
- The Pfizer 6 month trial showed the drug can save 1 life for every 22,000 people vaccinated. It also appeared from the trial that the drug killed more people than it saved (there were 20 deaths in the treatment group vs. 14 in placebo after unblinding). So we are “saving” fewer than 10,000 lives at the expense of over 150,000 deaths. In short, we kill 15 people to save 1. That’s incredibly stupid. But nobody in the Biden administration wants to meet with our team. They basically don’t want to hear the truth. Instead, they focus on deplatforming and censoring us which are techniques that are effective when the data doesn’t work out for you.
- Both the FDA and CDC have proven inept in spotting safety signals. They can’t even compute the VAERS URF which is a number that is required for any serious risk-benefit analysis. So the FDA and CDC outside committee members are all flying blind in approving the vaccines. Even after this deficiency is pointed out in the public comments by yours truly (and direct emails to the committee members), it makes no difference. We are ignored. The CDC safety monitoring is so bad that they even admitted at the last ACIP meeting that it was the DoD that spotted the myocarditis signal. So the FDA and CDC have basically been batting .000 in terms of spotting safety signals that have been sitting in plain sight the entire time.
- They can’t admit that they missed the signals now because that would be an admission they missed them before. So they will try to discredit this article with ad hominem attacks (this is a technique used to win an argument when you cannot win on the evidence).
- The serious events we highlight below are all consistent with the mechanism of action that Robert Malone and I first described in the Darkhorse podcast. Namely, that the spike protein that is produced in response to the delivery of the mRNA is cytotoxic and results in blood clots, inflammation and scarring throughout your body which then creates a wider range of severe adverse events than any vaccine in human history.
- The medical community is trained by the CDC to believe the vaccines are safe, so they interpret all the adverse events as not vaccine related. But if it wasn’t the vaccine that caused all these events, what was it? What’s worse is they tell their patients, “this is all in your head” or that “your baby died because you had a genetic defect.”
- In general, patients believe their doctors and never figure out where to get a cytokine panel to discover that they are vaccine injured (go to www.covidlonghaulers.com to get the cytokine panel and IncellDx to get the spike protein assay). So people never learn how to rid their body of the spike protein either (see my article on vaccine treatment for the drugs they use to do this) which is the first step in the road to recovery.
- The high adverse event rates aren’t “excess reporting.” It is due to excess events. For example, one neurologist had 0 cases of vaccine adverse events in her entire career, but this year, she has 2,000. Another physician I know has had 0 events in 29 years in his 700 patients. This year he needs to report 25 events. Physicians themselves have experienced stunningly higher incidence rates of reproductive, neurological, and cardiac events since the vaccines rolled in 2021. We couldn’t find a single cardiologist who actually had fewer cases of myocarditis after the vaccines rolled out as the members of the FDA and CDC claim.
- The serious events are primarily centered around menstruation, blood clots, inflammation and scarring, cardiovascular damage, and neurological damage, just as we predicted in the podcast in June of 2021.
- There are hundreds of serious adverse events that are caused by these vaccines. This of course is shocking to people since the CDC has repeatedly said you can’t ascribe causality to data in VAERS. Not true. The VAERS data analysis (temporal data, the dose dependency, and the elevated reporting rates compared to baseline) provide ample signal to enable us to show causality on all of these events using the five Bradford-Hill criteria applicable to vaccines.
- Nicki Minaj was right to complain about elevated rates of testicular swelling, impotence (erectile dysfunction), and orchitis. Every world authority who opined on the matter belittled her and said she was wrong, but all the symptoms she talked about are strongly elevated as you’ll see from the data below. None of these so-called experts of course ever looks at the data; it’s all based on arguing from their belief system rather than the scientific evidence. And even if those authorities disagreed with the VAERS data, it was irresponsible not to have pointed out the raw data to people and then explain why they totally ignored the elevated signal in the VAERS data. Today, we do science based on our belief system rather than the old-fashioned way of looking at what the data actually says. Our team is old-fashioned.
- There is a pretty good chance that the vaccines don’t really work at all and never did. We know the Pfizer Phase 3 trials were gamed in many ways. There is no doubt that the vaccines elevate antibodies, but it seems that it is quite possible that the immunity they confer is actually the result of killing off (or excluding as in the case of the trials) people with weaker immune systems. The people who are left are thus more resistant to the virus. Mathew Crawford will be coming out shortly with an analysis that makes a compelling case for this novel hypothesis. Subscribe to his substack here.
- It is unlikely that anyone in the world will want to debate us publicly on any of the claims above (or on any of my articles or on any of Mathew’s articles), but if you are a prominent supporter of the false narrative and want a public debate, we are here for you. Our team would be thrilled to accept the challenge as we have no desire to spread misinformation. If we got it wrong, we are happy to correct our mistakes if you can explain to us clearly the mistake we made and the correction you suggest (e.g., the “right” answer). Yet even with multiple million dollar incentives (listed in this article), nobody seems to be interested in showing how we got it wrong. Everyone talks about how bad the vaccine misinformation problem is, but nobody is willing to do anything to show that we got it wrong. For example, I’ve asked any prominent scientist in America who disagrees with my analysis (showing eight different ways to validate that over 150,000 Americans have been killed by the vaccines) to let me see their “correct” analysis showing the “correct” number, but nobody will. They won’t even come on a recorded call to show us how we got it wrong. It’s baffling. They all want to do it in slow motion via documents because that way it’s easier to obfuscate the truth and they can avoid answering questions. The latter is key.
- It’s really easy to tell who is telling you the truth here. John Su is the CDC expert on VAERS. If he’s wrong, the entire narrative falls apart. I personally attacked Dr. Su in a widely read article accusing him of being corrupt. I offered to publish his response in the article. He said nothing. I offered to debate him. No dice. TrialSiteNews tried to interview him. He refused to reply. Seriously? If the CDC gave us 2 hours to ask John Su questions, we would destroy his credibility and the credibility of the CDC. That’s why he’s not talking and that’s why the CDC will never let him talk to anyone on our team. Because we don’t ask softball questions like what John gets at the ACIP meetings. We play hardball.
What we found in the VAERS analysis below can be verified by anyone because it is all publicly accessible. Albert spent only a few hours to produce the tables. So the CDC should have been able to do the same work Albert did.
You can easily verify any entry yourself via manual queries to any VAERS interface (my favorite is MedAlerts, but others such as openvaers and the HHS site give the same results).
Before we get to Albert’s analysis of the VAERS data, let’s do a little background.
The Darkhorse Podcast
On June 10, 2021, my friend Robert Malone and I appeared on Bret Weinstein’s Darkhorse Podcast to tell the world what we had learned about the COVID vaccines. You can watch the 3 hour version here or the condensed 1 hour version here if you haven’t already seen it. I highly recommend the whole thing; I know a lot of people who watched it multiple times and raved about it.
Basically, we said the COVID vaccines were super dangerous, they had killed a lot of people at the time, the Pfizer bio-distribution data that Dr. Byram Bridle obtained from the Japanese government using a FOIA request showed the lipid nanoparticles delivered a very substantial dose of mRNA to female ovaries, and that the spike protein that is subsequently produced causes blood clots, inflammation, and scarring leading to a large number of cardiovascular and neurological symptoms, a number of which would be irreversible. Robert in particular noted that we had no clue about the amount, dose, and duration of the spike protein that is produced (we still don’t) because this testing was never done in animals (they looked only at the distribution of the nanoparticles which is not the same thing). Bret referenced a very long article I had written on May 25, 2021 for TrialSiteNews entitled “Should you get vaccinated?”
For reference, here is the bio-distribution graph that Bret showed in that podcast:

See anything wrong? Note that we deliberately omitted areas of the body where the vaccine was expected to accumulate in order to highlight areas of the body where it wasn’t supposed to go. Naturally, those supporting the mainstream narrative that the vaccines are safe and effective went into overdrive to suppress the episode and discredit what we said. They said we were dishonest not to include everything in the chart. YouTube censored the video after nearly 1M views. Wikipedia accused both of us of spreading misinformation and then blocked me when I tried to point out that the scientific evidence supported what I said. Wikipedia relies on fact checks for science.
We were right about everything we said in the podcast, and now, thanks to the work Albert did, it’s now easier to see we were telling the truth: the top elevated events were neurological, cardiovascular, and related to the female reproductive system, just like we said. I was stunned at the sheer number of menstrual events that made it to the very top of the list. That was a surprise to me.
Openvaers has been highlighting the damaging effects on both male and female reproductive systems for months with a page dedicated to reproductive health, but the medical community, Congress, and mainstream press wasn’t paying any attention at all. These event counts are not normal, but nobody really seems to care. President Biden not only doesn’t care; he wants to force all our kids to be vaccinated with the most dangerous vaccine in human history.

With the new analysis, the counts are much easier to interpret because instead of being just raw counts, they are numbers relative to a baseline rate so we can instantly see what symptoms are “abnormal” meaning 10X or more higher than “expected.” The answer: over 4,000 adverse events.
The X factor analysis (November 7, 2021)
Before I give you the link to the spreadsheet of VAERS symptoms sorted by X factor, you need to know a few things to properly interpret the data.
First, let’s address the myth that is promoted by the FDA that the VAERS database is “over reported.” As we said above, there are more events this year than any previous year, so that’s why the events are up. But there still could be a component of overreporting as well, i.e., that people this year are more likely to make a report on an event compared to last year since everyone is so “highly aware” of the vaccines. Nice theory. No data to back it up. Nobody making that argument has ever included any data to back up their assertion. We call that a hand-waving argument. Doctor surveys we’ve done show that, if anything, they are less likely to report an adverse event this year for a variety of reasons (hospital frowns on it, no time, still too frustrating, too many events to report). The other way we can tell is to look at the rates of events that are not comorbidities or causal. We find that events like Musculoskeletal pain, Screaming, Head banging, Local reaction, Diet refusal, Croup infectious, Hepatitis A, Eyelid oedema, and more occur at pretty much the same rate this year as in previous years.
Now let’s tackle the columns:
Symptom
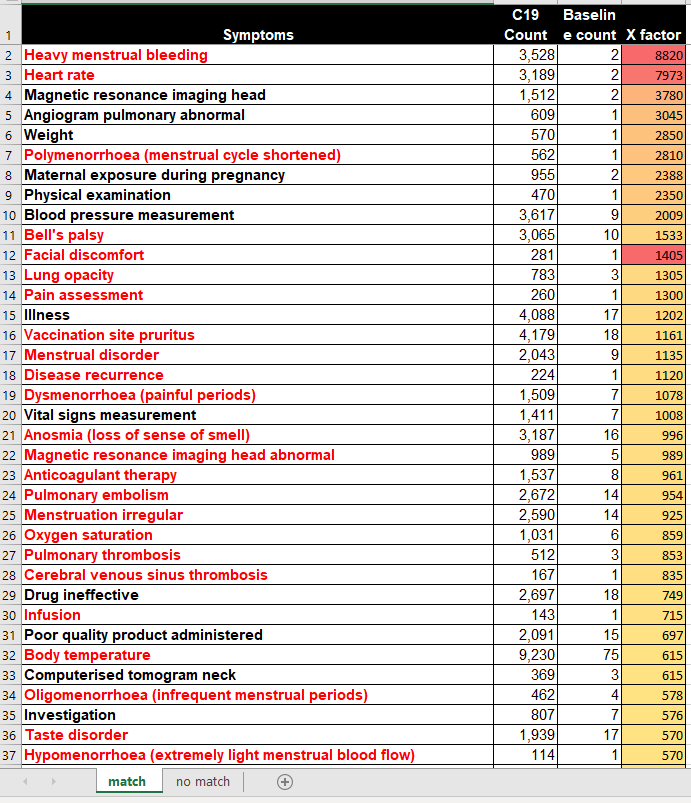
This is the VAERS symptom name. These are coded by HHS upon receipt of the report based on the contents of the report. Some of these symptoms are tests that are ordered. An elevation of a test is a good signal something is amiss. Other symptoms are not causal, but are comorbidities. For example, it might be that diabetes is there more often not because it makes diabetes worse, but because diabetic people are more likely to report symptoms. So for these symptoms, we have to be careful about the analysis. But for many of these symptoms such as cancer, herpes zoster (shingles), diabetes and more, these are all exacerbated by the vaccine as we know from talking directly to doctors. Finally, some symptoms like “rib fracture” or “suicide” are elevated because they are caused by the vaccine. For example, the vaccine can make you lose consciousness and fall and fracture your hip. The vaccine can give you tinnitus which is so bad that you want to kill yourself. So we have to be extremely careful to examine each one of these symptoms carefully because in most cases, we’ll find that they are indeed caused by the vaccine. I’ve coded a bunch of symptoms red that I thought were serious/interesting. I’m not done yet, so the redness coding was only methodically done on the first 100 symptoms and sporadically after that. When I get more time, I’ll go through them and update the file. Note that myocarditis is located on row 274, i.e., way way down.
Also, when looking at deaths, we never look at a “symptom” of death since death is coded in a separate field. So the event count for the “death” symptom (6,487) is lower than the over 8,000 domestic deaths.
Guillain-Barre syndrome is only elevated by a factor of 6 from baseline, likely because other vaccines also elevate GBS; this vaccine elevates it even more.
C19 count
This is the raw number of VAERS events in 2020 and 2021 due to the COVID vaccines for that symptom. The key here is that this count should be multiplied by 41 (known as the underreporting factor or URF to estimate the absolute number of events that occurred). See this article for how that is computed.
Baseline count
The baseline rate is the # of incidents occurring in a 5 year period from 2015-2019 for all vaccines given in that time period.
X-factor
The X-factor is the (C19 count*5/Baseline count). This is because the baseline is 5 years so we compare the COVID counts in a year vs. the average count in a typical year. So an X-factor of 10 or more would mean that the symptom is very likely to be caused by the vaccine since it is highly elevated from the “normal” rate.
Now let’s tackle the tabs. There are two tabs:
match tab
On the match tab are symptoms where the baseline count !=0
no match tab
On the “no match” tab are symptoms where the baseline count=0. So these are quite extraordinary since these symptoms are not typically seen even once in 5 years. So here, even a small value in the “count” field is very significant, e.g., 2 or more would be comparable to a 10X or more on the “match tab.”
Now here are some screenshots of the first page of the two tabs:
And the no match tab:
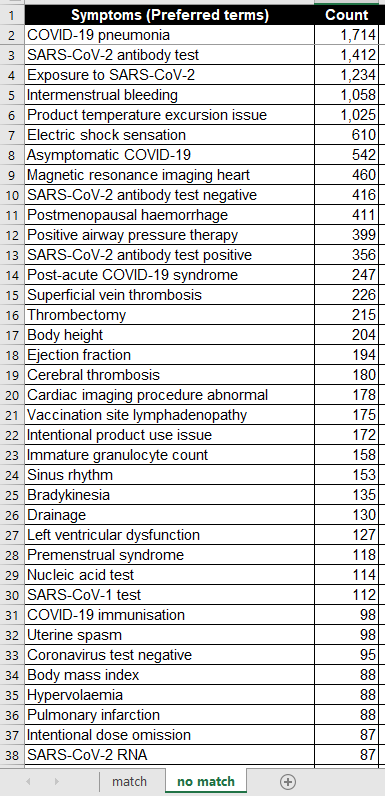
What the data tells us
Here are a few quick observations from the complete data set (see next section for downloading):
- Female reproductive issues top the list. These are strongly elevated by these vaccines. Many of the top symptoms are all related to the menstrual process.
- There are an enormous number of cardiovascular and neurological events that are strongly elevated, many of them serious.
- Fibrin D dimer increased is #53 on the list, elevated by a factor of over 400x above baseline. Charles Hoffe discovered D-dimer was elevated in over 60% of the patients he measured. This is very serious as D-dimer is a lagging indicator of blood clots.
- Troponin increased was #130, elevated by a factor of 205. Troponin indicates heart damage and it is elevated to extreme levels (10X heart attack levels or more) and can stay elevated for months at a time (with a heart attack, the levels start returning back to normal immediately after the incident)
- Death as a symptom (which is pretty unusual coding since it isn’t a symptom), is #433 and elevated by 96X. Hardly a “safe” vaccine.
- Brain herniation at #405 is elevated by a factor of 100X over baseline. However, this is not considered a big deal at the CDC (perhaps because many people there don’t use their brain).
- Cardiac arrest at #450 is elevated by 93X. This is when your heart stops. This is a relatively serious condition since you don’t last for too long after that. It’s a bit surprising that the CDC missed that one. Perhaps because they don’t have a heart?
- Pulmonary embolism #24 is elevated by 954 times normal. How the CDC can miss that one is simply astonishing! This was the cause of death of 2 of the 14 kids that the CDC looked at in their death analysis. Mainstream press will never ask them that question as to why the CDC would not find causality here. They wrote: “CDC reviewed 14 reports of death after vaccination. Among the decedents, four were aged 12–15 years and 10 were aged 16–17 years. All death reports were reviewed by CDC physicians; impressions regarding cause of death were pulmonary embolism (two), …” 954 times normal is hard to explain, isn’t it? So no causality? That’s hard to explain, so they didn’t. They just moved on as if there is nothing to see.
- Intracranial haemorrhage (their spelling) is at #604 and is elevated by 79X. Two of the 14 kids from the CDC analysis died from that. How could that not be causal? They never explained that.
- Tinnitus at #362 is elevated by 105X. This can be so bad that people can kill themselves from this alone. One of the people who work at Vaccine Safety Research Foundation (VSRF) had to talk a friend out of suicide.
- There are many many more issues to be concerned with, but I wanted to get the list out quickly so there can be more eyes on this.
- For months, I’ve offered to discuss our data and analyses to both the FDA and CDC outside committees as well as the CDC and FDA themselves, but nobody wanted to see it. Most hit delete on my emails. A few told me to wait for the public comment period and submit it then (which I’ve done). Nobody followed up.
The Excel file with the full results
I’m trying to increase the number of paying subscribers I have as this supports the substack community. All proceeds will go to paying the salaries of people working for the Vaccine Safety Research Foundation (vacsafety.org) as well as buying ads so we can get the message out.
You can find the full Excel file and Albert’s analysis in this article.
YouTube suspends senator over Covid-19 vaccine video
RT | November 13, 2021
Wisconsin Senator Ron Johnson was temporarily suspended from YouTube for allegedly spreading “harmful misinformation” after he published a video discussing injuries related to Covid-19 vaccination.
Johnson accused YouTube of “censoring the truth” on Friday evening after his roundtable discussion video, which featured “stories from doctors, scientists and the vaccine injured,” was taken off the platform and led to his temporary suspension.
In the video, the Republican senator listed statistics relating to alleged vaccine side-effect victims, while his guests made comments questioning the effectiveness of Covid-19 vaccines in preventing death.
“Why won’t they let the vaccine injured tell their stories and medical experts give a second opinion?” Johnson questioned in a statement. “Why can’t we discuss the harmful effects of mandates?
“Apparently, the Biden administration and federal health agencies must not be questioned,” he said.
In its own statement, YouTube cited policies on reducing “the risk of real-world harm” and “preventing the spread of harmful misinformation” as the reason behind Johnson’s suspension.
It is the second time that the senator has been suspended by the platform, and his account could be permanently removed if he receives further sanctions within the next 90 days.
Since May 2020, YouTube has enforced a lengthy ‘Covid-19 medical misinformation policy’, which prohibits users from questioning the effectiveness of vaccines or claiming that they can “cause death, infertility, miscarriage, autism, or contraction of other infectious diseases.”
In August, YouTube temporarily suspended Kentucky Senator Rand Paul for questioning the effectiveness of face masks, while in the same month, Sky News Australia was suspended for allegedly violating Covid-19 rules.
In January, YouTube even suspended the sitting president of the United States after it accused Donald Trump of violating policies which prohibit the incitement of violence.
Governor Grewsome re-emerges
Irish Savant | November 10, 2021
Well that particular mystery is solved. Or is it? We all know that vaxx evangelist Gavin Newsom disappeared from public view for nearly two weeks, cancelling a number of high-profile engagements, immediately after publicly taking his booster. He has now re-emerged but according to some reports appears to ‘look haggard’ and with shaking hands. All very interesting and couldn’t happen to a nicer guy.
But I’m intrigued by the thought that he actually did take the deadly shot. If he did it seriously undermined my whole Weltanschauung (I occasionally like to add a touch of class to this blog) – that our overlords know what the vaxx is really for and would under no circumstances inflict it on themselves. But if Newsom did actually take it rather than some saline-based alternative it means that, and this is a terrifying thought, he actually believes what he says. Can this be true?
Same question arises with Israel. Again, my working assumption was that only the goyim would benefit from the jab, that the Chosen Ones would, as is their wont, altruistically forego their share for our benefit. But no, they’re one of the most vaxxed countries in the world, and like all other highly-vaxxed countries, enjoying skyrocketing rates of infection. And presumably the accompanying reduced fertility levels?
Well no, actually. Popular commentator Flanders has supplied us with the following fascinating findings.

Yes, of all the highly-jabbed states only Israel hasn’t suffered from reduced fertility.
The plot thickens.
Featured Video

Seyed M. Marandi: US-Iran War Inevitable: Kuwait and Bahrain May Fall
or go to
Aletho News Archives – Video-Images
From the Archives
USS Liberty Massacre: A Pivotal Moment in the Hostile Takeover of America
By Kevin Barrett | Crescent | Dhu al-Qa’dah 24, 1445
In corporate America, hostile takeovers are commonplace. They occur when an aggressor—a larger corporation or rich individuals—seizes control of a smaller corporation without asking permission.
What few recognize is that the United States itself has been subjected to a hostile takeover. Since the aggressor, the illegitimate settler colony known as “Israel,” is much smaller than the US, the takeover has necessarily been surreptitious.
As of June, 2024, Israel’s gradual takeover of the US has become obvious and undeniable—a proverbial “elephant in the living room.” … continue
Blog Roll
 Aletho News
- Seyed M. Marandi: US-Iran War Inevitable: Kuwait and Bahrain May Fall
- Leaders Condemn Ansarallah Attack on Saudi Arabia While Ignoring Illegal War Against Yemen
- Leaked: Britain’s Covert Iraqi Psyops Network
- Yemeni Armed Forces Warn Airlines Against Using Saudi Airports, Exempt Mecca and Medina
- Iran security chief says powers greater than US tried to conquer Iran but ended in ‘dustbin of history’
- Europe’s mounting social chaos… chickens coming home to roost for proxy war against Russia
- US-Russia Diesel Deal Becomes Massive Defeat for Ukraine
- Hormuz and the Looming Economic Catastrophe
- Dhubab offensive, media blitz and the rapid unraveling of Saudi-backed coalition’s new gambit
- Putin Conveys to Trump Iran’s Vision on Possible Conflict Resolution – Kremlin
- If Americans Knew
- Gaza: Ceasefire Anniversary Marks Year of Failed Promises
- The American Conservative: Mike Huckabee Should Resign
- A C-Section in Shackles: A Palestinian Woman’s Harrowing Birth in Israeli Detention
- ‘He’s Desperate’: AIPAC Begins Spending Against Abdul El-Sayed to Boost Mike Rogers:
- Trump, Hormuz, and the Looming Economic Catastrophe
- For three years, Israel has killed a child in Gaza every 71 minutes – Daily Update
- Israeli forces kill another child in Gaza – Daily Update
- Gaza ceasefire exists in name only, say more than 100 organizations
- Nearly 2 Million in Gaza Need Urgent Shelter Assistance as Winter Looms: IOM Chief Warns
- Suppressing Palestinian resistance: US charity under fire for AI monitoring of Gaza classrooms
- No Tricks Zone
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI

