Fact checking the Radio New Zealand fact check
COVID Plan B | November 17, 2021
Radio New Zealand has recently criticized a Facebook live conversation between former National MP Matt King and epidemiologist Dr Simon Thornley. While people should undertake their own research, we provide some comments related to the media’s critique. The evidence related to covid-19 policy continues to change and be updated.
In the interview, Professor Rod Jackson made several claims, decrying Thornley personally during the interview. Let’s examine them in turn.
- “There is no trial evidence that ivermectin [an anti-parasitic drug used as early treatment for covid-19 in some parts of the world] works in people with Covid – it doesn’t exist.”
Trials do exist. In fact a meta-analysis or summary study of six such trials exist. The pooled effect of these trials is a 79% decline in all-cause mortality (95% confidence interval: 89% to 58%). These trials are from Iraq, Iran, Bangladesh, Egypt, Turkey and India, places less reticent about its use. But they are trials, and the reduction in all-cause mortality is stark, an endpoint which is generally considered clinically important and free of error and bias. Another trial points to effective treatment, such as from vitamin D supplementation, which reduced intensive care admissions to 1/50 (2%) in the treated from 13/26 (50%) in the untreated in Spanish covid-19 patients.
We’re not advocating ivermectin at all. But we are prepared to look at the evidence. The fact that Jackson didn’t know there were trials invalidates his point.
- “Professor Jackson also said claiming Covid-19 was no worse than the flu was nonsense”.
In the interview, Thornley claimed the infection fatality rate of covid-19 was as bad as a ‘severe flu’. A summary study of many countries indicates that the average global infection fatality rate of covid-19 is 0.15% or 1/667 people.
The fatality rate for H1N1 influenza is variable, but this figure from covid-19 is well within the range of estimates presented from a similar summary study.
The comparison between covid-19 and flu is therefore fair and accurate. Jackson’s claim is misinformation.
We should note that many fatality studies take the definition of a covid-19 death at face value but it does not mean the individual died exclusively from the virus. This was exemplified by the counting a recent covid-19 death in a man who was actually shot and killed, yet tested positive for SARS-CoV-2 during the autopsy. This was defended by the Ministry of Health, as it conformed with World Health Organization policy.
We are able to test the accuracy of Jackson’s claimed fatality risk. In May 2020, Jackson admonished Sweden for its lax approach. He said the fatality rate of covid-19 was 1/100 people infected, so predicted 56,000 deaths from covid-19 in the country, assuming 60% of the population would be infected. To date, there have been about 15,000 covid-19 deaths, with an age distribution similar to that of background deaths (figure). In fact, by all accounts, Sweden has fared through the epidemic particularly well compared to other European countries.
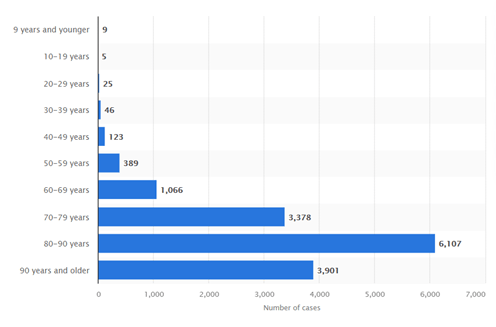
Figure. Deaths with covid-19 in Sweden, by age at November 3, 2021. Source: statistica.com
- “This is a severe disease and we have a evidence-based treatment [the vaccine] where there is definitive evidence that it reduces the risk of severe disease and death by 95 percent, in that order.”
This is an extraordinary claim for several reasons. First, the original Pfizer trial reported about the same number of overall deaths in the treated and the untreated groups (14 in the treated and 13 in the untreated). In the six-month trial results, only three covid-19 deaths occurred, one in the treated and two in the untreated group. This is not consistent with Jackson’s assertion of a 95% reduction in risk of severe disease and death.
Given the numbers of deaths in the original trial, it is possible to work out whether the trial would have picked up a 95% reduction as Jackson claims. The trial would have been expected to have only one death in the treated group, and would have detected a difference more than expected by chance with 96% certainty.
There is observational evidence from Sweden of reduced covid-19 hospitalisations and deaths (not from all-causes), however, the vaccine effect diminished to zero for all three outcomes eight months after the date that the vaccine was administered.
To compound the confusion about the effect of the vaccine, the original Pfizer trial now is marred by whistle-blowers who have given the British Medical Journal evidence of fraud occurring during its conduct. Sixteen Swedish doctors have now called for the injection to be suspended as a result of these revelations.
Both Jackson and RNZ use extensive use of ad hominem attacks, which are considered an invalid, and lowest, form of argument.
Examples include:
- “anti-vax”
- “discredited academic”
- “And we have someone who is questioning that evidence, who doesn’t know what they’re talking about, talking to an epidemiologist who doesn’t know what he’s talking about.”
- “outlier in his field”.
The purveyors and writers of such ‘argument’ appear to have no embarrassment at the anti-intellectualism and inhumanity of their conduct.
We’ll stick to the contest of ideas by again considering Jackson’s accuracy. Back in August 2020, Jackson and his colleagues claimed that elimination was still the best strategy for New Zealand to tackle covid-19. That article has not dated well, yet the personalised tirade and arguments are familiar.
“He [Thornley] is the only dissenter in the epidemiological community,”
“It’s not like this is a discussion like a boxing match with two equal partners. What you’ve got is every experienced epidemiologist in the country supporting the Government’s elimination approach.”
“We are all advising the Government, and we speak with one voice. And you have got a junior epidemiologist who is presenting a different case.”
Jackson has made increasingly inaccurate claims during the pandemic, claiming, unchallenged that one in five infected people will be hospitalised after infection with covid-19. No media have ever fact checked this.
New Zealand’s own government data shows Jackson overestimated by at least a factor of ten, since the proportion of cases (rather than infections) hospitalised is 2% (table).
Table. Counts of cases of covid-19 in New Zealand (16 November 2021).
| Count | % | |
| Self-isolation | 2058 | 56% |
| Isolation Complete | 969 | 26% |
| Managed Isolation | 396 | 11% |
| Hospital | 73 | 2% |
| Other | 198 | 5% |
As sailing great Russell Coutts has recently pointed out, it is questionable how “media entities can maintain objectivity when they have accepted a government grant that is conditional on them promoting certain government policies”.
It is prudent to check all sources of information, not only those who dare to question the what is coming from the Beehive.
We Must Not Shut Down University Campuses Again

By Dr. Alberto Giubilini | Collateral Global | November 17, 2021
Like many other pandemic measures, the extended closures of university campuses has been a massive social and public health experiment.
The results in the report published this week in Collateral Global this week on the impact of pandemic restrictions on university students’ mental health – sadly – should not be too surprising. Young people were not a priority during the pandemic. It is quite telling that most countries – and most people – did not change strategies and attitudes after the initial uncertainty, as we gained more evidence about how minuscule young people’s risk is from Covid. We continued imposing population-wide restrictions, including the closures of schools and university campuses, and moving to online-only teaching, even when it became clear that these restrictions would not benefit young people. They did not need protection from Covid as much as they needed protection from the effects of policy responses on their mental health and their psycho-physical development more generally. This report emphasises once more how we failed to protect young people’s well-being from the inevitable harms of prolonged restrictions.
Public health policies are justified to the extent that they produce significant enough collective benefits without disproportionately burdening certain groups. Admittedly, in situations of uncertainty, a rigorous cost-benefit analysis is not always possible. And yet, the stricter the restrictions, the stronger the duty to rigorously gather real-time evidence on what costs they impose on different groups. Like many other pandemic measures, the extended closures of university campuses have been a massive social and public health experiment. But even experiments require constant interrogation as to whether they are working, and a measure of their success must be the continuous evaluation of whether they are creating collateral damage. It seems we didn’t want to see or give due consideration to such damage.
The prolonged closure of university campuses and the decision to move online all the teaching, socializing, and formal and informal interactions that play a central role in young people’s psycho-physical development resulted in enormous costs that we could not see on our computer screens. With the report this week, the evidence of the significant damage we caused to them becomes more apparent – for example, with the studies showing one in three students reporting symptoms of anxiety and depression.
Those of us working in academic institutions (or better, working on that non-existent space that is Zoom) could not see what was happening beyond those discrete windows through which we were delivering classes or supervising students from our homes. When the world exists only to the extent that it appears on a computer screen, it is easy to forget that students’ existence and experiences do not end the moment they disappear from view. When Zoom meetings and classes are over and the computer shuts down, the young people remain out of sight. Many were sitting alone in their rooms, deprived of their lives as students and, indeed, as whole persons, at a developmental stage when experiences and social interactions play a critical role in helping them understand themselves and the world around them. Although we could not see that, it should not have been difficult to imagine the damage already when the cameras turned off.
There may be limited utility at this point in blaming those responsible for the public health decisions that completely disregarded this potential (and foreseeable) damage to students. It also might be pointless to assign culpability to the academics who kept (and continue to keep) supporting tight restrictions and advocating for online teaching from the comfort of their homes while relegating students to social isolation. But what is undoubtedly useful, in light of this week’s report, is to look ahead as winter in the Northern Hemisphere approaches and more people begin putting restrictions back on the table.
Before making any decisions, we must acknowledge that we don’t need to run social and public health experiments on students any more. We have data now about the harm we have caused to them. And we now know the threat that closing campuses and moving the whole student experience online can pose.
Any decision to close university campuses at this point can no longer be construed as an innocent mistake – if, indeed, it ever was.
Dr. Alberto Giubilini is a Senior Research Fellow in Practical Ethics at the University of Oxford.
Collateral Global is a U.K.-based charity researching the collateral impacts of the mandated non-pharmaceutical interventions.
BBC Believes a Conspiracy Drives Climate Conspiracy Theories
By Eric Worrall | Watts Up With That? | November 16, 2021
Shadows everywhere: The possibility that people might want to reject climate lockdowns and Covid lockdowns of their own volition does not seem to occur to BBC conspiracy theorists.
Covid denial to climate denial: How conspiracists are shifting focus
By Marianna Spring
Specialist disinformation reporter, BBC NewsMembers of an online movement infected with pandemic conspiracies are shifting their focus – and are increasingly peddling falsehoods about climate change.
Matthew is convinced that shadowy forces lie behind two of the biggest news stories of our time, and that he’s not being told the truth.
“This whole campaign of fear and propaganda is an attempt to try and drive some agenda,” he says. “It doesn’t matter whether it’s climate change or a virus or something else.” […]
And recently, groups like the ones he’s a part of have been sharing misleading claims not only about Covid, but about climate change. He sees “Covid and climate propaganda” as part of the same so-called plot.
The White Rose network
It’s part of a larger pattern. Anti-lockdown and anti-vaccine Telegram groups, which once focused exclusively on the pandemic, are now injecting the climate change debate with the same conspiratorial narratives they use to explain the pandemic.
The posts go far beyond political criticism and debate – they’re full of incorrect information, fake stories and pseudoscience.
According to researchers at the Institute for Strategic Dialogue (ISD), a think tank that researches global disinformation trends, some anti-lockdown groups have become polluted by misleading posts about climate change being overplayed, or even a so-called “hoax” designed to control people.
“Increasingly, terminology around Covid-19 measures is being used to stoke fear and mobilise against climate action,” says the ISD’s Jennie King.
She says this isn’t really about climate as a policy issue.
“It’s the fact that these are really neat vectors to get themes like power, personal freedom, agency, citizen against state, loss of traditional lifestyles – to get all of those ideas to a much broader audience.”
One group which has adopted such ideas is the White Rose – a network with locally-run subgroups around the world, from the UK to the US, Germany and New Zealand – where Matthew came across it.
“It’s not run by any one or two people,” Matthew explains. “It’s kind of a decentralised community organisation, so you obtain stickers and then post them on lampposts and things like that.” […]
While we chat, he mentions “The Great Reset” – an unfounded conspiracy theory that a global elite is using the pandemic to establish a shadowy New World Order, a “super-government” that will control the lives of citizens around the world. … Full article: https://www.bbc.com/news/blogs-trending-59255165
The Great Reset is a public programme promoted by the World Economic Forum. The annual “Great Reset” WEF Davos event costs more than $50,000. According to Wikipedia, in 2011 an annual membership cost $52,000 for an individual member, $263,000 for “Industry Partner” and $527,000 for “Strategic Partner”. An admission fee cost $19,000 per person. In 2014, WEF raised annual fees by 20 percent, bringing the cost for “Strategic Partner” from CHF 500,000 ($523,000) to CHF 600,000 ($628,000)
A simple google search turns up the WEF page near the top of the list of searches. The page cites Covid and climate change as justifications for their programme.
In my opinion there is room to debate the true nature of the Great Reset programme, but calling it “unfounded”, as in non-existent, is at best plain ignorant, and well below the BBC journalistic standards we once thought we had a right to expect.
As for the White Rose network, never heard of it. I have no doubt White Rose and many similar groups exist, in our unsettled world there are plenty of concerned people seeking out like minded fellows. But some groups are run by people with their own agenda, who are not acting in their member’s best interests, and any significant group will be heavily monitored by the government, so I strongly urge caution for anyone who participates in large private social media groups.
In Britain there is a “malicious communication act”, which makes it an offence to distribute written material which causes offence or anxiety, which has been used to arrest people campaigning against British government Covid policy. I am not a lawyer, but in my opinion it is only a matter of time before this act is used against people who oppose other high priority government policies in Britain. Be careful what electronic footprints you leave, your words could be misinterpreted. Above all, stay within the law, wherever you live.
The Geniuses Are Locking Down Again
By Tom Woods | Principia Scientific International | November 15, 2021
Today someone shared the chart below, generated by the Financial Times. Try to pick out which one of these countries hasn’t implemented a vaccine passport system:

I’ll bet you know which one it is.
Meanwhile, parts of Europe are going back into lockdown.
Austria is locking down the one-third of the population that is unvaccinated.
The Netherlands is 72 percent fully vaccinated and is going into lockdown for everyone, vaccinated and unvaccinated.
Wouldn’t it be nice if, instead of inanely blaming “the unvaccinated” for this, the robots on social media would at least admit that this isn’t how they expected it to go, and that there shouldn’t be this level of cases and deaths after the introduction of vaccines?
It’s like Sweden: we were supposed to believe that Sweden would have one of the worst death rates in the world because it ignored the so-called experts demanding lockdown.
Well, Sweden is currently #53 in the world for COVID death rate. Number fifty-three. Not one. Not two. Not ten. Not twenty. Fifty-three.
The crazies are still criticizing Sweden, naturally.
But my question is: when you were screaming hysterically at Sweden to lock down, did you think they’d end up all the way down at number 53 in the world in death rate?
Aren’t you the least bit curious about that? Is there a chance that if we hadn’t wrecked societies it wouldn’t have made any difference anyway?
Same with Florida: did the hysterics expect them to have one of the better rates of age-adjusted COVID mortality in the United States?
Of course not. They were warning that Florida would be one of the worst.
And yet in none of these cases can they bring themselves to say: thank goodness things turned out better than we predicted!
Instead, they just double down.
Long Covid doesn’t exist, volume one zillion
By Alex Berenson | November 10, 2021
The Journal of the American Medical Association has another stunning paper out, this one on post-Covid symptoms in almost 27,000 French adults.
Researchers asked people to report whether they had had Covid and whether they had any of 18 lasting symptoms like insomnia, fatigue, or cough. They found that self-reported Covid was very strongly associated with nearly every symptom.
But the scientists then went a step further.
They also had Sars-Cov-2 antibody test results for the people they had surveyed, so they didn’t have to depend on self-reported Covid. They knew who really had had Covid and who had not.
They then compared self-reported symptoms in people with antibodies – that is, people who had actually been infected and recovered from Covid – to the general population. And they found no difference in almost any symptom.
Covid was not a risk factor for chest pain, or breathing difficulties, or trouble focusing, or stomach pain, or any of the many, many other complaints that long Covid “patients” and interest groups say are real. There was one interesting exception; people with Covid antibodies did have a much higher rate of anosmia, losing one’s sense of smell. Because anosmia is a known and lasting side effect, it serves as a useful control of sorts.

The researchers also found that almost 60 percent of the people with antibodies HAD NO IDEA THEY HAD EVEN HAD COVID AT ALL. Meanwhile, while more than half the people who said they had had Covid had no antibodies. (Welcome to the plague so severe most halfway healthy adults don’t even know they’ve had it.)
The study strongly suggests that many people are using previous Covid diagnoses – either real or imagined – to help explain away common physical symptoms such as joint pain or cough. It also suggests that actually being infected Covid is far less risky than thinking you have been infected with Covid for many people.
The researchers concluded by explaining that people who claim they have long Covid may need help “to identify cognitive and behavioral mechanisms that may be targeted to relieve the symptoms.” Which is a very polite way of putting the truth.
This study should slow, if not stop, the rush to medicalize long Covid. It is yet more proof that the illness is a group of squishy (if painful and difficult) symptoms looking for a name – and more importantly a billing code.
But so many patients and physicians and public health experts are now invested (in some cases literally) in making long Covid real that the gravy train will likely roll on.
SOURCE: https://jamanetwork.com/journals/jamainternalmedicine/fullarticle/2785832
CDC Redefined Vaccine to Support Deficient Fake Vaccines Sold by Drug Companies
By Joel S. Hirschhorn | November 14, 2021
The CDC once was a federal agency that nearly everyone respected. That no longer is the case. Now there are many reasons why the CDC should be widely disrespected. Its latest debacle is how it changed the definition of vaccine.
Just imagine this: The entire push for COVID “vaccines” was based on a lie – they did not meet the official CDC definition of a vaccine. By doing this, the government could coerce the entire population to get the shot. Calling them “vaccines” was the biggest lie from Fauci and the key to drug companies making many billions of dollars.
Why would the government’s key public health agency change the definition of what a vaccine is in the midst of a pandemic? After millions of Americans have taken the shot? And millions more are being beaten into taking it for the first time and others to get booster shots.
Words matter
Here is the key point. It became widely recognized by medical experts and informed citizens that COVID vaccines clearly did not fit the official CDC vaccine definition. The CDC thought the answer was not to fix what was deficient with the COVID vaccines or stop their use by most people as so many medical experts advised. Their response was to change the vaccine definition to fit the so-called vaccines.
This was done so that vaccine mandates could keep getting pushed by the government. Of course, the COVID “vaccines” should be referred to as gene therapy products, even better than calling them experimental vaccines.
To see how corrupt this action by the CDC was, it is necessary to examine the details of the vaccine definition debacle.
Prior to September 1, 2021 here is how CDC defined vaccine:
A product that stimulates a person’s immune system to produce immunity to a specific disease, protecting the person from that disease. Vaccines are usually administered through needle injections, but can also be administered by mouth or sprayed into the nose.
This definition had been used for years and it makes sense. No expert or sensible citizen would find fault with it. But did it honestly apply to the COVID vaccines?
Then this is what the CDC concocted:
A preparation that is used to stimulate the body’s immune response against diseases. Vaccines are usually administered through needle injections, but some can be administered by mouth or sprayed into the nose.
Here is what the CDC also said:
Immunity: Protection from an infectious disease. If you are immune to a disease, you can be exposed to it without becoming infected.
Think about that last sentence: You can be exposed to COVID without being infected; but we know that is not true for fully vaccinated people who still get infected.
This is the key language in the original definition:
“stimulates a person’s immune system to produce immunity to a specific disease, protecting the person from that disease.”
How rational to invoke the purpose of a vaccine to stimulate an immune system to produce immunity to a specific disease that protects the recipient from that disease. Exactly what everyone for years thought was the correct way to think about a vaccine. People want permanent protection from the COVID infection disease.
But now the CDC has taken out the language referring to getting immunity for a specific disease and getting protection from that disease.
Now, COVID vaccines do not have to directly produce immunity. No, now they only have to stimulate the body’s immune system.
You don’t get immunity because COVID vaccines do not directly produce immunity. They do not directly kill the COVID virus. Vaccinated people can still have high viral loads and also transmit the virus to others. While some individuals may get some health benefits from COVID shots, they do not necessarily protect the entire population. This is why mandates to get everyone the shots really do not make sense from a public health perspective, that Dr. Paul Alexander has well substantiated.
Apparently, the only logical way to understand what the CDC has done is to accept the truth belatedly seen by the CDC that COVID vaccines do not, in fact, produce effective immunity for COVID infection and do not provide effective protection, once vaccinated, from that infection.
Much of the public surely does not yet know what the CDC has acknowledged for the COVID vaccines. Odds are that everyone who depends on mainstream media for good information about the pandemic has not been informed about what the CDC has done and its implications.
The new vaccine definition, if publicly known, would reduce public confidence in current COVID vaccines. You don’t have to be a medical expert to see how the new definition has been created to accommodate COVID shots.
In fact, these definition changes reflect what is now known about the limitations of the COVID vaccines.
Fully vaccinated people can still get COVID disease, referred to as breakthrough infections that, contrary to what the government says, can be very serious, often requiring hospitalization and sometimes causing death, as was the case for Colin Powell. Such serious effects have been well discussed by Dr. Günter Kampf. Other times, breakthrough infections greatly disrupt lives, as recently described by Madrigal, a strong proponent of COVID shots.
Moreover, the COVID vaccines are now widely known from considerable clinical evidence to lose their effectiveness typically in about six months. And even worse, they do not provide hardly any protection against variants like the delta variant. Same disease but from a different virus in terms of its complex genetic makeup. So, befitting the new CDC definition the COVID shots really do not have long lasting effective immunity to the specific COVID infection caused by all variants.
Elsewhere on the CDC website is a glossary of many terms; here is what is especially relevant to the debate about COVID vaccines:
Attenuated vaccine: A vaccine in which a live microbe is weakened (attenuated) through chemical or physical processes in order to produce an immune response without causing the severe effects of the disease. Attenuated vaccines currently licensed in the United States include measles, mumps, rubella, varicella, rotavirus, yellow fever, smallpox, and some formulations of influenza, and typhoid vaccines.
Most people would read this and find that it fits with what they think of as vaccines that have been routinely taken by most people, especially children. Clearly, COVID vaccines do not fit this definition. But seeing this established view of vaccines helps explain why so many people resist and reject the COVID shots. They are so fundamentally different than long accepted and used vaccines.
Natural immunity
One of the biggest pandemic scandals is that the government refuses to give full credit to natural immunity that people get from once being infected by the COVID virus. It should be officially recognized as equivalent to “vaccine” immunity.
The following CDC glossary definition is especially relevant:
Active immunity: The production of antibodies against a specific disease by the immune system. Active immunity can be acquired in two ways, either by contracting the disease or through vaccination. Active immunity is usually permanent, meaning an individual is protected from the disease for the duration of their lives.
This CDC definition of active immunity recognizes that you can get it by contracting the disease versus through vaccination. In other words, it recognizes what today is commonly called natural immunity achieved by once being infected by the COVID virus. And that such immunity is likely permanent and better than vaccine immunity, as recent clinical studies substantiate. But it also infers that active immunity obtained through vaccination is also permanent, which clearly is not the case for COVID shots, as evidenced by breakthrough infections.
Also note that it has recently been revealed that the CDC has not been able to provide any proof of at least one instance of an unvaccinated, naturally immune individual transmitting the COVID-19 virus to another individual.
And a new study found that almost 60 percent of the people with antibodies had no idea they had even had COVID at all. But they would have natural immunity. Quite consistent with the reality that most people suffer no significant health impacts from being infected with the COVID virus, regardless of all the fear mongering by Fauci and others.
Conclusions
To sum up, a close look at what the CDC has done lately reinforces the thinking of millions of people who have reservations and concerns about getting COVID genetic therapy shots that pose myriad adverse impacts and sometimes death.
There is a rational, science basis for thinking that the limited benefits of those shots do not adequately offset their risks. This is true for the vast majority of healthy people, especially children, who have extremely low risk from COVID infection for serious illness, hospitalization or death.
Mandates that do not recognize natural immunity are merely a sham tactic to make money for drug companies.
How interesting it would be, in the context of informed consent, if people were shown the original and new CDC vaccine definitions as a means to stimulate productive discussion with medical providers of COVID shots.
Dr. Joel S. Hirschhorn, author of Pandemic Blunder and many articles, podcasts and radio shows on the pandemic, worked on health issues for decades. As a full professor at the University of Wisconsin, Madison, he directed a medical research program between the colleges of engineering and medicine. As a senior official at the Congressional Office of Technology Assessment and the National Governors Association, he directed major studies on health-related subjects; he testified at over 50 US Senate and House hearings and authored hundreds of articles and op-ed articles in major newspapers. He has served as an executive volunteer at a major hospital for more than 10 years. He is a member of the Association of American Physicians and Surgeons, and America’s Frontline Doctors.
SAN DIEGO COUNTY BOARD OF SUPERVISORS MEETING – Dr. Scot Youngblood defends the science
Dr. Scot Youngblood spoke to the San Diego county Board of Supervisors on November 2, using the CDC and Pfizer data to show the vaccine provides no net benefit.
Top NIH Unvaxxed Scientist Willing to Lose Job and License, Will Argue Against Vaccine Mandates in Livestreamed Ethics Review
By Megan Redshaw | The Defender | November 9, 2021
A senior bioethicist who heads a research team at the National Institute of Allergy and Infectious Diseases (NIAID) is taking the lead at the National Institutes of Health (NIH) in the debate over the ethics of COVID vaccine mandates.
Dr. Matthew Memoli, director of the Laboratory of Infectious Diseases at NIH, will argue against vaccine mandates during a Dec. 1 livestreamed roundtable session, which will be open to the public.
“There’s a lot of debate within the NIH about whether [a vaccine mandate] is appropriate,” David Wendler, a senior NIH bioethicist in charge of planning the session, told the WSJ. “It’s an important, hot topic.”
Memoli opposes mandates for the COVID vaccines authorized for emergency use in the U.S., and has chosen not to be vaccinated.
Memoli sought a religious exemption from the mandatory vaccine requirements imposed by health authorities in the District of Columbia, where he is licensed to practice medicine.
Memoli said he is willing to risk his job and his license for the right not to receive a COVID vaccine. During the scheduled roundtable early next month, he will make the case against mandates.
“I think the way we are using the vaccines is wrong,” Memoli said in a July 30 email to Dr. Anthony Fauci, director of the NIAID, and two of his lieutenants. Memoli called mandated vaccination “extraordinarily problematic.”
Memoli told the WSJ one of Fauci’s colleagues thanked him for his email. Memoli said he supports COVID vaccines for high-risk populations including the elderly and obese, but said, “blanket vaccination of people at low risk of severe illness could hamper the development of more-robust immunity gained across a population from infection.”
Memoli, a 16-year veteran at the NIH was selected this month for a 2021 NIH director’s award — a top recognition from the head of the agency, for his supervision of a national study into undiagnosed COVID cases early in the pandemic.
Memoli said his children have received their childhood vaccines, and he will support the results of the ethics discussion regardless of the outcome.
“I do vaccine trials. I, in fact, help create vaccines,” Memoli told the WSJ. “Part of my career is to share my expert opinions, right or wrong … I mean, if they all end up saying I’m wrong, that’s fine. I want to have the discussion.”
Christine Grady, head of NIH’s Clinical Center bioethics department and Fauci’s wife, approved the Dec. 1 seminar — a session called “Grand Rounds.”
Grady said in an email she believes there is interest in the topic across the agency.
“Our hope is that the December Grand Rounds will be relevant to the debates that are going on around the country regarding vaccine mandates,” an agency spokeswoman said on Grady’s behalf.
Federal appeals court temporarily halts Biden’s COVID vaccine mandate for private employers
A federal appeals court on Saturday issued a stay temporarily halting the Biden administration’s private-employer COVID vaccine mandate, citing, “grave statutory and constitutional” issues with the requirement.
“Because the petitions give cause to believe there are grave statutory and constitutional issues with the mandate, the mandate is hereby stayed pending further action by this court,” the U.S. Court of Appeals for the Fifth Circuit said in the order.
The case was brought by multiple businesses and several states, including Texas, Utah, Louisiana, South Carolina and Mississippi. They argued the requirements exceed the authority of the Occupational Safety and Health Administration (OSHA), which will enforce the mandates, and amount to an unconstitutional delegation of power to the executive branch by Congress.
The Biden administration on Monday asked the federal court to lift the order blocking the mandate for large private employers. The administration said the petitioners were not claiming a “major prospect of harm” from the rule, so the court should allow the mandate to proceed while the case makes its way through the system.
“Accordingly, there is no need to address petitioners’ stay motions now, and the court should lift its administrative stay and allow this matter to proceed under the process that Congress set forth for judicial review of OSHA standards,” lawyers for the administration argued.
The White House on Monday said businesses should move forward with Biden’s vaccine mandate for private businesses, despite a federal court order temporarily halting the rules, CNBC reported.
“People should not wait,” White House Deputy Press Sec. Karine Jean-Pierre told reporters during a press briefing. “They should continue to move forward and make sure they’re getting their workplace vaccinated.”
The OSHA regulation applies to employers with at least 100 workers, creating an emergency temporary rule that will require employers to mandate workers be vaccinated against COVID or submit to regular testing. A deadline for companies to comply with the regulation was set for Jan. 4.
Petitioners said the mandate, publicized as an emergency temporary standard by OSHA, should be struck down because it exceeds OSHA’s authority under the Occupational Safety and Health Act.
More than two dozen states have filed lawsuits against the Biden administration over the vaccine mandate for large private employers in the 5th, 6th, 7th, 8th, 11th and D.C. Circuits. Federal law dictates cases be consolidated and heard by one federal appeals court chosen by a lottery.
According to the U.S. Department of Justice, the lottery could take place on or around Nov. 16, and the case could make its way to the Supreme Court.
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Featured Video

The Truth About the Trump Shootings with Ken Silva
or go to
Aletho News Archives – Video-Images
From the Archives
Trans ‘milk’ as good as the real thing – NHS
RT | February 18, 2024
The drug-induced nipple secretions of trans women are as good as mothers’ breast milk for babies, the University of Sussex Hospitals NHS Trust claimed in a letter to campaigners made public in a report by British think tank the Policy Exchange on Sunday.
The healthcare trust’s medical director, Rachel James, argued that the off-label prescription drug cocktail men transitioning to female take in order to produce milk was “similar to the natural hormones which encourage lactation to develop when the baby is newly born.”
“The evidence which is available demonstrates that the milk is comparable to that produced following the birth of a baby,” James wrote in the letter, sent to Children of Transitioners last August.
Biological men who wish to lactate must first take hormones to grow milk glands and then take high doses of either domperidone or metoclopramide to stimulate milk production. Neither drug is approved for this use, though they are occasionally prescribed off-label to biological women who have trouble lactating.
However, domperidone’s own manufacturer, Janssen, warns patients the drug “may cause unwanted side effects affecting the heart in a breastfed baby” and “should be used during breastfeeding only if your physician considers this clearly necessary.” … continue
Blog Roll
 Aletho News
- Anthrax Attacks Paved Way for COVID-Era ‘Junk Drugs and Vaccines’
- How Real Is the Impact of Western Sanctions on Israel?
- France, You Are Guilty: How Paris Turned Western Sahara into the Maghreb’s Powder Keg
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- Your Milk Is Not the Problem
- The Truth About the Trump Shootings with Ken Silva
- ARE PATIENTS BEING PROPERLY INFORMED ABOUT OZEMPIC?
- US lawmaker blocks $2.8 billion weapons sale to Israel: Report
- Yemeni army claims responsibility for strikes on sensitive sites in Saudi capital, Aramco facilities in Yanbu
- Iran Judiciary issues indictments against 159 US, Israeli officials for assassination of Leader, commanders
- If Americans Knew
- Salah Sarsour’s Legal Team Says DHS Has Not Met Its Burden to Prove He Is Deportable
- An analysis of tax forms by The Intercept show Kraft’s charity and LLC have donated to Friends of the IDF and AIPAC’s super PAC.
- Israeli attacks kill four Palestinians in Gaza – Daily Update
- Inside Gaza’s death trap of collapsing, bombed-out buildings
- The everyday items Israel bans from Gaza every day
- Inside the siege, the ruined buildings of Gaza – Daily Update
- Debunking The Claim That Macklemore Has A “History Of Antisemitism”
- CPJ demands release of arrested Palestinian-US journalist near Bethlehem
- Robert Kraft: The Billionaire Friend of Netanyahu Pulling The Strings Behind the Macklemore/Ed Sheeran Blow Up
- Columbia Administered Fund Gives Big Money to Pro-Israel Groups
- No Tricks Zone
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
 Aletho News
