New Zealand Doctors Speaking out with Science
NZDSOS – 15/11/2021
‘NZ Doctors Speaking out with Science’ featuring Drs Alison Goodwin, Matt Shelton, and Emanuel Garcia. News Conference 15th November, 2021.
See also:
Vaccinated “No Less Infectious” Than Unvaccinated, CDC Study Finds
By Will Jones • The Daily Sceptic • November 24, 2021
A pre-print study out this week from the U.S. Government’s Covid Response Team at the Centers for Disease Control and Prevention (CDC) has found vaccinated people to be “no less infectious” than unvaccinated people.
The study tested inmates in a federal prison with high vaccination rates daily during a SARS-CoV-2 Delta variant outbreak.
The study was very thorough. Inmates who tested positive for SARS-CoV-2 were, where willing, PCR-tested for 10 consecutive days and reported symptoms via a questionnaire. The researchers performed whole genome sequencing and viral culture analysis on a high proportion of the 978 specimens collected, allowing them to assess the duration of PCR positivity and viral culture positivity.
There were 95 participants in total, of whom 78 (82%) were double vaccinated and 17 (18%) were not double vaccinated (two having received one dose and 15 having received none). No significant differences were found between double vaccinated and not double vaccinated either in duration of PCR positivity (13 days each) or in duration of culture positivity (five days each).
The authors conclude that “clinicians and public health practitioners should consider vaccinated persons who become infected with SARS-CoV-2 to be no less infectious than unvaccinated persons”.
This is in line with the findings of Public Health England and others.
While this sounds like more good news for countering vaccine passports, vaccine mandates and all other vaccine-based coercion and discrimination, it may be less good news for ending general restrictions and interventions. The authors state: “These findings are critically important, especially in congregate settings where viral transmission can lead to large outbreaks.” Which suggests they think the lack of efficacy against transmission is a reason to intervene more generally to prevent “large outbreaks” in “congregate settings”. It could be a long winter.
French Presidential candidate Marine Le Pen speaks out against vaccine passports

By Ken Macon | Reclaim The Net | November 25, 2021
Presidential candidate in next year’s election in France, Marine Le Pen, has promised to remove vaccine passport mandates if she is elected because they are “useless” and a “disproportionate” restriction.
She will be running against current President Emanuel Macron, who supports the controversial measures.
“What is the vaccine passport for, apart from imposing a useless and disproportionate constraint on the French people?” Le Pen said in an interview on French radio France Inter.
Le Pen is against mandatory vaccination for everyone, including medical professionals. She supports “vaccine-freedom,” especially considering the vaccine does not prevent you from getting COVID or from contaminating others.”
Referring to vaccinated Prime Minister Jean Castex testing positive for the virus, Le Pen said, “I think we have a good example at the top here.”
“The real question is: can the vaccine prevent the spread of the virus? I think today the answer is no,” she said.
When asked if she supported vaccine boosters, she reiterated that vaccination should be a choice.
“I don’t have to be for or against it. I think everyone has to be free to do it or not, since in reality, it’s only your own life which is at stake,” Le Pen said.
“Everyone has to determine the risks and benefits for themselves.”
Le Pen said those with a vaccine passport could be more dangerous than the unvaccinated because they “shake hands and go to the restaurant” while sick with the virus.
“Nothing, it seems, can stop the spread of this virus, so all these constraints are meaningless,” she insisted.
She said she would remove the “senseless restrictions” if she is elected, particularly the suspension of healthcare workers who have not been vaccinated.
“The suspension of healthcare professionals is useless, [and] we need them,” she said.
“Hospitals are the main problem,” she added.
“It’s the government’s responsibility [to ensure there are enough hospital beds]…. They’ve removed beds [and] have allowed hospitals to become medical deserts with 30% of posts now vacant,” she continued.
“For the rest, we remove all of these constraints which are obviously useless.”
Ignorant and Afraid
Politicians and bureaucrats aren’t immune to their own propaganda, and they really are as ill-informed as they seem.

eugyppius | November 25, 2021
I’ve mentioned this episode a few times: On 11 March 2020, Angela Merkel held a press conference where she remarked that the best hope was to slow the spread of SARS-2, and that 70% of Germans could be infected. The Italian lockdown was only a few days old, and it was plainly not Merkel’s intent to go down the path of mass containment. The United Kingdom, Germany, Sweden and likely a few other countries too still planned for an ordinary approach to Corona, with minimal mitigations.
All the while, though, Team Lockdown was hard at work behind the scenes, to bend policy in their direction. As this leaked email from 20 March shows, German medical bureaucrats deputised by the Ministry of the Interior were soon consulting experts on how best to instil “fear and a willingness to obey in the population.”

Because Western governments doubted their capacity to enforce Chinese-style lockdowns outright, fomenting mass panic became a non-pharmaceutical intervention in its own right. The histrionic media messaging has continued to this day, and it has contributed to a profoundly important division in our society: There are on the one hand those people in essential roles, who have endured exposure to Corona from the beginning, and most of whom have had the virus by now. And there are on the other hand those in Martin Kulldorf’s “laptop class,” that is to say well-off urban professionals, who have spent most of the last 21 months at home, hiding from a virus that many of them believe is approximately as dangerous as SARS. Mass infections among these people are only starting to happen right now.
As members of this privileged, sheltered class, politicians and bureaucrats have absorbed the virus hysteria that they helped seed in their social milieu. In the beginning, Merkel did not especially fear the possibility of mass infections in Germany. Six months of press hysteria later, in October 2020, she had grown accustomed to carrying two plastic envelopes in her bag. One was for the careful, hygienic disposal of used surgical masks. The other carried precious new ones, whenever she judged her current mask had reached a dangerous state of virus saturation.
Press photographs captured her awkward mask-changing routine:

Merkel’s remarkable virus paranoia, quietly acknowledged by the press now for months, explains her fixation on social isolation, closures and curfews as the only acceptable pandemic policies.

She is a 67 year-old sedentary woman who likely suffers from one or more undisclosed health problems. And she is surrounded by other older, unfit government officials, like 73 year-old interior minister Horst Seehofer, who nearly died of a B19 virus infection in 2002, and so has a reason to fear viral infection. For months and months, all of these people have been taking every possible personal precaution – including house-arresting the entire domestic populations of the countries they govern – in the vain hope of escaping Corona.
You could feel their collective relief when the vaccines were rolled out. All of them eagerly accepted vaccination. Merkel even provided pictures of her personal yellow vaccine pass to the press, with the stamp documenting her first dose of AstraZeneca. (Her purpose, in part, was to allay public concerns over the propensity of AstraZeneca to cause blood clots.)

To the profound disappointment of Merkel and everybody like her, the vaccines have not eradicated Corona. Every day, the prospect of personal infection looms for these people as a new, uncomfortable certainty. Every day, they and the rest of the work-from-home bureaucracy become ever more terrified. The prime minister of Austria is so afraid that he has confined all unvaccinated Austrians to their homes. When asked, he declared that this measure would have no end date. The Chief Minister of Australia’s Northern Territory is terrified. New Zealand prime minister Jacinda Ardern is terrified.

You know who isn’t terrified right now? Everyone outside these circles. I and many of the people I know have had Corona, and we’re not terrified. Blue-collar workers have mostly been infected, and they’re not terrified. Grocery clerks, nurses, police officers and bus drivers aren’t terrified. All of the terror is at the top, blaring down at us all of the time. All these people know they are going to get sick in the next few months, and they are railing against this reality.
While I don’t agree with James Lindsay, that we are on the verge of a Second Enlightment, I think his distinction between official, curated, peer-reviewed information and analysis; and counter-cultural internet hive-mind information and analysis, is instructive.
All in all, it is the hive-mind that has been vastly more successful at understanding what is going on – not only as far as Corona, but everywhere. This has been obvious now for years. It is even true in my own field, where the official discourse suffers from a pervasive, unoriginal banality, while alternative theories pondered by intelligent outsiders and anonymous Twitter accounts become every day vastly more interesting. The reasons are simple: There are more people involved; the barriers to publishing are lower; nodes that provide bad analysis are easily removed; the thinkers are more thoroughly networked to each other; they gather audiences solely on the basis of their ability; they consider everything, not just the official line.
Meanwhile, it is only official, curated information that is allowed to inform bureaucratic decisions. Products of the hive-mind are deliberately excluded, via gate-keeping mechanisms like peer review and credentialism. All of the terrified Angela Merkels of the world act within an environment of outdated, poor-quality information, all the time.
Again, this is not unique to Corona. In an interview I will never find again, someone asked Noam Chomsky about the failures surrounding the American debacle in Afghanistan. He responded that it was above all a reflection of the distorted and inaccurate intelligence assessments that pollute the thought of American foreign policy planners and military strategists. Random people on the internet, he said, had a better view of the situation from the start.
Exactly the same phenomenon plagues official responses to Corona. The problem with curated information isn’t just that it is slow, subject to inertia, and produced by insular out-of-touch functionaries. Because the information has political importance, there are incentives everywhere to manipulate and degrade its quality. Bureaucratic actors will lie about what is going on to curry favour, save face or evade blame. What is more, many advisers, analysts and modellers are only in the position of providing analysis in the first place, because we need more women in STEM, or because they tell the Faucis of the world what they want to hear, or because they have the right combination of sociopathy and narrow-mindedness necessary to ascend complex bureaucratic hierarchies.
Corona policies really are as stupid as they look. Politicians and bureaucrats have locked themselves into a sad parody of the film Contagion, and their increasingly unsustainable, erratic behaviour merely reflects their desperation.
Covid Scariant With “Horrific Mutations” Arrives In Time For Christmas
By Richie Allen | November 25, 2021
A new covid variant has emerged, just in time for Christmas. It was discovered in Botswana, but is believed to have shown up in South Africa and Hong Kong too. Scientists are claiming that it has 32 “horrific mutations” and might be capable of beating the vaccines.
According to The Mail Online:
British experts have sounded the alarm over a new Covid variant believed to have emerged in Botswana that is the most mutated version of the virus yet. Only 10 cases of the strain, which could eventually be named ‘Nu’, have been detected so far.
But it has already been spotted in three countries, suggesting the variant is more widespread.
It carries 32 mutations, many of which suggest it is highly transmissible and vaccine-resistant, and has more alterations to its spike protein than any other variant.
Professor Francois Balloux, a geneticist at University College London, said it likely emerged in a lingering infection in an immunocompromised patient, possibly someone with undiagnosed AIDS.
Dr. Tom Peacock is a virologist at Imperial College London. He practically shit himself when he looked at the new covid strain, describing it as “horrific.”
He said that B.1.1.529 (its scientific label) has the potential to be worse than any other covid mutation including the world-dominant Delta strain. Good God! Close the borders. Bomb Botswana back to the Stone Age. Cancel Christmas.
They’re nothing if not predictable eh? Covid-19 is the gift that keeps on giving, or taking, depending on your perspective of course.
Why another lockdown would be met with mass non-compliance
By Andrew Devine | TCW Defending Freedom | November 25, 2021
LIKE many people, I went along with the first lockdown. I wasn’t very keen, and I was somewhat critical of it, but I believed the lie that it would be a temporary one-off measure. From the time of the second lockdown, I have been vehemently opposed to the policy. While I have never denied that Covid can be a nasty life-threatening illness for some people, I am critical of the way that governments have manipulated data to exaggerate the extent of the threat.
When Covid 19 vaccines were first rolled out in the UK and around the world in late 2020, we were promised by Western governments and their teams of scientific ‘experts’ who wield enormous, unaccountable power, the media and Big Pharma that the vaccines were a game-changer and that mass vaccination would lead us back to some kind of normality. I was initially very resistant to take the vaccine because it is a new drug with no long-term data regarding side effects and risks. I also have two autoimmune conditions, and while they are easily treated, I am genetically predisposed to a third one that can be quite serious.
However, in the end, and with much hesitation due to the already known side effects and autoimmune risks, I took the Pfizer vaccine. I did so for several reasons. Firstly, I am around my elderly parents a lot, and I thought I would be protecting them as I believed the ‘experts’ that the vaccines would significantly reduce transmission.
This has turned out to be false.
Secondly, I was convinced by the data that seems to show that getting vaccinated almost entirely eradicates the chances of someone my age ending up in hospital with a severe case of Covid. Due to fitness and age, my risk of serious illness was already low, but as a neurotic who is sometimes prone to viewing the glass half empty, I admit to having moments when I worried that I might be one of those outliers for my age group cut down prematurely by Covid and so this was an added factor, but not the main one, in my capitulation. The final reason was because I currently reside in the Republic of Ireland where the government have been very keen to enforce some of the harshest lockdowns globally with draconian rules on both inward and outward travel as well as compulsory vaccine certificates for access to various sectors. Therefore, one of my main reasons for getting jabbed, while I still defended vehemently the rights of others not to do so, was that I thought I would be doing my bit to put an end to these hideous lockdowns and other excessive restrictions once and for all. Looking at what has happened in Austria and Holland and the refusal of both the UK and Irish governments to rule out more lockdowns, it is now clear how very wrong I was. Another way of putting it is that I’ve realised how easily I have been duped.
In recent weeks, I have become even more sceptical of everything that the UK and Irish governments and their appointed health experts tell me with regard to Covid-19. For a start, if they were wrong about the effectiveness of the vaccines with regards to transmission, why would I trust them with regards to how rarely serious side effects occur? There would be far more political and career capital at stake to motivate suppression of this data. I’m not accusing governments, scientific ‘experts’ or Big Pharma of doing so, merely noting that there is a much bigger price for them to pay if they didn’t.
With regards to coercive measures and the removal of rights from the unvaccinated, governments don’t even have recourse to the dubious argument that it’s for the greater good as we now know that the vaccinated can also transmit the virus. I keep making the argument to vaccine zealots that people can exercise their right to abstain from taking any medications due to the risks of side effects, but that many governments now believe this right should be removed solely with regard to Covid vaccines. There is no compelling moral argument for why Covid vaccines fall into an exceptional category that warrants the state using coercion whether it be direct (vaccine mandates) or indirect (segregation and removal of rights) to force its citizens to reluctantly take a medicine they would otherwise refuse.
The enthusiasm for vaccines and excessive restrictions are now articles of faith for their proponents. It has become an ideological stance that no amount of reasoned scrutiny can alter. Rational analysis of the extent of the threat from Covid and strategies to deal with it have been abandoned for the simplistic dogma of ‘vaccines good’ and ‘lockdowns and restrictions good’. The truth is much more nuanced than the doom-mongering analysis which permeates the mainstream media. Lockdown enthusiasts and vaccine zealots, like all ideologues, have opponents whom they despise and whom they seek to demonise. This is why only ‘far Right conspiracy theorists’ and ‘anti-vaxxers’ would have an issue with mandatory vaccines which can have serious side effects being given to children to protect them from a virus that rarely makes children very ill.
How have we reached a stage in Western liberal democracies when those of us questioning and disagreeing with extreme public health policies that strip individual citizens of their inalienable rights under false pretences are the ones deemed to be the extremists? Asking questions and being critical of government policy is now viewed by the obedient media class and the political elites and partisan scientific ‘experts’ they serve as being synonymous with the far Right. In truth, it is your democratic duty to question all government policies and especially more so those that would remove your fundamental freedoms. For any government to wish to suspend the rights of its citizenry on a temporary basis, it must first seek consent from the people after explaining the exceptional circumstances in which they seek to do so. There has been no public debate and little media scrutiny across the English-speaking world about whether the threat posed by Covid-19 meets the very high threshold that could justify temporary lockdowns and other extreme restrictions imposed on the citizenry.
If the UK or Irish government or any of the devolved administrations try to impose another lockdown, I predict there will be mass non-compliance. It is very likely that much of the population of these islands will conclude that if several lockdowns, mask mandates and ‘game changing’ vaccines have not eradicated transmission, why comply with another lockdown, possible financial ruin and separation from loved ones? What would be the purpose? As someone once said (it wasn’t actually Einstein): ‘Insanity is doing the same thing over and over and expecting different results.’
This perverse ban on ivermectin, cheap and proven to work
By Kathy Gyngell | TCW Defending Freedom | November 23, 2021
GIVEN the feared winter resurgence of Covid infection despite, or because of, the government’s mass vaccination programme, the continued ban on ivermectin in this country becomes ever more perverse.
It beggars belief that the British public is still denied access to this proven prophylactic and treatment. If the public health authorities are genuinely worried about pressure on hospitals, why have not the Medicines and Health products Regulatory Agency (MHRA), Public Health England, the NHS and Department of Health all gone flat out over this last year to approve ivermectin with the same zeal they gave emergency authorisation to the limited trialled, novel gene therapy, Covid vaccines?
The answer is widespread misinformation from the top down. Put ‘ivermectin’ into the Google search box and what do you come up with? Topping the list is a warning from the US Food and Drug Administration (FDA) why it should NOT be used to treat or prevent Covid-19. Their reason? It’s as simple as the fact that they have not approved it and, because they have not approved, it cannot be used. Trials are ongoing they say. Maybe some are. But plenty have been completed, as Dr Pierre Kory’s paper (he was the lead author) ‘Review of the Emerging Evidence Demonstrating the Efficacy of Ivermectin in the Prophylaxis and Treatment of Covid-19’, published by the American Journal of Therapeutics earlier this year, made quite clear.
By contrast with this detailed review of the evidence the FDA’s substantive concern appears to rest on random reports of harms deriving from self-medication with ivermectin.
The BBC not to be behindhand entered the fray with its customary selective and biased take on ‘the science’. Its recent report entitled ‘How false science created a Covid ‘miracle’ drug‘ made not even the most minimal of checks on the veracity of their assertions, which are pulled apart here. A letter sent to a programme journalist in response to their request for information (in advance of transmission) by Dr Tess Lawrie, the Director of the British Ivermectin Recommendation Development Group (BIRD), an advocacy group of clinicians and scientists from around the world, setting out the science behind the case for authorising it, was completely ignored. Her letter can be found here.
How the BBC came not to ask how it was that remdesivir – a standard medication for Covid in the UK – was approved on the basis of one study when ivermectin, with 63 studies, of them 31 Randomised Controlled Trials (RCT), 7 meta-analyses, 32 Observational Controlled Trials (OCT), multiple country case studies, expert opinion, patient testimony ALL pointing in favour of the medication, was not, is inexplicable.
This is the news source the public is still told to trust.
A blog posted on BIRD last week asked whether there are indeed any genuine gripes about the quality of the evidence, as the FDA and others suggest?
No, there are not. The author argues it is down to a misinformation campaign based on misleading information produced by high profile public health agencies, like the World Health Organisation, itself a victim of disinformation tactics, that has been ‘perpetrated by a minority of corporations to manipulate and delay government action on matters that would adversely affect their income and profit’. Speculation of course. But every indication points that way.
As reported extensively in TCW Defending Freedom, for example here, the WHO is subject to the huge financial influence of the Bill and Melinda Gates Foundation, the organisation’s second biggest donor. Since one of the BMGF’s long-term interest is in delivering vaccines, why would they show any interest in promoting the use of cheap, old repurposed medications in the treatment and prevention of Covid-19? It’s for the very same reason that ivermectin has proved of so little interest to Big Pharma -it’s hardly the money spinner that indemnified world-wide vaccination is.
Worse perhaps than what these big interests have not done is what they have actively done to discredit ivermectin. The BIRD blog relays an analysis by Dr Kory setting out what the WHO ‘did’ with the ivermectin evidence. He says it:
· Failed to publish a pre-established protocol for data exclusion
· Excluded two ‘quasi-randomised’ controlled trials (RCTs) with lower mortality
· Excluded two RCTs that compared ivermectin to or gave it together with other medications, all reporting lower mortality
· Excluded seven other available ivermectin RCT results
· Excluded all RCTs and observational controlled trials (OCTs) investigating ivermectin in the prevention of Covid-19
· Excluded 13 OCTs, more than 5,500 patients, that showed reductions in mortality
· Excluded numerous published and pre-print epidemiologic studies.
The bottom line, however, remains – if ivermectin is good enough and provenly effective for the more than 20 lower-income countries which do distribute it and also benefit from lower Covid rates, why are the populations of wealthier nations and individuals still being denied?
It’s a point that clearly has bothered the chairman of the Tokyo Medical Association, Dr Haruo Ozaki, who would recommend ivermectin for Covid patients, noting that the parts of Africa that use ivermectin to control parasites have a Covid death rate of just 2.2 per 100,000 population, compared with 13 times that death rate among African countries that do not use ivermectin.
‘I would like,’ said Dr Ozaki, ‘the government to consider treatment at the level of the family doctor’ with the informed consent of the patient. So would we.
RFK, Jr.’s ‘The Real Anthony Fauci’ #1 Overall on Amazon Bestseller List
The Defender | November 19, 2021
Robert F. Kennedy, Jr.’s latest book, “The Real Anthony Fauci: Bill Gates, Big Pharma, and the Global War on Democracy and Public Health,” today claimed the #1 spot overall on Amazon’s bestseller list.
The book, released Tuesday, debuted at #2, but moved up on the list today. The book is also in the #1 spot on the Kindle books bestseller list.
“Conventional wisdom holds you can’t have a bestselling book without plenty of media attention” — and no surprise, ‘The Real Anthony Fauci’ has had a near-total news media blackout,” said Kennedy, Children’s Health Defense chairman and chief legal counsel. “Given that, it feels great to report this good news.”
The hardcover version is available at Barnes & Noble, Amazon, IndieBound, Bookshop.org, Target, Walmart, Books-A-Million and at independent booksellers throughout the U.S. and Canada.
The Real Anthony Fauci” chronicles Fauci’s 50-year tenure at the National Institute of Allergy and Infectious Diseases (NIAID), including his long list of failures.
The book also and sheds light on previously little-known experiments using animals and orphaned children. It recounts recent NIAID experiments performed on beagle puppies. In a recent letter to Fauci, U.S. Rep. Nancy Mace (R-S.C.) and a bipartisan coalition of Congress members described the experiments as ”cruel.”
Social media picked up on the revelations, with trending hashtags #AvengeTheBeagles and #ProtectOurChildren.
“Books might literally be the last bastion of free speech in America,” said Kennedy.“ They can’t be easily erased, deleted, canceled, or disappeared.”
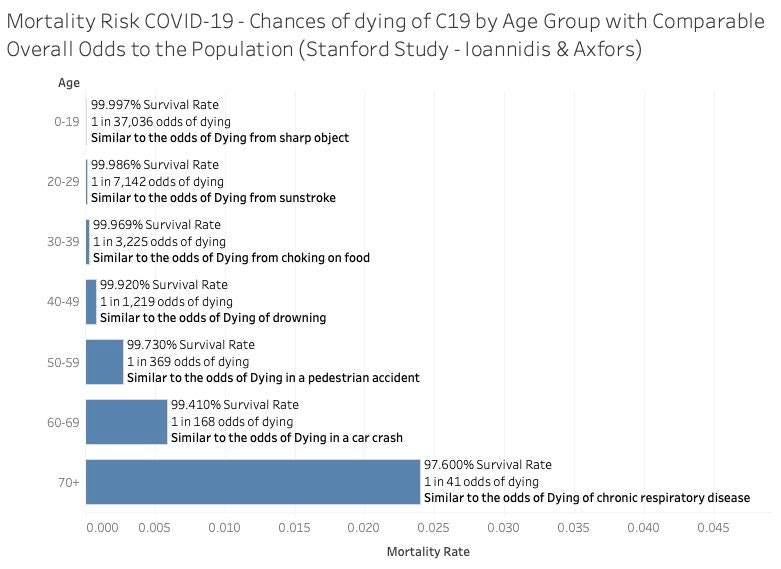
Chances of dying from COVID
By Joel S Hirschhorn | November 21, 2021
Nice table showing relatively low lethality from COVID relative to other risks; even for older people:
Featured Video
Iran is (probably) collecting tolls, and why Asia stopped buying oil from the US
or go to
Aletho News Archives – Video-Images
From the Archives
The Great Recycling Scam
By Dr. Vernon Coleman – 21st Century Wire – September 2, 2022
Recycling was introduced, worldwide, as a tool to teach citizens to become compliant.
Forcing citizens to sort their rubbish into up to nine separate bags or boxes every week had absolutely nothing to do with ‘saving the planet’ and everything to do with teaching citizens (through a mixture of fines and shame) to behave ‘responsibly’ i.e. to do as they were told without looking too closely at the rationale of what they were being told to do.
The recycling never had anything to do with protecting the planet, of course. Most of the rubbish sorted, washed and collected in the UK was taken abroad, by lorry or ship or train, and burnt or dumped. It was, quite simply, impractical and not cost effective to recycle the material that had been collected. And, of course, collecting the sorted rubbish involved massive costs in terms of cash and pollution.
Today, the recycling business has reached an apogee of lunacy. Councils introduce ever more complex rules and fees. They refuse to take away much of the waste that is collected. And those wanting to take their rubbish to a ‘recycling’ centre will probably have to make an appointment and answer a host of questions.
It is no surprise that fly-tipping has become a major problem. The biggest causes of plastic in the sea are dumped fishing gear and plastic waste (much of it officially designated as recycled) which has been dumped by ships.
The good news, however, is that in Britain, recycling rates are falling. More and more people have become aware that the whole recycling movement was just another piece of manipulative trickery.
Blog Roll
 Aletho News
- Beyond Netanyahu: what Israel’s election means for Palestinians
- Lithuania plans universal conscription
- Lies, Damn Lies, and Ukraine News
- Financial Times rejects Nordic demands to correct Putin call story – media
- The Case for Less Unity in Europe
- Ukraine expands minority rights under EU pressure – but Russians remain excluded
- Albania takes anti-riot crackdown cue from France
- The interest of the House of Rothschild in Ukraine
- Pentagon fires top military planner
- Three tankers hit mines on unauthorized Hormuz route: IRGC Navy
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!

