Top Misinformation Article Attributed to Chicago Tribune
By Dr. Joseph Mercola | September 2, 2021
According to Facebook’s content transparency report for the first quarter of 2021, released in mid-August 2021, the most popular article shared on the platform between January 2021 and March 2021 was about a 56-year-old Miami, Florida, obstetrician who died two weeks after his first Pfizer injection.1
The story initially ran in the South Florida Sun Sentinel 2 April 8, 2021, and was republished by the Chicago Tribune that same day.3 The doctor, Dr. Gregory Michael, received his first dose December 18, 2020.
Three days later, he developed small spots on his hands and feet, which prompted him to go to the emergency room, where they found he had an abnormally low blood count. Platelets stop bleeding by clotting, and when platelets drop too low, internal bleeding can occur, resulting in what looks like blood blisters on the skin.
Michael remained in intensive care for two weeks, but no matter what they did, his platelet count refused to budge. During the night of January 3, 2021, he died of a massive stroke. According to the coroner, the COVID injection could not be ruled out as a contributing or causative factor.
In a Facebook post, Michael’s widow stated he’d been “very healthy” and that he’d been a COVID-19 vaccine advocate. His death caused her to question the safety of the shot, however.
“I believe that people should be aware that side effects can happen, that the vaccine is not good for everyone and in this case destroyed a beautiful life, a perfect family and has affected so many people in this community.” she wrote. “Please do not let his death be in vain please save more lives my making this information news.”4
Even Viral Content Has Minor Reach
According to The New York Times,5 Facebook held off on publishing the first-quarter report for fear the findings might “look bad for the company.” Executives decided they wanted to make some “key fixes to the system” before releasing it. That’s why it wasn’t published until August.
Interestingly, the report reveals that even when something goes viral, the total number of views is still a tiny fraction of the overall content. Even the biggest accounts make up but a small portion of overall content views. Combined, the top 20 accounts with the most views during the first quarter — which included UNICEF, The Dodo and LADbible — accounted for only 1.18% of all U.S. content views.
As noted in the report, this “shows that, even though it may seem like a page or post has extensive reach on the platform, that isn’t the case when measured against the total amount of content available on the platform.”
Facebook Calls Out CCDH for Manufacturing ‘Faulty Narrative’
As you may know, an obscure one-man organization funded by dark money called the Center for Countering Digital Hate (CCDH) has published several reports, including “The Anti-Vaxx Playbook,”6 “The Disinformation Dozen”7 and “Disinformation Dozen: The Sequel,”8 in which the founder, Imran Ahmed — an unregistered foreign agent — claims to have identified the top most influential “anti-vaxxers” in the U.S.
In a completely unexpected turn of events, Facebook is now calling out the CCDH for having manufactured a faulty narrative without evidence against the 12 individuals targeted in its reports (myself included).9
This is important, seeing how the CCDH reports have been the primary “reference” source of authority used by media and government officials to smear, threaten and infringe on American citizens’ right to free speech.
The U.S. Department of Homeland Security even lists promulgating “false narratives” around COVID-19 as a top national security threat, which basically puts a “domestic terrorist” target on the backs of those of us who have been identified by the CCDH as the most prolific “superspreaders” of COVID misinformation.
As reported by GreenMed Info :10
“Google now shows an astounding 84,700 search results for CCDH’s defamatory phrase ‘disinformation dozen. ’Amazingly, this includes 16,000 news stories within the international press, approximately 100% of which are word-for-word amplifications of CCDH’s claims/defamatory statements and reported uncritically as fact.
In addition, the Surgeon General Vivek Murthy, the White House Press Secretary Jen Psaki, and president Biden all used CCDH’s report as the sole source for their own defamatory accusations, reaching a dangerous rhetorical climax on July 20th when Biden stated that these 12 individuals are literally “killing people” [by spreading misinformation].”
No Evidence to Support ‘Misinfo Superspreader’ Claim
In an August 18, 2021, Facebook report, Monika Bickert, vice president of Facebook content policy, sets the record straight, and in the process, demolishes the CCDH’s claims:11
“In recent weeks, there has been a debate about whether the global problem of COVID-19 vaccine misinformation can be solved simply by removing 12 people from social media platforms. People who have advanced this narrative contend that these 12 people are responsible for 73% of online vaccine misinformation on Facebook. There isn’t any evidence to support this claim …
That said, any amount of COVID-19 vaccine misinformation that violates our policies is too much by our standards — and we have removed over three dozen Pages, groups and Facebook or Instagram accounts linked to these 12 people, including at least one linked to each of the 12 people, for violating our policies.
We have also imposed penalties on nearly two dozen additional Pages, groups or accounts linked to these 12 people, like moving their posts lower in News Feed so fewer people see them or not recommending them to others. We’ve applied penalties to some of their website domains as well so any posts including their website content are moved lower in News Feed.
The remaining accounts associated with these individuals are not posting content that breaks our rules, have only posted a small amount of violating content, which we’ve removed, or are simply inactive.
In fact, these 12 people are responsible for about just 0.05% of all views of vaccine-related content on Facebook. This includes all vaccine-related posts they’ve shared, whether true or false, as well as URLs associated with these people.”
It’s worth restating the key point in this quote: Combined, the top 12 individuals and organizations identified by the CCDH as being responsible for a whopping 73% of vaccine misinformation on Facebook, are in fact only responsible for 0.05% of vaccine-related content — 1,460 times lower than the CCDH’s outrageous claim. That’s no small discrepancy.
CCDH Claims Blasted as Unjustified and Biased
Bickert goes on to refer directly to the CCDH report “The Disinformation Dozen,”12 stating:
“The report13 upon which the faulty narrative is based analyzed only a narrow set of 483 pieces of content over six weeks from only 30 groups, some of which are as small as 2,500 users.
They are in no way representative of the hundreds of millions of posts that people have shared about COVID-19 vaccines in the past months on Facebook.
Further, there is no explanation for how the organization behind the report identified the content they describe as ‘anti-vax’ or how they chose the 30 groups they included in their analysis. There is no justification for their claim that their data constitute a ‘representative sample’ of the content shared across our apps.”
CCDH Meets Definition of ‘Hateful Extremists’
Ironically, while the CCDH claims to “counter hate” online, and Ahmed sits on the Steering Committee of the U.K. Commission on Countering Extremism, CCDH itself actually meets the Commission’s definition of hateful extremists.14 In the 2019 Commission document, “Challenging Hateful Extremism,” the term is defined as:15
“Behaviours that can incite and amplify hate, or engage in persistent hatred, or equivocate about and make the moral case for violence; And that draw on hateful, hostile or supremacist beliefs directed at an out-group who are perceived as a threat to the wellbeing, survival or success of an in-group; And that cause, or are likely to cause, harm to individuals, communities or wider society.”
In addition, in the forward of the report, lead commissioner Sara Khan notes that “Hateful extremists seek to restrict individual liberties and curtail the fundamental freedoms that define our country.”
All of these definitions and clarifications of what hateful extremism is fit the CCDH to a T. Ahmed manufactured data to create a false narrative that 12 individuals pose a threat to the well-being and survival of the whole world, and then used that narrative to incite hate against us and curtail our freedom of speech.
Who Fact Checks the Fact Checkers?
In related news, the self-appointed arbiter of factual truths, NewsGuard, has had to backpedal in recent months and issue dozens of corrections to “fact checks” in which they’ve labeled the Wuhan lab leak theory as a debunked conspiracy theory with no basis in fact.
Since the beginning of the COVID pandemic, NewsGuard has wrongly down-rated 225 websites for articles mentioning the lab leak theory.16 In reality, there’s far more evidence to support the lab leak theory than any other theory, but it took over a year before the weight of this evidence became too obvious for the media to ignore.
NewsGuard’s erroneous fact checks were recently highlighted in an August 11, 2021, report by the American Institute for Economic Research (AIER).17
AIER decided to take a closer look at NewsGuard after receiving a request for comments on a NewsGuard fact check article regarding AIER and the Great Barrington Declaration — a statement written by public health experts from Harvard, Stanford and Oxford that calls on government to implement focused protection rather than lockdowns and self-isolation. AIERS investigation found that:18
“… NewsGuard falls far short of the very same criteria for accuracy and transparency that it claims to apply to other websites. Most of the company’s fact checkers lack basic qualifications in the scientific and social-scientific fields that they purport to arbitrate.
NewsGuard’s own track record of commentary — particularly on the Covid-19 pandemic — reveals a pattern of unreliable and misleading claims that required subsequent corrections, and analysis that regularly conflates fact with opinion journalism in rendering a judgement on a website’s content.
Furthermore, the company’s own practices fall far short of the transparency and disclosure standards it regularly applies to other websites … NewsGuard’s staff primarily evaluates scientific claims by appealing to the authority of public figures who they designate as ‘experts’ on the subject in question.
Their approach generally avoids direct examination of the evidence surrounding contested claims, and instead cherry-picks a figure to treat as an authoritative final word … many of their preferred authorities are political officeholders rather than persons trained in scientific or social-scientific methods.
By selectively curating cherry-picked political authorities rather than evaluating evidence directly, NewsGuard’s approach to fact-checking effectively sidesteps the scientific method. This strategy is rendered even more problematic by the general lack of scientific expertise within NewsGuard’s team of writers.
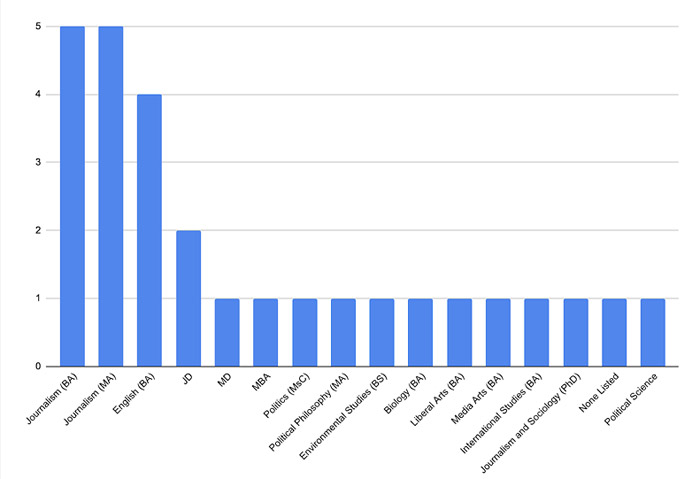
We examined the educational credentials, including the highest degree listed, for 28 publicly identified staff members on NewsGuard’s website. The company’s staff page reveals shockingly little expertise in either the hard sciences such as medicine or social sciences such as public policy, economics, and related fields …
Most NewsGuard articles on Covid-19 topics and policies are written by [NewsGuard Deputy Editor for Health, John] Gregory, whose only identified qualification is a bachelor’s degree in Media Arts … Gregory would not qualify as an expert in most of the fields he is responsible for fact-checking …
Of course, non-experts have every right to offer opinions on scientific and social-scientific matters. Whether or not they should be taken seriously as fact checkers or act as arbiters of scientific disputes is another question entirely.”
NewsGuard Staff by Field and Highest Degree Attained
NewsGuard Apologizes for Erroneous Fact Checks
After being confronted about its erroneous fact checks on the lab leak theory, NewsGuard offered the following apology in a statement sent to AIER:19
“NewsGuard either mischaracterized the sites’ claims about the lab leak theory, referred to the lab leak as a ‘conspiracy theory,’ or wrongly grouped together unproven claims about the lab leak with the separate, false claim that the COVID-19 virus was man-made without explaining that one claim was unsubstantiated, and the other was false.
NewsGuard apologizes for these errors. We have made the appropriate correction on each of the 21 labels.”
AIER commented on the apology:20
“Gregory and his colleagues appear to have simply decided that their own premature dismissal of the lab leak hypothesis equated to ‘fact’ and proceeded to penalize other sites not for factual errors, but rather for diverging from NewsGuard’s own editorial position on the same subject.
When this position turned out to be mistaken, NewsGuard pivoted to remove the errors — albeit in non-transparent ways that downplay the significance or pervasiveness of their mistake.”
NewsGuard Fails to Fulfill Its Own Credibility Criteria
In their report, AIER goes on to apply the criteria NewsGuard uses to evaluate a website’s credibility to NewsGuard itself. It’s ranking? A paltry 36.25 out of 100. According to AIER:21
“This website fails to adhere to several basic journalistic standards, and should be used with extreme caution as a source for verifying the reliability of the websites it purports to rate …
When we see fact checkers like NewsGuard, who not only fail to uphold their high-sounding principles but even publicly encourage working with the government to suppress speech, we should raise red flags.”
The NewsGuard ratings are meant to influence the reader, instructing them to disregard content with cautionary colors and cautions. That it would serve as the thought police of the technocratic establishment that seeks to silence dissent and bury information that doesn’t help move the Great Reset agenda forward is no surprise.
Especially considering its primary startup capital came from Publicis Groupe,22 a PR group that represents most of Big Pharma, including vaccine makers, and Big Tech. NewsGuard is also backed by Microsoft23 and Google.
The Publicis Groupe has been manipulating what people think about commercial products for nearly a century. Over that century, this advertising and communications firm bought or partnered with targeted advertising avenues, beginning with newspapers, followed by radio, TV, cinema and the internet.
With revenue avenues secured, Publicis’ clients and partners built a global presence that dominated the advertising world. Be it tobacco or sugar, Publicis Groupe found a way to promote and strengthen big industries. Publicis was recently sued24 for its deadly and illegal marketing of Purdue Pharma’s opioid products.
When you consider that Publicis describes its business model approach as putting clients and their needs and objectives at the center of all they do so their clients can “win and grow,” it’s easy to see what’s driving NewsGuard.
Overall, NewsGuard is just another big business aimed at keeping the chemical, drug and food industries, as well as mainstream media, intact by discrediting and eliminating unwanted competitors and analysts who empower you with information that runs counter to any given industry’s agenda.
If you’re as disturbed by censorship as I am, be sure to contact your local library today to find out if they’re one of the more than 700 libraries using NewsGuard. If they are, then ask them if they’re aware of NewsGuard’s censorship of truthful news that is now encroaching on scientific freedom and threatening the very roots of our democracy.
If your local library is using NewsGuard, it would be helpful to start a campaign to get it removed. Contact your neighbors and let them know what is happening so they can kick out this public health threat. Likewise, whenever you see someone referencing reports by the CCDH, call them out on it.
Sources and References
- 1 USA Today August 23, 2021
- 2 Sun Sentinel April 8, 2021
- 3 Facebook Heidi Neckelmann
- 4 Chicago Tribune April 8, 2021
- 5 New York Times August 20, 2021 (Archived)
- 6 The Anti-Vaxx Playbook (PDF)
- 7, 12, 13 CCDH, The Disinformation Dozen
- 8 Misinformation Dozen: The Sequel
- 9, 11 Facebook August 18, 2021
- 10 GreenMed Info August 19, 2021
- 14 Greenmed Info March 25, 2021
- 15 Challenging Hateful Extremism 2019
- 16, 17, 18, 19, 20, 21 AIER August 11, 2021
- 22 Washington Post March 3, 2018
- 23 axios.com August 23, 2018, NewsGuard Launches First Product With Help From Microsoft
- 24 Reuters May 6, 2021
Named, shamed and fined – the maskless marauders

By Frederick Edward | TCW Defending Freedom | September 2, 2021
MAGISTRATES have been busy enforcing the laws of Covid-land, with more than 20 miscreants in Northamptonshire fined last week for failing to abide by the rules. They are named and shamed in the Northamptonshire Telegraph, the digital equivalent of the village stocks.
There are a few things to glean from the list of those convicted. We have a small insight, firstly, into the demographic shifts that are happening in the small towns of England such as Corby, Kettering and Wellingborough, with M Jatczak, K Marjani and P Blaga making an appearance.
The relative youth of those who found themselves in court is telling. J Ayre, 22, went to an outdoor gathering of more than two souls, for which he must pay £248. C Hulse, also 22, went to an indoor gathering of more than two. She has to pay £344.
While we do not know the circumstances of these individuals, it is a reminder of the price the youth have been made to pay throughout the last 18 months or so. Stuck in small accommodation or at home with their parents, they have suffered a disproportionate impact from restriction on movement. Moreover, the fines are not insignificant for those unlikely to have much disposable income.
Those caught refusing to abide by Covid regulations include:
U Aurica, 51, fined £344 for being in a corner shop without a mask;
C Oxlade, 21, found maskless in Budgens, as was E McIlreavy, 29, at Asda. Both fined £344;
L Stachura, 29, fined £344 for not wearing a face mask in a pizza takeaway.
R Gilderleft, 26, ‘left his home . . . without reasonable excuse’. He must pay £344.
The local paper website does not make it clear, but the prosecutions are likely to have been under the Coronavirus Act and Health Protection Regulations. Both pieces of legislation were passed in March 2020, the former without a vote in the Commons and the latter presented to the House only after it had come into force.
This is just a snapshot of cases involving Covid-19 rules. The Crown Prosecution Service reported in May 2021 – more than one year into the pandemic – that more than 1,800 had been brought to court, though a high proportion were subsequently identified as incorrectly charged. Indeed, between March 2020 and March 2021, all charges brought under the Coronavirus Act were incorrect, with not a single prosecution resulting from this large expenditure of police and court time.
Around 80 per cent of prosecutions brought under the Health Protection (Coronavirus, Restrictions) Regulations were correctly charged: it is under this legislation, which includes restrictions on leaving home, social gatherings and the enforcement of mask-wearing, that our Northamptonshire rebels were probably charged.
That a man living in England can be sentenced for leaving his own home is a sign of how far down the path of illiberalism we have strayed: never before in our history have we accepted such perverse rules, a fact made all the more unconscionable by their disproportionality.
What concerns me doubly is that they are enforced with such officiousness and subsequently reported so eagerly by an unquestioning and uncritical press. The Northamptonshire Telegraph says sanctimoniously: ‘The defendants were the latest to be convicted after violating emergency rules – which were designed to slow the spread of coronavirus – between January and April. Many of them were punished after failing to stick to the laws in January or February, at a time when many thousands died as the virus spiraled [sic] out of control.’
In any society which abandons the precepts of freedom, there will be a large group of people who willingly become the enforcers of the new regime. Intoxicated with power, they thrive amid a sea of petty regulations.
Naturally, one will not find names such as Matt Hancock of Neil Ferguson on the lists of those convicted. While the man on the street has the book thrown at him for daring to venture into a supermarket without a mask or seeing some friends, those in the right places and with the right connections can carry out their assignations without repercussion.
We can be convicted and fined for going to a takeaway without a mask, while our elites philander and jet around the world.
How much longer will we tolerate these glaring double standards?
Victoria premier extends lockdown, again, as Aussie police granted power to covertly hack citizens’ phones & alter data

Police arrest a protester during an anti-lockdown rally in Melbourne on August 21, 2021 as the city experiences its sixth lockdown © AFP / William West
RT | September 1, 2021
Victoria’s premier has announced that a statewide lockdown will remain in place until most residents are vaccinated, just days after Australia adopted new legislation giving sweeping surveillance and spy powers to police.
Draconian measures covering the entire southeast Australian state will only start to be eased once 70% of the population receives at least one dose of the Covid vaccine, Premier Dan Andrews decreed on Wednesday. The government said it hoped to reach this target on or around September 23.
In a written statement, Andrews claimed that lifting restrictions would “overrun” the state’s healthcare system. With a population of around 6.6 million, Victoria currently has less than 60 Covid hospitalizations.
The entire state has been under strict lockdown for nearly a month. After shutting down non-essential activity in Melbourne, Andrews decided to extend restrictions to the entire state on August 5, citing the alleged detection of Covid-19 in wastewater 236km (147 miles) from the city. He was later forced to admit that the sewage in question had actually tested negative for the virus. Nonetheless, the statewide lockdown, which was only supposed to last seven days, has remained in place.
Currently, Victorians are not allowed to venture more than five kilometers (3.1 miles) from their homes – and only for “essential” activities. Andrews promised to increase the travel radius to 10km once the state’s vaccination benchmark is met.
The new conditions for easing lockdown were revealed a week after Australia passed a controversial bill giving police the ability to secretly seize and alter internet accounts.
Known as the Surveillance Legislation Amendment (Identify and Disrupt) bill, the legislation allows the Australian Federal Police (AFP) to take over, and modify or delete, the accounts of cybercriminal suspects.
Although authorities claim that the law will help crack down on pedophiles, terrorists and drug traffickers, many on social media expressed concern that the extensive powers were further evidence of Australia sliding into authoritarianism.
The Australian state has recorded 822 Covid-linked deaths since March 2020. To put this figure in perspective, more than 950 Victorians have died from suicide over the same period.
The state’s draconian restrictions have been blamed for fueling a mental health crisis, especially among the young. While only one Australian aged 19 or younger has died with Covid-19, eight teenage girls have taken their own lives in Victoria in the first seven months of the year.
Supporting Doctors’ Rights To Speak, Free From Censorship
doctors4covidethics.org

Dr. Paul Oosterhuis is an Australian anaesthetist with over thirty years experience, including in critical care and resuscitation, who urgently needs your support.
He is facing a hearing by the Medical Board of NSW for posting information on social media regarding COVID-19. His posts related to early treatment and prophylaxis, PCR tests, and risk-benefit calculations regarding COVID-19 vaccination and lockdowns (scroll down for details). His hearing is on September 3rd. Please help him by signing and sharing this petition.
We are practicing doctors and allied health professionals and/or scientists and academics and/or members of the public and/or represent professional organisations. We support the right of Dr Oosterhuis, and that of all doctors, to offer informed medical opinions on COVID-19 and to discuss the available evidence on COVID-19 interventions.
As doctors we too have advised and continue to advise patients and the general public about the medical management of COVID-19 disease and vaccination on the basis of good science. As members of the public we reserve the right to receive honest information, opinion and advice from our doctors, free from government interference.
From Dr Oosterhuis:
Dear colleagues and concerned citizens,
Thank you for taking the time to read this petition.
My name is Dr Paul Oosterhuis. I am an anaesthetist from Australia. I have been called before the NSW Medical Board for a hearing on September 3rd 2021 following anonymous complaints about my social media posts on Facebook regarding COVID-19. I have been advised by the Medical Council that:
“The Medical Council of NSW received two anonymous notifications regarding your activity on social media.
Due to the concerns outlined in the notifications the Council has resolved to convene proceedings under section 150 of the Health Practitioner Regulation National Law (NSW) to consider whether any action is required for the protection of the health and safety of the public or in the public interest.”
Ahead of the hearing I am seeking signatures from my medical and scientific colleagues and members of the public to help me defend my own and all doctors’ rights to offer our informed medical opinions, share our expertise, and engage in open discussion regarding COVID-19.
I am a Sydney University trained medical graduate. I undertook my internship and residency at Prince of Wales Hospital in Sydney, followed by postgraduate training in Anaesthesia at The Royal Prince Alfred Hospital. I have more than 30 years of practice, the first 20 years involving hands-on critical care and resuscitation, and the last 10-plus years as a senior Visiting Medical Officer working in the Sydney Local Health District.
In the social media posts for which I face a Medical Board hearing, I discussed issues such as early treatment and prophylaxis against COVID-19, evidence for government measures such as lockdowns and PCR tests, and evidence regarding risk-benefit analyses of COVID-19 vaccines.
For example:
“I wish you could just add EARLY TREATMENT and drug PROPHYLAXIS …..Tell everyone to take Vit D, Zinc, and EARLY TREATMENT with IVM/ HCQ as evidence based medicine alternatives.”
I provided a link to a presentation by Dr Paul Marik on prophylaxis in support of the post, highlighting a chart of vitamin D versus risk of COVID from Dr Marik’s presentation, to illuminate the low hanging fruit of prophylaxis.
In other posts I questioned the evidence base for the government’s policies of lockdowns and mask mandates, and pointed out that there is evidence of vaccines having low effectiveness and real risks and harms (which are being suppressed), along with harms from the totalitarian lockdowns causing massive damage society-wide.
The risk of Antibody Dependent enhancement of disease, predicted by Dr Geert Vanden Bossche, driven by immune escape from the selective evolutionary pressure of vaccinating with a non sterilising agent is a real and present danger and needs to be discussed. The danger to millions is distressing to me, and discussing that danger is, I believe, unarguably in the public interest.
Early in 2020, I was active in criticising my medical administrators for failure to prepare for an outbreak such as COVID-19 when it was apparent that PPE was being rationed (P95’s were in short supply). I urged my colleagues to perform quantitative fit testing of our available P95 masks in early 2020 during which we found a surprising number of staff failed quantitative fit testing with the hospital issued PPE. This was something I had hypothesised after looking at the number of healthcare workers in Northern Italy catching the disease.
I withdrew from clinical practice last year out of concerns about the increasing incompetence of the health administrators and the rapidly reduced autonomy of doctors to just be able to be a doctor.
Over the last 18 months I have been increasingly concerned about the misinformation and censorship creeping into science and medicine. Fellow physicians were saving lives with early treatment and medication/supplement approaches to prevention but it was THIS that was attacked and censored! People like Dr Paul Marik, Dr Pierre Kory of the FLCCC Alliance, Dr Robert Malone, Dr Geert Vanden Bossche, Dr Michael Yeadon, Dr Vlad Zelenko, Dr Chris Martensen, Dr Eric Weinstein and others are making credible and serious warnings about the gene therapy being coerced upon our populations.
Censoring their work, and the research of experts like Dr Tess Lawrie, Dr Peter McCullough, Dr Sucharit Bhakdi and America’s Frontline Doctors is dangerous.
The Medical Board of NSW is now using intimidation, threatening doctors like myself, who share data which questions the official narrative. I don’t believe that censorship is compatible with good science and good medicine, and I believe that it needs to stop now, in the name of public health and public interest.
I would be very grateful if you could help to support me in my effort to inform as many as possible about their true health choices. My hearing is in a matter of days.
While I wish I did not have to defend my right to speak truthfully as a doctor, the song and video below captures my attitude to fighting for that right. I hope you enjoy it.
With my most sincere thanks,
Dr Paul Oosterhuis
Australia
See also:
NZ Doctors Speaking Out with Science (petition)
The Science Is Clear – The Case Against Mandating Vaccines: One Executive’s POV
SOTT | August 31, 2021
SOTT Editors: We are publishing below, with permission, an email from a top executive at an American company whose clients include 100 of the Fortune 500 companies. The email was sent in reply to another executive asking for the writer’s thoughts on whether he plans to be vaccinated himself or mandate it for his employees as a requirement for returning to the office. All names and company references have been redacted for privacy reasons.
Unlike most of us who are worried about being on the receiving end of vaccine mandates by employers, this executive also has to worry about pressure from other executives and investors to mandate it on others. Few such business leaders are actively fighting for the rights, dignity, peace, and financial security of their employees. This exec is currently the only voice in his company opposing the madness.
Email to the executive:
Hey [REDACTED] – are you giving any thoughts to getting vaccinated with all this Delta variant stuff going on? We’ve been having management committee discussions here about mandatory vaccinations to be able to come in to the office. We have office support people coming in most days that are not vaccinated and some of those with kids don’t want to come in when they are in the office or invite clients into the office for meetings. Just curious as to how you are approaching it. Thx, [REDACTED]
The executive’s reply:
From: [REDACTED]
Date: Fri, Aug 27, 2021 at 9:56 PM
Subject: MY POV on Mandating Employee Vaccinations
To: [REDACTED]
I appreciate you reaching out. What follows is admittedly lengthy (though I do provide my “summary POV” a couple paragraphs down before I dive into supporting detail). I tried to be succinct, but practically speaking your question for me was akin to “hey, so what’s your take on management?” The analogy here being I’m passionate about both subjects so it was hard to choose between sending back a brief 2-minute POV, or filling this email with enough content fit for a university level course. I didn’t know what you had an appetite for, so I just simply did my best to try and be helpful (and heck, even had some fun while I was at it…).
My framework for this entire POV: in the famous words of W. Edwards Deming, “In God we trust. All others must bring data.” As I hope you’ve come to know me by now, I care more deeply about facts & morals than I do ideology or identity politics (for the latter I just don’t give a shit). If you give me a good reason to do something, I am 100% all over it. But if you give me either faulty reasoning or an unethical ultimatum, I simply cannot get on board out of a moral obligation to do what’s right.
So to answer your questions with that sole framework in mind, here’s my summary POV:
(#1) I still have no plans to get vaccinated anytime in the foreseeable future (unless something radically changes the risk equation), given:
(a) The virus at present poses de minimis risk for me personally (and virtually zero risk to any healthy child (a reference to your initial inquiry)); and
(b) Because these vaccines carry –> confirmed low/moderate short term — inferred moderate medium term — and expected high long-term health risk for what could be [though yet unknown] a majority of individuals who get the jab
(#2) I remain vehemently opposed to vaccine mandates for this specific virus (primarily on the basis of (i) 1b above, (ii) the medical literature, which strongly suggests that these vaccines will prolong this pandemic indefinitely through never-ending variants, and thus/therefore (iii) on moral grounds, as, if (i) and (ii) are true, then any decision to proceed with mandates would be nothing short of a descent by the West towards fascism**, the likes of which hasn’t reared its ugly head since the early 20th century. Finally, at a distant, distant second, I am against these mandates from a logistical perspective*.
*E.g., how will you account for boosters (i.e., will those who were vaccinated too far in the past e.g., January and thus have substantially waning transmission protection also be excluded from the office)? What about those who got a different jab (e.g., AstraZeneca, Sputnik, CoronaVac, etc.), each of which has varying levels of effectiveness (and varying levels of effectiveness reduction over time) against different variants? How will you handle those that already had COVID-19 (and therefore (a) have even higher immunity than the vaccinated, and (b) who face higher health risks if they get vaccinated post- natural infection)? What will you do with the immunocompromised (folks with organ transplants, lung problems or cancer patients) who got the vaccine but have low viable antibodies because they require evermore booster shots? What will you do when future variants require different jabs? I could go on, but I trust you get the point. My real question for you is, will you be responsible for coordinating monthly/quarterly management meetings to update & maintain these ever-changing mandate policies covering ever-growing future use cases?
**And if you think I’m exaggerating, look no further than NY State Assembly Bill A416, which proposes forcibly putting carriers of COVID-19 who do not conform to the state’s medical guidelines into something akin to internment camps, where they will be forced into a treatment deemed appropriate by the state and detained indefinitely until they comply. Imagine a U.S. legislative policy so bad, that even Russia Today was able to shit all over it as being far too draconian. And it’s not just the state of NY, but the CDC as well.
===================
Last comments before I dive into supporting details
To not lose sight of being pragmatic as it pertains to your inquiry, I want to point out that at this juncture even a discussion about vaccine mandates is mostly moot.
We already know (confirmed) that those who are vaccinated/infected carry as much viral load as the unvaccinated. Which, coupled with waning transmission prevention efficacy means for all practical intents & purposes those vaccinated and those unvaccinated pose similar risks to one another.
And this is notwithstanding even more cutting edge research (not even yet published i.e. currently pre-print in The Lancet), which suggests those vaccinated carry significantly (upwards of 200x) more viral load than the unvaccinated (which would, if peer-reviewed, flip the risk equation on its head even further in that those vaccinated would pose far greater risk to one another than those unvaccinated). (And it is worth noting that this development would be consistent with what has been found with other vaccines — in this 2017 study, for example, it was assessed that those who were vaccinated for influenza shed 6.3x as much virus as those who are unvaccinated. Crazy stuff.)
All of this is to say, despite the nationwide pushes you’re seeing for private & federal workplace vaccination mandates (which may have made at least some sense much earlier on), such mandates are unfortunately no longer effective models at this stage, unsupported by what we now understand via the latest science. Instead, if you really want to make a difference in improving workplace safety at this juncture, I would suggest implementing either the 1st, or both, of the following policies:
(1) Everyone at the company must perform a daily (pre-commute) self-assessment health survey, whereby all individuals must confirm they are not exhibiting any of the known symptoms of COVID-19 (i.e., if you can’t smell, have fever/chills, shortness of breath, etc., you can’t come in to the office, period), without any pressure from management to respond they are symptom-free.
(2) (Optional) everyone, irrespective of vaccination status, must get tested weekly for COVID-19, such testing to be reimbursed by the company. If you test positive, you aren’t allowed to come in until you test negative.
You asked how we’re handling it, and I can tell you that we’re doing the first one at [my company], and I would recommend utilizing the second one for any in-person company events. That’s it. No mandates. Anything beyond that will lead you into a logistical nightmare (at best), foster a false sense of security as it isn’t effective (worse), and in my humble opinion, is purely unethical (worst of all, which I’d like to think is a decent enough reason not to do something) at this stage.
So anyways, all of the above is the summary of my current POV. What follows below is/are the supporting details for the conclusions I reached in my summary POV 1(a), 1(b), and 2(i) above, if you’re interested in the data.
Always happy to chat/update further as the saga continues ✌
best, [REDACTED]
P.S. if you’re going to skip Parts 1 & 2 below*, then no worries… I get it, I probably wrote far more than you were looking for. But if indeed you do skip them, try to make it to the ‘Closing Thoughts’ section way down below — I’ve sourced a nifty chart down there that might give your colleagues pause in their ongoing discussions about mandates before they consider the unvaccinated to be idiots for whom behavioral mandates are the only appropriate solution.
*Though I highly recommend Part 1 (where it says “TWO OTHER THINGS TO CONSIDER” (then scroll to find #2)) as this contains a suggestion for how to naturally protect yourself from COVID-19.
===================
PART 1: RISK OF COVID-19 DEATH —> DE MINIMIS FOR ME
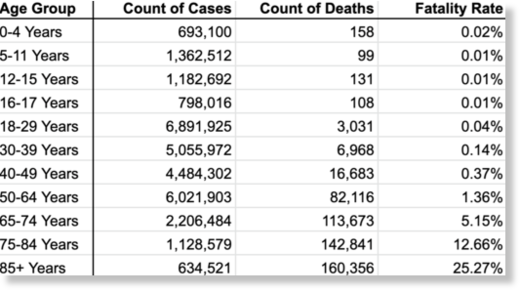
First I’ll address why I do not view COVID-19 as dangerous for me personally: from the CDC’s own data, available here, you can see current the Count of Cases and Count of Deaths by age ->
(Though before I go further, pardon me for abstaining from a lengthy discussion on the reliability of data from an organization that even Dr. Deborah Birx herself — (an individual who received a Meritorious Service Medal from the U.S. Department of Defense in 1991 and a Medal of Excellence from the CDC in 1994) — was quoted as saying she didn’t trust a single word from. Hmm, I wonder why she didn’t “trust” the data, could it be because they were —> overinflating “COVID-19 deaths”? <—… I digress.)
Anyways, according to the CDC, being 32, my “risk” stands at 0.14% (purely averages speaking, irrespective of the analysis below); a “starting statistic” you could call it.
The immediate issue with this data, unfortunately, is we’re only able to count cases with confirmed COVID-19 PCR (or other) test results, undercounting materially true case counts to date. As you might imagine, those asymptomatic do not test themselves regularly or out of nowhere. I mean, personally speaking, I am obviously not testing myself on any basis on any cadence — I’d only get tested if I had reason to. Thus is the reason, that the CDC already stated well early on in this pandemic that true case counts were “likely” to be upwards of 10x higher than we have documented (which they concluded based on widespread antibody testing).
Deaths in the U.S., on the other hand, are religiously tested for COVID-19, capturing the vast majority (if not nearly all) deaths, where a COVID-19 infection was present.
Using these two bits of information from the CDC, we can adjust for a “truer” baseline risk. Now, while I could exercise the luxury of taking on more than a 10x spread (because those younger tend to be more asymptomatic), I’ll be conservative just for the sake of it and just use the “10x average” figure. And so, a true starting statistic for me isn’t 0.14%, but a markedly lower 0.014%.
Next, we can use Exhibit B, taken right from the CDC website:
For… 5% of… [COVID-19] deaths, COVID-19 was the only cause mentioned on the death certificate. For deaths with conditions or causes in addition to COVID-19, on average, there were 4.0 additional conditions or causes per death.
Again, this is nothing new and has been known since very early in the pandemic, as you can see from this study for example listing the leading comorbidities as measured in NY as early as April 2020:

And herein lies my second issue with folks who preach to me that vaccines are necessary for my survival (the first being my initial lowly baseline risk).
Knock on wood, but I have no non- COVID-19 induced comorbidities — zero. My takeaway is just that: for someone like me, COVID-19 is mostly a virus known to exacerbate serious pre-existing conditions to the point of overwhelming the system definitively.
Put another way, imagine a motorcycle rider trying to assess their risk of death from riding (i.e., catching COVID-19). They see a study which puts the risk of death for those motorcycle riders who were (1) drunk (2) doing a wheelie on the highway (3) during a rainstorm, and (4) while texting with a friend (i.e., analogous to four comorbidities). It would be flawed reasoning for a rider who doesn’t do any of those things to put themselves in the same risk category as those who do. So while no one is saying motorcycles aren’t dangerous — they certainly are — they’re nowhere even in the vicinity as dangerous as riding while doing all the other things. Likewise, neither should a healthy teenager dwell on their COVID-19 risk with the same fervor as a 100 year-old morbidly obese individual with terminal cancer.
Okay, let’s revisit my personal risk again. First, I will ignore the 5% “no comorbidities” statistic above, because out of fairness I want to account for likely COVID-19 induced comorbidities like Respiratory Failure, Sepsis, etc. as well as possible ones like Renal Failure, Cardiac Arrest, and the like. So, let me simply reduce my risk not by 95%, but 57% (conservatively even rounded down further to a clean 50%), which removes just 1 non- COVID-19 induced comorbidity for my age group.
And just like that, my adjusted risk is downgraded to 0.0069% annually (annually, because it’s only once a year — after which time a better-than-vaccination natural immunity kicks in for that season).
So what really is 0.0069%, you might ask? After all, we humans aren’t terribly good with numbers like that. To help you put it in perspective, consider that according to the National Highway Traffic Safety Administration, your (or my) risk of dying from a freak car accident in any given year, is 1 in 5,407 or 0.018%.
Let that sink in: based on what we know today, I personally am 268% more likely to die in a car accident tomorrow (or any day this year) than COVID-19. But do you really think that in pre-pandemic times, the “1 in 5,407” statistic kept me locked up inside my house? You think even today (in the middle of a pandemic) that figure stops me from taking a leisurely drive to grab ice cream with my nephews? or catching a movie with my brother? or — God forbid!! — hanging out with and actually talking with my friends? No!, and it never could. Because life, my friend, is about dancing in the summer rain, not cowering in fear of getting struck by lightning. But hey, maybe that’s just me…
In any case, I want to come back to your comment about concerns your colleagues have regarding young children. When we look at the statistics available (table above), the results are even more stark: for kids aged 5-11, their odds of a fatal COVID-19 infection are 1 in 137,000 when you factor in asymptomatic cases. And again, we’re talking about a risk inclusive of those with comorbidities. For kids 5-11 who are perfectly healthy, you can consider their risk nil. Okay, well obviously it could never be actually zero, because we both know sometimes kids also fall off a bike and kill themselves — that’s life. But you don’t exactly see people running around freaking out over bicycles all day long, do you? Which is ironic as hell now that we’re on the subject, considering almost exactly the number of kids have died from bicycles as from COVID-19 in the same time frame.
So when I hear about folks taking their kids for a bike ride on the weekend (how awful), or worse!, maniacally driving their kids for ice cream (putting those precious kids at 5,091% (51x) the risk of death as COVID-19), but then trembling at the thought of walking into an office the following Monday because there’s an unvaccinated person there, so they feel the need to demand forcing medical decisions on those people (like getting jabs with vaccines made by companies whose rap sheets (Pfizer, J&J) would satisfy essay requirements at most colleges, approved by an organization that finds safety issues in 1/3 of its drugs post-approval), I come to the simple conclusion that common sense has left the building — it’s mass hysteria.
Alright, enough beating the completely de minimis personal risk dead horse because the point is clear. But let me add two more small things before getting to the dangers of the vaccine:
TWO OTHER THINGS TO CONSIDER
The section above looked at the whole thing purely from a mathematical risk perspective with neither proactive measures in mind, nor accounting for simple and effective (though IMO criminally suppressed) treatment options available to thwart COVID-19 risk even further.
(1) First, on the treatment side. Look, I know there was the whole “orange man (Trump) bad, the FDA disagrees” political BULLSHIT thing going on. Like I said above, I do not give a shit about the political angle of any of this. I require data, and the data could not be more ironclad on the subject matter. I will simply leave these two links here, and avoid another 5 pages in this POV on why IMO this is being criminally suppressed by federal agencies:
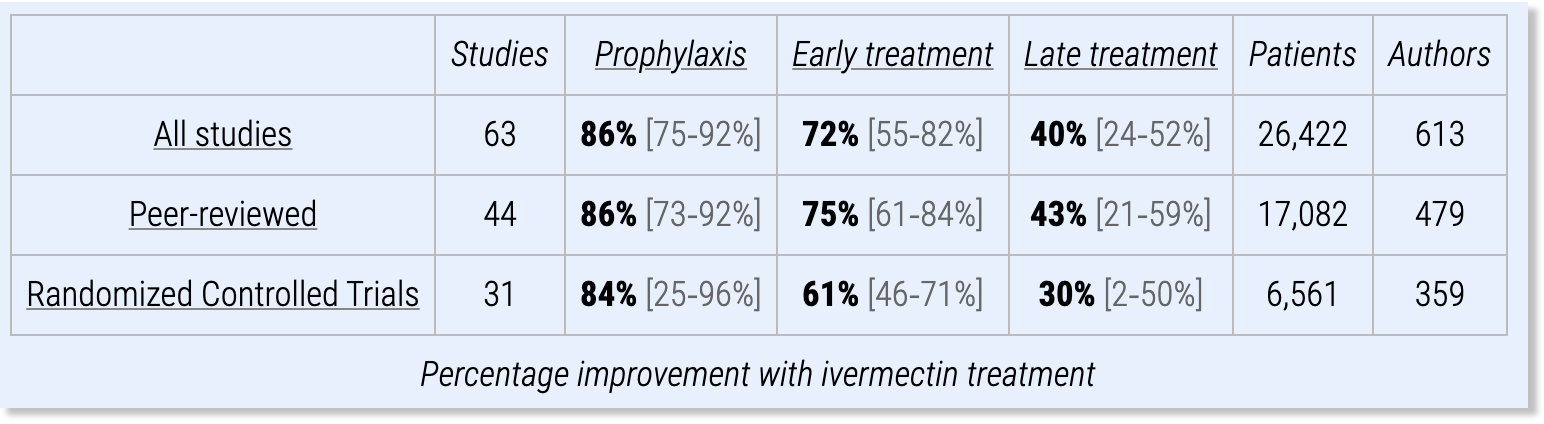
First, Ivermectin (links to the studies: (Link A & Link B)). Summary table as follows:
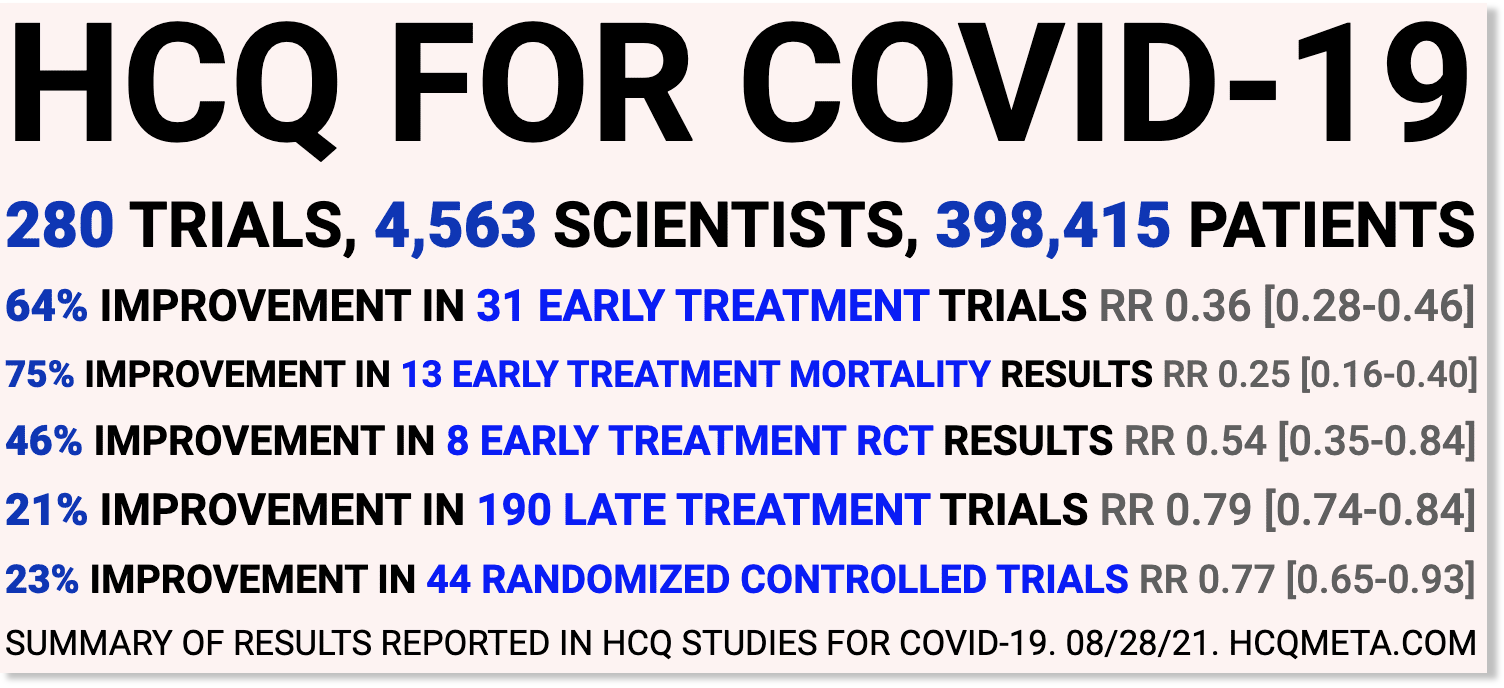
Second, Hydroxychloroquine (link to the studies). Summary table as follows:
By the way, it is worth noting I have a friend right now who has COVID-19. He has felt like shit for the past week. I sent him the studies, and he bought Ivermectin 3 days ago without a prescription from a local store I pointed him to. After a week of feeling like shit, it took him less than a day to get close to symptom free. But hey, I am not a doctor, and “your mileage may vary.” There are a dozen other treatments in addition to the ones above that aren’t getting approved for mass application, either. Go figure.. I could send you the studies if you want, but anyways let’s move on.
(2) As it pertains to the proactive side — okay, sit tight because I’m going to perform a holy miracle here and give you one of several simple things you can do to essentially ensure never needing to worry about COVID-19 again. Not for you, not for the kids, and not even for the neighbor’s dog. Ready? Okay drumroll please… . Did you catch that? If you didn’t, I’ll decipher it for you. It’s your new friend Vitamin D.
If you’d like dozens more studies on this subject, let me know, but start with this good summary I just found for you here — it’s worth a full read, but two pretty charts from the link sum it up:
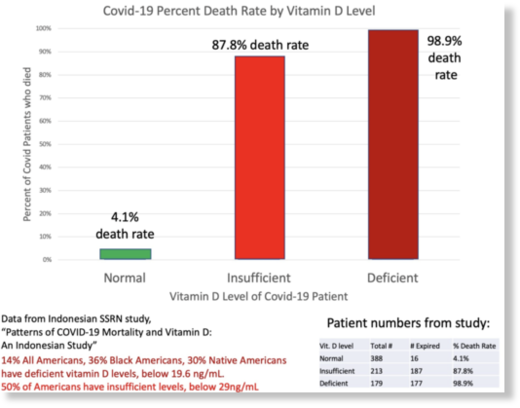
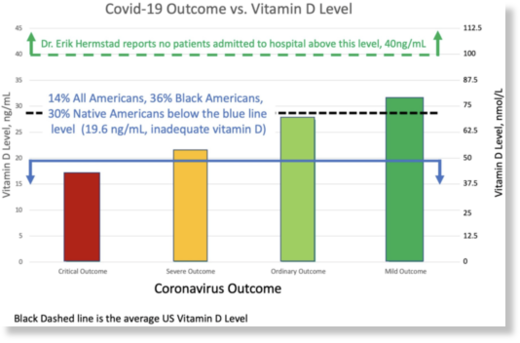
The first study is striking all on its own and worth internalizing, but unfortunately it did group an entire category called “normal” into a single bucket. FYI “normal” is what the medical world considers to be ~20ng/mL. But that’s all it is as a level: normal… but far from what we want, which is excellent.
That’s where the second study becomes helpful. It puts the explosive nature of the findings into real perspective: at levels of 25ng/mL in the study, no severe or critical hospitalized outcomes were observed. While at levels of 40ng/mL or greater, there were not even hospitalizations.
Now personally, I regard it as nothing less than a crime against humanity that neither the WHO nor CDC are PUSHING these (and dozens other peer-reviewed studies on the subject) onto the forefront of our collective media screens. But as for the reason, I must digress, because again I could go down a long and nasty rabbit hole about perverted incentives in the system in terms of why you likely haven’t seen them.
In any case, here’s what is just so awesome for me… remember when we concluded I had a higher risk of crashing & dying from my trip to the local ice cream shop than from COVID-19? Well, it just got a WHOLE lot better, because my Vitamin D levels happen to be considerably well above 40ng/mL. Which means we need to be honest with ourselves and admit that I effectively have a ZERO clinically observed risk of death from COVID-19. I mean shit…. at this point really the only way I can die of COVID-19 is by having it and then getting into a car accident. Then sure, I will die “with COVID-19” (and, as you’ll recall from the link above, they would count it!).
So my advice is as follows: get your dang sunshine first thing in the morning. Do not lockdown. In fact, I’d argue it’s what caused so many deaths. People were heavily Vitamin D deficient from sitting at home all day, and it literally increased their risk of death instead of reducing it. And what the CDC did in this regard was at best negligently or at worst intentionally, criminal, and I have nothing but disdain for the way they went about that. Don’t even get me started on the youth suicides it led to, the increases in domestic violence, increases in drug overdoses, infanticide, denial of healthcare, and let’s not dismiss the whammy of the sheer economic devastation to jobs and small businesses the world over, the bleak economic prognosis for the poorest (how convenient), and the future impact of staggering U.S. debt right here at home. All caused by the incompetence or criminality of the CDC and WHO.
Honestly — my personal advice if you want to stop worrying about COVID-19 for the rest of your life (if you still even are), would be to follow the Dan Miller protocol. Each of his bits of advice is like an extra layer of bulletproof glass on top of Kevlar against COVID-19. And remind your colleagues, too, to stop relying on the “American way” of taking a pill to solve all their problems and blaming the unvaccinated. That is not only completely debunked now as I’ve demonstrated throughout, but it is weak morally. It’s high time we all do the hard self-work of making ourselves physically resilient, and stop feebly making outward demands of others to inject into their bodies vaccines that are only now being tested, in vivo, on large numbers of human beings.
Speaking of which… perfect segway.
===================
(VERY BRIEFLY) PART 2: LONG-TERM RISKS OF [SPECIFICALLY] THE COVID-19 VACCINE –> HIGH
As I’m sure you’ll remember, a while back I mentioned I would send you a thorough, synthesized summary outlining the dangers of the COVID-19 vaccines and how the risks they carry far outweigh the risks of the virus itself. Unfortunately, I am not even a fraction of the way through the hundred plus pages of medical literature showing that conclusion — I’m still working through it. I absolutely feel terrible for not having lived up to my promise, though I’m sure you can appreciate the sheer herculean nature of synthesizing 7 months’ of research involving almost a thousand individual pieces of data, and weeks’ worth of video testimonials by researchers, all into something “succinct and digestible”, all the while working on [my company] in the middle of it all.
In any case, it would be disingenuous of me if I didn’t at least provide a sneak peak of a random assortment of links I had handy for why I will not get the vaccine (aside from the fact that COVID-19 poses no risk to me, per the first section):
- Imperfect Vaccination Can Enhance the Transmission of Highly Virulent Pathogens (bad for me, terrible for society; moral obligation not to partake in this)
- Is a Coronavirus Vaccine a Ticking Time Bomb? (Spoiler alert: likely is)
- A Pathologist Summary of What These Jabs do to the Brain & Other Organs
- Might COVID Injections Reduce Lifespan?
- MIT & International Journal of Vaccine Theory, Practice and Research: Worse Than the Disease? Reviewing Some Possible Unintended Consequences of the mRNA Vaccines Against COVID-19
- How COVID-19 Vaccine Can Destroy Your Immune System
- The Inanity of RNA Vaccines For COVID-19
- New Report Sheds Light on Vaccine Doomsday Cult (sketchy website, but well explained content. I suppose even a broken clock can be right twice a day…)
- Children 50 TIMES More Likely to Die from Covid Vaccine Than From Virus (from the former CSO of Pfizer)
- Pfizer vaccine in Israel: Mortality rate ‘hundreds of times greater in vaccinated young people’
- Are COVID shots fueling more dangerous mutations?
- Less than a third of delta variant deaths are in the unvaccinated (not really an article regarding vaccine dangers, but more so inefficacy)
- +1,000 additional articles, papers, studies, you name it that I could send anyone that wants the full dump of ’em (unsynthesized, of course)
Some bonus links in your spare time that caught my eye in just the past week:
- Fun Quick Video: Mt. Vernon, IN School Board Meeting (though he got a couple things wrong, some points are good food for thought)
- Podcast: The High Wire — A Sea of Lies (in depth discussion about perverse incentives driving bad decisions by the CDC (particularly the second half of the video))
- Podcast: Objective:Health – Study on the Adverse Effects of the Pfizer Vaccine (in which the presenters discuss a paper by the same name).
- Short & Sweet: Why non-lethal pressure on the virus is bad (versus natural immunity) -> Part 1 | Part 2
- +100 more videos and podcasts on the subject to anyone who asks (unsynthesized, of course)
===================
CLOSING THOUGHTS
If you made it this far and checked out even any of the content, kudos. Most folks here in the Northeast stop listening to me once I say “hey, there’s something not right here in this data” or “I’m not too worried about COVID-19 personally”. They think I’m a nut. Now, if you’ve made it this far and checked out most of the content, then I already know you’re starting to wonder if you’re losing your mind, because boy do I have a club pass with your name on it, if you’d like one.
Alas, contrary to popular belief it’s far from a nut club, despite how strong the external pressure is these days to try to make it out to be the case. Rather, It’s a club filled with precisely the very people who we’re supposed to be listening to as a society:
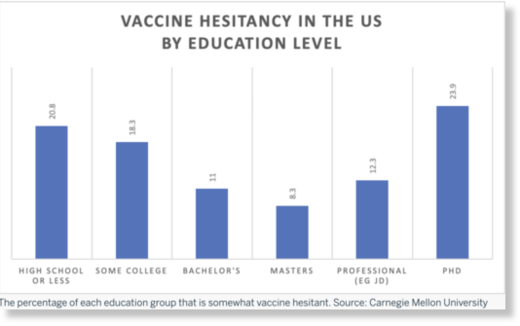
Source: https://www.medrxiv.org/content/10.1101/2021.07.20.21260795v1.full.pdf
AKA: a twisted rendition of the Dunning-Kruger effect in action
The CDC would have you believing it is just the crazy and uneducated who are most wary of their (and the FDA/WHO’s) conclusions — you know, it’s all the rednecks down south! And they’re right, it is the uneducated (left of the chart). But it is disingenuous for them to try and ignore on the nightly news research like this out of Carnegie Mellon suggesting the biggest group of those most vaccine-hesitant happen to be the smartest folks in the world — the ones I’ve certainly not been ignoring, despite their being shamed, cancelled off of social media, and publicly silenced.
Put another way, I would only posit the simple question of when in the history of the world have you ever had thousands of scientists, doctors, and researchers, some of the brightest minds* in their fields around the world sounding an alarm, and the official response be to label them all as batshit crazy and prevent them from speaking? Hint. Personally, I can’t support it. A free society must allow all open discussion without ridicule well before we dare discuss collectively forcing medical decisions on people using actual threats against their autonomy. We’re too far past that Vietnam-level of government lying bullshit that results in unholy suffering for society for this barbaric nonsense to continue, and it’s time for this country to start acting like we learned something about the importance of asking questions. I simply cannot place any trust in the idea I’m not being lied to until every scientist worth their salt has had an opportunity to speak up freely, and the nature of their concerns investigated transparently. And neither should anyone else.
*Such a fun fact it is that among this ocean of scientist voices being smeared & erased from history are (1) the guy who helped invent mRNA vaccine technology, and (2) the former Chief Scientific Officer (CSO) of Pfizer (who held that role for 16 years and focused on respiratory illnesses), both of whom are saying we have to stop vaccinations at once for those who aren’t at actual high-risk with COVID, because for everyone else they’re not only toxic & dangerous but will be the very cause of this never ending pandemic. Now I don’t know about you, but I neither invented mRNA technology nor worked at Pfizer for 16 years as CSO, but if I did, I’d sure prefer the American people heard my concerns, you know, sans the childish smear tactics part. Until then, I will not — cannot — accept any mandates on moral grounds.
And so there you have it. My opinion on mandatory vaccinations at this stage: if this were the Bubonic Plague, I’d be the first in line to get the shot. Same for Polio, Tetanus, and a whole lotta other great vaccines. But for COVID-19? Let’s just say I wouldn’t even know what to tell Saint Peter at the Pearly Gates to apologize sufficiently if I — knowing what I know now — supported a mandate. Come to think of it, there’s a quote that comes to mind here that I think is a nice way to wrap up this write-up, and commemorate those who continue to protect the rights of society:
‘The hottest places in Hell are reserved for those, who in time of moral crisis, preserve their neutrality.’ ~ unknown
========
DISCLAIMER –> OBLIGATORY
I obviously have to say this before I sign off.
At the end of the day, I’m not a doctor, I do not have an MD, a Ph.D., or any other useful acronym. All I am is an individual who values truth above hysteria & ideology. I will go wherever the truth points me to without regard for what “side” that puts me on. If it’s a contrarian side, then shit I guess I’m going to have to get in some fights. If I’m on the side of the majority, I guess I’ll rest easy. But wherever it is, I’m willing to go there, and as I said in my opening statement and reiterated to the group — I will always remain open to thoughtful and productive dialogue and my POV on every topic is subject to change through lifelong reflection. All I ask for these days is for those who disagree with me to either have the sincerity to work with me using the scientific method to get the facts on this subject, or if they have no interest in that, to let me do it alone without the constant coercion, which is how I’m sure the folks in your office who are unvaccinated, feel.
Anyways, for the actual disclaimer part: we all have to make our own decisions, do our own research (though I’m always happy to keep sending stuff I come across), and take our own risks. Freak accidents can happen, and just like I wouldn’t want to be responsible for a car accident that happens if you decide to go to a particular ice cream shop I recommend, it is the same for anything I’ve sent above and anything you or anyone you may share any of the information with do as a result of it. Always seek and follow professional, accredited advice! <– the disclaimer part.
Anyone who sees the vaccine as having more benefit than risk, should absolutely take it. I agree 100% with an 85 year-old with five comorbidities getting the jab — shit if that was me, I’d be getting quadruple jabbed walking around with a gas mask. No really, I would. Because for them the virus is actually very dangerous. And I’ve recommended it for some that I know personally would benefit from the vaccine because they are at high risk. But that’s where it ends. And not a single, inch, further.
China Suggests COVID-19 Could Have Been Imported Into Wuhan
By Tim Korso – Sputnik – 30.08.2021
China has been battling against being labeled the country allegedly responsible for the coronavirus pandemic since its onset. The first officially registered cases of COVID-19 were in the Chinese city of Wuhan, but Beijing has repeatedly suggested that the pathogen could have been imported into the country.
The Chinese Centre for Disease Control and Prevention (CDC) has unveiled its own suggestion regarding how the World Health Organisation (WHO) should handle the second phase of the investigation into the origins of the COVID-19 virus. According to the Chinese CDC, WHO investigators should focus their efforts on studying cold-chain products and their logistics ahead of the detection of the first COVID-19 cases in Wuhan – specifically between September and December 2019.
The Chinese CDC epidemiologists said that samples of COVID-19 could be found on some of the cold-chain products shipped to other Chinese cities, namely to Beijing and Dalian, right before the two cities suffered limited outbreaks of the disease in summer 2020. These incidents happened after China managed to quickly end the original outbreak in Wuhan in April 2020.
Chinese epidemiologists have thus suggested that COVID-19 might have been imported into Wuhan, either from another Chinese region or from a foreign supplier of cold-chain products. Members of the country’s CDC have proposed that the WHO explore this hypothesis and track the supply chain for this type of product. The scientists stressed in their publications that there have been numerous evidence of COVID-19 being present in other parts of the world, specifically the US, Italy, Spain and France, ahead of the detection of the first cases in China and as early as March 2019.
“We conducted epidemiological investigations, nucleic acid testing, antibody detections, cold-chain food retrospection and comparative analysis of viral gene sequencing of COVID-19 patients and food packages and confirmed that the virus was imported from other countries or regions through the cold-chain transportation”, Ma Huilai, an official from the China CDC said.
The researchers from the Chinese CDC further noted that over half of the stores in the Huanan seafood market, a suspected source of the original infection, imported 29 types of cold-chain products from 20 countries and regions of China.
The publication by the Chinese epidemiologists comes as the WHO is planning on carrying out the second phase of the investigation into the origins of the virus that has taken the lives of over 4,493,000 people around the world and disrupted economies. The previous probe yielded no answers as to when and how the virus jumped from animals to humans, and the global health body announced in July 2021 that a new investigation will be conducted. The announcement of the second phase probe also coincided with the US intelligence services opening an investigation into the allegations that the virus could have escaped from a Chinese laboratory.
Beijing has strongly rejected the idea of conducting the second phase probe on its territory, arguing that the new investigation is politicised and not based on science. The US probe into the allegation of the laboratory origin of the virus, however, produced a report in which most US intelligence agencies said that the virus was most likely naturally born, although some agents have refused to absolutely rule out the man-made theory.
“How Our Lives Could Soon Look”: The WEF Posts Yet Another Insane Dystopian Video
Vigilant Citizen | August 24, 2021
As you probably know, since 2020, this pandemic has poisoned the lives of billions of individuals across the world. Meanwhile, the World Economic Forum (WEF) cannot contain its excitement. Indeed, this powerful, influential, elite-owned organization keeps posting bizarrely upbeat videos about the “advantages” and “opportunities” of COVID-19.
For instance, in January, the WEF posted a video titled “What is the Great Reset” which basically acknowledges that it’s using the pandemic to bring about a new social and economic order … while making fun of those who predicted that would happen. A month later, the WEF posted another video titled “Lockdowns Are Quietly Improving Cities Across the World” which was nothing less than insane. In fact, the WEF eventually deleted that video … but that doesn’t mean they don’t believe it.
Needless to say, people absolutely hate these videos. They are ruthlessly downvoted on YouTube and 99.85% of the comments express utter disgust. But that did stop the WEF from creating more absurdities.
On August 17th, the WEF posted a video titled “This is how our lives would soon look”. And it looks likes the trailer of a dystopian horror movie where people are treated like dehumanized cattle.
Here’s the video:
The first thing they make abundantly clear is that they don’t want you or your children to leave the house. They want you to work from home and they want your children to learn from home. And they believe that these changes will be so permanent that offices will need to be repurposed and entire neighborhoods will need to be redesigned.

They don’t even want you to leave the house to get food. Also, they want you to wear a mask in your own house when you get that food. “Analytics-driven services” implies that big tech companies will analyze your web searches and consuming habits to “predict” what you want and have it sent to you.

Same thing.
If you decide to go crazy and actually get out of the house to meet other people, they want it to be like this:

If you meet another human being, it’s going to be with hand sanitizer and permanent masks. Don’t forget to scan that QR code so they know exactly where you are and who you are meeting with.
They’ll also want to track you in the creepiest way possible.

I hate every word in this sentence.
According to the WEF, masks will be a permanent thing. And, because of that, their precious face recognition systems won’t work as well. So what’s the solution? Stop with the masks because pandemics are temporary? Of course not. Stop with the tracking of individuals? Are you crazy? Their answer: Shoot lasers right at our hearts and listen to our heartbeats to ID us. Yes, that’s the most insane answer to that question and that’s what they put in their video.
These creeps are also “laser-focused” on our children. They want to shape and mold them according to their dystopian principles. For this reason, the WEF promotes permanent remote learning on screens.

They want your children to be locked inside the house, staring at screens all day.
Although remote learning has been nothing less than disastrous for the development and mental well-being of children, the WEF wants it to become permanent. And to sell that insane idea, they claim that it would “improve their digital skills”.
That’s the weakest argument I’ve ever heard regarding anything in my life. Children today absolutely do not need to “improve their digital skills”. They learn how to use phones and tablets before they actually learn how to walk. If anything, they need to scale back their “digital skills” by a couple of notches and boost their “go outside and get dirty” skills by a couple of notches.
The WEF knows very well that children need to play, socialize and communicate with other children to develop properly. However, they do not want children to develop properly. That’s the scary, terrifying truth about their agenda. They’re looking to deny vital elements of a child’s development in order to create the kind of human they want living in their dystopian society.

They really want COVID hysteria to be permanent.
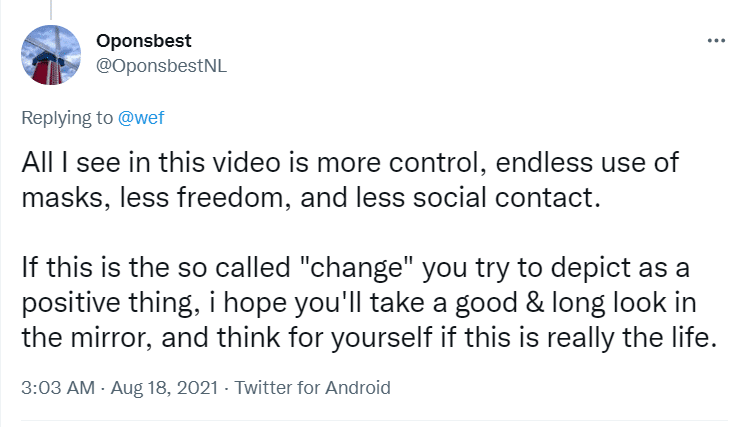
Not unlike previous WEF videos, this one was received with universal disgust. Here are some Twitter replies to the video (I didn’t cherrypick them, they’re literally all like that).
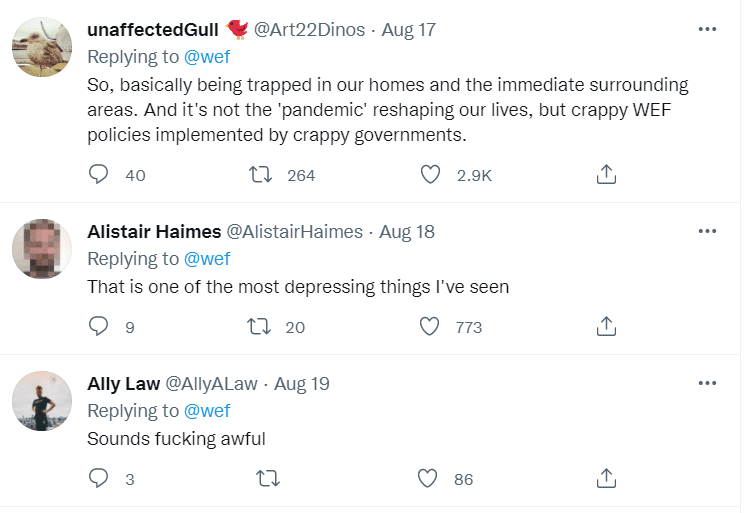
In Conclusion
As you might have noticed, these videos aggravate me, like they aggravate nearly everyone who watches them. And for several reasons. First, who voted for any of this? Did anyone see the name of Klaus Schwab – the head of the WEF – on any election ballot? Of course not. In fact, Schwab has been working for years to dismantle national democracies.
Schwab as publisher of the World Economic Forum’s 2010 “Global Redesign” report postulates that a globalized world is best managed by a coalition of multinational corporations, governments (including through the UN system) and select civil society organizations (CSOs). It argues that governments no longer are “the overwhelmingly dominant actors on the world stage” and that “the time has come for a new stakeholder paradigm of international governance”. The WEF’s vision includes a “public-private” UN, in which certain specialized agencies would operate under joint State and non-State governance systems.
According to the Transnational Institute (TNI), the Forum is hence planning to replace a recognised democratic model with a model where a self-selected group of ‘stakeholders’ make decisions on behalf of the people.The think tank summarises that we are increasingly entering a world where gatherings such as Davos are “a silent global coup d’etat” to capture governance.
– Wikiepdia, Klaus Schwab
Second, every single WEF video unironically promotes a joyless, freedomless world where everything that makes life worth living is banned. They want you to stay in your house while they extract what they need from you using technology. They want to train your children to be the same. They don’t want you to wander too far from your home and, if you do, they want to track you on a biological level. They especially don’t want you to interact with other human beings in a normal way because that might spark some humanity in you.
Is this how you want to live? Is this the world you want your children to grow up in? If not, we need to actively reject every attempt to make their plans a reality, on every level possible.
Media addiction to Covid-19 ‘fear porn’ is perpetuating a worsening cycle of societal damage worldwide

© REUTERS / Thilo Schmuelgen
By Eva Bartlett | RT | August 28, 2021
Over the past year and a half, hysterical media reporting on matters Covid-19 has reduced some people to a fearful state of unquestioning compliance – including a great number of otherwise critically-thinking journalists.
With screaming headlines in bold and large font such as, ‘Will this nightmare ever end?’ and ‘Mutant virus skyrockets…’ and ‘Fear grows across the country: VIRUS PANIC’, and ‘Coronavirus horror: Social media footage shows infected Wuhan residents ‘act like zombies’, it is no wonder many people are in a state of panic.
In times when many are suffering mentally and physically under unnecessary and prolonged lockdowns, the incessant fear porn is causing excessive anxiety, which in turn will affect the health & mental well-being of some, if not many.
In government documents from the UK’s Scientific Advisory Group for Emergencies (SAGE) dated from March 2020 advice was given saying:
“The perceived level of personal threat needs to be increased among those who are complacent, using hard-hitting emotional messaging… This could potentially be done by trained community support volunteers, by targeted media campaigns, social media”
I’d say the UK media campaigns weren’t so much ‘targeted’ as ‘blanket’ but they certainly did the job, and other Western nations got similar directives. The UK government also became the nation’s biggest advertiser in 2020, make what you will of the potential ramifications that could have on cash-strapped newspapers and their supposed ‘independence’.
Having myself been deeply focused on exposing war propaganda and other media lies around Syria, Palestine, Venezuela, and elsewhere over the years, my default position has become one of deep cynicism on mass media reporting. Yes, you can find nuggets of truth, or even excellent journalists in mainstream publications, honestly challenging the narratives.
But those are few and far between, generally you find copy-paste propaganda emanating largely from the bowels of the USA and the UK.
A study by Swiss Propaganda Research (SPR) noted, “most of the international news coverage in Western media is provided by only three global news agencies based in New York, London and Paris.”
Those agencies are AP, Reuters, and AFP. SPR notes:
“The key role played by these agencies means Western media often report on the same topics, even using the same wording. In addition, governments, military and intelligence services use these global news agencies as multipliers to spread their messages around the world.”
Given all of this, I’ve come to believe that with regard to media reporting on Covid-19, my cynicism is well-deserved.
Covid-19 reporting has increasingly been utterly absurd, with stories of people dropping dead in the streets, ice rink morgues to cope with the mountains of bodies, footage of an overcrowded New York hospital (that just happened to be of an Italian hospital), claims of animals testing positive for SARS-CoV-2, and more recently reports of people dying post-jab but we are told ‘it could have been worse!’
This campaign of fear caused the public to massively overestimate the lethality of Covid-19, which as un-alarmist voices note has a survival rate of over 99%.
When months into the outbreak it became apparent that SARS-CoV-2 was far less lethal than first predicted, the media and talking heads moved from talking about ‘Covid deaths’ to ‘positive cases’.
Although relatively early on a goat and pawpaw tested positive for Covid-19, instead of then scrutinizing the accuracy of the PCR test as a means of ‘detecting Covid-19’, the media continued to hype the rise in Covid ‘cases’.
In lockstep, ‘Covid testing’ was increased dramatically using the PCR test (recently revoked by the CDC). This inevitably pumped up the number of ‘cases’, which mass media have in turn promoted non-stop, this in turn gave ammunition to those enforcing lockdowns and vaccines.
By now hundreds of vocal doctors, nurses, virologists, immunologists, and other professionals actually worth listening to, whose data and experience counter the hype pumped out in media have very quickly disappeared from social media, or otherwise deemed quacks, and are thus largely silenced. This leaves the general public mainly getting their information via hyped-up media.
Alongside this, there have been relentless ad hominem attacks on journalists who pose legitimate questions and uncomfortable truths about the official narratives around Covid-19.
For offering perspectives which contradict the standard narratives around Covid-19, journalists have been deemed conspiracy theorists, pandemic-deniers, right-wingers, selfish… I’m sure I’ve missed quite a few slurs.
When it comes to matters Covid-19, it is suddenly unacceptable to question ‘The Science’, question the authorities, or question the same media that sold us WMDs in Iraq and chemical attacks in Syria.
Media are the drivers of Covid hysteria, and it is the daily bombardment of fear porn that confuses average people and enables tyrannical powers to be brought in, largely unchallenged.
As it is the responsibility of journalists to expose lies around wars of aggression, it is also the duty of journalists to do so around Covid-19. For some journalists who have stubbornly refused to hold power to account, instead toeing the line on all things Covid, it appears their fear is of losing an audience and not of a virus.
Whether or not you agree with dissenting voices’ questions and criticisms, we have the right to ask and make them. We do so, knowing that remaining silent in the face of the brutal Covid measures is a guaranteed path to tyranny.
Eva Bartlett is a Canadian independent journalist and activist. She has spent years on the ground covering conflict zones in the Middle East, especially in Syria and Palestine (where she lived for nearly four years).
“It’s all for your own good”
By TE Creus | OffGuardian | August 29, 2021
One of the most annoying aspects of the current measures supposedly created “against the pandemic” that we have been subjected to for almost two years now is the insistence that everything is done “for our own good”, as if governments and big companies were strict but caring parents, and we were just unruly or disobedient children who don’t really know what they need.
It brings to mind CS Lewis’ warning about that most oppressive of tyrannies, “a tyranny sincerely exercised for the good of its victims.”
Now, I cannot tell for sure if the vaccines, the lockdowns, the travel restrictions and the masks work or not. My feeling is that they don’t, or at least, not in the way we are being told, but that’s not the issue. The question is why are we being treated like stupid children who cannot simply choose, but have to take a “jab” and then get “green passes” to travel or work or enter any establishment.
Apparently, governments and big corporations worldwide are worried about our “health”.
But are they, really?
Like monomaniacs, they seem to be worried exclusively about Covid.
Not about the incredible amount of mental health issues and the alarming increase of teenage suicides during the various “lockdowns”.
Not about people, like my elderly neighbours, who could not see their family (who live in another country) for over two years and are suffering with solitude.
Not for the people who, afraid of contracting Covid, didn’t go to the hospital to treat other conditions and died.
Not for the people who died or got sick because of side effects of the vaccines.
No, it’s just “Covid”. And even that doesn’t seem to be their main worry. As long as they get their “vaccine passports” and their “tracking apps” and their “cashless society”, they don’t really care if you get the disease or not.
When did this wave of fake concern start? Ok, governments were probably always in the business of being annoying busybodies – “I’m from the government and I am here to help” was a scary sentence since who knows how long. But companies for decades were mostly concerned with selling their product, not with lecturing us.
However, at the peak of the BLM riots, I received dozens of emails from big companies assuring me that, to them, “blacks lives mattered”. In Pride Month, the same companies assured me that they were fighting for transgender rights to use whichever bathroom they wanted. I never asked nor cared what’s their position on those issues, just that they make a good product that I can use.
Now, the same companies send me emails about masks and vaccination and passes. Because, see, they are worried about my health.
Unfortunately, it’s not just governments and big companies. Almost every institution in the culture and the arts is also kowtowing (either by government decrees or to keep being funded, I don’t know) to this literal “new world order”.
For instance, the Baltimore Symphony Orchestra now has very strict regulations for entry. They tell us that they want to create “an environment in which we all may confidently discover what it means to be together again.”
And so, in the name of “togetherness”, they are banning all people who are not vaccinated, including all children under 12 years of age who cannot, alas, be legally vaccinated yet. Not even people with a negative Covid test will be allowed entry to the concerts: only the “vaxxed” ones, with their proper certificates. Still, even they will have to endure masks for the whole duration of the spectacle. It’s not clear if also the musicians have to wear masks – I suppose at least the flute players will be exempted.
And yet, despite all those draconian rules which really seem to take out all of the fun out of the process (and in this case it might really be better to just stay home and watch a video streaming online), “these protocols do not offer absolute protection against contracting COVID-19” and the spectators must “voluntarily assume all risks related to exposure to COVID-19.”
Note also that those showing any possible symptoms might not be allowed entry, vaccine or not. (I wonder if anyone who coughs during one of the breaks will be forcefully ejected.)
This is just one example among many of the ludicrous and merciless “new normal” that we are subject to in the name of our health.
But remember, “it’s all for your own good”.
TE Creus is a writer, translator and filmmaker. He is the author of “Our Pets and Us: The Evolution of a Relationship” and the collection of short stories “The Sphere”. He’s the editor of Contrarium.
Featured Video

or go to
Aletho News Archives – Video-Images
Book Review
The Zeolite Book — First Edition, 2026, Paperback
The volcanic mineral medicine will not patent — for the toxic burden medicine will not name
Lies are Unbekoming – October 30, 2026
 Zeolite is old. It is in Roman concrete that has held for two thousand years. It’s in the water filters of ancient cisterns. It’s in the stomachs of Pacific livestock whose keepers knew, somehow, that this grey crumbling rock made the animals healthier. It’s in Soviet clinical protocols from the 1960s. It’s in the standard emergency response to the Chernobyl explosion.
In 1986, after the Chernobyl reactor failure, the Soviet Union manufactured and distributed natural zeolite at industrial scale — for soil remediation, for livestock feed, for human consumption, for the cleanup itself. Karl Hecht, who had been director of the Institute for Experimental and Clinical Pathophysiology at the Charité of Humboldt University Berlin, spent the six decades after that building the clinical research base — on silicon’s role in human health, on zeolite’s clinical safety, on its applications in ageing. In 2018, Pavelić and colleagues published a comprehensive clinical safety review of natural clinoptilolite in Frontiers in Pharmacology. In 2019, Mastinu analysed its binding affinities. In the Western medical literature, these works sit largely uncited.
What has not been treated at book length, until now, is how a volcanic mineral with six decades of Soviet clinical work behind it, two major peer-reviewed Western reviews, and ongoing clinical use across the former Eastern Bloc, remains almost entirely absent from Western medical practice — and what the toxic burden it’s meant to address actually is.
The Zeolite Book gathers the Soviet clinical record, the Western peer-reviewed studies, three contemporary practitioner voices, and three serious counterviews into one honest treatment. That’s why the book runs to seven appendices. 288 pages, four parts, three practitioner voices, three counterviews, seven appendices. The honest treatment is the argument.
Blog Roll
 Aletho News
- Wrong, AP and NPR: Europe’s 50,000 Heat Deaths Are a Computer-Model Estimate, Not a Real Body Count
- Questioning Your Doctor Is Now Considered A Psychological Problem (Seriously)
- London tourism expo promotes Israeli agency linked to theft of Palestinian land
- Dockworkers launch global strike against Israeli and US military shipments
- Europe facing gas price shock – Gazprom chief
- Ukraine continues recruiting people with disabilities
- Weaponized Journalism: 2021 Sayer Ji Interview with NPR
- Beyond Netanyahu: what Israel’s election means for Palestinians
- Lithuania plans universal conscription
- Lies, Damn Lies, and Ukraine News
- If Americans Knew
- 1,300 will gather in Palo Alto on Nov. 1 for Z3 Conference on Zionism
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- The Long Arm of AIPAC
- Genocidal intent behind Hebron assault, rights group says
- This week, Israel killed 8-year-old who survived bombing that wiped out her family
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Israeli soldier poses at damaged Lebanon church, sparking anger
- New Report. Manufacturing the Great Replacement: Is Israel behind one of the largest racist influence campaigns ever documented?
- ‘Arab voice doesn’t count’: Jewish Israeli blocs reject Palestinian support
- Whether Bibi Stays or Goes, the ‘Special Relationship’ Must End
- No Tricks Zone
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!

