Washington State Creeps Toward COVID Police State With Vaccine Mandates, ‘Tracking Monitors’ in Schools
21st Century Wire | August 26, 2021
It’s a race to the bottom of humanity and the competition just keeps getting scarier by the day. On the heels of what we thought was a clear One Horse Race in the ‘Zero COVID’ Sweepstakes, led by New Zealand, a new contender has emerged stateside – Washington, USA.
Washington Governor Jay Inslee, a self-avowed climate zealot, now adds pseudo-medical segregationist and authoritarian to his political resume with a raft of new COVID diktats including a vaccination mandate for all educators across his state.
State education workers will need to be ‘fully vaccinated’ by the hard deadline of October 18th.
Inslee called the vaccines being mandated “incredibly effective, amazingly effective… they are a medical miracle, they are a double miracle…”
Personal and religious beliefs will also not be tolerated:
Inslee topped up his orders by declaring the state’s indoor mask mandate expanded to require everyone to ‘mask up’ in indoor settings, regardless of vaccine status, set to take effect on Monday, August 30th.
You may have seen by now New Zealand’s Jacinda Ardern gleefully advocating for COVID ‘ankle bracelets’ – she says “YEES!”:
The News Tribune reports that Eatonville High School in Washington has already implemented Ardern’s fanatical fantasy – requiring its student-athletes and coaches to wear tracking monitors during practices:
“We received grant funding (known as ESSER III) that specifically included provisions to support higher-risk athletic programs, and we used some of those funds to pay for athletic proximity monitors,” the statement reads. “We are using these monitors for high contact and moderate indoor contact sports. The monitors are for both staff (coaches) and students on the field, regardless if they are vaccinated or unvaccinated. If a student or coach tests positive, we will have immediate information regarding athletes’ and coaches’ contacts, so we can more tightly determine who might need to quarantine.”
A parent of two student-athletes at the high school, Jason Ostendorf, told The Times Tribune he had “no choice in the matter” but to sign the consent forms allowing the school to track his kids while they practiced their sports, adding:
“It’s just one more thing they’re doing to the kids through this whole covid thing,” he said. “The vaccine, now be tracked when you’re at practice. Where does this end? I feel like this is an experiment on our kids to see how much we can put them through before they start breaking.”
July’s Age-Standardised Mortality Rate Was Equal to the Five-Year Average
By Noah Carl • The Daily Sceptic • August 24, 2021
The ONS announced on Monday that there were 40,467 deaths registered in England in July, which is 4.8% more than in June, and 7.6% more than the five-year average. In fact, the number of deaths registered in England was above the five-year average in all four weeks of last month.
These increases make sense, given that there has been a small uptick in COVID-19 deaths associated with the ‘Delta wave’. Although COVID-19 was only the ninth leading cause of death in July, deaths from the first eight causes were all below their five-year averages.
However, because the English population is ageing, the absolute number of people at risk of dying each year is going up. You’d therefore expect to see a greater number of deaths each year, even without a pandemic. What’s more, people who die from COVID-19 tend to be slightly older than those dying of other causes, so the average COVID-19 death is associated with fewer life-years lost.
For these reasons, it’s more informative to track age-adjusted measures of mortality. In July, the age-standardised mortality rate was only 1.3% higher than in May, and was approximately equal to the five-year average. (The exact figure was marginally higher, but the percentage difference was only 0.4%.)
This chart from the ONS shows the age-standardised mortality rate for the first seven months of the year, each year, going back to 2001:

Although 2021’s figure was higher than the figure for 2019, it was 3.6% lower than the figure for 2015 and 2.0% lower than the figure for 2018. This means that – despite higher-than-expected mortality in the winter – the overall level of mortality in the first seven months of 2021 was still lower than three years before.
As a matter of fact, the age-standardised rate from January through July was only 0.8% higher than the five-year average. Another month without many excess deaths and 2021 will officially be an ‘average year’ for English mortality.
Who Is ‘The Real Anthony Fauci’?
By Robert F. Kennedy, Jr. | Children’s Health Defense | August 25, 2021
 Today, Dr. Anthony Fauci is a household hero to half of America. Drug companies, government officials and the pharma-funded corporate media invoke his name to justify lockdowns, masks and experimental vaccines. The other half do not look on him favourably.
A recent editorial in a leading medical journal urged Congress to make it a felony to publicly criticize Dr. Fauci.
Encouraging his own deification, Dr. Fauci has declared that all those who questioned his pronouncements are “anti-science.”
But who is Dr. Fauci really?
In my new book, I show that Dr. Fauci has done little to earn the sobriquet “America’s Doctor.”
Instead, he has survived 50 years as the J. Edgar Hoover of public health by consistently prioritizing Big Pharma profits over the welfare of his countrymen, and through mercenary homage to the chemical and agricultural industry, the military industrial complex, the intelligence apparatus and all the other pushers of pills, potions, powders, poisons, pricks and the police state.
During more than a year of painstaking and meticulous research, I unearthed a shocking story that obliterates the obsequious media’s spin on Dr. Fauci … and that will alarm every American — Democrat or Republican — who cares about democracy, our Constitution and the future of our children’s health.
In my book I reveal how Fauci:
- has been the principal architect of “agency capture” — the subversion of democracy by a drug industry that manipulates regulators like sock puppets.
- failed dismally over his 50-year career with the National Institute for Allergy and Infectious Diseases (NIAID) to address the cause, to prevent or cure the exploding epidemics of allergies and chronic disease that Congress charged him with curtailing. The chronic disease pandemic is his enduring legacy. Those ailments now debilitate 54 percent of American children compared to 6 percent when he joined NIAD.
- repeatedly used fraud, bullying, intimidation, dissembling and falsified science to win approval for worthless and deadly drugs and vaccines.
- sabotaged safe and effective off-patent therapeutic treatments for AIDS while promoting deadly chemotherapy drugs that almost certainly caused more deaths than HIV.
- transformed NIAD from a public health regulator into an incubator for pharmaceutical drugs for which he and his trusted deputies often file patents and collect royalties. Dr. Fauci has claimed Moderna vaccine patent rights worth billions of dollars for NIAD and hand-picked at least four of his NIAD underlings to receive $150,000 annually from royalties.
- exercises dictatorial control over the army of “knowledge-and-innovation” leaders who appear nightly on TV to parrot his orthodoxies and “debunk” his opponents who run his crooked clinical trials globally and who populate the “independent” federal panels that approve and mandate drugs and vaccines — including the committees that allowed the Emergency Use Authorization of COVID-19 vaccines.
- violated federal law to allow his pharma partners to sacrifice and kill hundreds of impoverished and dark-skinned children and orphans in the U.S and Africa as lab rats in deadly experiments with toxic AIDS and cancer chemotherapies.
- repeatedly concocted and weaponized fraudulent pandemics, including bird flu (2005), swine flu (2009) and Zika (2015-2016), in order to sell novel vaccines.
- partnered with the Pentagon and intelligence agencies to conduct “gain-of-function” experiments to breed pandemic superbugs in poorly regulated labs in Wuhan, China and elsewhere, under conditions that virtually guaranteed the escape of weaponized microbes like SARS-CoV-2.
That’s just the short list.
Dr. Fauci and his band of pharma and Silicon Valley profiteers — working with corrupted politicians, captured federal agencies and the bought and brain-dead mainstream media — have used the COVID pandemic to mint billions from vaccines and other profitable medicines.
His disastrous mismanagement ran up one of the biggest COVID death counts among all nations.
Dr. Fauci has led the crusade to suppress functional remedies like Ivermectin and hydroxychloroquine which could have avoided 80 percent of the deaths and hospitalizations from COVID and ended the pandemic overnight.
We need to stop Dr. Fauci and the coup d’état against the Constitution, human rights and liberal democracy globally.
Because this book threatens their trillion-dollar vaccine enterprise, Dr. Fauci and his allies in the medical cartel, the media and military will hurl fierce criticism and use censorship — to debunk and silence “The Real Anthony Fauci.”
With your help, this book can play a transformational role in exposing Dr. Fauci as a charlatan and quack and in showing the world that Dr. Fauci, far from being a healer, is one the most noteworthy mass murderers in human history.
It is my hope that this book will motivate — and mobilize — millions more advocates for truth, health and democracy.
“The Real Anthony Fauci” publication date is Nov. 9. By pre-ordering your copy today, you’ll help push the book to bestseller status, diminishing the powers of the censors to silence me. Thank you.
New study: Billions of vaccinated people are at real risk of suffering Antibody-Dependent Enhancement
DAILY EXPOSE • AUGUST 21, 2021
For over a year, intensive research conducted by health experts has brought to light increasing concerns about “Antibody-Dependent Enhancement” (ADE), a phenomenon where vaccines make the disease far worse by priming the immune system for a potentially deadly overreaction.
ADE is well known to occur with coronavirus vaccines that have been tested in animal experiments. The big question has been whether it will emerge in the billions of people who have now been vaccinated around the world.
According to OurWorldInData.org, 31.7% of the world population has been vaccinated with one or more covid vaccines as of the 21st August 2021. That’s around 2.4 billion people, and every single one of them has taken an unproven, experimental, potentially deadly medical treatment in possibly the largest experiment ever conducted on humanity.
But how many of these people will die from vaccine adverse events, including ADE?
Well, a new science paper published in the Journal of Infection appears to provide solid evidence that the Covid-19 injections being administered around the world will, without question, cause ADE effects in people when they are exposed to the Delta variant or potentially other coronavirus strains.

The study is entitled, Infection-enhancing anti-SARS-CoV-2 antibodies recognize both the original Wuhan/D614G strain and Delta variants. A potential risk for mass vaccination and explains that while the current injections may provide some level of immunity against the alleged original covid virus, they present an unfortunate side effect – The acceleration of “infection-enhancing antibodies” which overreact to Delta variant infections.
What the paper is describing is classic antibody-dependent enhancement, meaning a hyperinflammatory reaction can kill the person as their “primed” immune system overreacts to new infections.

The study concludes, “ADE of delta variants is a potential risk for current vaccines,” and it goes on to explain the mechanism by which this ADE is emerging –
Using molecular modeling approaches, we show that enhancing antibodies have a higher affinity for Delta variants than for Wuhan/D614G NTDs. We show that enhancing antibodies reinforce the binding of the spike trimer to the host cell membrane by clamping the NTD to lipid raft microdomains… facilitating antibodies display a strikingly increased affinity. Thus, ADE may be a concern for people receiving vaccines based on the original Wuhan strain spike sequence (either mRNA or viral vectors).

The paper goes on to suggest that the original vaccines should be scrapped, and replaced with new, “second generation” vaccines that are engineered to attack the antigen targets of the Delta variant, but this would still be foolish because if the Covid-19 virus really exists then the virus will always mutate to a new form and evade the current injections on offer, no matter how many injections are administered to the world’s population.
Only natural immunity could ever put an end to this alleged pandemic because the current injections on offer do not prevent infection and do not prevent transmission.
With billions of people already injected, the findings of this scientific study suggest that it perfectly plausible that billions of people could die due to antibody-dependent enhancement or other devastating effects caused by the Covid-19 vaccines such as spike protein vascular damage, and evidence from Public Health England shows that it is already beginning to happen in the United Kingdom.

According to the report since the 1st February 2021 and the 15th August 2021 there have been 390 deaths among the unvaccinated population, an increase of 137 on the last count made in the previous report where the confirmed figure was 253 up to the 2nd August 2021. This equates to 0.2% of all confirmed infections among the unvaccinated population, in line with the average death rate seen since the alleged Covid-19 pandemic began.
However, up to the 15th August 2021 the fully vaccinated population has suffered a total of 679 deaths. This in an increase of 277 on the previous report where the confirmed figure was 402. It also equates to 0.9% of all confirmed infections among the fully vaccinated population. This suggests the Covid-19 vaccine actually increases the risk of death by at least 338% rather than reducing the risk of death by 95%.
This is what we’re seeing in the middle of summer, but winter is only around the corner and the evidence to suggest it’s going to be a rough one is overwhelming.
Dr Peter McCullough, Louisiana House Oversight Hearing on Monday, August 16, 2021
HealthFreedomLouisiana | August 23, 2021
Dr Peter McCullough offers expert testimony to the LA House Oversight Hearing on Monday, August 16, 2021.
Robert Dingwall: We Need to Hold Advocates of Mask Mandates to Account
By Toby Young | The Daily Sceptic | August 23, 2021
Robert Dingwall, a Professor at Nottingham Trent University and a leading sociologist, has written an excellent piece for Social Science Space criticising the imposition of mask mandates, given the paucity of evidence that masks interrupt transmission and the lack of any robust evaluation of the harms masks cause.
First, Professor Dingwall looks at the two main sources of evidence purporting to show that masks are effective.
One is studies at various scales of the impact of mask mandates on reported infection rates. These may compare cities, states, provinces or entire nations using time series data to look for inflections of rates that may be attributable to the mandates. A great deal of mathematical ingenuity has been expended in trying to control for the numerous confounders from biases in reporting, differences in diagnosis, leads and lags in public behaviour in response to the mandates, seasonal fluctuations, mobility – the list is almost endless. By the time these manipulations are complete, though, it is very difficult to conclude that there is any clear and obvious effect. Infection rates do not seem to vary much between comparable communities regardless of the NPIs that have been introduced. I have yet to see a study that identifies a clear and unequivocal benefit from a mask mandate in the form of an obvious inflection point attributable to the intervention. For all the reasons cited, this would be hard to find so perhaps we should not treat its absence as conclusive proof of a lack of benefit so much as something that is consistent with the RCT evidence that any benefit is likely to be minimal.
The other main source of evidence is laboratory studies of the properties of masks using techniques from physics and engineering. Some studies treat masks as a straightforward air filtration experiment. These are well-controlled and reproducible, but bear little resemblance to real-world conditions. The more sophisticated studies use mannikins to create a jet of air carrying inert particles into a controlled space, mimicking human exhalation. Masks can then be used to interrupt the air flow. The resulting measurements are the basis for computational models that provide more general descriptions of the spread of particles, which may be used to create video simulations. These studies are often elegant but suffer familiar problems in generalising to real-world environments. Within reason, the experimenter can manipulate the average velocity of the jet, the size of particles and the permeability of the mask in ways that aim to mimic breathing at different rates, coughing or sneezing. To get reliable measurements, including video or photographic evidence of the dispersion of the particles, the simulated exhalations must enter still air. Air, however, is never still in the real world. In any space there are thermal currents that are moving air around and dispersing exhalations in ways that are not captured, and probably cannot be captured, by the experimenter in a physically meaningful way. The efficacy of masks is also sensitive to the choice of particle size. If the experimenter favours droplets, larger particles, masks capture these quite well – but they also fall quickly to the ground and are unlikely to be inhaled by anyone at a normal social distance. If the experimenter favours aerosols, smaller particles, these are likely to pass through or around cloth masks, whose pore size is typically significantly larger than the aerosol particles. In which case the masks may filter a small proportion of the particles but probably let most through or around the edges. Where higher quality masks have been mandated, the community evidence runs into the same problems as before.
Having concluded that neither body of evidence is remotely persuasive, he then turns to the potential harms that masks do.
The precautionary principle also requires a proper evaluation of the potential harms. Few such studies have actually been done but relevant issues can readily be identified. Four are clearly important. First, they discriminate against a large group of people with communicative disabilities of speech and hearing, with neurodisabilities, such as autism or Aspergers, or with mental health issues, such as prior trauma from confinement as an abused child or as a survivor of sexual assault. Second, they discriminate against people who have medical consequences such as acute skin infections, eye infections or respiratory infections as a result of mask use. In the pre-pandemic world, such people could find workplaces where these issues were avoided but they cannot escape the mandates. Third, there is the impact on child development, particularly in relation to language and social interaction. The American Academy of Pediatrics claimed that there was no evidence for this, but there is a substantial body of research from psychology, education and linguistics establishing the importance of observing faces, particularly for small children. Fourth, and perhaps hardest to measure, there is the impact on community levels of fear and anxiety. This, indeed, has been the ultimate fall-back for committed advocates of masks – they may not have an impact on the transmission of the virus but they remind everyone that there is a pandemic going on and that they should be cautious every time they set foot outside their home – the safety of the home is assumed, of course. The consequence, of course, is that we are nudged towards regarding our fellow human beings as no more than potential vectors of infection. Everyone is guilty until proven innocent. The trust on which everyday life depends in modern societies is fatally compromised.
He concludes that mask mandates should never have been introduced, given the paucity of the evidence and the lack of research into potential harms.
If we do not think it is acceptable to have our lives ordered in ways that discriminate against large sections of the population, that impair the development of children, that damage the mental health of the nation and that make each of us fearful of the other, then it is time to hold the advocates of masking to account for the quality of evidence. It is simply too fragile to justify coercive measures, whether by the state or by private actors. Why has there been so little investment in RCTs? Why are mask advocates now arguing that RCTs would be unethical because the benefits are obvious, when they patently are not? It is more unethical to perpetuate a practice without evidence than to challenge one’s preconceptions. This is truly how science progresses and debate should be conducted.
Worth reading in full.
The Vapor, the Hot Hat, & the Witches’ Potion

By Margaret Anna Alice | Through The Looking Glass | August 3, 2021
Once upon a time in a prosperous land, a rumor swept across the kingdom that there was an invisible vapor floating through the air. Many vapors had come before, but this one was so extraordinary, it called for an extraordinary response.
This vapor, the town criers cried, could kill you at any time, anywhere. You could get it by talking, breathing, or singing. You could get it by standing or walking too closely to someone. You could even get it by playing. And the scariest thing of all—you could get it and not even know you had it.
The only way to escape was to hide indoors, keep away from people, and rub your hands with a clear jelly every time you touched something. Merchants stopped trading, apprentices stopped learning, and people stopped seeing people.

Every day, the town criers yelled out the number of people who had caught the vapor, although most didn’t know it since they felt the same as usual—just a lot more scared. They only learned they had it because of a certain spell a sorcerer had written down before the vapor came. The sorcerer had said it wasn’t supposed to be cast for vapors and couldn’t tell people if they had caught a vapor or not. But the sorcerer had died, and the king’s counselors decided to cast the spell, anyway, and that is how people found out they had the vapor.
The town criers shouted the latest death tolls so often their voices grew hoarse. Almost every one who died was very, very old or very, very sick or very, very fat. Hardly anyone else died, and at the end of the year, it would turn out about the same number had died as had in other years.

Still, it was a very scary vapor, and the entire kingdom had to change for the good of the public. The land was no longer prosperous, but the king just minted more coins and tossed them out to his subjects so they wouldn’t notice right away.
Eventually, people were told they could come out of hiding and the marketplace could open back up if everyone followed a few rules. They had to wear a hot, scratchy hat that covered their ears and eyes so the vapor couldn’t get into their earholes or eyeholes. They had to hop five times forward and five times backward if they accidentally got too close to another person. And, of course, they had to rub their hands with jelly after touching anything.

Some people thought the hats looked silly and were even a little dangerous since they made it hard for them to hear and see and made them sweat in the summer. The hopping took so much time, people weren’t able to get much done. When those people didn’t wear the hats or hop around, the rest of the people got very, very angry and said it was their fault people were dying and getting sick and couldn’t live the way they used to live. Some even took to wearing two or more hats for extra protection against the anti-hatters and anti-hoppers.

Every so often, the king would tell people to hide back inside again because too many people were catching the vapor. They couldn’t work or shop or visit people they loved. There wasn’t much to do besides lie around listening to the town criers, who always let people know how scared and angry and resentful they should all feel, especially toward the anti-hatters and anti-hoppers.
Suddenly, people started feeling more hopeful. A few witches who were richer than all the world’s kingdoms and queendoms combined offered to make a potion people would need to swallow every so often to keep them safe from the vapor—but it would only work if everyone drank it together.

It took a few months, but eventually the witches each had their own flavor—grape and orange and tropical punch—and they were ready to pour them into people’s mouths. Whenever potions had been made in the past, the witches had had to spend years and years making sure it was safe before giving it to people. This time, though, the vapor was so scary, they skipped all those steps so people could be saved sooner. They even got the king to issue a special decree so no one could hurt the witches if anything bad happened to them after drinking the potion. The king gathered three-quarters of the coins he had collected from the people that year and presented them to the witches.

Almost everybody couldn’t wait to drink the grape or orange or tropical punch potion. They bragged about going to get it and told everyone after they got their first and second drinks. When they came across someone who didn’t want to drink it, they got very, very cross. The town criers told everyone to yell at the anti-drinkers because it was their fault they couldn’t go back to life like it was before the vapor.
Something strange happened after people started drinking the potion. Some of them caught the vapor, anyway, but that was because it was a version of the vapor the witches hadn’t planned for—still, it was important to drink both doses of the potion because it was better than not drinking them. To be safe, though, the town criers said they should go back to wearing hot hats and hopping—although most hadn’t stopped to begin with because they were afraid of what would happen if they did (or worse, they might be mistaken for an anti-hatter, anti-hopper, or anti-drinker).

Even stranger, some of the people who had drunk the potion died either right after or not long after drinking it. Unlike the people who died from the vapor, these people were often very, very young or very, very healthy or very, very fit. The town criers never shouted about these deaths. If anyone brought it up, they called them an anti-hatter, anti-hopper, and anti-drinker.
Being an anti-drinker was the worst of all because everyone knows you need to drink to survive. If you’re against drinking the potion, you must surely be against drinking water, too, and we all know you can’t live without drinking water.
Not everyone who drank the potion died. Some just had peculiar things happen to their bodies. They shook all the time or got rare diseases or noticed parts of their bodies stopped working. They were bedridden or lame or hurt in different ways and couldn’t live the way they did before or even after the vapor. The town criers didn’t tell anyone about these people, either.

And then there were the drinkers who felt perfectly fine … for now. The potion had never been tried for longer than a few months, so no one was really sure what would happen in the next year or two or longer. It was also a different kind of potion than anyone had ever drunk before. This potion changed something inside you that could never be undone. People would also need to drink new versions of the potion every few months, and the king would need to continue giving three-quarters of the kingdom’s coins to the witches forever, or at least as long as the kingdom existed.

All the surviving drinkers were grateful to the witches and thanked them for saving their lives. They proudly displayed a mark on their chin that meant they’d drunk the potion. The ones who’d drunk it twice had two marks.
Those who didn’t have any marks were to blame for the kingdom’s problems. They weren’t permitted to shop in the marketplace or work or apprentice or take part in any public activities. They were shamed and shunned for being a threat to the people of the land. These people started to feel like they should leave the kingdom, but they weren’t allowed to travel without the double marks, and besides, all the other kingdoms and queendoms were the same as theirs, anyway. There wasn’t anyplace left where people weren’t afraid of the vapor and where they didn’t demand that everyone drink the potion.
Soon, the king decided the anti-drinkers were so dangerous, they would need to be locked in a dungeon until they agreed to drink the potion. They were free to choose whichever flavor they liked. If they decided not to drink, they would simply remain in the dungeon. It was entirely up to them.

One year passed, and then another. There were fewer and fewer people left in the kingdom. Eventually, so few people were left, the king could no longer collect enough coins to pay the witches. The rest of the kingdoms and queendoms around the world were in the same fix. They decided to join together into one king-queendom so they could collect enough coins to buy the potion.
After eight more years passed, there weren’t enough people left in all the world to cover the witches’ dues. The rulers decided everything that belonged to the people now belonged to the king-queendom. The people could still live in their hovels, but they wouldn’t own anything. They could earn their keep through labor—indeed, they might be put to work making the potion!

People no longer needed to decide what they wanted to do or be in life because the king-queendom would decide for them. People didn’t need to pay for anything because all the subjects got equally small amounts of the necessities. Everyone looked the same, acted the same, and thought the same.
Most people didn’t remember what it was like before the vapor. Some didn’t even know there was such a time.
The rulers, on the other hand, never wanted for anything. Nor did their friends, the town criers. The witches were the wealthiest of all—and deservedly so, as they had saved the world from the deadly vapor.

It wasn’t long before there were no more subjects. The rulers, the counselors, the town criers, and the witches had all the earth’s riches to themselves, and they lived happily ever after.
If you liked this post from Margaret Anna Alice Through the Looking Glass, why not share it? You can also Buy Me a Coffee, donate via PayPal,
© Margaret Anna Alice, LLC
Is Natural Immunity More Effective Than the COVID Shot?
By Dr. Joseph Mercola | August 18, 2021
According to Centers for Disease Control and Prevention data,1 COVID-19 “cases” have trended downward since peaking during the first and second week of January 2021.
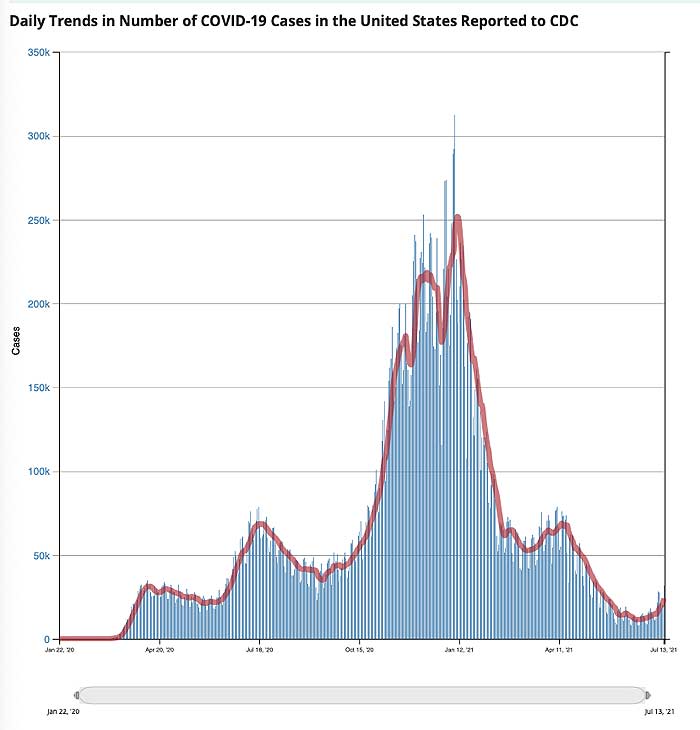
At first glance, this decline appears to be occurring in tandem with the rollout of COVID shots. January 1, 2021, only 0.5% of the U.S. population had received a COVID shot. By mid-April, an estimated 31% had received one or more shots,2 and as of July 13, 48.3% were fully “vaccinated.”3
However, as noted in a July 12, 2021, STAT News article,4 “cases” had started their downward trend before COVID shots were widely used. “Following patterns from previous pandemics, the precipitous decline in new cases of Covid-19 started well before a meaningful number of people had been vaccinated,” Robert M. Kaplan, Professor Emeritus at the UCLA Fielding School of Public Health, writes. He continues:
“Nearly 50 years ago, medical sociologists John and Sonja McKinlay examined5 death rates from 10 serious diseases: tuberculosis, scarlet fever, influenzae, pneumonia, diphtheria, whooping cough, measles, smallpox, typhoid, and polio. In each case, the new therapy or vaccine credited with overcoming it was introduced well after the disease was in decline.
More recently, historian Thomas McKeown noted6 that deaths from bronchitis, pneumonia, and influenza had begun rapidly falling 35 years before the introduction of new medicines that were credited with their conquest. These historical analyses are relevant to the current pandemic.”
‘Case’ Decline Preceded Widespread Implementation of Jab
As noted by Kaplan, COVID-19 “cases” peaked in early January 2021. January 8, more than 300,000 new positive test results were recorded on a daily basis. By February 21, that had declined to a daily new case count of 55,000. COVID-19 gene modification injections were granted emergency use authorization at the end of December 2020, but by February 21, only 5.9% of American adults had been fully vaccinated with two doses.
Despite such a low vaccination rate, new “cases” had declined by 82%. Considering health authorities claim we need 70% of Americans vaccinated in order to achieve herd immunity and stop the spread of this virus, this simply makes no sense. Clearly, the COVID shots had nothing to do with the decline in positive test results.
To be clear, reported cases mean positive test results, and we now know the vast majority of positive PCR tests have been, and still are, false positives. They’re not sick. They simply had a false “positive.” Right now, we’re also faced with yet another situation that complicates attempts at data analysis, and Kaplan understandably did not address any of these confounding factors.
But just so you’re aware, if you have been fully “vaccinated,” then the CDC recommends running the PCR test at a cycle threshold (CT) of 28 or lower, which dramatically lowers your chance of a false positive result, but if you are unvaccinated, the PCR test is recommended to be run at a CT of 40 or higher, virtually guaranteeing a false positive.
This is just one way by which the CDC is manipulating data to make the COVID shots appear more effective than they are. This also allows them to falsely claim that the vast majority of new cases are among the unvaccinated.
Naturally, if unvaccinated are tested in such a way as to maximize false positives, then they’re going to make up the bulk of the so-called caseload. In reality, though, the vast majority of them aren’t sick.
Meanwhile, those who have received the jabs only count as a COVID case if they’re hospitalized and/or die with a positive test result. These widely differing testing strategies skew the data and allow for false interpretations to be made.
Natural Immunity Explains Decline in Cases
As noted by Kaplan, the most reasonable explanation for declining rates of SARS-CoV-2 appears to be natural immunity from previous infections, which vary considerably from state to state.7 He goes on to cite a study8 by the National Institutes of Health, which suggests SARS-CoV-2 prevalence was 4.8 times higher than previously thought, thanks to undiagnosed infection.
In other words, they claim that for every reported positive test result, there were likely nearly five additional people who had the infection but didn’t get a diagnosis. To analyze this data further, Kaplan calculated the natural immunity rate by dividing the new estimated number of people naturally infected by the population of any given state. He writes:9
“By mid-February 2021, an estimated 150 million people in the U.S. (30 million times five) may have had been infected with SARS-CoV-2. By April, I estimated the natural immunity rate to be above 55% in 10 states: Arizona, Iowa, Nebraska, North Dakota, Oklahoma, Rhode Island, South Dakota, Tennessee, Utah, and Wisconsin.
At the other end of the continuum, I estimated the natural immunity rate to be below 35% in the District of Columbia, Hawaii, Maine, Maryland, New Hampshire, Oregon, Puerto Rico, Vermont, Virginia, and Washington …
By the end of 2020, new infections were already rapidly declining in nearly all of the 10 states where the majority may have had natural immunity, well before more than a minuscule percentage of Americans were fully vaccinated. In 80% of these states, the day when new cases were at their peak occurred before vaccines were available.
In contrast, the 10 states with lower rates of previous infections were much more likely to experience new upticks in Covid-19 cases in March and April … By the end of May, states with fewer new infections had significantly lower vaccination rates than states with more new infections.”
COVID Shots Cannot Eliminate COVID-19
So, SARS-CoV-2 cases were actually higher in states where natural immunity was low but vaccination rates were high. Meanwhile, in states where natural immunity due to undiagnosed exposure was high, but vaccination rates were low, the daily new caseload was also lower.
This makes sense if natural immunity is highly effective (which, historically it has always been and there’s no reason to suspect SARS-CoV-2 is any different in that regard). It also makes sense if the COVID shots aren’t really offering any significant protection against infection, which we also know is the case.
Vaccine manufacturers have already admitted these COVID shots will not provide immunity, meaning they will not prevent you from being infected. The idea behind these gene modification injections is that if/when you do get infected, you’ll hopefully experience milder symptoms, even though you’re still infectious and can spread the virus to others.
Kaplan ends his analysis by saying that COVID shots are a safer way to achieve herd immunity, and that they are “the best tool available for assuring that the smoldering fire of [COVID-19] is extinguished.” I disagree, based on two major issues.
First, and perhaps most importantly, this is an untested “vaccine” and we have no idea of the short-term let alone long-term damage it will cause, as any reasonable effort at collecting this data has been actively suppressed. Secondly, the survivability of COVID-19 outside of nursing homes is 99.74%. If you’re under the age of 40, your chance of surviving a bout of COVID-19 is 99.99%.10,11,12
You can’t really improve your chances of surviving beyond that, so COVID shots cannot realistically end the pandemic. Meanwhile, the COVID shots come with an ever-growing list of potential side effects that can take years if not decades off your natural life span. The shots are particularly unnecessary for anyone with natural immunity,13 yet that’s what the CDC recommends.14
Why Push COVID Jab on Those with Natural Immunity?
In January 2021, Dr. Hooman Noorchashm, a cardiac surgeon and patient advocate, sent a public letter15 to the U.S. Food and Drug Administration commissioner detailing the risks of vaccinating individuals who have previously been infected with SARS-CoV-2, or who have an active SARS-CoV-2 infection.
He urged the FDA to require prescreening for SARS-CoV-2 viral proteins to reduce the risk of injuries and deaths following vaccination, as the vaccine may trigger an adverse immune response in those who have already been infected with the virus. In March 2021, Fox TV host Tucker Carlson interviewed him about these risks. In that interview, Noorchashm said:16
“I think it’s a dramatic error on part of public health officials to try to put this vaccine into a one-size-fits-all paradigm … We’re going to take this problem we have with the COVID-19 pandemic, where a half-percent of the population is susceptible to dying, and compound it by causing totally avoidable harm by vaccinating people who are already infected …
The signal is deafening, the people who are having complications or adverse events are the people who have recently or are currently or previously infected [with COVID]. I don’t think we can ignore this.”
In an email to The Defender, Noorchashm fleshed out his concerns, saying:17
“Viral antigens persist in the tissues of the naturally infected for months. When the vaccine is used too early after a natural infection, or worse during an active infection, the vaccine force activates a powerful immune response that attacks the tissues where the natural viral antigens are persisting. This, I suggest, is the cause of the high level of adverse events and, likely deaths, we are seeing in the recently infected following vaccination.”
Despite being widely ignored, Noorchashm continues to push for the implementation of prevaccine screening using PCR or rapid antigen testing to determine whether the individual has an active infection, and an IgG antibody test to determine past infection.
If either test is positive, he recommends delaying vaccination for a minimum of three to six months to allow your IgG levels to wane. At that point, he recommends testing your blood IgG level and use that as a guide to decide the timing of your vaccination.
Those with Natural Immunity Have Higher Risk of Side Effects
Mere weeks after Noorchashm’s letter to the FDA, an international survey18 confirmed his concerns. After surveying 2,002 people who had received a first dose of COVID-19 vaccine, they found that those who had previously had COVID-19 experienced “significantly increased incidence and severity” of side effects, compared to those who did not have natural immunity.
The mRNA COVID-19 vaccines were linked to a higher incidence of side effects compared to the viral vector-based COVID-19 vaccines, but tended to be milder, local reactions. Systemic reactions, such as anaphylaxis, flu-like illness and breathlessness, were more likely to occur with the viral vector COVID-19 vaccines.
Like Noorchashm before them, the researchers called on health officials to reevaluate their vaccination recommendations for people who’ve had COVID-19:19
“People with prior COVID-19 exposure were largely excluded from the vaccine trials and, as a result, the safety and reactogenicity of the vaccines in this population have not been previously fully evaluated. For the first time, this study demonstrates a significant association between prior COVID19 infection and a significantly higher incidence and severity of self-reported side effects after vaccination for COVID-19.
Consistently, compared to the first dose of the vaccine, we found an increased incidence and severity of self-reported side effects after the second dose, when recipients had been previously exposed to viral antigen.
In view of the rapidly accumulating data demonstrating that COVID-19 survivors generally have adequate natural immunity for at least 6 months, it may be appropriate to re-evaluate the recommendation for immediate vaccination of this group.”
CDC Misrepresents Data to Push Jab on Those with Immunity
So far, the CDC has refused to change its stance on the matter. Instead, officials at the agency seem to have doubled down and actually go out of their way to misrepresent data in an effort to harass those with natural immunity to inappropriately take the jab, which is clearly clinically unnecessary.
In a report issued by the CDC’s Advisory Committee on Immunization Practices (ACIP) December 18, 2020, the Pfizer-BioNTech COVID-19 vaccine was said to have “consistent high efficacy” of 92% or more among people with evidence of previous SARS-CoV-2 infection.20
After looking at the Pfizer trial data, Rep. Thomas Massie — a Republican Congressman for Kentucky and an award-winning scientist in his own right — discovered that’s completely wrong. In a January 30, 2021, Full Measure report, investigative journalist Sharyl Attkisson described how Massie tried, in vain, to get the CDC to correct its error. According to Massie:21,22
“There is no efficacy demonstrated in the Pfizer trial among participants with evidence of previous SARS-CoV-2 infections and actually there’s no proof in the Moderna trial either …
It [the CDC report] says the exact opposite of what the data says. They’re giving people the impression that this vaccine will save your life, or save you from suffering, even if you’ve already had the virus and recovered, which has not been demonstrated in either the Pfizer or the Moderna trial.”
After multiple phone calls, CDC deputy director Dr. Anne Schuchat finally acknowledged the error and told Massie it would be fixed. “As you note correctly, there is not sufficient analysis to show that in the subset of only the people with prior infection, there’s efficacy. So, you’re correct that that sentence is wrong and that we need to make a correction of it,” Schuchat said in the recorded call.
January 29, 2021, the CDC issued its supposed correction, but rather than fix the error, they simply rephrased the mistake in a different way. This was the “correction” they issued:
“Consistent high efficacy (≥92%) was observed across age, sex, race, and ethnicity categories and among persons with underlying medical conditions. Efficacy was similarly high in a secondary analysis including participants both with or without evidence of previous SARS-CoV-2 infection.”
As you can see, the “correction” still misleadingly suggests that vaccination is effective for those previously infected, even though the data showed no such thing. Children of ever-younger ages are also being pushed to get the COVID jab, even though they have the absolute lowest risk of dying from COVID-19 of any group.
Data23 from the first 12 months of the pandemic in the U.K. show just 25 people under the age of 18 died from or with COVID-19.24 In all, 251 children under 18 were admitted to intensive care between March 2020 and February 2021. The absolute risk of death from COVID-19 in children is 2 in 1 million.
Vaccine Provides Far Less Protection Than Natural Immunity
While some claim vaccine-induced immunity offers greater protection against SARS-CoV-2 infection than natural immunity, historical and current real-world data simply fail to support this non-common sense assertion.
As recently reported by Attkisson25,26 and David Rosenberg 7 Israeli National News,27 recent Israeli data show those who have received the COVID jab are 6.72 times more likely to get infected than people who have recovered from natural infection.
Among the 7,700 new COVID cases diagnosed so far during the current wave of infections that began in May 2021, 39% were vaccinated (about 3,000 cases), 1% (72 patients) had recovered from a previous SARS-CoV-2 infection and 60% were neither vaccinated nor previously infected. Israeli National News notes:28
“With a total of 835,792 Israelis known to have recovered from the virus, the 72 instances of reinfection amount to 0.0086% of people who were already infected with COVID.
By contrast, Israelis who were vaccinated were 6.72 times more likely to get infected after the shot than after natural infection, with over 3,000 of the 5,193,499, or 0.0578%, of Israelis who were vaccinated getting infected in the latest wave.”
Breakthrough Infections Are on the Rise
Other Israeli data also suggest the limited protection offered by the COVID shot is rapidly eroding. August 1, 2021, director of Israel’s Public Health Services, Dr. Sharon Alroy-Preis, announced half of all COVID-19 infections were among the fully vaccinated.29 Signs of more serious disease among fully vaccinated are also emerging, she said, particularly in those over the age of 60.
Even worse, August 5, Dr. Kobi Haviv, director of the Herzog Hospital in Jerusalem, appeared on Channel 13 News, reporting that 95% of severely ill COVID-19 patients are fully vaccinated, and that they make up 85% to 90% of COVID-related hospitalizations overall.30
Other areas where a clear majority of residents have been vaccinated are also seeing spikes in breakthrough cases. In Gibraltar, which has a 99% COVID jab compliance rate, COVID cases have risen by 2,500% since June 1, 2021.31
US Outbreak Shatters ‘Pandemic of Unvaccinated’ Narrative
An investigation by the CDC32,33 also dispels the narrative that we’re in a “pandemic of the unvaccinated.” An outbreak in Barnstable County, Massachusetts, resulted in 469 new COVID cases among residents who had traveled into town between July 3 and July 17, 2021.
Of these cases, 74% were fully vaccinated, as were 80% of those requiring hospitalization.Most, but not all, had the Delta variant of the virus. The CDC also found that fully vaccinated individuals who contract the infection had as high a viral load in their nasal passages as unvaccinated individuals who got infected.34 This means the vaccinated are just as infectious as the unvaccinated. According to Attkisson:35
“CDC’s newest findings on so-called ‘breakthrough’ infections in vaccinated people are mirrored by other data releases. Illinois health officials recently announced36 more than 160 fully-vaccinated people have died of Covid-19, and at least 644 been hospitalized; 10 deaths and 51 hospitalizations counted in the prior week …
In July, New Jersey reported 49 fully vaccinated residents had died of Covid; 27 in Louisiana; 80 in Massachusetts … Nationally, as of July 12, CDC said it was aware of more than 4,400 people who got Covid-19 after being fully vaccinated and had to be hospitalized; and 1,063 fully vaccinated people who died of Covid.”
It is important to note this data is over 1 month old now and it is likely that many thousands of fully “vaccinated” have now died from COVID-19.
Natural Immunity Appears Robust and Long-Lasting
An argument we’re starting to hear more of now is that even though natural immunity after recovery from infection appears to be quite good, “we don’t know how long it’ll last.” This is rather disingenuous, seeing how natural immunity is typically lifelong, and studies have shown natural immunity against SARS-CoV-2 is at bare minimum longer lasting than vaccine-induced immunity.
Here’s a sampling of scholarly publications that have investigated natural immunity as it pertains to SARS-CoV-2 infection. There are several more in addition to these:
Science Immunology October 202038 found that “RBD-targeted antibodies are excellent markers of previous and recent infection, that differential isotype measurements can help distinguish between recent and older infections, and that IgG responses persist over the first few months after infection and are highly correlated with neutralizing antibodies.”
The BMJ January 202139 concluded that “Of 11, 000 health care workers who had proved evidence of infection during the first wave of the pandemic in the U.K. between March and April 2020, none had symptomatic reinfection in the second wave of the virus between October and November 2020.”
Science February 202140 reported that “Substantial immune memory is generated after COVID-19, involving all four major types of immune memory [antibodies, memory B cells, memory CD8+ T cells, and memory CD4+ T cells]. About 95% of subjects retained immune memory at ~6 months after infection. Circulating antibody titers were not predictive of T cell memory.
Thus, simple serological tests for SARS-CoV-2 antibodies do not reflect the richness and durability of immune memory to SARS-CoV-2.” A 2,800-person study found no symptomatic reinfections over a ~118-day window, and a 1,246-person study observed no symptomatic reinfections over 6 months.
A February 2021 study posted on the prepublication server medRxiv41 concluded that “Natural infection appears to elicit strong protection against reinfection with an efficacy ~95% for at least seven months.”
An April 2021 study posted on medRxiv42 reported “the overall estimated level of protection from prior SARS-CoV-2 infection for documented infection is 94.8%; hospitalization 94.1%; and severe illness 96·4%. Our results question the need to vaccinate previously-infected individuals.”
Another April 2021 study posted on the preprint server BioRxiv43 concluded that “following a typical case of mild COVID-19, SARS-CoV-2-specific CD8+ T cells not only persist but continuously differentiate in a coordinated fashion well into convalescence, into a state characteristic of long-lived, self-renewing memory.”
A May 2020 report in the journal Immunity 44 confirmed that SARS-CoV-2-specific neutralizing antibodies are detected in COVID-19 convalescent subjects, as well as cellular immune responses. Here, they found that neutralizing antibody titers do correlate with the number of virus-specific T cells.
A May 2021 Nature article45 found SARS-CoV-2 infection induces long-lived bone marrow plasma cells, which are a crucial source of protective antibodies. Even after mild infection, anti-SARS-CoV-2 spike protein antibodies were detectable beyond 11 months’ post-infection.
A May 2021 study in E Clinical Medicine 46 found “antibody detection is possible for almost a year post-natural infection of COVID-19.” According to the authors, “Based on current evidence, we hypothesize that antibodies to both S and N-proteins after natural infection may persist for longer than previously thought, thereby providing evidence of sustainability that may influence post-pandemic planning.”
Cure-Hub data47 confirm that while COVID shots can generate higher antibody levels than natural infection, this does not mean vaccine-induced immunity is more protective. Importantly, natural immunity confers much wider protection as your body recognizes all five proteins of the virus and not just one. With the COVID shot, your body only recognizes one of these proteins, the spike protein.
A June 2021 Nature article48 points out that “Wang et al. show that, between 6 and 12 months after infection, the concentration of neutralizing antibodies remains unchanged. That the acute immune reaction extends even beyond six months is suggested by the authors’ analysis of SARS-CoV-2-specific memory B cells in the blood of the convalescent individuals over the course of the year.
These memory B cells continuously enhance the reactivity of their SARS-CoV-2-specific antibodies through a process known as somatic hypermutation. The good news is that the evidence thus far predicts that infection with SARS-CoV-2 induces long-term immunity in most individuals.”
Another June Nature paper concluded that “In the absence of vaccination antibody reactivity [to the receptor binding domain (RBD) of SARS-CoV-2], neutralizing activity and the number of RBD-specific memory B cells remain relatively stable from 6 to 12 months.” According to the authors, the data suggest “immunity in convalescent individuals will be very long lasting.”
What Makes Natural Immunity Superior?
The reason natural immunity is superior to vaccine-induced immunity is because viruses contain five different proteins. The COVID shot induces antibodies against just one of those proteins, the spike protein, and no T cell immunity. When you’re infected with the whole virus, you develop antibodies against all parts of the virus, plus memory T cells.
This also means natural immunity offers better protection against variants, as it recognizes several parts of the virus. If there are significant alternations to the spike protein, as with the Delta variant, vaccine-induced immunity can be evaded. Not so with natural immunity, as the other proteins are still recognized and attacked.
Not only that but the COVID jabs actually actively promote the production of variants for which they provide virtually no protection at all, while those with natural immunity do not cause variants and are nearly universally protected against them.
If we are to depend on vaccine-induced immunity, as public health officials are urging us to do, we’ll end up on a never-ending booster treadmill. Boosters will absolutely be necessary, as the shot offers such narrow protection against a single protein of the virus. Already, Moderna has publicly stated that the need for additional boosters is expected.
Ultimately It’s About Wealth Transfer, Power and Control
Government agencies typically don’t issue recommendations without ulterior motives. Since current recommendations make absolutely no sense from a medical and scientific standpoint, what might the reason be for these illogical and reprehensibly unethical recommendations to inject people who don’t need it with experimental gene modification technology?
Why are they so hell-bent on getting a needle in every arm? And why are they refusing to perform any kind of risk-benefit analysis?
Data already indicate these COVID-19 injections could be the most dangerous medical product we’ve ever seen, and a June 24, 2021, peer-reviewed study published in the medical journal Vaccines warned we are in fact killing nearly as many with the shots as would die from COVID-19 itself.50
Using data from a large Israeli field study and two European drug reactions databases, they recalculated the NNTV for Pfizer’s mRNA shot. To prevent one case of COVID-19, anywhere between 200 and 700 had to be injected. To prevent a single death, the NNTV was between 9,000 and 50,000, with 16,000 as a point estimate.
Meanwhile, the number of people reporting adverse reactions from the shots was 700 per 100,000 vaccinations. For serious side effects, there were 16 reports per 100,000 vaccinations, and the number of fatal side effects was 4.11 per 100,000 vaccinations.
The final calculation suggested that for every three COVID-19 deaths prevented, two died from the shots. “This lack of clear benefit should cause governments to rethink their vaccination policy,” the authors concluded.
As has become the trend, a letter expressing “concern” about the study was published June 28, 2021, resulting in the paper being abruptly retracted July 2, 2021, against the authors’ objections. They disagreed with the accusation that their data and subsequent conclusion were misrepresentative, but the paper was retracted before they had time to publish a rebuttal.
Based on everything we’ve discovered so far, it seems a pandemic virus industrial complex is running the show, with a goal to eliminate medical rights and personal freedoms in order to centralize power, control and wealth.
By the looks of things, the COVID-19 mass psychosis and loss of any rational thinking by nearly half the population will continue to persist as long as the propaganda continues. Fear will continue and if need be, other engineered viruses may be released, for which they’ll create even more gene modification injections.
I believe the truth will eventually be so overwhelming, it’ll sweep away the confusion and the lies.
Sources and References
- 1 COVID.CDC.gov, COVID Cases in the US Reported to the CDC, Viewed July 15, 2021
- 2 Bloomberg COVID Vaccine Tracker, see US Vaccinations vs Cases graph, top portion
- 3 Mayo Clinic COVID Vaccine Tracker
- 4, 7, 9 STAT News July 12, 2021
- 5 Health and Society 1977; 55(3): 405-428
- 6 Population Studies, A Journal of Demography 1975; 29(3): 391-422
- 8 NIH.gov June 22, 2021
- 10 Annals of Internal Medicine September 2, 2020 DOI: 10.7326/M20-5352
- 11 Greek Reporter June 27, 2020
- 12 WFAE.org July 2, 2020
- 13 medRxiv June 1, 2021
- 14 U.S. CDC, COVID-19 Vaccination FAQs April 30, 2021
- 15 Medium February 15, 2021
- 16, 17 The Defender March 23, 2021
- 18 Life 2021; 11(3): 249
- 19 Life 2021; 11(3): 249, Discussion
- 20 MMWR December 18, 2020
- 21 Full Measure After Hours Podcast January 30, 2021
- 22 Full Measure News January 31, 2021
- 23 Research Square July 7, 2021
- 24 BBC July 9, 2021
- 25 Sharylattkisson.com August 8, 2021
- 26, 35 Sharylattkisson.com August 6, 2021
- 27, 28 David Rosenberg 7 July 13, 2021
- 29 Bloomberg August 1, 2021 (Archived)
- 30 American Faith August 8, 2021
- 31 Big League Politics August 4, 2021
- 32 CDC MMWR July 30, 2021; 70
- 33 CNBC July 30, 2021
- 34 NBC News August 7, 2021
- 36 NBC Chicago July 28, 2021
- 37 Reddit COVID-19 and Immunity
- 38 Science Immunology October 8, 2020; 5(52): eabe0367
- 39 BMJ 2021;372:n99
- 40 Science February 5, 2021; 371(6529): eabf4063
- 41 medrxiv February 8, 2021 DOI: 10.1101/2021.01.15.21249731
- 42 medRxiv April 24, 2021 (PDF)
- 43 BioRxiv April 29, 2021 DOI: 10.1101/2021.04.28.441880
- 44 Immunity June 16, 2020; 52(6): 971-977.E3
- 45 Nature 2021; 595: 421-425
- 46 E Clinical Medicine 2021; 36: 100902 (PDF)
- 47 Cure-hub June 11, 2021
- 48 Nature June 14, 2021
- 49 The Hill August 5, 2021
- 50 Vaccines 2021; 9(7): 693
Can ‘Big Brother’ Save You From a Virus?
By Dr. Joseph Mercola | August 17, 2021
In June 2021, the U.S. National Security Council released a new “National Strategy for Countering Domestic Terrorism” document.1 While it’s being largely framed as a tool to fight White supremacy and political extremism, the definition of what constitutes a “domestic terrorist” is incredibly vague and based on ideologies rather than specific behaviors.
It’s not difficult to imagine this policy being used to silence political opposition simply by labeling anyone who disagrees with the government as a domestic terrorist and charging them with a hate crime.
We’re already seeing signs suggesting that this is the path we’re on. July 28, 2021, Dr. Peter Hotez published a paper2 in PLOS Biology titled “Mounting Antiscience Aggression in the United States,” in which he suggests criticizing Dr. Anthony Fauci and other scientists ought to be labeled a “hate crime.” Commenting on the paper, Paul Joseph Watson at Summit News writes:3
“This is yet another transparent effort to dehumanize anti-lockdown protesters and demonize people who merely want to exercise bodily autonomy while elevating Fauci and his ilk to Pope-like status. Science isn’t supposed to be a religious dogma that is set in stone, it’s an ever-evolving knowledge base that changes and improves thanks to dissent and skepticism.”
Science Depends on Questioning and Challenging Assumptions
Attorney Jonathan Turley also responded to Hotez’s paper in an August 4, 2021, blog post, saying:4
“’Religion is a culture of faith; science is a culture of doubt.’ Feynman’s statement captures how science depends upon constant questioning and challenging of assumptions …
[T]here remain important debates over not just the underlying science relation to Covid-19 but the implications for such science for public policies. Criminalizing aspects of that debate would ratchet up the threats against those with dissenting views, including some scientists. That would harm not just free speech but science in the long run.”
Should We Have Protected Classes That Cannot Be Questioned?
Turley also points out how making scientists a protected class (and one would assume only those with specific political leanings) is a slippery slope that will likely have unwieldy ramifications:5
“The federal hate crime laws focus on basis of a person’s characteristics of race, religion, ethnicity, nationality, gender, sexual orientation, and gender identity. We have seen calls for adding professions like police officers, which I also opposed.
As with police officers, the inclusion of such professions would have a direct and inimical impact on free speech in our society. Indeed, it would create a slippery slope as other professions demand inclusion from reporters to ministers to physicians. Hate crimes would quickly apply to a wide array of people due to their occupations.”
Will America Accept No-Fly List for Unvaccinated?
Writing for The Atlantic,6 former assistant secretary for Homeland Security Juliette Kayyem posits that people who do not want to be part of the COVID injection experiment “need to bear the burden” when it comes to preventing the spread of SARS-CoV-2.
“The number of COVID-19 cases keeps growing, even though remarkably safe, effective vaccines are widely available,” Kayyem writes.7 “Many public agencies are responding by reimposing masking rules on everyone.
But at this stage of the pandemic, tougher universal restrictions are not the solution to continuing viral spread. While flying, vaccinated people should no longer carry the burden for unvaccinated people.
The White House has rejected a nationwide vaccine mandate … but a no-fly list for unvaccinated adults is an obvious step that the federal government should take.
It will help limit the risk of transmission at destinations where unvaccinated people travel — and, by setting norms that restrict certain privileges to vaccinated people, will also help raise the stagnant vaccination rates that are keeping both the economy and society from fully recovering.”
Travel Ban Identified as Effective Coercion Strategy
According to Kayyem, traveling in general and flying in particular is not a human right, and putting unvaccinated individuals on a no-fly list is a matter of national security, in the sense that the country needs to protect itself from people capable of spreading this dangerous virus.
She makes no mention of the scientifically confirmed fact that none of the COVID shots actually prevent you from getting infected, and that “vaccinated” individuals carry the same viral load as the unvaccinated,8,9 which means they’re just as infectious. The main difference is that vaccinated individuals might not realize that they’re carriers, as the primary effect when the injections do work is lessening symptoms of infection.
Kayyem also cites a New York Times and Kaiser Family Foundation poll in which 41% of unvaccinated respondents had said prohibition on airline travel would sway their decision, including 11% of those “adamantly opposed” to vaccination. In other words, where free doughnuts and million-dollar lotteries have failed to coerce people to get the shot, an airline travel ban might do the trick.
Despite her former position within government, she makes no mention of laws forbidding coercion of medical volunteers, such as the U.S. Code of Federal Regulations 45 CFR 46 (subpart A, the Belmont report),10 the International Covenant on Civil and Political Rights treaty,11 the Declaration of Helsinki12 or the Nuremberg Code.13 Supreme court rulings have also clarified that Americans have the right to choose their own health care in general.14,15
Reframing to Confuse the Issue
Kayyem suggests circumventing such basic human rights by reframing the issue. She writes:16
“The public debate about making vaccination a precondition for travel, employment, and other activities has described this approach as vaccine mandates, a term that … suggests that unvaccinated people are being ordered around arbitrarily.
What is actually going on, mostly, is that institutions are shifting burdens to unvaccinated people … rather than imposing greater burdens on everyone.
Americans still have a choice to go unvaccinated, but that means giving up on certain societal benefits. Nobody has a constitutional right to attend The Lion King on Broadway or work at Disney or Walmart … People who still want to wait and see about the vaccines can continue doing so. They just can’t keep pushing all the costs on everyone else.”
As pointed out by Swift Headline,17 the owner of Atlantic magazine, Laurene Powell Jobs, the billionaire widow of Steve Jobs, owns two private jets herself, giving her the freedom to fly around the world at will, regardless what vaccine mandates might be in place. Many other ultra-rich individuals would also be able to ignore the rules due to wealth alone, essentially turning them into a protected class. Swift Headline points out this projection:18
“The Atlantic went on to say unvaccinated people who are exercising their individual rights as free Americans ‘do not deserve’ to be a ‘protected class’ …
Jobs’s wealth and class status is detailed in Breitbart News’ Editor-in-Chief Alex Marlow’s book, ‘Breaking the News: Exposing the Establishment Media’s Hidden Deals and Secret Corruptions,’ which ‘exposes the hidden connections between the establishment media and the activist left.’
As Marlow details, Jobs’s past is a privileged one … Jobs ‘married well and inherited a lot of money, and her wealth is tied up in some of world’s biggest companies,’ Marlow continues. ‘She is the establishment.’”
The Price of Admission to Society
August 2, 2021, the San Francisco Chronicle also published an opinion piece19 by the Chronicle editorial board, in which they suggested we ought to “Make vaccination the price of admission to society.” One way to evaluate the reasonableness of such a proposition is to replace COVID “vaccination” with anything else. How about: “Make proof of contraception use the price of admission to bars and nightclubs.”
“Make clear skin the price of admission to gyms and public swimming pools.” “Make being taller than 5’ 9” the price of admission to theme parks.” “Make having a BMI below 25 the price of admission to airline flights.” “Make proof of not having an illness the price of admission to in-hospital care.”
According to the Chronicle editorial board, “the unvaccinated account for over 95% of hospitalizations and deaths.”20 The board does not cite where it got that data from, so let’s review the source of that data.
In an August 5, 2021, video statement, Centers for Disease Control and Prevention director Dr. Rochelle Walensky noted that this statistic was obtained by looking at hospitalization and mortality data from January through June 2021 — a timeframe during which the vast majority of the United States population were unvaccinated.
When you look at more recent data, the trend is swinging in the opposite direction.
January 1, 2021, only 0.5% of the U.S. population had received a COVID shot. By mid-April, an estimated 31% had received one or more shots,21 and as of June 15, 48.7% were fully “vaccinated.”22
The CDC has also pointed out that you are not considered “fully vaccinated” until two weeks after your second dose (in the case of Pfizer or Moderna), which is given six weeks after your first shot.23 This means that if you receive your first dose on June 1, you won’t be “fully vaccinated” until eight weeks later, around August 1.
So, the narrative that we’re in a “pandemic of the unvaccinated” was created by using statistics from a time period when the U.S. as a whole was largely unvaccinated. When you look at more recent data, the trend is swinging in the opposite direction.
Vaccinated Now Comprise the Bulk of Hospitalizations
For example, August 1, 2021, Dr. Sharon Alroy-Preis, director of Israel’s Public Health Services, announced half of all COVID-19 infections were among the fully vaccinated.24
A few days later, August 5, Dr. Kobi Haviv, director of the Herzog Hospital in Jerusalem, appeared on Channel 13 News, reporting that 95% of severely ill COVID-19 patients are fully vaccinated, and that they make up 85% to 90% of COVID related hospitalizations overall.25
In Scotland, official data on hospitalizations and deaths show 87% of those who have died from COVID-19 in the third wave that began in early July were vaccinated,26 and in Gibraltar, which has a 99% COVID jab compliance rate, COVID cases have risen by 2,500% since June 1, 2021.27
A CDC investigation of an outbreak in Barnstable County, Massachusetts between July 6 through July 25, 2021, found 74% of those who received a diagnosis of COVID19, and 80% of hospitalizations, were among the fully vaccinated.28,29 Most, but not all, had the Delta variant.
“What the breakthrough cases appear to show is that the delta variant of the coronavirus is more easily carried and transmitted by vaccinated people than its predecessors,” the Chronicle editorial board writes.30
“In any case, the greater apparent transmissibility of the variant makes it that much more important to protect as many people as possible from severe COVID by increasing inoculation rates.”
What the board appears to be saying is that unvaccinated people must be protected against severe infection, against their will, if need be, and the best way to do that is to discriminate against them and treat them like second-class citizens.
Again, a simple way to check the reasonableness of this argument is to swap out the COVID reference for something else. How about, “It’s important to protect as many people as possible from dying in car accidents by raising car prices so fewer people can get behind the wheel.”
Can ‘Big Brother’ Save You From a Virus?
As early as April 2020, The Times in the U.K. weighed in with similar suggestions, stating “We need Big Brother to beat this virus.”31 Clare Foges, the author of the piece in question, went on to say, “Don’t let the civil liberties lobby blind us to the fact that greater state surveillance, including ID cards, is required.”
The argument that Big Brother can protect us from infection is ludicrous on its face, because no amount of people surveillance can prevent microscopic viruses from circulating.
The No. 1 place of viral spread is in institutions, such as nursing homes and hospitals, yet the staff within them are among the most well-trained in pathogenic control. If trained hospital staff can’t prevent the spread of viruses, how can government officials do it?
Importantly, the argument that we need vaccine passports to prove we’re “clean” enough to participate in society immediately falls apart when you take into account the fact that the COVID shots do not provide immunity. You can still be infected, carry the virus and spread it to others.
We’ve already seen several examples of situations where 100% of people were fully “vaccinated” against COVID-19 yet an outbreak occurred. We’ve even seen over 100 fully COVID injected people die from COVID in one state alone, Massachusetts,32 so it is likely there are now many thousands of fully “vaccinated” who have died from COVID.
Even a 100% Vaccination Rate Cannot Eliminate COVID
Most recently, Carnival cruise lines experienced an outbreak despite every last person on that ship having proof of COVID “vaccination.”33 The cruise liner had even intentionally reduced capacity from 4,000 to 2,800 to provide ample social distancing capability. None of the measures worked. People got sick anyway, which makes perfect sense if you remember that the shot doesn’t provide immunity, only symptom reduction.
Cases such as these clearly reveal that even if everyone gets the shot, SARS-CoV-2 will mutate and continue to circulate, taking people out here and there. To think that giving up basic rights and freedoms is the answer simply isn’t logical. Taking responsibility for your own health is, and that includes deciding if and how you want to protect yourself from SARS-CoV-2.
Not everyone is deathly afraid of COVID-19. Many realize there are safe and effective treatments available, such as the Front Line COVID-19 Critical Care Alliance’s I-MASS Prevention and At-Home Treatment protocol and I-MASK+ Early Outpatient Treatment protocol.
Nebulized hydrogen peroxide can also be used for prevention and treatment of COVID-19, as detailed in Dr. David Brownstein’s case paper34 and Dr. Thomas Levy’s free e-book, “Rapid Virus Recovery.” And if there’s effective treatment, there’s little need to risk permanent side effects from an experimental gene technology that can only provide a narrow range of protection in the first place.
Featured Video

The Truth About the Trump Shootings with Ken Silva
or go to
Aletho News Archives – Video-Images
From the Archives
Trans ‘milk’ as good as the real thing – NHS
RT | February 18, 2024
The drug-induced nipple secretions of trans women are as good as mothers’ breast milk for babies, the University of Sussex Hospitals NHS Trust claimed in a letter to campaigners made public in a report by British think tank the Policy Exchange on Sunday.
The healthcare trust’s medical director, Rachel James, argued that the off-label prescription drug cocktail men transitioning to female take in order to produce milk was “similar to the natural hormones which encourage lactation to develop when the baby is newly born.”
“The evidence which is available demonstrates that the milk is comparable to that produced following the birth of a baby,” James wrote in the letter, sent to Children of Transitioners last August.
Biological men who wish to lactate must first take hormones to grow milk glands and then take high doses of either domperidone or metoclopramide to stimulate milk production. Neither drug is approved for this use, though they are occasionally prescribed off-label to biological women who have trouble lactating.
However, domperidone’s own manufacturer, Janssen, warns patients the drug “may cause unwanted side effects affecting the heart in a breastfed baby” and “should be used during breastfeeding only if your physician considers this clearly necessary.” … continue
Blog Roll
 Aletho News
- Seyed M. Marandi: U.S. Strike Imminent – Toward Total War in the Middle East
- Russia Voted Under Fire. Washington Is Loading the Tankers.
- 12 Things Your Oncologist Was Trained Not to Tell You
- Anthrax Attacks Paved Way for COVID-Era ‘Junk Drugs and Vaccines’
- How Real Is the Impact of Western Sanctions on Israel?
- France, You Are Guilty: How Paris Turned Western Sahara into the Maghreb’s Powder Keg
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- Your Milk Is Not the Problem
- The Truth About the Trump Shootings with Ken Silva
- ARE PATIENTS BEING PROPERLY INFORMED ABOUT OZEMPIC?
- If Americans Knew
- Salah Sarsour’s Legal Team Says DHS Has Not Met Its Burden to Prove He Is Deportable
- An analysis of tax forms by The Intercept show Kraft’s charity and LLC have donated to Friends of the IDF and AIPAC’s super PAC.
- Israeli attacks kill four Palestinians in Gaza – Daily Update
- Inside Gaza’s death trap of collapsing, bombed-out buildings
- The everyday items Israel bans from Gaza every day
- Inside the siege, the ruined buildings of Gaza – Daily Update
- Debunking The Claim That Macklemore Has A “History Of Antisemitism”
- CPJ demands release of arrested Palestinian-US journalist near Bethlehem
- Robert Kraft: The Billionaire Friend of Netanyahu Pulling The Strings Behind the Macklemore/Ed Sheeran Blow Up
- Columbia Administered Fund Gives Big Money to Pro-Israel Groups
- No Tricks Zone
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
 Aletho News
