Madness

Philosophers-stone.info, 2020
By Richard Hugus | September 4, 2021
Looking at the last year and a half, it seems people have forgotten that evil is a significant and real force in our world. The term has religious connotations which secular societies would like to avoid, but we might do well to remember the old story of good versus evil. Evil people are not stupid. They know very well how to lie while appearing to be the soul of virtue. How could we doubt that the homely philanthropist Bill Gates, or the smiling Justin Trudeau, or Anthony Fauci with his Brooklyn accent, or the fatherly Joe Biden, could have anything but the best of intentions for us? Well, that’s how the game works. These people were chosen for their job because they are effective liars — one of the perks of selling one’s soul.
The “pandemic” is an attack on human freedom being conducted in increments. We started out with a three week quarantine to relieve supposedly overwhelmed hospitals and health care workers. Now, 18 months later, “there will be consequences” for people who refuse to get “vaccinated” says Trudeau in Canada. In Australia, people who have been under strict lockdown for months are now being told not to talk to each other or bring their children to playgrounds. Internment camps have been mentioned, and some say they are being built for those who refuse the jab. Children are being taken away from “unvaccinated” parents. If current jab rates are any indication, half the world’s population may end up in the camps, but that’s not an insanity too far for our would-be masters.
The globalists seem to care very much about getting something injected into us. They know better than we do what that is and what it is supposed to do — we can only speculate. Is it a slow-acting poison like glyphosate, promoted for many years by the same cast of characters? Is it a tool for chronic disease to keep the pharmaceutical industry and the medical establishment in business, like conventional vaccines? Is it a sterilizing agent to reduce the world population? Is it a code to genetically modify human beings? Is it the foundation of the circuitry that will connect us to 5G so that we can be completely surveilled? Or is it 6G, which will have enough bandwidth to bring us into the completely manufactured reality of The Matrix? We don’t know. But clearly there is a hidden agenda.
Some say the agenda of mass immunization is to institute “vaccine passports” to bring in totalitarian social control. But if this was the only goal, why would the clever technocrats, with all their careful planning, have chosen to inject people with a “vaccine” that doesn’t prevent or stop transmission of the alleged virus and is so harmful that not long after it was rolled out it started killing and injuring people in such large numbers that it couldn’t be covered up? The genius technocrats would have been much better off using a saline solution, then declare victory over the “pandemic” with no side effects. No, it seems that there is something important in the shot, and that the idea is to change all of humanity with it. If so, there will have been no crime more diabolical in the history of the world. While patriots thought their love of country and their guns would protect them, Klaus Schwab walked right in the front door and robbed them blind. Full-on psychological warfare of 2020 became biological warfare in 2021, and not a shot was fired. Our enemy were kindly medical personnel with syringes. Bullets don’t stop nano-scale mRNA.
In a 2017 TedX talk, Tal Zaks, the Israeli chief medical officer of Moderna, bragged about “hacking the software of life.” At this point, science revealed hubris perhaps not seen since the development of the atom bomb. We learn from Greek tragedy that there is always a reckoning when man meddles with forces he knows nothing about — in this case, the human genome. “Whom the gods would destroy, they first drive mad.” The same story goes back to the ancients.
As they go mad, the globalists are on a race to the bottom. They want to get as many people injected as they can before people realize the injections are not only not stopping disease, they are causing it. The masters of the universe have to suppress clear proof that safe conventional medicines effectively treat whatever the illness is called “covid” — how we hate the word! They want as many people as they can enrolled in their social credit system before people realize they’ve fallen into a trap. They want so much of the crime accomplished that it can no longer be reversed.
The race is desperate. New York Mayor deBlasio has declared that the 8 million people who live in the city be segregated according to their injection status, just like Jim Crow. Dictator Dan is re-enacting the Milgram experiment on the entire population of Australia. Emmanuel Macron wants the French to starve to death if they don’t get the “pass sanitaire.” Joe Biden has told employers outright to require the jab as a condition for work, since the federal government can’t legally do it. He has social media doing the same thing with censorship. Colleges and universities are making injection status a condition of enrollment, destroying careers and higher ducation. Variants of “the virus” are being hyped to create more fear, when there was never a valid test for the original. The dark ritual of masking is coming back. Children are again being muzzled in school, and our entire society is being humiliated as the most innocent and least protected among us — children — are publicly abused. The children themselves may come to see their parents and all adults as cowards for not protecting them. The “unvaccinated” are being vilified, with virtue signalers openly suggesting they deserve to be punished. All this is happening apace because so many people will be getting sick from the injections that there will be no way to cover it up. The globalists are acting more like mad scientists than confident leaders serene in their power . . . because they are mad.
We should understand that what the authorities pretend to be incompetence and unfortunate mistakes are actually intended goals. They haven’t destroyed economies or immiserated, injured, and killed thousands of people by mistake. They know what they’re doing, and they’re doing their best to cover it up. The next flu season may bring disaster, with large numbers of people getting sick because their immune systems have been seriously damaged by the jab. At that point, the plan may be so obvious that even the brainwashed will wake up.
It is up to us to put a stop to the mass injection program. If only one person changes their mind after seeing our protests, we will have made a difference. It is not too late.
Why all the fuss about Ivermectin?
By Brian C. Joondeph | American Thinker | September 3, 2021
First hydroxychloroquine, now ivermectin, is the hated deadly drug de jour, castigated by the medical establishment and regulatory authorities. Both drugs have been around for a long time as FDA-approved prescription medications. Yet now we are told they are as deadly as arsenic.
As a physician, I am certainly aware of ivermectin but don’t recall ever writing a prescription for it in my 30+ years’ medical career. Ivermectin is an anthelmintic, meaning it cures parasitic infections. In my world of ophthalmology, it is used on occasion for rare parasitic or worm infections in the eye.
Ivermectin was FDA approved in 1998 under the brand name Stromectol, produced by pharmaceutical giant Merck, approved for several parasitic infections. The product label described it as having a “unique mode of action,” which “leads to an increase in the permeability of the cell membrane to chloride ions.” This suggests that ivermectin acts as an ionophore, making cell membranes permeable to ions that enter the cell for therapeutic effect.
Ivermectin is one of several ionophores, others including hydroxychloroquine, quercetin, and resveratrol, the latter two available over the counter. These ionophores simply open a cellular door, allowing zinc to enter the cell, where it then interferes with viral replication, providing potential therapeutic benefit in viral and other infections.
This scientific paper reviews and references other studies demonstrating antibacterial, antiviral, and anticancer properties of ivermectin. This explains the interest in this drug as having potential use in treating COVID.
Does ivermectin work in COVID? I am not attempting to answer that question, instead looking at readily available information because this drug has been the focus of much recent media attention. For the benefit of any reader eager to report this article and author to the medical licensing boards for pushing misleading information, I am not offering medical advice or prescribing anything. Rather, I am only offering commentary on this newsworthy and controversial drug.
What’s newsworthy about ivermectin? A simple Google search of most medications describes uses and side effects. A similar search of ivermectin provides headlines of why it shouldn’t be taken and how dangerous it is.

YouTube screen grab
The Guardian describes ivermectin as horse medicine reminding readers considering taking the drug, “You are not a horse. You are not a cow”, saying it’s a medicine meant for farm animals. The FDA echoed that sentiment in a recent tweet, adding “Seriously, y’all. Stop it,” their word choice making it obvious who the tweet was directed to.
Perhaps the FDA didn’t realize that Barack and Michelle Obama often used the term “y’all” and that some might construe the FDA tweet as racist.
The FDA says ivermectin “can be dangerous and even lethal,” yet they approved it in 1998 and have not pulled it from the market despite it being “dangerous and lethal.” Any medication can be “dangerous and lethal” if misused. People have even overdosed on water.
It is true that ivermectin is also used in animals, as are many drugs approved for human use. This is a list of veterinary drugs with many familiar names of antibiotics, antihypertensives, and anesthetics commonly used by humans. Since these drugs are used in farm animals, should humans stop taking them? That seems a rather unscientific argument against ivermectin, especially coming from the FDA.
And healthcare professionals are not recommending or prescribing animal versions of ivermectin as there is an FDA-approved human formulation.
Does ivermectin work against COVID? That is the bigger question and worthy of investigation, rather than reminding people that they are not cows.
A study published several months ago in the American Journal of Therapeutics concluded,
Meta-analyses based on 18 randomized controlled treatment trials of ivermectin in COVID-19 have found large, statistically significant reductions in mortality, time to clinical recovery, and time to viral clearance. Furthermore, results from numerous controlled prophylaxis trials report significantly reduced risks of contracting COVID-19 with the regular use of ivermectin. Finally, the many examples of ivermectin distribution campaigns leading to rapid population-wide decreases in morbidity and mortality indicate that an oral agent effective in all phases of COVID-19 has been identified.
To my knowledge, these 18 studies have not been retracted, unlike previous studies critical of hydroxychloroquine which were ignominiously retracted by prestigious medical journals like The Lancet and the New England Journal of Medicine.
Yet the medical establishment refuses to even entertain the possibility of some benefit from ivermectin, castigating physicians who want to try it in their patients. 18 studies found benefit. Are they all wrong?
Podcaster Joe Rogan recently contracted COVID and recovered within days of taking a drug cocktail including ivermectin. Was it his drug cocktail, his fitness, or just good luck? Impossible to know but his experience will keep ivermectin in the news.
Highly unvaccinated India had a surge in COVID cases earlier this year which abruptly ended following the widespread use of ivermectin, over the objections and criticism of the WHO. In the one state, Tamil Nadu, that did not use ivermectin, cases tripled instead of dropping by 97 percent as in the rest of the country.
This is anecdotal and could have other explanations but the discovery of penicillin was also anecdotal and observational. Good science should investigate rather than ignore such observations.
The Japanese Medical Association recently endorsed ivermectin for COVID. The US CDC cautioned against it.
There is legal pushback as an Ohio judge ordered a hospital to treat a ventilated COVID patient with ivermectin. After a month on the ventilator, this patient is likely COVID free and ivermectin now will have no benefit, allowing the medical establishment to say “see I told you so” that it wouldn’t help.
By this point, active COVID infection is not the issue; instead, it is weaning off and recovery from long-term life support. The early hydroxychloroquine studies had the same flaw, treating patients too late in the disease course to provide or demonstrate benefit.
These drugs have been proposed for early outpatient treatment, not when patients are seriously ill and near death. Looking for treatment benefits in the wrong patient population will yield expected negative results.
Given how devastating COVID can be and how, despite high levels of vaccination in countries like the US, UK, and Israel, we are seeing surging cases and hospitalizations among the vaccinated, we should be pulling out all the stops in treating this virus.
Medical treatment involves balancing risks and benefits. When FDA-approved medications are used in appropriate doses for appropriate patients, prescribed by competent physicians, the risks tend to be low, and any benefit should be celebrated. Instead, the medical establishment, media, and regulatory authorities are taking the opposite approach. One has to wonder why.
Journal Nature: COVID lockdowns are key to begin ‘personal carbon allowances’
Restrictions on individuals… that were unthinkable only 1 year before’ have us ‘more prepared to accept tracking & limitations’ to ‘achieve a safer climate’
Nature Sustainability |
Authors argue COVID restrictions, smart meters & tracking apps can be used as a stepping stone for a personal carbon allowance:
Journal article urges for “the need for a low-carbon recovery from the COVID-19 crisis” by using “personal carbon allowances (PCAs).”
“A PCA scheme would entail all adults receiving an equal, tradable carbon allowance that reduces over time in line with national targets… encompassing individuals’ carbon emissions relating to travel, space heating, water heating and electricity.” …
“Allowances were envisioned to be deducted from the personal budget with every payment for transport fuel, home-heating fuels and electricity bills. People in shortage would be able to purchase additional units in the personal carbon market from those with excess to sell. New, more ambitious PCA proposals include economy-wide emissions, encompassing food, services and consumption-related carbon emissions, for example.”
In particular, during the COVID-19 pandemic, restrictions on individuals for the sake of public health, and forms of individual accountability and responsibility that were unthinkable only one year before, have been adopted by millions of people. People may be more prepared to accept the tracking and limitations related to PCAs to achieve a safer climate and the many other benefits (for example, reduced air pollution and improved public health) associated with addressing the climate crisis.Sustainable Development Goals (SDGs)
Other lessons that could be drawn relate to the public acceptance in some countries of additional surveillance and control in exchange for greater safety… Recent studies show how COVID-19 contact-tracing apps were successfully implemented with mandatory schemes in several East Asian countries, such as China, Taiwan and South Korea… Recent advances in smarter home and transport options make it possible to easily track and manage a large share of individuals’ emissions. Evidence from the roll-out of smart meters and informative displays can be used to design feedback that is highly effective in engaging individuals to reduce their energy-related emissions… In terms of implementation platforms, while in the 2000s carbon allowances were expected to be managed by a card, in the 2020s high ownership would make smartphones the preferred option for accounting and trading (while providing alternative options for the few without smartphones).
The State That Doesn’t Care If You Live Or Die

By Tom Woods | Principia Scientific | September 3, 2021
Ask the average person in whatever country you choose what his chances of hospitalization with or death from COVID are and the answers will shock you. Nearly everyone you speak to is completely uninformed.
Naturally it is impossible to make rational decisions amidst this degree of ignorance.
Now is as good a time as any for some perspective.
The survival rate for people in the 0-19 age group is 99.997 percent. For 20-29 it’s 99.986 percent. You can find all the figures in the graphic below.
The data come from a recent paper by Stanford’s Cathrine Axfors and John Ioannidis, “Infection fatality rate of COVID-19 in community-dwelling populations with emphasis on the elderly: An overview.” Here’s how it breaks down:

A person under 50 is therefore at greater risk of death from drowning, choking on food, sunstroke, or from a sharp object.
This is not to say that we’re not dealing with a nasty virus for some people who contract it. But do you think the average person has any idea that the numbers for survival are this high?
In the UK, the Daily Mail just published an article called, “Is it time to stop obsessing over Covid figures? Statistics reveal virus is NOT the biggest killer — with heart disease, dementia and cancer each claiming four times as many lives in an average week last month.”
“Even before the rollout of the vaccine,” the article notes, “fewer than one per cent of people who caught Covid died. Now, scientists say that figure is ten times smaller.”
They included this graphic, for perspective:

Much as I welcome this, it’s pretty rich for the British press (or indeed any press) to publish an article and a chart like that, though, scratching their heads as to why people are obsessed about COVID, when they themselves are directly responsible for the misinformation that brought about that obsession.
Remember when the Washington Post called Iowa the “state that doesn’t care if you live or die” when that state removed its COVID restrictions? That was seven months ago.
Here’s the chart. Think we’re going to hear any apologies, or any “gee, I guess I don’t understand this virus as well as I thought,” or…?

That’s enough perspective for one day.
No Animal Studies for the Vaccines
By Martin Armstrong | ArmstrongEconomics | September 2, 2021
I find it extremely unbelievable that nobody will investigate this entire scam for what it is. The people behind the vaccines should be dragged in to testify what is going on. Moderna has admitted it took them only 2 days to create the vaccine. In Texas, they are trying to launch a criminal investigation. The FDA is no longer trustworthy, for the normal time to get anything approved is 12 years. What has been released in less than one year with no animal studies? There has been NO TESTING to determine side effects on pregnancy, fertility, or lactation.
It is just stunning that we have politicians REFUSING to look at anything, probably because they are too busy counting their bribes. The White House said under NO condition would they ever fire Fauci, meaning under NO condition will they investigate anyone.
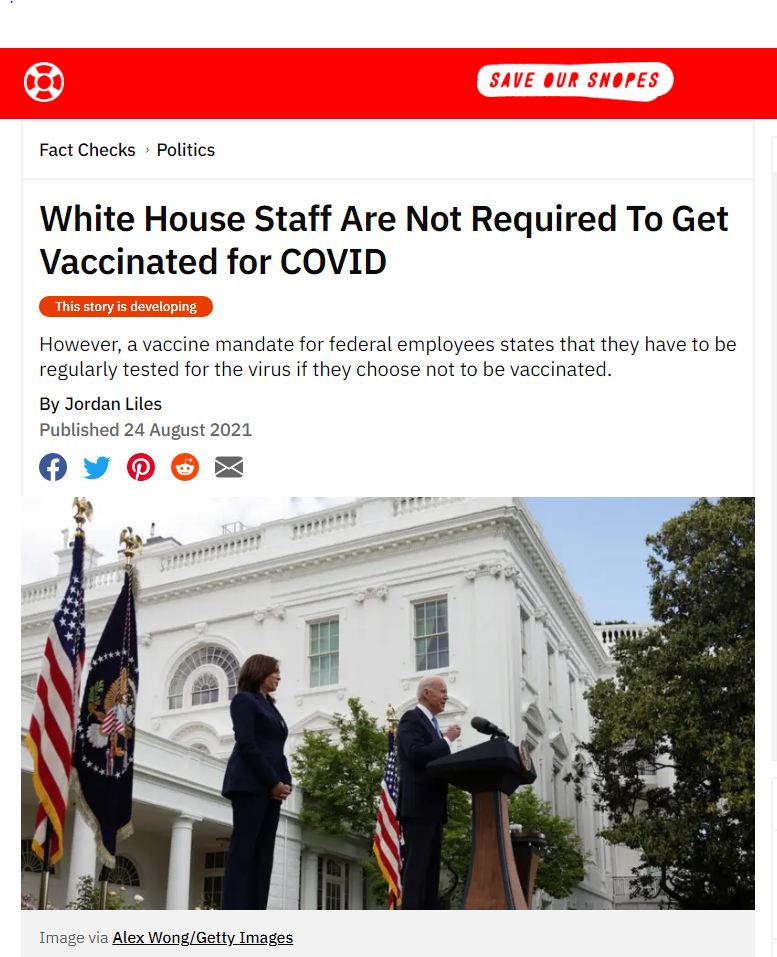
Meanwhile, even the notorious corrupt Snopes had to admit this is TRUE. Despite demanding everyone gets vaccinated, the White House said its own staff DOES NOT need to be vaccinated provided they are routinely checked. So why is the White House the entire exception? Even the military is demanding 100% compliance. Meanwhile, the White House has demanded everyone else receive vaccinations or lose their job.

The fact that they have skipped animal trials is very disturbing. When the government is part of the conspiracy against the public, we will NEVER know the truth about anything. Jack Dorsey has been especially protective of the narrative. Nobody is allowed to question the government no matter what.
Then there are studies revealing that natural immunity to COVID is 13 times better than the vaccines. They try to bury such studies, and they also try to ensure that they are not peer-reviewed in order to discredit them. The Science journalist Alex Berenson was permanently suspended from Twitter one day after his tweets that reported an Israeli study that making this finding that natural immunity from a prior Covid-19 infection is 13 times more effective than vaccines against the delta variant. Twitter is now acting against the very basis of free speech, which is threatening people’s lives. I would love to see Twitter taken down, for they are clearly now responsible for the deaths of many people from vaccine injuries.

To show that this is one giant cover-up, OSHA has instructed employers NOT TO REPORT vaccine injuries suffered by employees if they only “recommend” the shots. Many employers with more than 10 employees are required to keep a record of serious work-related injuries and illnesses. Nobody should volunteer to be vaccinated to satisfy an employer, for you will not be covered for any injury or loss of pay, and you could be fired for not showing up to work for a period of time. However, if employers mandate vaccines to work, then the vaccine injuries should become subject to reporting, lawsuits, and workman’s comp claims.
Ivermectin Metaanalysis
By Meryl Nass, MD | September 3, 2021
Tess Lawrie’s group’s metaanalysis of ivermectin research papers, published in June, has received a great deal of positive attention. It was, as expected, carefully done. The authors graded the quality of the papers they reviewed.
The abstract noted:
“Therapeutic Advances: Meta-analysis of 15 trials found that ivermectin reduced risk of death compared with no ivermectin (average risk ratio 0.38, 95% confidence interval 0.19–0.73; n 5 2438; I2 5 49%; moderate-certainty evidence)…” This means that using only evidence of moderately good quality (high quality is often hard to come by, especially using observational data), if 100 people sick enough with Covid to die are given ivermectin, only 38 will die, and 62% will be saved.
“Low-certainty evidence found that ivermectin prophylaxis reduced COVID-19 infection by an average 86% (95% confidence interval 79%–91%).”
More doctors are using the drug. More patients are hearing about it. I have been getting more calls from patients who want to know about it. The NY Times said pharmacists are filling 88,000 scripts a week now.
Covid death rates, compared to the number of cases diagnosed, are way down compared to 2020 and last winter. While the NYT says there are 100,000 Covid patients in hospital now, only 1,500 are dying daily, or 1.5%, a much lower percentage than previous waves.
This is probably due to lower virulence of current variants, some benefit from vaccination, less use of ventilators and more use fo effective therapeutics.
And so now the CDC is coming down hard and many pharmacist have decided to stop filling the scripts in the past week. More on this in my next post.
Top Misinformation Article Attributed to Chicago Tribune
By Dr. Joseph Mercola | September 2, 2021
According to Facebook’s content transparency report for the first quarter of 2021, released in mid-August 2021, the most popular article shared on the platform between January 2021 and March 2021 was about a 56-year-old Miami, Florida, obstetrician who died two weeks after his first Pfizer injection.1
The story initially ran in the South Florida Sun Sentinel 2 April 8, 2021, and was republished by the Chicago Tribune that same day.3 The doctor, Dr. Gregory Michael, received his first dose December 18, 2020.
Three days later, he developed small spots on his hands and feet, which prompted him to go to the emergency room, where they found he had an abnormally low blood count. Platelets stop bleeding by clotting, and when platelets drop too low, internal bleeding can occur, resulting in what looks like blood blisters on the skin.
Michael remained in intensive care for two weeks, but no matter what they did, his platelet count refused to budge. During the night of January 3, 2021, he died of a massive stroke. According to the coroner, the COVID injection could not be ruled out as a contributing or causative factor.
In a Facebook post, Michael’s widow stated he’d been “very healthy” and that he’d been a COVID-19 vaccine advocate. His death caused her to question the safety of the shot, however.
“I believe that people should be aware that side effects can happen, that the vaccine is not good for everyone and in this case destroyed a beautiful life, a perfect family and has affected so many people in this community.” she wrote. “Please do not let his death be in vain please save more lives my making this information news.”4
Even Viral Content Has Minor Reach
According to The New York Times,5 Facebook held off on publishing the first-quarter report for fear the findings might “look bad for the company.” Executives decided they wanted to make some “key fixes to the system” before releasing it. That’s why it wasn’t published until August.
Interestingly, the report reveals that even when something goes viral, the total number of views is still a tiny fraction of the overall content. Even the biggest accounts make up but a small portion of overall content views. Combined, the top 20 accounts with the most views during the first quarter — which included UNICEF, The Dodo and LADbible — accounted for only 1.18% of all U.S. content views.
As noted in the report, this “shows that, even though it may seem like a page or post has extensive reach on the platform, that isn’t the case when measured against the total amount of content available on the platform.”
Facebook Calls Out CCDH for Manufacturing ‘Faulty Narrative’
As you may know, an obscure one-man organization funded by dark money called the Center for Countering Digital Hate (CCDH) has published several reports, including “The Anti-Vaxx Playbook,”6 “The Disinformation Dozen”7 and “Disinformation Dozen: The Sequel,”8 in which the founder, Imran Ahmed — an unregistered foreign agent — claims to have identified the top most influential “anti-vaxxers” in the U.S.
In a completely unexpected turn of events, Facebook is now calling out the CCDH for having manufactured a faulty narrative without evidence against the 12 individuals targeted in its reports (myself included).9
This is important, seeing how the CCDH reports have been the primary “reference” source of authority used by media and government officials to smear, threaten and infringe on American citizens’ right to free speech.
The U.S. Department of Homeland Security even lists promulgating “false narratives” around COVID-19 as a top national security threat, which basically puts a “domestic terrorist” target on the backs of those of us who have been identified by the CCDH as the most prolific “superspreaders” of COVID misinformation.
As reported by GreenMed Info :10
“Google now shows an astounding 84,700 search results for CCDH’s defamatory phrase ‘disinformation dozen. ’Amazingly, this includes 16,000 news stories within the international press, approximately 100% of which are word-for-word amplifications of CCDH’s claims/defamatory statements and reported uncritically as fact.
In addition, the Surgeon General Vivek Murthy, the White House Press Secretary Jen Psaki, and president Biden all used CCDH’s report as the sole source for their own defamatory accusations, reaching a dangerous rhetorical climax on July 20th when Biden stated that these 12 individuals are literally “killing people” [by spreading misinformation].”
No Evidence to Support ‘Misinfo Superspreader’ Claim
In an August 18, 2021, Facebook report, Monika Bickert, vice president of Facebook content policy, sets the record straight, and in the process, demolishes the CCDH’s claims:11
“In recent weeks, there has been a debate about whether the global problem of COVID-19 vaccine misinformation can be solved simply by removing 12 people from social media platforms. People who have advanced this narrative contend that these 12 people are responsible for 73% of online vaccine misinformation on Facebook. There isn’t any evidence to support this claim …
That said, any amount of COVID-19 vaccine misinformation that violates our policies is too much by our standards — and we have removed over three dozen Pages, groups and Facebook or Instagram accounts linked to these 12 people, including at least one linked to each of the 12 people, for violating our policies.
We have also imposed penalties on nearly two dozen additional Pages, groups or accounts linked to these 12 people, like moving their posts lower in News Feed so fewer people see them or not recommending them to others. We’ve applied penalties to some of their website domains as well so any posts including their website content are moved lower in News Feed.
The remaining accounts associated with these individuals are not posting content that breaks our rules, have only posted a small amount of violating content, which we’ve removed, or are simply inactive.
In fact, these 12 people are responsible for about just 0.05% of all views of vaccine-related content on Facebook. This includes all vaccine-related posts they’ve shared, whether true or false, as well as URLs associated with these people.”
It’s worth restating the key point in this quote: Combined, the top 12 individuals and organizations identified by the CCDH as being responsible for a whopping 73% of vaccine misinformation on Facebook, are in fact only responsible for 0.05% of vaccine-related content — 1,460 times lower than the CCDH’s outrageous claim. That’s no small discrepancy.
CCDH Claims Blasted as Unjustified and Biased
Bickert goes on to refer directly to the CCDH report “The Disinformation Dozen,”12 stating:
“The report13 upon which the faulty narrative is based analyzed only a narrow set of 483 pieces of content over six weeks from only 30 groups, some of which are as small as 2,500 users.
They are in no way representative of the hundreds of millions of posts that people have shared about COVID-19 vaccines in the past months on Facebook.
Further, there is no explanation for how the organization behind the report identified the content they describe as ‘anti-vax’ or how they chose the 30 groups they included in their analysis. There is no justification for their claim that their data constitute a ‘representative sample’ of the content shared across our apps.”
CCDH Meets Definition of ‘Hateful Extremists’
Ironically, while the CCDH claims to “counter hate” online, and Ahmed sits on the Steering Committee of the U.K. Commission on Countering Extremism, CCDH itself actually meets the Commission’s definition of hateful extremists.14 In the 2019 Commission document, “Challenging Hateful Extremism,” the term is defined as:15
“Behaviours that can incite and amplify hate, or engage in persistent hatred, or equivocate about and make the moral case for violence; And that draw on hateful, hostile or supremacist beliefs directed at an out-group who are perceived as a threat to the wellbeing, survival or success of an in-group; And that cause, or are likely to cause, harm to individuals, communities or wider society.”
In addition, in the forward of the report, lead commissioner Sara Khan notes that “Hateful extremists seek to restrict individual liberties and curtail the fundamental freedoms that define our country.”
All of these definitions and clarifications of what hateful extremism is fit the CCDH to a T. Ahmed manufactured data to create a false narrative that 12 individuals pose a threat to the well-being and survival of the whole world, and then used that narrative to incite hate against us and curtail our freedom of speech.
Who Fact Checks the Fact Checkers?
In related news, the self-appointed arbiter of factual truths, NewsGuard, has had to backpedal in recent months and issue dozens of corrections to “fact checks” in which they’ve labeled the Wuhan lab leak theory as a debunked conspiracy theory with no basis in fact.
Since the beginning of the COVID pandemic, NewsGuard has wrongly down-rated 225 websites for articles mentioning the lab leak theory.16 In reality, there’s far more evidence to support the lab leak theory than any other theory, but it took over a year before the weight of this evidence became too obvious for the media to ignore.
NewsGuard’s erroneous fact checks were recently highlighted in an August 11, 2021, report by the American Institute for Economic Research (AIER).17
AIER decided to take a closer look at NewsGuard after receiving a request for comments on a NewsGuard fact check article regarding AIER and the Great Barrington Declaration — a statement written by public health experts from Harvard, Stanford and Oxford that calls on government to implement focused protection rather than lockdowns and self-isolation. AIERS investigation found that:18
“… NewsGuard falls far short of the very same criteria for accuracy and transparency that it claims to apply to other websites. Most of the company’s fact checkers lack basic qualifications in the scientific and social-scientific fields that they purport to arbitrate.
NewsGuard’s own track record of commentary — particularly on the Covid-19 pandemic — reveals a pattern of unreliable and misleading claims that required subsequent corrections, and analysis that regularly conflates fact with opinion journalism in rendering a judgement on a website’s content.
Furthermore, the company’s own practices fall far short of the transparency and disclosure standards it regularly applies to other websites … NewsGuard’s staff primarily evaluates scientific claims by appealing to the authority of public figures who they designate as ‘experts’ on the subject in question.
Their approach generally avoids direct examination of the evidence surrounding contested claims, and instead cherry-picks a figure to treat as an authoritative final word … many of their preferred authorities are political officeholders rather than persons trained in scientific or social-scientific methods.
By selectively curating cherry-picked political authorities rather than evaluating evidence directly, NewsGuard’s approach to fact-checking effectively sidesteps the scientific method. This strategy is rendered even more problematic by the general lack of scientific expertise within NewsGuard’s team of writers.
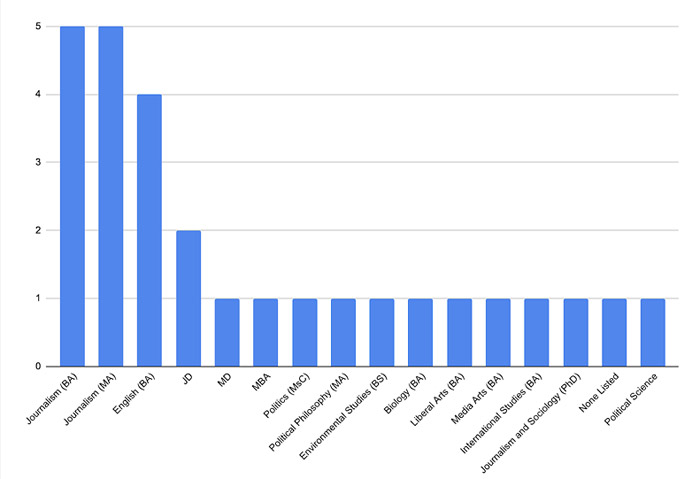
We examined the educational credentials, including the highest degree listed, for 28 publicly identified staff members on NewsGuard’s website. The company’s staff page reveals shockingly little expertise in either the hard sciences such as medicine or social sciences such as public policy, economics, and related fields …
Most NewsGuard articles on Covid-19 topics and policies are written by [NewsGuard Deputy Editor for Health, John] Gregory, whose only identified qualification is a bachelor’s degree in Media Arts … Gregory would not qualify as an expert in most of the fields he is responsible for fact-checking …
Of course, non-experts have every right to offer opinions on scientific and social-scientific matters. Whether or not they should be taken seriously as fact checkers or act as arbiters of scientific disputes is another question entirely.”
NewsGuard Staff by Field and Highest Degree Attained
NewsGuard Apologizes for Erroneous Fact Checks
After being confronted about its erroneous fact checks on the lab leak theory, NewsGuard offered the following apology in a statement sent to AIER:19
“NewsGuard either mischaracterized the sites’ claims about the lab leak theory, referred to the lab leak as a ‘conspiracy theory,’ or wrongly grouped together unproven claims about the lab leak with the separate, false claim that the COVID-19 virus was man-made without explaining that one claim was unsubstantiated, and the other was false.
NewsGuard apologizes for these errors. We have made the appropriate correction on each of the 21 labels.”
AIER commented on the apology:20
“Gregory and his colleagues appear to have simply decided that their own premature dismissal of the lab leak hypothesis equated to ‘fact’ and proceeded to penalize other sites not for factual errors, but rather for diverging from NewsGuard’s own editorial position on the same subject.
When this position turned out to be mistaken, NewsGuard pivoted to remove the errors — albeit in non-transparent ways that downplay the significance or pervasiveness of their mistake.”
NewsGuard Fails to Fulfill Its Own Credibility Criteria
In their report, AIER goes on to apply the criteria NewsGuard uses to evaluate a website’s credibility to NewsGuard itself. It’s ranking? A paltry 36.25 out of 100. According to AIER:21
“This website fails to adhere to several basic journalistic standards, and should be used with extreme caution as a source for verifying the reliability of the websites it purports to rate …
When we see fact checkers like NewsGuard, who not only fail to uphold their high-sounding principles but even publicly encourage working with the government to suppress speech, we should raise red flags.”
The NewsGuard ratings are meant to influence the reader, instructing them to disregard content with cautionary colors and cautions. That it would serve as the thought police of the technocratic establishment that seeks to silence dissent and bury information that doesn’t help move the Great Reset agenda forward is no surprise.
Especially considering its primary startup capital came from Publicis Groupe,22 a PR group that represents most of Big Pharma, including vaccine makers, and Big Tech. NewsGuard is also backed by Microsoft23 and Google.
The Publicis Groupe has been manipulating what people think about commercial products for nearly a century. Over that century, this advertising and communications firm bought or partnered with targeted advertising avenues, beginning with newspapers, followed by radio, TV, cinema and the internet.
With revenue avenues secured, Publicis’ clients and partners built a global presence that dominated the advertising world. Be it tobacco or sugar, Publicis Groupe found a way to promote and strengthen big industries. Publicis was recently sued24 for its deadly and illegal marketing of Purdue Pharma’s opioid products.
When you consider that Publicis describes its business model approach as putting clients and their needs and objectives at the center of all they do so their clients can “win and grow,” it’s easy to see what’s driving NewsGuard.
Overall, NewsGuard is just another big business aimed at keeping the chemical, drug and food industries, as well as mainstream media, intact by discrediting and eliminating unwanted competitors and analysts who empower you with information that runs counter to any given industry’s agenda.
If you’re as disturbed by censorship as I am, be sure to contact your local library today to find out if they’re one of the more than 700 libraries using NewsGuard. If they are, then ask them if they’re aware of NewsGuard’s censorship of truthful news that is now encroaching on scientific freedom and threatening the very roots of our democracy.
If your local library is using NewsGuard, it would be helpful to start a campaign to get it removed. Contact your neighbors and let them know what is happening so they can kick out this public health threat. Likewise, whenever you see someone referencing reports by the CCDH, call them out on it.
Sources and References
- 1 USA Today August 23, 2021
- 2 Sun Sentinel April 8, 2021
- 3 Facebook Heidi Neckelmann
- 4 Chicago Tribune April 8, 2021
- 5 New York Times August 20, 2021 (Archived)
- 6 The Anti-Vaxx Playbook (PDF)
- 7, 12, 13 CCDH, The Disinformation Dozen
- 8 Misinformation Dozen: The Sequel
- 9, 11 Facebook August 18, 2021
- 10 GreenMed Info August 19, 2021
- 14 Greenmed Info March 25, 2021
- 15 Challenging Hateful Extremism 2019
- 16, 17, 18, 19, 20, 21 AIER August 11, 2021
- 22 Washington Post March 3, 2018
- 23 axios.com August 23, 2018, NewsGuard Launches First Product With Help From Microsoft
- 24 Reuters May 6, 2021
Named, shamed and fined – the maskless marauders

By Frederick Edward | TCW Defending Freedom | September 2, 2021
MAGISTRATES have been busy enforcing the laws of Covid-land, with more than 20 miscreants in Northamptonshire fined last week for failing to abide by the rules. They are named and shamed in the Northamptonshire Telegraph, the digital equivalent of the village stocks.
There are a few things to glean from the list of those convicted. We have a small insight, firstly, into the demographic shifts that are happening in the small towns of England such as Corby, Kettering and Wellingborough, with M Jatczak, K Marjani and P Blaga making an appearance.
The relative youth of those who found themselves in court is telling. J Ayre, 22, went to an outdoor gathering of more than two souls, for which he must pay £248. C Hulse, also 22, went to an indoor gathering of more than two. She has to pay £344.
While we do not know the circumstances of these individuals, it is a reminder of the price the youth have been made to pay throughout the last 18 months or so. Stuck in small accommodation or at home with their parents, they have suffered a disproportionate impact from restriction on movement. Moreover, the fines are not insignificant for those unlikely to have much disposable income.
Those caught refusing to abide by Covid regulations include:
U Aurica, 51, fined £344 for being in a corner shop without a mask;
C Oxlade, 21, found maskless in Budgens, as was E McIlreavy, 29, at Asda. Both fined £344;
L Stachura, 29, fined £344 for not wearing a face mask in a pizza takeaway.
R Gilderleft, 26, ‘left his home . . . without reasonable excuse’. He must pay £344.
The local paper website does not make it clear, but the prosecutions are likely to have been under the Coronavirus Act and Health Protection Regulations. Both pieces of legislation were passed in March 2020, the former without a vote in the Commons and the latter presented to the House only after it had come into force.
This is just a snapshot of cases involving Covid-19 rules. The Crown Prosecution Service reported in May 2021 – more than one year into the pandemic – that more than 1,800 had been brought to court, though a high proportion were subsequently identified as incorrectly charged. Indeed, between March 2020 and March 2021, all charges brought under the Coronavirus Act were incorrect, with not a single prosecution resulting from this large expenditure of police and court time.
Around 80 per cent of prosecutions brought under the Health Protection (Coronavirus, Restrictions) Regulations were correctly charged: it is under this legislation, which includes restrictions on leaving home, social gatherings and the enforcement of mask-wearing, that our Northamptonshire rebels were probably charged.
That a man living in England can be sentenced for leaving his own home is a sign of how far down the path of illiberalism we have strayed: never before in our history have we accepted such perverse rules, a fact made all the more unconscionable by their disproportionality.
What concerns me doubly is that they are enforced with such officiousness and subsequently reported so eagerly by an unquestioning and uncritical press. The Northamptonshire Telegraph says sanctimoniously: ‘The defendants were the latest to be convicted after violating emergency rules – which were designed to slow the spread of coronavirus – between January and April. Many of them were punished after failing to stick to the laws in January or February, at a time when many thousands died as the virus spiraled [sic] out of control.’
In any society which abandons the precepts of freedom, there will be a large group of people who willingly become the enforcers of the new regime. Intoxicated with power, they thrive amid a sea of petty regulations.
Naturally, one will not find names such as Matt Hancock of Neil Ferguson on the lists of those convicted. While the man on the street has the book thrown at him for daring to venture into a supermarket without a mask or seeing some friends, those in the right places and with the right connections can carry out their assignations without repercussion.
We can be convicted and fined for going to a takeaway without a mask, while our elites philander and jet around the world.
How much longer will we tolerate these glaring double standards?
Victoria premier extends lockdown, again, as Aussie police granted power to covertly hack citizens’ phones & alter data

Police arrest a protester during an anti-lockdown rally in Melbourne on August 21, 2021 as the city experiences its sixth lockdown © AFP / William West
RT | September 1, 2021
Victoria’s premier has announced that a statewide lockdown will remain in place until most residents are vaccinated, just days after Australia adopted new legislation giving sweeping surveillance and spy powers to police.
Draconian measures covering the entire southeast Australian state will only start to be eased once 70% of the population receives at least one dose of the Covid vaccine, Premier Dan Andrews decreed on Wednesday. The government said it hoped to reach this target on or around September 23.
In a written statement, Andrews claimed that lifting restrictions would “overrun” the state’s healthcare system. With a population of around 6.6 million, Victoria currently has less than 60 Covid hospitalizations.
The entire state has been under strict lockdown for nearly a month. After shutting down non-essential activity in Melbourne, Andrews decided to extend restrictions to the entire state on August 5, citing the alleged detection of Covid-19 in wastewater 236km (147 miles) from the city. He was later forced to admit that the sewage in question had actually tested negative for the virus. Nonetheless, the statewide lockdown, which was only supposed to last seven days, has remained in place.
Currently, Victorians are not allowed to venture more than five kilometers (3.1 miles) from their homes – and only for “essential” activities. Andrews promised to increase the travel radius to 10km once the state’s vaccination benchmark is met.
The new conditions for easing lockdown were revealed a week after Australia passed a controversial bill giving police the ability to secretly seize and alter internet accounts.
Known as the Surveillance Legislation Amendment (Identify and Disrupt) bill, the legislation allows the Australian Federal Police (AFP) to take over, and modify or delete, the accounts of cybercriminal suspects.
Although authorities claim that the law will help crack down on pedophiles, terrorists and drug traffickers, many on social media expressed concern that the extensive powers were further evidence of Australia sliding into authoritarianism.
The Australian state has recorded 822 Covid-linked deaths since March 2020. To put this figure in perspective, more than 950 Victorians have died from suicide over the same period.
The state’s draconian restrictions have been blamed for fueling a mental health crisis, especially among the young. While only one Australian aged 19 or younger has died with Covid-19, eight teenage girls have taken their own lives in Victoria in the first seven months of the year.
Supporting Doctors’ Rights To Speak, Free From Censorship
doctors4covidethics.org

Dr. Paul Oosterhuis is an Australian anaesthetist with over thirty years experience, including in critical care and resuscitation, who urgently needs your support.
He is facing a hearing by the Medical Board of NSW for posting information on social media regarding COVID-19. His posts related to early treatment and prophylaxis, PCR tests, and risk-benefit calculations regarding COVID-19 vaccination and lockdowns (scroll down for details). His hearing is on September 3rd. Please help him by signing and sharing this petition.
We are practicing doctors and allied health professionals and/or scientists and academics and/or members of the public and/or represent professional organisations. We support the right of Dr Oosterhuis, and that of all doctors, to offer informed medical opinions on COVID-19 and to discuss the available evidence on COVID-19 interventions.
As doctors we too have advised and continue to advise patients and the general public about the medical management of COVID-19 disease and vaccination on the basis of good science. As members of the public we reserve the right to receive honest information, opinion and advice from our doctors, free from government interference.
From Dr Oosterhuis:
Dear colleagues and concerned citizens,
Thank you for taking the time to read this petition.
My name is Dr Paul Oosterhuis. I am an anaesthetist from Australia. I have been called before the NSW Medical Board for a hearing on September 3rd 2021 following anonymous complaints about my social media posts on Facebook regarding COVID-19. I have been advised by the Medical Council that:
“The Medical Council of NSW received two anonymous notifications regarding your activity on social media.
Due to the concerns outlined in the notifications the Council has resolved to convene proceedings under section 150 of the Health Practitioner Regulation National Law (NSW) to consider whether any action is required for the protection of the health and safety of the public or in the public interest.”
Ahead of the hearing I am seeking signatures from my medical and scientific colleagues and members of the public to help me defend my own and all doctors’ rights to offer our informed medical opinions, share our expertise, and engage in open discussion regarding COVID-19.
I am a Sydney University trained medical graduate. I undertook my internship and residency at Prince of Wales Hospital in Sydney, followed by postgraduate training in Anaesthesia at The Royal Prince Alfred Hospital. I have more than 30 years of practice, the first 20 years involving hands-on critical care and resuscitation, and the last 10-plus years as a senior Visiting Medical Officer working in the Sydney Local Health District.
In the social media posts for which I face a Medical Board hearing, I discussed issues such as early treatment and prophylaxis against COVID-19, evidence for government measures such as lockdowns and PCR tests, and evidence regarding risk-benefit analyses of COVID-19 vaccines.
For example:
“I wish you could just add EARLY TREATMENT and drug PROPHYLAXIS …..Tell everyone to take Vit D, Zinc, and EARLY TREATMENT with IVM/ HCQ as evidence based medicine alternatives.”
I provided a link to a presentation by Dr Paul Marik on prophylaxis in support of the post, highlighting a chart of vitamin D versus risk of COVID from Dr Marik’s presentation, to illuminate the low hanging fruit of prophylaxis.
In other posts I questioned the evidence base for the government’s policies of lockdowns and mask mandates, and pointed out that there is evidence of vaccines having low effectiveness and real risks and harms (which are being suppressed), along with harms from the totalitarian lockdowns causing massive damage society-wide.
The risk of Antibody Dependent enhancement of disease, predicted by Dr Geert Vanden Bossche, driven by immune escape from the selective evolutionary pressure of vaccinating with a non sterilising agent is a real and present danger and needs to be discussed. The danger to millions is distressing to me, and discussing that danger is, I believe, unarguably in the public interest.
Early in 2020, I was active in criticising my medical administrators for failure to prepare for an outbreak such as COVID-19 when it was apparent that PPE was being rationed (P95’s were in short supply). I urged my colleagues to perform quantitative fit testing of our available P95 masks in early 2020 during which we found a surprising number of staff failed quantitative fit testing with the hospital issued PPE. This was something I had hypothesised after looking at the number of healthcare workers in Northern Italy catching the disease.
I withdrew from clinical practice last year out of concerns about the increasing incompetence of the health administrators and the rapidly reduced autonomy of doctors to just be able to be a doctor.
Over the last 18 months I have been increasingly concerned about the misinformation and censorship creeping into science and medicine. Fellow physicians were saving lives with early treatment and medication/supplement approaches to prevention but it was THIS that was attacked and censored! People like Dr Paul Marik, Dr Pierre Kory of the FLCCC Alliance, Dr Robert Malone, Dr Geert Vanden Bossche, Dr Michael Yeadon, Dr Vlad Zelenko, Dr Chris Martensen, Dr Eric Weinstein and others are making credible and serious warnings about the gene therapy being coerced upon our populations.
Censoring their work, and the research of experts like Dr Tess Lawrie, Dr Peter McCullough, Dr Sucharit Bhakdi and America’s Frontline Doctors is dangerous.
The Medical Board of NSW is now using intimidation, threatening doctors like myself, who share data which questions the official narrative. I don’t believe that censorship is compatible with good science and good medicine, and I believe that it needs to stop now, in the name of public health and public interest.
I would be very grateful if you could help to support me in my effort to inform as many as possible about their true health choices. My hearing is in a matter of days.
While I wish I did not have to defend my right to speak truthfully as a doctor, the song and video below captures my attitude to fighting for that right. I hope you enjoy it.
With my most sincere thanks,
Dr Paul Oosterhuis
Australia
See also:
NZ Doctors Speaking Out with Science (petition)
The Science Is Clear – The Case Against Mandating Vaccines: One Executive’s POV
SOTT | August 31, 2021
SOTT Editors: We are publishing below, with permission, an email from a top executive at an American company whose clients include 100 of the Fortune 500 companies. The email was sent in reply to another executive asking for the writer’s thoughts on whether he plans to be vaccinated himself or mandate it for his employees as a requirement for returning to the office. All names and company references have been redacted for privacy reasons.
Unlike most of us who are worried about being on the receiving end of vaccine mandates by employers, this executive also has to worry about pressure from other executives and investors to mandate it on others. Few such business leaders are actively fighting for the rights, dignity, peace, and financial security of their employees. This exec is currently the only voice in his company opposing the madness.
Email to the executive:
Hey [REDACTED] – are you giving any thoughts to getting vaccinated with all this Delta variant stuff going on? We’ve been having management committee discussions here about mandatory vaccinations to be able to come in to the office. We have office support people coming in most days that are not vaccinated and some of those with kids don’t want to come in when they are in the office or invite clients into the office for meetings. Just curious as to how you are approaching it. Thx, [REDACTED]
The executive’s reply:
From: [REDACTED]
Date: Fri, Aug 27, 2021 at 9:56 PM
Subject: MY POV on Mandating Employee Vaccinations
To: [REDACTED]
I appreciate you reaching out. What follows is admittedly lengthy (though I do provide my “summary POV” a couple paragraphs down before I dive into supporting detail). I tried to be succinct, but practically speaking your question for me was akin to “hey, so what’s your take on management?” The analogy here being I’m passionate about both subjects so it was hard to choose between sending back a brief 2-minute POV, or filling this email with enough content fit for a university level course. I didn’t know what you had an appetite for, so I just simply did my best to try and be helpful (and heck, even had some fun while I was at it…).
My framework for this entire POV: in the famous words of W. Edwards Deming, “In God we trust. All others must bring data.” As I hope you’ve come to know me by now, I care more deeply about facts & morals than I do ideology or identity politics (for the latter I just don’t give a shit). If you give me a good reason to do something, I am 100% all over it. But if you give me either faulty reasoning or an unethical ultimatum, I simply cannot get on board out of a moral obligation to do what’s right.
So to answer your questions with that sole framework in mind, here’s my summary POV:
(#1) I still have no plans to get vaccinated anytime in the foreseeable future (unless something radically changes the risk equation), given:
(a) The virus at present poses de minimis risk for me personally (and virtually zero risk to any healthy child (a reference to your initial inquiry)); and
(b) Because these vaccines carry –> confirmed low/moderate short term — inferred moderate medium term — and expected high long-term health risk for what could be [though yet unknown] a majority of individuals who get the jab
(#2) I remain vehemently opposed to vaccine mandates for this specific virus (primarily on the basis of (i) 1b above, (ii) the medical literature, which strongly suggests that these vaccines will prolong this pandemic indefinitely through never-ending variants, and thus/therefore (iii) on moral grounds, as, if (i) and (ii) are true, then any decision to proceed with mandates would be nothing short of a descent by the West towards fascism**, the likes of which hasn’t reared its ugly head since the early 20th century. Finally, at a distant, distant second, I am against these mandates from a logistical perspective*.
*E.g., how will you account for boosters (i.e., will those who were vaccinated too far in the past e.g., January and thus have substantially waning transmission protection also be excluded from the office)? What about those who got a different jab (e.g., AstraZeneca, Sputnik, CoronaVac, etc.), each of which has varying levels of effectiveness (and varying levels of effectiveness reduction over time) against different variants? How will you handle those that already had COVID-19 (and therefore (a) have even higher immunity than the vaccinated, and (b) who face higher health risks if they get vaccinated post- natural infection)? What will you do with the immunocompromised (folks with organ transplants, lung problems or cancer patients) who got the vaccine but have low viable antibodies because they require evermore booster shots? What will you do when future variants require different jabs? I could go on, but I trust you get the point. My real question for you is, will you be responsible for coordinating monthly/quarterly management meetings to update & maintain these ever-changing mandate policies covering ever-growing future use cases?
**And if you think I’m exaggerating, look no further than NY State Assembly Bill A416, which proposes forcibly putting carriers of COVID-19 who do not conform to the state’s medical guidelines into something akin to internment camps, where they will be forced into a treatment deemed appropriate by the state and detained indefinitely until they comply. Imagine a U.S. legislative policy so bad, that even Russia Today was able to shit all over it as being far too draconian. And it’s not just the state of NY, but the CDC as well.
===================
Last comments before I dive into supporting details
To not lose sight of being pragmatic as it pertains to your inquiry, I want to point out that at this juncture even a discussion about vaccine mandates is mostly moot.
We already know (confirmed) that those who are vaccinated/infected carry as much viral load as the unvaccinated. Which, coupled with waning transmission prevention efficacy means for all practical intents & purposes those vaccinated and those unvaccinated pose similar risks to one another.
And this is notwithstanding even more cutting edge research (not even yet published i.e. currently pre-print in The Lancet), which suggests those vaccinated carry significantly (upwards of 200x) more viral load than the unvaccinated (which would, if peer-reviewed, flip the risk equation on its head even further in that those vaccinated would pose far greater risk to one another than those unvaccinated). (And it is worth noting that this development would be consistent with what has been found with other vaccines — in this 2017 study, for example, it was assessed that those who were vaccinated for influenza shed 6.3x as much virus as those who are unvaccinated. Crazy stuff.)
All of this is to say, despite the nationwide pushes you’re seeing for private & federal workplace vaccination mandates (which may have made at least some sense much earlier on), such mandates are unfortunately no longer effective models at this stage, unsupported by what we now understand via the latest science. Instead, if you really want to make a difference in improving workplace safety at this juncture, I would suggest implementing either the 1st, or both, of the following policies:
(1) Everyone at the company must perform a daily (pre-commute) self-assessment health survey, whereby all individuals must confirm they are not exhibiting any of the known symptoms of COVID-19 (i.e., if you can’t smell, have fever/chills, shortness of breath, etc., you can’t come in to the office, period), without any pressure from management to respond they are symptom-free.
(2) (Optional) everyone, irrespective of vaccination status, must get tested weekly for COVID-19, such testing to be reimbursed by the company. If you test positive, you aren’t allowed to come in until you test negative.
You asked how we’re handling it, and I can tell you that we’re doing the first one at [my company], and I would recommend utilizing the second one for any in-person company events. That’s it. No mandates. Anything beyond that will lead you into a logistical nightmare (at best), foster a false sense of security as it isn’t effective (worse), and in my humble opinion, is purely unethical (worst of all, which I’d like to think is a decent enough reason not to do something) at this stage.
So anyways, all of the above is the summary of my current POV. What follows below is/are the supporting details for the conclusions I reached in my summary POV 1(a), 1(b), and 2(i) above, if you’re interested in the data.
Always happy to chat/update further as the saga continues ✌
best, [REDACTED]
P.S. if you’re going to skip Parts 1 & 2 below*, then no worries… I get it, I probably wrote far more than you were looking for. But if indeed you do skip them, try to make it to the ‘Closing Thoughts’ section way down below — I’ve sourced a nifty chart down there that might give your colleagues pause in their ongoing discussions about mandates before they consider the unvaccinated to be idiots for whom behavioral mandates are the only appropriate solution.
*Though I highly recommend Part 1 (where it says “TWO OTHER THINGS TO CONSIDER” (then scroll to find #2)) as this contains a suggestion for how to naturally protect yourself from COVID-19.
===================
PART 1: RISK OF COVID-19 DEATH —> DE MINIMIS FOR ME
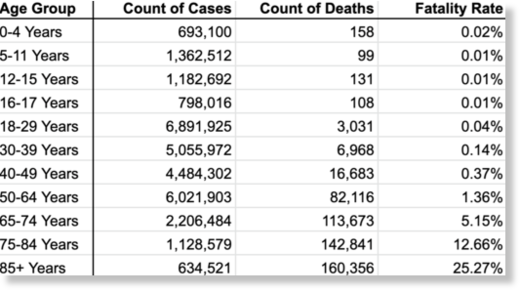
First I’ll address why I do not view COVID-19 as dangerous for me personally: from the CDC’s own data, available here, you can see current the Count of Cases and Count of Deaths by age ->
(Though before I go further, pardon me for abstaining from a lengthy discussion on the reliability of data from an organization that even Dr. Deborah Birx herself — (an individual who received a Meritorious Service Medal from the U.S. Department of Defense in 1991 and a Medal of Excellence from the CDC in 1994) — was quoted as saying she didn’t trust a single word from. Hmm, I wonder why she didn’t “trust” the data, could it be because they were —> overinflating “COVID-19 deaths”? <—… I digress.)
Anyways, according to the CDC, being 32, my “risk” stands at 0.14% (purely averages speaking, irrespective of the analysis below); a “starting statistic” you could call it.
The immediate issue with this data, unfortunately, is we’re only able to count cases with confirmed COVID-19 PCR (or other) test results, undercounting materially true case counts to date. As you might imagine, those asymptomatic do not test themselves regularly or out of nowhere. I mean, personally speaking, I am obviously not testing myself on any basis on any cadence — I’d only get tested if I had reason to. Thus is the reason, that the CDC already stated well early on in this pandemic that true case counts were “likely” to be upwards of 10x higher than we have documented (which they concluded based on widespread antibody testing).
Deaths in the U.S., on the other hand, are religiously tested for COVID-19, capturing the vast majority (if not nearly all) deaths, where a COVID-19 infection was present.
Using these two bits of information from the CDC, we can adjust for a “truer” baseline risk. Now, while I could exercise the luxury of taking on more than a 10x spread (because those younger tend to be more asymptomatic), I’ll be conservative just for the sake of it and just use the “10x average” figure. And so, a true starting statistic for me isn’t 0.14%, but a markedly lower 0.014%.
Next, we can use Exhibit B, taken right from the CDC website:
For… 5% of… [COVID-19] deaths, COVID-19 was the only cause mentioned on the death certificate. For deaths with conditions or causes in addition to COVID-19, on average, there were 4.0 additional conditions or causes per death.
Again, this is nothing new and has been known since very early in the pandemic, as you can see from this study for example listing the leading comorbidities as measured in NY as early as April 2020:

And herein lies my second issue with folks who preach to me that vaccines are necessary for my survival (the first being my initial lowly baseline risk).
Knock on wood, but I have no non- COVID-19 induced comorbidities — zero. My takeaway is just that: for someone like me, COVID-19 is mostly a virus known to exacerbate serious pre-existing conditions to the point of overwhelming the system definitively.
Put another way, imagine a motorcycle rider trying to assess their risk of death from riding (i.e., catching COVID-19). They see a study which puts the risk of death for those motorcycle riders who were (1) drunk (2) doing a wheelie on the highway (3) during a rainstorm, and (4) while texting with a friend (i.e., analogous to four comorbidities). It would be flawed reasoning for a rider who doesn’t do any of those things to put themselves in the same risk category as those who do. So while no one is saying motorcycles aren’t dangerous — they certainly are — they’re nowhere even in the vicinity as dangerous as riding while doing all the other things. Likewise, neither should a healthy teenager dwell on their COVID-19 risk with the same fervor as a 100 year-old morbidly obese individual with terminal cancer.
Okay, let’s revisit my personal risk again. First, I will ignore the 5% “no comorbidities” statistic above, because out of fairness I want to account for likely COVID-19 induced comorbidities like Respiratory Failure, Sepsis, etc. as well as possible ones like Renal Failure, Cardiac Arrest, and the like. So, let me simply reduce my risk not by 95%, but 57% (conservatively even rounded down further to a clean 50%), which removes just 1 non- COVID-19 induced comorbidity for my age group.
And just like that, my adjusted risk is downgraded to 0.0069% annually (annually, because it’s only once a year — after which time a better-than-vaccination natural immunity kicks in for that season).
So what really is 0.0069%, you might ask? After all, we humans aren’t terribly good with numbers like that. To help you put it in perspective, consider that according to the National Highway Traffic Safety Administration, your (or my) risk of dying from a freak car accident in any given year, is 1 in 5,407 or 0.018%.
Let that sink in: based on what we know today, I personally am 268% more likely to die in a car accident tomorrow (or any day this year) than COVID-19. But do you really think that in pre-pandemic times, the “1 in 5,407” statistic kept me locked up inside my house? You think even today (in the middle of a pandemic) that figure stops me from taking a leisurely drive to grab ice cream with my nephews? or catching a movie with my brother? or — God forbid!! — hanging out with and actually talking with my friends? No!, and it never could. Because life, my friend, is about dancing in the summer rain, not cowering in fear of getting struck by lightning. But hey, maybe that’s just me…
In any case, I want to come back to your comment about concerns your colleagues have regarding young children. When we look at the statistics available (table above), the results are even more stark: for kids aged 5-11, their odds of a fatal COVID-19 infection are 1 in 137,000 when you factor in asymptomatic cases. And again, we’re talking about a risk inclusive of those with comorbidities. For kids 5-11 who are perfectly healthy, you can consider their risk nil. Okay, well obviously it could never be actually zero, because we both know sometimes kids also fall off a bike and kill themselves — that’s life. But you don’t exactly see people running around freaking out over bicycles all day long, do you? Which is ironic as hell now that we’re on the subject, considering almost exactly the number of kids have died from bicycles as from COVID-19 in the same time frame.
So when I hear about folks taking their kids for a bike ride on the weekend (how awful), or worse!, maniacally driving their kids for ice cream (putting those precious kids at 5,091% (51x) the risk of death as COVID-19), but then trembling at the thought of walking into an office the following Monday because there’s an unvaccinated person there, so they feel the need to demand forcing medical decisions on those people (like getting jabs with vaccines made by companies whose rap sheets (Pfizer, J&J) would satisfy essay requirements at most colleges, approved by an organization that finds safety issues in 1/3 of its drugs post-approval), I come to the simple conclusion that common sense has left the building — it’s mass hysteria.
Alright, enough beating the completely de minimis personal risk dead horse because the point is clear. But let me add two more small things before getting to the dangers of the vaccine:
TWO OTHER THINGS TO CONSIDER
The section above looked at the whole thing purely from a mathematical risk perspective with neither proactive measures in mind, nor accounting for simple and effective (though IMO criminally suppressed) treatment options available to thwart COVID-19 risk even further.
(1) First, on the treatment side. Look, I know there was the whole “orange man (Trump) bad, the FDA disagrees” political BULLSHIT thing going on. Like I said above, I do not give a shit about the political angle of any of this. I require data, and the data could not be more ironclad on the subject matter. I will simply leave these two links here, and avoid another 5 pages in this POV on why IMO this is being criminally suppressed by federal agencies:
First, Ivermectin (links to the studies: (Link A & Link B)). Summary table as follows:
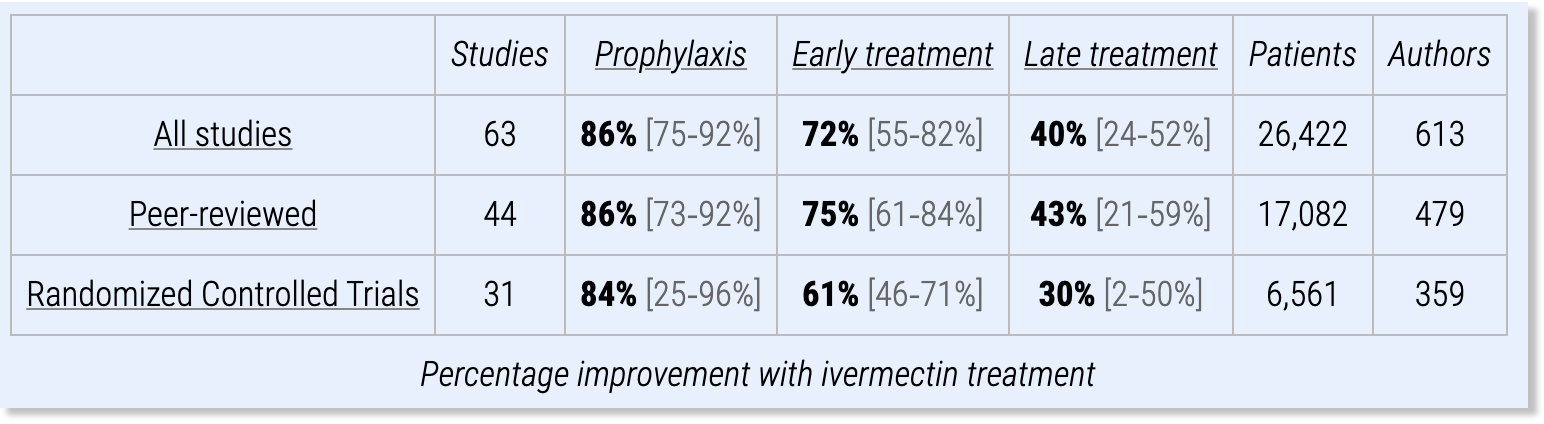
Second, Hydroxychloroquine (link to the studies). Summary table as follows:
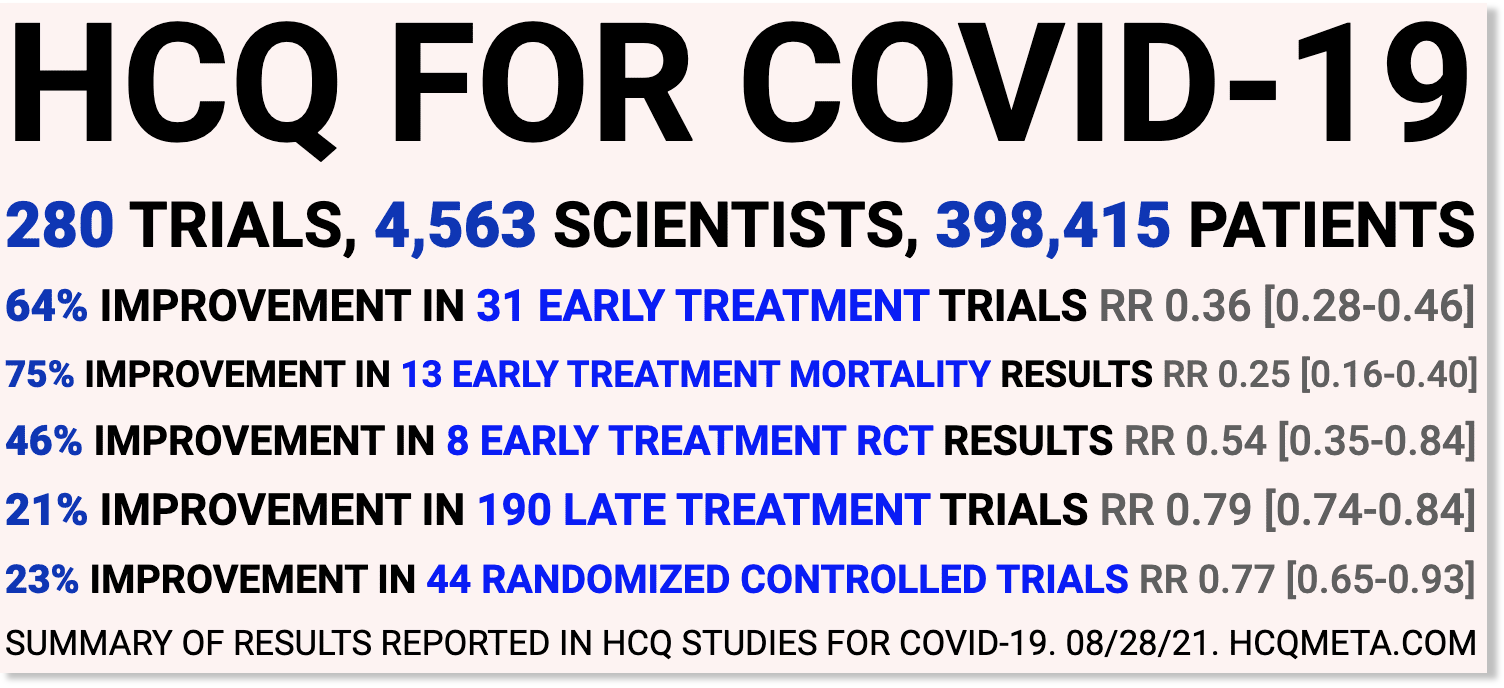
By the way, it is worth noting I have a friend right now who has COVID-19. He has felt like shit for the past week. I sent him the studies, and he bought Ivermectin 3 days ago without a prescription from a local store I pointed him to. After a week of feeling like shit, it took him less than a day to get close to symptom free. But hey, I am not a doctor, and “your mileage may vary.” There are a dozen other treatments in addition to the ones above that aren’t getting approved for mass application, either. Go figure.. I could send you the studies if you want, but anyways let’s move on.
(2) As it pertains to the proactive side — okay, sit tight because I’m going to perform a holy miracle here and give you one of several simple things you can do to essentially ensure never needing to worry about COVID-19 again. Not for you, not for the kids, and not even for the neighbor’s dog. Ready? Okay drumroll please… . Did you catch that? If you didn’t, I’ll decipher it for you. It’s your new friend Vitamin D.
If you’d like dozens more studies on this subject, let me know, but start with this good summary I just found for you here — it’s worth a full read, but two pretty charts from the link sum it up:
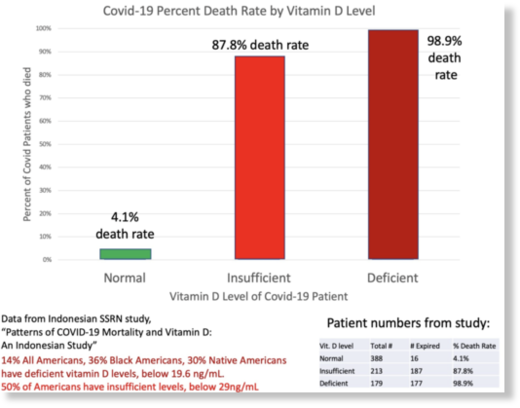
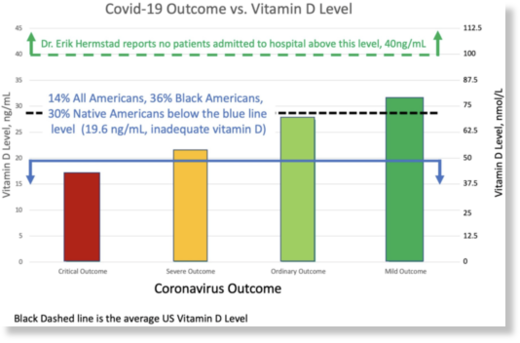
The first study is striking all on its own and worth internalizing, but unfortunately it did group an entire category called “normal” into a single bucket. FYI “normal” is what the medical world considers to be ~20ng/mL. But that’s all it is as a level: normal… but far from what we want, which is excellent.
That’s where the second study becomes helpful. It puts the explosive nature of the findings into real perspective: at levels of 25ng/mL in the study, no severe or critical hospitalized outcomes were observed. While at levels of 40ng/mL or greater, there were not even hospitalizations.
Now personally, I regard it as nothing less than a crime against humanity that neither the WHO nor CDC are PUSHING these (and dozens other peer-reviewed studies on the subject) onto the forefront of our collective media screens. But as for the reason, I must digress, because again I could go down a long and nasty rabbit hole about perverted incentives in the system in terms of why you likely haven’t seen them.
In any case, here’s what is just so awesome for me… remember when we concluded I had a higher risk of crashing & dying from my trip to the local ice cream shop than from COVID-19? Well, it just got a WHOLE lot better, because my Vitamin D levels happen to be considerably well above 40ng/mL. Which means we need to be honest with ourselves and admit that I effectively have a ZERO clinically observed risk of death from COVID-19. I mean shit…. at this point really the only way I can die of COVID-19 is by having it and then getting into a car accident. Then sure, I will die “with COVID-19” (and, as you’ll recall from the link above, they would count it!).
So my advice is as follows: get your dang sunshine first thing in the morning. Do not lockdown. In fact, I’d argue it’s what caused so many deaths. People were heavily Vitamin D deficient from sitting at home all day, and it literally increased their risk of death instead of reducing it. And what the CDC did in this regard was at best negligently or at worst intentionally, criminal, and I have nothing but disdain for the way they went about that. Don’t even get me started on the youth suicides it led to, the increases in domestic violence, increases in drug overdoses, infanticide, denial of healthcare, and let’s not dismiss the whammy of the sheer economic devastation to jobs and small businesses the world over, the bleak economic prognosis for the poorest (how convenient), and the future impact of staggering U.S. debt right here at home. All caused by the incompetence or criminality of the CDC and WHO.
Honestly — my personal advice if you want to stop worrying about COVID-19 for the rest of your life (if you still even are), would be to follow the Dan Miller protocol. Each of his bits of advice is like an extra layer of bulletproof glass on top of Kevlar against COVID-19. And remind your colleagues, too, to stop relying on the “American way” of taking a pill to solve all their problems and blaming the unvaccinated. That is not only completely debunked now as I’ve demonstrated throughout, but it is weak morally. It’s high time we all do the hard self-work of making ourselves physically resilient, and stop feebly making outward demands of others to inject into their bodies vaccines that are only now being tested, in vivo, on large numbers of human beings.
Speaking of which… perfect segway.
===================
(VERY BRIEFLY) PART 2: LONG-TERM RISKS OF [SPECIFICALLY] THE COVID-19 VACCINE –> HIGH
As I’m sure you’ll remember, a while back I mentioned I would send you a thorough, synthesized summary outlining the dangers of the COVID-19 vaccines and how the risks they carry far outweigh the risks of the virus itself. Unfortunately, I am not even a fraction of the way through the hundred plus pages of medical literature showing that conclusion — I’m still working through it. I absolutely feel terrible for not having lived up to my promise, though I’m sure you can appreciate the sheer herculean nature of synthesizing 7 months’ of research involving almost a thousand individual pieces of data, and weeks’ worth of video testimonials by researchers, all into something “succinct and digestible”, all the while working on [my company] in the middle of it all.
In any case, it would be disingenuous of me if I didn’t at least provide a sneak peak of a random assortment of links I had handy for why I will not get the vaccine (aside from the fact that COVID-19 poses no risk to me, per the first section):
- Imperfect Vaccination Can Enhance the Transmission of Highly Virulent Pathogens (bad for me, terrible for society; moral obligation not to partake in this)
- Is a Coronavirus Vaccine a Ticking Time Bomb? (Spoiler alert: likely is)
- A Pathologist Summary of What These Jabs do to the Brain & Other Organs
- Might COVID Injections Reduce Lifespan?
- MIT & International Journal of Vaccine Theory, Practice and Research: Worse Than the Disease? Reviewing Some Possible Unintended Consequences of the mRNA Vaccines Against COVID-19
- How COVID-19 Vaccine Can Destroy Your Immune System
- The Inanity of RNA Vaccines For COVID-19
- New Report Sheds Light on Vaccine Doomsday Cult (sketchy website, but well explained content. I suppose even a broken clock can be right twice a day…)
- Children 50 TIMES More Likely to Die from Covid Vaccine Than From Virus (from the former CSO of Pfizer)
- Pfizer vaccine in Israel: Mortality rate ‘hundreds of times greater in vaccinated young people’
- Are COVID shots fueling more dangerous mutations?
- Less than a third of delta variant deaths are in the unvaccinated (not really an article regarding vaccine dangers, but more so inefficacy)
- +1,000 additional articles, papers, studies, you name it that I could send anyone that wants the full dump of ’em (unsynthesized, of course)
Some bonus links in your spare time that caught my eye in just the past week:
- Fun Quick Video: Mt. Vernon, IN School Board Meeting (though he got a couple things wrong, some points are good food for thought)
- Podcast: The High Wire — A Sea of Lies (in depth discussion about perverse incentives driving bad decisions by the CDC (particularly the second half of the video))
- Podcast: Objective:Health – Study on the Adverse Effects of the Pfizer Vaccine (in which the presenters discuss a paper by the same name).
- Short & Sweet: Why non-lethal pressure on the virus is bad (versus natural immunity) -> Part 1 | Part 2
- +100 more videos and podcasts on the subject to anyone who asks (unsynthesized, of course)
===================
CLOSING THOUGHTS
If you made it this far and checked out even any of the content, kudos. Most folks here in the Northeast stop listening to me once I say “hey, there’s something not right here in this data” or “I’m not too worried about COVID-19 personally”. They think I’m a nut. Now, if you’ve made it this far and checked out most of the content, then I already know you’re starting to wonder if you’re losing your mind, because boy do I have a club pass with your name on it, if you’d like one.
Alas, contrary to popular belief it’s far from a nut club, despite how strong the external pressure is these days to try to make it out to be the case. Rather, It’s a club filled with precisely the very people who we’re supposed to be listening to as a society:
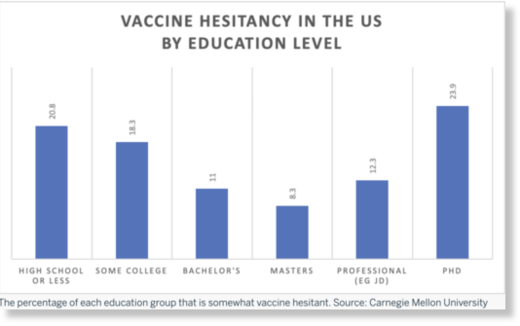
Source: https://www.medrxiv.org/content/10.1101/2021.07.20.21260795v1.full.pdf
AKA: a twisted rendition of the Dunning-Kruger effect in action
The CDC would have you believing it is just the crazy and uneducated who are most wary of their (and the FDA/WHO’s) conclusions — you know, it’s all the rednecks down south! And they’re right, it is the uneducated (left of the chart). But it is disingenuous for them to try and ignore on the nightly news research like this out of Carnegie Mellon suggesting the biggest group of those most vaccine-hesitant happen to be the smartest folks in the world — the ones I’ve certainly not been ignoring, despite their being shamed, cancelled off of social media, and publicly silenced.
Put another way, I would only posit the simple question of when in the history of the world have you ever had thousands of scientists, doctors, and researchers, some of the brightest minds* in their fields around the world sounding an alarm, and the official response be to label them all as batshit crazy and prevent them from speaking? Hint. Personally, I can’t support it. A free society must allow all open discussion without ridicule well before we dare discuss collectively forcing medical decisions on people using actual threats against their autonomy. We’re too far past that Vietnam-level of government lying bullshit that results in unholy suffering for society for this barbaric nonsense to continue, and it’s time for this country to start acting like we learned something about the importance of asking questions. I simply cannot place any trust in the idea I’m not being lied to until every scientist worth their salt has had an opportunity to speak up freely, and the nature of their concerns investigated transparently. And neither should anyone else.
*Such a fun fact it is that among this ocean of scientist voices being smeared & erased from history are (1) the guy who helped invent mRNA vaccine technology, and (2) the former Chief Scientific Officer (CSO) of Pfizer (who held that role for 16 years and focused on respiratory illnesses), both of whom are saying we have to stop vaccinations at once for those who aren’t at actual high-risk with COVID, because for everyone else they’re not only toxic & dangerous but will be the very cause of this never ending pandemic. Now I don’t know about you, but I neither invented mRNA technology nor worked at Pfizer for 16 years as CSO, but if I did, I’d sure prefer the American people heard my concerns, you know, sans the childish smear tactics part. Until then, I will not — cannot — accept any mandates on moral grounds.
And so there you have it. My opinion on mandatory vaccinations at this stage: if this were the Bubonic Plague, I’d be the first in line to get the shot. Same for Polio, Tetanus, and a whole lotta other great vaccines. But for COVID-19? Let’s just say I wouldn’t even know what to tell Saint Peter at the Pearly Gates to apologize sufficiently if I — knowing what I know now — supported a mandate. Come to think of it, there’s a quote that comes to mind here that I think is a nice way to wrap up this write-up, and commemorate those who continue to protect the rights of society:
‘The hottest places in Hell are reserved for those, who in time of moral crisis, preserve their neutrality.’ ~ unknown
========
DISCLAIMER –> OBLIGATORY
I obviously have to say this before I sign off.
At the end of the day, I’m not a doctor, I do not have an MD, a Ph.D., or any other useful acronym. All I am is an individual who values truth above hysteria & ideology. I will go wherever the truth points me to without regard for what “side” that puts me on. If it’s a contrarian side, then shit I guess I’m going to have to get in some fights. If I’m on the side of the majority, I guess I’ll rest easy. But wherever it is, I’m willing to go there, and as I said in my opening statement and reiterated to the group — I will always remain open to thoughtful and productive dialogue and my POV on every topic is subject to change through lifelong reflection. All I ask for these days is for those who disagree with me to either have the sincerity to work with me using the scientific method to get the facts on this subject, or if they have no interest in that, to let me do it alone without the constant coercion, which is how I’m sure the folks in your office who are unvaccinated, feel.
Anyways, for the actual disclaimer part: we all have to make our own decisions, do our own research (though I’m always happy to keep sending stuff I come across), and take our own risks. Freak accidents can happen, and just like I wouldn’t want to be responsible for a car accident that happens if you decide to go to a particular ice cream shop I recommend, it is the same for anything I’ve sent above and anything you or anyone you may share any of the information with do as a result of it. Always seek and follow professional, accredited advice! <– the disclaimer part.
Anyone who sees the vaccine as having more benefit than risk, should absolutely take it. I agree 100% with an 85 year-old with five comorbidities getting the jab — shit if that was me, I’d be getting quadruple jabbed walking around with a gas mask. No really, I would. Because for them the virus is actually very dangerous. And I’ve recommended it for some that I know personally would benefit from the vaccine because they are at high risk. But that’s where it ends. And not a single, inch, further.
Featured Video

The Truth About the Trump Shootings with Ken Silva
or go to
Aletho News Archives – Video-Images
From the Archives
Trans ‘milk’ as good as the real thing – NHS
RT | February 18, 2024
The drug-induced nipple secretions of trans women are as good as mothers’ breast milk for babies, the University of Sussex Hospitals NHS Trust claimed in a letter to campaigners made public in a report by British think tank the Policy Exchange on Sunday.
The healthcare trust’s medical director, Rachel James, argued that the off-label prescription drug cocktail men transitioning to female take in order to produce milk was “similar to the natural hormones which encourage lactation to develop when the baby is newly born.”
“The evidence which is available demonstrates that the milk is comparable to that produced following the birth of a baby,” James wrote in the letter, sent to Children of Transitioners last August.
Biological men who wish to lactate must first take hormones to grow milk glands and then take high doses of either domperidone or metoclopramide to stimulate milk production. Neither drug is approved for this use, though they are occasionally prescribed off-label to biological women who have trouble lactating.
However, domperidone’s own manufacturer, Janssen, warns patients the drug “may cause unwanted side effects affecting the heart in a breastfed baby” and “should be used during breastfeeding only if your physician considers this clearly necessary.” … continue
Blog Roll
 Aletho News
- Seyed M. Marandi: U.S. Strike Imminent – Toward Total War in the Middle East
- Russia Voted Under Fire. Washington Is Loading the Tankers.
- 12 Things Your Oncologist Was Trained Not to Tell You
- Anthrax Attacks Paved Way for COVID-Era ‘Junk Drugs and Vaccines’
- How Real Is the Impact of Western Sanctions on Israel?
- France, You Are Guilty: How Paris Turned Western Sahara into the Maghreb’s Powder Keg
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- Your Milk Is Not the Problem
- The Truth About the Trump Shootings with Ken Silva
- ARE PATIENTS BEING PROPERLY INFORMED ABOUT OZEMPIC?
- If Americans Knew
- Salah Sarsour’s Legal Team Says DHS Has Not Met Its Burden to Prove He Is Deportable
- An analysis of tax forms by The Intercept show Kraft’s charity and LLC have donated to Friends of the IDF and AIPAC’s super PAC.
- Israeli attacks kill four Palestinians in Gaza – Daily Update
- Inside Gaza’s death trap of collapsing, bombed-out buildings
- The everyday items Israel bans from Gaza every day
- Inside the siege, the ruined buildings of Gaza – Daily Update
- Debunking The Claim That Macklemore Has A “History Of Antisemitism”
- CPJ demands release of arrested Palestinian-US journalist near Bethlehem
- Robert Kraft: The Billionaire Friend of Netanyahu Pulling The Strings Behind the Macklemore/Ed Sheeran Blow Up
- Columbia Administered Fund Gives Big Money to Pro-Israel Groups
- No Tricks Zone
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
 Aletho News
