GP with the courage to say No to vaccines
By Sally Beck | The Conservative Woman | June 28, 2021
A GP who resigned his ‘job for life’ as a partner with a Hampshire practice because of his doubts about Covid-19 vaccines has been suspended by NHS England for questioning coronavirus protocol.
Dr Sam White received a letter on Friday informing him that he was suspended with immediate effect, which stops him practising as a doctor within the NHS. On Saturday he was telephoned by a senior clinical adviser to NHS England, who condescendingly called him ‘poppet’.
In a soothing manner, she told him she was concerned for his welfare. ‘I’m worried about whether you’re well,’ she said, the undercurrent of the conversation being the suggestion that Dr White is suffering mental health issues.
In fact, Dr White has never felt saner even though he has pressed the nuclear button on his professional life. The two main reasons for detonation involved the Covid-19 vaccine roll out, an initiative that he fundamentally disagrees with because vaccines are not needed if there’s an effective treatment; and the mandatory wearing of masks, a theme introduced by psychologists not scientists, which Stanford University research shows is nothing more than theatre.
He said: ‘It’s hard to go against the grain like this, but when I found out they were going to start testing the vaccine on children, I couldn’t sleep. I knew it didn’t matter what the results of the trials were, negative or positive, they would begin injecting children regardless. A healthy child is more likely to be struck by lightning than die of Covid. They don’t need an experimental vaccine that has no proven benefit.
‘The risks from the vaccine are completely unknown because it’s barely been tested. But reactions are beginning to come to light. Adolescent boys seem to be developing myocarditis – heart inflammation – which can permanently damage the heart. The risks could be potentially devastating compared with them contracting Covid and surviving it.
‘I began waking up in a cold sweat. I was so anxious that I ended up calling in sick. That was back in March, and I never went back.’ He now fears this anxiety will be used to question his mental health.
The second dig in his ribs came when someone in the Twitter community posted in the wake of apocalyptic stories about the vaccine-injured: ‘What are all the doctors doing about this crime against humanity?’ It struck a chord, and it was then he knew he had to reveal how he’d taken a stand.
Dr White explained in a heartfelt resignation video that went viral after he posted it to Twitter on Friday June 4. ‘I had to go because of all the lies. They’re so vast it’s been impossible to stomach.
‘I became a doctor because I wanted to help people and make a difference.
‘Since the pandemic was announced, I’ve had my hands tied behind my back. There are safe treatments that I have researched and there is good science behind them, proven treatments, but we’re not allowed to use them.’
During our interview, Dr White explained that the ‘vaccine cure’ was worse than the ‘disease’. He said: ‘After the vaccine programme began, I started to see more people with vaccine damage than with Covid.
‘I effectively left my practice three months after the rollout but before I left, I saw eight vaccine injured patients, they felt feverish and short of breath post-vaccination, and one was hospitalised in his 50s. He’d had Covid-19 so he didn’t need the vaccine, but no one had checked his medical notes. When I got his discharge letter back from A&E, it just said Covid-19, not that he’d had a reaction to the injection.’
The lack of information available about the vaccine worried him, as did his contract to be complicit in potentially causing harm. He said: ‘A lot of doctors don’t know that this is not a vaccine, but genetic manipulation.
‘When you sign up to become a GP you sign a contract with the NHS who tell you what to do. Essentially you can’t refuse to do what you’re told. I was hoping in December that the General Practitioners’ Committee (GPC), our governing body, would say, “Hang on, we haven’t got enough data here, we need to hold off doing this”, but that didn’t happen.’
Now, he wonders how many of his elderly Covid patients would not have died if he’d been allowed to prescribe ivermectin, the medication recommended by Dr Tess Lawrie from British Ivermectin Recommendation Development (BIRD), a group of health researchers who say research shows it can cure and prevent Covid.
On Wednesday afternoon last week, Dr White had a call from a woman claiming to be a doctor from NHS England who expressed concerns that he’d discussed drugs such as the malaria prevention medicine hydroxychloroquine which research says could increase Covid survival rates by 200 per cent. She also did not want him to mention the steroid inhaler budesonide, talked about by a doctor in the US.
A clean getaway was too much to hope for, especially as he’d made his feelings known so publicly. Since that video flew around the world it’s had close to a million views, and Dr White has paid dearly for his outspoken departure. His bank account has been hacked and a five-figure sum removed. He has no idea if it’s connected but according to the International Women’s Media Foundation (IWMF) it’s a ‘thing’: thieving people’s identities and stealing their money is a tactic used to intimidate the outspoken.
It has affected his personal relationships and is a divisive subject within his family, who all have their roots in healthcare.
As painful as the response from his family has been, the outpouring of support from strangers on social media has been phenomenal. He said: ‘Before I posted the video, I had 100 followers on Instagram which increased to 37.5k after my video. I had 11 followers on Twitter and now I have over 8k, but Instagram are taking down my posts. I put up a list of vitamins I take for boosting immunity. I didn’t even mention Covid, and they labelled it: “Covid-19 misinformation. False treatments. WARNING”.’
Dr White, 41, is not a naïve rookie. He qualified in 2004, worked as a GP for 11 years and was invited to become a partner in the Hampshire practice where he’d worked as a popular locum in February 2020. He’s worked in A&E, and he helped to run a palliative care unit for a while.
Initially, he turned down their offer of a partnership because he said: ‘Being a GP is a mill, you’re seeing 40 patients a day, a third of your day is spent doing paperwork, a lot of it is meaningless. It’s what we call tick-box medicine. What I felt was that I was, if I can be frank with you, a bitch for Big Pharma.
‘If you take someone coming in with newly diagnosed type 2 diabetes, the agenda is to get them on a drug for the diabetes, get them on a different drug for their blood pressure, it’s not about reversing type 2 diabetes which you can do by changing their diet.’
Since he walked away from general practice, he feels lighter and is excited for the future. Dr White is now focusing on functional medicine, from which he is not suspended – a biology-based approach to healthcare that identifies and addresses the root cause of disease, for example poor diet and lifestyle.
He wants to cure people, not just control their symptoms with drugs with side effects that can potentially harm.
The vaccines, and the Armageddon he, and many other doctors and scientists, fear they could cause, are never far from his thoughts though. He has this advice for people undecided about whether to have a Covid vaccination or not: ‘Please don’t have this because you think they will let you go on holiday. Your ability to travel should not be impeded for a virus with a survival rate of 99.7 per cent. It makes no sense.’
Fauci and the Biden Admin are purposely deceiving us about the ‘Delta variant’ threat
By Jordan Schachtel | June 24, 2021
Prominent actors within the U.S. government have been lying to the American people about COVID-19 for 18 months and counting, and their latest behavior shows that the individuals in charge of U.S. Government Science have no intention of stopping the charade anytime soon. Over time, their lies have evolved to become so common and so reckless to the point that someone with even the most rudimentary understanding of viruses can instantly debunk the lies. The latest “Delta variant” paranoia peddling has put their incompetence, deliberate spreading of falsehoods, and perpetual gaslighting of their own citizens on display for the world to see.
The Biden Administration, through lifelong government bureaucrat Anthony Fauci, is making a hard push to fear monger about the supposed dangers posed by the “Delta variant” of the virus that causes COVID-19.
A video posted from the White House account made the rounds Thursday morning, stating:
“Here’s the deal: The Delta variant is more contagious, it’s deadlier, and it’s spreading quickly around the world – leaving young, unvaccinated people more vulnerable than ever. Please, get vaccinated if you haven’t already. Let’s head off this strain before it’s too late.”
Fauci has been on a media tear this week hyping up the threat of the Delta variant.
Sometimes it’s easy to reflexively dismiss these warnings of doom and gloom as total nonsense, especially when they are in fact total, bald-faced nonsense.
(Check out this video from Ivor Cummins breaking down how the Delta variant, previously referred to as the Indian variant, is nothing more than a “political scariant.”)
First of all, it goes against all understanding of 101 concepts for a virus to mutate to become both more contagious and more deadly. If a virus becomes more contagious, it spreads faster but does not kill off its host. If a virus becomes more deadly, it doesn’t spread as fast because it has taken out its host. In fact, the best evidence we have on the Delta variant shows that it is probably less deadly than previous mutations. And it’s always good to remember that we’re talking about a disease that sports an original recovery rate well over 99%.
Second, the idea that human intervention can “head off” a strain is an idea straight out of the “COVID Zero” (the idea that you can eliminate the virus from this earth) pseudoscience playbook. Fauci and the gang are by no means brilliant minds, but they are well aware that they cannot eliminate a virus from circulation. This makes it obvious that there are several ulterior motives in play, none of which have anything to do with our health.
Outside of academic models (we all know how well those held up in the past with lockdowns, masks, etc), there is no hard evidence anywhere in the world that this Delta variant is any more or less dangerous than any other mutation of the virus. In fact, the statistics on this variant shows no particular reason for alarm. Yet the government is — let me know if this sounds familiar — baselessly making stuff up about a virus based on absolutely zero real world data.
Since the beginning of COVID Mania, the government has never been on the side of science, evidence, and data. From the infamous Gates-funded panic models and fraudulent Chinese government “science” that encouraged the world to lock down indefinitely, to the absurd mannequin “studies” about the efficacy of masks, this latest Delta variant scaremongering has once again put their lies on display for the world to see. Given the almost two years of immunity building related to the virus, the threat posed by COVID-19 at this point in time is virtually nonexistent. There never was a legitimate reason for a single restriction on our liberties, and today, the “delta variant” argument to curb our rights and transform our society is more baseless than ever before.
Re-Evaluating Mask Mandates – Part I: Science Gives Way to the “Talisman”
By Masha Krylova | C2C Journal | June 13, 2021
The health of my patient will be my first consideration; I will not use my medical knowledge to violate human rights and civil liberties, even under threat.
—World Medical Association: Declaration of Geneva, 2006
Where all men think alike, no one thinks very much.
—Walter Lippmann, 1937
We all remember when it was natural to strike up a conversation with a stranger on a street, in a mall or in a café. Sharing a smile would often start the enjoyable process from which mutual trust and understanding could flow. Seeing other people’s open faces and hearing them laugh felt contagious and energizing. A spontaneous encounter had a chance to turn into something long-lasting and meaningful.
Those times were pre-Covid-19; the pandemic has brought great upheaval to social norms. Rarely do many of us talk to strangers in public places. Communication is largely transactional – aiming a few words at a clerk behind a plexiglass shield and straining to hear the muffled reply. Laughter has become a rarity. And even if others smile at us, we hardly can tell – or know when to smile back. All we see are faces largely hidden behind masks and staring, shifting or downcast eyes.
Happily, that is beginning to change. Mask mandates are dropping left and right across the United States. As of June 8, 35 U.S. states had removed these requirements in indoor or outdoor public settings. A few U.S. governors have even prohibited local governments and school boards from countermanding such state policy. At the same time, the exposure of Anthony Fauci’s serial contradictions has loosened his grip on the American psyche – weakening the entire pro-mask side. Gathering limits are disappearing as well; the recent Indy 500 was packed with mostly unmasked auto race enthusiasts and fans are once again jamming stadiums for pro sports.
In Canada, a number of provinces are also reopening – led in speed by Alberta, where all provincial restrictions will be dropped within two weeks of 70 percent of the population receiving one dose of vaccine. That pointedly includes the mask mandate. If this occurs, and much of the rest of Canada follows suit, the summer of 2021 could end up being, if not exactly the “best summer ever” in the previous hopeful words of Alberta Premier Jason Kenney, then at least one to rekindle normal life and, perhaps, look back upon as the time when the Covid-19 pandemic was put in its grave.
These lovely sentiments – surely shared by millions of Canadians – could be dashed, however. Reopening is threatened by a number of political leaders, urged on by an entrenched medical/scientific faction, who appear almost terrified of normality’s return and whose default position is to lock down, prohibit and prevent. Ontario, for example, only re-authorized camping last Friday and recently extended its state of emergency until December. Premier Doug Ford, wrote Matthew Lau in the Financial Post, “has turned the presumption of liberty completely on its head. In Ontario there is now a presumption of government control.”
Even in Alberta, big-city mayors are suggesting they might defy the province’s mask mandate lifting. They are egged on by vocal medical experts who have formally demanded that masks remain in place until 70 percent of the population has had two vaccine doses. This may amount to something like “forever,” since vaccination curves in other countries to date have gone nearly flat at approximately 55-65 percent with even one dose. Alberta, it was reported last week, is having trouble achieving the last several percentage points leading to 70 percent with one dose.
In short, if some have their way, it could be masks for a long time. Should further new Covid-19 variants or new infectious diseases come along in the meantime, it might be masks forever.
If Canada is to enter a major political struggle over the possibility of long-term masking, then surely it is worth revisiting the basic question of whether masks actually work. And, even if masks are shown to be useful in slowing the transmission of Covid-19, the public has a right to understand whether habitual mask-wearing carries negative health effects, in order to weigh the costs against the benefits of such an intrusive long-term policy.
With those questions in mind, C2C Journal brings you this exclusive, carefully researched two-part analysis. In Part I, we review the recent history of mask requirements and discuss the initial evidence around widespread mask-wearing.
When it Began: The WHO Mask Guidance
On April 6, 2020, the World Health Organization (WHO) issued Interim Guidance on the use of facemasks against Covid-19. The organization advised only health professionals to wear medical masks or respirators and to avoid non-medical masks because the effectiveness of the latter, it stated, was not established.
Significantly for the wider population – or seemingly so – it also cautioned that “the wide use of masks by healthy people in the community setting is not supported by current evidence and carries uncertainties and critical risks.” Among these were potential self-contamination by frequent touching and re-wearing of single-use masks, breathing difficulties and a “false sense of security, leading to potentially less adherence to other preventive measures such as physical distancing and hand hygiene.”
The WHO’s April guidance was consistent with the statements of numerous public health officials worldwide. It was, for example, preceded by the official statement by Canada’s Chief Public Health Officer Theresa Tam who suggested that “putting a mask on an asymptomatic person is not beneficial, obviously if you’re not infected.”
The official advice should have been unsurprising, even though by this time millions of individuals were rushing to scour store shelves for any and all mask varieties, while others rigged up bizarre contraptions out of old diving helmets or even fish bowls, and a few were seen shuffling down aisles in full hazmat suits (real or home-fashioned). But the official advice was consistent with decades of established international guidance for the management of disease outbreaks, in which masks are recommended for those who are sick – to protect the healthy – but not ubiquitously (see, for example, the WHO’s guide of 2018, or Public Health England Principles of 2015, or the Association of Faculties of Medicine of Canada Primer on Population Health).
Physician Margaret Harris, a member of the WHO’s coronavirus response team, was quoted saying that “the mask is almost like a talisman,” making “people feel more secure and protected.” An official scientist appeared to say that mask-wearing was no longer about science, but about sorcery and emotion.
Regardless of how sound these recommendations are, they soon were thrown overboard as fears spread of “asymptomatic spreaders,” many doctors and scientists started asserting benefits to the public wearing almost any sort of mask, and governments and international organizations sought to reassure jittery populations they were taking “crucial steps” to “save lives” – which now included requiring people to wear masks in a variety of settings.
The WHO subsequently updated its mask guidance, with the most recent document issued on December 1, 2020. Citing a number of studies, this one advised the general public to wear either medical or three-layer fabric facemasks in indoor and outdoor settings where ventilation is inadequate and physical distancing is less than 1 metre. It asserted several pandemic control benefits to such practice, including reduced spread of viral respiratory droplets and reduced stigmatization towards mask-wearers (a transient phenomenon early in the pandemic). Further stated benefits included making people feel that “they can play a role in contributing to stopping spread of the virus,” encouraging proper hygiene and, finally, reducing transmission of other respiratory illnesses such as tuberculosis and influenza.

Caution to the wind: The WHO’s explicit list of negative effects from ubiquitous mask wearing was ignored by all.
The WHO’s list of disadvantages, however, had grown significantly and now also included potential headaches, facial skin problems, difficulties communicating, discomfort, improper mask disposal, poor compliance among young children and difficulties for people with developmental challenges, with chronic respiratory problems or those living in hot and humid conditions. Nor should this have been surprising either, for as we shall see it too was consistent with longstanding scientific understanding. None of these mask-associated risks, however, received a thorough airing in news and social media.
On the contrary, many governments imposed even more stringent and often duplicative requirements, like requiring masks and distancing even outdoors where ventilation was good, or masks and plexiglass barriers, or masks, face shields and distancing. Masks, meanwhile, took on novel roles as political statements or articles of faith employed by political leaders, organizations, public health figures and much of the population. People were even seen swimming with paper masks. Physician Margaret Harris, a member of the WHO’s coronavirus response team, was quoted in an NPR column saying that “the mask is almost like a talisman,” making “people feel more secure and protected.” An official scientist appeared to say that mask-wearing was no longer about science, but about sorcery and emotion.
Meanwhile, no one in the public sphere seemed willing to peruse the WHO’s December 2020 guideline in detail. Had they done so, they might have noticed two statements eerie in their juxtaposition. First, the WHO clearly recognized the serious limitations of the studies it cited about the efficacy of masking to reduce viral spread: “[The] studies differed in setting, data sources and statistical methods and have important limitations to consider notably the lack of information about actual exposure risk among individuals, adherence to mask wearing and the enforcement of other preventive measures.” Second, the WHO nonetheless insisted on universal mask usage: “Despite the limited evidence of protective efficacy of mask wearing in community settings, in addition to all other recommended preventive measures, the [guidelines development group] advised mask wearing.”
The WHO’s categorical recommendation, then, rested on admittedly shaky foundations. Over half a year has passed. One would expect there to be an ever-growing number of studies dedicated to Covid-19 and related issues, including masking. And so there has been.
Current Evidence on Mask Effectiveness
More than 300 scientific papers have been published specifically on masking during the pandemic. The best way to evaluate such a vast body of research without losing the forest for the trees is to focus primarily on literature reviews and systematic reviews (special types of scientific analysis that summarize up-to-date knowledge on a particular issue). This narrows the search to some 20 review studies (as of May 2021). Six of these provide support for universal mask wearing using epidemiological data (1, 2, 3, 4, 5 and 6). Six others offer mechanical evidence by describing material and filtration properties of masks. Two reviews are inconclusive (this and this), while the rest are less relevant (comparing medical masks to N95 masks in a healthcare setting, for example, this).
The most recent and comprehensive review is by researchers from the University of Hawaii at Manoa, Honolulu, published in April 2021. This interdisciplinary report outlines the “state-of-the-art understanding of mask usage against Covid-19” by covering the most important epidemiological data, face mask filtration mechanisms and mask recontamination and reuse.
In their epidemiological evidence the researchers cite eight publications that report a positive association between mask wearing and a reduced risk of Covid-19 infection. These studies were conducted in China, Thailand, the U.S., Germany and Canada. The Canadian evidence notably encompassed both provincial data from Ontario and nationwide data analyzing the effect of mask wearing on Covid-19 case numbers over the course of eight months. “In the first few weeks after their introduction, mask mandates are associated with an average reduction of 25 to 31% in the weekly number of newly diagnosed COVID-19 cases in Ontario,” the study concluded. It also speculated that had indoor masking been mandated by early July, there would have been 25-45 percent fewer weekly cases across the country than actually occurred.
The other studies were different in methodology and reported varying strengths of the association between mask wearing and risk reduction, ranging from 15 percent to 80 percent. The University of Hawaii team’s conclusion appears decisive: “All available epidemiologic evidence suggests that community-wide mask-wearing results in reduced rates of COVID-19 infections.”
Not All Science Is Created Equal: RCTs vs. Observational Studies
The take-home message from the above research appears unequivocal: masks work. The factual conclusion provides scientific support for the political decision to impose a public mask mandate. But for one fact: nearly all Covid-19-related epidemiological studies are either observational analyses (such as this or this), simulation studies (such as this), or a combination thereof (like the Canadian study described above). Almost none involved randomized controlled trials (RCTs).
Why does that matter?
The distinction between study types is imperative for it speaks of the quality and not simply the quantity of the available scientific evidence. Setting aside simulation studies that are hypothetical and therefore of lesser empirical value, it is important to understand the differences between RCTs and observational studies (case-control and cohort studies are two types).
The RCT facilitates an objective comparison between various types of intervention, or between treatment and non-treatment. The RCT achieves this by using the process of randomization, assigning participants randomly either to experimental or control groups. The goal of such studies is to prevent manipulation of the results and to draw, as accurately as possible, a causal relationship between an intervention, or a behaviour, and the subsequent outcome.
The link of causality cannot be achieved in observational research, which involves analyzing data gathered in natural conditions without researchers’ intervention. Although observational studies are illuminating and useful in various scenarios, they are inevitably biased. The bias occurs because such studies do not allow for direct control over confounding variables that may have an impact on the study results. For example, for one to say that “A causes B” requires ensuring that the effects of all other important variables on B have been removed or cancelled through randomization.

Through the process of randomization, RCTs are able to establish a causal link between a treatment or behaviour and an outcome. Observational studies are limited to showing correlation, or association – and thereby can be misunderstood.
This is impossible in observational studies, always leaving a chance that the observed outcome B might have been caused by a variable, or variables, other than A. Thus, observational studies, even those employing advanced statistical analyses, cannot reach conclusions stronger than establishing temporal associations between one thing and another. But association, or correlation, does not demonstrate causation. (The Canadian study cited above, for example, notes that mask mandates are “associated” with a reduction in the rate of Covid-19 infection; it does not assert a causal relationship.)
The Odd Reluctance to Conduct RCTs in Regard to Public Health Matters
Which brings us back to the 300-odd mask-related studies conducted in the Covid-19 era. Many, indeed, found associations or correlations between widespread adoption of masks and a reduction in Covid-19 case counts, or a slowing of acceleration in case counts. In an observational study like this one, however, it is reasonable to ask whether the detected reduction in Covid-19 transmission was caused by mask wearing. Could it not have been due to other preventative health measures adopted around the same time, such as improved hand hygiene, limited social interaction, physical distancing in public settings or even individuals’ general health regimen? And what about the impact of other variables such as age or race on the risk of catching the virus? Finally, could there be other, as-yet overlooked confounders that affect virus spread? Randomization is required to negate the effects of the confounding variables, known or unknown.

Correlation does not show causation: Masks may be associated with a reduced rate of Covid-19 infection, as frequently documented in observational studies, but a host of other factors could also be at work.
Because of these known limitations of observational studies, the RCT is recognized as the gold standard of clinical research practice, a rigorous tool of cause-and-effect analysis. One of the world’s leading experts in medical standards and statistics, Dr. Janus Christian Jakobsen, who is frequently cited for her systematic reviews of meta analyses, authoritatively stated:
“Clinical experience or observational studies should never be used as the sole basis for assessment of intervention effects – randomized clinical trials are always needed…Observational studies should primarily be used for quality control after treatments are included in clinical practice.” (Emphasis added.)
It is thus clear that in health-related contexts, researchers should rely on RCTs whenever possible and use observational studies to gather supplementary evidence.
The most common arguments against RCTs are that they are expensive, time-consuming and impractical for population-wide interventions. There are also understandable ethical objections against exposing healthy control groups to contagious and potentially fatal infections, in this instance attempting to determine whether unmasked people are more likely to catch Covid-19. In fact, some have asserted, in reference to the WHO, that “we should not generally expect to be able to find controlled trials” in the context of population health measures.
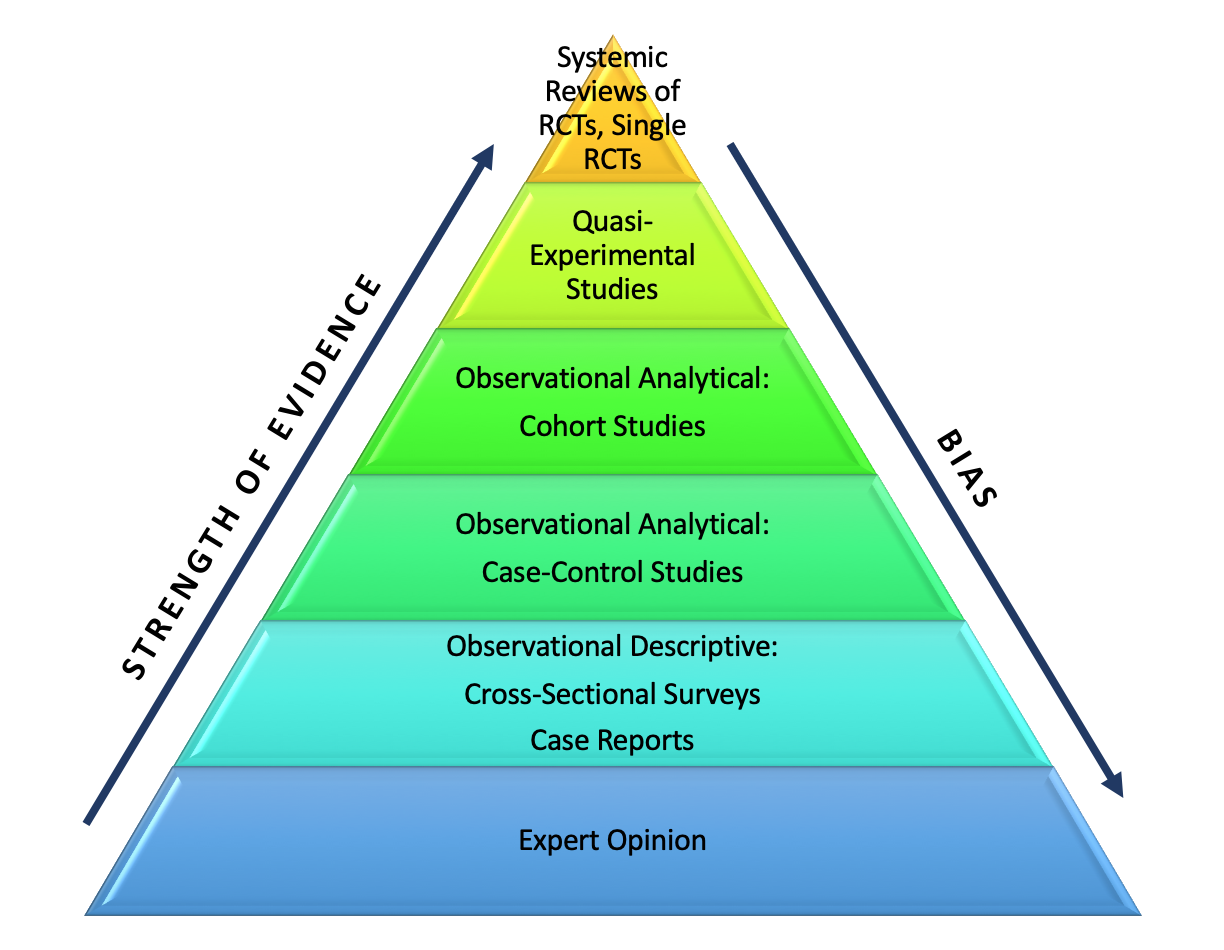
Maximum strength of evidence, minimum degree of bias: Not for nothing is the randomized controlled trial considered the “gold standard” of clinical practice. (Graphic by Masha Krylova/ C2C Journal)
Unethical and impractical? It is claimed that RCTs should not be used to study the effects of health measures on Covid-19 infection – yet numerous RCTs have examined influenza on a community-wide scale.
Still, it has been over a year since mask mandates were first imposed in many countries. Given the prodigious effort poured into seemingly anything to do with Covid-19, this should be ample time for researchers to gather resources and test mask effectiveness in a controlled experimental setting. Nor was it unheard-of prior to the pandemic to perform RCTs in healthcare and wider-population settings to evaluate the effect of mask wearing on the transmission of respiratory illnesses such as influenza (see this review of 2010) and influenza-like illness (also see this scoping review of 2020). These studies clearly overcame objections related to practicality and ethics. Why should Covid-19 be different?
The cited reviews present intriguing details: with respect to influenza, five out of six RCTs conducted in healthcare settings found no significant difference between mask-wearing and control groups. Even more important from the standpoint of the current pandemic, none of four RCTs performed in broader community settings found a significant difference between masking and remaining bare-faced. For influenza-like illnesses, the pooled data from five other RCTs as well showed a non-significant protective effect of mask wearing for avoiding either primary or secondary infection. These results appear substantial and would seem of some relevance to the current pandemic. But there is more.
End of Part I.
Coming next in Part II: Should you care whether masks are more like a sieve or a filter? Is there really no RCT-generated “gold standard” evidence regarding whether wearing masks reduces the spread of Covid-19? And is there any basis to concerns of ill effects from wearing masks?
Maria (Masha) V. Krylova is a Social Psychologist and writer based in Calgary, Alberta who has a particular interest in the role of psychological factors affecting the socio-political climate in Russia and Western countries.
All Risk. Zero Benefit. 10 Reasons to Say No to the Jab for the Young
By Abir Ballan | Trial Site News | June 26, 2021
 Here are 10 Reasons why children and young people should NOT get the COVID-19 vaccines:
- Children and young people have a mostly mild or asymptomatic presentation when infected with SARS-CoV-2. They are at near-zero risk of death from COVID-19.
- There is an unusually high rate of reported adverse events and deaths following the COVID-19 vaccines compared to other vaccines. Some adverse events are more common in the young, especially myocarditis. Where potential harm exists from an innovation and little is known about it, the precautionary principle dictates to first do no harm. Better safe than sorry.
- Medium and long-term safety data about the COVID-19 vaccines are still lacking. Children and young people have a remaining life expectancy of 55 to 80 years. Unknown harmful long-term effects are far more consequential for the young than for the elderly.
- Vaccination policies rely on expected benefits clearly outweighing the risk of adverse events from the vaccination. The risk-benefit analysis for the COVID-19 vaccines points to a high potential risk versus no benefit for children and young people.
- Transmission of SARS-CoV-2 from children to adults is minimal and adults in contact with children do not have higher COVID-19 mortality.
- It is unethical to put children and young people at risk to protect adults. Altruistic behaviors such as organ and blood donation are all voluntary.
- Several prophylactic treatments as well as the COVID-19 vaccines are available to high-risk individuals so they can protect themselves.
- Natural immunity from infection with SARS-CoV-2 is broad and robust and more effective than vaccine immunity, especially in combating variants. Children and young people are safer with natural immunity.
- There are several prophylactic (preventive) protocols and effective treatments available to children and young people with comorbidities.
- Vaccinating children and young people is not necessary for herd immunity. After a year and a half of the pandemic, most people either have pre-existing immunity from other coronaviruses, have recovered from COVID-19 or have been vaccinated.
There is no Covid third wave in Africa
Alarmist reporting is getting basic facts wrong
By Toby Green | Unherd | June 24, 2021
The last few days have seen an avalanche of reports that a third wave of Covid-19 is underway in Africa. Seasoned coronavirus watchers will not be surprised that the alarm was raised in Geneva. WHO Central issued alarming press releases on June 7th and 17th, with the Regional Director for Africa, Dr Matshidiso Moeti, stating in the latter that “Africa is in the midst of a full-blown third wave”. So what’s happening?
Since the June 7th press release, there have been 1,651 new deaths reported from Covid-19 across the entire continent in 17 days, less than 100 per day. In a continent where 9 million people die annually (roughly 25,000 per day), reported Covid deaths in this “full-blown” third wave thus currently account for roughly 0.4% of daily mortality in Africa. Certainly, there are mortality increases from Covid reported in some countries such as Cape Verde and the Democratic Republic of Congo, but they are not anything like on the scale of what has happened elsewhere.
Moreover, the vast majority of these fatalities have occurred in temperate zones: South Africa, Morocco, Egypt, Algeria, Libya and Tunisia account for 105,000 of the 139,500 deaths reported from Covid-19 across the continent.
Many of the reports on this “third wave” point to the failure to count deaths accurately, and suggest that these figures mask the true problem. Reports from the BBC and the New York Times have pointed to a continent-wide lack of systemic mortality figures. But running at 0.4% of current mortality, and touching a small area of the continent as a whole, even if this was an underestimate by 1000%, Covid would still only be a minor concern to most Africans. In fact, a recent paper disputes these accusations of undercounting: the authors note that “while only 34.6% of countries [in Africa] have complete death registration data… all countries have a system in place, and there is no evidence that COVID-19 mortality data is less accurately reported in Africa than elsewhere”.
What certainly does go under-reported are cases. This is good news, as it indicates that much of the continent’s population has already developed antibodies to Covid-19 through mild infections. In a study from July to October 2020 of mineworkers tested in Ivory Coast, 25.1% had Covid antibodies; meanwhile, a February study in South Africa based on blood donors found antibody levels of 63% in Eastern Cape, 46% in Free State, and 52% in KwaZulu Natal, while a study from Cameroon just published found antibody levels of 32%. These figures far outstrip recorded cases, suggesting that many Africans already have protection from Covid.
However the WHO redefined herd immunity last year as only achievable through vaccination, so it may not want to publicise this. The Guardian last week added to the clamour, reporting on research that had not been peer-reviewed and which claimed that Covid infection did not provide immunity. Ironically, a series of studies published in Nature the week before had found that “the evidence thus far predicts that infection with SARS-CoV-2 induces long-term immunity in most individuals”.
The evidence from Africa is quite clear, in fact. Large sections of the population have now developed Covid antibodies, and death rates are low compared to other chronic illnesses. Herd immunity does not have to be achieved through vaccination, either in Africa or elsewhere. But none of these conclusions fit with the catastrophic decisions taken by global policy elites over the past year, so they won’t be coming to a television news channel near you any time soon.
Toby Green is the author of The Covid Consensus: The New Politics of Global Inequality (Hurst).
Johnson’s govt taken to court by theatre bosses to force release of Covid-19 trial data
RT | June 24, 2021
A group of concert and theatre bosses led by Andrew Lloyd Webber has launched legal action against the British government in a bid to force it to publish data from a trial assessing the safety of indoor events during the pandemic.
The concert managers and theatre producers are demanding that the government provide data from its Events Research Programme – a trial assessing the safety of indoor events – so that they can plan to finally reopen their institutions.
In a statement on Thursday, they said the government had “refused to publish the results from the first phase of the Events Research Programme, despite saying that it would do so on numerous occasions.”
The statement adds that, in addition to not publishing the data from the trial, the government has not provided any form of insurance scheme to safeguard the industry against any further delays following 15 months of closures due to Covid curbs.
The entertainment bosses claim that, according to the government, the trial has been a huge success, which in turn has contributed to the increasing frustration within the entertainment sector concerning the industry’s continuing dormant state.
Pilot events under the programme, which the industry participated in, included the BRIT Awards at the O2 Arena, an outdoor festival event in Liverpool for 5,000 people, a snooker tournament at the Crucible Theatre in Sheffield, and the Download festival for 10,000 people last weekend.
The reopening of the theatre industry in England has been pushed back from its anticipated late June date until July 19, following the spread of the more infectious Delta variant.
Speaking later on Thursday, a spokesman for Prime Minister Boris Johnson said the government had made £2 billion available via a major arts funding package. He added that the government understands “the necessary delay to step four is challenging for live events.”
The impresarios note in their statement that live entertainment and theatre generate £11.25 billion for the UK economy each year, supporting just under one million jobs.
Featured Video

Ivermectin and iodine
or go to
Aletho News Archives – Video-Images
Book Review
UAE tortured, killed journalist for opposing Israel normalization
The Cradle | October 31, 2026
UAE security officers detained, tortured, and killed Emirati poet and news editor Habib al-Sayegh in August 2019, shortly after he published a column opposing UAE normalization with Israel, according to a newly published book.
“Princes and Thieves,” a book by investigative journalist Matthew Cole published on 25 October, alleges that UAE security officers raided Sayegh’s Abu Dhabi home shortly after the publication of the column, hooded him in front of his wife and took him to a detention facility where he was tortured to death.
His interrogators reportedly pulled out several of his teeth with pliers and beat him repeatedly with a sharp metal object.
On 11 August 2019, Sayegh criticized the UAE’s plan to normalize relations with Israel as part of the Abraham Accords in his weekly column for Khaleej newspaper. The column was titled “Israel Is Our Real Enemy and A Dangerous Project.”
Sayegh described Israel as “a real and natural enemy” while questioning “who authorized the normalizers to speak on behalf of everyone?”
Nine days after the column was published, Emirati state media announced his death, without stating a cause. … continue
Blog Roll
 Aletho News
- Ivermectin and iodine
- Congratulations climate skeptics — you are a ‘Hybrid weapon of war’ and a growing public health threat
- ‘The Arab Vote’: How Israeli Racism Has Ruined Their Elections
- Israel forces Palestinians in Gaza to choose between assassination alone or death with their families: Report
- US Approves Sale of 500 Patriot Missiles to Ukraine, Deliveries May Take Years
- German Imperialism: An Urgent Explainer
- Backed by AAP, West Virginia Proposal Would Allow Dental Hygienists to Give HPV Vaccine to 9-Year-Olds
- Poland Is the Symptom and Europe Is the Patient
- UAE security forces tortured, killed journalist for opposing Israel normalization: Report
- They Compared the Spice to the Drug. The Spice Won — Again. (Part 2)
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!

