Victoria premier extends lockdown, again, as Aussie police granted power to covertly hack citizens’ phones & alter data

Police arrest a protester during an anti-lockdown rally in Melbourne on August 21, 2021 as the city experiences its sixth lockdown © AFP / William West
RT | September 1, 2021
Victoria’s premier has announced that a statewide lockdown will remain in place until most residents are vaccinated, just days after Australia adopted new legislation giving sweeping surveillance and spy powers to police.
Draconian measures covering the entire southeast Australian state will only start to be eased once 70% of the population receives at least one dose of the Covid vaccine, Premier Dan Andrews decreed on Wednesday. The government said it hoped to reach this target on or around September 23.
In a written statement, Andrews claimed that lifting restrictions would “overrun” the state’s healthcare system. With a population of around 6.6 million, Victoria currently has less than 60 Covid hospitalizations.
The entire state has been under strict lockdown for nearly a month. After shutting down non-essential activity in Melbourne, Andrews decided to extend restrictions to the entire state on August 5, citing the alleged detection of Covid-19 in wastewater 236km (147 miles) from the city. He was later forced to admit that the sewage in question had actually tested negative for the virus. Nonetheless, the statewide lockdown, which was only supposed to last seven days, has remained in place.
Currently, Victorians are not allowed to venture more than five kilometers (3.1 miles) from their homes – and only for “essential” activities. Andrews promised to increase the travel radius to 10km once the state’s vaccination benchmark is met.
The new conditions for easing lockdown were revealed a week after Australia passed a controversial bill giving police the ability to secretly seize and alter internet accounts.
Known as the Surveillance Legislation Amendment (Identify and Disrupt) bill, the legislation allows the Australian Federal Police (AFP) to take over, and modify or delete, the accounts of cybercriminal suspects.
Although authorities claim that the law will help crack down on pedophiles, terrorists and drug traffickers, many on social media expressed concern that the extensive powers were further evidence of Australia sliding into authoritarianism.
The Australian state has recorded 822 Covid-linked deaths since March 2020. To put this figure in perspective, more than 950 Victorians have died from suicide over the same period.
The state’s draconian restrictions have been blamed for fueling a mental health crisis, especially among the young. While only one Australian aged 19 or younger has died with Covid-19, eight teenage girls have taken their own lives in Victoria in the first seven months of the year.
The Añez Regime Tried To Assassinate Morales, Mexico Reveals
teleSUR | September 1, 2021
On Tuesday, Mexican Air Force (FAM) pilot Miguel Hernandez disclosed that a projectile could have been fired at the aircraft in which he rescued former President Evo Morales after the 2019 coup in Bolivia.
“Upon taking off from Cochabamba airport in Bolivia, the pilot observed a rocket-like trail of light from the left side of the cockpit when he nearly reached 1,500 feet over the ground,” FAM stated.
To avoid the projectile, Hernandez made a turn to the opposite side of its trajectory and increased the ascent speed. While making this maneuver, he observed that the projectile returned to the ground in a parabola-shaped trace without reaching much height.
The pilot did not communicate the incident to his crew so as not to increase tension during a diplomatic mission whose purpose was to lead Morales to Mexico as a political asylee. The aircraft was chased by a rocket-propelled grenade (RPG) while taking off from Cochabamba airport. Therefore, he suspects that the rocket could have come from this launcher.
“I got a lump in my throat when I thought what could have happened in our country if Morales had been murdered. The shadows of terror sown over the Bolivian people cannot go unpunished,” Gabriela Montaño, Health Ministry during the Morales administration, tweeted.
In a plenary meeting of the Bolivian Congress, President Luis Arce affirmed that he would not rest until Jeanine Añez’s facto government is punished for torture, persecution, illegal detentions, and murders that it committed during the coup d’état.
On Aug. 19, the Interdisciplinary Group of Independent Experts (GIEI) confirmed that 38 citizens were killed and over 100 were injured during the protests against the Añez regime, which allowed Armed Forces and the Police to act with impunity during their repressive operations against Bolivians.
Supporting Doctors’ Rights To Speak, Free From Censorship
doctors4covidethics.org

Dr. Paul Oosterhuis is an Australian anaesthetist with over thirty years experience, including in critical care and resuscitation, who urgently needs your support.
He is facing a hearing by the Medical Board of NSW for posting information on social media regarding COVID-19. His posts related to early treatment and prophylaxis, PCR tests, and risk-benefit calculations regarding COVID-19 vaccination and lockdowns (scroll down for details). His hearing is on September 3rd. Please help him by signing and sharing this petition.
We are practicing doctors and allied health professionals and/or scientists and academics and/or members of the public and/or represent professional organisations. We support the right of Dr Oosterhuis, and that of all doctors, to offer informed medical opinions on COVID-19 and to discuss the available evidence on COVID-19 interventions.
As doctors we too have advised and continue to advise patients and the general public about the medical management of COVID-19 disease and vaccination on the basis of good science. As members of the public we reserve the right to receive honest information, opinion and advice from our doctors, free from government interference.
From Dr Oosterhuis:
Dear colleagues and concerned citizens,
Thank you for taking the time to read this petition.
My name is Dr Paul Oosterhuis. I am an anaesthetist from Australia. I have been called before the NSW Medical Board for a hearing on September 3rd 2021 following anonymous complaints about my social media posts on Facebook regarding COVID-19. I have been advised by the Medical Council that:
“The Medical Council of NSW received two anonymous notifications regarding your activity on social media.
Due to the concerns outlined in the notifications the Council has resolved to convene proceedings under section 150 of the Health Practitioner Regulation National Law (NSW) to consider whether any action is required for the protection of the health and safety of the public or in the public interest.”
Ahead of the hearing I am seeking signatures from my medical and scientific colleagues and members of the public to help me defend my own and all doctors’ rights to offer our informed medical opinions, share our expertise, and engage in open discussion regarding COVID-19.
I am a Sydney University trained medical graduate. I undertook my internship and residency at Prince of Wales Hospital in Sydney, followed by postgraduate training in Anaesthesia at The Royal Prince Alfred Hospital. I have more than 30 years of practice, the first 20 years involving hands-on critical care and resuscitation, and the last 10-plus years as a senior Visiting Medical Officer working in the Sydney Local Health District.
In the social media posts for which I face a Medical Board hearing, I discussed issues such as early treatment and prophylaxis against COVID-19, evidence for government measures such as lockdowns and PCR tests, and evidence regarding risk-benefit analyses of COVID-19 vaccines.
For example:
“I wish you could just add EARLY TREATMENT and drug PROPHYLAXIS …..Tell everyone to take Vit D, Zinc, and EARLY TREATMENT with IVM/ HCQ as evidence based medicine alternatives.”
I provided a link to a presentation by Dr Paul Marik on prophylaxis in support of the post, highlighting a chart of vitamin D versus risk of COVID from Dr Marik’s presentation, to illuminate the low hanging fruit of prophylaxis.
In other posts I questioned the evidence base for the government’s policies of lockdowns and mask mandates, and pointed out that there is evidence of vaccines having low effectiveness and real risks and harms (which are being suppressed), along with harms from the totalitarian lockdowns causing massive damage society-wide.
The risk of Antibody Dependent enhancement of disease, predicted by Dr Geert Vanden Bossche, driven by immune escape from the selective evolutionary pressure of vaccinating with a non sterilising agent is a real and present danger and needs to be discussed. The danger to millions is distressing to me, and discussing that danger is, I believe, unarguably in the public interest.
Early in 2020, I was active in criticising my medical administrators for failure to prepare for an outbreak such as COVID-19 when it was apparent that PPE was being rationed (P95’s were in short supply). I urged my colleagues to perform quantitative fit testing of our available P95 masks in early 2020 during which we found a surprising number of staff failed quantitative fit testing with the hospital issued PPE. This was something I had hypothesised after looking at the number of healthcare workers in Northern Italy catching the disease.
I withdrew from clinical practice last year out of concerns about the increasing incompetence of the health administrators and the rapidly reduced autonomy of doctors to just be able to be a doctor.
Over the last 18 months I have been increasingly concerned about the misinformation and censorship creeping into science and medicine. Fellow physicians were saving lives with early treatment and medication/supplement approaches to prevention but it was THIS that was attacked and censored! People like Dr Paul Marik, Dr Pierre Kory of the FLCCC Alliance, Dr Robert Malone, Dr Geert Vanden Bossche, Dr Michael Yeadon, Dr Vlad Zelenko, Dr Chris Martensen, Dr Eric Weinstein and others are making credible and serious warnings about the gene therapy being coerced upon our populations.
Censoring their work, and the research of experts like Dr Tess Lawrie, Dr Peter McCullough, Dr Sucharit Bhakdi and America’s Frontline Doctors is dangerous.
The Medical Board of NSW is now using intimidation, threatening doctors like myself, who share data which questions the official narrative. I don’t believe that censorship is compatible with good science and good medicine, and I believe that it needs to stop now, in the name of public health and public interest.
I would be very grateful if you could help to support me in my effort to inform as many as possible about their true health choices. My hearing is in a matter of days.
While I wish I did not have to defend my right to speak truthfully as a doctor, the song and video below captures my attitude to fighting for that right. I hope you enjoy it.
With my most sincere thanks,
Dr Paul Oosterhuis
Australia
See also:
NZ Doctors Speaking Out with Science (petition)
UK Schoolchildren To Be Covid Vaxxed With Or Without Parental Consent
ALERT: ALL PARENTS IN U.K. WITH CHILDREN AGED 12 – 15 years
By Dr. Mike Yeadon | Health Impact News | August 26, 2021
I’ve just been informed via someone senior in the vaccination authorities that they will begin VACCINATING ALL SCHOOL CHILDREN AGED 12 – 15 years old STARTING SEPTEMBER 6th 2021.
WITH OR WITHOUT YOUR CONSENT.
Children are at no measurable risk from SARS-CoV-2 & no previously healthy child has died in U.K. after infection. Not one.
The vaccines are NOT SAFE. The USA reporting system VAERS is showing around 13,000 deaths in days to a few weeks after administration. A high % occur in the first 3 days. Around 70% of serious adverse events are thromboembolic in nature (blood clotting- or bleeding-related).
We know why this is: all of the gene-based vaccines cause our bodies to manufacture the virus spike protein & that spike protein triggers blood coagulation.
The next most common type of adverse events are neurological.
Death rates per million vaccinations are running everywhere at around 60X more than any previous vaccine.
Worse, thromboembolic events such as pulmonary embolisms, appear at over 400X the typical low rate after vaccination.
These events are serious, occur at a hideously elevated level & are at least as common in young people as in elderly people. The tendency is that younger people are having MORE SEVERE adverse events than older people.
There is literally no benefit whatsoever from this intervention. As stated, the children are unquestionably NOT AT RISK & vaccinating them WILL ONLY RESULT IN PAIN, SUFFERING, LASTING INJURIES AND DEATH.
Children rarely even become symptomatic & are very poor transmitters of the virus. This isn’t theory. It’s been studied & it pretty much doesn’t happen that children bring the virus into the home. In a large study, on not one occasion was a child the ‘index case’ – the first infected person in a household.
So if you’re told “it’s to protect vulnerable family members”, THAT IS A LIE.
The information emerging over time from U.K. & Israel is now showing clearly that the vaccines DO NOT EVEN WORK WELL. If there’s any benefit, it wanes.
Finally, the vaccines ARE NOT EVEN NECESSARY. There are good, safe & effective treatments.
IF YOU PERMIT THIS TO GO AHEAD I GUARANTEE THIS: THERE WILL BE AVOIDABLE DEATHS OF PERFECTLY HEALTHY CHILDREN, and severe illnesses in ten times as many.
And for no possible benefit.
KNOWING WHAT I KNOW FROM 40 years TRAINING & PRACTISE IN TOXICOLOGY, BIOCHEMISTRY & PHARMACOLOGY, to participate in this extraordinary abuse of innocent children in our care can be classified in no other way than MURDER.
It’s up to you. If I had a secondary school age child in U.K., I would not be returning them to school next month, no matter what.
The state is going to vaccinate everyone. The gloves are off. This has never been about a virus or public health. It’s wholly about control, totalitarian & irreversible control at that, and they’re nearly there.
PLEASE SHARE THIS INFORMATION WIDELY.
With somber best wishes,
Mike
ACIP vote yesterday, after deceitful CDC briefings, removes liability from Comirnaty and opens door to mandates
By Meryl Nass, MD | August 31, 2021
In a nutshell: Yesterday CDC asked its advisory committee to “recommend” the Comirnaty vaccine for 16 and 17 year olds. And it agreed, unanimously. Or pusillanimously.
The vote may seem silly or superfluous, because it had already been recommended for this age group as an EUA.
But this vote was anything but superfluous. This seemingly minor recommendation, which did not get headlines, moves the licensed Comirnaty vaccine from a place where the manufacturer is legally liable for injuries, to a berth within the Childhood Vaccine Injury Compensation Program, for which there is no manufacturer liability. Instead a $0.75 excise tax is charged per dose, which goes into a fund administered by DHHS to pay for injuries, if one is lucky enough to convince the special masters (judges) in the program that a vaccine caused your injury. Once a vaccine is recommended for children, its liability is waived no matter who receives it.
But the important part is that once this process is complete (which I expect to be only a very few weeks), Pfizer can roll out stocks of the licensed vaccine while still having its liability waived. That means that the loophole I told you about last week is being backfilled by the USG, with the help of the supine and spineless ACIP committee members, and will soon disappear.
I say spineless with true conviction, because the briefings they received yesterday were a load of fraud and hogwash. Yet no one challenged the data nor the conclusions. It is hard to believe that the lot of them are really that stupid that they believed what they heard. It is also hard to believe that none of them had a conflict of interest, which they all asserted along with their vote.
Furthermore, no one ever actually said why the vote was held: which was for liability purposes, nor that the vote would lead to mandates, which could not be implemented under the EUA.
So, it is disappointing.
Children’s Health Defense went to court today in Tennessee to challenge the FDA on issuing both a license and EUA for the same product. AFLDS also went to court today in Colorado challenging the mandate. More on these cases later.
The Science Is Clear – The Case Against Mandating Vaccines: One Executive’s POV
SOTT | August 31, 2021
SOTT Editors: We are publishing below, with permission, an email from a top executive at an American company whose clients include 100 of the Fortune 500 companies. The email was sent in reply to another executive asking for the writer’s thoughts on whether he plans to be vaccinated himself or mandate it for his employees as a requirement for returning to the office. All names and company references have been redacted for privacy reasons.
Unlike most of us who are worried about being on the receiving end of vaccine mandates by employers, this executive also has to worry about pressure from other executives and investors to mandate it on others. Few such business leaders are actively fighting for the rights, dignity, peace, and financial security of their employees. This exec is currently the only voice in his company opposing the madness.
Email to the executive:
Hey [REDACTED] – are you giving any thoughts to getting vaccinated with all this Delta variant stuff going on? We’ve been having management committee discussions here about mandatory vaccinations to be able to come in to the office. We have office support people coming in most days that are not vaccinated and some of those with kids don’t want to come in when they are in the office or invite clients into the office for meetings. Just curious as to how you are approaching it. Thx, [REDACTED]
The executive’s reply:
From: [REDACTED]
Date: Fri, Aug 27, 2021 at 9:56 PM
Subject: MY POV on Mandating Employee Vaccinations
To: [REDACTED]
I appreciate you reaching out. What follows is admittedly lengthy (though I do provide my “summary POV” a couple paragraphs down before I dive into supporting detail). I tried to be succinct, but practically speaking your question for me was akin to “hey, so what’s your take on management?” The analogy here being I’m passionate about both subjects so it was hard to choose between sending back a brief 2-minute POV, or filling this email with enough content fit for a university level course. I didn’t know what you had an appetite for, so I just simply did my best to try and be helpful (and heck, even had some fun while I was at it…).
My framework for this entire POV: in the famous words of W. Edwards Deming, “In God we trust. All others must bring data.” As I hope you’ve come to know me by now, I care more deeply about facts & morals than I do ideology or identity politics (for the latter I just don’t give a shit). If you give me a good reason to do something, I am 100% all over it. But if you give me either faulty reasoning or an unethical ultimatum, I simply cannot get on board out of a moral obligation to do what’s right.
So to answer your questions with that sole framework in mind, here’s my summary POV:
(#1) I still have no plans to get vaccinated anytime in the foreseeable future (unless something radically changes the risk equation), given:
(a) The virus at present poses de minimis risk for me personally (and virtually zero risk to any healthy child (a reference to your initial inquiry)); and
(b) Because these vaccines carry –> confirmed low/moderate short term — inferred moderate medium term — and expected high long-term health risk for what could be [though yet unknown] a majority of individuals who get the jab
(#2) I remain vehemently opposed to vaccine mandates for this specific virus (primarily on the basis of (i) 1b above, (ii) the medical literature, which strongly suggests that these vaccines will prolong this pandemic indefinitely through never-ending variants, and thus/therefore (iii) on moral grounds, as, if (i) and (ii) are true, then any decision to proceed with mandates would be nothing short of a descent by the West towards fascism**, the likes of which hasn’t reared its ugly head since the early 20th century. Finally, at a distant, distant second, I am against these mandates from a logistical perspective*.
*E.g., how will you account for boosters (i.e., will those who were vaccinated too far in the past e.g., January and thus have substantially waning transmission protection also be excluded from the office)? What about those who got a different jab (e.g., AstraZeneca, Sputnik, CoronaVac, etc.), each of which has varying levels of effectiveness (and varying levels of effectiveness reduction over time) against different variants? How will you handle those that already had COVID-19 (and therefore (a) have even higher immunity than the vaccinated, and (b) who face higher health risks if they get vaccinated post- natural infection)? What will you do with the immunocompromised (folks with organ transplants, lung problems or cancer patients) who got the vaccine but have low viable antibodies because they require evermore booster shots? What will you do when future variants require different jabs? I could go on, but I trust you get the point. My real question for you is, will you be responsible for coordinating monthly/quarterly management meetings to update & maintain these ever-changing mandate policies covering ever-growing future use cases?
**And if you think I’m exaggerating, look no further than NY State Assembly Bill A416, which proposes forcibly putting carriers of COVID-19 who do not conform to the state’s medical guidelines into something akin to internment camps, where they will be forced into a treatment deemed appropriate by the state and detained indefinitely until they comply. Imagine a U.S. legislative policy so bad, that even Russia Today was able to shit all over it as being far too draconian. And it’s not just the state of NY, but the CDC as well.
===================
Last comments before I dive into supporting details
To not lose sight of being pragmatic as it pertains to your inquiry, I want to point out that at this juncture even a discussion about vaccine mandates is mostly moot.
We already know (confirmed) that those who are vaccinated/infected carry as much viral load as the unvaccinated. Which, coupled with waning transmission prevention efficacy means for all practical intents & purposes those vaccinated and those unvaccinated pose similar risks to one another.
And this is notwithstanding even more cutting edge research (not even yet published i.e. currently pre-print in The Lancet), which suggests those vaccinated carry significantly (upwards of 200x) more viral load than the unvaccinated (which would, if peer-reviewed, flip the risk equation on its head even further in that those vaccinated would pose far greater risk to one another than those unvaccinated). (And it is worth noting that this development would be consistent with what has been found with other vaccines — in this 2017 study, for example, it was assessed that those who were vaccinated for influenza shed 6.3x as much virus as those who are unvaccinated. Crazy stuff.)
All of this is to say, despite the nationwide pushes you’re seeing for private & federal workplace vaccination mandates (which may have made at least some sense much earlier on), such mandates are unfortunately no longer effective models at this stage, unsupported by what we now understand via the latest science. Instead, if you really want to make a difference in improving workplace safety at this juncture, I would suggest implementing either the 1st, or both, of the following policies:
(1) Everyone at the company must perform a daily (pre-commute) self-assessment health survey, whereby all individuals must confirm they are not exhibiting any of the known symptoms of COVID-19 (i.e., if you can’t smell, have fever/chills, shortness of breath, etc., you can’t come in to the office, period), without any pressure from management to respond they are symptom-free.
(2) (Optional) everyone, irrespective of vaccination status, must get tested weekly for COVID-19, such testing to be reimbursed by the company. If you test positive, you aren’t allowed to come in until you test negative.
You asked how we’re handling it, and I can tell you that we’re doing the first one at [my company], and I would recommend utilizing the second one for any in-person company events. That’s it. No mandates. Anything beyond that will lead you into a logistical nightmare (at best), foster a false sense of security as it isn’t effective (worse), and in my humble opinion, is purely unethical (worst of all, which I’d like to think is a decent enough reason not to do something) at this stage.
So anyways, all of the above is the summary of my current POV. What follows below is/are the supporting details for the conclusions I reached in my summary POV 1(a), 1(b), and 2(i) above, if you’re interested in the data.
Always happy to chat/update further as the saga continues ✌
best, [REDACTED]
P.S. if you’re going to skip Parts 1 & 2 below*, then no worries… I get it, I probably wrote far more than you were looking for. But if indeed you do skip them, try to make it to the ‘Closing Thoughts’ section way down below — I’ve sourced a nifty chart down there that might give your colleagues pause in their ongoing discussions about mandates before they consider the unvaccinated to be idiots for whom behavioral mandates are the only appropriate solution.
*Though I highly recommend Part 1 (where it says “TWO OTHER THINGS TO CONSIDER” (then scroll to find #2)) as this contains a suggestion for how to naturally protect yourself from COVID-19.
===================
PART 1: RISK OF COVID-19 DEATH —> DE MINIMIS FOR ME
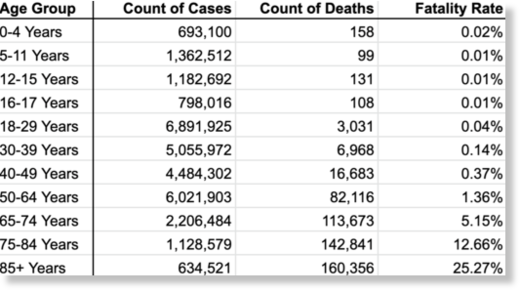
First I’ll address why I do not view COVID-19 as dangerous for me personally: from the CDC’s own data, available here, you can see current the Count of Cases and Count of Deaths by age ->
(Though before I go further, pardon me for abstaining from a lengthy discussion on the reliability of data from an organization that even Dr. Deborah Birx herself — (an individual who received a Meritorious Service Medal from the U.S. Department of Defense in 1991 and a Medal of Excellence from the CDC in 1994) — was quoted as saying she didn’t trust a single word from. Hmm, I wonder why she didn’t “trust” the data, could it be because they were —> overinflating “COVID-19 deaths”? <—… I digress.)
Anyways, according to the CDC, being 32, my “risk” stands at 0.14% (purely averages speaking, irrespective of the analysis below); a “starting statistic” you could call it.
The immediate issue with this data, unfortunately, is we’re only able to count cases with confirmed COVID-19 PCR (or other) test results, undercounting materially true case counts to date. As you might imagine, those asymptomatic do not test themselves regularly or out of nowhere. I mean, personally speaking, I am obviously not testing myself on any basis on any cadence — I’d only get tested if I had reason to. Thus is the reason, that the CDC already stated well early on in this pandemic that true case counts were “likely” to be upwards of 10x higher than we have documented (which they concluded based on widespread antibody testing).
Deaths in the U.S., on the other hand, are religiously tested for COVID-19, capturing the vast majority (if not nearly all) deaths, where a COVID-19 infection was present.
Using these two bits of information from the CDC, we can adjust for a “truer” baseline risk. Now, while I could exercise the luxury of taking on more than a 10x spread (because those younger tend to be more asymptomatic), I’ll be conservative just for the sake of it and just use the “10x average” figure. And so, a true starting statistic for me isn’t 0.14%, but a markedly lower 0.014%.
Next, we can use Exhibit B, taken right from the CDC website:
For… 5% of… [COVID-19] deaths, COVID-19 was the only cause mentioned on the death certificate. For deaths with conditions or causes in addition to COVID-19, on average, there were 4.0 additional conditions or causes per death.
Again, this is nothing new and has been known since very early in the pandemic, as you can see from this study for example listing the leading comorbidities as measured in NY as early as April 2020:

And herein lies my second issue with folks who preach to me that vaccines are necessary for my survival (the first being my initial lowly baseline risk).
Knock on wood, but I have no non- COVID-19 induced comorbidities — zero. My takeaway is just that: for someone like me, COVID-19 is mostly a virus known to exacerbate serious pre-existing conditions to the point of overwhelming the system definitively.
Put another way, imagine a motorcycle rider trying to assess their risk of death from riding (i.e., catching COVID-19). They see a study which puts the risk of death for those motorcycle riders who were (1) drunk (2) doing a wheelie on the highway (3) during a rainstorm, and (4) while texting with a friend (i.e., analogous to four comorbidities). It would be flawed reasoning for a rider who doesn’t do any of those things to put themselves in the same risk category as those who do. So while no one is saying motorcycles aren’t dangerous — they certainly are — they’re nowhere even in the vicinity as dangerous as riding while doing all the other things. Likewise, neither should a healthy teenager dwell on their COVID-19 risk with the same fervor as a 100 year-old morbidly obese individual with terminal cancer.
Okay, let’s revisit my personal risk again. First, I will ignore the 5% “no comorbidities” statistic above, because out of fairness I want to account for likely COVID-19 induced comorbidities like Respiratory Failure, Sepsis, etc. as well as possible ones like Renal Failure, Cardiac Arrest, and the like. So, let me simply reduce my risk not by 95%, but 57% (conservatively even rounded down further to a clean 50%), which removes just 1 non- COVID-19 induced comorbidity for my age group.
And just like that, my adjusted risk is downgraded to 0.0069% annually (annually, because it’s only once a year — after which time a better-than-vaccination natural immunity kicks in for that season).
So what really is 0.0069%, you might ask? After all, we humans aren’t terribly good with numbers like that. To help you put it in perspective, consider that according to the National Highway Traffic Safety Administration, your (or my) risk of dying from a freak car accident in any given year, is 1 in 5,407 or 0.018%.
Let that sink in: based on what we know today, I personally am 268% more likely to die in a car accident tomorrow (or any day this year) than COVID-19. But do you really think that in pre-pandemic times, the “1 in 5,407” statistic kept me locked up inside my house? You think even today (in the middle of a pandemic) that figure stops me from taking a leisurely drive to grab ice cream with my nephews? or catching a movie with my brother? or — God forbid!! — hanging out with and actually talking with my friends? No!, and it never could. Because life, my friend, is about dancing in the summer rain, not cowering in fear of getting struck by lightning. But hey, maybe that’s just me…
In any case, I want to come back to your comment about concerns your colleagues have regarding young children. When we look at the statistics available (table above), the results are even more stark: for kids aged 5-11, their odds of a fatal COVID-19 infection are 1 in 137,000 when you factor in asymptomatic cases. And again, we’re talking about a risk inclusive of those with comorbidities. For kids 5-11 who are perfectly healthy, you can consider their risk nil. Okay, well obviously it could never be actually zero, because we both know sometimes kids also fall off a bike and kill themselves — that’s life. But you don’t exactly see people running around freaking out over bicycles all day long, do you? Which is ironic as hell now that we’re on the subject, considering almost exactly the number of kids have died from bicycles as from COVID-19 in the same time frame.
So when I hear about folks taking their kids for a bike ride on the weekend (how awful), or worse!, maniacally driving their kids for ice cream (putting those precious kids at 5,091% (51x) the risk of death as COVID-19), but then trembling at the thought of walking into an office the following Monday because there’s an unvaccinated person there, so they feel the need to demand forcing medical decisions on those people (like getting jabs with vaccines made by companies whose rap sheets (Pfizer, J&J) would satisfy essay requirements at most colleges, approved by an organization that finds safety issues in 1/3 of its drugs post-approval), I come to the simple conclusion that common sense has left the building — it’s mass hysteria.
Alright, enough beating the completely de minimis personal risk dead horse because the point is clear. But let me add two more small things before getting to the dangers of the vaccine:
TWO OTHER THINGS TO CONSIDER
The section above looked at the whole thing purely from a mathematical risk perspective with neither proactive measures in mind, nor accounting for simple and effective (though IMO criminally suppressed) treatment options available to thwart COVID-19 risk even further.
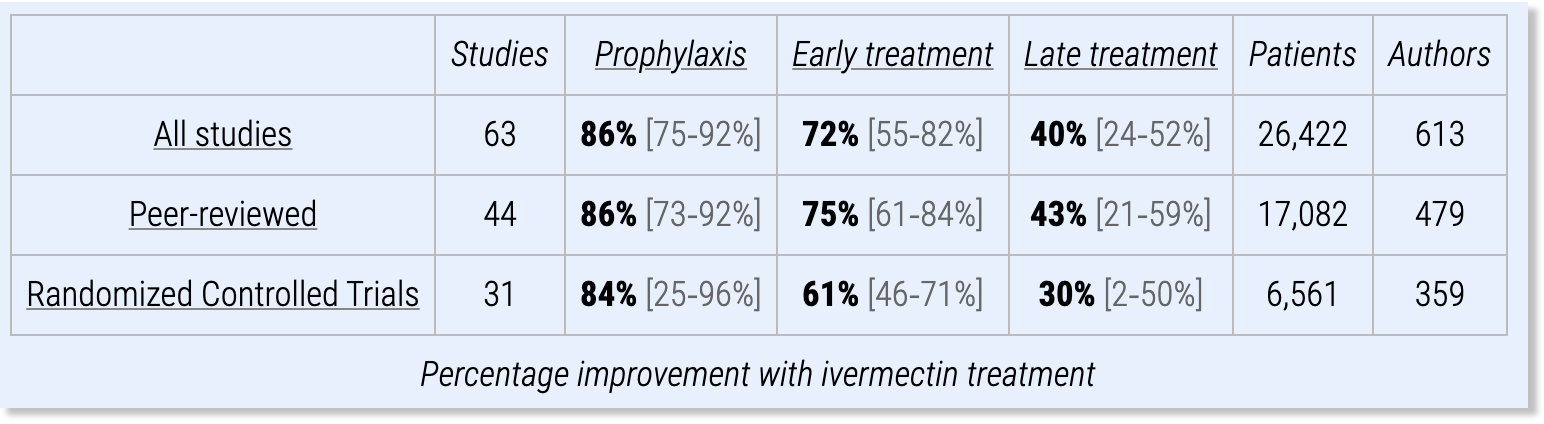
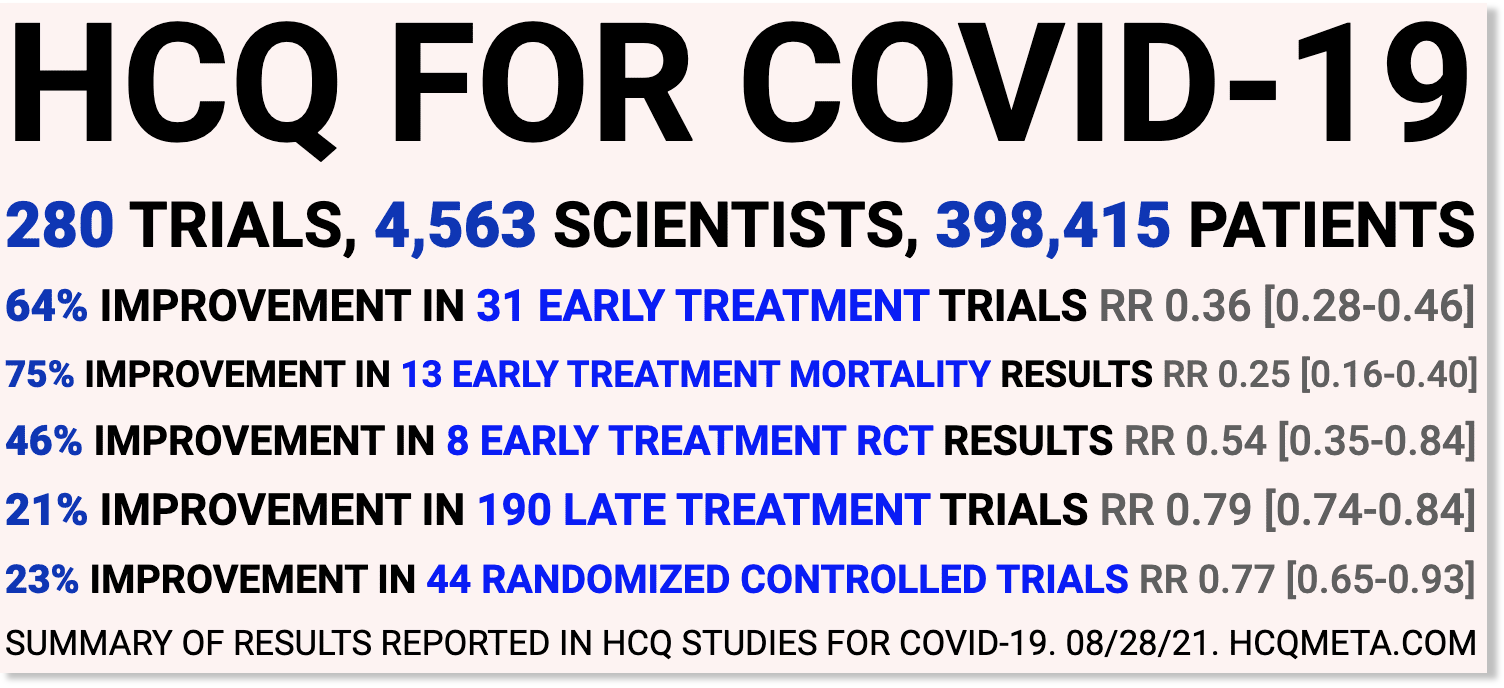
(1) First, on the treatment side. Look, I know there was the whole “orange man (Trump) bad, the FDA disagrees” political BULLSHIT thing going on. Like I said above, I do not give a shit about the political angle of any of this. I require data, and the data could not be more ironclad on the subject matter. I will simply leave these two links here, and avoid another 5 pages in this POV on why IMO this is being criminally suppressed by federal agencies:
First, Ivermectin (links to the studies: (Link A & Link B)). Summary table as follows:
Second, Hydroxychloroquine (link to the studies). Summary table as follows:
By the way, it is worth noting I have a friend right now who has COVID-19. He has felt like shit for the past week. I sent him the studies, and he bought Ivermectin 3 days ago without a prescription from a local store I pointed him to. After a week of feeling like shit, it took him less than a day to get close to symptom free. But hey, I am not a doctor, and “your mileage may vary.” There are a dozen other treatments in addition to the ones above that aren’t getting approved for mass application, either. Go figure.. I could send you the studies if you want, but anyways let’s move on.
(2) As it pertains to the proactive side — okay, sit tight because I’m going to perform a holy miracle here and give you one of several simple things you can do to essentially ensure never needing to worry about COVID-19 again. Not for you, not for the kids, and not even for the neighbor’s dog. Ready? Okay drumroll please… . Did you catch that? If you didn’t, I’ll decipher it for you. It’s your new friend Vitamin D.
If you’d like dozens more studies on this subject, let me know, but start with this good summary I just found for you here — it’s worth a full read, but two pretty charts from the link sum it up:
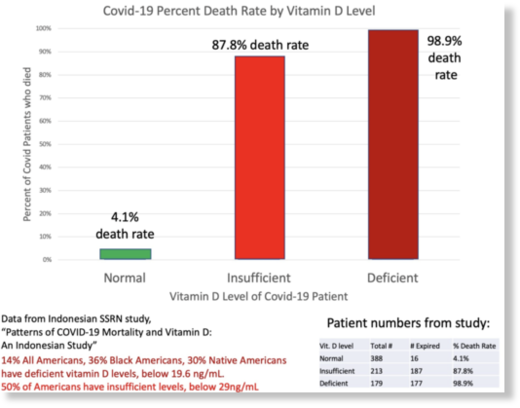
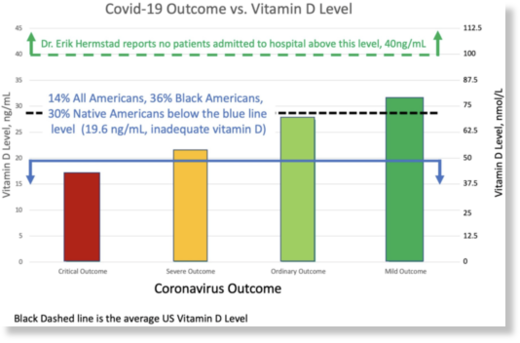
The first study is striking all on its own and worth internalizing, but unfortunately it did group an entire category called “normal” into a single bucket. FYI “normal” is what the medical world considers to be ~20ng/mL. But that’s all it is as a level: normal… but far from what we want, which is excellent.
That’s where the second study becomes helpful. It puts the explosive nature of the findings into real perspective: at levels of 25ng/mL in the study, no severe or critical hospitalized outcomes were observed. While at levels of 40ng/mL or greater, there were not even hospitalizations.
Now personally, I regard it as nothing less than a crime against humanity that neither the WHO nor CDC are PUSHING these (and dozens other peer-reviewed studies on the subject) onto the forefront of our collective media screens. But as for the reason, I must digress, because again I could go down a long and nasty rabbit hole about perverted incentives in the system in terms of why you likely haven’t seen them.
In any case, here’s what is just so awesome for me… remember when we concluded I had a higher risk of crashing & dying from my trip to the local ice cream shop than from COVID-19? Well, it just got a WHOLE lot better, because my Vitamin D levels happen to be considerably well above 40ng/mL. Which means we need to be honest with ourselves and admit that I effectively have a ZERO clinically observed risk of death from COVID-19. I mean shit…. at this point really the only way I can die of COVID-19 is by having it and then getting into a car accident. Then sure, I will die “with COVID-19” (and, as you’ll recall from the link above, they would count it!).
So my advice is as follows: get your dang sunshine first thing in the morning. Do not lockdown. In fact, I’d argue it’s what caused so many deaths. People were heavily Vitamin D deficient from sitting at home all day, and it literally increased their risk of death instead of reducing it. And what the CDC did in this regard was at best negligently or at worst intentionally, criminal, and I have nothing but disdain for the way they went about that. Don’t even get me started on the youth suicides it led to, the increases in domestic violence, increases in drug overdoses, infanticide, denial of healthcare, and let’s not dismiss the whammy of the sheer economic devastation to jobs and small businesses the world over, the bleak economic prognosis for the poorest (how convenient), and the future impact of staggering U.S. debt right here at home. All caused by the incompetence or criminality of the CDC and WHO.
Honestly — my personal advice if you want to stop worrying about COVID-19 for the rest of your life (if you still even are), would be to follow the Dan Miller protocol. Each of his bits of advice is like an extra layer of bulletproof glass on top of Kevlar against COVID-19. And remind your colleagues, too, to stop relying on the “American way” of taking a pill to solve all their problems and blaming the unvaccinated. That is not only completely debunked now as I’ve demonstrated throughout, but it is weak morally. It’s high time we all do the hard self-work of making ourselves physically resilient, and stop feebly making outward demands of others to inject into their bodies vaccines that are only now being tested, in vivo, on large numbers of human beings.
Speaking of which… perfect segway.
===================
(VERY BRIEFLY) PART 2: LONG-TERM RISKS OF [SPECIFICALLY] THE COVID-19 VACCINE –> HIGH
As I’m sure you’ll remember, a while back I mentioned I would send you a thorough, synthesized summary outlining the dangers of the COVID-19 vaccines and how the risks they carry far outweigh the risks of the virus itself. Unfortunately, I am not even a fraction of the way through the hundred plus pages of medical literature showing that conclusion — I’m still working through it. I absolutely feel terrible for not having lived up to my promise, though I’m sure you can appreciate the sheer herculean nature of synthesizing 7 months’ of research involving almost a thousand individual pieces of data, and weeks’ worth of video testimonials by researchers, all into something “succinct and digestible”, all the while working on [my company] in the middle of it all.
In any case, it would be disingenuous of me if I didn’t at least provide a sneak peak of a random assortment of links I had handy for why I will not get the vaccine (aside from the fact that COVID-19 poses no risk to me, per the first section):
- Imperfect Vaccination Can Enhance the Transmission of Highly Virulent Pathogens (bad for me, terrible for society; moral obligation not to partake in this)
- Is a Coronavirus Vaccine a Ticking Time Bomb? (Spoiler alert: likely is)
- A Pathologist Summary of What These Jabs do to the Brain & Other Organs
- Might COVID Injections Reduce Lifespan?
- MIT & International Journal of Vaccine Theory, Practice and Research: Worse Than the Disease? Reviewing Some Possible Unintended Consequences of the mRNA Vaccines Against COVID-19
- How COVID-19 Vaccine Can Destroy Your Immune System
- The Inanity of RNA Vaccines For COVID-19
- New Report Sheds Light on Vaccine Doomsday Cult (sketchy website, but well explained content. I suppose even a broken clock can be right twice a day…)
- Children 50 TIMES More Likely to Die from Covid Vaccine Than From Virus (from the former CSO of Pfizer)
- Pfizer vaccine in Israel: Mortality rate ‘hundreds of times greater in vaccinated young people’
- Are COVID shots fueling more dangerous mutations?
- Less than a third of delta variant deaths are in the unvaccinated (not really an article regarding vaccine dangers, but more so inefficacy)
- +1,000 additional articles, papers, studies, you name it that I could send anyone that wants the full dump of ’em (unsynthesized, of course)
Some bonus links in your spare time that caught my eye in just the past week:
- Fun Quick Video: Mt. Vernon, IN School Board Meeting (though he got a couple things wrong, some points are good food for thought)
- Podcast: The High Wire — A Sea of Lies (in depth discussion about perverse incentives driving bad decisions by the CDC (particularly the second half of the video))
- Podcast: Objective:Health – Study on the Adverse Effects of the Pfizer Vaccine (in which the presenters discuss a paper by the same name).
- Short & Sweet: Why non-lethal pressure on the virus is bad (versus natural immunity) -> Part 1 | Part 2
- +100 more videos and podcasts on the subject to anyone who asks (unsynthesized, of course)
===================
CLOSING THOUGHTS
If you made it this far and checked out even any of the content, kudos. Most folks here in the Northeast stop listening to me once I say “hey, there’s something not right here in this data” or “I’m not too worried about COVID-19 personally”. They think I’m a nut. Now, if you’ve made it this far and checked out most of the content, then I already know you’re starting to wonder if you’re losing your mind, because boy do I have a club pass with your name on it, if you’d like one.
Alas, contrary to popular belief it’s far from a nut club, despite how strong the external pressure is these days to try to make it out to be the case. Rather, It’s a club filled with precisely the very people who we’re supposed to be listening to as a society:
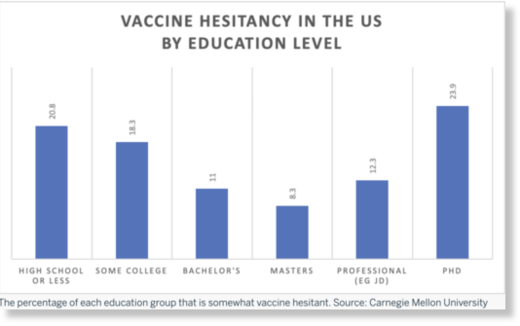
Source: https://www.medrxiv.org/content/10.1101/2021.07.20.21260795v1.full.pdf
AKA: a twisted rendition of the Dunning-Kruger effect in action
The CDC would have you believing it is just the crazy and uneducated who are most wary of their (and the FDA/WHO’s) conclusions — you know, it’s all the rednecks down south! And they’re right, it is the uneducated (left of the chart). But it is disingenuous for them to try and ignore on the nightly news research like this out of Carnegie Mellon suggesting the biggest group of those most vaccine-hesitant happen to be the smartest folks in the world — the ones I’ve certainly not been ignoring, despite their being shamed, cancelled off of social media, and publicly silenced.
Put another way, I would only posit the simple question of when in the history of the world have you ever had thousands of scientists, doctors, and researchers, some of the brightest minds* in their fields around the world sounding an alarm, and the official response be to label them all as batshit crazy and prevent them from speaking? Hint. Personally, I can’t support it. A free society must allow all open discussion without ridicule well before we dare discuss collectively forcing medical decisions on people using actual threats against their autonomy. We’re too far past that Vietnam-level of government lying bullshit that results in unholy suffering for society for this barbaric nonsense to continue, and it’s time for this country to start acting like we learned something about the importance of asking questions. I simply cannot place any trust in the idea I’m not being lied to until every scientist worth their salt has had an opportunity to speak up freely, and the nature of their concerns investigated transparently. And neither should anyone else.
*Such a fun fact it is that among this ocean of scientist voices being smeared & erased from history are (1) the guy who helped invent mRNA vaccine technology, and (2) the former Chief Scientific Officer (CSO) of Pfizer (who held that role for 16 years and focused on respiratory illnesses), both of whom are saying we have to stop vaccinations at once for those who aren’t at actual high-risk with COVID, because for everyone else they’re not only toxic & dangerous but will be the very cause of this never ending pandemic. Now I don’t know about you, but I neither invented mRNA technology nor worked at Pfizer for 16 years as CSO, but if I did, I’d sure prefer the American people heard my concerns, you know, sans the childish smear tactics part. Until then, I will not — cannot — accept any mandates on moral grounds.
And so there you have it. My opinion on mandatory vaccinations at this stage: if this were the Bubonic Plague, I’d be the first in line to get the shot. Same for Polio, Tetanus, and a whole lotta other great vaccines. But for COVID-19? Let’s just say I wouldn’t even know what to tell Saint Peter at the Pearly Gates to apologize sufficiently if I — knowing what I know now — supported a mandate. Come to think of it, there’s a quote that comes to mind here that I think is a nice way to wrap up this write-up, and commemorate those who continue to protect the rights of society:
‘The hottest places in Hell are reserved for those, who in time of moral crisis, preserve their neutrality.’ ~ unknown
========
DISCLAIMER –> OBLIGATORY
I obviously have to say this before I sign off.
At the end of the day, I’m not a doctor, I do not have an MD, a Ph.D., or any other useful acronym. All I am is an individual who values truth above hysteria & ideology. I will go wherever the truth points me to without regard for what “side” that puts me on. If it’s a contrarian side, then shit I guess I’m going to have to get in some fights. If I’m on the side of the majority, I guess I’ll rest easy. But wherever it is, I’m willing to go there, and as I said in my opening statement and reiterated to the group — I will always remain open to thoughtful and productive dialogue and my POV on every topic is subject to change through lifelong reflection. All I ask for these days is for those who disagree with me to either have the sincerity to work with me using the scientific method to get the facts on this subject, or if they have no interest in that, to let me do it alone without the constant coercion, which is how I’m sure the folks in your office who are unvaccinated, feel.
Anyways, for the actual disclaimer part: we all have to make our own decisions, do our own research (though I’m always happy to keep sending stuff I come across), and take our own risks. Freak accidents can happen, and just like I wouldn’t want to be responsible for a car accident that happens if you decide to go to a particular ice cream shop I recommend, it is the same for anything I’ve sent above and anything you or anyone you may share any of the information with do as a result of it. Always seek and follow professional, accredited advice! <– the disclaimer part.
Anyone who sees the vaccine as having more benefit than risk, should absolutely take it. I agree 100% with an 85 year-old with five comorbidities getting the jab — shit if that was me, I’d be getting quadruple jabbed walking around with a gas mask. No really, I would. Because for them the virus is actually very dangerous. And I’ve recommended it for some that I know personally would benefit from the vaccine because they are at high risk. But that’s where it ends. And not a single, inch, further.
The optimal diet for longevity and weight loss?
By Sebastian Rushworth, M.D. | August 29, 2021
It started with an experiment on locusts in 1991. David Raubenheimer and Stephen Simpson, two zoologists who were at the time doing research at Oxford University, wanted to know what would happen to locusts if they varied the relative proportions of protein and carbohydrate in their diets. They therefore conducted an experiment in which they fed locusts pellets containing varying proportions of protein and carbohydrate, and the results astounded them so much that they ended up determining the course of their research over the next thirty years, which they’ve chronicled in their book, Eat like the animals.
What Raubenheimer and Simpson found was that the locusts were not eating until they’d satisfied their overall need for calories. Rather they ate until they’d satisfied their need for protein, so that overall, all the locusts were consuming the same total amount of protein. This meant that the locusts on the high protein diet were consuming much less food overall than the locusts on the low protein diet. Consequently, the locusts on the high protein diet became extremely lean, while the locusts on the low protein diet became fat (which they describe in their book as equivalent to an overweight knight squeezing in to a suit of armour that is a few sizes too small).
This led Raubenheimer and Simpson to conclude that protein is the dominant macronutrient in terms of determining how much we eat – At least if we’re locusts. They wanted to see if the same pattern would be seen in other species. They started off with flies, and the results were similar, which was encouraging. But flies and locusts are relatively closely related, at least in the sense that they’re both insects. What Raubenheimer and Simpson really wanted to know was whether they’d stumbled on a general dietary principle, that could be applied to all animals.
For reasons of practicality, they next chose mice. Unlike locusts and flies, which subsist pretty much entirely on protein and carbs, mice also eat fat, so in order to get a full understanding of how macronutrients impact body composition, this variable also needed to be part of the experiment. Additionally, Raubenheimer and Simpson wanted to increase the scope of their research, to look not just at the effect of various macronutrient combinations on body composition, but also on longevity. They were also curious to see what effect differing levels of dietary fibre would have on the mice.
The experiment took five years to carry out. 856 mice were sorted in to 25 different groups, that were fed identical pellets but with varying compositions of protein, fat, carbs, and fibre. They were followed from birth to death. In terms of body composition, the results were largely as expected. The mice fed a high protein diet all became lean and muscular. When it came to the mice fed a high carb diet, however, there was more variation. Those on a high carb diet that was low in fibre grew fat, while those on a high carb diet that was high in fibre remained slim.
The fact that fibre mattered so much to the body composition of the mice on a high carb diet is interesting. It provides a reasonable explanation for why people in traditional agrarian societies usually aren’t fat, even though their diets are very high in carbohydrates, and for why the current obesity epidemic coincided with a massive increase in intake of processed foods that were rich in carbs but lacking in fibre. It also provides an explanation for why people are able to lose weight both on a paleo/carnivore/keto diet that is low in carbs, and on a vegan diet that is high in carbs but also high in fibre. Fibre appears to provide a kind of “get out of jail free” card that lets you consume lots of carbs without becoming fat.
What about fat? Fat was found to be neutral in terms of it’s effect on how much the mice ate. In other words, fat intake didn’t have any limiting effect on appetite, so the mice on a high fat low protein diet grew fat, just like the mice on a high carb low protein diet that was low in fibre. If this result were to apply also to humans (which is, of course, not necessarily the case), it would suggest that LCHF/keto diets don’t work because people are replacing carbs with fat, but rather because they’re replacing carbs with protein.
Ok, so we know how the various macronutrient combinations affected body composition. What about the effect on life span? Here, the results as presented in Eat like the animals surprised me. Alot. The longest lived mice, according to Raubenheimer and Simpson, were the ones following a high carb low protein diet. Whether they ate a high or low fibre diet didn’t seem to matter. So the fat high carb mice were actually living longer than the lean, muscular high protein mice!
Baffled by these results, I decided to go and take a look at the data, to confirm that they weren’t just trying to pull a fast one, as nutrition researchers so often do when presenting their research. Hidden away in the supplement to the published study, is this table:

Two things immediately jump out at me. The first is that the group with the longest median lifespan was on a 42% protein diet. Hardly low protein!
If instead of looking at the median lifespan, we look at the maximum, we get a different picture. We see that the extremely low protein mice did best. But their median lifespans were far more average. The authors have obviously based the claims in their book, and in their published research article, on the maximum lifespan, rather than the median. That is something I find very odd.
Personally, I assume I’m going to live an average amount of time for people like me, following my type of lifestyle. I don’t assume I’m going to be the outlier who lives to 120! The median provides a much better picture of the effect of a diet on a group than the maximum lifespan seen in a few individuals.
Apart from that, they’ve chosen an odd definition of maximum life span. They’ve defined it as the top 10% with the longest life span in each group. Which is suspicious. Why the top 10% rather than just the top individual, which would be the more common way to define “maximum”? And why not the top 20%? Or top 30%? The definition really seems to have been chosen specifically because it gave the desired result, which is what is usually referred to as “torturing the data”.
I can only imagine that they chose to base their claims on their odd definition of the maximum rather than on the more appropriate median because the maximum showed a picture more in line with their own biases, possibly shaped by an environmental or animal rights agenda, or by the fact that it’s easier to get research published if it feeds in to the dominant dogmas.
The second thing that jumps out from the table is that the mice eating a high fibre diet (i.e. with a low energy density) lived much shorter lives than the other mice. That is by far the biggest difference, much bigger than any difference induced by varying protein or carb concentrations. Does this mean fibre is deadly and should be avoided it like the plague?
Well, no. The pellets that the mice were fed only contained one fibre, cellulose, which is hardly representative of the full spectrum of fibres that exist in real food. So it’s impossible to draw any conclusions from this about the effects of fibre on longevity. What we can say is that cellulose appears to be toxic to mice.
Next, I took the data from the table and re-tabulated it in a form that would allow for easier analysis of the data, which you can see here:

So what we see is that the low protein mice do appear to live the longest, but the differences between the groups are small and hardly linear. The difference between the 5% protein mice and the 42% protein mice is only 2 weeks, equivalent to about a year and a half if translated to a human lifetime. Since there’s no evidence of a linear relationship between protein intake and life expectancy, it’s hard to say that that result isn’t just caused by chance.
If we move on to carbs, then it again isn’t clear that the high carb diet leads to a longer life. The longest lived group is actually the one consuming a moderate 29% carbs, and again, there is no evidence of a linear relationship. The same is also true for fats.
So overall, the claims the authors make about a high carb low protein diet resulting in the longest life expectancy don’t hold up to close inspection. They’ve tortured the data until they’ve gotten the result they want.
What can we conclude?
If you want to be lean, muscular, and beautiful, then you should eat a high protein diet. If you just want to lose weight and be slim, then you can either go high protein or high fiber, or do a combination of both.
Well, as long as you’re a lab mouse, that is. Whether all of this also applies to humans is harder to say for certain. The results from the experiments mentioned here and others have led Raubenheimer and Simpson to develop the “protein leverage hypothesis” of obesity, which basically states that the modern obesity epidemic is due to the fact that modern diets are lacking in protein and fibre. This has come to be one of three main hypotheses that try to explain the rise in obesity. The other two are the “carbohydrate-insulin model”, which argues that the rise in obesity is due to the high consumption of carbohydrates and their downstream effects on insulin levels and thus body fat storage, and the traditional “calories in vs calories out model”, which argues that the rise of obesity is due to the fact that modern foods taste too good and are too readily available while our lifestyles have become too sedentary. From my perspective, Raubenheimers and Simpson’s hypothesis is the one of the three that fits the known facts the best. Their book, Eat like the animals, is therefore well worth a read, even though the claims they make about diet and longevity are unsupported by the evidence they present.
VACCINATION: THEY’RE BECOMING DESPERATE
Computing Forever | August 21, 2021
Support my work here: https://computingforever.com/donate/
Support my work on Subscribe Star: https://www.subscribestar.com/dave-cullen
Follow me on Bitchute: https://www.bitchute.com/channel/hybM74uIHJKf/
Buy How is This a Thing Mugs here: https://teespring.com/stores/computing-forever-store
Source links:
https://www.irishmirror.ie/news/irish-news/irish-community-mourning-tributes-paid-24786114
https://www.which.co.uk/news/2021/08/travel-croatia-austria-vaccine-expiry-booster/
http://www.computingforever.com
KEEP UP ON SOCIAL MEDIA:
Gab: https://gab.ai/DaveCullen
Subscribe on Gab TV: https://tv.gab.com/channel/DaveCullen
Minds.com: https://www.minds.com/davecullen
Subscribe on Odysee: https://odysee.com/@ComputingForever
Recent drone strikes in Afghanistan prove ‘Over-the-horizon’ is just a buzz phrase for US incompetence
By Scott Ritter | RT | August 31, 2021
Following the Kabul airport attack, the US military conducted two “over-the-horizon” air strikes against suspected ISIS-K targets. The results inspire zero confidence in the efficacy of this approach toward counterterrorism.
The August 26 suicide bombing outside Hamid Karzai International Airport in the Afghan capital killed more than 150 people, including 13 American troops. The Islamic State-Khorasan, or ISIS-K, claimed responsibility for the attack.
That night, in a televised address to the American people, President Joe Biden declared “We will not forgive. We will not forget. We will hunt you down and make you pay,” adding that the US “will respond with force and precision at our time, where we choose and when we choose.”
The next day, August 27, the US carried out what it termed an “over-the-horizon” attack against an ISIS-K “planner” and “facilitator” at a home in the city of Jalalabad in Nangarhar Province in eastern Afghanistan, killing both men and, according to the US, wounding a third accomplice.
US defense sources sources said the men were killed by a special variant of the Hellfire missile, known as the R9X, or ‘flying Ginsu’, a reference to the six blade-like devices which emerge from the missile, killing its target by cutting it to shreds in lieu of the normal high explosive payload carried by the Hellfire. The R9X was developed specifically to handle situations such as the one in Jalalabad, where legitimate targets have taken refuge among a civilian population.
According to reports, the “planner” and “facilitator” were traveling in a three-wheeled vehicle common to the region as public transportation. The men were tracked by an MQ-9 ‘Reaper’ drone which maintained sufficient “eyes and knowledge” of the target to confirm their identities. The three-wheeled vehicle entered a compound believed to be the home of the “planner.” Reportedly, US personnel monitoring the live video images coming from the MQ-9 drone waited until the planner’s wife and children left the compound before launching the ‘flying Ginsu’.
“Initial indications are that we killed the target,” a CENTCOM spokesperson said. “We know of no civilian casualties.” The strike was reportedly authorized by President Biden and ordered by Secretary of Defense Lloyd Austin.
The US assertions about casualties were contradicted by a Jalalabad community elder, Malik Adib, who declared that three people were killed and four were wounded in the drone strike, noting that “women and children are among the victims.”
If the statements of Malik Adib are to be believed, then something went very wrong with the analysis of the imagery used to justify the launching of the missile. While no one has questioned the validity of the US claims that the targets struck were in fact affiliated with ISIS-K (while keeping in mind the US has provided no evidence that corroborates its claim that they were, in fact, ISIS-K operatives), either someone is lying about waiting for the wife and children to leave, or there were other civilians in the vicinity of the attack, one of whom was killed.
Before the media could press the Pentagon about the apparent inconsistencies in the official US account, however, the US launched a second drone strike, this time targeting a vehicle in Kabul, eliminating “an imminent ISIS-K threat” to Hamid Karzai International Airport. According to US officials, the existence of a “large secondary explosion” at the scene of the attack confirmed the assessment about the existence of a car bomb. It is not known if the US used a conventional Hellfire or one of the non-explosive RX9 variants in the attack.
According to unnamed defense sources, the alleged ISIS-K operatives inside the vehicle had been observed placing what was assessed to be a considerable amount of explosives in the trunk of a white Toyota Corolla, before driving the vehicle into the driveway of a home located near the airport. The decision was made to strike, resulting in the destruction of the vehicle. US officials claimed that at least one ISIS-K suicide bomber was killed in the incident. Allegedly, nine civilians also perished as a result of the attack.
“We are aware of reports of civilian casualties,” Major General William Taylor, a spokesperson for the Joint Staff, told the media on Monday. “We take these reports extremely seriously.”
The driver of the vehicle, Zemari Ahmadi, did not fit the profile one would expect of an ISIS-K suicide bomber. Zemari worked for an American-based charity called Nutrition and Education International.
According to his family, he was on his way home from work after dropping off colleagues on Sunday evening. As he pulled into the driveway of his home, where he lived with three brothers and their families, the children of his relatives ran out to greet him. The missile believed to be launched by the American drone struck the rear of the vehicle, killing Zemari and nine others, including seven children, the youngest of whom was two years old. Also killed was Zemari’s nephew, Ahmad Naser, who had previously served as a guard at a US military facility in Herat, and who was awaiting final approval of his Special Immigrant Visa paperwork so that he could leave Afghanistan.
“No military on the face of the Earth works harder to avoid civilian casualties than the United States military,” Pentagon spokesman John Kirby said after reports emerged about possible civilian casualties. “We take it very, very seriously. And when we know that we have caused innocent life to be lost in the conduct of our operations, we’re transparent about it.”
Kirby went on to suggest that the civilians were killed as a result of the detonation of the explosives alleged to have been contained in Zemari’s vehicle. At a later press conference, Kirby maintained this position, but refused to release any imagery that would sustain his contention of a powerful secondary explosion.
The drone strike that killed Zemari Ahmadi and his relatives represented the very scenario the Biden administration was trying to avoid when setting up the “over-the-horizon” strike capability used in the two responses to the suicide-bomb attack on Kabul Airport.
Back in April, when the totality of the failure that was to mark the US withdrawal from Afghanistan remained unknown (although not unknowable – many military and intelligence professionals anticipated the collapse of the Afghan government, but the Biden White House overrode their concerns in favor of better “optics”), General Frank McKenzie, the Marine commanding US Central Command, responsible for all US forces deployed in the Middle East, Central and South Asia, testified before Congress about his command’s efforts to conduct “over-the-horizon” counterterrorism missions once the US drawdown in Afghanistan was completed.
CENTCOM had a long history of conducting “over-the-horizon” (OTH) operations in support of its counterterrorism mission, using a mix of special operations commandos (i.e., the Bin Laden and Abu al-Baghdadi assaults), manned aircraft (the airstrikes against pro-Iranian militias in Syria and Iraq), and drone strikes, such as that carried out against Qassem Soleimani at Baghdad International Airport in January 2020.
“I don’t want to make light of it, I don’t want to put on rose-colored glasses and say it’s going to be easy to do,” McKenzie told the House Armed Services Committee. Any OTH operations in Afghanistan in a post-US drawdown, McKenzie noted, would require significant intelligence support at a time when US intelligence collection capabilities in Afghanistan were diminished to the point of non-existence. “It will be harder to do that, it is not impossible.”
The bulk of the burden of maintaining this OTH capability would fall on the US system of armed drones, which in the past operated from bases inside Afghanistan, providing them with greater reaction time and longer loiter time over the target. Any post-Afghanistan operation of drones in support of OTH operations would mean operating from bases outside of Afghanistan.
According to acting Air Force Secretary John Roth, the US planned on using existing bases in the region to host the drones, noting that the US operated from Al Udeid Air Base in Qatar, Al Dhafra Air Base in the United Arab Emirates, and Kuwait’s Ali Al Salem and Ahmad al-Jaber air bases. The cost of maintaining this OTH capability for fiscal year 2022 was expected to run somewhere around $10 billion.
The Biden White House engaged in a policy review of OTH operations, temporarily placing limits on counterterrorism drone strikes and commando raids, and tightening the approval process for such missions, which had been loosened under the Trump administration.
Biden, according to press reports, was particularly sensitive to the need to limit civilian deaths as it looked into how it would respond to future terrorist threats from Afghanistan and elsewhere in the Middle East. The decision was made to continue the program of drone-based assassination/pre-emptive killing but restrict the ability of field commanders to make the final decision, instead requiring White House permission before any OTH attack could occur.
The MQ-9 drones that were involved in the Jalalabad and Kabul drone attacks were operated out of Al Udeid Air Base in Qatar. The MQ-9 system, however, operates according to what the Air Force calls “remote split operations,” which employs a launch-and-recovery ground control station for takeoff and landing operations at Al Udeid, before passing control of the MQ-9 to a crew based out of Creech Air Force Base in Nevada, which takes control of the aircraft for the remainder of the mission using satellite communication links.
Traditionally, an MQ-9 crew consists of a pilot and a sensor operator, who employ what is known as the Multi-Spectral Targeting System, which integrates an infrared sensor, color/monochrome daylight TV camera, image-intensified TV camera, laser range finder/designator, and laser illuminator, all of which can be viewed together or separately on display screens set up in front of the crew.
The MQ-9 would usually operate as part of an overall “intelligence surveillance reconnaissance” (ISR) package which used a variety of intelligence collection resources to identify and track potential targets. The US drawdown in Afghanistan, however, eliminated most if not all of the supporting infrastructure normally available to the MQ-9 crew to discriminate targets. To help compensate for this loss of capability, the US Air Force developed a special signals intelligence (SIGINT) pod that could be carried by the MQ-9 that provided full-spectrum SIGINT capability to the drone operators, who could now search for, identify and track signals of interest, such as the cell phones, walkie-talkies or satellite phones that comprise the communications network of terrorist organizations like ISIS-K. To better employ this capability, the MQ-9 crew would be supplemented by a linguist who could listen in real time to any conversations of interest, helping with the evaluation of potential targets in terms of both identity and intent.
Intelligence, properly done, is a combination of art and science which requires those involved to be true subject matter experts in the mission they have been given. Imagery analysts need to understand not only what it is they are seeing, but also what it means. Likewise, linguists monitoring conversations need not only be fluent in the language, but adept at slang and other colloquialisms used by people in their daily conversations. For this reason, the best imagery analysts and intercept linguists have been doing their respective jobs for years and, in doing so, are adept at sifting out the unusual from the normal.
However, the airmen operating the MQ-9 most likely did not have this level of experience and expertise. By way of example, the vehicle Zemari Ahmadi was driving was allegedly tracked as “containers containing explosives” were loaded into its trunk. While there is no doubt that an imagery analyst witnessed items being loaded into the trunk of the vehicle, the key question is what was in those containers. Basic identification signatures for car bombs include the use of bags of fertilizer mixed with diesel oil placed in the trunk of a car. However, were the analysts trained to know that Afghanistan blocked the sale of fertilizer back in 2010 because of its extensive use as a bomb-making material, and that the terrorists instead began using potassium chlorate as the primary bomb making material, and that potassium chlorate is loaded into containers virtually identical to those used to store cooking oil?
Moreover, experienced terrorist operatives, which you would expect to be operating from inside Kabul, would anticipate that their communications are being monitored, and as such never use specific words or phrases that could trigger interest on the part of anyone listening in. As such, it is highly unlikely that Zemari or anyone he might have been communicating with would have spoken about explosives or the intent to build a car bomb. He might, however, state that he is picking up cooking oil. If an experienced linguist intercept specialist were listening in, he or she would be able to discern if this was part and parcel of normal activity, or a deviation from the norm. An inexperienced linguist, however, would not possess such insights, and be prone to reading into Zemari’s words content and intent that did not, in reality, exist.
It is unlikely the public will ever know the truth about what happened in Creech Air Base that led the MQ-9 crew to believe that their targets were affiliated with ISIS-K. Despite John Kirby’s assertions regarding transparency, the US military and intelligence community is loath to discuss the specifics regarding intelligence collection capabilities. Likewise, to what extent the extended chain of approval was involved in modifying these assessments as they made their way up the White House will likewise most likely remain secret, further shielding all involved from the kind of scrutiny that full transparency demands.
The Biden administration has placed its hopes for containing terrorism in a post-Afghanistan drawdown on “over-the-horizon” strike capabilities that the president and his supporters believe adequate for the task of identifying and interdicting terrorists before they can carry out an attack against US interests, all the while reducing the likelihood of unintended civilian casualties. If the experience in Afghanistan proves anything, it is that OTH is no panacea when it comes to counterterrorism.
It also underscores the reality that the US intelligence community and military is prone to see what it wants to see. The time-tested adage of “if the only tool available is a hammer, then every problem looks like a nail” holds true in every respect when it comes to OTH in a counterterrorism role: when the only tool available is an MQ-9 drone operated by crews who are not up to the task of properly identifying and tracking targets, then the only solution will be a Hellfire missile which, when employed, will more often than not kill innocent civilians.
Revealed, the vaccine safety alert that drugs watchdog is ignoring
By Sally Beck | TCW Defending Freedom | September 1, 2021
FOR nearly a decade, Dr Tess Lawrie, MBBCh, DFSRH, PhD, has run the Evidence-Based Medicine Consultancy, an independent company concerned with rigorous medical research in healthcare.
She produces reports that can be found in the Cochrane Library, a respected organisation providing unbiased scientific paper analyses.
Dr Lawrie is a frequent member of technical teams developing international guidelines in the healthcare sector, and her peer-reviewed publications have received more than 3,000 citations. In short, Dr Lawrie should not be ignored.
Unless of course you are the Medicines and Healthcare products Regulatory Agency, the deaf-eared UK body regulating the novel, experimental, and under-tested Covid-19 mRNA and traditional vaccines.
With vaccine-associated deaths passing 1,600 in Britain, the MHRA should suspend the vaccination programme, like it did after 47 deaths caused by the Pandemrix swine flu jab.
However, it has no intention of doing so and continues to insist that the vaccine is ‘safe and effective and the best protection against Covid-19’.
Dr Lawrie sent Dr June Raine, the MHRA’s chief executive, a 39-page, fully-referenced paper criticising the agency’s complicated Yellow Card Scheme, a government system designed to collate information about adverse events caused by new drugs, as ‘not fit for purpose.’
She reminded Dr Raine, and copied in 15 of her colleagues, that they had a duty to ‘take any necessary action to minimise risk to individuals, after weighing risks against expected benefits.’ She pointed out that because of omissions in their data collecting, such as age and gender, and the timeframe of reaction post vaccination, the Yellow Card Scheme is non-transparent.
She said: ‘These omissions mean that basic conclusions about safety cannot be drawn. Consequently, the public and trial participants are not fully informed of the potential risks of taking a Covid-19 vaccine and are unable to give fully informed consent.’
Dr Lawrie concluded that the voluntary reporting system needed a complete overhaul, saying the Vaccine Adverse Event Reporting System (VAERS) in the US was doing a much better job giving citizens and healthcare professionals detailed information.
From VAERS’ database, she was able to conclude that more than 90 per cent of deaths occurred afterfirst vaccination and there was a clear link between vaccination and death, something MHRA members frequently say they cannot prove and insist is more than likely ‘coincidental’.
Speaking of VAERS, Dr Lawrie said: ‘From that system it is apparent that sporadic event reporting is high in number, as in the UK, and that there is a tight temporal relationship between Covid-19 vaccination and deaths: 15 per cent of deaths occurring within 24 hours, 22 per cent within 48 hours and in 37 per cent of deaths, the patient became unwell within 48 hours of Covid-19 vaccination with an event that led to their death.
‘The deaths analysed followed an almost equal number of Pfizer and Moderna Covid-19 vaccinations, and 91 per cent of deaths occurred after administration of the first Covid-19 vaccine.’
With the AstraZeneca #clotshot, which has not been approved for use in the US, double the number of people are impacted compared with Pfizer.
Dr Lawrie said that, as well as vaccine-induced immune thrombotic thrombocytopaenia (VITT), the European Medicines Agency has identified Guillain-Barreì Syndrome as a potential risk from the AstraZeneca vaccine.
It is adding a warning to the product information that ‘vaccinated persons need to seek immediate medical attention if they develop weakness and paralysis in the extremities.’
In conclusion, Dr Lawrie asked Dr Raine a simple question, yet to be answered: ‘Why is this clear safety signal not being acted upon by MHRA?’
This is an updated report published on August 26, 2021, detailing MHRA Yellow Card Reporting up to August 18:
• Pfizer – 21.3million people, 37.9million doses. Yellow Card reporting rate, one in 199 impacted.
• AstraZeneca – 24.8million people, 48.7million doses. Yellow Card reporting rate, one in 108 impacted.
• Moderna – 1.4million people, 2.1million doses. Yellow Card reporting rate, one in 100 impacted.
Overall, one in 135 people experience a Yellow Card Adverse Event from the 47.5million injected (20.7million men, women and children remain not injected in UK).
The Yellow Card reporting rate may be approximately ten per cent of actual figures, according to MHRA.
Proportional to the number of weeks each brand has been administered, currently the reported toll is:
• Approximately 47 linked deaths reported per week
• More than 10,500 reported adverse event injuries per week with unknown long-term consequences.
A significant proportion of these adverse events require urgent medical care, may be life-changing or long-lasting. These figures represent immense distress for those 351,404 people suffering adverse events and their families.
Reactions: 302,146 (Pfizer) + 816,393 (AZ) + 43,949 (Moderna) + 3,148 (Unknown) = 1,165,636.
Reports: 107,215 (Pfizer) + 229,134 (AZ) + 14,019 (Moderna) + 1,036 (Unknown) = 351,404.
Fatal: 508 (Pfizer) + 1,056 (AZ) + 17 (Moderna) + 28 (Unknown) = 1,609.
Acute Cardiac: 4,831 (Pfizer) + 9,102 (AZ) + 495 (Moderna) + 35 (Unknown) = 14,463.
Pericarditis/Myocarditis (Heart inflammation): 362 (Pfizer) + 245 (AZ) + 65 (Moderna) + 2 (Unknown) = 674
Anaphylaxis: 466 (Pfizer) + 810 (AZ) + 32 (Moderna) + 1 (Unknown) = 1,309
Blood Disorders: 10,283 (Pfizer) + 7,354 (AZ) + 829 (Moderna) + 44 (Unknown) = 18,510.
Infections: 7,116 (Pfizer) + 18,102 (AZ) + 730 (Moderna) + 89 (Unknown) = 26,037
Herpes: 1,574 (Pfizer) + 2,475 (AZ) + 75 (Moderna) + 13 (Unknown) = 4,137.
Headaches: 21,646 (Pfizer) + 83,513 (AZ) + 2576 (Moderna) + 229 (Unknown) = 107,964
Migraine: 2,474 (Pfizer) + 8,015 (AZ) + 284 (Moderna) + 29 (Unknown) = 10,802.
Eye Disorders: 5,025 (Pfizer) + 13,718 (AZ) + 495 (Moderna) + 55 (Unknown) = 19,293.
Blindness: 99 (Pfizer) + 281 (AZ) + 12 (Moderna) + 4 (Unknown) = 396.
Deafness: 185 (Pfizer) + 360 (AZ) + 13 (Moderna) + 2 (Unknown) = 560.
Psychiatric Disorders: 6,135 (Pfizer) + 17,011 (AZ) + 884 (Moderna) + 74 (Unknown) = 24,104.
Skin Disorders: 21,263 (Pfizer) + 50,240 (AZ) + 6,657 (Moderna) + 211 (Unknown) = 78,371.
Spontaneous Miscarriages: 278 + 6 stillbirth/foetal death (Pfizer) + 195 + 2 stillbirth (AZ) + 24 + 1 foetal death (Moderna) + 1 (Unknown) = 499 + 9 (figures imply 20 related maternal deaths – four more this week alone).
Vomiting: 3,242 (Pfizer) + 11,347 (AZ) + 496 (Moderna) + 41 (Unknown) = 15,126.
Facial Paralysis including Bell’s Palsy: 691 (Pfizer) + 860 (AZ) + 48 (Moderna) + 5 (Unknown) = 1,604.
Nervous System Disorders: 52,947 (Pfizer) + 173,935 (AZ) + 6788 (Moderna) + 600 (Unknown) = 234,270.
Strokes and CNS haemorrhages: 496 (Pfizer) + 1,993 (AZ) + 17 (Moderna) + 9 (Unknown) = 2,515
Guillain-Barré Syndrome: 42 (Pfizer) + 388 (AZ) + 2 (Moderna) + 5 (Unknown) = 437.
Tremor: 1,288 (Pfizer) + 9673 (AZ) + 153 (Moderna) + 38 (Unknown) = 11,152.
Pulmonary Embolism and Deep Vein Thrombosis: 601 (Pfizer) + 2,696 (AZ) + 25 (Moderna) + 18 (Unknown) = 3,340.
Respiratory Disorders: 12,950 (Pfizer) + 27,425 (AZ) + 1,138 (Moderna) + 109 (Unknown) = 41,622.
Seizures: 713 (Pfizer) + 1,874 (AZ) + 119 (Moderna) + 9 (Unknown) = 2715
Paralysis: 301 (Pfizer) + 735 (AZ) + 39 (Moderna) + 6 (Unknown) = 1,081.
Haemorrhage (All types): 2,568 (Pfizer) + 4713 (AZ) + 321 (Moderna) + 24 (Unknown) = 7,626.
Vertigo/Tinnitus: 2,692 (Pfizer) + 6313 (AZ) + 271 (Moderna) + 25 (Unknown) = 9,301.
Renal & Urinary Disorders: 795 (Pfizer) + 2,507 (AZ) + 93 (Moderna) + 23 (Unknown) = 3,418
Reproductive/Breast: 17,108 (Pfizer) + 16,689 (AZ) + 2,215 (Moderna) + 120 (Unknown) = 36,132.
For full reports see Annex One.
‘Blood for Blood’: On Jenin and Israel’s Fear of an Armed Palestinian Rebellion
By Ramzy Baroud | MintPress News | August 26, 2021
The killing of four young Palestinians by Israeli occupation soldiers in the Jenin refugee camp in the northern West Bank, on August 16, is a consequential event, the repercussions of which are sure to be felt in the coming weeks and months.
The four Palestinians – Saleh Mohammed Ammar, 19, Raed Ziad Abu Seif, 21, Nour Jarrar, 19, and Amjad Hussainiya, 20 – were either newly born or mere toddlers when the Israeli army invaded Jenin in April 2002. The objective, then, based on statements by Israeli officials and army generals, was to teach Jenin a lesson, one they hoped would be understood by other resisting Palestinian areas throughout the occupied West Bank.
In my book, Searching Jenin, published a few months after what is now known as the ‘Massacre of Jenin’ or the ‘Battle of Jenin’, I tried to convey the revolutionary spirit of this place. Although, in some ways, the camp was a representation of the wider Palestinian struggle, in other aspects it was a unique phenomenon, deserving of a thorough analysis and understanding.
By the end of that battle, Israel seemed to have entirely eliminated the armed resistance of Jenin. Hundreds of fighters and civilians were killed and wounded, hundreds more arrested and numerous homes destroyed. Even voices sympathetic to the Palestinian struggle have underestimated Jenin’s ability to resurrect its resistance under seemingly impossible circumstances.
Writing in the Israeli newspaper, Haaretz, on June 10, 2016, Gideon Levy and Alex Levac described the state of affairs in the small camp. “Jenin, always the most militant of the refugee camps, was battered and destroyed, suppressed and bloodied, by Israel. These days its spirit seems to be broken. Every person is dealing with his own fate, his own private struggle for survival,” they wrote. The title of their article was “Jenin, Once the Most Militant of Palestinian Refugee Camps, Waves a White Flag”.
Being suppressed and shattered by an overwhelming force, however, is entirely different from “raising the white flag”. In fact, this truism does not just apply to Jenin but to the entirety of occupied Palestine, where Palestinians, at times, find themselves fighting on multiple fronts: Israeli occupation, armed illegal Jewish settlers, and the co-opted Palestinian Authority.
However, May 2021 changed so much. The Israeli attempt at ethnically cleansing Palestinian families from the Sheikh Jarrah neighborhood in East Jerusalem, the subsequent war on Gaza and the unprecedented uprising of unity, bringing all Palestinians, everywhere, together, lifted Jenin and other Palestinian areas from their state of despondency. The stiff resistance in Gaza, in particular, has had a direct impact on the various fighting groups in the West Bank, which were either disbanded or marginalized.
An unprecedented scene in Ramallah, on May 17, tells the whole story. Tens of fighters, belonging to the Al-Aqsa Martyrs Brigades, which is affiliated with the Fatah movement – the political party that dominates Mahmoud Abbas’ PA – marched on the streets of Ramallah, where the Authority is situated, in a relatively calm environment. The fighters chanted against the Israeli occupation and their ‘collaborators’ before clashing with Israeli soldiers, who were manning the Qalandiya military checkpoint.
This event was quite unusual, for it ushered in the return of a phenomenon that Israel, with the help of its ‘collaborators’, had crushed during the Second Palestinian Intifada – or uprising – between 2000-2005.
The Israeli military understands that the May war and uprising have triggered an unwelcomed transition in Palestinian society. Long-suppressed, occupied Palestinians are ready to rebel, eager to move on, beyond octogenarian Abbas and his corrupt clique, past the stifling factionalism and self-serving political discourses. The questions are how, where and when.
This is precisely why Israel is back in Jenin, once more trying to teach the nearly 12,000 refugees there a lesson, one that is also meant for Palestinians throughout the West Bank. Israel believes that if the nascent armed resistance in Jenin is suppressed now, the rest of the West Bank will remain ‘quiet’.
According to Palestinian journalist, Atef Daghlas, the Israeli occupation forces killed ten Palestinians during their frequent nightly raids on Jenin. Eight of the victims have been killed since the end of the Gaza war alone. There are two main reasons behind the increased number of casualties among the Palestinians in the last few months: first, the increased number of Israeli raids – where occupation soldiers, often disguising themselves as Palestinians, enter the camp at night and attempt to capture young Palestinian fighters; second, because of the growing number of youth enlisting in various resistance groups. According to Daghlas, the rifles carried by these youth are purchased by the young men themselves, as opposed to being supplied by a group or a faction.
“Blood for blood, bullet for bullet, fire for fire,” were some of the chants that echoed in the Jenin town and its adjacent refugee camp, when the Palestinian residents carried the bodies of two of the four killed youth, before burying them in the ever-crowded martyrs’ graveyard. The fact that Jenin is, once more, openly championing the armed struggle option is sending alarm bells throughout occupied Palestine. Israel is now worried that an armed Intifada is in the making, and Abbas knows very well that any kind of Intifada would spell doom for his Authority.
It is obvious that what is currently taking place in Jenin is indicative of something much larger. Israel knows this, thus the exaggerated violence against the camp. In fact, two of the bodies of killed Palestinians are yet to be returned to their families for proper burial. Israel often resorts to this tactic as a bargaining chip, and to increase the psychological pressure on Palestinian communities, especially those who dare resist.
It might be relevant to note that the Jenin refugee camp was officially formed in 1953, a few years after the Nakba of 1948, the year when historic Palestine was destroyed and the State of Israel was created. Since then, generation after generation, Jenin’s youth continue fighting and dying for their freedom.
It turns out that Jenin never waved the white flag, after all, and that the battle which began in 2002 – in fact in 1948 – was never truly finished.
Ramzy Baroud is a journalist and the Editor of The Palestine Chronicle. He is the author of five books. His latest is “These Chains Will Be Broken: Palestinian Stories of Struggle and Defiance in Israeli Prisons” (Clarity Press).
Featured Video

Iranians Want Revenge /Sulaiman Ahmed
or go to
Aletho News Archives – Video-Images
From the Archives
Are There 50,000 ‘Israeli-born’ Individuals Living in the UK?
By Professor David Miller | August 18, 2026
Recent disclosures by the Zionist regime show that some 2,069 British nationals were serving in the IDF as of March 2025, according to Freedom of Information (FoI) requests submitted to the occupation forces (1,686 dual British-Israeli, plus 383 multinational). We cannot tell from the figures how many of these were already settler colonists and intend to stay in the colony, and how many will return or have returned to the UK. Presumably, those returning to the UK will number far fewer than 2,000, since many are known to have become permanently residents of the colony.
Additionally, the IDF figures only provide a snapshot, and do not tell us how many have served in the Jewish supremacist military either before or after March 2025. One way into the question of how many genocidaires are living in Britain is to ask how many current British residents were born in the Zionist colony. There is data on that, as we shall see. … continue
Blog Roll
 Aletho News
- Iranians Want Revenge /Sulaiman Ahmed
- ‘Israel’ bombs Nasser Medical Complex in Khan Younis, killing 5
- The beginning of the end: Israel at the heart of America’s political civil war
- US-Israeli war on Iran cost Persian Gulf states nearly $1T in damage, lost growth: Report
- Congress probe could put ‘Israel’ in dock over Iran war: Israeli media
- Spanish public prosecutor backs US demand to extradite pro-Palestine philanthropist Fergie Chambers
- Zelensky spent over 740 days outside Ukraine while West serves as his real home
- Indian captain of Russian ‘shadow fleet’ tanker faces 10-year jail term in UK
- Europe, US face higher heating bills amid Iran war fallout
- The Leak That Arrived Right on Cue
- If Americans Knew
- These Democrats Are Bringing a Christian Case Against Israel’s War to Congress
- Netanyahu calling Trump ‘every day’ to push for renewed war on Iran
- What will big wins by Democrats actually mean for Palestine?
- What is Section 219 of the US defense bill, and what would it mean for Israel?
- Hegseth dodges impeachment after using troops and vets for cover
- Israel Bombs Lebanon’s Churches
- Israel Targets U.S. Conservatives in New Influence Operation
- Declassified FBI Files Reveal Early U.S. Counterintelligence Probe into Israeli Espionage and Smuggling Networks
- Israelis perpetrated 1,182 arson attacks in the West Bank in past 3 years
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- No Tricks Zone
- German Authorities Start Initiative To Evaluate Public Register For Climate “Disinformation” Spreaders!
- Zonal Asymmetry of Temperature Change in the Antarctic Circumpolar Current
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!

