This Week in the New Normal #4
OffGuardian | August 29, 2021
1. VACCINE BRAND WARS?
On Friday, a UK coroner confirmed that BBC presenter Lisa Shaw, who died in May, was killed by the AstraZeneca (AZ) vaccine.
The media have, naturally, gone out of their way to remind their public that “vaccines are safe for most people”, and that Covid is “more likely to give you blood clots than the vaccine”. But that’s hardly surprising.
What’s really interesting is that the story made headlines at all. If the media were 100% dedicated to painting the vaccines as safe, why not just bury it completely?
The AZ brand of experimental Covid therapy has been the acceptable punching bag of the vaccine roll out. From as early as last December, the AZ shot was being described as an “also ran” compared to the products made by pfizer and Moderna.
In the spring of 2021 some countries, including Norway and the Netherlands, stopped using it completely after initial concerning reports of blood clots. The US, still, refuses to recognise those given the AZ jab as “vaccinated”. The Indian-made “Covishield” brand of the AZ shot is not recognised by the EU’s vaccine passport system.
Why is this?
Well, it could be a simple psy-op designed to create, and reinforce, faith in the system. You produce several vaccines all in the space of a year (all with equally unknown long-term effects), and then you repudiate one for “being unsafe”, and you create the illusion that a) the others are safe b) the system works and c) you honestly care about public health.
It should also be noted that the AZ shot is not an mRNA vaccine, unlike the Pfizer and Moderna jabs. So there might be an interest in bad-mouthing it, if your end goal is to study the impact of mRNA technology on humans.
In June the BBC reported that internet “influencers” were being paid to bad mouth Pfizer’s and prop-up AstraZeneca’s. The press blamed “Russian antivaxxers”, but that doesn’t make any sense at all. It was far more likely a marketing agency employed by AstraZeneca.
In fact, Facebook has already banned a UK-based marketing company that has attacked both the Pfizer AND AZ “vaccines” at different points.
And when the headlines about AstraZeneca’s product causing bloodcluts first hit, it was Pfizer that benefited, as their stock value took a jump.
All together I would say that evidence points to a behind-the-scenes catfight between big pharma companies. They’re all fighting each other for the lion’s share of their soon-to-be-mandated market.
It’s funny that, even in a plan as grand as total global control, they can’t put petty greed aside and actually co-operate, and it also tells you exactly the kind of short-term thinking psychopathic minds at work here.
2. AMAZON PAYING FOR PALM PRINTS
This is exactly what it sounds like.
Amazon is installing biometric pay points in their in-person stores, and are giving out $10 gift cards to anyone willing to have their unique palm print scanned into the system. They are pushing it as a way to pay without any physical contact, perfect for avoiding becoming infected by the “pandemic”.
But – shockingly – Amazon might not be entirely trustworthy. They have stated that the biometric data will be used to monitor shopping activity and target ads, which is bad enough, but there are myriad other applications. None of them especially reassuring. For one thing, Amazon could sell the data…to anyone.
As a precedent for that, there is the Amazon facial recognition tech, which they already sold to the US government:
Amazon’s controversial facial recognition technology, which it historically sold to police and law enforcement, was the subject of lawsuits that allege the company violated state laws that bar the use of personal biometric data without permission.
Still though, if you value your privacy as little as 10 dollars, go for it.
(And yes, we know this story is from earlier this month, but we didn’t see it ’til now, and it’s worth mentioning.)
3. JUDGE TAKES AWAY PARENTAL RIGHTS OVER “VACCINATION” STATUS
Again, exactly what it sounds like.
According to a story from Fox News local Chicago station, at a digital child support hearing over Zoom, judge James Shapiro asked the mother – Rebecca Firlit – if she had been “vaccinated”.
When Firlit answered “no”, the judge awarded full custody to the father and gave the mother zero visitation rights. She is currently not allowed to see her son until she gets “vaccinated”.
Previous to that hearing the divorced couple had shared custody. And the vaccine status of the parents had never been a bone of contention.
BONUS: DISTURBING HEADLINE OF THE WEEK
Not even a write up for this, just a picture of the front page of the Toronto Star :

…. yeah.
IT’S NOT ALL BAD…
As you no doubt know, there were more protests this week. In Ireland, Australia, New York, London and many others. There was a great protest against Covid passes in Rheims, where people set-up picnic blankets outside cafes:
Also, Eric Clapton released a new song about the vaccine situation:
All told a pretty hectic week for the new normal crowd, and we didn’t even mention the UK’s media war on parental consent, or the subtle anti-US slant appearing the press following the US’s withdrawal from Afghanistan (including renewed calls for an EU army).
Twitter bans Alex Berenson over COVID tweets
By Cindy Harper | Reclaim The Net | August 29, 2021
Former New York Times reporter Alex Berenson has been permanently banned from Twitter for violating its COVID-19 “misinformation policies.”
The author has become well-known as a critic of coronavirus quarantines and mandates.
A Twitter spokesperson confirmed that the commentator’s account was blocked on Saturday due to “repeated violations.”
“The account you referenced has been permanently suspended for repeated violations of our COVID-19 misinformation rules,” the Twitter representative stated.
The journalist has repeatedly expressed his views about COVID-19, in particular the efficacy of the vaccines, but a recent tweet apparently triggered Twitter’s decision to ban him.
“It doesn’t stop infection or transmission,” stated the tweet, which casts doubt on vaccine effectiveness. “It doesn’t stop infection or transmission. Don’t think of it as a vaccine.”
“Think of it — at best — as a therapeutic with a limited window of efficacy and terrible side effect profile that must be dosed IN ADVANCE OF ILLNESS.”
Twitter later claimed the message was “misleading,” resulting in Berenson’s account being deactivated.
After being suspended from Twitter, Benson made an entry on Substack, a newsletter service, which featured the tweet that appears to have caused the issue.
In the post headlined “Goodbye Twitter,” Berenson wrote: “I am officially suspended. This was the tweet that did it. Entirely accurate. I can’t wait to hear what a jury will make of this. Meantime, guess you’ll be getting more Substacks.”
“We have reached a dangerous moment. Social media companies that have audiences which dwarf any other are now actively censoring reporters at the behest of governments,” Berenson said in a statement.
“I will continue to fight to get out the truth and am considering all legal options.”
Media addiction to Covid-19 ‘fear porn’ is perpetuating a worsening cycle of societal damage worldwide

© REUTERS / Thilo Schmuelgen
By Eva Bartlett | RT | August 28, 2021
Over the past year and a half, hysterical media reporting on matters Covid-19 has reduced some people to a fearful state of unquestioning compliance – including a great number of otherwise critically-thinking journalists.
With screaming headlines in bold and large font such as, ‘Will this nightmare ever end?’ and ‘Mutant virus skyrockets…’ and ‘Fear grows across the country: VIRUS PANIC’, and ‘Coronavirus horror: Social media footage shows infected Wuhan residents ‘act like zombies’, it is no wonder many people are in a state of panic.
In times when many are suffering mentally and physically under unnecessary and prolonged lockdowns, the incessant fear porn is causing excessive anxiety, which in turn will affect the health & mental well-being of some, if not many.
In government documents from the UK’s Scientific Advisory Group for Emergencies (SAGE) dated from March 2020 advice was given saying:
“The perceived level of personal threat needs to be increased among those who are complacent, using hard-hitting emotional messaging… This could potentially be done by trained community support volunteers, by targeted media campaigns, social media”
I’d say the UK media campaigns weren’t so much ‘targeted’ as ‘blanket’ but they certainly did the job, and other Western nations got similar directives. The UK government also became the nation’s biggest advertiser in 2020, make what you will of the potential ramifications that could have on cash-strapped newspapers and their supposed ‘independence’.
Having myself been deeply focused on exposing war propaganda and other media lies around Syria, Palestine, Venezuela, and elsewhere over the years, my default position has become one of deep cynicism on mass media reporting. Yes, you can find nuggets of truth, or even excellent journalists in mainstream publications, honestly challenging the narratives.
But those are few and far between, generally you find copy-paste propaganda emanating largely from the bowels of the USA and the UK.
A study by Swiss Propaganda Research (SPR) noted, “most of the international news coverage in Western media is provided by only three global news agencies based in New York, London and Paris.”
Those agencies are AP, Reuters, and AFP. SPR notes:
“The key role played by these agencies means Western media often report on the same topics, even using the same wording. In addition, governments, military and intelligence services use these global news agencies as multipliers to spread their messages around the world.”
Given all of this, I’ve come to believe that with regard to media reporting on Covid-19, my cynicism is well-deserved.
Covid-19 reporting has increasingly been utterly absurd, with stories of people dropping dead in the streets, ice rink morgues to cope with the mountains of bodies, footage of an overcrowded New York hospital (that just happened to be of an Italian hospital), claims of animals testing positive for SARS-CoV-2, and more recently reports of people dying post-jab but we are told ‘it could have been worse!’
This campaign of fear caused the public to massively overestimate the lethality of Covid-19, which as un-alarmist voices note has a survival rate of over 99%.
When months into the outbreak it became apparent that SARS-CoV-2 was far less lethal than first predicted, the media and talking heads moved from talking about ‘Covid deaths’ to ‘positive cases’.
Although relatively early on a goat and pawpaw tested positive for Covid-19, instead of then scrutinizing the accuracy of the PCR test as a means of ‘detecting Covid-19’, the media continued to hype the rise in Covid ‘cases’.
In lockstep, ‘Covid testing’ was increased dramatically using the PCR test (recently revoked by the CDC). This inevitably pumped up the number of ‘cases’, which mass media have in turn promoted non-stop, this in turn gave ammunition to those enforcing lockdowns and vaccines.
By now hundreds of vocal doctors, nurses, virologists, immunologists, and other professionals actually worth listening to, whose data and experience counter the hype pumped out in media have very quickly disappeared from social media, or otherwise deemed quacks, and are thus largely silenced. This leaves the general public mainly getting their information via hyped-up media.
Alongside this, there have been relentless ad hominem attacks on journalists who pose legitimate questions and uncomfortable truths about the official narratives around Covid-19.
For offering perspectives which contradict the standard narratives around Covid-19, journalists have been deemed conspiracy theorists, pandemic-deniers, right-wingers, selfish… I’m sure I’ve missed quite a few slurs.
When it comes to matters Covid-19, it is suddenly unacceptable to question ‘The Science’, question the authorities, or question the same media that sold us WMDs in Iraq and chemical attacks in Syria.
Media are the drivers of Covid hysteria, and it is the daily bombardment of fear porn that confuses average people and enables tyrannical powers to be brought in, largely unchallenged.
As it is the responsibility of journalists to expose lies around wars of aggression, it is also the duty of journalists to do so around Covid-19. For some journalists who have stubbornly refused to hold power to account, instead toeing the line on all things Covid, it appears their fear is of losing an audience and not of a virus.
Whether or not you agree with dissenting voices’ questions and criticisms, we have the right to ask and make them. We do so, knowing that remaining silent in the face of the brutal Covid measures is a guaranteed path to tyranny.
Eva Bartlett is a Canadian independent journalist and activist. She has spent years on the ground covering conflict zones in the Middle East, especially in Syria and Palestine (where she lived for nearly four years).
“It’s all for your own good”
By TE Creus | OffGuardian | August 29, 2021
One of the most annoying aspects of the current measures supposedly created “against the pandemic” that we have been subjected to for almost two years now is the insistence that everything is done “for our own good”, as if governments and big companies were strict but caring parents, and we were just unruly or disobedient children who don’t really know what they need.
It brings to mind CS Lewis’ warning about that most oppressive of tyrannies, “a tyranny sincerely exercised for the good of its victims.”
Now, I cannot tell for sure if the vaccines, the lockdowns, the travel restrictions and the masks work or not. My feeling is that they don’t, or at least, not in the way we are being told, but that’s not the issue. The question is why are we being treated like stupid children who cannot simply choose, but have to take a “jab” and then get “green passes” to travel or work or enter any establishment.
Apparently, governments and big corporations worldwide are worried about our “health”.
But are they, really?
Like monomaniacs, they seem to be worried exclusively about Covid.
Not about the incredible amount of mental health issues and the alarming increase of teenage suicides during the various “lockdowns”.
Not about people, like my elderly neighbours, who could not see their family (who live in another country) for over two years and are suffering with solitude.
Not for the people who, afraid of contracting Covid, didn’t go to the hospital to treat other conditions and died.
Not for the people who died or got sick because of side effects of the vaccines.
No, it’s just “Covid”. And even that doesn’t seem to be their main worry. As long as they get their “vaccine passports” and their “tracking apps” and their “cashless society”, they don’t really care if you get the disease or not.
When did this wave of fake concern start? Ok, governments were probably always in the business of being annoying busybodies – “I’m from the government and I am here to help” was a scary sentence since who knows how long. But companies for decades were mostly concerned with selling their product, not with lecturing us.
However, at the peak of the BLM riots, I received dozens of emails from big companies assuring me that, to them, “blacks lives mattered”. In Pride Month, the same companies assured me that they were fighting for transgender rights to use whichever bathroom they wanted. I never asked nor cared what’s their position on those issues, just that they make a good product that I can use.
Now, the same companies send me emails about masks and vaccination and passes. Because, see, they are worried about my health.
Unfortunately, it’s not just governments and big companies. Almost every institution in the culture and the arts is also kowtowing (either by government decrees or to keep being funded, I don’t know) to this literal “new world order”.
For instance, the Baltimore Symphony Orchestra now has very strict regulations for entry. They tell us that they want to create “an environment in which we all may confidently discover what it means to be together again.”
And so, in the name of “togetherness”, they are banning all people who are not vaccinated, including all children under 12 years of age who cannot, alas, be legally vaccinated yet. Not even people with a negative Covid test will be allowed entry to the concerts: only the “vaxxed” ones, with their proper certificates. Still, even they will have to endure masks for the whole duration of the spectacle. It’s not clear if also the musicians have to wear masks – I suppose at least the flute players will be exempted.
And yet, despite all those draconian rules which really seem to take out all of the fun out of the process (and in this case it might really be better to just stay home and watch a video streaming online), “these protocols do not offer absolute protection against contracting COVID-19” and the spectators must “voluntarily assume all risks related to exposure to COVID-19.”
Note also that those showing any possible symptoms might not be allowed entry, vaccine or not. (I wonder if anyone who coughs during one of the breaks will be forcefully ejected.)
This is just one example among many of the ludicrous and merciless “new normal” that we are subject to in the name of our health.
But remember, “it’s all for your own good”.
TE Creus is a writer, translator and filmmaker. He is the author of “Our Pets and Us: The Evolution of a Relationship” and the collection of short stories “The Sphere”. He’s the editor of Contrarium.
Some are horrified the Taliban seized biometric devices. The real scandal is the extent of US’ data collection.

US soldier scans an Afghan resident with an Automated Biometric Identification System (ABIS) during a mission © AFP / TAUSEEF MUSTAFA
By Kit Klarenberg | RT | August 28, 2021
A huge amount of opprobrium was heaped on the Americans for allowing this sensitive data to fall ‘into the wrong hands’. However, surely a better question is why had they gathered all this deeply personal data in the first place?
It’s been reported that the Taliban has seized US military biometric devices in the wake of Washington’s flight from Afghanistan, which could put civilians who assisted coalition forces at significant risk.
The devices, known as HIIDE, for Handheld Interagency Identity Detection Equipment, contain identifying biometric data such as iris scans and fingerprints, as well as biographical information – while their primary stated purpose is to track insurgents, biometric data was also collected and stored on Afghans who assisted the US occupation forces.
The story sparked outcry, widely invoked by both opponents and advocates of the 20-year war as yet another deplorable example of Washington leaving its allies high and dry. While it seems clear there was no consideration given to what could happen if the technology fell into the ‘wrong’ hands, critics have nonetheless overwhelmingly failed to consider the terrifying ramifications of this data being in the right hands, and how the US came into possession of it in the first place.
When precisely the practice of collecting Afghans’ biometric data began isn’t certain, although at a 2010 conference in Kabul, US military officials laid out the terms of Afghan 1,000, a program which sought to collate information on 80% of the country’s population, around 25 million people. It was framed in extremely positive terms, not merely as a means to identify terrorists and criminals, but “enable progress in society” due to its “countless applications for the provision of services” to citizens.
It’s uncertain if that target was reached before Washington’s withdrawal, but the strategy remained in operation for over a decade. The next year, it was reported that Washington ultimately sought to gather biometric data on all living Afghans.
To achieve the lofty goal, a policy of mandatory data collection was imposed for every traveler entering the country via any means, and a dedicated Population Registration Department was created, with offices throughout the country. Even foreign journalists covering the war were fingerprinted, and their irises scanned. Moreover, occupation forces conducted innumerable “enrolment missions”, entering towns and villages and forcing locals to hand over their biometric data at literal gunpoint.
A US Army guide states emphatically that “all combat outposts and checkpoints throughout Afghanistan make it a priority to collect biometric data from as many local nationals as possible.” In the aftermath of a bombing or skirmish, soldiers are told to “enroll everyone”, including the dead, their DNA to be collected using buccal swabs to capture cells lining the mouth. The “payoff” for coalition forces was said to be so great, “commanders must be creative and persistent in their efforts to enroll as many Afghans as possible.”
In a section disturbingly titled “Population Management”, the guide recommends that everyone who lives within an operational area “should be identified and fully biometrically enrolled with facial photos, iris scans, and all ten fingerprints (if present).” Soldiers must also record “good contextual data” about individuals, such as “where they live, what they do, and to which tribe or clan they belong.” Citizens were to be told the collection protected them from potentially violent elements and troublemakers.
A lengthy article in the January 2014 edition of Military journal Joint Forces Quarterly offers a glowing appraisal of the “biometric-enabled intelligence” system rolled out in Kabul, declaring it to be a “key enabling factor” in US counterinsurgency efforts, and “an invaluable part of the campaign that has even greater potential in the future.” It documents how enrolment was often carried out using colorful trucks with jingling bells, in the manner of an ice cream van, in order to make the process “more culturally appealing” – particularly in respect of children, presumably.
Also included are several alleged “success stories”, such as one instance in which two Afghan police officers, neither of whom could read or write, spotted an individual on a “biometrically developed insurgent watch list” approaching their checkpoint.
One of the officers is said to have taken the man – identified as having been involved in “multiple IED events” – into custody “with a broad smile,” and the anecdote ends on an upbeat note, hailing how the officers’ illiteracy was no barrier to them removing a dangerous insurgent from the battlefield due to the miracle of biometric intelligence. Cheery stuff, although journalist Annie Jacobsen has exposed in chilling detail just how fallible biometric evidence can be.
In July 2012, US Army First Lieutenant Clint Lorance ordered his platoon to shoot three unarmed motorcycle riders in Kandahar province. The next year, a court martial found him guilty of two counts of second-degree murder, attempted murder, wrongfully communicating a threat, reckless endangerment, soliciting a false statement, and obstructing justice, sentencing him to 20 years in prison. However, in November 2019, he received a pardon from Donald Trump.
The then-president released Lorance after he was shown fingerprints and DNA data that purportedly indicated the Afghan men killed were Taliban bomb makers, not civilians. However, after some determined digging, Jacobsen found that one set of fingerprints allegedly found on an exploded IED said to prove one of the dead men was a bomber actually belonged to a police officer, who was likely to have contaminated the evidence in the line of duty. The other set did indeed belong to a bomber – who was still alive.
Lorance isn’t an isolated example either. Staff Sergeant Robert Bales is serving life for killing 16 Afghan villagers in cold blood in March 2012. While he pleaded guilty to the charges and admitted his tours of Afghanistan and Iraq had instilled a loathing of the local population within him, he’s now appealing his sentence. The case rests on data provided by a biometrics expert who also worked on the Lorance case, which he claims proves witnesses to Bales’ crimes were Taliban bomb makers who left their fingerprints on bomb components.
Evidently though, Afghanistan was just an experiment – and Washington was enamored with the results. The White House’s proposed Army budget for 2022 seeks over $11 million to purchase 95 new biometric collection devices, meaning the policy will almost inevitably be rolled out again in whichever country is next in the US crosshairs.
Where that will be is unknown, but there’s also the question of what implications the Afghan test run has for the Western world. Governments, police forces, security services and even big business are increasingly using cutting-edge technology to amass, store and analyze vast reams of sensitive personal data – much of it was similarly trialed during the War on Terror, and sold to home audiences on the basis of convenience and security, just as the military’s biometric data harvest was sold to Afghans. Now the troops are finally home, has the fight been brought back with them?
Kit Klarenberg is an investigative journalist exploring the role of intelligence services in shaping politics and perceptions.
Afghanistan Withdrawal Is Hurting Its Profits. It’s Funding a Pro-War Think Tank.
BY SARAH LAZARE | IN THESE TIMES | AUGUST 25, 2021
On August 12, the military contractor CACI International Inc. told its investors that the U.S. withdrawal from Afghanistan is hurting its profits. The same contractor is also funding a think tank that is concurrently arguing against the withdrawal. This case is worth examining both because it is routine, and because it highlights the venality of our “expert”-military contractor feedback loop, in which private companies use think tanks to rally support for wars they’ll profit from.
The contractor is notorious to those who have followed the scandal of U.S.-led torture in Iraq. CACI International was sued by three Iraqis formerly detained in Abu Ghraib prison who charge that the company’s employees are responsible for directing their torture, including sexual assault and electric shocks. (The suit was brought in 2008 and the case is still ongoing.)
In 2019, CACI International was awarded a nearly $907 million, five-year contract to provide “intelligence operations and analytic support” for the U.S. Army in Afghanistan.
During an August 12 earnings call, CACI International noted repeatedly that President Biden’s withdrawal from the 20-year Afghanistan War harmed the company’s profits. John Mengucci, president and CEO of CACI International, said, “we have about a 2 percent headwind coming into FY 2022 because of Afghanistan.” A “headwind” refers to negative impacts on profits.
Afghanistan was mentioned 16 times throughout the call — either in reference to the dent in profits, or to assure investors that other areas of growth were offsetting the losses. For example, Mengucci said, “We’re seeing positive growth in technology and expect it to continue to outpace expertise growth, collectively offsetting the impact of the Afghanistan drawdown.”
Similar themes were repeated in an April 22 earnings call, where the company lamented the “headwinds” posed by the Afghanistan withdrawal. (Industry and defense publications have picked up on this theme, but framed it in the company’s terms, by emphasizing the offsets to its losses.)
Despite CACI International’s clear economic interest in continuing the war, on the August 12 call, company officials were careful not to editorialize about the Biden administration’s decision. The closest they came was a cautious statement from Mengucci: “At least as of today we’ve watched the administration make the decision to completely exit Afghanistan by 9 – 11 and all I can say is they’re executing on that decision.”
But CACI International does not have to broadcast its positions on the war: Instead, it is funding a think tank that has been actively urging the Biden administration not to leave Afghanistan.
CACI International is listed as a “corporate sponsor” of the Institute for Study of War, which describes itself as a “non-partisan, non-profit, public policy research organization.” Dr. Warren Phillips, lead director of CACI International, is on the board of the think tank. (Other funders include General Dynamics and Microsoft.)
When it comes to the U.S. withdrawal from Afghanistan, however, the think tank is extremely partisan. In an August 20 paper, the think tank argued that “Russia, China, Iran, and Turkey are weighing how to take advantage of the United States’ hurried withdrawal.”
Jack Keane, a retired four star general and board member of the Institute for Study of War, meanwhile, has been on a cable news blitz arguing against the U.S. withdrawal from Afghanistan, as reported by Ryan Grim, Sara Sirota, Lee Fang and Rose Adams for The Intercept. (The Intercept noted CACI’s International’s backing of the think tank.)
Kimberly Kagan, founder and president of the Institute for the Study of War, told Fox News on August 17 that the U.S. withdrawal could cause Afghanistan to become the “second school of jihadism.” She warned, “It is not clear that the Taliban, which seeks international recognition and legitimacy, is going to want to tolerate or encourage direct attacks on the U.S. from al Qaeda or other extremist groups based in Afghanistan.”
The think tank’s backing from a military contractor was not discussed in these media appearances.
The case of CACI International is not unique. The Intercept notes, “Among the other talking heads who took to cable news segments or op-ed pages without disclosing their defense industry ties were retired Gen. David Petraeus; Rebecca Grant, a former staffer for the Air Force secretary; Richard Haass, who worked as an adviser to then-Secretary of State Colin Powell; and former Secretary of State Condoleezza Rice.”
This cacophony of voices matters because Biden is facing a media uproar over the withdrawal. Pundits and mainstream press outlets that have been ignoring civilian deaths for years are suddenly expressing moral outrage at their hardships now that the war is ending. While there are legitimate concerns about the fate of Afghans as the Taliban seizes control, the vast majority of the firestorm stems from a reflexively pro-war perspective, in favor of the indefinite extension of an occupation that has proven brutal and lethal for civilians. The overwhelming effect is to send the message to Biden, and any future presidents, that they should think twice before withdrawing from a war, lest they have a media revolt on their hands.
But this outcry didn’t materialize out of nowhere. Think tank “experts,” whose organizations are financed by the very companies profiting from the war, play a key part. They are trotted out in front of cameras and quoted in major media outlets, presented as above-the-fray observers. They are well-financed, polished and groomed precisely for moments like these. And the companies financing them get to launder their own objectives through institutions that are seen as respectable, academic and rigorous. It’s a grotesque system that is functioning as it was designed.
In its August 12 call, CACI International simply acknowledged the company’s economic interests out loud.
THE U.S. HAS SPENT $2.313 TRILLION ON WAR IN AFGHANISTAN SINCE 2001
Watson Institute | August 2021
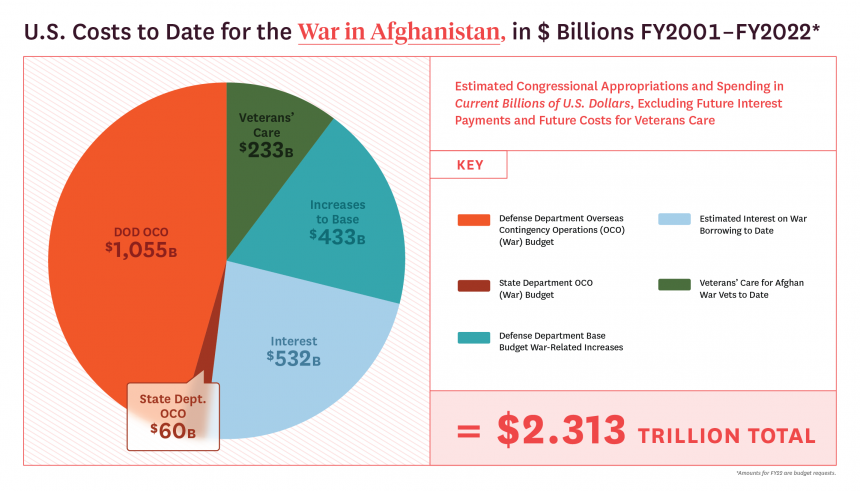
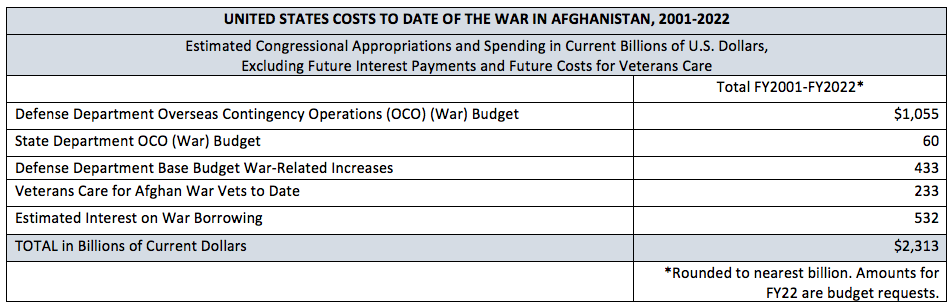
Since invading Afghanistan in 2001, the United States has spent $2.313 trillion on the war, which includes operations in both Afghanistan and Pakistan. Note that this total does not include funds that the United States government is obligated to spend on lifetime care for American veterans of this war, nor does it include future interest payments on money borrowed to fund the war. This $2.313 trillion spent on Afghanistan is a portion of the total estimated cost of the post-9/11 wars.
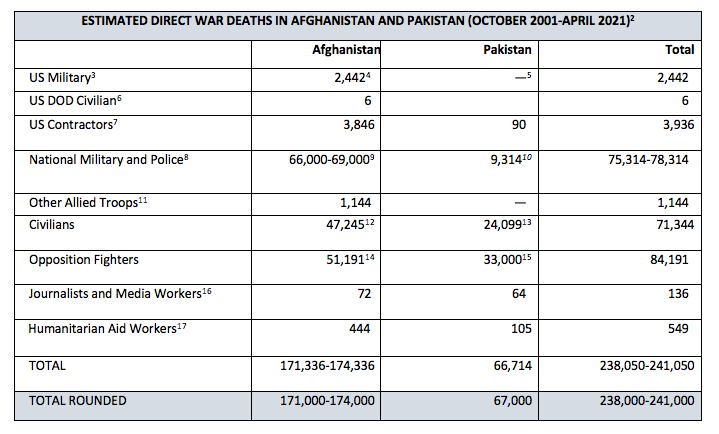
The Costs of War Project also estimates that 241,000 people have died as a direct result of this war. These figures do not include deaths caused by disease, loss of access to food, water, infrastructure, and/or other indirect consequences of the war.
The figures for Afghanistan are part of the larger costs of the U.S. post-9/11 wars, which extend to Iraq, Syria, Yemen, Somalia and elsewhere. The numbers are approximations based on the reporting of several data sources.
Hezbollah grows stronger in Lebanon amid energy crisis, arranging oil shipments from Iran
By Uriel Araujo | August 28, 2021
Hassan Nasrallah, the leader of the Lebanese Shia Islamist organization Hezbollah has announced more Iranian ships are bringing fuel to Lebanon. The country is under an unprecedented political and economic crisis and is facing massive gasoline shortages – even after the first vessel arrived on August 19. Some worry Iran-funded Hezbollah could thus take the place of the almost collapsing Lebanese state or companies. Others worry the US could impose sanctions on Lebanon due to its relation with the Islamic Republic of Iran. The US Ambassador to Lebanon in fact stated, hours after Hezbollah’s statement, that Washington was in talks with Jordan and Egypt to find solutions to Lebanon’s fuel crisis, which has affected businesses, hospitals, and homes.
Riad Toufic Salameh, the Governor of Lebanon’s central bank claimed two weeks ago that Beirut simply lacks the foreign reserves needed to release dollars to import fuel. On August 12, Salamesh announced Lebanon decided to change the exchange rate used as a base for importing fuel, thus sharply increasing retail prices. Gasoline prices may rise up to 66% as subsidies were cut in an attempt to ease shortages. This central bank measure clashed with outgoing Prime Minister Hassand Diab’s government, which pledged to keep the subsidies in an ongoing dispute. Diab described Salamesh’s decision as illegal and irresponsible. Several roads were closed by protesters the same day and the demonstrations are still going on. It is in this context that Hezbollah and its network of Shia businessmen arranged for the shipments of oil. This move was criticised by former Prime Minister Saad Hariri and other political figures as an infringement on the Lebanese state’s sovereignty.
According to the Iranian semi-official Nour News agency, the first fuel shipment was bought by a group of Lebanese Shiite merchants. The same agency reported that the shipment should be considered Lebanese property “from the moment it is loaded”, and described the fuel dispatch as a “strong action taken by Iran and Hezbollah to break the economic siege of the Lebanese people by a western-Arab-Israeli axis”.
According to Laury Haytayan, a Middle East gas and oil expert and a Natural Resource Charter Senior Officer, Hezbollah’s announcement in itself could place Lebanon in danger of being sanctioned for the ships bringing fuel from Iran are carrying a product that is under US sanctions and thus anyone engaging with such product could also be sanctioned under the current regime that targets third parties buying Iranian oil or merely interacting with the Iranian financial sector.
The Lebanese government could of course ask for a waiver of these sanctions (such as the ones that were granted to Iraq pertaining to Iranian gas imports) but the hard truth is that Lebanon today barely has a government. Any political void always invites political entrepreneurship and Hezbollah seems to be showing itself capable of doing what the government can’t.
Furthermore, there have been Israeli attacks on shipments of Iranian fuel to Syria, which neighbors Lebanon. If such were to happen with a shipment heading to Lebanon, this would obviously further increase anti-Israeli sentiment in a country where tensions are already escalating. Some see Hezbollah’s move as a part of a kind of a deterrence equation, that is, the Shia organization would retaliate in case Israel attacks any ship bringing fuel during a major energy crisis.
Nasrallah also said Hezbollah could help bring an Iranian company to drill, if necessary. These remarks were made during his televised speech for Ashura, an Islamic holiday of particular significance for Shias. With the current crisis, Hezbollah is showing itself to be the only faction that can organize the country. This means Iran’s influence on the Levant is to increase which will worry many actors, particularly Saudi Arabia.
Earlier this year Iran and Saudi Arabia started a series of talks, urged by Qatar, but they have been suspended. The new Iranian President Ebrahim Raisi has claimed his foreign policy priority now is to improve relations with the Persian Gulf Arab countries, which are led by Saudi Arabia. The current war in Yemen is a point of contention, though, for Tehran supports the Houthi insurgency in Yemen. Riad leads a major military intervention in the country against the Houthi rebels (in a coalition that includes Bahrain, and the United Arab Emirates, as well as Egypt, Jordan, and Sudan). This makes the conflict in Yemen a proxy war between Iran and Saudi Arabia. If Tehran and Riad could put such differences aside they could help bring peace and stability to the region. But this is not an easy task, as the two rivals still seem to compete in Iraq and Lebanon and might further compete in Afghanistan after the US withdrawal.
Washington and the European powers are losing their influence in the Lebanese political game. Solving the energy crisis in Lebanon is first and foremost a humanitarian issue and if the US chooses to act in terms of sanctioning Lebanon this would greatly harm US President Joe Biden’s narrative of the United States as a champion of human rights worldwide. The current crisis after all is also about Iran – whose economy has been hit hard by sanctions and today has a 45% inflation rate and has reached the highest price for food products.
If the US does not sanction Lebanon, such will serve Hezbollah as a kind of a show of force. If Washington does sanction the country, Hezbollah also wins somehow for it would corroborate its narrative of Lebanon under siege. Under such a scenario Lebanon should further enhance its relations with Iran. Thus, no scenario is good for the US.
Alberta government refuses to take part in digital vaccine passports
By Christina Maas | Reclaim The Net | August 28, 2021
The government of the Canadian Province of Alberta has refused to share its residents’ vaccination status data with the federal government. Other provinces are cooperating with the government and have even launched vaccine passport plans.
In a press release, the Alberta Institute, a non-profit, said that the provincial government had confirmed to it, and “then later publicly announced, that they will not be providing the federal government with Albertans’ vaccination status and data for use in a federal vaccine pass system.”
“Albertans will be able to opt-in to provide their information to the federal government should they choose to do so,” the press release added.
Alberta seems to be the only province choosing to protect the privacy rights and civil liberties of its residents. The provinces of British Columbia, Quebec, and Manitoba are working on their own vaccine passport programs.
Quebec will launch its vaccination certification system in September.
“Quebec’s Health Department says police complaints have been filed after politicians’ COVID-19 vaccine passport information was allegedly hacked,” stated a report from FM96. “The department said in a statement Friday it is aware of reports that people have managed to steal the QR codes of members of the Quebec legislature and is taking the matter seriously.”
British Columbia is also set to launch a vaccine passport that would be required to access many businesses.
BC’s system will be one of the most restrictive in the world as it does not allow for any religious or medical exemptions.
While on the re-election campaign trail in Ontario on Friday, Prime Minister Justin Trudeau promised, if re-elected (the election is on September 20th), the Liberal government would create a $1 billion fund to be used by provincial governments to develop and launch vaccine passport systems.
Featured Video

Iranians Want Revenge /Sulaiman Ahmed
or go to
Aletho News Archives – Video-Images
From the Archives
Are There 50,000 ‘Israeli-born’ Individuals Living in the UK?
By Professor David Miller | August 18, 2026
Recent disclosures by the Zionist regime show that some 2,069 British nationals were serving in the IDF as of March 2025, according to Freedom of Information (FoI) requests submitted to the occupation forces (1,686 dual British-Israeli, plus 383 multinational). We cannot tell from the figures how many of these were already settler colonists and intend to stay in the colony, and how many will return or have returned to the UK. Presumably, those returning to the UK will number far fewer than 2,000, since many are known to have become permanently residents of the colony.
Additionally, the IDF figures only provide a snapshot, and do not tell us how many have served in the Jewish supremacist military either before or after March 2025. One way into the question of how many genocidaires are living in Britain is to ask how many current British residents were born in the Zionist colony. There is data on that, as we shall see. … continue
Blog Roll
 Aletho News
- Iranians Want Revenge /Sulaiman Ahmed
- ‘Israel’ bombs Nasser Medical Complex in Khan Younis, killing 5
- The beginning of the end: Israel at the heart of America’s political civil war
- US-Israeli war on Iran cost Persian Gulf states nearly $1T in damage, lost growth: Report
- Congress probe could put ‘Israel’ in dock over Iran war: Israeli media
- Spanish public prosecutor backs US demand to extradite pro-Palestine philanthropist Fergie Chambers
- Zelensky spent over 740 days outside Ukraine while West serves as his real home
- Indian captain of Russian ‘shadow fleet’ tanker faces 10-year jail term in UK
- Europe, US face higher heating bills amid Iran war fallout
- The Leak That Arrived Right on Cue
- If Americans Knew
- These Democrats Are Bringing a Christian Case Against Israel’s War to Congress
- Netanyahu calling Trump ‘every day’ to push for renewed war on Iran
- What will big wins by Democrats actually mean for Palestine?
- What is Section 219 of the US defense bill, and what would it mean for Israel?
- Hegseth dodges impeachment after using troops and vets for cover
- Israel Bombs Lebanon’s Churches
- Israel Targets U.S. Conservatives in New Influence Operation
- Declassified FBI Files Reveal Early U.S. Counterintelligence Probe into Israeli Espionage and Smuggling Networks
- Israelis perpetrated 1,182 arson attacks in the West Bank in past 3 years
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- No Tricks Zone
- German Authorities Start Initiative To Evaluate Public Register For Climate “Disinformation” Spreaders!
- Zonal Asymmetry of Temperature Change in the Antarctic Circumpolar Current
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!

