$1,000,000 to forecast Vaccine Misinformation narratives
The Naked Emperor’s Newsletter | January 16, 2023
On 20 October 2022, the CDC published a grant opportunity to develop a public health tool to predict the virality of vaccine misinformation narratives. The application closed a few days ago.
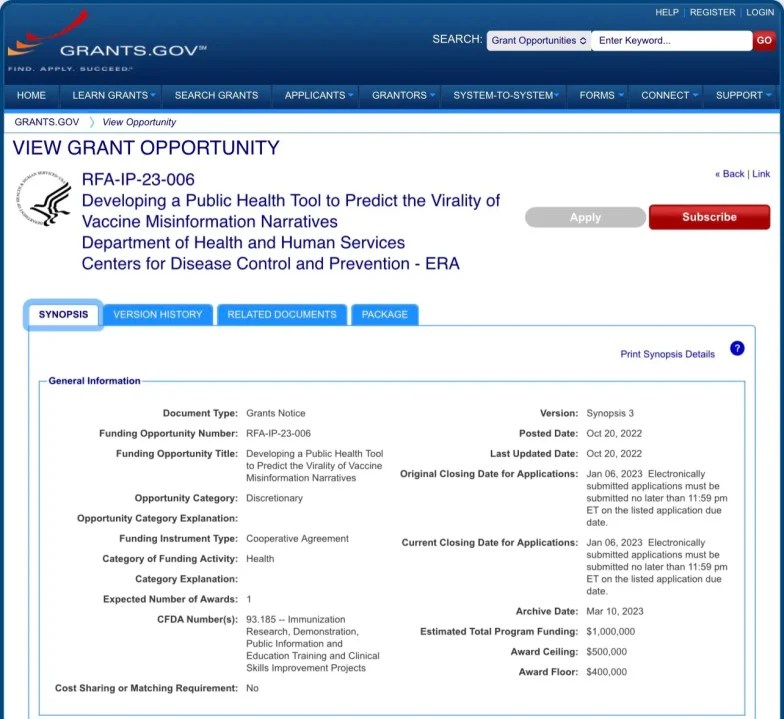
The purpose of the $1,000,000 grant is “to conduct research to develop and pilot a predictive model and tool to aid…in identifying emerging vaccine misinformation about recommended vaccines, including COVID-19 vaccines, that is likely to spread and have a high potential for impacting vaccine confidence”. It will enable public health agencies to identify misinformation before it spreads or impacts people’s health decisions.
According to the proposal, evidence for the negative impact of misinformation continues to grow. Therefore, this proposal has the potential to impact the Healthy People 2030 scheme by ensuring people get vaccinated. Healthy People 2030 sounds and looks suspiciously like something from Agenda 2030 but equally this might just be someone jumping on the bandwagon. However, one of the developmental objectives is to “increase the proportion of immunization information systems that track adult immunizations across their lifespan” which sounds a lot like vaccine passports. Maybe not but unfortunately these things need keeping an eye on these days.
The CDC estimates that “COVID-19 misinformation and disinformation caused $50-$300 million per day in additional medical costs, monetized lives lost and morbidity, and economic costs”. Therefore, they want this new tool to increase vaccination rates and disseminate accurate scientific messages.
There are 3 phases to successfully complete the proposal:
- Phase 1 – Develop a predictive model that identifies misinformation. To do this they will look at old data to find topics (such as vaccine safety and fertility), the types of people sharing this information and the relationship to societal concerns (e.g. personal liberty);
- Phase 2 – Develop a tool that can be used to prioritise the response to misinformation.
- Phase 3 – Pilot and evaluate the tool (that can be used at federal, state, local, tribal and territorial public health agency levels)
Now, I’m all for getting rid of misinformation. In an ideal world I just want to be reading facts, more facts with a few more facts sprinkled on top. However, this isn’t an ideal world and unfortunately, over the last few years, much of the misinformation has come from the CDC itself.
So a ‘Minority Report’ style system that will identify vaccine misinformation pre-crime and eliminate it before it can get out will only add to public distrust.
A Soviet-style public health propaganda set-up is not going to increase vaccine take-up. The only way to do that is to provide transparent data and allow hypotheses to formulate. These can quite easily be shut-down with accurate and open data.
What does increase vaccine hesitancy, is not having a truly independent body to analyse pharmaceutical data and then trying to bury that data for 75 years. Misinforming the public that they are going to die without a vaccine was the most harmful thing they could have done to trust in public health. Along with the suppression of adverse event signals, harms and deaths. However rare they may or may not be, by hiding just one of these causes the public to question what else is being hidden.
So I would like to claim the $1,000,000 to reduce vaccine misinformation with the following steps:
- Firstly produce a product that actually does what it is supposed to do;
- Conduct proper trials that look at short, medium and long term risks;
- Create a truly independent body that not only analyses the data it’s provided with but tests the products themselves;
- Remove propaganda such as ‘95% effective’ or ‘safe and effective’;
- Don’t conduct studies on how to manipulate the population into taking vaccines;
- Don’t force anybody to take a vaccine (by use of the psychological techniques above or through vaccine passports);
- Don’t use fear to convince people they are going to die without being vaccinated;
- Don’t supress safety-signals;
- Don’t gaslight the vaccine injured or families with members killed by vaccines;
- Remove the product from the market as soon as any safety signals, injuries or deaths occur. Explain clearly and openly what has been found and why the product has been removed;
- Don’t label anybody concerned about big pharma corruption or vaccine safety a conspiracy theorist or worse.
There you go. You don’t need any fancy and expensive systems to get people vaccinated. Just follow the steps above. But unfortunately, if your product isn’t up to scratch, you won’t make any money. You can send my $1,000,000 cheque in the post. Thanks.
Did I miss any points? And is it too late anyway? Has the amount of public health misinformation eroded away all trust, never to be regained again?
The Lancet has become a laughing stock

By Norman Fenton and Martin Neil | Where are the numbers? | January 14, 2023
In summary:
- On 6 May 2021 The Lancet published a blatantly flawed study of the effectiveness of the Pfizer covid vaccine on the population of Israel, claiming it was 95% effective.
- On 17 May 2021 we submitted a rapid response 250 word letter explaining why the study was flawed.
- After an initial response saying they would ask the authors for a response to our letter we heard nothing until 20 months later.
- On 8 January 2023 we got an email out of the blue from The Lancet Senior Editor Josefine Gibson apologising for never having got back to us about the letter, saying that they had asked the lead author Dr Sharon Alroy-Preis (SA-P) to respond to our letter but, because she did not provide any formal response, they have decided not to publish our letter.
- We tweeted The Lancet’s response and within 24 hours it got over one million impressions. We also published a substack article highlighting the fact we were now aware of additional problems with the paper relating to SA-P’s relationship with Pfizer.
- On 10 January 2023 we got an unsolicited email from Josefine Gibson (which we can only assume was a result of the reputation hit they got from our tweet) saying “Thank you for bringing your letter from May 2021 back to our attention. We are looking into next steps and will get back to you as soon as we can.”
- On 11 January 2023 (at 10:58) we sent an email to The Lancet’s Editor-in-Chief Richard Horton directing him to our substack article (which highlighted these new problems relating to SA-P’s relationship with Pfizer) stating that The Lancet was clearly taking a credibility hit surrounding the publication of the Israel-Pfizer study and its response to criticisms of it.
- On 11 January 2023 (at 11:21) we got an email from Josefine Gibson apologising for the ‘sub standard experience’ we had with The Lancet. She said that, after discussing it with Horton, they were now inviting us to publish the original letter or an update to it, suggesting the update ‘reflect more current experience with the vaccine’.
- On 12 January 2023 we submitted our updated letter (of an agreed 350 words).
- On 13 January 2023 we got a response from Josefine Gibson saying they had decided against publishing the letter.
Here is the full narrative and January 2023 correspondence in date order (personal details redacted)… continue
Insider reveals truth about Covid-19 pandemic from within the National Health Service
How the misdiagnosis of deaths occurred and was due to changes from 2016
The Naked Emperor’s Newsletter | January 15, 2023
An ex-director at one of the largest hospital trusts in the UK decided they wanted to reveal what really happened during the pandemic. They have kindly allow me to reproduce their thoughts. The catalyst for this revelation, according to the insider, was Dr. Malhotra speaking out about cardiac problems post vaccination.
This is an interesting take on what happened inside the National Health Service (NHS) and confirms, with more details, what we already knew and suspected.
Introduction (Long but important to understand the rest)
In 2016, the British Government proposed & piloted a change to the process of how deaths were certified across all hospitals in the UK. I have attached a link to this Department of Health (DoH) document.
The DoH document proposed a switch to the “Medical Examiner” (ME) System and was sent to a number of different audiences for feedback and consultation. The ME system was already being piloted at two hospitals up north. The results of the consultation are here.
Prior to the Covid-19 Pandemic, the death certification process involved treating doctors of a patient to attend Bereavement Services/Patient Affairs to discuss the death and either:
a) refer the death to the Coroner or
b) write a Medical Certificate of Cause of Death (MCCD).
The MCCD states the cause of death. Whereby a direct cause (1a) or contributing causes (1b) (1c) (1d) are stated along with co-morbidities (not directly causing the death) being written in (2) on the MCCD. The MCCD is only ever a probable cause of death, it is not definitive.
The only definitive way of determining an accurate and plausible cause of death is to refer the deceased patient to HM Coroner (if certain criteria is met), for HM Coroner to accept and take on the case, resulting in a Post Mortem (PM) being conducted by a Histopathologist. When a death is seen as natural and there is nothing untoward, the MCCD is written by the treating doctor of a deceased patient. Usually this is an F1, F2, SHO or Registrar that attends. It is rare for a treating Consultant to attend, but they will finalise the cause of death.
A strict hospital hierarchy exists within the NHS for doctors. It is as follows – from lowest to highest rank: Foundation Year 1 (FY1), Foundation Year 2 (FY2), Senior House Officer (SHO), Registrar (Reg), Consultant, Clinical Lead, Medical Director. Junior doctors will very rarely speak up or challenge their seniors. A senior decision is seen as final and it will be carried out and executed without any hesitance or questioning. In my 5.5 years of experience in End of Life Care, I have only ever seen one junior doctor disagree with a proposed cause of death and challenge their consultant.
With the number of deaths that occur in a hospital, as you can imagine, there is a great deal of variation with regards to causes of death, as we have numerous different doctors writing an MCCD and coming up with various different potential diseases in different orders.
The proposed ME system would change this, as the government would now hire and pay one Medical Examiner, to sit in every hospital and write all MCCD’s for all deceased patients. This would effectively eliminate any variation in causes of death.
In 2016, when I heard of this proposal, I worked as a Bereavement Officer at a hospital in Central London. My mentor/line manager at the time was a former Chief Nurse who managed Bereavement Services and all hospital deaths would be controlled by her and the department.
We essentially carried a huge amount of power with regards to decision making, as we would go through all patient notes following the death of a patient, and essentially guide and advise doctors on what would need to be written with regards to an MCCD or Coroners Referral.
In my personal opinion, our role was to sit on the fence and act in the best interests of a deceased patient (and their families), but also protect the hospital and our doctors from any potential negligence. As you can imagine many battles were fought over decisions about a cause of death of a patient or a referral to the coroner with a vast amount of doctors over the years.
F2’s and SHO’s were particularly the worst with regards to carrying an arrogance of knowing what should be written on an MCCD or stating that a patient didn’t need to be referred to the Coroner (often stating that their Consultant had given them instructions). It is worth noting that Consultants are also only human and can be incorrect at times too. We have to remember that they are succeeded in hierarchy by a Clinical Lead and beyond that a Medical Director. Who have far more experience and knowledge.
When I asked my mentor in 2016, how the ME system would change things, I was told that Bereavement Services/Patient Affairs would become purely administrative and that the clinical judgement would fall to the Medical Examiner.
The power and decision making with regards to MCCD/Coroners Referrals was being taken away not only from treating doctors but also from Bereavement Services/Patient Affairs/Bereavement Officers/Bereavement Service Managers/Directors of End of Life Care.
This decision making power was being handed solely to the Medical Examiner, who has not been involved in the treatment of a patient during an admission. I took all this information in at the time and acquired as much knowledge as I could from my mentor/line manager.
In 2016, I also happened to make a move and take up an opportunity to manage my own Bereavement Services at one of the largest hospital trusts in the whole of the UK. On average, I would oversee MCCD/Coroner Referrals for approx 1750 deaths on an annual basis. I developed a very close working relationship and friendship with one of the Medical Directors (a doctor with the highest ranking in a hospital). This was especially helpful when having to challenge doctors with regards to MCCDs/Coroners Referrals.
Progressing to Director of End of Life Care, I became involved with the reporting of mortality rates, conducting mortality reviews and writing hospital policies. I had also developed an excellent working relationship with the HM Coroner who oversaw our Trust. HM Coroner holds the power to investigate any hospital or trust with regards to a death or a number of deaths. A slight problem may arise, in that HM Coroner has an allegiance to the Crown and the Government.
When a death is reported to the Coroner. This was previously reported via telephone call by the treating doctor. A discussion was had with the Coroners Office and a direct outcome and instruction would come from the Coroner’s Office, by way of HM Coroner (via a phone call).
There is a fundamental flaw to this system, as there is no documentation of the decision and instruction from the Coroner’s. It comes via word of mouth. There is always room for error without any electronic documentation. Every Hospital/Trust & HM Coroner will have a different system of reporting deaths. I personally made a decision to safeguard my hospital and the trust, by developing an electronic coroners referral form, which I proposed to our Coroner and developed after their agreement. We now had documentation of every death being reported and every outcome.
When reporting a death, the Coroner will look at a proposed cause of death and accept it, or reject the cause of death and take on the case (death of the patient), leading to an Inquest or a PM.
In 2019, our Medical Director, came into my office one morning and stated that the Board of Directors at the Hospital had made a decision to switch to the Medical Examiner System. Hearing the words ME system was a massive case of Déjà vu (conversation with my mentor in 2016). I knew exactly what the ME system was, but I chose instead, to play the fool and enquire what exactly the ME system was and what it meant for our service, my staff and our roles. Everything the Medical Director mentioned to me that day was a carbon copy of what I already knew
I knew that my time in End of Life Care had come to an end. I’d reached the top and there was no more progress for me. Losing all power and decision making to any ME coming into the hospital did not appeal to me. I’d already made up my mind that I needed to leave. Seeking a new challenge and experience, I made a move in 2019 to another major hospital in Central London, this time side tracking into operational management. I was in charge of the operational management of Nephrology, Rheumatology, Dermatology and Diabetes & Endocrinology.
2020 – Covid Arrives
In Jan 2020, I remember hearing about the first case of Covid-19 at our hospital, with a patient arriving from China and walking into our A&E. A&E was shutdown and steam cleaned that day, I recollect the moment I heard about this. In my mind, I saw the reporting of Covid-19 in the media as nothing more than Bird Flu or Ebola, which had caused panic but yet passed. I wasn’t worried in the slightest bit.
Things began to escalate around in Feb 2020, around the time I was going on holiday. Due to the reporting by the media, I bought N95 masks as a precaution for my trip and to give to my parents and younger sister. I was blessed to have had an opportunity to spend a few days in Sri Lanka for a wedding and then nearly a whole month in Australia (March 2020). I watched as the narrative of a deadly infectious disease continued to grow with every day that passed. I made a decision to cut my holiday short by a couple of days so that I could make sure I got back to my family and not end up being stranded in Australia.
Upon returning to the UK in late March 2020. One of the immediate things that struck me was the lack of any temperature monitoring or questioning at Heathrow Airport. This seemed odd for a potentially deadly infectious disease that was spreading around the world. This was especially odd, as Sri Lanka & Australia had questioned me/checked temperatures upon arrival, with even Singapore monitoring temperatures during transit.
My mother had just recovered from Cancer, my father was over 70 and my younger sister was born with Down’s Syndrome alongside having multiple other conditions. I had three high risk individuals to Covid-19 in my family and I was scared/fearful of giving them Covid-19. I asked my hospital to allow me to work from home. They refused. I wasn’t deemed high risk, although I lived with my parents at the time. I needed to help my mum and my sister. The hospital held no regard for the safety of it’s employees. They forced me to come into work. I spent two months isolating in my bedroom, I barely came out of my room, for fear of spreading an infectious disease. Never once did I think about the situation or my prior experience or knowledge, I was just reacting to the media frenzy. I was full of panic and stress.
The first irregularity I noticed, was the government and media stating that Covid-19 was an infectious disease. However just before the first lockdown was implemented, I noted that the government had downgraded the status of Covid-19 stating it was no longer infectious. This made no sense to me. Why would we need to isolate if they downgraded the status? My circle of friends contained many medics and dentists. They were all panicking at the time, saying they had inadequate surgical masks and that they needed N95 masks.
N95 masks were seen as the only way to prevent medical professionals from becoming infected with Covid-19. The public being asked to wear surgical masks made no sense to me. The virus would be able to go straight through. Something didn’t seem right.
I ended up meeting and dating an FY1 doctor (my ex gf) around October 2020. We clicked because she was different from every other doctor, I had previously spoken to about Covid-19. She also had her suspicions and believed it wasn’t as infectious as it was made out to be. We both started to slowly realise that Covid-19 was a real disease (as it was showing up on X-rays in patients) but that it wasn’t infectious at all [NE – I have since confirmed with them that they mean not as infectious as was being made out], despite all the reporting in the media.
I needed to experience working in a Covid-19 hotspot and see all the action for myself. In March 2021, I quit my job at the hospital in Central London and took up an opportunity to manage A&E and AMU (Acute Medical Unit) at a hospital in South London. The 6 months that I spent working in A&E/AMU confirmed all my suspicions and culminated in my decision to end my career in the NHS.
The entire 6 months, I was not tested once with a PCR Test, despite walking into wards full of Covid-19 Positive patients on a daily basis. Yet we were required to test multiple times when visiting another country.
The PCR Test that the NHS was using to test patients, is known to have false-positive results. This is shown in numerous studies which can be found online, an example of which is:
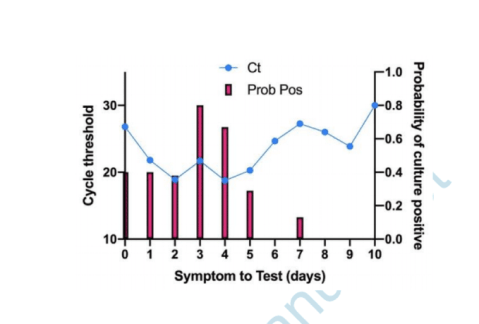
Are you infectious if you have a positive PCR test result for COVID-19? – The Centre for Evidence-Based Medicine.
If a patient tests positive for Covid-19 with a PCR Test, this doesn’t mean they are infected. If tested again, they may well turn out with a negative test. However in the NHS, patients are only tested once and this stays on their record throughout their admission. Hospital policies were changed alongside the implementation of the Medical Examiner System, to ensure that any patient who died within 30 days of positive test, would have to have Covid-19 as their primary cause of death. This was regulated by the Medical Examiner.
The highest cause of death at every hospital per annum pre Covid-19 is Pneumonia. Pneumonia is a Respiratory Disease like Covid-19. Pneumonia can be broken down into 4 different causes of death: Bronchopneumonia, Aspiration Pneumonia, Community Acquired Pneumonia & Hospital Acquired Pneumonia.
These four causes when added together kill the largest number of people on an annual basis prior to the pandemic.
The Medical Examiner (one individual in each hospital), was certifying all these Pneumonia deaths as Covid-19 deaths. When 4 different diseases being grouped and now being called Covid-19, you will inevitably see Covid-19 with a huge death rate.
The mainstream media was reporting on this huge increase in Covid-19 deaths due to the Medical Examiner system being in place. Patients being admitted and dying with very common conditions such as Old Age, Myocardial Infarctions, End Stage Kidney Failure, Haemorrhages, Strokes, COPD & Cancer etc were all now being certified as Covid-19 via the Medical Examiner System.
Hospitals were switching to and from the Medical Examiner system and the Pre Pandemic System as when they pleased. When Covid-19 deaths needed to be increased, the hospital would switch to the Medical Examiner System. Doctors were one week being told they needed to complete an MCCD, to then be told the following week that they weren’t required to fill out an MCCD, as the Medical Examiner was handling this.
Hospitals were incentivised to report Covid-19 deaths over normal deaths, as the government was paying hospitals additional money for every Covid-19 death that was being reported. The Medical Examiner system ensured that Covid-19 was being put down as the cause of death. The government sends out the annual NHS budget to Primary Care Trusts. This is split to fund Hospitals and GP Surgeries. A clinical coding team at each hospital will assign codes to each treatment or death, so that money is paid out to the hospitals.
Any doctor who argued against Covid-19 as a cause of death was bullied and vilified. The General Medical Council maintains a register of all doctors within the UK. This ensures that there is a fear of being struck off for speaking out against an agenda. The GMC effectively controls all doctors in the UK. Even if a doctor realises what is going on and wants to speak out. They will think twice about talking, as they would be risking their entire career and everything that they’ve worked so hard for.
Doctors essentially have their hands tied, many have families, kids, mortgages and mouths to feed. If I was in their situation, I would think twice about speaking out, for fear of being struck off by the GMC and losing everything.
The NHS Track & Trace App, which was introduced to try and control the spread of the virus, did not apply to medical professionals. We were all asked to turn this off, as Doctors and staff isolating for 14 days disrupted patient flow, beds and the discharge of patients.
Any doctor that I spoke to regarding taking the Covid-19 vaccine, were insistent that they were going to wait for a period of time, before taking it themselves, to ensure that it was safe. How is it ethical to give a vaccine to your patients, but not want to take it yourself? In my 12 years of NHS service, never has a doctor pushed or influenced the public to take a vaccine. Yet on social media, I was seeing close friends who were doctors, starting to post on social media that they have taken the vaccine and that the public should. I wouldn’t be surprised if doctors were being forced to promote the vaccine by their superiors or if they were receiving monetary gain in doing so.
I have no doubt in my mind, that the Government has planned the entire pandemic since 2016, when they first proposed the change to medical death certification. Stress leads to disease and illness. Panic leads to people following whatever orders and instructions that are given to them by authority, such as prolonged mask use, which leads to an increase in admissions in to the NHS system due to hypoxia and bacterial pneumonia.
The NHS treatment pathway involved patients being placed onto ventilators. There is a 50% chance of death from this clinical decision alone. How many innocent people have died from the clinical decision to place them onto a ventilator.
During boardrounds (where every admitted patient is discussed), we were seeing patients on a daily basis being admitted due to suffering from adverse affects of taking the vaccine. Patients were blacking out after taking the vaccine or suffering from clots or strokes.
The NHS is all about money and making money. The safety of a patient didn’t seem like the most important thing. It was more about how do we make more beds available so that another patient can be treated. Patients with no next of kin are discharged to nursing homes with care packages. I can’t comment on what happened to these patients in nursing homes, during the pandemic, as I have no experience of their inner workings.
Patients are seen as money, even upon death, hospitals receive money for each death. Is there an actual concern for patient health and safety? I know numerous doctors who are driven primarily by money and monetary gain.
THE REASON WHY I LEFT THE NHS in 2021
56 yr old male, admitted into A&E with end stage kidney failure, has a previous history of regular dialysis treatment for this. No respiratory symptoms on admission and no temperature. However when tested with a PCR Test he unfortunately tests positive. This stays on his record throughout his admission. Our hospital is relatively small in comparison to others I have worked at, we have no dialysis machine as a result. We urgently need to transfer this patient to another hospital otherwise this patient will die. Our treating doctor calls up larger hospitals with a dialysis machine to organise his transfer. All doctors pick up the phone and request the Covid-19 status of the patient. A transfer is declined due to a Covid-19 infection protocol. Our doctors again reiterate the point that this patient will die without dialysis. We are told there is nothing that can be done and that the patient cannot be accepted for transfer.
This gentleman ended up dying without dialysis. Now please tell me what goes on the MCCD….
1a) Covid-19
2) End Stage Kidney Failure
Not written by the treating doctor who disagreed with this cause of death, but by a medical examiner, put in place by the government and the hospital.
When innocent people are being killed by a corrupt organisation and system, for pure monetary gain, I can’t stand by and be part of this anymore. My conscience was clear and I no longer wanted to be a part of this anymore. I am very blessed and lucky that I was in a position to walk away. I’ve been able to speak out, because my hands are not tied and I am not regulated by any organisation or governing body. I believe in speaking the truth and in doing so, I am only just an instrument for God.
I joined the NHS, 12 years ago because I had a desire to help those in need, but the moment I realised that I was not doing this anymore was the time for me to walk away. I apologise to you all if the above thread is confusing with regards to terminology or you cannot understand it’s contents. I’m hoping that at the very least, it can be understood by my fellow medical professionals or by journalists who would like to report the truth.
Authorities want to grab/jab our kids and are trying to legalize 11 year old vaccine consent
It was beaten down in DC but that did not stop these criminals
By Meryl Nass | January 15, 2023
I have the documents showing that kids in Philadelphia, San Francisco and Kings County, WA were given COVID vaccines without parental permission. I have been told this happened elsewhere. So the perps are doing what makes sense for them: trying to legalize the process so they can’t be penalized for this crime.
Why are their efforts so focused on HS and college kids? To give kids access? ‘Access’ my A—-ss.

The age of ‘self-consent’ was lowered to 11 from 12 by Philadelphia’s health authorities. Presumably CDC came up with this brilliant idea.
Now, In order to give itself cover regarding the fig leaf that children can in fact provide a legal informed consent without a parent or guardian, the Health Commissioner of Philadelphia, PA claimed that handing a totally inadequate EUA “Fact Sheet” to an 11 year old at the time of vaccination would substitute for informed consent.
However, we know that the Fact Sheets that were used in lieu of a package insert omitted known information on health risks of the vaccine and incorrectly stated the benefits of the vaccine. So how could there be informed consent?
WHEREAS, on April 21, 2021, the Health Commissioner issued an Emergency Order
Concerning COVID-19 Vaccine Information Statements, which clarified that an FDA-issued COVID-19 Fact Sheet for Recipients and Caregivers is an appropriate substitute for a VIS for purposes of Section 4 of the Board of Health’s Regulations Governing the Immunization and Treatment of Newborns, Children, and Adolescents; and
WHEREAS, on May 10, 2021, the FDA authorized a COVID vaccine for use in people twelve years of age or older pursuant to an EUA; and
WHEREAS, the Board of Health hereby reaffirms, consistent with Section 4 of its Regulations Governing the Immunization and Treatment of Newborns, Children, and Adolescents, that minors eleven (11) years of age and older are typically capable of providing informed consent on their own behalf to be vaccinated for a reportable disease, subject to a vaccine provider’s individual determination that the minor is able to and does provide such informed consent, and the Board hereby clarifies that an FDA-issued COVID-19 Fact Sheet for Recipients and
Caregivers is an appropriate substitute for a VIS; and
NOW, THEREFORE, the Board of Health hereby adopts the following emergency regulation, effective upon delivery to the Department of Records, while the remaining procedures and formalities of Section 8-407 are followed to promulgate this as a formal regulation:
Section 1. Temporary Emergency Supplement to Board of Health Regulations
Governing the Immunization and Treatment of Newborns, Children, and
Adolescents
With respect to a minor eleven (11) years of age or older, the Emergency Use
Authorization Fact Sheet for Recipients and Caregivers for a COVID-19 vaccine authorized by the U.S. Food and Drug Administration for use in persons of the age of the vaccine recipient, if and when such an authorization exists, may be provided for the purposes of Section 4 of the Board of Health’s Regulations Governing the Immunization and Treatment of Newborns, Children, and Adolescents, when a Vaccine Information Statement does not exist for the COVID-19 vaccine being administered…https://vax.phila.gov/wp-content/uploads/2021/05/BOH-reg-VIS-substitution-1-2.pdf
Turtles All the Way Down: Vaccine Science and Myth
Edited by Zoey O’Toole and Mary Holland
 If you are reading this, you are probably aware of the fierce debate surrounding vaccination and looking for information that will allow you to make the best decisions for yourself and your loved ones. Whether you are a parent or a parent to be, sorting through the many arguments on vaccines can be daunting. Still, you need an answer, a definitive one, to the crucial question: Who has it right in the great vaccine debate – the critics, who claim that vaccines often cause serious harm, or the medical establishment, which tells us that vaccines are safe and effective and the science is settled?
Rest assured, you have come to the right place. “Turtles All the Way Down: Vaccine Science and Myth” will resolve the vaccine question for you, once and for all. By the time you finish reading, not only will you see the answer clearly for yourself, you will also have the scientific references and specific quotes at your disposal that prove it — more than 1,200 of them – all from mainstream scientific papers and textbooks, the official publications of relevant government agencies, or manufacturers’ documents.
The book consolidates a great deal of information (accompanied by detailed analysis) that is scattered in hundreds of medical articles, books, and websites. All discussion is presented in clear and easy-to-understand language, so no medical education is required. It presents several original concepts in addition to laying a robust scientific foundation for the more established ones.
Some of the fundamental vaccine safety issues covered in the book are:
- How is safety demonstrated before a new vaccine is licensed? What technique do vaccine manufacturers use in clinical trials to make vaccines appear safer than they actually are?
- What “last ditch” technique is employed when the above one cannot be, and what are its grave (and damning) ethical implications?
- What is the scientific foundation of the safety of vaccination, and what practical tools does this body of science provide physicians to anticipate, diagnose, and treat vaccine injury?
- What fundamental flaws are built into vaccine adverse events reporting systems, and how are these systems used (or misused) by health authorities to support their safety claims?
- What kinds of post-marketing vaccine studies are conducted, and how can they be manipulated by researchers to produce “favorable” outcomes?
- Why would researchers want to skew vaccine research, and how could skewed results be promulgated by the scientific community?
- Why would medical journals publish faulty vaccine science? What is the role of the famed “peer review” in this process?
- What are “the studies that will never be done” by the medical establishment and how long it has resisted doing them? (Hint: more than 100 years!)
- What key CDC-recommended childhood vaccination guidelines were arbitrarily set, without an adequate scientific basis?
In addition, three cornerstones of vaccination lore are covered in depth:
- What is herd immunity, and how does it apply (or not) to the vaccines on the childhood schedule?
- What role did vaccines actually play in the historical decline of infectious disease?
- Was the paralysis associated with polio actually caused by the poliovirus? Is there a better explanation for the great paralysis epidemics of the 20th century? What are the “19 polio mysteries”?
The book is intended for parents overwhelmed by conflicting messaging on this important topic, but it is also an excellent reference for medical researchers and professionals who seek a better understanding of vaccine safety science. Whether you are new to the vaccine debate or a “veteran” seeking a deeper grasp of the science, this book is a must-read. It also serves as an excellent primer on vaccination to share with friends and relatives who may benefit from a deep dive into the subject.
Who designed global guidelines for puberty blockers?
Free West Media | January 13, 2023
Clinics around the world follow guidelines from the Netherlands for gender treatments in children. The basis for this is, among other things, a much-criticized study sponsored by a German hormone manufacturer.
More and more children and young people believe they have to question their gender identity. Some 60 minors were treated in the Netherlands in 2010, but the number has increased to around 1,600 last year. Another 1,800 people under the age of 18 were on the waiting list because gender clinics in the country are full.
Institutions around the world use a standard procedure developed in Amsterdam in the 1990s when it comes to the drug treatment of supposedly transsexual children.
A report by the Dutch newspaper NRC Handelsblad has meanwhile cast doubt on the directive and the independence of gender research at the Amsterdam UMC hospital. As strict as the conditions for treatment may appear, several complications have been overlooked: The terrible side effects of the heavy drug has been brushed off by doctors as being the lesser evil.
Hormone manufacturer sponsored ‘puberty blocker’ study
The approach with puberty inhibitors has since been known internationally as the “Dutch protocol”. The protocol has become the basis for the “gender-affirming standard of care” used throughout the world. Tens of thousands of children are affected worldwide, and in the Netherlands certainly several hundreds, although no precise figures are available.
Scientists investigated whether hormone treatment in transsexuals is more successful if their puberty was initially suppressed with medication. The sponsor of the study was the German hormone manufacturer.
Ferring Pharmaceuticals, the company that markets the drug Triptorelin as a puberty inhibitor had a strong commercial interest in the outcome. Primarily, treatment relies on administering hormones from the opposite sex: men are given oestrogen to become more feminine, women testosterone to become more masculine. But teenagers are additionally administered puberty inhibitors, which prevent boys from developing a low voice and beard growth and girls from developing breasts and other feminine shapes.
There are many criticisms of the study. Questionnaires were inconsistent, there was no control group at all, and the researchers used random samples from the 196 treated children for the results.
Several countries are moving away from ‘puberty blockers’
In the meantime, there is objection in more and more countries to the treatment of children with “puberty blockers”. Not only are they said to impair the physical sexual development of minors, but they can also cause osteoporosis, anorgasmia and infertility. According to the NRC, the drug is said to sometimes even impair the ability to make rational decisions.
Worldwide, there is increasing criticism of the scientific content and non-existent empirical basis of the Dutch protocol developed at the gender clinic of the Free University of Amsterdam. In several countries, health authorities have already decided to treat children mainly psychologically and prescribe puberty inhibitors only exceptionally. In Sweden, they concluded that “the risks currently outweigh the possible benefits” and spoke of possibly the country’s “worst medical scandal”.
In the UK, criticism of the Dutch protocol was so serious that the Tavistock gender clinic, the largest in the world, was closed by the authorities.
Sweden, Finland and Great Britain only want to prescribe the drug in rare, particularly severe cases. Instead, they are increasingly relying on psychological support for patients.
Since February last year, Sweden’s National Board of Health and Welfare has followed the Karolinska Institute’s policy regarding hormonal interventions for gender-dysphoric minors. Karolinska’s pediatric gender services at Astrid Lindgren Children’s Hospital (ALB) has ended the practice of prescribing puberty blockers and cross-sex hormones to gender-dysphoric patients under the age of 18.
Marketing redundant drugs for the wrong condition
In the US, Texas Attorney General Ken Paxton has been investigating two pharmaceutical companies for advertising puberty blockers to children. This is a condition they are not approved to treat.
In December, Paxton announced investigations under the Texas Deceptive Trade Practices Act into Endo Pharmaceuticals and AbbVie Inc., the two companies that sell puberty blockers. The drugs were approved to treat precocious puberty and forms of prostate cancer but were being marketed and prescribed off-label to treat gender dysphoria.
“These drugs were approved for very different purposes and can have detrimental and even irreversible side effects,” Paxton said. “I will not allow pharmaceutical companies to take advantage of Texas children.”
Moscow: Sweden’s Refusal to Share Nord Stream Findings Suggests They’re ‘Hiding Something’

Samizdat – 14.01.2023
Russia’s Foreign Ministry spokeswoman skewered Sweden for staying silent about the identity of the perpetrators of the notorious terrorist attack that crippled Russian revenues and European energy supplies.
Sweden’s refusal to disclose the results of its investigation into the terrorist attack that crippled the Nord Stream pipeline in September suggests Stockholm is “hiding something,” Russian Foreign Ministry spokeswoman Maria Zakharova has said.
As one of the attack’s primary victims, Russia deserves answers, Zakharova told reporters at a Thursday briefing.
“The refusal of the Swedish side to respond on the merits to another request from the Russian Prosecutor General’s Office for legal aid in the criminal case on Nord Stream and Nord Stream 2 pipeline damage in September 2022 is genuinely perplexing,” Zakharova said.
A message sent three months ago by Russian Prime Minister Mikhail Mishustin to the head of the Swedish government regarding “the need to conduct a comprehensive and open investigation” of the attacks with Moscow officials still “remains unanswered,” Zakharova explained, noting Sweden’s silence stood “in defiance of all the decorum of international diplomatic communication.”
“Stockholm explains its refusal by saying… that meeting the Russian request will allegedly ‘pose a security threat to Sweden,’” she noted.
“What are the threats to national security that Stockholm is talking about?” Zakharova asked.
“Who committed these sabotage and terrorist acts, who is behind them, who devised and implemented them – withholding the established facts irrefutably testifies to the obvious: the Swedish authorities are hiding something.”
Sweden invoked the same ‘national security’ justification in October when attempting to explain why it was unwilling to commit to a joint investigation on the Nord Stream attack alongside Germany and Denmark.
As the main recipient of Nord Stream’s affordable supply of Russian gas, Germany was arguably the prime beneficiary of the pipelines. But Moscow has also suffered serious economic damage as a result of the act of industrial sabotage.
“We consider ourselves to be the party that sustained material damage, to say nothing of losses,” Zarakhova explained.
As such, “we have the right to receive appropriate information, have the right to ask questions and demand an answer to them,” she said, adding “we must make sure that it doesn’t happen again in the future.”
Ivermectin’s Effectiveness Proven Again; 72% Efficacy
800,000 people died in the USA for nothing
By Igor Chudov | January 11, 2023
You are not a horse! You are not a cow! That’s what the FDA told us to dissuade us from taking Ivermectin.

Fortunately, we are also not sheep and did not believe the FDA. Many of us stocked up on Ivermectin, and most found it helpful. While I did not use it when I had my Covid in Nov 2020, it worked great for my wife in Dec 2021 and other family members during the summer of 2022.
Ivermectin, a cheap and safe generic medication, was of little interest to profit-minded pharmaceutical giants like Pfizer and Merck. Therefore, they conspired with the FDA to lie that it did not work and instead pushed expensive Covid vaccines and non-working drugs like mutagenic Molnupiravir and rebound-causing Paxlovid.
MedinCell conducted a randomized controlled trial of their version of Ivermectin and found that it reduces Covid infections by 72%!

The study was very well designed because the participants were EXPOSED to the Covid infection within five days. Given the exposure, the outcomes were more likely to happen and thus were easier to compare between groups, giving the trial greater statistical power.
The 72% reduction in infection is much MORE effective than the “covid vaccine.”
The trial encompassed the period of Mar-Nov 2022, thus giving us the real-world effectiveness of Ivermectin against the Omicron variant.
While I am happy at the finding, there are several things to be NOT happy about.
- If we are to believe official numbers, about 1,121,000 people died of Covid in the USA. Given published effectiveness estimates of Ivermectin coming from honest studies, Ivermectin could have saved eight hundred thousand of those lives. The intentional suppression of Ivermectin cost us so dearly.
- Given a 72% reduction in infection, natural immunity with Ivermectin would likely have stopped the pandemic entirely in 2020.
- Had Ivermectin been recognized as an effective antiviral, the “Covid vaccines” could not get EUA approval, and thus we would avoid thousands of vaccine victims and destroyed immune systems.
- Second-largest Democratic donor and the largest crypto thief Sam Bankman-Fried donated 18 million dollars to the Together trial after it falsely demonstrated a finding that Democrat-aligned Covid vaccine pushers wanted, namely that Ivermectin allegedly was useless.

The good news here is that Ivermectin works.
Here are some of my other articles about Ivermectin — with honest trials showing a comparable reduction in illness and death.
So, thousands of people died of Covid. Thousands of people died of Covid vaccines. The pandemic, prolonged by vaccination, is raging and reinfects people with immunity disabled by mystery genetic treatments. My prediction from last March, unfortunately, is coming true.
AIDS-Like “Chronic Covid” is Taking Over Europe, Australia and NZ
All of this happened because of the recklessness and greed of the biomedical-industrial complex, which developed Sars-Cov-2 and then pushed an unproven, ineffective vaccine that worsened the pandemic.
While the above paragraph is upsetting, the good news is that Ivermectin was validated, and “we have the tools” to manage a Covid infection or exposure.
Lastly, take a minute to think about millions of victims of suppression of Ivermectin worldwide, who died to make a few companies and foundations richer and more powerful.
Will Ivermectin ever be recommended officially? And do we even care about such approval if we can still order it online?
Nobody is safe from the Nudgers
Even Prime Ministers
The Naked Emperor’s Newsletter | January 11, 2023
The Behavioural Insights Team (BIT) was set up in 2010 by the UK Cabinet Office to nudge the population into doing things they might not necessarily decide to do without prompting. Since then it has gone from strength to strength, massively expanded and its methods exported around the world.
David Halpern, a British psychologist, has been in charge of the BIT since its formation. In an astonishing admission in a recent Telegraph ‘article’, David revealed how he and his team even used their techniques on Boris Johnson, the Prime Minister of the UK at the time.
Professor Halpern and his team had decided that everyone needed to wear masks but Boris wasn’t as convinced. This was probably due to all the previous advice, trials and science showing that masks did little to help during a pandemic. However, the behavioural scientist thought it was their jobs to push back against Boris’ leadership that saw masks as “nonsensical”.
“We did share with him a slide pack at one point. It had a series of images of pretty much every single world leader wearing a mask, and then a picture with him not,” he recalls. This nudge was used to point out that “a normal thing for a world leader to do right now is wear a mask”.
David Halpern brazenly tells the British public how he used psychological techniques to change the mind of the man running the country. From his point of view, it is perfectly acceptable to use nudging on anyone and everyone, no matter their position, on an issue that he has decided is the correct path to take.
And this is the nudging he admits to, what else did he nudge Boris Johnson or other members of the government to do without them realising it?
The ‘article’ was in fact a piece commissioned for the Reckitt Global Hygiene Institute an “independent, not-for-profit founded in 2020 to generate practical, high-quality scientific research and behavioural insights in the area of health hygiene”.
But how ‘independent’ and ‘not-for-profit’ is an institute set up by a company motivated by profit? The Institute was set up by the Reckitt Benckiser Group (trading as Reckitt) whose brands include Dettol (antiseptics), Disprin & Neurofen (pain killers), Strepsils (sore throat medicine), other health and cleaning brands and…you guessed it…masks.
For example, in 2018, Reckitt teamed up with the Cambridge Mask Co to produce masks combatting the effects of air pollution.
So where is the line between nudging and advertising? Here we have a company motivated by profit, setting up a behavioural insights research team which no doubt advises the BIT on health hygiene issues. The BIT then nudges the population to buy and wear masks, which in turn leads to a healthy profit for the original company.
And if something gets in the way, like the leader of a country, no matter, we’ll just nudge them to do what we want.
The Telegraph ‘article’ notes how, in the US, mask wearing became a political issue, which happened to a much lesser extent in the UK. They determine that not wearing masks in the UK is due to cultural, not political reasons.
Comparing mask-wearing in East Asia to the UK, they seem to suggest that the way forward is for the state to be given more power.
“Because of that experience [past pandemics], they have changed their statutory laws to allow the state to have certain rights during a pandemic that trump individuals’ liberty.”
Another reason masking in the West is so controversial, according to the ‘article’ is that we don’t have a collectivist mindset.
“it’s harder to get people to do something they don’t want to do for the common good,” Prof Kwong said. “Even if it’s something as simple or as easy as wearing a mask.”
David Halpern thinks there is a link between experience and collectivism. Therefore because of Covid-19 “the response to a future pandemic may be more prepared and less individualistic”.
In a glimpse at what may be in store for the West, Professor Halpern explains how ‘behavioural and cultural imprinting’ may be used to create ‘habit loops’.
“in the same way that your body reacts to seeing the virus before… behaviourally some of the same is true. You can respond because the behavioural pathway is ready.” This allows for a “much clearer habit loop” for everyone, as well as for society.
So to encourage future masking there will be several focus points. Using key figures to create a ‘thread’ or ‘prompt’ to declare a social norm. Religion will also be targeted to create ‘social cues’ as well as clear messaging.
All of this combined creates a ‘scaffolding’ which can then be removed once mask wearing becomes habit.
“It’s like a little booster shot for your vaccination,” said Prof Halpern. “Occasionally you need to be reminded of wearing a mask. Then it can become quite a robust habit.”
In this revealing insight in to how the head of the BIT thinks, we can see that David Halpern has no problem into nudging world leaders to follow an agenda that he has deemed to be the correct one. Everything must be done for the common good so individuals can’t stand in the way.
With a complete lack of transparency in the BIT, especially now that it is private company, we have no idea what ‘common good’ agendas they are pursuing. The common good might benefit society as a whole but be detrimental to a segment within it. Is that ok?
We have learnt recently that children were forced to wear masks in school purely to appease teaching unions who threatened to stop teaching. So in this case the common good can be defined as keeping children in school, justifying nudging the use of masks. It is easy to find a common good to pursue which can then result in the justification of something bad.
And using the common good can quickly get out of hand. The defence cultural specialist unit, which co-incidentally was launched in the same year as the BIT, works “side-by side with psychological operation teams”. This unit is part of the infamous 77th Brigade which has been used against Covid misinformation.
This in turn can lead to a whole legion of fake doctors pushing for masking and lockdowns.
The masking nudging/propaganda is returning again which can be seen in this Times article. Wear a mask to help the health service. Wear a mask voluntarily so that we don’t succumb to another bout of Covid. Wear a mask, it’s the responsible thing to do.
Clear as day when you understand what is going on but for the rest of the population the masks will start being worn again.
Featured Video

Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
or go to
Aletho News Archives – Video-Images
From the Archives
Why Saudi Ties to 9/11 Mean U.S. Ties to 9/11
By Kevin Ryan | Dig Within | September 27, 2015
Media interest in Saudi Arabian connections to the crimes of 9/11 has centered on calls for the release of the 28 missing pages from the Joint Congressional Inquiry’s report. However, those calls focus on the question of hijacker financing and omit the most interesting links between the 9/11 attacks and Saudi Arabia—links that implicate powerful people in the United States. Here are twenty examples. … continue
Blog Roll
 Aletho News
- Neria Leiter Was A Legitimate Military Target
- Integrity Initiative: UK-funded network framed dissent as Russian disinformation for years
- ‘We don’t seek permission to defend our country’: Snippets from President Pezeshkian’s UNGA address
- NATO chief wants Europeans to fight American wars [for Israel]
- German chemicals giant reveals details of downsizing
- Refaat Al-Areer Was The Canary In The Coal Mine In Israel’s War On The Truth
- Israeli election committee bars candidate from Knesset race over Gaza war opposition
- French-Lebanese man files war crimes complaint over Israeli attacks
- Mahan Air Flight Lands in China Despite US Threat against Iranian Airlines
- US eyes $10bn fund to rebuild war-battered Gulf infrastructure
- If Americans Knew
- Caught on Tape: AIPAC CEO Boasted of Controlling Trump’s National Security Officials
- Why Hamas Attacked Israel in October 2023 – Israeli professor Ilan Pappé
- They see them, then kill them: Israeli quadcopters track, deliberately target civilians in Gaza
- Winter could turn Gaza’s treacherous, war-damaged buildings into deathtraps
- Majority of Democratic Voters Want to Prosecute Both Biden and Trump Administration Officials Over Gaza
- As Gaza languishes, world leaders gather at the UN – Daily Update
- Sanctions are collective punishment: immoral and self-defeating
- Phosphorus Munitions Fired by Israel Burn Groves, Orchards in Southern Lebanon
- Israel Carries Out New Ceasefire Violations Across Gaza
- AI – Emphasis on the ‘I’: Israel Is Funding AI Chatbot Propaganda
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

