Sky News has just run a story which includes this paragraph about people living in Moscow:
‘Now it is the police who people are scared of, and the pervasive Orwellian fear of speaking out against the official line.’
I didn’t know whether to laugh or cry.
If a reporter or an editor at Sky News would pop their heads out into the real world they would know that Moscow is no more oppressive, repressive and suppressive than London, Paris, New York and every other city in the West. They’d also know that fear of the police is now common in the UK and elsewhere.
Doesn’t anyone at Sky News actually look at the news?
I’m sure there are restrictions in Moscow.
But there is NO freedom of speech in the UK.
Hundreds of doctors and other truth-tellers have been banned, ostracised and demonised by the mainstream media.
Many have, like me, been demonised on Wikipedia, suppressed and de-ranked by search engines like Google, or outright banned by YouTube – simply for telling the truth and sharing facts.
In the last two years I have been attacked and/or lied about by: Sky News, BBC, Daily Mail, Mail on Sunday and most other parts of the mainstream media.
My crime?
Telling the truth about the Covid fraud – and spreading solid facts in a world dominated by the deliberate dissemination of misinformation.
I’ve spent my life working for the media, but I am now banned from all mainstream media.
I have had four books banned in the last two years.
I have been banned from YouTube, Facebook, Twitter, LinkedIn and all other social media platforms. I am even banned from accessing YouTube. YouTube removed my channel, with over 100 videos. It had acquired well over 200,000 subscribers in just a couple of months in 2020.
I was expelled from the Royal Society of Arts for the crime of telling the truth.
And so on, and so on.
I became a ‘conspiracy theorist’ overnight – for daring to share the truth.
I have repeatedly challenged Whitty and Vallance to a live TV debate. But they have ignored the challenge.
If any producer at Sky TV had the guts to give me five minutes of live airtime, I could broadcast the evidence which would destroy the whole Covid fraud. The proof that Covid was the rebranded flu. The proof that government scientists admitted that Covid was no more deadly than the flu. The proof that mortality rates in 2020 and 2021 were much the same as previous years. And so on and so on.
But they won’t dare let me anywhere near a studio.
I believe that is because the mainstream media in the UK does what it’s told to do.
So, report what is happening in Moscow. That’s important.
But Sky, and others, need also to report how the truth is being suppressed in Western cities.
Because the suppression of the truth is dangerous wherever it is happening.
***
Vernon Coleman’s book Endgame explains what has happened, what is happening and what will happen next. Endgame is available as a hardback, paperback and eBook.
March 3, 2022, CDC director Dr. Rochelle Walensky answered questions in front of medical students at her alma mater, Washington University. This is an excerpt of the 45-minute presentation,1 during which Walensky made several statements about the public health response to COVID-19 in the past two years, admitting the CDC had relied heavily on vaccines, that she’d learned of the 95% efficacy from CNN and was not told the shots would lose effectiveness.
In fact, much of her presentation is riddled with statements that likely revealed more than she intended. She might not have realized the presentation was being taped or thought a taped presentation in front of medical students wouldn’t be found. Or maybe, the CDC simply doesn’t care that what they say in 2022 is the same information that caused many to be censored or maligned in 2020 and 2021.
It would be an interesting test to repeat her statements on social media today to see if the information would be tagged as misinformation or disinformation now that the CDC has publicly recognized what scientists have been saying for years.
Walensky Admits Her Source Was CNN
Walensky was invited to speak to the medical students at Washington University as the 2022 Gerald Medoff Visiting Professor in the Department of Medicine. During the interview conducted by Dr. William G. Powderly, co-director of the Division of Infectious Diseases, she was asked what the CDC got right and how that might affect the response to future pandemics. Three minutes into her answer, she said:2
“Where could we have improved? Well, you know, I think … I can tell you where I was when the CNN feed came that it was 95% effective, um, the vaccine. So many of us wanted it to be helpful. Many of us wanted to say, “OK, this is our ticket out.” Right? Now we’re done.”
This may be a mind-blowing admission — that the head of the CDC’s information came from a CNN news report and not from Pfizer. It turns out the CNN report was a regurgitated Pfizer press release. Investigative journalist Paul Thacker, writing in The Disinformation Chronicle, discusses the timeline of events that led to Walensky believing the Pfizer vaccine was 95% effective.3
It is likely the CNN report Walensky is referring to was published November 18, 20204 by Maggie Fox and Amanda Sealy, who it appears did little to augment the story after pulling information from a Pfizer press release published the same day.5 What is remarkable, and unfortunate, is that a story in CNN influenced Walensky’s thinking about the vaccine and future guidance from the CDC.
It turns out it is even more deplorable since it wasn’t a story but a republished press release. Also interesting is that it took two CNN reporters to present one republished press release/story. As Thacker writes, “The Pfizer press release became CNN headline, became CDC pandemic policy.” Walensky went on to say during the interview:6
“So I think we had perhaps too little caution and too much optimism for some good things that came our way. I really do. I think all of us wanted this to be done. Nobody said waning, when you know, oh this vaccine is going to work. Oh well, maybe it’ll work — (laughs) it’ll wear off. Nobody said what if the next variant doesn’t, it doesn’t, it’s not as potent against the next variant.”
Thacker dug into the published transcript7 of a Pfizer earnings call held February 2, 2021, in which an analyst from global financial services firm Cantor Fitzgerald asked four pointed questions.
If the COVID vaccine becomes routine, how do you think governments and physicians will choose among these vaccines that have received emergency use authorization?
And then how do you think about that 95% efficacy rate in light of mutations?
And the last question is on your PCV20, if it’s approved, what do you expect the ACIP [Advisory Committee on Immunization Practices] recommendation to be your — what would you ideally like it to be?
And do you think there will be any upgrade for those 65-plus due to the additional serotypes?
It seems interesting that the analyst from Cantor Fitzgerald understood enough to ask about whether the vaccine would be effective against a virus nearly every scientist in the world expected to mutate. And yet, Walensky did not consider the possibility,8 despite having been a professor of medicine at Harvard Medical School with years of experience dealing with viruses.9
Where Does the COVID ‘Science’ Come From?
When asked about the ACIP recommendation, Pfizer responded, “And then to your question about ACIP. Of course, we’re working closely with the FDA for approval and with the CDC at the right moments in time to get the right recommendation.”10 Many believe that the “right recommendation” was not given, yet Pfizer likely got exactly what they wanted from the CDC.
Walensky has overruled or avoided asking the ACIP’s advice on COVID booster issues at least three times, according to a STAT News report.11 As Thacker writes, this sequence of events is:12
“… direct evidence of a corporation influencing federal policy by laundering their press release through media outlets like CNN. Further, republishing press releases seems a pervasive practice in how the media covers COVID-19 vaccines — meaning, they don’t do much reporting. This has been obvious since late 2020.”
Walensky’s presentation at Washington University was just days after it was revealed that Biden and the CDC are parroting talking points developed by the same firm that conducted polling for Biden’s 2020 presidential campaign.13 The memo sent February 24, 2022, closely matches statements Biden used in the State of the Union Address.
In other words, it appears that at least some of the “science” driving public health policy for COVID-19 and destroying the economy is coming directly from Impact Research,14 who are “the proud pollsters for President Joe Biden” and whose marketing includes “electing Democrats in the toughest districts,” “electing presidents” and “crafting the most authentic and persuasive language for your communications.”
Two days after Walensky spoke at Washington University, former New York Times reporter Alex Berenson, wrote,15 “She’s right. Nobody could possibly have known variants might be a problem.” Under this, he posted a tweet dated January 20, 2021, in which he had posted, “Spoiler alert: the vaccines probably don’t work against at least one new variant and they’re going to want you to get vaccinated again next fall.”
By August, Twitter banned Berenson permanently for “repeated violations of our COVID-19 misinformation rules.”16 The tweet that put Twitter over the edge compared the vaccine to a “therapeutic “with a limited window of efficacy and terrible side effect profile.” He also questioned vaccine mandates.”
Data supporting limited efficacy17 and terrible side effects18,19 are not difficult to find. In fact, Walensky admitted the vaccine has limited efficacy to Washington University — will Twitter ban her?
Walensky Knows She’s Wrong for Half the Country
Midway through the interview, Powderly asked how Walensky balances the risks of infectious disease against the mental health and economic risks from decisions the CDC has made. Her response was telling:20
“This is such an important question. The easy answer is I know I’m going to be wrong for half the country (laugh) so now that I’ve accepted that um … some fraction of people will be unhappy.
We are looking under the lamppost of all the cases and all the deaths and there have been so many other things that we’re counting that don’t make the headlines — opioid deaths, mental health challenges, cancer screening. I’ve heard from colleagues of people who came in whose elective surgeries were deferred who now come in with metastatic disease.”
Minutes before, she was asked what she thought the next couple of years would look like. She started by saying, “So this is a safe space because every piece of advice I’ve gotten is don’t predict what’s going to happen.”21 The implication appears to be that she didn’t think what she said would be made public. She went on to predict that in the months ahead she believes:
“… [O]verall immunity is going to hold us in good stead. I don’t know whether we’re going to need another boost and I don’t know when and I don’t know what that’s going to look like but I do think ultimately we will have a good level of population immunity for variants that come our way … Ultimately we will have a coronavirus that will lead to death in some people every season, that we will tolerate in some way.”
This coronavirus that will lead to death every season sounds amazingly like seasonal flu. The final estimates by the CDC22 of the 2017-2018 flu season showed 41 million people were symptomatic with an estimated 18.9 million who received medical care, 710,572 who were hospitalized and 51,646 who died.
She also hinted that mask-wearing may be here to stay, saying, “I haven’t had a cold in a really long time, and I suspect we don’t miss those.”23 Yet, Walensky has also admitted that the CDC’s mask policy for public schools to reopen was influenced by teachers’ unions who were against in-person learning.
In other words, the guidelines for children to wear masks throughout their school day were not developed based on science but, rather, on “hearing firsthand from parents and teachers directly about their experiences and concerns.” and “superintendents, principals, civil rights groups, and all sorts of other folks.”24
Despite History, CDC Is Calling for Transparency
Anyone who has held an opinion that differs from the mainstream narrative has been censored, questioned and fake “fact-checked” so the debate over science would never see the light of day. Mainstream media outlets took up the banner, quashing any information that didn’t neatly fit the story.
If data might demonstrate that the vaccine was not functioning the way it was promised, then the CDC25 withheld the information and Health and Human Services26 stopped tracking hospital deaths related to COVID-19. But they haven’t been able to stop the data coming from Israel,27 the U.K,28 Germany29 and insurance companies.30
During Walensky’s appearance, she said she was “proud of our ability to get data out,”31 in reference to the vaccine. She indicated that they used a “pedal-to-the-metal”32 system to analyze and assimilate data that was published, on average, every 48 hours. Yet, her comments are in direct contradiction to a recent investigative report published in The New York Times33 that shows the CDC was not transparently publishing “large portions” of vaccine data.
In fact, Walensky has also publicly discredited the Vaccine Adverse Event Reporting System (VAERS), which is co-administered34 by the FDA and CDC. During her January 11, 2022, testimony before the Senate,35 Walensky clearly stated that any death after a vaccine could be reported to VAERS using the example of an individual who gets vaccinated, hit by a car and dies.
She implied without outright stating that this death would also be recorded in VAERS and logged as a death related to the vaccine. In other words, she skirted the issue without having to outright lie to the Senate.
Just days before she declared her pride in the CDC’s ability to publish accurate and informative data, The New York Times36 revealed that the FDA had been aware the COVID shots were only 12% effective in children under the age of 5. However, they withheld the information before a scheduled meeting on February 15, 2022, which was subsequently canceled. According to the Times :37
“Experts worried that the news would further dissuade hesitant parents from immunizing their children. Other studies have shown the vaccine was not powerfully protective against infection with the Omicron variant in adults, either.”
Will the Gaslighting Stop?
During the interview, Walensky alluded to people in the media who “reject evidence,” saying,38 “You know in the media now, there are a lot of people who are using their voice that may or may not be helpful for public health … then that decreases public health in general so our messaging I think we have to be clear about.”
The information that Walensky revealed during the interview makes you wonder about who’s making public health decisions and why. It’s difficult to imagine and scary to think that after two years, one of the largest and most powerful health care agencies in the U.S. is led by a director who is potentially uninformed, or worse, purposefully misleading the public.
In approximately 35 short minutes Walensky revealed much. While she characterizes those who reject her propaganda as “rejecting evidence” since scientific debate is no longer part of the scientific process according to the CDC, it’s interesting to note that she:
Admits learning about the Pfizer 95% efficacy — information which was then used to formulate CDC guidelines — from a CNN report,39 which was nothing more than a republished press release from Big Pharma.40
Believes the CDC is transparently publishing data in a “pedal-to-the-metal” scenario41 even though The New York Times uncovered evidence the CDC is withholding data.42
Believes that no one told her or the CDC that a virus may mutate and render the vaccine ineffective,43 yet a financial analyst was astute enough to ask the question.44
Isn’t sure if we will need another booster45 after Pfizer told the world last year that a fourth dose may be needed sooner than expected.46
Blames the “public” at large for believing “the science” is black and white despite her colleague, Dr. Anthony Fauci, who as director of the NIAID, has been the face of COVID-19 for the White House, claiming HE was the science.47 Walensky now admits: “I think the public heard that science is black and white, science is immediate … and the truth is, science is gray.”48
A great and detailed discussion with Chris Knobbe MD, on the science behind the modern vegetable / seed oils. He has devoted many years of his life to this science – and it shows!
What is the reality in terms of negative health impacts…resulting from these “factory fats”?
The book The Year the World Went Mad by SAGE-member Mark Woolhouse, has now been published as an audiobook and will be available in hard cover on April 12th. This is an important book, for here the author, a key player in the pandemic response in the UK, admits that more or less everything he and his colleagues suggested and the government did was wrong.
In this interview with Spiked-online, Woolhouse admits that focused protection, as suggested by the proponents of the Great Barrington Declaration, would have been the right approach, and that he and his associates knew it. He even claims they suggested it, but nobody listened. However, even if they did, why didn’t they speak up? The scientists who wrote and published the Great Barrington Declaration were denounced as pseudo-scientists – and by whom? Among others, by the very people who knew they were right all along.
In the author‘s own words:
“So how do you protect those people? First of all, since they have to have contact with certain people, you make it as Covid-safe as possible for them to have those interactions. Take all the precautions we know to take now, about wearing masks, ventilation and physical distancing. But that alone is not enough. You need to make sure that the contact themselves does not have an infection and is not going to pass it on to the vulnerable people they’re interacting with. We were talking about this in April and May 2020 to many people in government. But we never implemented it. It never took off. And yet it’s quite clear from our work that this would have had a very significant impact. It would not be enough by itself “You still need to suppress the virus to a degree, but you would not need lockdown.”
The lockdowns, travel bans, school closures and all the rest were useless and extremely harmful to society. But still the scientists in charge of the pandemic response, including Mark Woolhouse, promoted those methods and justified them. They derided those who criticised their methods, cancelled them, claimed they didn’t respect science. But it was the other way around. This, we must never forget.
This book is a good step. But I wonder if the author has apologised to those who were right all along, to Martin Kulldorff, Sunetra Gupta, Jay Bhattacharya and all the other honest, real scientists who had the courage and moral standard to tell the truth. If he hasn’t, I urge him to do so.
A study from Stanford University, published in Cell, has found that vaccine mRNA and spike protein persist in lymph nodes for up to two months following the second vaccine dose. This is in contrast to what happens following infection, where spike protein was found only rarely.
In contrast to disrupted germinal centres in lymph nodes during infection, mRNA vaccination stimulates robust germinal centres containing vaccine mRNA and spike antigen up to eight weeks postvaccination in some cases…
The observed extended presence of vaccine mRNA and spike protein in vaccinee lymph node germinal centres for up to two months after vaccination was in contrast to rare foci of viral spike protein in COVID-19 patient lymph nodes… COVID-19 patient lymph nodes showed lower quantities of spike antigen.
The researchers also found the concentration of spike protein in the blood following vaccination was similar to that during infection.
At least some portion of spike antigen generated after administration of BNT162b2 becomes distributed into the blood. We detected spike antigen in 96% of vaccinees in plasma collected one to two days after the prime injection, with antigen levels reaching as high as 174 pg/mL. The range of spike antigen concentrations in the blood of vaccinees at this early time point largely overlaps with the range of spike antigen concentrations reported in plasma in a study of acute infection, although a small number of infected individuals had higher concentrations in the ng/mL range. At later time points after vaccination, the concentrations of spike antigen in blood quickly decrease although spike is still detectable in plasma in 63% of vaccinees one week after the first dose.
The researchers found evidence of ‘original antigenic sin’ from the vaccines, where a person vaccinated and then infected with a variant develops a weaker antibody response to that variant than an unvaccinated person infected with the variant. They describe it as a “strong imprinting effect of prior vaccination”.
We find that prior vaccination with Wuhan-Hu-1-like antigens followed by infection with Alpha or Delta variants gives rise to plasma antibody responses with apparent Wuhan-Hu-1-specific imprinting manifesting as relatively decreased responses to the variant virus epitopes, compared with unvaccinated patients infected with those variant viruses…
The extent to which vaccine boosting or infection with different variants will effectively elicit antibody responses to new epitopes or rather increase responses to the epitopes of antigens encountered previously, as in the ‘original antigenic sin’ phenomenon described for influenza virus infection and vaccination, will be an important topic of ongoing study.
The researchers confirmed the fast decline of antibodies following vaccination, finding a 20-fold drop after nine months.
Our data demonstrate that vaccinee plasma and saliva spike and receptor-binding domain-specific IgG concentrations decrease from their peak values by approximately 20-fold by nine months after primary vaccination but quickly exceed prior peak concentrations in seven to eight days after boosting with a third vaccine dose.
The study also confirms that vaccination doesn’t generate IgA antibodies (found especially in the respiratory and digestive tracts and mounting a first defence against infection) or IgM antibodies (found especially in the blood and lymph fluid), but only IgG antibodies (found in the blood). This has been proposed as a reason that vaccination is so poor at preventing infection and transmission.
Surprisingly, perhaps, the researchers found that vaccination (whether mRNA, adenoviral or inactivated virus) stimulated a broader antibody (IgG) response than infection, leading them to predict that “antibodies derived from infection may provide somewhat decreased protection against virus variants compared with comparable concentrations of antibodies stimulated by vaccination”.
However, the post-infection IgG antibody response improved over several weeks.
Over time, infected patient plasma samples showed improvement in variant receptor-binding domain binding relative to Wuhan-Hu-1 receptor-binding domain, suggesting evolution of the antibody response through at least seven weeks post-onset of symptoms.
In addition, the apparent breadth-benefit of vaccination over infection disappeared when “whole spike antigens” were tested rather than just the receptor-binding domain targeted by the vaccine, suggesting the benefit may be an artefact of the study design not found in a real encounter with the virus.
Notably, the increased breadth of vaccinee IgG compared with COVID-19 patient IgG binding to viral variant antigens was greatest for receptor-binding domain, the main target of neutralising antibodies, and was decreased or not detected when whole spike antigens were tested.
Other limitations mentioned include not looking at “antibodies binding to the spike N-terminal domain” or other antibodies: “Our data do not reflect potentially functional antibodies binding to the spike N-terminal domain, or antibodies that may have other activities in vivo.”
The study also didn’t look at T cell responses, among other things:
Further mechanistic investigations into the differences in antibody breadth elicited by vaccination and infection are needed to define the roles of T cell help, antibody affinity maturation, germinal centre function, and innate immune responses to vaccine components, as well as the cellular and subcellular distribution of vaccine RNA and expressed antigen in lymphoid tissues.
The high concentration in the blood of spike protein following vaccination and its persistence along with vaccine mRNA in lymph nodes for months, in contrast to the situation post-infection where such persistence is rare, will fuel concerns about the safety of these Covid vaccines. It has been argued that the spike protein is itself pathogenic, not inert, and that the free spike proteins generated by the vaccines have greater capacity to bind to more types of cells than the virus particles themselves, and that this may be what lies behind many of the serious adverse events reported to regulatory bodies and identified in case reports. This warrants further investigation.
of all the insanity around covid that took what would literally have been a baddish flu year would have passed with little comment or historical import and turned it into a mass hallucination of apocalypse, defining “covid death” as a death not “from covid as a proximate cause” but rather as “death from any cause if you had had a positive PCR test for covid in the previous 28-30 days” carries a special pride of place.
many of us stood up and screamed about this right from the beginning.
it made zero sense. nothing else is counted this way (for a reason) and the confluence of doing so with the staggeringly unprecedented mass testing of healthy people with overclocked PCR tests run at a 40 or higher Ct that was so over-amplified that it lacked any clinical relevance whatsoever and was probably kicking out 70-90% rates of non-clinical positivity was madness.
once this disastrous definition was put in place, apocalypse was assured.
but “the experts” ran with it, defended it, and treated as unarguable truth that “800k+ americans died from covid.” but they didn’t. it was not even close.
and now that the panic they drove has ended and further deaths are “inconvenient” they are starting to walk it back over what they claim was a “coding error.”
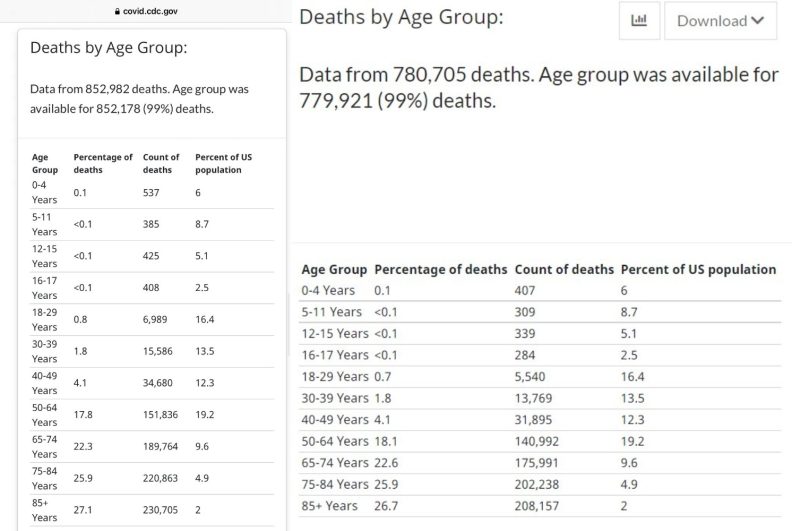
** Correction with updated numbers. The CDC may have removed closer to 70k deaths. Difficult to tell exacts as prior data has been removed. pic.twitter.com/zqoH1Wa1q4
the one on the left is from BEFORE the one on the right.
historical deaths dropped 72k.
huh.
it’s a start, but this is still a glaring, whopping overstatement.
now do “died from, not merely in proximity to a positive PCR sample for” covid and let’s see what happens.
my bet is that you drop the count by another ~70%.
here’s some fun math:
the average person probably has (to be conservative) 2 episodes a year in which they would, at a 40 Ct, test positive for the common cold. this does not mean you were sick, felt sick, were contagious, or any of that. it just means “you had enough viral genetic material in your mucus that someone using 1 trillion X amplification on it before looking for it could find it.”
let’s say these periods last 3 days and if you die in the 28 days following, this gets called a “common cold death” just as we did for covid.
this gives you something on the order of 62 days a year when getting hit by a car would still get counted as “cold death” just as in covid.
that’s ~17% of the year. (and these times will tend to overlap with peak winter seasons when more people die anyhow, but let’s ignore that.)
about 2.9 million people die in the US annually.
17% of 2.9 million is 493,000.
starting to see the problem?
adjust this for higher rates of positive viral tests for the old and infirm who are also more likely to die and this really blows out.
53% of US covid deaths were in the 6.9% of population over 75 years old and 75% were in over 65s’.
only about 8% of deaths were in the 39% of the population under 30.
the number of people who “tested positive for covid” was likely overstated by 70-90% when considering who had actual clinical covid and was sick/contagious.
and i fear we are in for more of the same because the CDC are completely, hopelessly politicized and compromised and their federal paymasters need to ensure that 2 things happen:
that non-pharmaceutical interventions look like they worked
that the vaccines they pushed so hard and got so wrong worked
many of the tactics and praxis of running and manipulating the scare to grab for cash, prominence and power have been the same and i expect this to remain so. it’s the same playbook.
so let me show you a trick play that has been all too common in climate and that i suspect we’re about to see run here:
when the data goes against you, change the data.
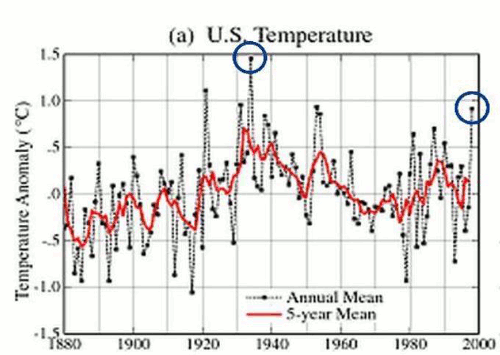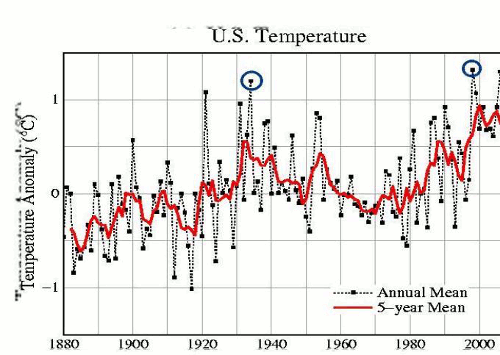
in climate, this has gone on for decades. they literally go back and change the past, cooling the warm periods of the 1930’s and adjusting current temperatures up. bingo, bango, instant warming trend and “unprecedented highs.”
this wonderful gif from steven goddard makes the process clear. and this was LONG before the east anglia “climategate” scandal and the 100 other times they have been caught adulterating data. it’s rife to the point that you pretty much cannot trust anything in the space. i found this so hard to believe i actually once went and checked the paper records myself to comp them to those in the databases. it’s true. they literally inverted the slope of the curve from the 1930’s to 2000 by fiddling the data.
and if you think they will not play this game on covid, i must sincerely ask you: “what movie have you been watching for the last 2 years?”
the fix is about to be in. “adjustments” are going to be applied selectively to make masks look like they worked and vaccines look like they reduced overall societal hospitalization and deaths from covid.
the US data is about to be turned into propaganda.
will this spread globally? who knows? it certainly did in climate. i don’t think this crowd is any nobler and the incentives are the same.
the same people who overstated this situation so aggressively are going to be the ones “fixing” the data to make sure it’s correct.
the same people who pushed and mandated draconian responses that have failed so spectacularly are going to be the ones “adjusting” the data that allows us to assess those outcomes.
we’re already caught them lying who knows how many times.
it is not a conspiracy theory to expect them to lie again.
it is a conspiracy theory to claim they’ll be honest this time.
i recommend grabbing all the data you can now and storing it. the presumption it will be available in unaltered form in the future may not be a good one.
honestly, tracking the changes to the dataset may be the only way to see if the CDC is playing it straight and they look to be disappearing past references already.
this is probably a worthwhile project for some of the datahawks.
With the reveal that the objectivity of the CDC (and US HHS) has become both politicized by the executive branch and compromised by the pharmaceutical industry, we have to come to terms with living in a world in which we can no longer take governmental public health pronouncements as gospel truth. Those of us who are thinking for ourselves (and our children) now need to make personal assessments and decisions about COVID-19 vaccines, and then booster vaccination, and then boosters again. As we all assess the advice of HHS, CDC, NIAID, Dr. Fauci, White House Advisor Dr. Francis Collins, the Surgeon General, the FDA, and of course Pfizer, let’s briefly revisit what many consider to be history’s most effective vaccine: the smallpox vaccine produced from variola.
Smallpox kills, and it has been eradicated from the world by use of a highly effective vaccine (with the exception of samples stored in various freezers). It was (is?) a far more serious threat than SARS-CoV-2, in terms of death and disease. In order to understand the science behind vaccines, one must understand the strategies behind vaccination campaigns, and the smallpox vaccines provide a great case study.
Vaccinia (cowpox) virus is closely related to smallpox (variola) virus, and Jenner (in 1796) is often credited with discovering that milkmaids (exposed to cowpox) were resistant to Smallpox disease, and then actively vaccinating against variola using vaccinia virus. The historic smallpox vaccine product principally credited with eradicating Smallpox was labeled as Dryvax, (Wyeth Laboratories, Inc.- formally discontinued in 1982) and was prepared from calf lymph using the New York City Board of Health (NYCBOH) strain of vaccinia. What that means is that the skin of calves were infected with the NYCBOH vaccinia, resulting in widespread infection and a sort of weeping exudate on the skin of the calves as the virus replicates. The calves were loaded into a mechanical holder and the exudate (with the virus) was scraped off (using something that resembled a sweat scraper used for horses) and “processed”, placed into glass vials, freeze dried, and then sealed with a standard stopper. The quality control on the “processing” was pretty crude, and I have personally seen legacy vials of Dryvax that included calf hair in the final vialed product. The vials were shipped out, and then reconstituted with a diluent (saline) and a “bifurcated needle” was dipped into the solution and then repeatedly poked into the skin (typically over the deltoid muscle – the shoulder) of the vaccine recipient, resulting in the typical round smallpox vaccine scar.
The art and science of vaccinology teaches that vaccines can vary in both safety and effectiveness. That this is a sliding scale for which disease severity, pathogen infectiousness (transmissibility, or Ro) and safety of the vaccine product all must be simultaneously optimized, resulting in a three dimensional plot (or “response surface”). The teaching is that if a vaccine is to be given to the general population, it has to have a low adverse event profile (be very safe), particularly if the disease is generally thought to either have a lower risk profile or infection is a rare event. In general, a more “hot” vaccine, in other words one that typically has a more serious adverse event profile, will also be better at preventing infection. In the case of a highly infectious, highly pathogenic virus, the risk profile of the vaccine may be greater – in order to achieve disease people contracting the disease and with the ultimate hope of disease eradication. The licensed Merck Ebola vaccine is an example of a relatively “hot” (reactogenic) vaccine which is only deployed in populations at high risk during an Ebola (highly infectious and pathogenic virus) outbreak. Benefits versus risks. If the pathogen is particularly nasty, then it becomes more acceptable to deploy a vaccine that causes some degree of disease. Makes sense?
There is another important element in the national vaccine program, which is the requirement to keep the vaccine production facilities up and running. These facilities are producing a biological product; they must be kept in production or the process for re-licensure is onerous, if not impossible. In the case of seasonal flu, one of the justifications for the yearly vaccine is to keep the manufacturing plants running and ready for business in case of a truly severe strain of flu or some other, unknown pathogen become a threat. If those facilities are moth-balled, they can’t be brought back on line quickly. Bet you did not know that. One major reason for pushing annual influenza vaccines is to maintain influenza vaccine manufacturing capacity. The industry term used is “warm base manufacturing”. Of course, this results in a very nice annual “cash cow” for the vaccine industry, one which gets annually milked for a tidy guaranteed profit. The term “rent seeking behavior” applies. The same is true of the various “biodefense” vaccines and products which are maintained in the “strategic national stockpile”. In the context of Smallpox, these include ACAM2000. These products have half lives, which is to say that even though they are (hopefully) not used, they still have to be replaced every few years. Again, nice predictable profit. The corporation “Emergent Biololutions” has become particularly adept at exploiting this “market opportunity”, and has managed to monopolize many of the biodefense-related vaccines and products which the US Government purchases for the Strategic National Stockpile, including ACAM2000.
So, there is more than one reason to vaccinate the entire population on a regular basis, and the government basically props up the entire vaccine industry with what are functionally major annual subsidies. Once a policy decision is made to acquire a vaccine product or establish a “standard of care” involving a vaccine, it is never re-evaluated. Any politician or government administrator that even considers rethinking whether a vaccine policy makes good sense is confronted by the specter of being blamed for any outbreak or cases of that disease that may arise – regardless of how (in)effective or risky that vaccine product may be. So, a combination of public policy realities and regulatory barriers to entry (very, very difficult and expensive to demonstrate improved effectiveness or safety for an improved vaccine when there is already an accepted vaccine on the market) make the vaccine business particularly lucrative and predictable for the large manufacturers that produce licensed vaccines.
What is Smallpox?
Before smallpox was eradicated, it was a serious infectious disease caused by the variola virus. It was contagious—meaning, it spread from one person to another. People who had smallpox had a fever and a distinctive, progressive skin rash.
Thanks to the success of vaccination, smallpox was eradicated, and no cases of naturally occurring smallpox have happened since 1977. The last natural outbreak of smallpox in the United States occurred in 1949.
First, note that the modern smallpox vaccine is not the same as the inoculation that has been throughout history.
The earliest smallpox prevention efforts date back to at least the 10th century in China, when physicians found that nasal inoculation of susceptible persons with material from smallpox lesions would sometimes provide immunity. The practice of inoculation appears to have arisen independently in several other regions prior to the 17th century, including Africa and India, but the practice did not gain popularity in western Europe until the 18th century. The wife of an English ambassador, Lady Montagu, observed inoculation in Turkey, and later had her own child successfully inoculated during a smallpox epidemic in England. In this procedure a lancet or needle was used to deliver a subcutaneous dose of smallpox material to a susceptible person. The procedure, also known as variolation, was controversial. It generated immunity in many cases, but it also killed some people and contributed to smallpox outbreaks.
In other words, smallpox is deadly. Historically, 30% of the people who contract the virus die. Many people were maimed and disabled permanently.
That said, the designers of this vaccine wanted it work to not only stop disease, but eradicate it completely. So, the smallpox vaccine was designed to be “hot.” The adverse event profile is much greater than than say, that of the influenza vaccine. It is designed to stop infection and as much as possible, transmission. With flu, the vaccine is only partially effective, because otherwise the cure would be worse than the disease for most healthy people.
The CDC knows this. But they have a mission to stop vaccine hesitancy. To do this, they promote vaccines and the vaccine enterprise as safe and effective. Full stop. No exceptions or questioning tolerated.
The smallpox vaccine is old enough that its risks are well known, and those data can be used to help us better understand how the CDC assesses vaccine safety. It is naive to think that all vaccines are “safe” – no matter what and no matter which vaccine. Unfortunately, officials at the CDC appear to have a belief system that all vaccines are “safe and effective”, which belief has become more a view of a world, a sort of object of faith (catechism) rather than objective science.
Frankly, positioning this as a statement of faith, a sort of ritual endorsed by annoitedhigh priests of public health, gives these officials benefit by removing any reason to doubt or question. The determination and public statements that most vaccines are “safe and effective” is a promotional tool. And this propaganda is not holding up to scrutiny. People are becoming more and more distrustful of the whole vaccine enterprise, and for good reason. It is time that public health be honest and transparent. Vaccines carry risk, some vaccines carry a lot more risk than others. In the case of the vaccines for children program, the cumulative risk of the entire expanding vaccine schedule on our children has never been rigorously assessed.
So, let’s get back to assessing the benefits and risks of the smallpox vaccine as a case study.
Let’s see what safe means to the CDC, from their own website:
Serious Side Effects of Smallpox Vaccine
· Heart problems
· Swelling of the brain or spinal cord
· Severe skin diseases
· Spreading the virus to other parts of the body or to another person
· Severe allergic reaction after vaccination
· Accidental infection of the eye (which may cause swelling of the cornea causing watery painful eyes and blurred vision, scarring of the cornea, and blindness)
The CDC then lists the types of people who might have reason to not take the smallpox vaccine…
The risks for serious smallpox vaccine side effects are greater for:
· People with any three of the following risk factors for heart disease: high blood pressure, high cholesterol, diabetes, high blood sugar, a family history of heart problems, or smoking
Let’s take a break here and look at just the first four items, the people described as being at greater risk of serious smallpox vaccine side effects:
People with diabetes – that’s 34 million Americans; people with high blood pressure (108 million Americans); people with high cholesterol (76 million Americans); people with heart disease (96 million Americans)
And there’s more:
· People with heart or blood vessel problems, including angina, previous heart attack, artery disease, congestive heart failure, stroke, or other cardiac problems
· People with skin problems, such as eczema [31 million Americans], atopic dermatitis, burns, impetigo, contact dermatitis, chickenpox [more than 95% of American adults have had chicken pox], shingles, psoriasis, or uncontrolled acne
· Infants less than 1 year of age
· Women who are pregnant or breastfeeding
· People who are taking steroid eye drops or ointment
So, while the CDC definitively states that “The smallpox vaccine is safe,” they then exclude huge segments of the population, leaving very few people for whom it might be safe. The list of people at greater risk also includes people with a “family history of heart problems.” Do any of us know even a single person who doesn’t fit that into that category?
However, other researchers place the risks as higher.
A 2021 study assessing vaccine risks in the military population who have received the more modern, smallpox vaccines reported the following.
897,227 SM who received ACAM2000 smallpox vaccine and 450,000 SM who received Dryvax smallpox vaccine were included in the surveillance population. The rate of adjudicated (proven) myopericarditis among ACAM2000 smallpox vaccine recipients was 20.06/100,000 and was significantly higher for males (21.8/100,000) than females (8.5/100,000) and for those < 40 years of age (21.1/100,000) than for those 40 years or older (6.3/100,000). Overall rates for any cardiovascular event (Group 1 plus Group 2) were 113.5/100,000 for ACAM2000 vaccine and 439.3/100,000 for Dryvax vaccine; rate ratio, 0.26 (95% CI, 0.24-0.28). The rates of subjects with one or more defined neurological events were 2.12/100,000 and 1.11/100,000 for ACAM2000 and Dryvax vaccines respectively; rate ratio, 1.91 (95% CI, 0.71-5.10).
The study above is based off of a passive data reporting system, not a clinical trial – so the actual numbers of adverse events are much higher than reported here.
So, cardiac events associated with the smallpox vaccines were at least 1 in every 885 people for the ACAM2000 vaccine and one in every 228 people for Dryvax vaccine in a healthy population. These risks seem highly significant to me, given that the risk of small pox is nil at this time (unless the military knows something that we don’t). Which is why the push to vaccinate all first responders against Smallpox during the Cheney administration (otherwise known as POTUS #43 George W. Bush) was halted – because of too many cases of myopericarditis and no circulating Smallpox. Sound familiar?
The term safe obviously means different things to different scientists and differing cohorts of people.
Note: The Mayo Clinic disagrees with the CDC on the risk and benefits of the smallpox vaccine:
Too high for patients of the Mayo Clinic – but not too high for Americans advised by the CDC. Although a note about the above quote, as 70% of people survive smallpox, it sure seems like they are “cured.” As for treatments, we no longer live in the middle ages – supportive care for infectious diseases work and are highly effective. Words matter – fearporn is not helpful.
To bring this topic home: Is avoiding COVID-19/Omicron worth taking the known and unknown risks of serious adverse events? In some age categories, it might be. In most age categories, it is not worth much risk. For young people, it is not worth any risk, and for children, the risks of the Covid vaccine far outweigh the risks of Covid.
The US Government had relentlessly promoted that “The vaccines are safe and effective,” the same words used for the modern smallpox vaccine. In both cases, safety is a matter of opinion and semantics – not science. Clearly, safety is relative, such as the precautions one might take when skydiving or riding a motorcycle (e.g., having a second parachute, wearing a helmet) – in order to reach the point that an activity is acceptably safe, all the while knowing it’s safer to just skip the activity.
If I proposed a person drink some potion, and said “This potion is safe, unless you are from a family with a history of heart problems,” few people would want the drink. If I added “Oh yeah, and the Mayo Clinic says the risk of side effects from this potion are too high to justify you drinking it, I’d have even fewer takers.
Mandates, which are rigid by definition, seem a bad match for assessments of personal safety, which are, by our nature, flexible and variable. Since the word safe and the idea of safety means different things to different people, such decisions are best left to those who would be most affected by, in this case, vaccination.
The smallpox vaccine shows us what the CDC means when they say something is “safe,” and it isn’t what most people using the word would mean. With risk must come choice. This is the bedrock foundation of modern bioethics and medicine.
After all that we have been through over the last two years, and the admission the the CDC has been withholding data from all of us for political reasons and to avoid “vaccine hesitancy” (which is another way of saying if you knew what the data really show you would not accept the product), who are you going to trust? Your own lying eyes and brain, or what the CDC, HHS, legacy media and the “factchecking” industry tell you?
Pfizer CEO Albert Bourla on Sunday told CBS “Face the Nation” a fourth dose of its COVID-19 vaccine will be necessary to maintain manageable levels of hospitalizations and mild infections.
The company plans to submit data on a fourth dose to the U.S. Food and Drug Administration (FDA) and is working on a vaccine that protects against all COVID variants for at least a year.
“I think we’re going to submit to FDA a significant package of data about the need for a fourth dose, and they need to make their own conclusions, of course, and then CDC also. […] to see that clearly there is a need in an environment of Omicron to boost the immune response.”
Bourla said a fourth dose is “necessary for right now” because protection after three doses of Pfizer’s vaccine is “not that good against infections” and “doesn’t last very long” when faced with a variant like Omicron.
Bourla said Pfizer is making a vaccine that covers Omicron and all other variants and is optimistic about the preliminary data he’s seen so far.
“There are so much trials that are going right now, and a lot of them we’ll start reading by the end of the month,” he added.
Bourla told CBS he foresees Americans needing to prepare themselves every fall for a COVID booster just like they do with the flu vaccine.
A third dose of Pfizer’s vaccine is currently available to anyone 12 and older who received a second dose at least five months prior to seeking the third dose.
Pfizer always planned for yearly boosters to boost profits
As The Defender reported Feb. 26, 2021, just two months after the FDA granted Emergency Use Authorization for the Pfizer-BioNTech vaccine, Bourla was already telling media outlets the company’s plan long-term was to have yearly vaccine boosters.
“Every year, you need to go to get your flu vaccine,” Bourla said during an interview with NBC News. “It’s going to be the same with COVID. In a year, you will have to go and get your annual shot for COVID to be protected.”
That will mean even more sales — and more profits — from the vaccine, reported WRCBtv, a CBS subsidiary.
During a February 2021 earnings call, Bourla told analysts, big banks and investors the company could make significant profits by charging higher prices and implementing routine booster doses for new variants of the virus.
During the Barclays’ Global Health Conference in March 2021, CFO Frank D’Amelio said Pfizer didn’t see this as a one-time event, but “as something that’s going to continue for the foreseeable future.”
At the time, Pfizer had already launched a study of a third vaccine dose to address variants, called for annual boosters and told investors to expect a revenue stream similar to that of flu vaccines.
The FDA said at the time it was willing to authorize booster shots based on small clinical trials, accepting data on how well vaccines prime the immune system rather than holding out for long-term safety and efficacy results on protection against COVID.
Pfizer said last month it expects 2022 sales of its COVID vaccine and antiviral pill, Paxlovid, to yield $54 billion, Reutersreported.
Pfizer said its vaccine is projected to bring in $32 billion in 2022 — a 13% decline from 2021 levels.
New UK data suggest vaccines aren’t effective
According to data published on Substack by Alex Berenson, a former New York Times reporter, hospitalizations and deaths in the UK “remain stubbornly high and overwhelmingly occur in vaccinated people.”
Last month, 90% of the 1,000 Britons who died each week of COVID were vaccinated. During the four weeks ending Feb. 27, 397 unvaccinated people in Britain died of COVID compared to 3,512 who were vaccinated.
“Using a broader definition, which may include more incidental deaths unrelated to COVID infections, the numbers are even worse, with 5,871 vaccinated people dying compared to 570 unvaccinated. (The United States does not publicly provide this data; it is not even clear American public health authorities collect it comprehensively.)
“The report also shows for the first time that adults under 50 are now just as likely to be hospitalized for COVID whether they are boosted or unvaccinated. The report does not provide a similar hospitalization estimate for people who were vaccinated but unboosted, but based on the raw numbers it does provide, those rates are the highest of all.
“Meanwhile, new Covid infections have nearly doubled in Britain in the last two weeks, and now top 60,000 a day.”
According to data, even boosters appear to “offer no protection against hospitalizations in younger people,” Berenson wrote.
Pfizer shot for kids under 5 could be authorized by May, company says
According to The New York Times, more than 22 million people in the U.S. under 18 are fully vaccinated with Pfizer’s vaccine, but the number of people getting vaccinated is tapering off. Yet, there is still a demand to vaccinate children under the age of 5.
Last month regulators pressed Pfizer and BioNTech to submit preliminary results from its three-dose pediatric trial. The FDA was poised to begin vaccinating the youngest age group with two doses even though it did not yet have final results on three doses.
While it’s still not clear why the effort collapsed, data from Pfizer showed overwhelmingly that two doses failed to adequately protect against symptomatic infection.
“The data that we saw made us realize that we needed to see data from a third dose, as in the ongoing trial, in order to make a determination that we could proceed with doing an authorization,” Dr. Peter Marks, director of the FDA’s Center for Biologics Evaluation and Research, told reporters on a call.
Marks said he hoped the decision would “reassure” people the FDA was “making sure that anything that we authorize has the safety and efficacy that people have come to expect from our regulatory review of medical products.”
Asked about the situation on Sunday, Bourla said FDA officials were “very keen” for the company to send the data over but Pfizer executives were “a little bit reluctant to submit on two doses because we felt that the three-dose [regimen] is what kids will need.”
Bourla said data on how a three-dose regimen works for children as young as 6 months will probably be available in April, with authorization granted in May, “if it works.”
Pfizer asked FDA to waive reporting of some safety data
While Pfizer doesn’t know if its vaccine will prove effective enough for the youngest age group, the company says its research shows the vaccine is safe.
According to the most recent data from the Vaccine Adverse Event Reporting System (VAERS) — the primary government-funded system for reporting adverse vaccine reactions in the U.S. — a total of 1,168,894 adverse events following COVID vaccines were reported between Dec. 14, 2020, and March 4, 2022.
Of the total adverse events reported, 667,973 are attributed to Pfizer’s vaccine. Of the 25,158 reported deaths following COVID vaccines, 16,475 are attributed to Pfizer’s vaccine.
According to Pfizer data obtained through a Freedom of Information Act request, the company applied for an FDA waiver to avoid recording certain safety data on the injections because the company claimed the VAERS system was adequate in revealing any safety issues with the injections.
In its waiver request, Pfizer stated VAERS is a “robust” system that is “designed to detect safety concerns with vaccines.”
Pfizer documents also revealed the company paid $2.87 million when it submitted its COVID vaccine application to the FDA, which has been reluctant to release the documents forming the basis of approval for Pfizer’s vaccine.
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
The subject of excess deaths during the pandemic, meaning deaths more than prior years, has received much attention. Now comes an analysis by medical establishment researchers, funded by Bill Gates and published in the premier establishment medical journal – The Lancet. An establishment publication commented positively on the article.
Before explaining what was intentionally omitted, here are the key findings.
The study covered the initial two years of the COVID pandemic, 2020 and 2021. It estimated excess mortality from the COVID-19 pandemic in 191 countries and territories, and 252 subnational units for selected countries. Global deaths directly attributed to COVID-19 reached 5.9 million, yet estimates put excess deaths during this period at a staggering 18.2 million. In other words, about 12 million people probably died from causes other than COVID infection. Something that the public health establishment should be held accountable for.
At the country level, the highest numbers of cumulative excess deaths due to the pandemic were estimated in India 4·07 million, the USA 1·13 million, Russia 1·07 million, Mexico 798 000, Brazil 792 000, Indonesia 736 000, and Pakistan 664 000. Note that the figure for the USA was about 300,000 greater than the CDC official number of deaths related to COVID infection through 2021.
Among countries, the excess mortality rate was highest in Russia 374·6 deaths per 100 000 and Mexico 325·1 per 100 000, and was similar in Brazil 186·9 per 100 000 and the USA 179·3 per 100 000. The highest estimated excess mortality rate from COVID infection was in Bolivia at 734.9 deaths per 100,000, followed by Bulgaria, Eswatini, North Macedonia, and Lesotho. Iceland had the lowest excess mortality rate 47.8 per 100,000. Australia, Singapore, New Zealand, and Taiwan had negative excess mortality rates, meaning fewer people died than in pre-pandemic years.
The study noted: “Our estimates of COVID-19 excess mortality suggest the mortality impact from the COVID-19 pandemic has been more devastating than the situation documented by official statistics. Official statistics on reported COVID-19 deaths provide only a partial picture of the true burden of mortality.” In other words, something other than the virus is to blame for millions of deaths.
An interesting finding was that studies from several countries including Sweden, Belgium and the Netherlands, suggest COVID-19 infection was the direct cause of most excess deaths, most likely because these nations maintained a more open society than other countries.
The study did recognize that there was likely underreporting in some places of direct deaths due to COVID infection.
The key goal in excess death studies is explaining deaths not resulting from COVID infection, and this usually means collateral or indirect deaths from how the pandemic was managed or, more correctly, mismanaged. So many people died from the many impacts of economic lockdowns, inability to get regular medical care, suicides and illegal drug use, for example.
Most interesting in this very detailed study was absolutely no consideration of deaths associated with COVID vaccines. Data from the US, UK and European Union indicate at least several hundred thousand deaths. Many more in other global locations could easily bring the total to several million, especially recognizing that millions of adverse health impacts from vaccines likely will keep explaining deaths for quite some time.
But the study had a very positive view of the benefits of COVID vaccines: “the development and deployment of SARS-COV-2 vaccines have considerably lowered mortality rates among people who contract the virus and among the general population. As a result, we expect trends in excess mortality due to COVID-19 to change over time as the coverage of vaccination increases among populations and as new variants emerge.” This, obviously, is an establishment view of the COVID vaccines despite a large medical literature with an opposite view.
Also interesting was the detailed analysis for states in India that totally ignored what is now widely known. Namely, that a number of states, especially Uttar Pradesh, used ivermectin to successfully wipe out the pandemic.
Death numbers in a number of other nations were also surely reduced by wide use of ivermectin. But this study had no interest in examining this.
US excess deaths
There are reasons to think that the excess death data for the US was an undercount. Various insurance industry officials have spoken about very high death rates not due to COVID infection in working age people. CDC data shows the Millennial generation suffered a “Vietnam War event,” with more than 61,000 excess deaths in that age group in the second half of 2021, according to an analysis by Edward Dowd a former Wall Street executive who made a career of crunching numbers to make big-dollar investment decisions. The Millennials, about ages 25 to 40, experienced an 84% increase in excess mortality in the fall, he said, describing it as the “worst-ever excess mortality, I think, in history.”
Along this same line is this: According to the CEO of OneAmerica, a national life insurance corporation headquartered in Indiana, deaths are up 40% in the third quarter of 2021. These deaths are primarily non-COVID deaths among workers aged 18 through 64. “We are seeing, right now, the highest death rates we have seen in the history of this business – not just at OneAmerica,” the company’s CEO Scott Davison said. The data is consistent across every player in that business. What the data is showing to us is that the deaths that are being reported as COVID deaths greatly understate the actual death losses among working-age people from the pandemic. It may not all be COVID on their death certificate, but deaths are up just huge, huge numbers.”
Conclusions
The massive number of all pandemic deaths shows how totally ineffective all actions by governments and public health groups, as well as the medical establishment, have been. It has all been one gigantic pandemic blunder.
Even if there was some undercounting of COVID infection deaths, there probably was at least 10 million pandemic deaths in the two years covered in this study that can and should be blamed on a number of ineffective and unnecessary public health actions. Where is the accountability for these non-infection deaths?
Considering the enormous number of COVID vaccine shots given globally there also should be no praise for them saving lives. In some countries like the US with high rates of vaccination there were still high COVID deaths. What must always be emphasized is that the use of ivermectin and various non-vaccine protocols could have prevented nearly all COVID infection deaths.
UNTIL now in our regular MHRA adverse effects reports we’ve focused quite heavily on myocarditis and acute cardiac disorders, not least for the dramatically increased risk of the vaccine for younger age groups, young men in particular. In terms of numbers recorded, however, these are eclipsed by what the MHRA classifies as nervous system disorders and about which we hear little.
Adverse events for this ‘category’ now stand at an astonishing 282,041, which is possibly less than 10 per cent of the real figure, 182,251 of them associated with the AstraZeneca vaccine. Nor does the overall figure include the further 12,769 ‘tremor’ events. Eugyppius, written about elsewhere in these pages today, has been recording his readers’ reports of their adverse vaccine reactions. He recently reported the response, commenting on the ‘many letters describing shingles and Bell’s Palsy following vaccination; and of more puzzling and potentially more serious neurological problems, from vertigo to muscular tremors to seizures’.
We hope to be able to report on a breakdown of the nervous disorder data in weeks to come.
It’s high time the NHS, the MHRA and individual doctors came clean about what they have seen. We need to know about ALL the ‘coincidences’.
Here is the latest Yellow Card summary, a little late from us this week. Once again, overall deaths are up and overall reactions are heading for the half million mark. If this is only 10 per of the real numbers (as the MHRA itself suggests) I leave you to do the maths.
MHRA Yellow Card reporting summary up to February 23, 2022 (published March 3)
Dr. Peter A. McCullough joins Del in studio for a dive into the science of vaccinating for Covid, vaccinating your children for Covid, and the risks and benefits. Is the risk worth the benefit? Are we doing more harm than good?
Before ‘The Science’ flipped in the spring of 2020, the consensus among Western epidemiologists was that community masking doesn’t affect the spread of respiratory pathogens like influenza. As Jonathan Van Tam said on April 3rd 2020, “there is no evidence” to support the general wearing of face masks.
Although masks might block large droplets in close-contact settings like hospitals, and thereby slightly lower the risk of transmission, they can’t block airborne particles – which simply go through/around them, and then remain aloft for minutes or even hours.
As a result, large indoor setting like supermarkets, transit stations or classrooms soon fill up with airborne particles – even if everyone’s wearing a mask.
A new Spanish study strongly supports the pre-Covid conventional wisdom that masks don’t stop transmission of respiratory pathogens. The study uses quite a powerful design, which makes its results all the more convincing.
Ermengol Coma and colleagues analysed data on a large cohort of Spanish children aged three to eleven, whom they followed for the first term of the school year from September to December of 2021. During this period, there was a mask mandate in place for children in primary school (aged six and up) but not for those in pre-school (aged three to five).
Hence the researchers compared outcomes between children aged five (who were not subject to the mandate) and those aged six (who were subject to the mandate).
This constitutes a relatively well-controlled comparison, given that the two groups differ by only one year in age. In other words, since six-year olds are only one year older than five-year olds, you wouldn’t expect the rate of transmission to differ much between them for reasons other than the mask mandate.
The researchers estimated the incidence of Covid, the secondary attack rate and the R number separately for the two groups. If mask mandates work, you’d expect all these quantities to be higher among the five-year olds. However, the researchers found no statistically significant differences between the two groups.
What’s more, they found a strong positive association between measures of transmission and age across all the age-groups in their sample. In other words, transmission was higher among older age-groups, despite the fact that these groups were subject to the mask mandate, whereas the younger ones weren’t.
Ermengol Coma and colleagues’ findings suggest that mask mandates do essentially nothing to reduce the spread of Covid. And given that masks plausibly impede both learning and social interaction, on top of being uncomfortable, there’s no good reason for children to wear them. Indeed, the fact that they were ever made to is a scandal.
The US Democratic Party has embraced a transgender agenda that amounts to “the normalization of sadism,” author A.J. Rice has said, warning that radical trans policies would return if the party is allowed to regain power.
Speaking to RT’s America First host Scotty Nell Hughes about his new book, ‘The Curse of the Bearded Lady: How the Trans Mafia Whacked American Sanity’, Rice argued that activists have gained significant influence in schools, medicine, and corporate America while people who questioned the agenda have faced pressure to stay silent.
The author described the “trans mafia” as the sprawling network of people and institutions that have helped the movement gain influence. He singled out parts of academia, wealthy backers, and corporations, and stated that providers of transition-related treatment also have a financial incentive to keep young people in their care indefinitely.
Rice argued that the consequences of these policies ultimately fall on children who are being drawn toward gender-affirming medical treatments and on girls who are expected to share locker rooms or compete in sports with biological males.
He noted that while voters rejected the Democrats’ approach to gender in 2024, the party, which has been “captured by madness,” has since only doubled down and is seeking what is effectively “the normalization of sadism.” … Full report
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.