Digital Surveillance — the Real Motive Behind Push to Vaccinate Kids
By Michael Nevradakis, Ph.D. | The Defender | December 15, 2021
COVID-19 may have caught much of the planet by surprise in late 2019 and early 2020, but much of the groundwork for the technology now widely used as a “response” to the pandemic was conceptualized and developed years prior.
In the U.S. and throughout the world, there has been a recent push to implement a variety of “vaccine passport” regimes, many of which rely on digital technologies such as mobile applications to carry a record of — so far, at least — one’s COVID-19 vaccination records.
These “tools” are presented by public officials and significant sections of the media in recent weeks and months as an inevitability of sorts, a technological progression as natural as breathing.
They are also presented as a “new” response to an unprecedented crisis.
These technological applications are touted as a means of keeping businesses open and ensuring “peace of mind” for members of the public who remain wary about entering public spaces.
But just how new is this “new” technology? And will the use of technology be limited to COVID vaccinations, or for purposes of “health?”
International ‘alliances’ backing the melding of ‘Big Tech’ and ‘Big Health’
It was the beginning of the preceding decade, January 2010, when Bill Gates, via the Bill & Melinda Gates Foundation, proclaimed “[w]e must make this the decade of vaccines,” adding that “innovation will make it possible to save more children than ever before.”
In launching this so-called “Decade of Vaccines,” the Gates Foundation pledged $10 billion in funding. But Gates wasn’t the only actor behind this initiative.
For instance, the “Decade of Vaccines” program used a model originating from the Johns Hopkins Bloomberg School of Public Health to project the potential impact of vaccines on childhood deaths throughout the decade to come.
And the announcement for the “Decade of Vaccines” initiative was made at that year’s annual meeting of the World Economic Forum (WEF).
These same actors — the Bill & Melinda Gates Foundation, the Johns Hopkins Bloomberg School of Public Health and the WEF — organized the now-notorious Event 201 pandemic simulation exercise, in October 2019, just before COVID entered our lives.
Moreover, in 2010, a “Global Vaccine Action Plan” was announced as part of this initiative. It was a collaboration with the World Health Organization (WHO), UNICEF and the National Institute of Allergy and Infectious Diseases (NIAID), with Dr. Anthony Fauci serving on the leadership council.
As the Gates Foundation stated at the time:
“The Global Vaccine Action Plan will enable greater coordination across all stakeholder groups — national governments, multilateral organizations, civil society, the private sector and philanthropic organizations — and will identify critical policy, resource and other gaps that must be addressed to realize the life-saving potential of vaccines.”
The steering committee for the “Global Vaccine Action Plan” included a member from the GAVI Alliance. Notably, the initial announcement for the “Decade of Vaccines” was made in the presence of Julian Lob-Levyt, then-CEO of the GAVI Alliance.
What, or who, is the GAVI Alliance? Also known as the “Vaccine Alliance,” it proclaims a mission to “save lives and protect people’s health,” and states it “helps vaccinate almost half the world’s children against deadly and debilitating infectious diseases.”
GAVI goes on to describe its core partnership with various international organizations, including names that are by now familiar: the WHO, UNICEF, the Bill & Melinda Gates Foundation and the World Bank. (Far from helping the world’s poor, the World Bank has been described by a former insider, John Perkins, as an organization that uses “economic hit men” to subjugate financially crippled countries).
In 2018, GAVI, through its INFUSE (innovation for update, scale and equity in immunization) Initiative, put forth the following “food for thought”:
“Imagine a future in which all children have access to life-saving vaccines no matter where they live — a future in which parents and health workers ensure their timely vaccination, a future in which they have their own digitally stored health record that cannot be lost or stolen, a future in which, regardless of gender, economic or social standing, this record allows each child (and parents) to have access to a bank account, go to school, access services and ultimately build a prosperous life.
“This future is possible today. With the latest advances in digital technologies that enable more effective ways to register, identify births and issue proof of identity and authentication for access to services — we are on the brink of building a healthier and more prosperous future for the world’s most vulnerable children.”
This would be accomplished, according to GAVI, through the INFUSE initiative, specifically by “calling for innovations that leverage new technologies to modernize the process of identifying and registering the children who are most in need of life-saving vaccines.”
As described by investigative reporter Leo Hohmann:
“Don’t be confused by the bit about ‘building a healthier and more prosperous future.’ That’s just window dressing. This is all about data collection and has nothing to do with health.
“The real purpose behind the historic, unprecedented push to vaccinate the very young, even against diseases like COVID that do not pose a threat to them, is to fold the current generation of children into the blossoming global digital identity system.”
GAVI itself confirmed the above statement, as it has described potential uses of these “new technologies” as going beyond the issuance of a “digital child health card” toward encompassing “access to other services,” including the broadly defined “financial services.”
Limitations on “access” to such “other services” are already apparent in jurisdictions where COVID passports restrict access to businesses, banks and other private spaces for the non-vaccinated
The GAVI Alliance also closely collaborates with the ID2020 Alliance, founded in 2016, which claims to advocate in favor of “ethical, privacy-protecting approaches to digital ID,” adding that “doing digital ID right means protecting civil liberties.
Unsurprisingly, there is no clarification provided regarding the potential loss of civil liberties for individuals who choose, for any reason, not to be vaccinated and who are therefore excluded from large swaths of society in areas where COVID passports have been implemented and enforced.
Such rhetoric on the part of ID2020 is reminiscent of the public statements put forth by the European Union (EU) as it was preparing to launch its so-called “Green Pass” earlier this year.
EU officials, such as European Commission President Ursula von der Leyen — who recently called for a “discussion” on mandatory vaccinations in the EU — went to great lengths to stress how individuals’ privacy would be protected.
In a manner which some may consider tone-deaf, they further emphasized that such a digital pass would enable people to “move safely” for “work or tourism,” as if such free movement is a new concept that only a digital pass could make possible.
Again, restrictions on the unvaccinated, including those involving “work or tourism,” were entirely absent from the public rhetoric surrounding this new measure.
Highlighting the possibilities that the GAVI-ID2020 collaboration could bring, the INFUSE call for innovation states:
“According to the ID2020 Alliance — a public-private partnership that includes Gavi — the use of digital health cards for children could directly improve coverage rates by ensuring a verifiable, accurate record and by prompting parents to bring their children in for a subsequent dose.
“From the parents’ perspective, digital records can make it convenient to track a child’s vaccines and eliminate unnecessary paperwork.
“And as children grow, their digital health card can be used to access secondary services, such as primary school, or ease the process of obtaining alternative credentials. Effectively, the digital health card could, depending on country needs and readiness, potentially become the first step in establishing a legal, broadly recognized identity.”
All of these proposals and initiatives appear, in turn, to be closely aligned with the United Nations’ Sustainable Development Goals, and in particular, Goal 16.9, which calls for the provision of a digital legal identity for all, including newborns, by 2030.
To this end, the UN established the UN Legal Identity Agenda Task Force in 2018. In May 2021, this task force, alongside the United Nations Development Programme and a variety of private sector actors, organized the “Future of Technology and Institutional Governance in Identity Management” roundtable sessions.
The final report from these sessions indicates, among other things, a desire from the stakeholders for the expansion of public-private partnerships for the further development and implementation of digital ID regimes worldwide, including in the Global South.
One of the stakeholders present, the not-for-profit Secure Identity Alliance, touts its support for “the provision of legal, trusted identity for all and driving the development of inclusive digital services necessary for sustainable, worldwide economic growth and prosperity.”
A paper published in July by the Security Identity Alliance discusses “making health certificates a workable reality.”
One of the five principles the paper puts forth for such health passports is that they are “futureproofed,” by offering “multi-purpose functionality” in order to “ensure ongoing value beyond today’s current crisis.”
The Secure Identity Alliance counts among its observers governmental authorities from countries such as Germany, The Netherlands, Estonia, Slovenia, the United Arab Emirates, Nigeria and Guinea.
Moreover, one of its founding members and current board members is the Thales Group, a private company involved in aerospace, defense and security — in short, a defense contractor.
On its website, the Thales Group proudly promotes its “smart health card” and Digital ID Wallet technology. Amidst utopian language claiming “we’re ready for change” and “putting citizens in control,” the Digital ID Wallet promises the public the ability to “access the rights and services to which we are entitled.”
Indeed, the documents that would be available via this Digital ID Wallet go beyond “health credentials” and include national identification cards, driver’s licenses and any number of other items of official documentation.
Numerous countries worldwide, including the U.S., currently find themselves in varying stages of implementing exactly this sort of “digital wallet.”
Taking ‘health passports’ a step (or more) further: digital wallet regimes take shape
The U.S. House of Representatives on Nov. 30 passed H.R. 550, the Immunization Infrastructure Modernization Act of 2021.
If passed by Congress, this law would provide $400 million in funding to expand vaccine-tracking systems at the state and local level, enabling state health officials to monitor the vaccination status of American citizens and to provide this information to the federal government.
Vaccine passports and no-fly lists for the unvaccinated — a concept for which Fauci expressed his support — could be created under the law.
The bill, sponsored by Rep. Annie Kuster (NH-02), passed the U.S. House of Representatives with 294 votes, including all Democrats and 80 Republicans. It is now before the Senate, where it is being reviewed by the Committee on Health, Education, Labor, and Pensions.
Since being passed by the House, the bill has garnered a fair amount of attention — other recent digital identification developments in the U.S., however, seem to have remained relatively under the radar.
In September, for instance, Apple announced a partnership with eight states — Arizona, Connecticut, Georgia, Iowa, Kentucky, Maryland, Oklahoma and Utah — to make those respective states’ driver’s licenses available in digital form via the Apple Wallet platform.
Meanwhile, several states, including New York (via its “Excelsior Pass”) and Connecticut introduced their own digital COVID vaccination certificate.
Similar to how the EU has promoted vaccine passports, these state-level initiatives in the U.S. are touted as a means of “safely” reopening the economy and encouraging travel and movement.
Indeed, New York went so far as to make a “blueprint” of its vaccine pass platform available, “as a guide to assist other states, territories, and entities in the expansion of compatible COVID-19 vaccine credential systems to advance economic development efforts nationwide.”
Looking at the EU, one of the bloc’s priorities as part of its 2019-2024 five-year plan is to create a “digital identity for all Europeans.” Namely, each EU citizen and resident would have access to a “personal digital wallet” under this initiative.
This “personal digital wallet” could include documentation such as national ID cards, birth certificates, medical certificates and driver’s licenses.
The EU subsequently presented its plans for the “European Digital Decade,” where under the EU’s “Digital Compass,” 100% of key public services will be available digitally, with a target of 80% uptake of digital identification documents.
Already, several EU member states are getting into the act.
Germany, which had electronic national ID cards (via biometric chips) since 2010, introduced digital versions of these ID cards this past fall, via the AusweisApp2. The same app makes German driver’s licenses available digitally.
Germany and Spain also recently signed an agreement to launch a cross-border program for digital identification, which would entail mutual recognition of each other’s official digital documents
France also recently announced its intention to integrate its national identification card with smartphones.
Greece received praise from the global press when it introduced particularly draconian digital tools during its two COVID lockdowns, such as a government SMS platform to which residents would have to send a text message in order to circulate in public for a limited set of “reasons.”
More recently, Greece announced the forthcoming creation of a digital wallet that will contain documents such as one’s national ID card, driver’s license and health documentation.
Estonia, viewed as a world leader in introducing digital e-governance and which has had digital identification cards in place since 2002, is preparing its own digital wallet system while expressing support for the EU’s “Digital Compass.”
Outside of Europe, several other countries also have expanded their digital identification regimes in various ways.
In Australia, for instance, states such as New South Wales, South Australia and Queensland introduced or trialed digital driver’s licenses.
It is in India, though, where such digital documents appear to have generated the greatest degree of controversy thus far.
The Ayushman Bharat Digital Mission was announced in 2020 and launched as a pilot program in six regions of India in 2021. It is an app that provides a unique digital health ID to each citizen and is linked to their personal health records.
Its establishment comes on the footsteps of the development of Aadhaar, India’s national digital identification card system.
Aadhaar generated controversy over the government’s plans to link it to the national voter database, while it has also been the target of hackers.
Questions arise as more digital platforms rolled out for ‘official purposes’
The rollout of digital platforms gives rise to questions about the safety of individuals’ data on these digital platforms, despite government reassurances to the contrary regarding privacy.
Moreover, it remains unclear how long “COVID passports,” whether in digital or paper form, will remain enforced, or if governments plan to make such a regime permanent.
A recent article in The Atlantic, “Why Aren’t We Even Talking About Easing COVID Restrictions?” questioned why vaccine passport mandates in the U.S. have no sunset date.
Indeed, if the proclamation of the Secure Identity Alliance regarding the need to “futureproof” such digital documents is any indication, it may be the case that governments have no intention to scrap vaccine passports.
Even if such specific uses of digital “passports” eventually go away, the range of ways in which digital wallets can potentially be utilized is staggering, including, for instance, via the tracking of “personal carbon allowances,” as previously reported by The Defender.
Michael Nevradakis, Ph.D., is an independent journalist and researcher based in Athens, Greece.
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Russia’s QR code regime is collapsing
It was never about public health and Russians know it

Resistance to QR codes in Russia has taken on many forms, including boycotts and beating up ID inspectors. It is what it is.
By Edward Slavsquat | December 15, 2021
The Russian government is still planning to push through a deeply unpopular nationwide QR code law—but making such legislation a reality could be a tall order.
In some regions where QR codes are already in place, authorities have hastily abandoned enforcement efforts.
Fed-up Russians are boycotting, bypassing, and beating people up.
Non-existent enforcement in Kazan
On November 22, Kazan, the capital of Tatarstan, became the first city in Russia to require QR codes for public transportation. The new rule led to absolute chaos: buses were being delayed by twenty minutes or more as conductors struggled to check QR codes—and there were numerous reports of angry passengers starting brawls.
It appears that Kazan basically… gave up. QR codes are still required to use public transport, but the rule is not enforced in any meaningful way.
In early December, Ilya Zotov, a member of the Public Chamber of the Russian Federation, Chairman of the All-Russian Association of Passengers, decided to investigate how Kazan’s QR codes regime works in practice.
His findings were quite extraordinary:
“Briefly: I traveled on 4 different bus routes, 1 trolleybus, and also in the metro. What did I see in fact?
– on 4 bus routes the QR code was never asked;
– in the trolleybus they asked if I had a code, I said yes (which is true), but they did not ask me to show it;
“In the metro, QR codes are checked at the entrance to the station, but you can show any code (of a relative or friend), there is no data reconciliation,” Zotov, wrote in his Telegram channel.
He also said that 70% of passengers were not complying with mask rules. The takeaway? Maybe this is not such a good policy:
“I come to the conclusion that this whole imitation is not needed… It is better for the authorities of Tatarstan to honestly admit this and cancel QR codes in transport,” Zotov wrote.
Enforcement reportedly remains quite lax. At the Doctors for Truth conference in Moscow on Sunday, your correspondent spoke with an activist who said that she recently took several bus rides in Kazan without having to present a QR code.
The most dangerous job in Russia?
One of the problems with enforcing QR codes in Russia is that you can get stabbed for doing it. On paper it sounds like a major growth industry, but is it really worth the lousy pay and the constant beatings?
For example, at the end of November a mall cop in Kazan was wounded in the arm with a knife after he asked a man for his QR code.
In some parts of Russia, violent opposition to QR codes appears to have played a key role in dropping the regime altogether.
Reason: constant beatings.
REGNUM, citing local media, reported that a city in Altai gave up on enforcing QR codes in their shopping centers—partly due to the “very aggressive attitude of citizens towards the procedure”:
According to one of the managers of the shopping center, two inspectors were beaten up in the first ten days of the introduction of the vaccination inspection system in the Altai Territory.
We’ve read similar reports from across Russia.
St. Petersburg business revolt
St. Petersburg restauranteur Alexander Konovalov owns dozens of businesses. He announced last month that he would not be complying with the city’s QR code rules:
“The introduction of QR codes, the assignment of numbers, as in a concentration camp, is fascism. I have more than 200 establishments (among them bars, hookah bars, bakeries, beauty salons), in all my establishments they will not ask for a QR code. From time to time they come to us with checks, but we simply do not pay attention to it. Let them come.”
Notably, he claimed he has yet to be fined for disobeying the “public health” measure.
Meanwhile, dozens of St. Petersburg residents have filed a class action lawsuit against the city government demanding the removal of the QR code regime.
United Russia continues to push for nationwide QR codes
Curiously, Putin’s United Russia continues to ignore overwhelming opposition to legislation that would make QR codes mandatory nationwide for many aspects of ordinary life:
The United Russia party supported the bill on QR codes in public places, subject to its deep revision. This was announced on Monday, December 13, by the head of the faction in the State Duma, Vladimir Vasiliev.
Earlier this week it was announced that the State Duma had withdrawn parts of this bill that called for QR codes for trains and air travel—but it turns out this was slightly inaccurate:
“As for the introduction of QR codes in transport, this bill has not been removed from the agenda, but sent for revision. It is being studied and worked out in detail. As a doctor and as an MP, I believe it is very important to maintain restrictive anti-epidemic measures in order to curb the growth of morbidity. Tatyana Alekseevna Golikova came to the State Duma, she answered questions in great detail, with all the clarifications. In public places, QR codes will be valid. The only exception will be grocery stores and pharmacies. And all other publicly accessible places will be admitted only by QR codes. These are restaurants, theaters, museums, shopping centers—all of this will be done using QR codes,” said [United Russia member] Tamara Frolova, member of the State Duma Health Protection Commission.
What is the public health benefit of these codes? Can anyone explain this? And why does United Russia continue to pursue brazen political suicide? It’s very weird.
As we’ve mentioned before, the Russian government will probably need to simulate a fake alien invasion in order to spook people into accepting a digital ausweis. In the meantime, Russians will continue to use QR codes taken from washing machines to gain access to their local shopping centers.
It’s Russia.
Between the Forceps and the Stone
Vaccinating children with the Pfizer mRNA vaccine to protect the aged?

By Robert W Malone MD, MS | December 14, 2021
Before you vaccinate your child, which is irreversible and potentially permanently damaging, find out why 16,000 physicians and medical scientists around the world signed a declaration publicly declaring that healthy children should NOT be vaccinated for COVID-19. On behalf of these MDs and PhDs, I have published a clear statement outlining the scientific facts behind this decision.
My name is Robert Malone, and I am speaking to you as a parent, grandparent, physician and scientist. I don’t usually read from a prepared speech, but this is so important that I wanted to make sure that I get every single word and scientific fact correct.
I stand by this statement with a career dedicated to vaccine research and development. I’m vaccinated for COVID and I’m generally pro-vaccination. I have devoted my entire career to developing safe and effective ways to prevent and treat infectious diseases.
After this, I will be posting the text of this statement so you can share it with your friends and family.
Before you inject your child – a decision that is irreversible – I wanted to let you know the scientific facts about this genetic vaccine, which is based on the mRNA vaccine technology I created:
There are three issues parents need to understand:
The first is that a viral gene will be injected into your children’s cells. This gene forces your child’s body to make toxic spike proteins. These proteins often cause permanent damage in children’s critical organs, including
- Their brain and nervous system
- Their heart and blood vessels, including blood clots
- Their reproductive system
- And this vaccine can trigger fundamental changes to their immune system
The most alarming point about this is that once these damages have occurred, they are irreparable
- You can’t fix the lesions within their brain
- You can’t repair heart tissue scarring
- You can’t repair a genetically reset immune system, and
- This vaccine can cause reproductive damage that could affect future generations of your family
The second thing you need to know about is the fact that this novel technology has not been adequately tested.
- We need at least 5 years of testing/research before we can really understand the risks
- Harms and risks from new medicines often become revealed many years later
Ask yourself if you want your own child to be part of the most radical medical experiment in human history
One final point: the reason they’re giving you to vaccinate your child is a lie.
- Your children represent no danger to their parents or grandparents
- It’s actually the opposite. Their immunity, after getting COVID, is critical to save your family if not the world from this disease
In summary: there is no benefit for your children or your family to be vaccinating your children against the small risks of the virus, given the known health risks of the vaccine that as a parent, you and your children may have to live with for the rest of their lives.
The risk/benefit analysis isn’t even close.
As a parent and grandparent, my recommendation to you is to resist and fight to protect your children.
RW Malone, MD
Chief Medical and Regulatory Officer, the Unity Project
President, International Alliance of Physicians and Medical Scientists
More on the twisted logic of vaccinating the children to protect the elderly
“Never in human history have old people required young people to take risks, make sacrifices and die to preserve older people. We have a fiduciary duty to our children. Old people sacrifice themselves for children in a moral society, in a robust society, in a society that we are proud of. We do not tell children to take risks to preserve old people. We need to stand up and take a moral choice and an ethical choice for our children.”
Robert F. Kennedy, Jr. Testimony before the Louisiana State Legislature, 06 December 2021.
I first became conscious of the twisted logic of vaccinating the children to protect the elderly when I saw the CNN “indirect marketing” campaign to vaccinate children with an unlicensed experimental Pfizer product. After the shock of the realization that what was going on was that Pfizer used CNN as a surrogate to advertise directly to children, thereby driving consumer demand and cause the USG/CDC to purchase additional Pfizer unlicensed EUA SARS-CoV-2 vaccines, I took time to review the clip more carefully and think through what was storyboarded and scripted. I am no longer confident that children were the target market – I think it was the elderly who watch TV and soak up the constant barrage of CNN fearporn regarding SARS-CoV-2.
The CNN/Sesame Street piece is actually promoting the logic that an elderly grandmother should schedule and transport her grandchild to receive an unlicensed experimental medical product, and that it is the grandmother who is advocating that the child should accept this procedure. And this is being promoted by a licensed Physician who works for CNN, Dr. Sanjay Gupta. Having posted this observation to Twitter, of course I was immediately ridiculed and defamed by various shadowy media outlets, who seem to think that personal ad hominum attacks are a reasonable substitute for examining the logic of my statements.
“The use of trusted and beloved figures in this propaganda assault to induce children into submitting as guinea pigs to injections with an experimental high-risk zero-liability medical product with no proven benefits for kids is unconscionable and revolting. Big Pharma has turned Big Bird into a child predator.”
Just stop for a moment. Think about what is happening here. If you make a decision to administer this product to your child, or you allow the State to insert itself into the family and force you to vaccinate your child, there is a chance that your child will be seriously damaged by the vaccine. The probability of this happening is much greater than the probability that your child will be seriously damaged by SARS-CoV-2. It is likely that this is particularly true in the case of the Omicron variant. Despite the fearporn that you may be subjected to by CNN and other legacy media. This is a scientific fact.
“I think it’s time we stop. Children, what’s that sound? Everybody look – what’s going down?.”
Frankly, I am really tired of the coordinated propaganda, censorship, and social engineering being promoted by Pfizer, “public health officials”, legacy media and governments from around the world. Perhaps you are also? If so, you are in the 20-30% of the global population who are increasingly aware that they have been misled. Well, actually (calling it what it is), actively lied to and psychologically manipulated.
The prepared statement at the start of this post came about when I went down to Puerto Rico last weekend to meet with colleagues that are supporting the 16,000+ strong International Alliance of Physicians and Medical Scientists, and we prepared the blunt, concise statement of fact to alert parents of what they are signing up for if they agree to go along with the narrative that is being so actively sold to us, and have their children vaccinated.
This was then video recorded as a statement which is being distributed worldwide via many decentralized channels so that the censors cannot remove it. And then we held a live-streamed question and answer event focused on vaccination of children with the Pfizer SARS-CoV-2 vaccine. The invitation-only event was attended by over 50 local physicians, medical providers, and parents.
The text of the statement at the start of this post is indeed blunt and may seem shocking to some. But I think that the time for carefully parsing the truth has long since passed. Children are being harmed in the mindless rush to achieve universal vaccination.
Few if any have come out with such a brief, plain-speaking statement about the reality of what parents and their children are being asked or forced to do by government bureaucrats. But so many have been subjected to so much propaganda, such intentional hypnotism to accept the logic that it is a good idea to vaccinate our children with an experimental product that is associated with unacceptable and irreparable toxicities in order to protect the small fraction of the population at high risk of death and hospitalization.
According to the latest CDC data, more than 60% of the total US population has been vaccinated, and about 45% of the entire population has already been infected by the virus, recovered, and developed natural immunity. The elderly are heavily vaccinated. The vaccines do not prevent you from becoming infected, replicating high levels of virus, and spreading infection to others. I will say it again- the elderly are highly vaccinated.
The problem is that the vaccines are not doing what they are supposed to do- prevent infection and spread of the virus. This is even more the case with the Omicron variant. So what to do? Start jabbing children who, unless they have other major problems, shrug off COVID-19 disease like they do most other RNA respiratory viruses? Or start allowing physicians to treat COVID-19 patients in the outpatient setting to prevent them from ever getting to the hospital setting where (almost exclusively in USA alone) they are immunosuppressed with high levels of Dexamethasone, placed into a coma-like state and hooked up to a ventilator, and treated with Remdesivir (which is clearly toxic and mimics many of the toxicities of the virus)?
This is madness. And it reflects a profound arrogance on the part of the Pharma-Govie-World Health elite. They assert that they understand immunology, virology, and evolutionary biology so well that they can freely tinker with the lives of our children using an experimental technology and rushed vaccine product which is neither safe nor effective based on standards and bioethical consensus that have been developed and applied over decades. They believe that they can inject novel unproven technology and improve the highly evolved human immune system that has developed over millennia to resist respiratory RNA virus pressure. Arrogance is the kindest term I can think of.
“I know no one’s going to show me everything. We all come and go unknown. Each so deep and superficial. Between the forceps and the stone. Well, I looked at the granite markers, those tributes to finality, to eternity. And then I looked at myself here. Chicken scratching for my immortality.”
None of us are immortal. Despite the objectives of the transhumanism agenda. Death cannot be avoided. We pass through this world, and hopefully leave it a bit better when we are gone. Our children are the only true legacy, the only real form of immortality. Please protect them, and do not ask them to make sacrifices with their health on your behalf. You know this is wrong. So do the right thing. And take this seriously. Think long and hard before taking an action that can never be undone.
Danish Study Confirms That Natural Immunity Protects Better Against Infection Than the Vaccines
By Noah Carl | The Daily Sceptic | December 15, 2021
Last week, I wrote about a second major study finding that natural immunity protects better against infection than the Pfizer vaccine. Both this study and the earlier one were from Israel, and while there’s every reason to believe the results generalise to other populations, it’s always good to have data from multiple countries.
We now have those data in the form of a study published by the Statens Serum Institut in Denmark. I can’t say the report itself is worth reading in full, since it’s written in Danish. But I’ve posted the key figure below. It shows protection against infection for three different groups – adjusting for age, sex, comorbidities, and time of year.
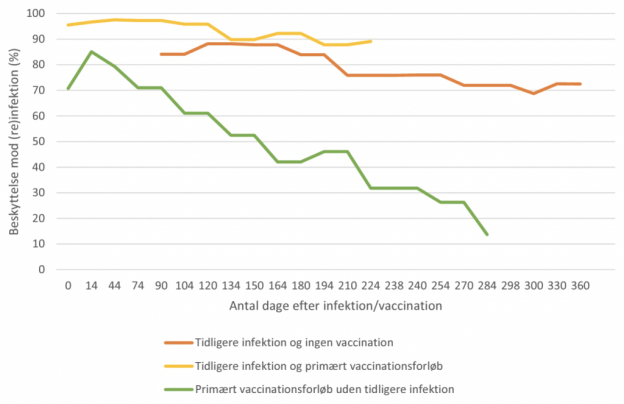
The orange line corresponds to people who’ve been previously infected but not vaccinated; the yellow line to those who’ve been previously infected and vaccinated; and the green line to those who’ve been vaccinated but not previously infected.
The y-axis gives the percentage reduction in the number of infections, compared to those who haven’t been vaccinated or previously infected. For example, a value of 90% means there would be only 10 infections for every 100 in the comparison group. The x-axis gives the number of days since the relevant event.
As you can see, vaccine-induced immunity wanes rapidly, beginning a few weeks after vaccination. And at the five month mark, protection is well below 50%. Natural immunity, by contrast, is robust: a full year after infection, protection is still above 70%.
Consistent with what the two Israeli studies found, hybrid immunity – conferred by the combination of vaccination and previous infection – is slightly better than natural immunity. However, the difference is small compared to that between natural and vaccine-induced immunity.
Evidence for the superiority of natural immunity is now robust. So while those who’ve already had Covid should be perfectly free to get vaccinated, there’s no obvious need for them to do so. The tricky part may be getting this message through to politicians.
32,649 Deaths 3,003,296 Injuries Following COVID Shots in European Database of Adverse Reactions
Young, Previously Healthy People Continue to Die

By Brian Shilhavy | Health Impact News | December 15, 2021
The European Union database of suspected drug reaction reports is EudraVigilance, and they are now reporting 32,649 fatalities, and 3,003,296 injuries, following COVID-19 injections.
A Health Impact News subscriber from Europe reminded us that this database maintained at EudraVigilance is only for countries in Europe who are part of the European Union (EU), which comprises 27 countries.
The total number of countries in Europe is much higher, almost twice as many, numbering around 50. (There are some differences of opinion as to which countries are technically part of Europe.)
So as high as these numbers are, they do NOT reflect all of Europe. The actual number in Europe who are reported dead or injured following COVID-19 shots would be much higher than what we are reporting here.
The EudraVigilance database reports that through December 4, 2021 there are 32,649 deaths and 3,003,296 injuries reported following injections of four experimental COVID-19 shots:
- COVID-19 MRNA VACCINE MODERNA (CX-024414)
- COVID-19 MRNA VACCINE PFIZER-BIONTECH
- COVID-19 VACCINE ASTRAZENECA (CHADOX1 NCOV-19)
- COVID-19 VACCINE JANSSEN (AD26.COV2.S)
From the total of injuries recorded, almost half of them (1,409,643) are serious injuries.
“Seriousness provides information on the suspected undesirable effect; it can be classified as ‘serious’ if it corresponds to a medical occurrence that results in death, is life-threatening, requires inpatient hospitalisation, results in another medically important condition, or prolongation of existing hospitalisation, results in persistent or significant disability or incapacity, or is a congenital anomaly/birth defect.”
A Health Impact News subscriber in Europe ran the reports for each of the four COVID-19 shots we are including here. It is a lot of work to tabulate each reaction with injuries and fatalities, since there is no place on the EudraVigilance system we have found that tabulates all the results.
Since we have started publishing this, others from Europe have also calculated the numbers and confirmed the totals.*
Here is the summary data through December 4, 2021.
Total reactions for the mRNA vaccineTozinameran (code BNT162b2,Comirnaty) from BioNTech/ Pfizer: 15,061 deaths and 1,399,513 injuries to 04/12/2021
- 38,170 Blood and lymphatic system disorders incl. 217 deaths
- 43,454 Cardiac disorders incl. 2,204 deaths
- 404 Congenital, familial and genetic disorders incl. 38 deaths
- 18,886 Ear and labyrinth disorders incl. 10 deaths
- 1,330 Endocrine disorders incl. 5 deaths
- 21,574 Eye disorders incl. 35 deaths
- 115,450 Gastrointestinal disorders incl. 602 deaths
- 354,635 General disorders and administration site conditions incl. 4,251 deaths
- 1,589 Hepatobiliary disorders incl. 78 deaths
- 15,371 Immune system disorders incl. 77 deaths
- 57,255 Infections and infestations incl. 1,605 deaths
- 22,928 Injury, poisoning and procedural complications incl. 261 deaths
- 34,691 Investigations incl. 464 deaths
- 9,568 Metabolism and nutrition disorders incl. 256 deaths
- 172,420 Musculoskeletal and connective tissue disorders incl. 187 deaths
- 1,254 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 122 deaths
- 236,435 Nervous system disorders incl. 1,609 deaths
- 2,000 Pregnancy, puerperium and perinatal conditions incl. 60 deaths
- 215 Product issues incl. 3 deaths
- 25,493 Psychiatric disorders incl. 182 deaths
- 4,981 Renal and urinary disorders incl. 236 deaths
- 49,076 Reproductive system and breast disorders incl. 5 deaths
- 60,177 Respiratory, thoracic and mediastinal disorders incl. 1,664 deaths
- 65,710 Skin and subcutaneous tissue disorders incl. 128 deaths
- 3,007 Social circumstances incl. 19 deaths
- 7,280 Surgical and medical procedures incl. 90 deaths
- 36,160 Vascular disorders incl. 653 deaths
Total reactions for the mRNA vaccine mRNA-1273(CX-024414) from Moderna: 9,084 deaths and 409,189 injuries to 04/12/2021
- 8,678 Blood and lymphatic system disorders incl. 102 deaths
- 13,650 Cardiac disorders incl. 953 deaths
- 166 Congenital, familial and genetic disorders incl. 7 deaths
- 4,940 Ear and labyrinth disorders incl. 4 deaths
- 373 Endocrine disorders incl. 4 deaths
- 5,992 Eye disorders incl. 31 deaths
- 33,407 Gastrointestinal disorders incl. 339 deaths
- 109,178 General disorders and administration site conditions incl. 3,117 deaths
- 673 Hepatobiliary disorders incl. 44 deaths
- 4,054 Immune system disorders incl. 16 deaths
- 15,636 Infections and infestations incl. 849 deaths
- 8,535 Injury, poisoning and procedural complications incl. 172 deaths
- 8,001 Investigations incl. 211 deaths
- 3,893 Metabolism and nutrition disorders incl. 220 deaths
- 49,233 Musculoskeletal and connective tissue disorders incl. 184 deaths
- 568 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 74 deaths
- 68,948 Nervous system disorders incl. 870 deaths
- 754 Pregnancy, puerperium and perinatal conditions incl. 6 deaths
- 82 Product issues incl. 2 deaths
- 7,472 Psychiatric disorders incl. 149 deaths
- 2,398 Renal and urinary disorders incl. 174 deaths
- 8,859 Reproductive system and breast disorders incl. 7 deaths
- 18,183 Respiratory, thoracic and mediastinal disorders incl. 975 deaths
- 21,946 Skin and subcutaneous tissue disorders incl. 82 deaths
- 1,872 Social circumstances incl. 39 deaths
- 1,642 Surgical and medical procedures incl. 115 deaths
- 10,056 Vascular disorders incl. 338 deaths
Total reactions for the vaccine AZD1222/VAXZEVRIA (CHADOX1 NCOV-19) from Oxford/ AstraZeneca: 6,515 deaths and 1,088,775 injuries to 04/12/2021
- 13,292 Blood and lymphatic system disorders incl. 254 deaths
- 19,523 Cardiac disorders incl. 720 deaths
- 203 Congenital familial and genetic disorders incl. 7 deaths
- 12,845 Ear and labyrinth disorders incl. 4 deaths
- 619 Endocrine disorders incl. 4 deaths
- 19,170 Eye disorders incl. 29 deaths
- 103,368 Gastrointestinal disorders incl. 340 deaths
- 286,356 General disorders and administration site conditions incl. 1,544 deaths
- 971 Hepatobiliary disorders incl. 62 deaths
- 4,99 Immune system disorders incl. 30 deaths
- 33,416 Infections and infestations incl. 441 deaths
- 12,583 Injury poisoning and procedural complications incl. 180 deaths
- 23,958 Investigations incl. 159 deaths
- 12,472 Metabolism and nutrition disorders incl. 96 deaths
- 161,308 Musculoskeletal and connective tissue disorders incl. 114 deaths
- 650 Neoplasms benign malignant and unspecified (incl cysts and polyps) incl. 25 deaths
- 223,680 Nervous system disorders incl. 1,007 deaths
- 533 Pregnancy puerperium and perinatal conditions incl. 14 deaths
- 191 Product issues incl. 1 death
- 20,150 Psychiatric disorders incl. 60 deaths
- 4,093 Renal and urinary disorders incl. 63 deaths
- 15,594 Reproductive system and breast disorders incl. 2 deaths
- 38,722 Respiratory thoracic and mediastinal disorders incl. 817 deaths
- 49,877 Skin and subcutaneous tissue disorders incl. 53 deaths
- 1,533 Social circumstances incl. 6 deaths
- 1,499 Surgical and medical procedures incl. 26 deaths
- 27,179 Vascular disorders incl. 457 deaths
Total reactions for the COVID-19 vaccine JANSSEN (AD26.COV2.S) from Johnson & Johnson: 1,989 deaths and 105,819 injuries to 04/12/2021
- 1,029 Blood and lymphatic system disorders incl. 41 deaths
- 1,952 Cardiac disorders incl. 169 deaths
- 36 Congenital, familial and genetic disorders
- 1,080 Ear and labyrinth disorders incl. 2 deaths
- 72 Endocrine disorders incl. 1 death
- 1,415 Eye disorders incl. 7 deaths
- 8,743 Gastrointestinal disorders incl. 80 deaths
- 27,925 General disorders and administration site conditions incl. 533 deaths
- 130 Hepatobiliary disorders incl. 11 deaths
- 473 Immune system disorders incl. 9 deaths
- 4,676 Infections and infestations incl. 157 deaths
- 974 Injury, poisoning and procedural complications incl. 20 deaths
- 4,927 Investigations incl. 111 deaths
- 664 Metabolism and nutrition disorders incl. 50 deaths
- 15,331 Musculoskeletal and connective tissue disorders incl. 45 deaths
- 59 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 4 deaths
- 20,725 Nervous system disorders incl. 219 deaths
- 43 Pregnancy, puerperium and perinatal conditions incl. 1 death
- 32 Product issues
- 1,479 Psychiatric disorders incl. 17 deaths
- 443 Renal and urinary disorders incl. 26 deaths
- 2,249 Reproductive system and breast disorders incl. 6 deaths
- 3,799 Respiratory, thoracic and mediastinal disorders incl. 259 deaths
- 3,241 Skin and subcutaneous tissue disorders incl. 8 deaths
- 337 Social circumstances incl. 4 deaths
- 718 Surgical and medical procedures incl. 58 deaths
- 3,267 Vascular disorders incl. 151 deaths

*These totals are estimates based on reports submitted to EudraVigilance. Totals may be much higher based on percentage of adverse reactions that are reported. Some of these reports may also be reported to the individual country’s adverse reaction databases, such as the U.S. VAERS database and the UK Yellow Card system. The fatalities are grouped by symptoms, and some fatalities may have resulted from multiple symptoms.
UK approves vaccine passes and mandatory jabs for healthcare workers
OffGuardian | December 15, 2021
Last night the UK Parliament voted through a bill forcing NHS workers to either get vaccinated or lose their jobs, as well bringing in “vaccine passports” for some events and venues.
Over 70,000 NHS workers are officially counted as “unvaccinated”, if you trust government numbers. Considering the NHS employs well over a million people, I wouldn’t be surprised if that number were actually much higher.
If just half of the unvaccinated workers resign it could put a lot of pressure on the always-over-burdened healthcare system.
The government wouldn’t mind that, of course, because it will make it easier to claim the NHS is being “overwhelmed” with Covid patients, and this will be blamed on the unvaccinated and used to justify further mandates and coercion.
Any deaths resulting from the under-staffed health system can be PCR tested and added to the “died with Covid” tally.
It’s a win-win.
The vaccine passport element of the bill is likewise concerning, even if it currently only applies to nightclubs and venues with a capacity of more than 10,000. That’s the thin edge of a rapidly-expanding wedge.
An interesting aspect of the vote was that it passed entirely thanks to the Labour party. Labour leader Sir Keir Starmer announced on Tuesday, in a bizarre-looking televised speech, that his party would support the government.
As a result all but eight “opposition” MPs voted with the government, whilst Tory rebel votes counted an even 100. If Labour had opposed the bill, it would not have passed.
Jeremy Corbyn, now an independent, voted against the government and emerged from his Covid hibernation to (finally) make a statement.
Much too little, and far too late, but it does illustrate why they needed to get rid of him in December 2019, just before the Covid roll-out, and why they so obviously rigged that election.
If he, as leader of the opposition, had been offering even this small amount of resistance from the beginning, the Covid narrative would never have made it this far.
Labour voting with the government, without even asking for concessions on sick pay or pay rises for NHS workers, is a sign that a changing of the guard may be on the horizon, with Keir Starmer being groomed to be the next PM, perhaps in the very near future.
That would explain the sudden emergence of the Christmas party scandal, which had further fuel added to its fire just today by yet another leak.
That, combined with the massive rebellion by his own MPs, is a massive knock on his authority.
Official polls, always a tool for controlling opinion rather than a scale for measuring it, are already putting Starmer 13 points ahead as the nations “most capable Prime Minister”.
Don’t be surprised if there are calls for another election, probably sometime soon. And they won’t be rigging this one for Boris.
New German Chancellor Says There Will Be “No Red Lines” As Regards COVID Restrictions
By Steve Watson | Summit News | December 15, 2021
Angela Merkel’s successor in Germany has declared that there is nothing he won’t do to battle COVID, a stark statement given previous pledges to make compulsory vaccinations legal.
Chancellor Olaf Scholz used his first address to the nation in Germany to push vaccinations, declaring that they are the only way Germany can overcome the pandemic.
Scholz added that there would be “no red lines” in the battle against the current wave of COVID, which he declared to be fueled by unvaccinated citizens.
“We will pull every possible lever,” he continued, adding “It will get better. Yes, we will win the fight against this pandemic with the biggest determination. And, yes, … we will overcome the crisis.”
He added that “our society is not divided,” and referring to people opposed to vaccinations proclaimed “We will not put up with a tiny minority of uninhibited extremists trying to impose their will on our entire society.”
While claiming “We are listening. We are looking for debate,” Scholz stated “There is in Germany today . . . denial of reality, absurd conspiracy stories, wilful disinformation and violent extremism.”
“We will counter this with the means of our democratic constitutional state. Our democracy is a democracy capable of defending itself,” the Chancellor further warned.
On Sunday, Scholz stated that he supports vaccine mandates across Germany, noting that he intends to “vote for compulsory vaccination, because it is legally permissible and morally right.”
Scholz previously said he wants to introduce mandatory coronavirus vaccination for all Germans as early as February, according to sources close to him.
Germany recently recorded its highest COVID death toll for 9 months, despite having mask mandates and stringent rules in many regions that banned the unvaccinated from numerous venues.
The country is preparing to follow the example of Austria by imposing new lockdown measures that will exclusively apply to the unvaccinated.
Featured Video

Get ready for the big Israeli false flag cyber-attack
or go to
Aletho News Archives – Video-Images
From the Archives
Some Call It Conspiracy Theory – Part 1
BY IAIN DAVIS | SEPTEMBER 25, 2023
There are certain assumptions that are applied to anyone labelled a “conspiracy theorist”—and all of them are fallacies. Indeed, the term “conspiracy theory” is nothing more than a propaganda construct designed to silence debate and censor opinion on a range of subjects. Most particularly, it is used as a pejorative to marginalise and discredit whoever challenge the pronouncements and edicts of the State and of the Establishment—that is, the public and private entities that control the State and that profit from the State.
Those of us who have legitimate criticisms of government and its institutions and representatives, who are therefore labelled “conspiracy theorists,” face a dilemma. We can embrace the term and attempt to redefine it or we can reject it outright. Either way, it is evident that the people who weaponise the “conspiracy theory” label will continue to use it as long as it serves their propaganda purposes.
One of the most insidious aspects of the “conspiracy theory” fabrication is that the falsehoods associated with the term have been successfully seeded into the public’s consciousness. Often, propagandists need do no more than slap this label on the targeted opinion and the audience will immediately dismiss that viewpoint as a “lunatic conspiracy theory.” Sadly, this knee-jerk reaction is usually made absent any consideration or even familiarity with the evidence presented by that so-called “lunatic conspiracy theorist.”
This was the reason why “conspiracy theorist” label was created. The State and its propagandists do not want the public to even be aware of inconvenient evidence, let alone to examine it. The challenging evidence is buried under the “wild conspiracy theory” label, thereby signalling to the unsuspecting public that they should automatically reject all of the offered facts and evidence.
There are a number of components that collectively form the conspiracy theory canard. Let’s break them down. … continue
Blog Roll
 Aletho News
- ‘Stop Putting Drugs in Our Food’: Scientists Link Folic Acid in Food to Rising Rates of Colorectal Cancer
- The 14 Things That Happen to Your Newborn in the First 48 Hours
- JFK’s Forgotten Confrontation with Israel
- Trump’s Cyber Director Pick Has Deep Ties To Israeli Intelligence
- Get ready for the big Israeli false flag cyber-attack
- The Ukrainian Reset experiment: A war and surveillance state blueprint for the EU
- Pentagon fails ninth financial audit in a row, unable to account for trillions in assets
- Russia rejects Danish plot claims, vows response to expulsion
- Study of 14,000 Children Links Vaccination to Higher Rates of Chronic Illness
- Strike Iran Again, Open Pandora’s Box | Brian McGlinchey
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- Germany’s Renewable Energies Lead to 1.4 Billion Euro Electric Power Trade Deficit
- Argentina’s Perito Moreno Glacier Joins Antarctica and Arctic In Defying Doomsday Melt Claims
- New Study: Barents Sea Temperatures Were Warmer And Sea Ice Less Extensive In The 1700s Than Today
- German Authorities Start Initiative To Evaluate Public Register For Climate “Disinformation” Spreaders!
- Zonal Asymmetry of Temperature Change in the Antarctic Circumpolar Current
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles

