OSHA to Cover Up Vaccine Injuries by Preventing Workers’ Compensation Claims
By Dr. Joseph Mercola | November 3, 2021
As reported by Kim Iversen above, around the world people are gathering for massive protests against COVID shot mandates. In mid-September 2021, Italy became the first European country to announce the implementation of mandatory COVID-19 health passes (so-called “Green Pass”) for all workers, both public and private.
The Italian mandate took effect October 15, 2021. Residents have been protesting in the streets for months on end and there’s no sign of them letting up. Demonstrations are also taking place in The Netherlands, Switzerland, Luxembourg, Greece, Romania, Slovenia, Australia and France.
Even in Israel, mass protests are now taking place as it was announced Israeli’s will lose their health pass privileges unless they get a third booster shot six months after their second dose. New York City has also seen large protests in the wake of its vaccine requirement for restaurants and other public venues.
Leaders Turn a Blind Eye
Yet, despite massive protests, the push for vaccine mandates and vaccine passports that will create a two-tier society continue unabated. With few exceptions, world leaders are simply turning a blind eye and a deaf ear to the fact that their residents want nothing to do with their new world order.
At the same time, government agencies charged with keeping us safe are doing the complete opposite. That includes the Occupational Safety and Health Administration (OSHA), which President Biden has placed in charge of enforcing his unconstitutional edict that private companies with 100 employees or more must make COVID “vaccination” a requirement for employment or face fines of as much as $700,000 per incidence.1
OSHA will issue the mandate for employers as an emergency temporary standard (ETS), but as of this writing, no official mandate has actually been issued.
According to an October 18, 2021, report by PJ Media,2 OSHA has sent a draft to the Office of Management and Budget (OMB) for review. Since it’s being issued as an ETS, there will be no public comment period.
Once the OMB review is finalized, the vaccination rule will be published. Only then will the mandate actually go into effect. That said, OSHA has already amended an already existing rule in a way that will hide the true extent of the damage that this mandate will have on the American workforce.
OSHA Rule Change Covers Up Vaccine Injuries
According to OSHA rules (29 CFR 19043), employers must record and report work-related illnesses, injuries and fatalities, whether the employer was at fault or not. As reported on May 26, 2021, by employment law firm Ogletree Deakins,4 this recording requirement initially also applied to adverse reactions suffered by employees who had to get the COVID shot as a requirement for employment.
The original guidance stated that employers were required to record an employee’s adverse reaction to the COVID jab if the shot was a) work-related, 2) a new case under 29 C.F.R. 1904.6 and 3) met one or more OSHA general recording criteria set out in 29 C.F.R. 1904.7. OSHA specified that an adverse reaction to the jab would be considered “work-related” if the shot was required for employment.
Then, in late May 2021, OSHA suddenly revoked this guidance, saying it will not enforce the recording requirement if the injury or fatality involves the COVID jab, even if required for employment. The nonenforcement will remain in place through May 2022, at which time the agency will reevaluate its position.
Why would they remove the requirement to record and report vaccine injuries incurred as a result of a vaccine mandate? According to OSHA, the agency is “working diligently to encourage COVID-19 vaccinations,” “does not wish to have any appearance of discouraging workers from receiving COVID-19 vaccination, and also does not wish to disincentivize employers’ vaccination efforts.”5,6 As reported by Ogletree Deakins:7
“There is no doubt that OSHA’s guidance created a disincentive for employers to mandate that their employees get vaccinated. With a mandatory vaccination policy, the guidance ensured that employees’ adverse reactions (with arguably little correlation to actual work-related injuries) could end up on a company’s OSHA recordkeeping logs — which could, in turn, negatively affect its insurance rates and, in some industries, its ability to bid for work.”
What Ogletree fails to address is that by not enforcing this recording requirement for COVID jab injuries, OSHA is intentionally covering up the ramifications these vaccine mandates might have on employees’ health. Meanwhile, employers are still required to record and report COVID-19 infections and COVID-19 deaths among their employees.
Federal Employees Get Special Treatment
In related news, federal employees must be fully “vaccinated” by November 22, 2021, or face the unemployment line. While coercion of this nature is abhorrent under any circumstance, federal employees at least get special treatment if they’re injured by the required jab. As reported by Stacey Lennox for PJ Media:8
“… October 1, 2021, the Federal Employee’s Compensation Act (FECA) issued a bulletin regarding coverage for vaccine injuries.9 FECA did not traditionally cover preventative measures and any resulting illness or injury. As of September 9, 2021, when President Biden announced the federal mandate, adverse reactions to COVID-19 vaccination are covered.”
As indicated in FECA Bulletin No. 22-01, dated October 1, 2021:10
“… this executive order now makes COVID-19 vaccination a requirement of most Federal employment. As such, employees impacted by this mandate who receive required COVID-19 vaccinations on or after the date of the executive order may be afforded coverage under the FECA for any adverse reactions to the vaccine itself, and for any injuries sustained while obtaining the vaccination.”
“This bulletin is an interesting turn of events given previous OSHA guidance to private employers,” Lennox writes.11 Indeed, while OSHA is selectively choosing to hide the vaccine injuries of private employees, federal employees will have access to financial compensation for their vaccine injuries, over and above the Countermeasures Injury Compensation Act (CICP).12
Who Will Pay for Private Employees Injured by the Jabs?
On the whole, it’s clear that private employees will be at a distinct disadvantage in terms of compensation. If their employer requires them to get the jab to keep their job, and they get injured by it, the only recourse they have is to file a CICP claim, which is near-impossible to get. By not requiring companies to record vaccine injuries, it effectively shuts down the path for an employee to seek worker’s compensation if they’re injured by a mandated COVID jab.
“While OSHA recordability does not govern worker’s compensation, after managing both for several employers, I have never seen a compensable injury that is not OSHA recordable,” Lennox writes.13
As for CICP, in its 15-year history, it has paid out fewer than 1 in 10 claims.14,15,16 It also offers rather limited help, as you first have to exhaust your personal insurance before it kicks in to pay the difference.
Even if they can get it, CICP awards are likely to be a drop in the bucket for most people. The average award is $200,000, and compensation for fatalities are capped at $370,376.17 Meanwhile, you can easily rack up a $1 million hospital bill if you suffer a serious thrombotic event.18
Perhaps most egregious of all, it’s your responsibility to prove your injury was the “direct result of the countermeasure’s administration based on compelling, reliable, valid, medical and scientific evidence beyond mere temporal association.”
In other words, you basically have to prove what the vaccine developer itself has yet to ascertain, seeing how you are part of their still-ongoing study. You must also pay for your own legal help and any professional witnesses you may need to support your claim.
The fact that federal workers who are injured by the mandated COVID jabs will be covered by FICA now gives unionized employees a new bargaining chip though. As noted by Lennox:19
“Without the OSHA ETS, unions would have bargained about having a vaccine mandate as a term or condition of employment at all. Now, unions should still have an opportunity for effects bargaining to ensure their members are covered if they sustain a vaccine injury.”
Recordability Guidance Must Be Changed Back
As mentioned earlier, the OSHA requirement to record vaccine injuries was scrapped because it disincentivized employers to mandate the shot. Having large numbers of injury reports can raise a company’s insurance costs. However, if OSHA is now going to require all employers with 100 or more employees to implement vaccine mandates, then most companies will be in the same boat.
Since no employer will be at a particular disadvantage, OSHA really needs to change its recordability guidance back, Lennox says, adding:20
“Private sector employees deserve the same protection as federal employees in the face of mandatory vaccines. The mandates will put a severe risk between them and their ability to earn a living for some people.
If they [employers] cave, they should be liable just as every taxpayer is now liable for a vaccine injury to a federal employee. If employers don’t want the liability, they should fight the mandate.”
Sources and References
- 1 Reuters September 13, 2021
- 2, 8, 11, 13, 19, 20 PJ Media October 18, 2021
- 3 OSHA 29 CFR 1904
- 4, 7 Ogletree.com May 26, 2021
- 5 OSHA FAQ Vaccine Related Questions
- 6 OSHA Protecting Workers, COVID-19
- 9 FECA Bulletin 2020-2024 (Archived)
- 10 FECA Bulletin No. 22-01 October 1, 2021
- 12 Congressional Research Service Legal Sidebar CICP March 22, 2021 (PDF)
- 14 Life Site News June 15, 2021
- 15 Insurance Journal August 14, 2020
- 16, 17 Insurance Journal December 29, 2020
- 18 The Defender June 2, 2021
Are Vaccines Driving Excess Deaths in Scotland, a Professor of Biology Asks
The Daily Sceptic • November 4, 2021
Professor Richard Ennos, a retired Professor of Evolutionary Biology at Edinburgh University, writes:
In Scotland this summer there has been excess mortality for the past 21 weeks with the total excess now exceeding 3,000 deaths. I and others have written to MSPs about the dreadful situation asking for a thorough analysis of what is responsible. In response we have been sent a reply from Anita Morrison, Head of Health and Social Care Analysis and Support, that I reproduce below. Five possible explanations are given, none of which reflect favourably on the Scottish Government’s public health policy. To paraphrase her reply, 45% are due to COVID-19 and the rest are accounted for by one or more of:
- COVID-19 deaths that were not recognised.
- Unintended consequences of the Scottish Government’s non-clinical response to COVID-19 (masks, social isolation etc.).
- Problems with access to the health and social care services (presumably due to Scottish government policy of withdrawing these).
- Patients not accessing services that were available (presumably because they were too scared of catching COVID-19 due to Scottish government exaggeration of the risks).
- Some other cause that has not been identified.
What follows is my reply to Anita Morrison to point out that her response is a damning indictment of Scottish Government public health policy whose outcome should ultimately be measured by the metric of excess deaths.


FAO: Anita Morrison
Head of Health and Social Care Analysis and Support
Directorate for Covid Public Health
Cc Dr. Gregor Smith, Jason Leitch, Caroline Lamb, Maree Todd MSP, Kevin Stewart MSP, Nicola Sturgeon MSP
28th October 2021
Dear Anita Morrison
Thank you for your response to my letter, originally addressed to Sarah Boyack MSP, concerning the unprecedented rise in excess deaths in Scotland this summer that continues as I write (252 excess deaths above five-year average in the past week 42, 24% higher than normal). It is now indisputable that some major health catastrophe is unfolding in Scotland this summer. It is clearly essential that there is serious scrutiny of the health policies that have been adopted by the Scottish Government that have led to this situation. To help with this I would like to look in some detail at the explanations that you have provided for the incredibly worrying situation, and set out the implications of what you have written.
In your response you have put forward the argument that some 45% of these excess deaths have been caused by Covid. This proposition relies on the assumption that all Covid deaths represent excess deaths, a position that is hard to sustain given that Covid deaths are associated with multiple comorbidities, and therefore are unlikely to be exclusively in addition to deaths that would have occurred anyway from other causes.
Setting aside this difficulty, and assuming that 45% of excess deaths are due to Covid, this indicates that the policies that have been pursued by the Scottish Government have been unsuccessful in controlling deaths from Covid this summer. This is in contrast to the summer of 2020 when there was no such excess of deaths due to Covid or any other cause. This increase in the impact of Covid in Scotland between the summers of 2020 and 2021 is nicely illustrated using National Records of Scotland data from the two years stratified by different age groups.

A simple and compelling explanation for these data is that a policy has been enacted in 2021 that was not enacted in 2020 that has caused a three- to six-fold increase in summer Covid hospitalisations. What could that be?
Let us now turn to the majority of excess deaths that cannot be accounted for by Covid. I will be using the most up to date figures from the National Records of Scotland for the summer period 2021 up to week 42 that indicate 3,028 excess deaths (rather than your figures that extend only to week 40). The National Records of Scotland classify these deaths according to their causes, location and age. This is illustrated below.

Here we see that Covid can actually account for a maximum of only 26% of excess deaths in summer 2021. Significant rises in cancer and circulatory deaths are concerning, but perhaps of greater note is that 44% of excess deaths come under the classification of ‘Other’. They are not the kinds of deaths that are readily classifiable into the normal categories that we expect in Scotland, or they would have been placed in those categories. It is therefore these ‘Other’ deaths, some 44% of the total, that we need to investigate in great detail.
From the other panels in the graph above we can see that these ‘Other’ deaths are occurring at home, implying that they are likely to have been sudden because there has been no hospital admission. Furthermore, these excess deaths are not confined to the oldest age groups, where we expect most deaths, but are extended into the younger age group. Analysis of the timing of this rise in excess death shows that it started in the oldest age group and is initiated sequentially in ever younger age groups (see graph below). This strongly suggests that there is some cause for these excess deaths at home that operates first in the elderly and works its way sequentially down the age groups in Scotland. What could this be?

Now let us look at the non-Covid explanations that you have provided for the dramatic increase in excess deaths in Scotland over the past summer.
Your first explanation is that the summer excess deaths recorded as non-Covid are actually due to Covid, but have not been certified as such. I see that you yourself are not convinced by this explanation given the level of testing that has taken place. However, let us suppose this to be true. In that case the Scottish Government’s public health measures that have been put in place in summer 2021 to prevent Covid have been far worse than those put in place in summer 2020 – indeed they have been disastrous.
Your second explanation is that the non-clinical responses to COVID-19 put in place by the Scottish Government (mask-wearing, social isolation etc.) have had unintended deleterious consequences on public health and have dramatically increased the rates of death in the Scottish population. This is an admission of abject failure of the Scottish Government’s public health response to Covid. Public health policy is all about balancing the benefits and risks of interventions to achieve the lowest possible impact during a health emergency. It is pertinent to remember that no benefit-risk assessment of non-clinical interventions on the physical and mental health of the Scottish population was conducted before these interventions were enforced.
Your third explanation is that there has been a problem with access to health and social care services, and patients have not received the care they required from the NHS. Access to these services over the past 20 months has been under the control of the Scottish Government, so if this explanation is correct, then the Scottish Government is culpable for increasing the death rate in Scotland. Numerous policies have been deliberately pursued to dramatically reduce GP face-to-face consultation, to cancel appointments and operations in hospitals etc., so the evidence to support this, as at least a partial explanation, is overwhelming.
Your fourth explanation is that individuals who are in poor health have not referred themselves to health and social care services as they would at other times. To some extent this would be confounded with Scottish Government policies of restricting health care provision discussed above. However there has also been a concerted and relentless media campaign by the Scottish Government to increase fear in the public, particularly fear of hospitals where they may catch Covid. This has meant that they have not gone for treatment when it was necessary. Whatever the proximal cause of failure to seek medical attention, the ultimate cause and responsibility lies in Scottish Government policy.
Your final explanation for the dramatic rise in excess deaths in summer 2021 is that there is some other cause that has not yet been identified. As noted earlier the phenomenon of excess deaths in the presence of a Covid epidemic was not seen in summer 2020, but is seen in summer 2021. What differs between the two years? The glaringly obvious answer is the rollout of COVID-19 vaccination. There was no COVID-19 vaccination programme in 2020, but there was rollout of Covid vaccinations in a sequential way to increasingly younger age groups in 2021, a pattern that we see in the manifestation of excess deaths. All of the COVID-19 vaccines are novel and experimental with no long-term safety data. They are now associated with a wide range of serious side-effects (blood clotting, myocarditis, Guillain-Barre syndrome) whose likely frequency in the wider population was not assessed in the small-scale phase one and two trials that included only a subset of healthy volunteers. The Yellow Card adverse events reporting system, that capture only a fraction of events, has already recorded over 1,700 deaths in the U.K. population associated with the COVID-19 vaccines. There is therefore a prima facie case for COVID-19 vaccination being a contributing factor to the dramatic rise in summer excess deaths in Scotland in 2021.
I am very grateful for your response to my original letter. It has been extremely helpful in crystalising my thoughts about the causes of the dramatic and continuing rise in excess deaths that we currently see in Scotland. My conclusion is that whatever the true explanation for the phenomenon, it is rooted in the misguided and disastrous public health policies of the Scottish Government. The analysis has moreover highlighted that a significant contributor to the excess death of the Scottish population this summer may be adverse reactions to the COVID-19 vaccines, a factor that apparently has not occurred to either the Scottish Government or yourself. I would be grateful if you would pass on this insight to the Scottish Health minister so that unnecessary suffering and death is not meted out on the adults, and now children of Scotland.
Yours sincerely
Richard Ennos
White House Expands Vaccine Mandate To Cover 80 Million Workers
By Tyler Durden | Zero Hedge | November 4, 2021
The White House has just released new policies requiring all companies – big and small – to coerce their workers into accepting the vaccine, or face termination, as the Biden Administration continues to up the pressure on all working Americans to get vaccinated before Jan. 4.
According to Axios, President Biden is planning to announce Thursday that employers with more than 100 workers on their payroll must guarantee that their workers are fully vaccinated, or tested weekly, by Jan. 4, 2022. If not, they could face federal fines starting at tens of thousands of dollars per offense.
What’s more, health-care workers will face even tougher restrictions which will effectively require every health-care worker in the country to be vaccinated, or lose their job, despite the fact that millions of health-care workers have already been infected with the virus by natural means.
To be sure, managing weekly testing programs for a minority of corporate employees will be extremely costly, and the ramifications of this new policy will essentially force employees for the biggest companies in the US to accept the vaccine.
Per Axios, the new rules – formally known as the COVID-19 Vaccination and Testing Emergency Temporary Standard – will be enforced by OSHA. They will affect roughly two-thirds of America’s workforce, or roughly 80MM people. Many businesses and hospitals have already started to enforce vaccine mandates, and while Axios reports that they have seen “minimal” noncompliance, that doesn’t exactly square with the fact that less than 60% of the American population is fully vaccinated.
While corporations might be able to absorb some of these costs, small businesses will likely be left with some difficult decisions to make. However, there’s one important catch: OSHA will mostly rely on “complaints” to enforce the rule, meaning it will be up to American workers whether or not they want to hold their fellow workers accountable for defying the policy. This incentive to snitch out co-workers and neighbors has already elicited criticism from some, including Conservative Radio host Dan Bongino, who has pushed back against vaccine mandates in favor of bodily autonomy.
The strict mandate for health-care workers is already creating some problems because, while 40% of health-care businesses have purportedly already enforced the policy, the supposedly “minimal” level of noncompliance is reportedly exacerbating worker shortages at hospitals and other critical service providers.
In another indication of how companies are struggling with the mandate, some federal contractors had been expected to enforce the Biden Admin’s vaccine mandate by Dec. 8, but those expectations have now been pushed back to Jan. 4. When asked whether the pushback was due to worker shortages, or the timing of the holiday season, they refused to comment, saying only that the delay is meant to “align” with health-care facilities and US employers.
Perhaps President Biden (and VP/President-in-waiting Kamala Harris) have already forgotten the lessons of Tuesday’s “off-year” election?
Pfizer Is Calling The Shots To Jab Kids
Dr. Joseph Mercola | November 1, 2021
In late February 2021, The Bureau of Investigative Journalism reported1 that Pfizer was demanding countries put up sovereign assets as collateral for expected vaccine injury lawsuits resulting from its COVID-19 inoculation.
While at least two countries, Argentina and Brazil, initially rejected the demands, calling them abusive, many others accepted Pfizer’s terms from the start.
Public Citizen has now reviewed and published the secret contracts2,3 between Pfizer and Albania, Brazil, Colombia, Chile, Dominican Republic, the European Commission, Peru, the U.S. and the U.K. These contracts reveal nations have handed over unprecedented power to Pfizer. In virtually all scenarios, Pfizer’s interests come first.
Pfizer Is Calling The Shots
Public Citizen points out six ways in which nations are allowing Pfizer to call the shots. For example, Albania, Brazil and Colombia have handed over unilateral authority to the company for the delivery schedule and other key decisions. As reported by Public Citizen:4
“As a condition to entering into the agreement, the Colombian government is required to ‘demonstrate, in a manner satisfactory to Suppliers, that Suppliers and their affiliates will have adequate protection, as determined in Suppliers’ sole discretion’ … from liability claims.
Colombia is required to certify to Pfizer the value of the contingent obligations (i.e., potential future liability), and to start appropriating funds to cover the contingent obligations, according to a contribution program.”
Pfizer also maintains tight control over vaccine supplies, and dictates who can buy their vaccine, when, and who can give and receive vaccine donations. If there are shortages, Pfizer decides which countries get priority.
Bypassing Pfizer can be costly. For example, if Brazil were to accept vaccine donations from another country without Pfizer’s approval, the company can terminate the contract and force Brazil to pay the full prize for all remaining contracted doses. Meanwhile, Pfizer incurs no penalty if its delivery is late, even if it’s so late that the shots are no longer needed.
Some countries, including Brazil, Chile, Colombia, the Dominican Republic and Peru, also ended up agreeing to Pfizer’s demand to put up sovereign assets as collateral for vaccine injury lawsuits, including bank reserves, military bases and embassy buildings.
In short, theses governments are guaranteeing Pfizer will be compensated for any expenses resulting from injury lawsuits against it, so the company won’t lose a dime if its COVID shot injures people — even if those injuries are the result of negligent company practices, fraud or malice!
At the same time, government purchasers must acknowledge that the effectiveness and safety of the shots are completely unknown. This is the ultimate corporate maleficence, using their leverage to force the kill shot down these countries’ throats and avoiding any personal responsibility for damages.
Secret Arbitration
The contracts also dictate how contractual disputes will be settled. As reported by Public Citizen:5
“What happens if the United Kingdom cannot resolve a contractual dispute with Pfizer? A secret panel of three private arbitrators — not a U.K court — is empowered under the contract to make the final decision. The arbitration is conducted under the Rules of Arbitration of the International Chamber of Commerce (ICC). Both parties are required to keep everything secret:
‘The Parties agree to keep confidential the existence of the arbitration, the arbitral proceedings, the submissions made by the Parties and the decisions made by the arbitral tribunal, including its awards, except as required by Law and to the extent not already in the public domain.’
The Albania draft contract and Brazil, Chile, Colombia, Dominican Republic, and Peru agreements require the governments to go further, with contractual disputes subject to ICC arbitration applying New York law. While ICC arbitration involving states is not uncommon, disputes involving high-income countries and/or pharmaceuticals appear to be relatively rare
Private arbitration reflects an imbalance of power. It allows pharmaceutical corporations like Pfizer to bypass domestic legal processes. This consolidates corporate power and undermines the rule of law.”
Pfizer Secured Intellectual Property Rights
Amazingly, the contracts not only secure Pfizer’s intellectual property rights, but should Pfizer be found guilty of stealing the intellectual property rights of others, some of the contracts shift the responsibility away from Pfizer onto the government purchasers! What this means is that Pfizer can steal the intellectual property of others without consequence in at least four countries.
“For example, if another vaccine maker sued Pfizer for patent infringement in Colombia, the contract requires the Colombian government to foot the bill,” Public Citizen writes.6 “Pfizer also explicitly says that it does not guarantee that its product does not violate third-party IP, or that it needs additional licenses.
Pfizer takes no responsibility in these contracts for its potential infringement of intellectual property. In a sense, Pfizer has secured an IP waiver for itself. But internationally, Pfizer is fighting similar efforts to waive IP barriers for all manufacturers.”
Pfizer Given Right To Silence Governments
Perhaps most egregious of all, some of the contracts give Pfizer the right to muzzle government. In Brazil, government officials are prohibited from making “any public announcement concerning the existence, subject matter or terms of [the] Agreement” without the written consent of the company.
The gag order also includes commenting on the government’s relationship with Pfizer in general. Similar nondisclosure provisions are included in the contracts with the European Commission and the U.S. government. The only difference, Public Citizen notes, is that the nondisclosure rules apply to both parties.
Pfizer Can Prevent Use Of Other Remedies
Equally shocking, though, is that countries are forced to follow through on their vaccine orders even if other drugs or treatments emerge that can prevent, treat or cure COVID-19.7 Is it any wonder, then, that governments around the world have suppressed the use of drugs like hydroxychloroquine and ivermectin?
If these drugs were allowed to be used and could be proven to work, the COVID injections would be completely unnecessary, yet governments are on the hook for hundreds of millions of doses. While COVID-19 vaccines are “free” to receive in the U.S., they’re being paid for by taxpayer dollars at a rate of $19.50 per dose. In Albania, the cost of each dose is $12, and in the EU, $14.70.
In the case of the price disparity between the U.S. and the EU, Pfizer is said to have given a price break to the EU because it financially supported the development of their COVID-19 vaccine.
As noted Public Citizen, Pfizer is being allowed to profit from this self-inflicted global disaster in unprecedented ways. In many instances, a nation’s laws will not apply to Pfizer.
These secret contracts grant Pfizer total control over its product and ensures full payment, regardless of whether the shots are needed or usable, while simultaneously eliminating all liability. In short, Pfizer wins, no matter what the outcome of the vaccination campaign might be.
At the same time, Pfizer is also controlling media through its advertising dollars. As you’ve probably realized by now, media companies in most instances will not report on anything that might jeopardize the profits of its advertisers.
As illustrated in the short video above, it couldn’t be more obvious that Pfizer is bankrolling the media, which in turn will refuse to bite the hand that feeds it. You can see the wide spectrum of media programming being sponsored by Pfizer, including “Nightline,” “Making a Difference,” “CNN Tonight,” “Early Start,” “Erin Burnett Out Front,” “This Week with George Stephanopoulos,” “CBS Sports,” “Meet the Press,” “CBS This Morning” and “60 Minutes.”
The terms of these contracts are all the more disturbing when you consider how dangerous the Pfizer shot is turning out to be. No wonder the company refused to accept any liability.
According to Pfizer’s own data, one COVID death per 20,000 fully vaccinated individuals is prevented. That means 10,000 lives are saved if 200 million are fully vaccinated.
But how many lives are lost from the shots? This is the other side of the equation that simply demands to be analyzed before any governmental authority can make a decision as to whether the mass vaccination campaign is of benefit or not.
Here, we find that Pfizer’s data10 show the shots are actually killing more than they save. To look at this information yourself, click on “Supplementary Material” on the right-hand side of the paper, then, beside Supplementary Appendix, click on supplements/261159 and scroll down to page 12, Table S4.
In the vaccine group, 15 died; in the placebo group 14 died. Two people died from COVID-19 in the placebo group, while only one died from COVID pneumonia in the vaccine group. That’s how you get a net false positive impact — one life is spared from COVID. However, the all-cause mortality was actually higher in the vaccine group (15, compared to 14).
So, while the shots saved one person from dying from COVID, they also killed one extra person. So, the net effect is nil. There’s no mortality benefit at all. Other investigations using different data strongly suggest the net effect is profoundly negative, and the shots are doing FAR more harm than good.
We Face Looming Vaccine-Induced Public Health Catastrophe
For this, Kirsch cites a paper11 by Dr. Bart Classen, published in the August 2021 issue of the journal Trends in Internal Medicine. Classen points out that Pfizer, Moderna and Janssen are all using a “dangerously misleading” clinical trial design. The problem is that they’re all using a surrogate endpoint for health, namely “severe infections with COVID-19.”
Disease specific primary endpoints are no longer used in many fields of medicine, for the fact that it can hide problems. If a person dies from the treatment or is severely injured by it, even if the treatment helped block the progression of the disease they’re being treated for, the end result is still a negative one.
For this reason, the appropriate endpoint that should be used is all-cause mortality and morbidity. When Classen reexamined the clinical trial data from all three manufacturers using all-cause severe morbidity as the endpoint, a disturbing picture emerged.
As explained by Classen in his paper, “US COVID-19 Vaccines Proven to Cause More Harm than Good Based on Pivotal Clinical Trial Data Analyzed Using the Proper Scientific Endpoint, ‘All Cause Severe Morbidity’”:12
“‘All-cause severe morbidity’ in the treatment group and control group was calculated by adding all severe events reported in the clinical trials. Severe events included both severe infections with COVID-19 and all other severe adverse events in the treatment arm and control arm respectively.
This analysis gives reduction in severe COVID-19 infections the same weight as adverse events of equivalent severity. Results prove that none of the vaccines provide a health benefit and all pivotal trials show a statistically significant increase in ‘all-cause severe morbidity’ in the vaccinated group compared to the placebo group.
The Moderna immunized group suffered 3,042 more severe events than the control group. The Pfizer data was grossly incomplete but data provided showed the vaccination group suffered 90 more severe events than the control group, when only including ‘unsolicited’ adverse events.
The Janssen immunized group suffered 264 more severe events than the control group. These findings contrast the manufacturers’ inappropriate surrogate endpoints:
Janssen claims that their vaccine prevents 6 cases of severe COVID-19 requiring medical attention out of 19,630 immunized; Pfizer claims their vaccine prevents 8 cases of severe COVID-19 out of 21,720 immunized; Moderna claims its vaccine prevents 30 cases of severe COVID-19 out of 15,210 immunized.
Based on this data it is all but a certainty that mass COVID-19 immunization is hurting the health of the population in general. Scientific principles dictate that the mass immunization with COVID-19 vaccines must be halted immediately because we face a looming vaccine induced public health catastrophe.”
To make the above numbers more clear and obvious, here are the prevention stats in percentages:
- Pfizer 0.00036 percent
- Moderna 0.00125 percent
- Janssen 0.00030 percent
CDC Claims COVID Shots Lower All-Cause Mortality
Despite all of that, the U.S. Centers for Disease Control and Prevention now claims Americans “vaccinated” against COVID-19 have lower all-cause mortality rates.13 As reported by Forbes:14
“Partially and fully vaccinated people died from non-coronavirus causes at a lower rate than their unvaccinated peers, according to the study,15 which looked at millions of patients at seven U.S. health organizations from December to July.
All three vaccines approved by U.S. regulators were tied to lower non-COVID death rates, though the difference in mortality among people who took Johnson & Johnson’s vaccine was slightly smaller than for recipients of Pfizer or Moderna’s vaccines …
This result suggests the vaccines don’t increase a patient’s risk of death, which ‘reinforces the safety profile of currently approved COVID-19 vaccines,’ the study said.”
October 26, 2021, the FDA unanimously voted to grant emergency use approval of the COVID shots for children between the ages of 5 and 11.16 This despite acknowledging they have no idea what the long-term risk to children might be. As noted by one voting member, “We’re never going to learn about how safe the vaccine is until we start giving it.”17
All we have at present is two Pfizer trials, one in which 5- to 11-year-olds were followed for two months and another with just six weeks of follow-up. Both were too small to detect potential risks such as myocarditis. That won’t be studied until AFTER the shot is authorized for children. As reported by The Defender :18
“Experts raised concerns over the lack of safety and efficacy data presented by Pfizer for use of its COVID vaccine in younger children, and they pointed to increasing safety signals based on reports to the Vaccine Adverse Event Reporting System (VAERS). They also questioned the need to vaccinate children — whose risk of dying from COVID is “almost nil” — at all.
According to Dr. Meryl Nass, member of the Children’s Health Defense Scientific Advisory Panel, Pfizer once again did not use all of the children who participated in the trial in their safety study.
‘Three thousand children received Pfizer’s COVID vaccine, but only 750 children were selectively included in the company’s safety analysis,’ Nass said.
‘Studies in the 5-11 age group are essentially the same as the 12-15 group — in other words, equally brief and unsatisfying, with inadequate safety data and efficacy data, with no strong support for why this type of immuno-bridging analysis is sufficient … All serious adverse events were considered unrelated to the vaccine’
Dr. Jessica Rose, viral immunologist and biologist, told the panel EUA of biological agents requires the existence of an emergency and the nonexistence of alternate treatment. ‘There is no emergency and COVID-19 is exceedingly treatable,’ Rose said.
In a peer-reviewed study19 co-authored by Rose, myocarditis rates were significantly higher in people 13 to 23 years old within eight weeks of the COVID vaccine rollout. In 12- to15-year-olds, Rose said, reported cases of myocarditis were 19 times higher than background rates …
Rose said tens of thousands of reports have been submitted to VAERS for children ages 0 to 18. Rose explained: ‘In this age group, 60 children have died — 23 of them were less than 2 years old. It is disturbing to note that ‘product administered to patient of inappropriate age’ was filed 5,510 times in this age group. Two children were inappropriately injected, presumably by a trained medical professional, and subsequently died.’”
During the meeting, Dr. Cody Meissner noted we don’t know whether the shot is safe for this age group, and the risk of COVID is extremely low. If the shot is authorized, mandates will likely follow, which would be “bad.”
Brownstone Institute is also objecting to the authorization. In an October 20, 2021, article,20 Paul Elias Alexander, Ph.D., a former assistant professor of evidence-based medicine and research methods, called the plan to vaccinate young children “absolutely reckless” and “dangerous based on lack of safety data and poor research methodology.”
Meanwhile, data show not a single child has died from COVID-19 who did not have a serious underlying health condition. Alexander reviews a lot of that data in his article.
Staggering Conflicts Of Interest
When you look at the roster of the FDA’s committee members21 who reviewed and voted to authorize the Pfizer shot for children as young as 5, the unanimous “yes” vote becomes less of a mystery. As reported by National File,22 they have staggering conflicts of interest. Members include:
- Gregg Sylvester — A former vice president of Pfizer Vaccines
- Arnold S. Monto — A paid Pfizer consultant
- Archana Chatterjee — A recent Pfizer research grant recipient
- Myron Levine — Mentor to Raphael Simon, senior director of vaccine research and development at Pfizer
- James Hidreth — President of Meharry Medical College, which administers Pfizer vaccines
- Geeta Swamy — Chair of the Independent Data Monitoring Committee for the Pfizer Group B Streptococcus Vaccine Program
- Steven Pergam — Proudly photographed taking a Pfizer vaccine
- Several people who are already on the record supporting coronavirus vaccines for children, including Ofer Levy, Jay Portnoy and Melinda Wharton
In addition to that, former FDA commissioner Scott Gottlieb is currently on Pfizer’s board of directors.
FDA Buries Data On Seriously Injured Children
With these shots now being pushed on young children, it’s more imperative than ever to understand how data are being massaged and manipulated to support the ongoing lunacy. Of particular concern is evidence that the U.S. Food and Drug Administration is burying data on children who were seriously injured in the vaccine trials. As reported by Aaron Siri on Substack:23
“Pfizer’s clinical trial for children aged 12-15 included only 1,131 children who were vaccinated and at least one of those children suffered a devastating, life-altering injury which, despite incontrovertible proof and the cries of both the victim and her parents, has not been appropriately acknowledged by Pfizer or the FDA.
Putting aside that one serious injury in a small trial should alone raise blaring alarm bells, one must ask: what other serious adverse events have been hidden and ignored by regulators?”
Siri tells the story of 12-year-old Maddie de Garay, who along with her two brothers were enrolled by her parents in Pfizer’s clinical trial. That decision has changed the lives of the entire family, possibly forever. Within 24 hours of her second dose, Maddie suffered crippling pain and systemic injuries.
Maddie is now wheelchair-bound and requires a feeding tube. Pfizer’s principal investigator initially claimed Maddie’s injuries were unrelated to the shot and treated her as a mental patient. Eventually, her injury was listed as “functional abdominal pain” in Pfizer’s report to the FDA.
“For a virus that rarely harms children, the need to assure safety of the Covid-19 vaccine is high. A study with only 1,131 children is underpowered. It will not pick up anything but the most common adverse events.
If what Maddie suffered will occur in 1/1,000 children, that would result in 75,000 children in this country suffering this serious injury. If it happens 1/10,000 children, that is 7,500 suffering this serious injury.
“It could be that the cure is worse than the disease. But that will only be known if there is a properly powered (a.k.a., sized) clinical trial with children,” Siri writes, adding that:
“International scientists have declared that ‘inadequately powered studies should themselves be considered a breach of ethical standards.’24 Without a clinical trial of sufficient size that reviews all potential adverse events, such as that experienced by Maddie, for a sufficient duration, this potentially catastrophic result will not be identified prior to authorization or licensure …
The real lesson is not that pharmaceutical companies, or the FDA should act better or do a better job. That just won’t always be the case. The real lesson is that civil and individual rights should never be contingent upon a medical procedure. Never.
Preserving those rights to choose whether to get a medical product, without any government coercion, is the final and ultimate safeguard.
Removing that right results in dangerous authoritarianism because just as the FDA will not admit to Maddie’s serious injury after having promoted this vaccine, politicians that mandate the vaccine will not want to later admit a mistake by repealing the mandate.”
FDA Sued To Access COVID Jab Trial Data
We’re now in a position where it’s near-impossible for many to refuse the COVID jab, and if injured, they cannot sue anyone for damages. Adding insult to injury, we don’t even have access to all the data governments are supposedly relying on to mandate these hazardous products.
To address this last point, an organization called Public Health and Medical Professionals for Transparency (PHMPT) is now suing25 the FDA after the agency refused to release the data on which it based its decision to approve Comirnaty.26
The FDA denied the PHMPT request for expedited processing of its Freedom of Information Act (FOIA) request on the basis that no “imminent threat to the life or physical safety of an individual” existed. Per the complaint:27
“… in an effort to ensure that the FDA acts in furtherance of its commitment to transparency, PHMPT seeks to obtain the data and information relied upon by the FDA to license the Pfizer Vaccine.
The importance of releasing to the public this information is also recognized under federal law which provides that: ‘After a license has been issued, the following data and information in the biological product file are immediately available for public disclosure unless extraordinary circumstances are shown: (1) All safety and effectiveness data and information. (2) A protocol for a test or study …’”
‘Just Say No’ To The COVID Shot
While U.S. authorities are doing their best to hide incriminating data and manipulating the rest to show some sort of benefit, common sense, medical facts and available data all point in the opposite direction. It’s crystal clear to me that children do not need the COVID shot, as their risk of serious COVID-19 infection and death is virtually nonexistent.
On the other hand, children are quite likely to be seriously injured by these injections. The reason you’re not getting the truth from the media is explained by Dr. Peter McCullough in the video above. In short, it’s a planned propaganda campaign — “the promotion of false information by the people in charge.”
According to McCullough, anyone under the age of 50 has a less than 1 percent chance of a bad outcome if they come down with COVID-19. “Why would you take the vaccine?” he asks. “My advice,” he says, “is just say no to this [shot], especially young people who are not at risk.”
Sources and References
- 1 The Bureau of Investigative Journalism February 23, 2021
- 2, 4, 5, 6 Public Citizen October 19, 2021
- 3 Twitter Zain Rizvi October 19, 2021
- 7 COVID19up.org August 17, 2021
- 8 SKirsch.io/vaccine-resources
- 9, 10 MedRxiv July 28, 2021
- 11, 12 Trends in Internal Medicine 2021; 1(1): 1-6 (PDF)
- 13, 15 CDC Morbidity and Mortality Weekly Report October 22, 2021: 70
- 14 Forbes October 22, 2021
- 16 ZeroHedge October 26, 2021
- 17 Twitter Techno Fog October 26, 2021
- 18 The Defender October 26, 2021
- 19 Curr. Probl. Cardiol. September 30, 2021; 101011
- 20 Brownstone Institute October 20, 2021
- 21 FDA Members Office of Vaccine Research and Review Meeting Roster
- 22 National File October 26, 2021
- 23 Aaronsiri.substack.com October 22, 2021
- 24 PLOS Medicine August 2008; 5(8): e172
- 25, 27 US District Court Northern District of Texas Case 4:21-cv-01058-P
- 26 Aaronsiri.substack.com October 11, 2021
CDC Advisors Unanimously Endorse Pfizer’s COVID Vaccine for Kids 5-11 Despite Expert Concerns Over Clinical Data
By Megan Redshaw | The Defender | November 2, 2021
The Centers for Disease Control and Prevention’s (CDC) vaccine advisory panel today unanimously recommended Pfizer’s COVID vaccine for children 5 to 11, despite concerns raised during the meeting about Pfizer’s clinical data, the fact that children who previously acquired natural immunity to COVID were included in clinical trials and evidence showing COVID poses little risk to children.
If Dr. Rochelle Walensky, the CDC’s director signs off on the decision, children ages 5 through 11 could start receiving COVID vaccines as early as tonight.
The younger age group will receive one-third of the dose authorized for those 12 and older in two shots at least three weeks apart. The doses will be delivered by smaller needles and stored in smaller vials to avoid a mix-up with adult doses.
The CDC’s guidelines for the vaccine’s use are not legally binding, but heavily influence the medical community’s practice.
Prior to today’s decision by the CDC’s Advisory Committee on Immunization Practices (ACIP) the Biden administration enlisted more than 20,000 pediatricians, family doctors and pharmacies to administer the vaccines — with 15 million doses already packed with dry ice, loaded into small specialized containers and shipped via airplanes and trucks to vaccination sites across the country, federal officials said on Monday.
Walensky sent a clear signal during the ACIP meeting about where she stands, CNN reported. “We have been asking when we will be able to expand this protection to our younger children,” Walensky said in opening comments to the committee.
“As you review the data today, it will be key to keep in mind the specific risks to children from this virus and the pandemic, and to put that risk into context of other vaccine-preventable diseases,” Walensky said.
Walensky noted that children are routinely vaccinated against diseases like chickenpox — which results in far fewer hospitalizations and deaths in children compared to COVID.
During today’s meeting, ACIP members reviewed and discussed the science behind the U.S. Food and Drug Administration’s (FDA) authorization last week of Pfizer’s COVID vaccine in all children 5-11 years old.
That authorization was based mostly on a Pfizer-BioNTech study of 4,600 children worldwide, of whom approximately 3,100 got the low-dose vaccine and about 1,500 got a placebo.
These studies showed the vaccine is about 91% effective against COVID. The immune system response to the vaccine, as measured by antibodies, was comparable to the response seen in 16- to 25-year-olds, NPR reported.
During the meeting, the CDC said 745 children under 18 have died of COVID since the beginning of the pandemic — although the COVID-19 team admitted 79% were confirmed to be hospitalized for COVID, while the rest were hospital admissions for other causes.
“The chance that a child will have severe COVID, require hospitalization or develop a long-term complication like MIS-C [multisystem inflammatory syndrome] remains low, but still the risk is too high and too devastating to our children, and far higher than for many other diseases for which we vaccinate children,” Walensky said.
Efficacy of Pfizer’s COVID vaccine in children
The CDC said Pfizer’s COVID vaccine was 90.9% effective against symptomatic COVID and none of the adverse events experienced during clinical trials were assessed by “the investigator” as related to the vaccine.
To determine the efficacy of the Pfizer-BioNTech COVID vaccine, Pfizer measured the blood of 264 children for antibodies.
“There were 3,000 vaccinated children in the trial. Why isn’t blood from the other 2,700-plus being measured for antibodies?” asked Dr. Meryl Nass, a member of the Children’s Health Defense Scientific Advisory Panel.
“Pfizer never explains why, when they have an important clinical trial in which over 3,000 children were injected in this age group, only a subset of less than 10% were used to assess efficacy,” Nass said.
Nass explained:
“Pfizer claims three cases of COVID in the vaccinated group versus 16 in the placebo group show efficacy of the vaccine. But the FDA did not accept this claim. Note that all cases were mild, none hospitalized or died. So are they planning to vaccinate 28 million kids to prevent colds?”
Nass noted Pfizer also enrolled kids who had prior evidence of having had COVID in the clinical trial, “which should never have been allowed.”
“Of the kids who were already immune at the start of the trials, none developed COVID,” Nass said. “About 150 kids in the placebo group were recovered and none got COVID.”
Nass said kids with preceding COVID infection did not have their antibody levels checked after the first dose, as Pfizer stated they did not collect the data because they “tried to minimize blood draws in children.”
“The real reason they did not want to collect data is because it might support the fact that kids who already had COVID might only need one vaccine dose, or none at all,” Nass said.
During the brief public comment session, Patricia Neuenschwander, a registered nurse noted there was no prevention of hospitalization, death or multisystem inflammatory syndrome in children — a condition being used to justify vaccinating younger children against COVID, despite numerous cases of MIS-C having been reported after receipt of a COVID vaccine.
Neuenschwander reminded the ACIP that vaccinations do not prevent infection or transmission. It is a mild illness in the vast majority of children, she said, and prior immunity is being ignored — the expansion group was only followed for 17 days.
David Wiseman, a research scientist with a background in pharmacy, pharmacology and experimental pathology, asked the CDC panel why the efficacy study was not validated by the FDA, and why Pfizer changed the buffer [see page 14] in the vaccine but did not test it in animals or kids — planning to use an untested version of the vaccine in 5 to 11-year-olds.
Wiseman said the FDA abandoned its responsibility, and he asked if the ACIP would do the same.
Myocarditis and COVID in 5- to 11-year-olds
One side effect that generated considerable discussion at today’s meeting was myocarditis — a form of heart inflammation.
The CDC said 1,640 cases of myocarditis have been reported to the CDC’s Vaccine Adverse Event Reporting System in people under age 30 after having received a COVID vaccine, but only 877 met the CDC’s case definition.
The CDC said there were nine reported deaths in people with myocarditis, but then the agency reduced the number to three, with two cases pending evaluation and one case without adequate information.
“I have to say that it is beyond belief that CDC could whittle down 877 cases reported in young people to three actual cases. Where did the rest go?” Nass asked.
“According to the CDC’s Vaccine Safety Datalink, 7 of 16 12- to 17-year-olds with myocarditis were still on exercise restriction three months after diagnosis — that is 44% could not exercise three months later,” Nass said. “This is huge.”
Nass further noted 25% of 250 myocarditis cases were still symptomatic at three months, and only 74% of cases were designated by cardiologists as definitely resolved at 3 months.
As it pertains to safety, some who testified during a public comment period, as well as other commentators, questioned whether the study used by the FDA to grant Emergency Use Authorization is large enough to assure parents that the vaccine is safe in young children.
“The bottom line is getting COVID, I think, is much riskier to the heart than getting this vaccine,” said Dr. Matthew Oster, a pediatric cardiologist at Children’s Hospital of Atlanta.
Dr. Tom Shimabukuro covered vaccine safety monitoring from the CDC’s surveillance system in children. Shimabukuro said COVID is getting the “most intensive vaccine monitoring program in history,” yet he did not go into detail on surveillance data.
Acknowledging that some parents are hesitant about vaccinating their children right away, Dr. Matthew Daley, a member of the ACIP said, “we hear you loud and clear and of course you only want what’s best for your child. I encourage you to talk to your family physician or pediatrician, they can walk through this with you.”
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
The EU is not revealing the details of its contracts with vaccine makers. Why?
By Robert Bridge | RT | November 3, 2021
As some Europeans continue to resist mandatory vaccine measures, a group of parliamentarians have upbraided the Commission for allowing pharmaceutical companies to ‘run roughshod over democracy.’
One of the most important lessons people learn early in life is to never plunk down hard-earned cash on a product before reading all of the fine print contained in the contract. ‘Caveat emptor,’ as every subject of the Roman Empire instinctively understood.
Yet, it seems that few bureaucrats in Brussels have purchased a new home, used car or some newfangled device lately, because that’s exactly what these bumbling fools have done. In an effort to ‘protect the health of their constituents,’ they bought millions of batches of Covid vaccines from various pharmaceutical companies without letting lawmakers sneak a peek at the contracts.
As it turns out, entire pages of these documents – the few that have been made public, that is – have been heavily redacted. This has raised more than one eyebrow in the European Union, and perhaps none more conspicuously than that of Romanian MEP Cristian Terhes.
At the weekend, Terhes appeared at a press conference in Brussels with several other EU lawmakers at this side, all visibly shaken by the news that they would be required to produce, starting on November 3, a digital ‘green pass’ to gain entry into Parliament. Like many EU citizens, these lawmakers have declined to get the vaccine not because they are ‘anti-vaxxers’ but because they have been denied critical information regarding the product and procedures. Now they will be refused entry into Parliament, the place where the will of their people is (supposedly) represented.
Terhes revealed that, back in January, EU lawmakers were demanding “full access to the contracts signed between these companies that produce the vaccines and the European Union.” To say the parliamentarians were disappointed would be a gross understatement.
The Romanian MEP, who represents the Christian-Democratic National Peasants Party, quoted from a Euractiv article that reported: “The contract, signed between pharmaceutical company CureVac and the European Commission in November, was made available to MEPs [on January 12, 2021] in a redacted format after the company agreed to open the contract up to scrutiny.”
That is really putting the cart before the horse, for how can something that has been so grossly redacted be opened up to scrutiny? Terhes railed that Brussels is “imposing a medical product on European citizens without them knowing what’s in these contracts.” That’s simply inexcusable and should be easily struck down by even a third-rate lawyer.
More astonishing is that not even the EU members of Parliament know the details of the agreements.
To prove his point, the Romanian MEP held up individual pages of the CureVac contract, each one heavily redacted like some kind of imitation of artist Kazimir Malevich’s ‘Black Square.’ It doesn’t get any less concerning when we drill down to which parts of the contract were blacked out. According to an analysis conducted by Euractiv, “4.22% of the liability section and 15.38% of the indemnification section was found to be redacted, while 0% of the section on the processing of personal data was redacted.”
Meanwhile, the contract’s annexes, which delve into the nitty-gritty details of the agreement, were redacted by some 61%. In total, almost 24% of the contract was hidden. Now ask yourself this simple question: Would you sign up for a home mortgage if it was discovered that one-quarter of the agreement was missing? I’ll crawl out on a limb and guess ‘no.’ Nor would anyone think you were ‘anti-mortgage’ or ‘mortgage hesitant’ if you did so.
The truth is that you, and millions of other rational people exactly like you, are simply ‘pro-transparency.’ Yet these medical consumers are being treated like second-class citizens for simply wanting more information before they agree to be injected with something. ‘My body, my choice’ is a battle cry that no longer applies, as millions of people are quickly discovering, in the current authoritarian climate.
Keep in mind that it is on the basis of these contracts that Europeans must come to a decision, based on “informed consent,” that they will ‘voluntarily’ take the jab so as not to be ostracized from polite society. Unless they agree to take one of the available vaccines, citizens of the EU face potentially being denied the right to work, enter a store, buy medicine, take their children to school and freely travel from one country to another.
Naturally, this makes the stakes for not taking the jab incredibly high, but that only makes it worse that details are being deliberately withheld from the public. It is no secret that the pharmaceutical giants enjoy full indemnity in the event that an individual suffers death or injury after receiving a Covid shot. And although such unfortunate occurrences appear to be rare, even Pfizer-BioNTech, which has been granted approval to extend vaccinations to 12 to 15-year-olds in the EU, seems uncertain as to what the long-term effects of the vaccines may be.
“Additional adverse reactions, some of which may be serious, may become apparent with more widespread use of the Pfizer-BioNTech Covid-19 Vaccine,” it clearly states on its website.
In February, the Bureau of Investigative Journalism released a damning report on Pfizer, saying negotiators for the drug company had behaved in a “bullying” manner with several Latin American countries. In Argentina they demanded “additional indemnity” against civilians seeking legal compensation after suffering adverse effects from their vaccines. In the agreements, Pfizer takes great care to ensure that all financial responsibility for compensating citizens injured from the inoculations is that of the respective government.
The company also enjoys the protection of non-disclosure agreements with many of its nation clients, including the European Commission and the US government. With regards to the EU, Brussels is forbidden from disclosing information that would be “material to Pfizer without the consent of Pfizer,” Public Citizen reported.
In fact, CureVac was being quite generous with the EU Commission, considering it was the only pharmaceutical company that agreed to release its contract to the light of day. Of course there wasn’t much to inspect with all of the redactions, but beggars can’t be choosers, right?
In light of the steady pressure bearing down on Brussels, much of it happening behind closed doors, the European Commission has obliquely admitted – almost one year too late, and after the rights and freedoms of European citizens have been crushed underfoot – that they failed to use good judgment when ramming through these emergency vaccines.
Last week, in an overwhelmingly passed resolution (458 in favor, 149 against and 86 abstaining), the EU Parliament demanded legislation that would make “the process of researching, purchasing and distributing Covid-19 vaccines more transparent, stating:
“This would enable MEPs to effectively scrutinize EU vaccine policies. At the same time, the Commission should be discussing these policies more openly with citizens.”
This shocking statement by the EU Parliament shows how little respect Brussels had for democratic principles when it was negotiating with the vaccine makers, who have, incidentally, reaped a windfall from the pandemic. The parliamentarians, who are coming under fire at home, demanded that “the Commission discloses who negotiates vaccine purchases on its behalf. It should publish purchase agreements made with vaccine suppliers, including details of public investments and vaccine costs, and publicise any potential breaches of contract.”
Then, in what comes off as the understatement of the century, the MEPs are of the opinion that “more information could help counter vaccine hesitancy and disinformation, and pharmaceutical companies should also release extensive clinical trial data and reports.”
Oh, you think so?
The following question is not an idle one: Why are MEPs ONLY NOW talking about the total lack of transparency and democracy that occurred between the EU Commission and Big Pharma? A more cynical person would be tempted to say it’s because the draconian vaccine mandates have finally reached the very door of Parliament, where the power brokers find themselves locked out of their offices, much like thousands of people on the street. Welcome to the club.
In any case, the fact that Brussels has withheld the details of its agreements with the vaccine makers for almost a year, while at the same time casually destroying the civil liberties of its citizens, totally disqualifies them from punishing those people who are ‘hesitant’ about receiving the vaccine. ‘Informed consent’ is essential to any functioning democracy, and Europeans were clearly denied that right. Do the right thing, Brussels, and release these heavy chains from your people. The world is watching.
Robert Bridge is an American writer and journalist. He is the author of ‘Midnight in the American Empire,’ How Corporations and Their Political Servants are Destroying the American Dream.
What is the Number Needed to Vaccinate to prevent a single COVID fatality in kids 5 to 11 based on Pfizer’s EUA application?
And what are the risks that go along with injecting that many kids?
By Toby Rogers | October 31, 2021
Number Needed to Vaccinate (NNTV), the standard policy tool that Pharma, the FDA, & CDC no longer want to talk about
A funny thing happened this afternoon. Not funny as in “haha”. More like funny as in, “ohhhhh that’s how the FDA rigs the process.”
I was reading the CDC’s “Guidance for Health Economics Studies Presented to the Advisory Committee on Immunization Practices (ACIP), 2019 Update” and I realized that the FDA’s woeful risk-benefit analysis in connection with Pfizer’s EUA application to jab children ages 5 to 11 violates many of the principles of the CDC’s Guidance document. The CDC “Guidance” document describes 21 things that every health economics study in connection with vaccines must do and the FDA risk-benefit analysis violated at least half of them.
Today I want to focus on a single factor: the Number Needed to Vaccinate (NNTV). In four separate places the CDC Guidance document mentions the importance of coming up with a Number Needed to Vaccinate (NNTV). I did not recall seeing an NNTV in the FDA risk-benefit document. So I checked the FDA’s risk-benefit analysis again and sure enough, there was no mention of an NNTV.
Because the FDA failed to provide an NNTV, I will attempt to provide it here.
First a little background. The Number Needed to Treat (NNT) in order to prevent a single case, hospitalization, ICU admission, or death, is a standard way to measure the effectiveness of any drug. It’s an important tool because it enables policymakers to evaluate tradeoffs between a new drug, a different existing drug, or doing nothing. In vaccine research the equivalent term is Number Needed to Vaccinate (NNTV, sometimes also written as NNV) in order to prevent a single case, hospitalization, ICU admission, or death (those are 4 different NNTVs that one could calculate).
Pharma HATES talking about NNTV and they hate talking about NNTV even more when it comes to COVID-19 vaccines because the NNTV is so ridiculously high that this vaccine could not pass any honest risk-benefit analysis.
Indeed about a year ago I innocently asked on Twitter what the NNTV is for coronavirus vaccines.

Pharma sent a swarm of trolls in to attack me and Pharma goons published hit pieces on me outside of Twitter to punish me for even asking the question. Of course none of the Pharma trolls provided an estimate of the NNTV for COVID-19 shots. That tells us that we are exactly over the target.
Various health economists have calculated a NNTV for COVID-19 vaccines.
- Ronald Brown, a health economist in Canada, estimated that the NNTV to prevent a single case of coronavirus is from 88 to 142.
- Others have calculated the NNTV to prevent a single case at 256.
- German and Dutch researchers, using a large (500k) data set from a field study in Israel calculated an NNTV between 200 and 700 to prevent one case of COVID-19 for the mRNA shot marketed by Pfizer. They went further and figured out that the “NNTV to prevent one death is between 9,000 and 100,000 (95% confidence interval), with 16,000 as a point estimate.”
You can see why Pharma hates this number so much (I can picture Pharma’s various PR firms sending out an “All hands on deck!” message right now to tell their trolls to attack this article). One would have to inject a lot of people to see any benefit and the more people who are injected the more the potential benefits are offset by the considerable side-effects from the shots.
Furthermore, the NNTV to prevent a single case is not a very meaningful measure because most people, particularly children, recover on their own (or even more quickly with ivermectin if treated early). The numbers that health policy makers should really want to know are the NNTV to prevent a single hospitalization, ICU admission, or death. But with the NNTV to prevent a single case already so high, and with significant adverse events from coronavirus vaccines averaging about 15% nationwide, Pharma and the FDA dare not calculate an NNTV for hospitalizations, ICU, and deaths, because then no one would ever take this product (bye bye $93 billion in annual revenue).
Increased all cause mortality in the Pfizer clinical trial of adults
As Bobby Kennedy noted in personal correspondence with me, Pfizer’s clinical trial in adults showed alarming increases in all cause mortality in the vaccinated :
In Pfizer’s 6 month clinical trial in adults — there was 1 covid death our of 22,000 in the vaccine (“treatment”) group and 2 Covid deaths out of 22,000 in the placebo group (see Table s4). So NNTV = 22,000. The catch is there were 5 heart attack deaths in the vaccine group and only 1 in placebo group. So for every 1 life saved from Covid, the Pfizer vaccine kills 4 from heart attacks. All cause mortality in the 6 month study was 20 in vaccine group and 14 in placebo group. So a 42% all cause mortality increase among the vaccinated. The vaccine loses practically all efficacy after 6 months so they had to curtail the study. They unblinded and offered the vaccine to the placebo group. At that point the rising harm line had long ago intersected the sinking efficacy line.
Former NY Times investigative reporter Alex Berenson also wrote about the bad outcomes for the vaccinated in the Pfizer clinical trial in adults (here). Berenson received a lifetime ban from Twitter for posting Pfizer’s own clinical trial data.
Pfizer learned their lesson with the adult trial and so when they conducted a trial of their mRNA vaccine in children ages 5 to 11 they intentionally made it too small (only 2,300 participants) and too short (only followed up for 2 months) in order to hide harms.
Estimating an NNTV in children ages 5 to 11 using Pfizer’s own clinical trial data
All of the NNTV estimates above are based on data from adults. In kids the NNTV will be even higher (the lower the risk, the higher the NNTV to prevent a single bad outcome). Children ages 5 to 11 are at extremely low risk of death from coronavirus. In a meta-analysis combining data from 5 studies, Stanford researchers Cathrine Axfors and John Ioannidis found a median infection fatality rate (IFR) of 0.0027% in children ages 0-19. In children ages 5 to 11 the IFR is even lower. Depending on the study one looks at, COVID-19 is slightly less dangerous or roughly equivalent to the flu in children.
So how many children would need to be injected with Pharma’s mRNA shot in order to prevent a single hospitalization, ICU admission, or death?
Let’s examine Pfizer’s EUA application and the FDA’s risk-benefit analysis. By Pfizer’s own admission, there were zero hospitalization, ICU admissions, or deaths, in the treatment or control group in their study of 2,300 children ages 5 to 11.
So the Number Needed to Vaccinate in order to prevent a single hospitalization, ICU admission, or death, according to Pfizer’s own data, is infinity. ∞. Not the good kind of infinity as in God or love or time or the universe. This is the bad kind of infinity as in you could vaccinate every child age 5 to 11 in the U.S. and not prevent a single hospitalization, ICU admission, or death from coronavirus according to Pfizer’s own clinical trial data as submitted to the FDA. Of course Pfizer likes this kind of infinity because it means infinite profits. [Technically speaking the result is “undefined” because mathematically one cannot divide by zero, but you get my point.]
Estimating an NNTV and risk-benefit model in children ages 5 to 11 using the limited data that are available
Everyone knows that Pfizer was not even trying to conduct a responsible clinical trial of their mRNA shot in kids ages 5 to 11. Pfizer could have submitted to the FDA a paper napkin with the words “Iz Gud!” written in crayon and the VRBPAC would have approved the shot. They are all in the cartel together and they are all looking forward to their massive payoff/payday.
But let’s not be like Pharma. Instead, let’s attempt to come up with a best guess estimate based on real world data. Over time, others will develop a much more sophisticated estimate (for example, Walach, Klement, & Aukema, 2021 estimated an NNTV for 3 different populations based on “days post dose”). But for our purposes here I think there is a much easier way to come up with a ballpark NNTV estimate for children ages 5 to 11.
Here’s the benefits model:
- As of October 30, 2021, the CDC stated that 170 children ages 5 to 11 have died of COVID-19-related illness since the start of the pandemic. (That represents less than 0.1% of all coronavirus-related deaths nationwide even though children that age make up 8.7% of the U.S. population).
- The Pfizer mRNA shot only “works” for about 6 months (it increases risk in the first month, provides moderate protection in months 2 through 4 and then effectiveness begins to wane, which is why all of the FDA modeling only used a 6 month time-frame). So any modeling would have to be based on vaccine effectiveness in connection with the 57 (170/3) children who might otherwise have died of COVID-related illness during a 6-month period.
- At best, the Pfizer mRNA shot might be 80% effective against hospitalizations and death. That number comes directly from the FDA modeling (p. 32). I am bending over backwards to give Pfizer the benefit of considerable doubt because again, the Pfizer clinical trial showed NO reduction in hospitalizations or death in this age group. So injecting all 28,384,878 children ages 5 to 11 with two doses of Pfizer (which is what the Biden administration wants to do) would save, at most, 45 lives (0.8 effectiveness x 57 fatalities that otherwise would have occurred during that time period = 45).
- So then the NNTV to prevent a single fatality in this age group is 630,775 (28,384,878 / 45). But it’s a two dose regimen so if one wants to calculate the NNTV per injection the number doubles to 1,261,550. It’s literally the worst NNTV in the history of vaccination.
If you inject that many children, you certainly will have lots and lots of serious side effects including disability and death. So let’s look at the risk side of the equation.
Here’s the risk model:
- Because the Pfizer clinical trial has no useable data, I have to immuno-bridge from the nearest age group.
- 31,761,099 people (so just about 10% more people than in the 5 to 11 age bracket) ages 12 to 24 have gotten at least one coronavirus shot.
- The COVID-19 vaccine program has only existed for 10 months and younger people have only had access more recently (children 12 to 15 have had access for five months; since May 10) — so we’re looking at roughly the same observational time period as modeled above.
- During that time, there are 128 reports of fatal side effects following coronavirus mRNA injections in people 12 to 24. (That’s through October 22, 2021. There is a reporting lag though so the actual number of reports that have been filed is surely higher).
- Kirsch, Rose, and Crawford (2021) estimate that VAERS undercounts fatal reactions by a factor of 41 which would put the total fatal side effects in this age-range at 5,248. (Kirsch et al. represents a conservative estimate because others have put the underreporting factor at 100.)
- With potentially deadly side effects including myo- and pericarditis disproportionately impacting youth it is reasonable to think that over time the rate of fatal side effects from mRNA shots in children ages 5 to 11 might be similar to those in ages 12 to 24.
So, to put it simply, the Biden administration plan would kill 5,248 children via Pfizer mRNA shots in order to save 45 children from dying of coronavirus.
For every one child saved by the shot, another 117 would be killed by the shot.
The Pfizer mRNA shot fails any honest risk-benefit analysis in children ages 5 to 11.
Even under the best circumstances, estimating NNTV and modeling risk vs. benefits is fraught. In the current situation, with a new and novel bioengineered virus, where Pfizer’s data are intentionally underpowered to hide harms, and the FDA, CDC, & Biden Administration are doing everything in their power to push dangerous drugs on kids, making good policy decisions is even more difficult.
If the FDA or CDC want to calculate a different NNTV (and explain how they arrived at that number) I’m all ears. But we all know that the FDA refused to calculate an NNTV not because they forgot, but because they knew the number was so high that it would destroy the case for mRNA vaccines in children this age. Your move CDC — your own Guidance document states that you must provide this number.
The Vaccines Cannot Do What Is Asked of Them
eugyppius | November 1, 2021
Increasingly, politicians and medical bureaucrats are entranced by a bizarre pandemic ideology. Like most ideologies, it remains oblivious to evidence and argument, holding that the risk of severe outcomes from Corona infection is far more evenly distributed across the population than it is; and allowing only universal solutions, such as quarantining and vaccinating entire populations. These obtuse views, which just won’t go away, are at the root of our failed and destructive policies. For 20 months now, this pandemic ideology has blinded everyone in charge to the possibility of shielding the vulnerable, leveraging seasonal patterns in infection, and leaving the kids alone. The stratified nature of Corona risk is the key to unravelling the pandemic, and it’s the one thing nobody will recognise.
Success in the pandemic has come to be defined by a series of vague, poorly differentiated statistics, including above all Corona infections, hospitalisations and deaths, and now vaccination rates. In their exclusive focus on these numbers, the press propagate constantly the myth that this is all there is to know about Corona. This impoverished discussion drives bureaucrats and politicians to seek solutions for one vague meaningless metric (Corona ICU admissions) in another vague meaningless metric (vaccination rates). In this way their policies are constructed in a rhetorical world that has very little to do with what is actually happening.
Every day our understanding of what the vaccines can do becomes clearer. It’s not nothing, but it’s much less than we were promised.
Some of our best evidence so far comes from this Swedish retrospective cohort study, which tracks outcomes in 1,684,958 individuals (matched vaccinated and unvaccinated pairs) from 12 January to 4 October 2021. It has been around the block, with an especially good analysis by El Gato Malo, so there’s no point in anything more than a brief review here.
Above all, they find that the vaccines provide temporary protection against infection:

Unfortunately, this protection likely falls below zero – into the zone of negative efficacy – after 7 to 9 months. This is one of multiple lines of evidence confirming that the vaccinated, sooner or later, achieve higher rates of infection than the unvaccinated. According to me, even early vaccine efficacy is likely overstated in studies like these. Probably the vaccinated are always highly vulnerable to infection, but they’re not tested as rigorously and at first their symptoms are so mild as to be nearly unnoticeable. SARS-2 nevertheless lurks among them, mostly undetected, until vaccine protection against overt disease dissipates.
This would explain what happened in Iceland over the summer: A bunch of freshly vaccinated Icelanders went on holiday in the UK, where they promptly picked up SARS-2 and brought the latest Delta update back home with them. In the following weeks, energetic Icelandic testing uncovered rates of infection almost as high in the vaccinated as in the unvaccinated – and this well before we would’ve expected the vaccines to have faded.
The Swedish study finds that efficacy against severe disease last longer, but also decays substantially in much the same way:
After the 240-day mark, protection against severe outcome is not even at 30%. The decay is most rapid among men, the old and frail, and those with comorbidities – precisely those subpopulations already at greatest risk of severe disease.
So those are the benefits, but as in everything there are also costs – and here they turn out to be substantial.
We’ve already touched on one: The vaccines appear to induce negative efficacy against infection. This probably arises from a combination of minimally symptomatic super-spreading among the vaccinated, the selective pressure that vaccine-elicited antibodies place upon the virus, and the narrow immunity against an obsolete arrangement of the spike protein that the vaccines confer. For a period of several weeks after dose 1 (and likely dose 3), they also make the vaccinated more susceptible to infection, and mass vaccination campaigns have induced case spikes across many countries.
By now it is also clear that the vaccines cause a range of adverse reactions. The best documented is myocarditis in young men, a side effect observed most frequently after dose 2 of the mRNA vaccines. We probably won’t know the true rate of vaccine-induced myocarditis for many years. From excess mortality in younger cohorts and many anecdotal media reports, we can surmise that it is much more common than anybody will admit.
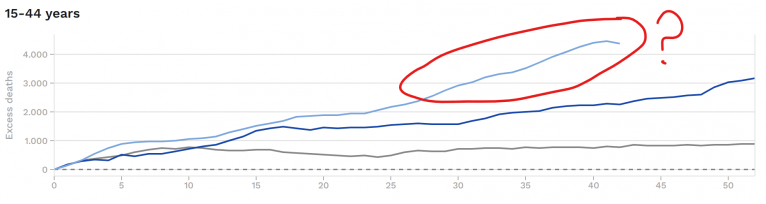
It does not take a Ph.D. in public health to extract a sensible vaccination policy from all this:
1. There is just no question that vaccinating low-risk cohorts (including the recovered) is not only pointless, but also dangerous. These aren’t the people who end up in the hospital dying of Corona anyway. And because the vaccinated sooner or later end up driving transmission, there is only downside and no upside here.
2. All the vaccines are good for, is reducing the likelihood of severe disease among the old and the vulnerable. It follows that only the old and the vulnerable should be vaccinated.
3. In these groups, carefully timed annual vaccinations, like flu shots, might well provide good protection at the height of the winter coronavirus season and limit mortality. Even here, though, you’d have to proceed carefully, to avoid causing case spikes in the newly vaccinated during that brief period where their vulnerability to infection is heightened.
Of course, this is the opposite of what our pandemic ideology permits. Instead, almost all of our governments deploy the vaccines in the most reckless and counterproductive ways possible.
The southern districts of Bavaria are quickly becoming the regions of highest infection in Germany, and Markus Söder, our governor, is demanding a renewed “vaccine push,” including a campaign for booster doses “independently of age,” even obliquely threatening lockdown if we can’t ensure the “safety and stability” of hospitals.
These are exactly the kinds of crackpot universalist solutions that have failed for the past twenty months, and that will do nothing to unburden our healthcare facilities, and very likely end up swamping them with unnecessary patients.
If booster doses are a good idea for anyone – and it’s far from clear they are – it’s frail nursing home residents, most of whose vaccinations are now well past their expiration date, and who are once again beginning to die of SARS-2 just as they did last fall. Vaccinating children and triple vaccinating low-risk adults won’t prevent nursing home deaths, and it will do very little to keep our hospitals “safe,” because the vaccines don’t reduce spread and these people rarely end up in hospital. What is worse, ever newer pushes to vaccinate all hospital personnel and nursing home staff threaten to introduce vaccinated super-spreaders into these sensitive environments. Söder will continue to pound the table demanding ever harsher restrictions for the unvaccinated and more vaccine doses for the already-vaccinated, all while deaths and hospitalisations continue to climb.
Ultimately, the great problem with our vaccine policies, as with our lockdowns, arises from the fact that they don’t work. Because lockdowns and vaccination campaigns are powerless to remove the conditions that brought them about, you can never stop locking down, and you can never stop vaccinating – even as your policies turn out to do worse than nothing.
Blood Clots Associated with Johnson & Johnson COVID Shot
By Dr. Joseph Mercola | November 2, 2021
Researchers at Mayo Clinic have published a study in JAMA showing that there is a 3.5 times higher risk of getting brain blood clots if you take the Astra Zeneca or Johnson & Johnson COVID-19 shots.
Reported incidents of cerebral venous sinus thrombosis (CVST) after the jabs were what instigated a temporary pause in their rollout in April 2021. The researchers used data from the CDC’s Vaccine Adverse Event Reporting System (VAERS) to compare to data compiled in a Minnesota county from 2001 to 2015.
Study authors said women appeared to be more affected than men, although they couldn’t ascertain why. “Most CVST events occurred within 15 days after vaccination, which is likely the highest at-risk period,” they added. ‘The postvaccination CVST rate among females was higher than the prepandemic rate among females. The highest risk was among women aged 30 to 49 years.”
Featured Video

Seyed M. Marandi: US-Iran War Inevitable: Kuwait and Bahrain May Fall
or go to
Aletho News Archives – Video-Images
From the Archives
USS Liberty Massacre: A Pivotal Moment in the Hostile Takeover of America
By Kevin Barrett | Crescent | Dhu al-Qa’dah 24, 1445
In corporate America, hostile takeovers are commonplace. They occur when an aggressor—a larger corporation or rich individuals—seizes control of a smaller corporation without asking permission.
What few recognize is that the United States itself has been subjected to a hostile takeover. Since the aggressor, the illegitimate settler colony known as “Israel,” is much smaller than the US, the takeover has necessarily been surreptitious.
As of June, 2024, Israel’s gradual takeover of the US has become obvious and undeniable—a proverbial “elephant in the living room.” … continue
Blog Roll
 Aletho News
- Seyed M. Marandi: US-Iran War Inevitable: Kuwait and Bahrain May Fall
- Leaders Condemn Ansarallah Attack on Saudi Arabia While Ignoring Illegal War Against Yemen
- Leaked: Britain’s Covert Iraqi Psyops Network
- Yemeni Armed Forces Warn Airlines Against Using Saudi Airports, Exempt Mecca and Medina
- Iran security chief says powers greater than US tried to conquer Iran but ended in ‘dustbin of history’
- Europe’s mounting social chaos… chickens coming home to roost for proxy war against Russia
- US-Russia Diesel Deal Becomes Massive Defeat for Ukraine
- Hormuz and the Looming Economic Catastrophe
- Dhubab offensive, media blitz and the rapid unraveling of Saudi-backed coalition’s new gambit
- Putin Conveys to Trump Iran’s Vision on Possible Conflict Resolution – Kremlin
- If Americans Knew
- Gaza: Ceasefire Anniversary Marks Year of Failed Promises
- The American Conservative: Mike Huckabee Should Resign
- A C-Section in Shackles: A Palestinian Woman’s Harrowing Birth in Israeli Detention
- ‘He’s Desperate’: AIPAC Begins Spending Against Abdul El-Sayed to Boost Mike Rogers:
- Trump, Hormuz, and the Looming Economic Catastrophe
- For three years, Israel has killed a child in Gaza every 71 minutes – Daily Update
- Israeli forces kill another child in Gaza – Daily Update
- Gaza ceasefire exists in name only, say more than 100 organizations
- Nearly 2 Million in Gaza Need Urgent Shelter Assistance as Winter Looms: IOM Chief Warns
- Suppressing Palestinian resistance: US charity under fire for AI monitoring of Gaza classrooms
- No Tricks Zone
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI

