CDC Advisors Unanimously Endorse Pfizer’s COVID Vaccine for Kids 5-11 Despite Expert Concerns Over Clinical Data
By Megan Redshaw | The Defender | November 2, 2021
The Centers for Disease Control and Prevention’s (CDC) vaccine advisory panel today unanimously recommended Pfizer’s COVID vaccine for children 5 to 11, despite concerns raised during the meeting about Pfizer’s clinical data, the fact that children who previously acquired natural immunity to COVID were included in clinical trials and evidence showing COVID poses little risk to children.
If Dr. Rochelle Walensky, the CDC’s director signs off on the decision, children ages 5 through 11 could start receiving COVID vaccines as early as tonight.
The younger age group will receive one-third of the dose authorized for those 12 and older in two shots at least three weeks apart. The doses will be delivered by smaller needles and stored in smaller vials to avoid a mix-up with adult doses.
The CDC’s guidelines for the vaccine’s use are not legally binding, but heavily influence the medical community’s practice.
Prior to today’s decision by the CDC’s Advisory Committee on Immunization Practices (ACIP) the Biden administration enlisted more than 20,000 pediatricians, family doctors and pharmacies to administer the vaccines — with 15 million doses already packed with dry ice, loaded into small specialized containers and shipped via airplanes and trucks to vaccination sites across the country, federal officials said on Monday.
Walensky sent a clear signal during the ACIP meeting about where she stands, CNN reported. “We have been asking when we will be able to expand this protection to our younger children,” Walensky said in opening comments to the committee.
“As you review the data today, it will be key to keep in mind the specific risks to children from this virus and the pandemic, and to put that risk into context of other vaccine-preventable diseases,” Walensky said.
Walensky noted that children are routinely vaccinated against diseases like chickenpox — which results in far fewer hospitalizations and deaths in children compared to COVID.
During today’s meeting, ACIP members reviewed and discussed the science behind the U.S. Food and Drug Administration’s (FDA) authorization last week of Pfizer’s COVID vaccine in all children 5-11 years old.
That authorization was based mostly on a Pfizer-BioNTech study of 4,600 children worldwide, of whom approximately 3,100 got the low-dose vaccine and about 1,500 got a placebo.
These studies showed the vaccine is about 91% effective against COVID. The immune system response to the vaccine, as measured by antibodies, was comparable to the response seen in 16- to 25-year-olds, NPR reported.
During the meeting, the CDC said 745 children under 18 have died of COVID since the beginning of the pandemic — although the COVID-19 team admitted 79% were confirmed to be hospitalized for COVID, while the rest were hospital admissions for other causes.
“The chance that a child will have severe COVID, require hospitalization or develop a long-term complication like MIS-C [multisystem inflammatory syndrome] remains low, but still the risk is too high and too devastating to our children, and far higher than for many other diseases for which we vaccinate children,” Walensky said.
Efficacy of Pfizer’s COVID vaccine in children
The CDC said Pfizer’s COVID vaccine was 90.9% effective against symptomatic COVID and none of the adverse events experienced during clinical trials were assessed by “the investigator” as related to the vaccine.
To determine the efficacy of the Pfizer-BioNTech COVID vaccine, Pfizer measured the blood of 264 children for antibodies.
“There were 3,000 vaccinated children in the trial. Why isn’t blood from the other 2,700-plus being measured for antibodies?” asked Dr. Meryl Nass, a member of the Children’s Health Defense Scientific Advisory Panel.
“Pfizer never explains why, when they have an important clinical trial in which over 3,000 children were injected in this age group, only a subset of less than 10% were used to assess efficacy,” Nass said.
Nass explained:
“Pfizer claims three cases of COVID in the vaccinated group versus 16 in the placebo group show efficacy of the vaccine. But the FDA did not accept this claim. Note that all cases were mild, none hospitalized or died. So are they planning to vaccinate 28 million kids to prevent colds?”
Nass noted Pfizer also enrolled kids who had prior evidence of having had COVID in the clinical trial, “which should never have been allowed.”
“Of the kids who were already immune at the start of the trials, none developed COVID,” Nass said. “About 150 kids in the placebo group were recovered and none got COVID.”
Nass said kids with preceding COVID infection did not have their antibody levels checked after the first dose, as Pfizer stated they did not collect the data because they “tried to minimize blood draws in children.”
“The real reason they did not want to collect data is because it might support the fact that kids who already had COVID might only need one vaccine dose, or none at all,” Nass said.
During the brief public comment session, Patricia Neuenschwander, a registered nurse noted there was no prevention of hospitalization, death or multisystem inflammatory syndrome in children — a condition being used to justify vaccinating younger children against COVID, despite numerous cases of MIS-C having been reported after receipt of a COVID vaccine.
Neuenschwander reminded the ACIP that vaccinations do not prevent infection or transmission. It is a mild illness in the vast majority of children, she said, and prior immunity is being ignored — the expansion group was only followed for 17 days.
David Wiseman, a research scientist with a background in pharmacy, pharmacology and experimental pathology, asked the CDC panel why the efficacy study was not validated by the FDA, and why Pfizer changed the buffer [see page 14] in the vaccine but did not test it in animals or kids — planning to use an untested version of the vaccine in 5 to 11-year-olds.
Wiseman said the FDA abandoned its responsibility, and he asked if the ACIP would do the same.
Myocarditis and COVID in 5- to 11-year-olds
One side effect that generated considerable discussion at today’s meeting was myocarditis — a form of heart inflammation.
The CDC said 1,640 cases of myocarditis have been reported to the CDC’s Vaccine Adverse Event Reporting System in people under age 30 after having received a COVID vaccine, but only 877 met the CDC’s case definition.
The CDC said there were nine reported deaths in people with myocarditis, but then the agency reduced the number to three, with two cases pending evaluation and one case without adequate information.
“I have to say that it is beyond belief that CDC could whittle down 877 cases reported in young people to three actual cases. Where did the rest go?” Nass asked.
“According to the CDC’s Vaccine Safety Datalink, 7 of 16 12- to 17-year-olds with myocarditis were still on exercise restriction three months after diagnosis — that is 44% could not exercise three months later,” Nass said. “This is huge.”
Nass further noted 25% of 250 myocarditis cases were still symptomatic at three months, and only 74% of cases were designated by cardiologists as definitely resolved at 3 months.
As it pertains to safety, some who testified during a public comment period, as well as other commentators, questioned whether the study used by the FDA to grant Emergency Use Authorization is large enough to assure parents that the vaccine is safe in young children.
“The bottom line is getting COVID, I think, is much riskier to the heart than getting this vaccine,” said Dr. Matthew Oster, a pediatric cardiologist at Children’s Hospital of Atlanta.
Dr. Tom Shimabukuro covered vaccine safety monitoring from the CDC’s surveillance system in children. Shimabukuro said COVID is getting the “most intensive vaccine monitoring program in history,” yet he did not go into detail on surveillance data.
Acknowledging that some parents are hesitant about vaccinating their children right away, Dr. Matthew Daley, a member of the ACIP said, “we hear you loud and clear and of course you only want what’s best for your child. I encourage you to talk to your family physician or pediatrician, they can walk through this with you.”
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
The EU is not revealing the details of its contracts with vaccine makers. Why?
By Robert Bridge | RT | November 3, 2021
As some Europeans continue to resist mandatory vaccine measures, a group of parliamentarians have upbraided the Commission for allowing pharmaceutical companies to ‘run roughshod over democracy.’
One of the most important lessons people learn early in life is to never plunk down hard-earned cash on a product before reading all of the fine print contained in the contract. ‘Caveat emptor,’ as every subject of the Roman Empire instinctively understood.
Yet, it seems that few bureaucrats in Brussels have purchased a new home, used car or some newfangled device lately, because that’s exactly what these bumbling fools have done. In an effort to ‘protect the health of their constituents,’ they bought millions of batches of Covid vaccines from various pharmaceutical companies without letting lawmakers sneak a peek at the contracts.
As it turns out, entire pages of these documents – the few that have been made public, that is – have been heavily redacted. This has raised more than one eyebrow in the European Union, and perhaps none more conspicuously than that of Romanian MEP Cristian Terhes.
At the weekend, Terhes appeared at a press conference in Brussels with several other EU lawmakers at this side, all visibly shaken by the news that they would be required to produce, starting on November 3, a digital ‘green pass’ to gain entry into Parliament. Like many EU citizens, these lawmakers have declined to get the vaccine not because they are ‘anti-vaxxers’ but because they have been denied critical information regarding the product and procedures. Now they will be refused entry into Parliament, the place where the will of their people is (supposedly) represented.
Terhes revealed that, back in January, EU lawmakers were demanding “full access to the contracts signed between these companies that produce the vaccines and the European Union.” To say the parliamentarians were disappointed would be a gross understatement.
The Romanian MEP, who represents the Christian-Democratic National Peasants Party, quoted from a Euractiv article that reported: “The contract, signed between pharmaceutical company CureVac and the European Commission in November, was made available to MEPs [on January 12, 2021] in a redacted format after the company agreed to open the contract up to scrutiny.”
That is really putting the cart before the horse, for how can something that has been so grossly redacted be opened up to scrutiny? Terhes railed that Brussels is “imposing a medical product on European citizens without them knowing what’s in these contracts.” That’s simply inexcusable and should be easily struck down by even a third-rate lawyer.
More astonishing is that not even the EU members of Parliament know the details of the agreements.
To prove his point, the Romanian MEP held up individual pages of the CureVac contract, each one heavily redacted like some kind of imitation of artist Kazimir Malevich’s ‘Black Square.’ It doesn’t get any less concerning when we drill down to which parts of the contract were blacked out. According to an analysis conducted by Euractiv, “4.22% of the liability section and 15.38% of the indemnification section was found to be redacted, while 0% of the section on the processing of personal data was redacted.”
Meanwhile, the contract’s annexes, which delve into the nitty-gritty details of the agreement, were redacted by some 61%. In total, almost 24% of the contract was hidden. Now ask yourself this simple question: Would you sign up for a home mortgage if it was discovered that one-quarter of the agreement was missing? I’ll crawl out on a limb and guess ‘no.’ Nor would anyone think you were ‘anti-mortgage’ or ‘mortgage hesitant’ if you did so.
The truth is that you, and millions of other rational people exactly like you, are simply ‘pro-transparency.’ Yet these medical consumers are being treated like second-class citizens for simply wanting more information before they agree to be injected with something. ‘My body, my choice’ is a battle cry that no longer applies, as millions of people are quickly discovering, in the current authoritarian climate.
Keep in mind that it is on the basis of these contracts that Europeans must come to a decision, based on “informed consent,” that they will ‘voluntarily’ take the jab so as not to be ostracized from polite society. Unless they agree to take one of the available vaccines, citizens of the EU face potentially being denied the right to work, enter a store, buy medicine, take their children to school and freely travel from one country to another.
Naturally, this makes the stakes for not taking the jab incredibly high, but that only makes it worse that details are being deliberately withheld from the public. It is no secret that the pharmaceutical giants enjoy full indemnity in the event that an individual suffers death or injury after receiving a Covid shot. And although such unfortunate occurrences appear to be rare, even Pfizer-BioNTech, which has been granted approval to extend vaccinations to 12 to 15-year-olds in the EU, seems uncertain as to what the long-term effects of the vaccines may be.
“Additional adverse reactions, some of which may be serious, may become apparent with more widespread use of the Pfizer-BioNTech Covid-19 Vaccine,” it clearly states on its website.
In February, the Bureau of Investigative Journalism released a damning report on Pfizer, saying negotiators for the drug company had behaved in a “bullying” manner with several Latin American countries. In Argentina they demanded “additional indemnity” against civilians seeking legal compensation after suffering adverse effects from their vaccines. In the agreements, Pfizer takes great care to ensure that all financial responsibility for compensating citizens injured from the inoculations is that of the respective government.
The company also enjoys the protection of non-disclosure agreements with many of its nation clients, including the European Commission and the US government. With regards to the EU, Brussels is forbidden from disclosing information that would be “material to Pfizer without the consent of Pfizer,” Public Citizen reported.
In fact, CureVac was being quite generous with the EU Commission, considering it was the only pharmaceutical company that agreed to release its contract to the light of day. Of course there wasn’t much to inspect with all of the redactions, but beggars can’t be choosers, right?
In light of the steady pressure bearing down on Brussels, much of it happening behind closed doors, the European Commission has obliquely admitted – almost one year too late, and after the rights and freedoms of European citizens have been crushed underfoot – that they failed to use good judgment when ramming through these emergency vaccines.
Last week, in an overwhelmingly passed resolution (458 in favor, 149 against and 86 abstaining), the EU Parliament demanded legislation that would make “the process of researching, purchasing and distributing Covid-19 vaccines more transparent, stating:
“This would enable MEPs to effectively scrutinize EU vaccine policies. At the same time, the Commission should be discussing these policies more openly with citizens.”
This shocking statement by the EU Parliament shows how little respect Brussels had for democratic principles when it was negotiating with the vaccine makers, who have, incidentally, reaped a windfall from the pandemic. The parliamentarians, who are coming under fire at home, demanded that “the Commission discloses who negotiates vaccine purchases on its behalf. It should publish purchase agreements made with vaccine suppliers, including details of public investments and vaccine costs, and publicise any potential breaches of contract.”
Then, in what comes off as the understatement of the century, the MEPs are of the opinion that “more information could help counter vaccine hesitancy and disinformation, and pharmaceutical companies should also release extensive clinical trial data and reports.”
Oh, you think so?
The following question is not an idle one: Why are MEPs ONLY NOW talking about the total lack of transparency and democracy that occurred between the EU Commission and Big Pharma? A more cynical person would be tempted to say it’s because the draconian vaccine mandates have finally reached the very door of Parliament, where the power brokers find themselves locked out of their offices, much like thousands of people on the street. Welcome to the club.
In any case, the fact that Brussels has withheld the details of its agreements with the vaccine makers for almost a year, while at the same time casually destroying the civil liberties of its citizens, totally disqualifies them from punishing those people who are ‘hesitant’ about receiving the vaccine. ‘Informed consent’ is essential to any functioning democracy, and Europeans were clearly denied that right. Do the right thing, Brussels, and release these heavy chains from your people. The world is watching.
Robert Bridge is an American writer and journalist. He is the author of ‘Midnight in the American Empire,’ How Corporations and Their Political Servants are Destroying the American Dream.
What is the Number Needed to Vaccinate to prevent a single COVID fatality in kids 5 to 11 based on Pfizer’s EUA application?
And what are the risks that go along with injecting that many kids?
By Toby Rogers | October 31, 2021
Number Needed to Vaccinate (NNTV), the standard policy tool that Pharma, the FDA, & CDC no longer want to talk about
A funny thing happened this afternoon. Not funny as in “haha”. More like funny as in, “ohhhhh that’s how the FDA rigs the process.”
I was reading the CDC’s “Guidance for Health Economics Studies Presented to the Advisory Committee on Immunization Practices (ACIP), 2019 Update” and I realized that the FDA’s woeful risk-benefit analysis in connection with Pfizer’s EUA application to jab children ages 5 to 11 violates many of the principles of the CDC’s Guidance document. The CDC “Guidance” document describes 21 things that every health economics study in connection with vaccines must do and the FDA risk-benefit analysis violated at least half of them.
Today I want to focus on a single factor: the Number Needed to Vaccinate (NNTV). In four separate places the CDC Guidance document mentions the importance of coming up with a Number Needed to Vaccinate (NNTV). I did not recall seeing an NNTV in the FDA risk-benefit document. So I checked the FDA’s risk-benefit analysis again and sure enough, there was no mention of an NNTV.
Because the FDA failed to provide an NNTV, I will attempt to provide it here.
First a little background. The Number Needed to Treat (NNT) in order to prevent a single case, hospitalization, ICU admission, or death, is a standard way to measure the effectiveness of any drug. It’s an important tool because it enables policymakers to evaluate tradeoffs between a new drug, a different existing drug, or doing nothing. In vaccine research the equivalent term is Number Needed to Vaccinate (NNTV, sometimes also written as NNV) in order to prevent a single case, hospitalization, ICU admission, or death (those are 4 different NNTVs that one could calculate).
Pharma HATES talking about NNTV and they hate talking about NNTV even more when it comes to COVID-19 vaccines because the NNTV is so ridiculously high that this vaccine could not pass any honest risk-benefit analysis.
Indeed about a year ago I innocently asked on Twitter what the NNTV is for coronavirus vaccines.

Pharma sent a swarm of trolls in to attack me and Pharma goons published hit pieces on me outside of Twitter to punish me for even asking the question. Of course none of the Pharma trolls provided an estimate of the NNTV for COVID-19 shots. That tells us that we are exactly over the target.
Various health economists have calculated a NNTV for COVID-19 vaccines.
- Ronald Brown, a health economist in Canada, estimated that the NNTV to prevent a single case of coronavirus is from 88 to 142.
- Others have calculated the NNTV to prevent a single case at 256.
- German and Dutch researchers, using a large (500k) data set from a field study in Israel calculated an NNTV between 200 and 700 to prevent one case of COVID-19 for the mRNA shot marketed by Pfizer. They went further and figured out that the “NNTV to prevent one death is between 9,000 and 100,000 (95% confidence interval), with 16,000 as a point estimate.”
You can see why Pharma hates this number so much (I can picture Pharma’s various PR firms sending out an “All hands on deck!” message right now to tell their trolls to attack this article). One would have to inject a lot of people to see any benefit and the more people who are injected the more the potential benefits are offset by the considerable side-effects from the shots.
Furthermore, the NNTV to prevent a single case is not a very meaningful measure because most people, particularly children, recover on their own (or even more quickly with ivermectin if treated early). The numbers that health policy makers should really want to know are the NNTV to prevent a single hospitalization, ICU admission, or death. But with the NNTV to prevent a single case already so high, and with significant adverse events from coronavirus vaccines averaging about 15% nationwide, Pharma and the FDA dare not calculate an NNTV for hospitalizations, ICU, and deaths, because then no one would ever take this product (bye bye $93 billion in annual revenue).
Increased all cause mortality in the Pfizer clinical trial of adults
As Bobby Kennedy noted in personal correspondence with me, Pfizer’s clinical trial in adults showed alarming increases in all cause mortality in the vaccinated :
In Pfizer’s 6 month clinical trial in adults — there was 1 covid death our of 22,000 in the vaccine (“treatment”) group and 2 Covid deaths out of 22,000 in the placebo group (see Table s4). So NNTV = 22,000. The catch is there were 5 heart attack deaths in the vaccine group and only 1 in placebo group. So for every 1 life saved from Covid, the Pfizer vaccine kills 4 from heart attacks. All cause mortality in the 6 month study was 20 in vaccine group and 14 in placebo group. So a 42% all cause mortality increase among the vaccinated. The vaccine loses practically all efficacy after 6 months so they had to curtail the study. They unblinded and offered the vaccine to the placebo group. At that point the rising harm line had long ago intersected the sinking efficacy line.
Former NY Times investigative reporter Alex Berenson also wrote about the bad outcomes for the vaccinated in the Pfizer clinical trial in adults (here). Berenson received a lifetime ban from Twitter for posting Pfizer’s own clinical trial data.
Pfizer learned their lesson with the adult trial and so when they conducted a trial of their mRNA vaccine in children ages 5 to 11 they intentionally made it too small (only 2,300 participants) and too short (only followed up for 2 months) in order to hide harms.
Estimating an NNTV in children ages 5 to 11 using Pfizer’s own clinical trial data
All of the NNTV estimates above are based on data from adults. In kids the NNTV will be even higher (the lower the risk, the higher the NNTV to prevent a single bad outcome). Children ages 5 to 11 are at extremely low risk of death from coronavirus. In a meta-analysis combining data from 5 studies, Stanford researchers Cathrine Axfors and John Ioannidis found a median infection fatality rate (IFR) of 0.0027% in children ages 0-19. In children ages 5 to 11 the IFR is even lower. Depending on the study one looks at, COVID-19 is slightly less dangerous or roughly equivalent to the flu in children.
So how many children would need to be injected with Pharma’s mRNA shot in order to prevent a single hospitalization, ICU admission, or death?
Let’s examine Pfizer’s EUA application and the FDA’s risk-benefit analysis. By Pfizer’s own admission, there were zero hospitalization, ICU admissions, or deaths, in the treatment or control group in their study of 2,300 children ages 5 to 11.
So the Number Needed to Vaccinate in order to prevent a single hospitalization, ICU admission, or death, according to Pfizer’s own data, is infinity. ∞. Not the good kind of infinity as in God or love or time or the universe. This is the bad kind of infinity as in you could vaccinate every child age 5 to 11 in the U.S. and not prevent a single hospitalization, ICU admission, or death from coronavirus according to Pfizer’s own clinical trial data as submitted to the FDA. Of course Pfizer likes this kind of infinity because it means infinite profits. [Technically speaking the result is “undefined” because mathematically one cannot divide by zero, but you get my point.]
Estimating an NNTV and risk-benefit model in children ages 5 to 11 using the limited data that are available
Everyone knows that Pfizer was not even trying to conduct a responsible clinical trial of their mRNA shot in kids ages 5 to 11. Pfizer could have submitted to the FDA a paper napkin with the words “Iz Gud!” written in crayon and the VRBPAC would have approved the shot. They are all in the cartel together and they are all looking forward to their massive payoff/payday.
But let’s not be like Pharma. Instead, let’s attempt to come up with a best guess estimate based on real world data. Over time, others will develop a much more sophisticated estimate (for example, Walach, Klement, & Aukema, 2021 estimated an NNTV for 3 different populations based on “days post dose”). But for our purposes here I think there is a much easier way to come up with a ballpark NNTV estimate for children ages 5 to 11.
Here’s the benefits model:
- As of October 30, 2021, the CDC stated that 170 children ages 5 to 11 have died of COVID-19-related illness since the start of the pandemic. (That represents less than 0.1% of all coronavirus-related deaths nationwide even though children that age make up 8.7% of the U.S. population).
- The Pfizer mRNA shot only “works” for about 6 months (it increases risk in the first month, provides moderate protection in months 2 through 4 and then effectiveness begins to wane, which is why all of the FDA modeling only used a 6 month time-frame). So any modeling would have to be based on vaccine effectiveness in connection with the 57 (170/3) children who might otherwise have died of COVID-related illness during a 6-month period.
- At best, the Pfizer mRNA shot might be 80% effective against hospitalizations and death. That number comes directly from the FDA modeling (p. 32). I am bending over backwards to give Pfizer the benefit of considerable doubt because again, the Pfizer clinical trial showed NO reduction in hospitalizations or death in this age group. So injecting all 28,384,878 children ages 5 to 11 with two doses of Pfizer (which is what the Biden administration wants to do) would save, at most, 45 lives (0.8 effectiveness x 57 fatalities that otherwise would have occurred during that time period = 45).
- So then the NNTV to prevent a single fatality in this age group is 630,775 (28,384,878 / 45). But it’s a two dose regimen so if one wants to calculate the NNTV per injection the number doubles to 1,261,550. It’s literally the worst NNTV in the history of vaccination.
If you inject that many children, you certainly will have lots and lots of serious side effects including disability and death. So let’s look at the risk side of the equation.
Here’s the risk model:
- Because the Pfizer clinical trial has no useable data, I have to immuno-bridge from the nearest age group.
- 31,761,099 people (so just about 10% more people than in the 5 to 11 age bracket) ages 12 to 24 have gotten at least one coronavirus shot.
- The COVID-19 vaccine program has only existed for 10 months and younger people have only had access more recently (children 12 to 15 have had access for five months; since May 10) — so we’re looking at roughly the same observational time period as modeled above.
- During that time, there are 128 reports of fatal side effects following coronavirus mRNA injections in people 12 to 24. (That’s through October 22, 2021. There is a reporting lag though so the actual number of reports that have been filed is surely higher).
- Kirsch, Rose, and Crawford (2021) estimate that VAERS undercounts fatal reactions by a factor of 41 which would put the total fatal side effects in this age-range at 5,248. (Kirsch et al. represents a conservative estimate because others have put the underreporting factor at 100.)
- With potentially deadly side effects including myo- and pericarditis disproportionately impacting youth it is reasonable to think that over time the rate of fatal side effects from mRNA shots in children ages 5 to 11 might be similar to those in ages 12 to 24.
So, to put it simply, the Biden administration plan would kill 5,248 children via Pfizer mRNA shots in order to save 45 children from dying of coronavirus.
For every one child saved by the shot, another 117 would be killed by the shot.
The Pfizer mRNA shot fails any honest risk-benefit analysis in children ages 5 to 11.
Even under the best circumstances, estimating NNTV and modeling risk vs. benefits is fraught. In the current situation, with a new and novel bioengineered virus, where Pfizer’s data are intentionally underpowered to hide harms, and the FDA, CDC, & Biden Administration are doing everything in their power to push dangerous drugs on kids, making good policy decisions is even more difficult.
If the FDA or CDC want to calculate a different NNTV (and explain how they arrived at that number) I’m all ears. But we all know that the FDA refused to calculate an NNTV not because they forgot, but because they knew the number was so high that it would destroy the case for mRNA vaccines in children this age. Your move CDC — your own Guidance document states that you must provide this number.
The Vaccines Cannot Do What Is Asked of Them
eugyppius | November 1, 2021
Increasingly, politicians and medical bureaucrats are entranced by a bizarre pandemic ideology. Like most ideologies, it remains oblivious to evidence and argument, holding that the risk of severe outcomes from Corona infection is far more evenly distributed across the population than it is; and allowing only universal solutions, such as quarantining and vaccinating entire populations. These obtuse views, which just won’t go away, are at the root of our failed and destructive policies. For 20 months now, this pandemic ideology has blinded everyone in charge to the possibility of shielding the vulnerable, leveraging seasonal patterns in infection, and leaving the kids alone. The stratified nature of Corona risk is the key to unravelling the pandemic, and it’s the one thing nobody will recognise.
Success in the pandemic has come to be defined by a series of vague, poorly differentiated statistics, including above all Corona infections, hospitalisations and deaths, and now vaccination rates. In their exclusive focus on these numbers, the press propagate constantly the myth that this is all there is to know about Corona. This impoverished discussion drives bureaucrats and politicians to seek solutions for one vague meaningless metric (Corona ICU admissions) in another vague meaningless metric (vaccination rates). In this way their policies are constructed in a rhetorical world that has very little to do with what is actually happening.
Every day our understanding of what the vaccines can do becomes clearer. It’s not nothing, but it’s much less than we were promised.
Some of our best evidence so far comes from this Swedish retrospective cohort study, which tracks outcomes in 1,684,958 individuals (matched vaccinated and unvaccinated pairs) from 12 January to 4 October 2021. It has been around the block, with an especially good analysis by El Gato Malo, so there’s no point in anything more than a brief review here.
Above all, they find that the vaccines provide temporary protection against infection:

Unfortunately, this protection likely falls below zero – into the zone of negative efficacy – after 7 to 9 months. This is one of multiple lines of evidence confirming that the vaccinated, sooner or later, achieve higher rates of infection than the unvaccinated. According to me, even early vaccine efficacy is likely overstated in studies like these. Probably the vaccinated are always highly vulnerable to infection, but they’re not tested as rigorously and at first their symptoms are so mild as to be nearly unnoticeable. SARS-2 nevertheless lurks among them, mostly undetected, until vaccine protection against overt disease dissipates.
This would explain what happened in Iceland over the summer: A bunch of freshly vaccinated Icelanders went on holiday in the UK, where they promptly picked up SARS-2 and brought the latest Delta update back home with them. In the following weeks, energetic Icelandic testing uncovered rates of infection almost as high in the vaccinated as in the unvaccinated – and this well before we would’ve expected the vaccines to have faded.
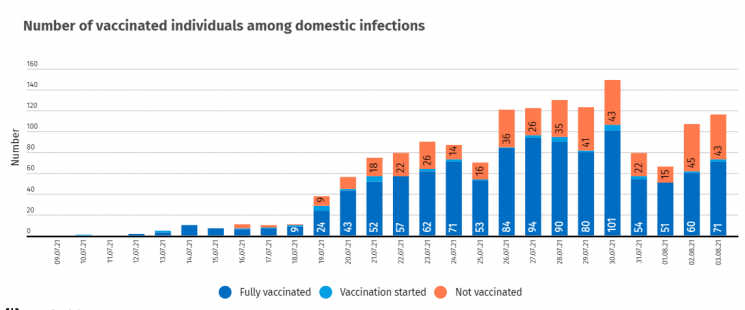
The Swedish study finds that efficacy against severe disease last longer, but also decays substantially in much the same way:
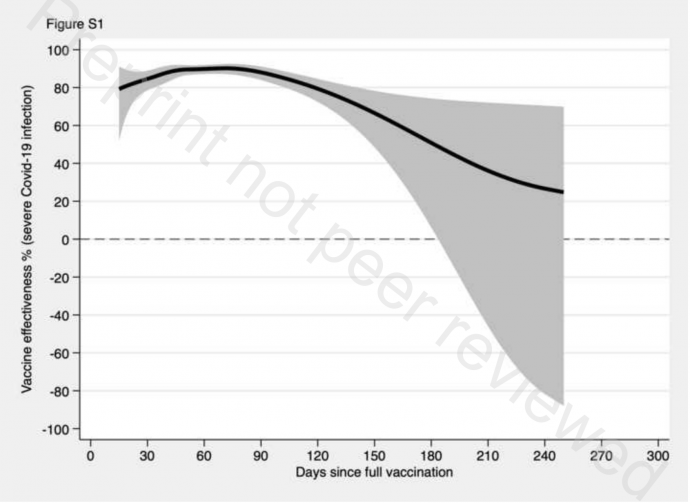
After the 240-day mark, protection against severe outcome is not even at 30%. The decay is most rapid among men, the old and frail, and those with comorbidities – precisely those subpopulations already at greatest risk of severe disease.
So those are the benefits, but as in everything there are also costs – and here they turn out to be substantial.
We’ve already touched on one: The vaccines appear to induce negative efficacy against infection. This probably arises from a combination of minimally symptomatic super-spreading among the vaccinated, the selective pressure that vaccine-elicited antibodies place upon the virus, and the narrow immunity against an obsolete arrangement of the spike protein that the vaccines confer. For a period of several weeks after dose 1 (and likely dose 3), they also make the vaccinated more susceptible to infection, and mass vaccination campaigns have induced case spikes across many countries.
By now it is also clear that the vaccines cause a range of adverse reactions. The best documented is myocarditis in young men, a side effect observed most frequently after dose 2 of the mRNA vaccines. We probably won’t know the true rate of vaccine-induced myocarditis for many years. From excess mortality in younger cohorts and many anecdotal media reports, we can surmise that it is much more common than anybody will admit.
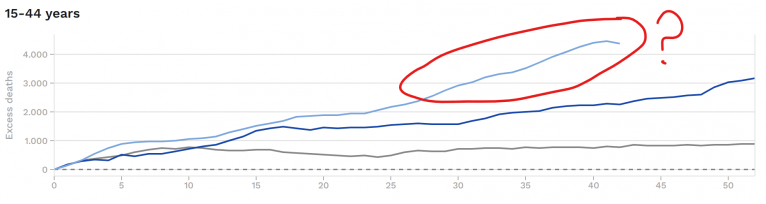
It does not take a Ph.D. in public health to extract a sensible vaccination policy from all this:
1. There is just no question that vaccinating low-risk cohorts (including the recovered) is not only pointless, but also dangerous. These aren’t the people who end up in the hospital dying of Corona anyway. And because the vaccinated sooner or later end up driving transmission, there is only downside and no upside here.
2. All the vaccines are good for, is reducing the likelihood of severe disease among the old and the vulnerable. It follows that only the old and the vulnerable should be vaccinated.
3. In these groups, carefully timed annual vaccinations, like flu shots, might well provide good protection at the height of the winter coronavirus season and limit mortality. Even here, though, you’d have to proceed carefully, to avoid causing case spikes in the newly vaccinated during that brief period where their vulnerability to infection is heightened.
Of course, this is the opposite of what our pandemic ideology permits. Instead, almost all of our governments deploy the vaccines in the most reckless and counterproductive ways possible.
The southern districts of Bavaria are quickly becoming the regions of highest infection in Germany, and Markus Söder, our governor, is demanding a renewed “vaccine push,” including a campaign for booster doses “independently of age,” even obliquely threatening lockdown if we can’t ensure the “safety and stability” of hospitals.
These are exactly the kinds of crackpot universalist solutions that have failed for the past twenty months, and that will do nothing to unburden our healthcare facilities, and very likely end up swamping them with unnecessary patients.
If booster doses are a good idea for anyone – and it’s far from clear they are – it’s frail nursing home residents, most of whose vaccinations are now well past their expiration date, and who are once again beginning to die of SARS-2 just as they did last fall. Vaccinating children and triple vaccinating low-risk adults won’t prevent nursing home deaths, and it will do very little to keep our hospitals “safe,” because the vaccines don’t reduce spread and these people rarely end up in hospital. What is worse, ever newer pushes to vaccinate all hospital personnel and nursing home staff threaten to introduce vaccinated super-spreaders into these sensitive environments. Söder will continue to pound the table demanding ever harsher restrictions for the unvaccinated and more vaccine doses for the already-vaccinated, all while deaths and hospitalisations continue to climb.
Ultimately, the great problem with our vaccine policies, as with our lockdowns, arises from the fact that they don’t work. Because lockdowns and vaccination campaigns are powerless to remove the conditions that brought them about, you can never stop locking down, and you can never stop vaccinating – even as your policies turn out to do worse than nothing.
Blood Clots Associated with Johnson & Johnson COVID Shot
By Dr. Joseph Mercola | November 2, 2021
Researchers at Mayo Clinic have published a study in JAMA showing that there is a 3.5 times higher risk of getting brain blood clots if you take the Astra Zeneca or Johnson & Johnson COVID-19 shots.
Reported incidents of cerebral venous sinus thrombosis (CVST) after the jabs were what instigated a temporary pause in their rollout in April 2021. The researchers used data from the CDC’s Vaccine Adverse Event Reporting System (VAERS) to compare to data compiled in a Minnesota county from 2001 to 2015.
Study authors said women appeared to be more affected than men, although they couldn’t ascertain why. “Most CVST events occurred within 15 days after vaccination, which is likely the highest at-risk period,” they added. ‘The postvaccination CVST rate among females was higher than the prepandemic rate among females. The highest risk was among women aged 30 to 49 years.”
FDA approves Pfizer jab for kids, but even they don’t seem sure it’s safe
By Helen Buyniski | RT | November 1, 2021
American children have no choice but to act as experimental test subjects for the Pfizer Covid-19 vaccine to determine the jab’s safety, the Food and Drug Administration has apparently concluded. Good luck, kids!
“We’re never going to learn about how safe the vaccine is unless we start giving it,” editor of the New England Journal of Medicine and Harvard adjunct professor Eric Rubin argued last week, his words buried within the eight-hour barrage of presentations and discussions that swirled around the FDA advisory panel’s approval of the mRNA jab for children aged five to 11.
The FDA followed up on the advisory panel’s 17-0 recommendation with approval, as it typically does, on Friday. If the Centers for Disease Control and Prevention follows suit, some 28 million American children will be quickly served up as fresh-faced fodder for a smaller dose of the Covid-19 vaccine already poised to inject some 100 million American adults. That is, as soon as President Joe Biden is able to whip up a legally-binding demand he can submit to the Occupational Safety and Health Administration.
Friday’s FDA approval means only the CDC stands between American children and a warp-speed rollout of the Pfizer jab. However, the rush to approval doesn’t necessarily mean there are no concerns. A disturbingly large portion of the FDA committee’s members are connected to Pfizer in some way or another, leading vaccine skeptics to cry foul. Meanwhile, a growing portion of the country continues to denounce the mandates in general, insisting everyone should be able to make their own decision regarding whether or not they wish to get injected.
Echoing the newly-reanimated pro-choice slogan, mandate protesters recently swarmed the Brooklyn Bridge declaring ‘My body, my choice’ as New York City employees faced the potential loss of their jobs as firefighters, police officers, sanitation handlers, and corrections officers due to Mayor Bill de Blasio’s insistence that all municipal employees get vaxxed or be relegated to the purgatory of open-ended unpaid leave.
The FDA’s effort to put the cart so far in front of the horse mirrored the words of House Speaker Nancy Pelosi during the congressional tug-of-war over Obamacare in 2010. Faced with a phonebook-sized, dubiously-legal bill unlike anything Congress had passed before and no realistic timeframe to wrangle with the details, Pelosi suggested Congress would have to “pass the bill to find out what’s in it, away from the fog of controversy.”
Since then, legislation by brute force has only grown as the means by which laws are passed in the US, as ever-more-polarized parties refuse to give an inch and betray the appearance of weakness. Allowing the ‘other side’ to be seen as achieving even the slightest victory is unconscionable, and that framework remains in place in the vaccination arena – where it makes less sense than anywhere else.
After all, it was former President Donald Trump’s Operation Warp Speed that brought the world the Pfizer shot, even if the jab itself wasn’t rolled out until shortly (some would say deliberately) after the 2020 election and vaccine mandates have since become a cause celebre of the Democratic Party.
With half the US up in arms about the other half’s supposed refusal to roll up its sleeves and submit to an intensely politicized needle, anyone who hesitates is denounced posthaste in a 21st-century witch hunt – to be fired, if not set on fire; outfitted with the scarlet A for anti-vaxxer, not adulteress; and otherwise chased out of the public square – deplatformed from Twitter, YouTube and Facebook, if not chased physically with pitchforks and torches. Similar divisions have erupted across Europe, and countries like Italy and France have pushed the issue even further, barring the unvaccinated from so much as entering grocery stores to buy food.
While the US study of the Pfizer vaccine’s effects on children five to 11 failed to turn up any deadly side effects, critics argued its population size was too small to be effective for such a purpose. Parents of some jab recipients have observed disturbing symptoms in their offspring in the hours and days following the shots and filmed heartbreaking testimonials describing their downfall from healthy children to pain-wracked perma-patients experiencing near-constant seizures, facial distortions, debilitating heart problems, or other dire health issues.
Another doctor on the FDA committee, Michael Kurilla of the National Institutes of Health, abstained from voting on recommending Pfizer-BioNTech’s vaccine entirely, citing a lack of evidence that all children need the shot, and while Kurilla, an infectious disease and pathology expert, was the only panel member to abstain from voting, he was not the only member to openly express misgivings about doling out the jab to young Americans. His colleague, Dr. Cody Meissner of Tufts University, suggested that it would be an “error” to mandate the jab for children to return to school until there was more hard data.
“We simply don’t know what the side effects are going to be,” he said, acknowledging the shot – like its adult equivalent – probably wouldn’t prevent transmission of the virus. While he was not opposed to administering the shot to certain vulnerable subgroups inside the 5-11 age group, Meissner was concerned approving the shot for everyone in that category would lead to a heavy-handed mandate the likes of which is currently being wielded against American adults.
Children who receive the Pfizer-BioNTech jab may actually get less immunity and face more risk than supplied by getting and recovering from a current strain of Covid-19, Kurilla told the Daily Mail, referring to the Delta variant and other current strains of Covid-19 circulating among the population. “The question really becomes, does this vaccine offer any benefits to them at all?” he asked rhetorically during the FDA committee meeting. He would have voted ‘yes’ if the FDA had merely proposed opening up access to the vaccine to a ‘subset’ of those ages five to 11, but he disagreed with administering it to all children within that age group.
Two other panel members voted to approve despite their misgivings. Meissner argued that a “very small percent of otherwise healthy six-to-11-year-old children…might derive some benefit,” while President and CEO of Meharry Medical College James Hildreth agreed that “vaccinating all of the children…seems a bit much for me,” pointing to the relatively low risk of hospitalization and near-zero risk of death by Covid-19 for children.
Speaking up against the jab, even circumstantially, has become the kiss of death in the medical community, with even medical rock stars like Robert Malone, one of the inventors of mRNA as a drug, cast into the dustbin of history for expressing skepticism that his invention was being incorrectly used to deliver the Covid-19 vaccine.
However, governments worldwide are setting themselves up for civil war as populations are forced to choose one ‘side’ or another. Even many of the vaccinated have acknowledged that the jab should not be forced on anyone, while entire industries like shipping, air travel, defense, and the like grind to a halt as mandates run up against the stubborn will of their employees. Southwest Airlines was allegedly forced to cancel thousands of flights earlier this month, due to a reported mass ‘sickout’ by air traffic controllers unwilling to get vaxxed, though the airline itself has denied this, and rumors of trucker strikes from Australia to America have food sellers panicking at the thought of empty shelves.
As it stands, parents who were willing to submit themselves to experimental shots in the name of convenience and retaining employment may not be so willing to offer up their children as sacrifices to a company once denounced by the US Justice Department as the worst fraudster in the pharmaceutical industry.
Governments that have shown themselves as profoundly untrustworthy throughout the Covid-19 pandemic are unlikely to change their behavior at the last minute, and parents are wise to take care in where they place their trust.
Media Kinda-Sorta Forgets to Mention Doctor’s $2 Million From Pfizer

By Dr. Joseph Mercola | November 02, 2021
A Canadian doctor pushing COVID-19 vaccine shots for children ages 5 years and up who’s been featured in numerous media reports received nearly $2 million in Pfizer funding for vaccine research.
Whether it was intentional or if the media kinda-sorta forgot to mention the conflict, or if they simply didn’t bother doing their own research before using Dr. Jim Kellner as a lead adviser on the COVID shot isn’t clear. But what is clear is that Pfizer has given the University of Calgary professor and pediatrician $1.9 million, with $787,004 of it still being allocated until 2022.
Kellner didn’t attempt to hide his conflict of interest; it’s easily found in his publicly posted curriculum vitae, with the current funding explicitly stated.
Yet, according to True North news, “Kellner’s name turns up over 41 times and appears in numerous videos and articles on the topic of vaccination without any indication of how much money he has received from the vaccine manufacturer Pfizer.”
100% of Covid-19 Vaccine Deaths were caused by just 5% of the batches produced: Official Government data
THE EXPOSÉ • OCTOBER 31, 2021
An investigation of data found in the USA’s Vaccine Adverse Event Reporting System (VAERS) has revealed that extremely high numbers of adverse reactions and deaths have been reported against specific lot numbers of the Covid-19 vaccines several times, meaning deadly batches of the experimental injections have now been identified.
But what’s perhaps more concerning is that the “deadly” lots were distributed widely across the United States whilst other “benign” lots were sent to just a few locations.
The data used in the investigation was pulled from the publicly accessible VAERS database which can be viewed here. The Vaccine Adverse Event Reporting System (VAERS) is a United States programme for vaccine safety, co-managed by the U.S. Centers for Disease Control and Prevention (CDC) and the Food and Drug Administration (FDA).
The programme collects information via reports made by doctors, nurses, and patients about adverse events (possible harmful side effects) that occur after administration of vaccines to ascertain whether the risk–benefit ratio is high enough to justify continued use of any particular vaccine.
The reports pulled from the database were ones that had been submitted up to October 15th 2021 and they included all adverse reactions reported against the Pfizer and Moderna mRNA Covid-19 injections, as well as all adverse reactions reported against the influenza vaccines; which were used to generate a control dataset .

The VAERS database showed a total of 1,608 adverse event reports against the flu vaccines alongside 15 deaths and 73 hospitalisations. The total count of lot numbers returned was 494.
The ‘lot number’ is a specific string of numbers and letters that tracks a specific batch of vaccine from production and into a persons arm and it is usually found on a vaccine label or accompanying packaging.

The above chart shows the number of adverse event report made to VAERS against the influenza vaccines sorted by the lot number of vaccine that was administered prior to the adverse event.
Except for a few spikes the number of adverse events per lot number was generally the same, with no more than 26 reports being made against a single lot number of influenza vaccine.

The above charts shows the count of lots by number of reports of adverse reactions per lot for the influenza vaccines. It shows that 33% of the lots (165 / 494) only had a single adverse reaction report made against them, whilst just 0.6% of the lots (3 / 494) had at least 20 adverse reaction reports made against them.

The above chart shows how many times a specific lot number was identified in an adverse reaction report of which the person had died following vaccination against the Flu. Ninety-seven-percent of the lots (480 / 494) were associated with zero deaths, whilst 13 lots were associated with a single death and 1 lot was associated with 2 deaths.

The above chart shows the number of states within the USA a specific log number of the influenza vaccine was distributed to.
The VAERS data shows that 44% of the lots (219 / 494) were sent to just a single state within the USA, whilst a further 17% (86 / 494) were sent to 2 states, 10% (50 / 494) were sent to 3 states, 5% (24 / 494) were sent to 4 states, 3% (17 / 494) were sent to 5 states, 2% (11 / 494) were sent to 6 states, and just 0.4 (2 / 494) were sent to 12 states within the USA.
All of the above data was then used as a control dataset to compare against VAERS data for the Pfizer and Moderna mRNA Covid-19 vaccines.

The VAERS database showed a total of 171,463 adverse event reports against the Pfizer Covid-19 vaccine alongside 2,828 deaths and 14,262 hospitalisations. The total count of lot numbers returned was 4,522.
This data alone shows that there have been 106 times as many adverse reactions, 189 times as many deaths, and 195 times as many hospitalisations due to the Pfizer Covid-19 jab than there have been due to all other influenza vaccines combined.

The above chart shows the number of adverse event reports made to VAERS against the Pfizer Covid-19 vaccine sorted by the lot number of vaccine that was administered prior to the adverse event. We do not have reliable information about standard lot size, but news articles indicate an average lot size of 1000 vials (approx. 6000 doses).
The highest number of adverse event reports made to VAERS against a single lot number of the influenza vaccine was 26. Which makes it all the more shocking to discover that the highest number of adverse event reports made to VAERS against a single lot number of the Pfizer Covid-19 vaccine up to October 15th 2021 was 3,563, and this isn’t an anomaly.
Thousands of adverse event reports have been made against a single lot number of the Pfizer Covid-19 vaccine numerous times, and unfortunately the Moderna Covid-19 vaccine hasn’t fared any better.

The VAERS database showed a total of 188,998 adverse event reports against the Moderna Covid-19 vaccine alongside 2,603 deaths and 10,225 hospitalisations. The total count of lot numbers returned was 5,510.
This data alone shows that there have been 118 times as many adverse reactions, 174 times as many deaths, and 140 times as many hospitalisations due to the Moderna Covid-19 jab than there have been due to all other influenza vaccines combined.

The above chart shows the number of adverse event reports made to VAERS against the Moderna Covid-19 vaccine sorted by the lot number of vaccine that was administered prior to the adverse event, and it shows that the Moderna jab fared even worse than the Pfizer jab in this department with the highest number of adverse event reports against a single lot number of Moderna Covid-19 vaccine totalling a staggering 4,967.

The above chart shows the count of lots against the range of adverse events reported per lot of Pfizer Covid-19 vaccine. The data reveals that 2,908 lots (64%) had just a single adverse event report made against them, whilst 2 specific lots had over 3000 adverse event reports made against them.
Shockingly we can also see from the data that 30 lots of Pfizer vaccine had between 1,000 and 1,499 adverse event reports per lot, another 20 lots had between 1,500 and 1,999 adverse event reports per lot, and another 23 lots had between 2,000 and 2,499 adverse event reports per lot.
This suggests that there were a small quantity of dangerous batches of the Pfizer Covid-19 vaccine and a large quantity of seemingly harmless (at least in the short term) batches of the Pfizer Covid-19 vaccine.

But the investigation of VAERS data also revealed that reported deaths due to the Pfizer vaccine were again only associated with certain batches of the jab. The chart above shows that 96% of the lots of Pfizer vaccine had zero death reports made against them. Meaning the 2,828 reported deaths were associated with just 4% of the lots of Pfizer vaccine.
Five lot numbers were associated with 61-80 deaths each, a further 5 lot numbers were associated with 81-100 deaths each, and just 2 separate lot numbers were associated with over 100 deaths each.

The same can be seen for the Moderna Covid-19 vaccine. Ninety-five-percent of the lots of Moderna vaccine had zero death reports made against them. Meaning the 2,603 deaths were associated with just 5% of the lots of Moderna vaccine.
Thirteen lot numbers were associated with 41-60 deaths each, 2 lot numbers were associated with 61-80 deaths each and 1 lot number was associated with 81-100 deaths.
The investigation of VAERS data also found that specific batches of the pfizer and Moderna Covid-19 vaccines which were distributed to between 13 and 50 states across the USA had an unusually high number of adverse event reports and deaths compared to lots that were distributed to 12 states or less across the USA

As you can see from the above table 4,289 different lots of Pfizer vaccine were distributed to 12 states or less across the USA, recording 9,141 adverse event reports against them alongside 99 deaths and 657 hospitalisations. This equates to an average of 2 adverse event reports per lot and 0 deaths and hospitalisations.
However, a further 130 different lots of Pfizer vaccine were distributed to between 13-50 states across the USA, recording 166,170 adverse event reports, 2,799 deaths, and 14,155 hospitalisations. This equates to an average of 1,278 adverse event reports per lot number, alongside 22 deaths and 109 hospitalisations.
This data therefore shows that each lot from the 130 different lot numbers of Pfizer Covid-19 vaccine distributed to more than 13 states, harmed on average 639 times more people, hospitalised on average 109 times more people, and killed on average 22 times more people.

The above chart on the left shows the number of adverse event reports by lot number sent to 13 or more states across the USA. This chart has identified the actual lot numbers of Pfizer vaccine that have caused the most harm in the USA. The most harmful of which is lot number ‘EK9231’; causing over 3,500 adverse event reports.

The above chart on the left shows the number of deaths reported as adverse reactions to the Pfizer vaccine by lot number sent to 13+ states across the USA. This chart has identified the actual lot numbers of Pfizer vaccine that have caused the most deaths in the USA. The deadliest of which is lot number ‘EN6201’ causing almost 120 deaths.

The above chart on the left shows the number of adverse event reports against the Moderna vaccine by lot number sent to 13 or more states across the USA. This chart has identified the actual lot numbers of Moderna vaccine that have caused the most harm in the USA. The most harmful of which is lot number ‘039K20A’; causing over 4,000 adverse event reports.
The second most harmful batch of Moderna vaccine was assigned lot number ‘041L20A’, and media reports show that it was actually recalled by the Orange County Healthcare Agency in January 2021 following reports of allergic reactions.


The above chart on the left shows the number of deaths reported as adverse reactions to the Moderna vaccine by lot number sent to 13+ states across the USA. This chart has identified the actual lot numbers of Moderna vaccine that have caused the most deaths in the USA. The deadliest of which is lot number ‘039K20A’ causing almost 100 deaths.
Conclusion
This investigation of VAERS data reveals several concerning findings which warrant further investigation, but it also leads to questions of why authorities within the USA which are supposed to monitor the safety of the Covid-19 vaccines have not discovered this themselves.
The data clearly shows that the Covid-19 vaccination campaign has been significantly more harmful and deadly than the influenza vaccination campaign. This fact alone begs the question as to how the FDA advisory committee could possibly vote Seventeen to Zero in favour of approving the Pfizer vaccine for use in children aged 5 to 11.
One voting member of the Food and Drug Administration (FDA) advisory committee admitted that it will not be fully known whether Pfizer’s vaccine is safe for 5 to 11-year-old children, until it begins being administered.
Dr Eric Rubin of Harvard University said – “We’re never going to learn how safe the vaccine is unless we start giving it, and that’s just the way it goes”.
But the investigation of VAERS has also identified the specific batches of Pfizer and Moderna vaccine that have caused the most harm across the USA, which leads to other extremely serious questions requiring urgent answers.
Why is it that certain batches of the vaccine have proven to be more harmful than others?
Why is it that certain batches of Covid-19 vaccine have proven to be deadlier than others?
Why is it that the most harmful and deadly Covid-19 vaccines were distributed across the entire USA, whilst the least harmful and deadly were only ever distributed to a few states? Was this done on purpose?
Could this just be a quality control issue?
A Pfizer whistleblower from a Kansas manufacturing facility did after all reveal that “People are being made to sign off on things that normally they wouldn’t, and then they wonder why their own employees won’t take it”.
CDC’s Committee Member Dr. Chen Should Be Removed Immediately Due to Conflict of Interest
By Toby Roger Ph.D. | The Defender | November 1, 2021
Dr. Wilbur H. Chen wants you to know that he’s very upset (see comment’s section)!
He’s upset the peasants have access to email!
He’s upset the peasants have access to common sense and reason!
He’s upset the peasants actually read scientific studies for themselves!
And he’s very upset that the peasants are speaking to him without his express written permission!
Apparently, he’s also clairvoyant (like Santa) because he knows what you are writing before you even send it to him, so he has set up an auto-reply on his email account to let you know he’s very important, he gets lots of emails and he does not like “misinformation.”
Chen defines “misinformation” as anything that contradicts the Pharma narrative. Chen is adamant that nothing be allowed to pierce his protective Pharma information bubble.
I’m reminded of the phrase, “Methinks thou doth protest too much.”
What Chen is actually mad about is that he got caught with his hand in the cookie jar.
A search of the government website Open Payments reveals Chen accepted $437,250.70 from Emergent BioSolutions and GlaxoSmithKline (GSK) in 2020.
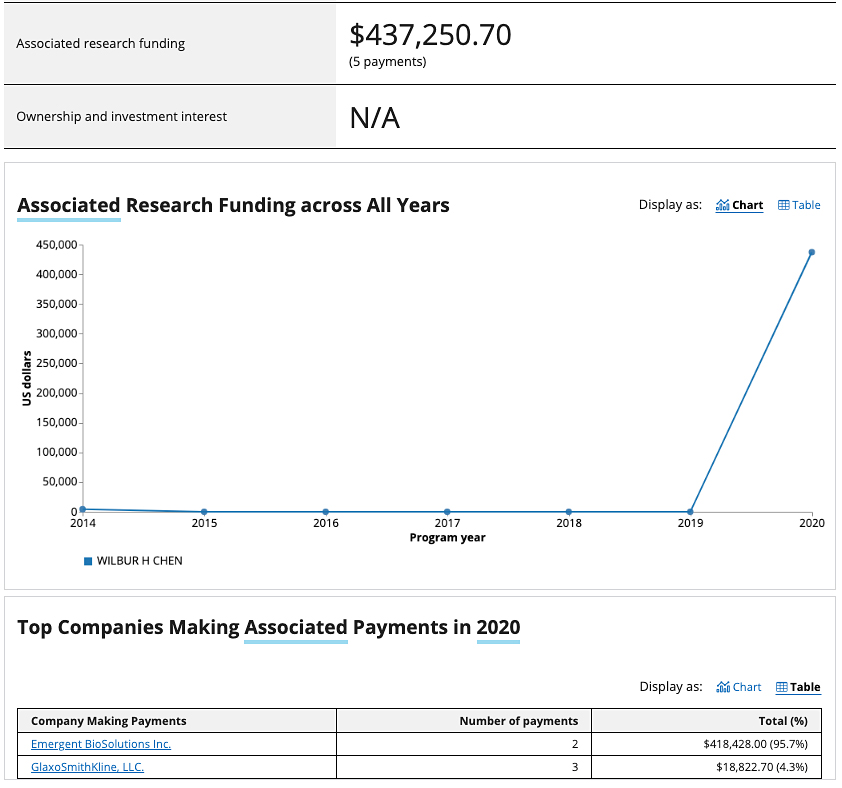
GSK is one of the four largest vaccine makers in the world. GSK makes the incredibly toxic Hep B vaccine (Engerix-B), the troubled HPV vaccine (Cervarix), a meningococcal vaccine that is loaded with aluminum (Bexsero) and various flu vaccines among others.
GSK is also working on a COVID-19 vaccine that is now in Phase 3 clinical trials.
All of GSK’s products must go before the Centers for Disease Control and Prevention (CDC) Advisory Committee on Immunization Practices (ACIP), that Chen sits on, in order to be approved.
Emergent BioSolutions is a contract manufacturer that makes vaccines for others including the Johnson & Johnson (J&J) COVID-19 vaccine that has been linked to blood clots and a bleeding disorder.
Emergent BioSolutions has an abysmal safety record. Even though federal regulators are generally like Mr. Magoo when it comes to spotting safety problems, the issues at Emergent’s plant in Baltimore were so egregious that earlier this year the U.S. Food and Drug Administration shut down the plant and ordered J&J to take it over and run it themselves.
The FDA also ordered 75 million doses of COVID-19 vaccines manufactured at that plant be destroyed because of contamination. All of the vaccines manufactured at the Emergent BioSolutions plant must first be approved by the ACIP where Chen is a member.
This is completely unacceptable. According to the Bureau of Labor Statistics, there were 27,550 pediatricians employed in the U.S. There is absolutely no reason for the ACIP to utilize a person with such extensive financial conflicts of interest.
The CDC must be above reproach in order to have any credibility with the general public. Sadly the CDC appears to do whatever it can get away with — a classic example of the fox guarding the henhouse.
The fact that these decisions involve the health of our children makes corruption all the more appalling.
Please contact the following four officials (as well your elected representatives) to let them know that you are troubled by Chen’s extensive financial conflicts of interest and please ask that he be removed from the ACIP before it meets on Tuesday, Nov. 2.
Dr. Rochelle Walensky
Director, Centers for Disease Control and Prevention
Roybal Building 21, Rm 12000
1600 Clifton Rd, Atlanta, GA 30333
phone: (404) 639-7000
Aux7@cdc.gov
Xavier Becerra
Secretary, Health and Human Services
200 Independence Avenue S.W., Washington, D.C. 20201
c/o Sean McCluskie
sean.mccluskie@hhs.gov
Captain Amanda Cohn
Chief medical officer
National Center for Immunizations and Respiratory Diseases
Centers for Disease Control and Prevention
1600 Clifton Rd, Atlanta, GA 30333 MS C-09
phone: (404) 639-6039
fax: (404) 315-4679
acohn@cdc.gov
anc0@cdc.gov
Grace Lee, M.D.
Chair, Advisory Committee on Immunizations Practices
Center for Academic Medicine
Pediatric Infectious Diseases, Mail Code: 5660
453 Quarry Road, Stanford, CA 94304
phone: (650) 497-0618
phone: (650) 498-6227
fax: (650) 725-8040
It is beyond alarming that the ACIP has failed to properly monitor financial conflicts of interest amongst its members. All prior ACIP votes involving Chen should be reviewed by an independent outside review board to see if they must be thrown out because of this blatant corruption.
The CDC should also examine and release publicly all financial conflict of interest statements from all remaining ACIP members to determine if there are additional problems before Tuesday.
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Featured Video

Get ready for the big Israeli false flag cyber-attack
or go to
Aletho News Archives – Video-Images
From the Archives
Some Call It Conspiracy Theory – Part 1
BY IAIN DAVIS | SEPTEMBER 25, 2023
There are certain assumptions that are applied to anyone labelled a “conspiracy theorist”—and all of them are fallacies. Indeed, the term “conspiracy theory” is nothing more than a propaganda construct designed to silence debate and censor opinion on a range of subjects. Most particularly, it is used as a pejorative to marginalise and discredit whoever challenge the pronouncements and edicts of the State and of the Establishment—that is, the public and private entities that control the State and that profit from the State.
Those of us who have legitimate criticisms of government and its institutions and representatives, who are therefore labelled “conspiracy theorists,” face a dilemma. We can embrace the term and attempt to redefine it or we can reject it outright. Either way, it is evident that the people who weaponise the “conspiracy theory” label will continue to use it as long as it serves their propaganda purposes.
One of the most insidious aspects of the “conspiracy theory” fabrication is that the falsehoods associated with the term have been successfully seeded into the public’s consciousness. Often, propagandists need do no more than slap this label on the targeted opinion and the audience will immediately dismiss that viewpoint as a “lunatic conspiracy theory.” Sadly, this knee-jerk reaction is usually made absent any consideration or even familiarity with the evidence presented by that so-called “lunatic conspiracy theorist.”
This was the reason why “conspiracy theorist” label was created. The State and its propagandists do not want the public to even be aware of inconvenient evidence, let alone to examine it. The challenging evidence is buried under the “wild conspiracy theory” label, thereby signalling to the unsuspecting public that they should automatically reject all of the offered facts and evidence.
There are a number of components that collectively form the conspiracy theory canard. Let’s break them down. … continue
Blog Roll
 Aletho News
- ‘Stop Putting Drugs in Our Food’: Scientists Link Folic Acid in Food to Rising Rates of Colorectal Cancer
- The 14 Things That Happen to Your Newborn in the First 48 Hours
- JFK’s Forgotten Confrontation with Israel
- Trump’s Cyber Director Pick Has Deep Ties To Israeli Intelligence
- Get ready for the big Israeli false flag cyber-attack
- The Ukrainian Reset experiment: A war and surveillance state blueprint for the EU
- Pentagon fails ninth financial audit in a row, unable to account for trillions in assets
- Russia rejects Danish plot claims, vows response to expulsion
- Study of 14,000 Children Links Vaccination to Higher Rates of Chronic Illness
- Strike Iran Again, Open Pandora’s Box | Brian McGlinchey
- If Americans Knew
- Reporting Raises Fresh Questions About Israeli Role in CNN’s ‘Preposterous’ Iranian Dirty Bomb Story
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Under the West’s watch, genocide apologism has become entirely respectable
- Israeli Diplomat Offered Iowa Attorney General Free Trip, Then Asked for Favors
- On World Children’s Day, 350 Palestinian Children Remain in Israeli Prisons
- Why Is Israel Jailing a Palestinian Student Without Trial? Because It Can
- ICJ ruling on Rohingya genocide could strengthen South Africa’s case against Israel
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Newly nominated House Speaker funded Gaza genocide
- Leaked: How Silicon Valley Elites Bankrolled an Anti-Migrant, Pro-Israel Propaganda Machine
- No Tricks Zone
- Germany’s Renewable Energies Lead to 1.4 Billion Euro Electric Power Trade Deficit
- Argentina’s Perito Moreno Glacier Joins Antarctica and Arctic In Defying Doomsday Melt Claims
- New Study: Barents Sea Temperatures Were Warmer And Sea Ice Less Extensive In The 1700s Than Today
- German Authorities Start Initiative To Evaluate Public Register For Climate “Disinformation” Spreaders!
- Zonal Asymmetry of Temperature Change in the Antarctic Circumpolar Current
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles

