In the latest editions of This Week in the New Normal, we mentioned a group of Members of the European Parliament who held a press conference where they opposed mandatory vaccination and the “Green Pass”.
On the 28th five of those same MEPs held another press conference, and while the whole thing is worth watching (embedded above), the highlight is definitely German MEP Christine Anderson who speaks for two of the truest minutes in the EU’s history:
All through Europe, governments have gone to great length to get people vaccinated. We were promised the vaccinations will be a “game changer”, and it will restore our freedom… turns out none of that was true. It does not render you immune, you can still contract the virus and you can still be infectious.
The only thing this vaccine did for sure was to spill billions and billions of dollars in the pockets of pharmaceutical companies.
I voted against the digital green certificate back in April, unfortunately it was adopted nonetheless, and this just goes to show there is only a minority of MEPs who truly stand for European values. The majority of MEPs, for whatever reasons unbeknown to me, obviously support oppression of the people while claiming – shamelessly – to do it for the people’s own good.
But it is not the goal that renders a system oppressive it is always the methods by which the goal is pursued. Whenever a government claims to have the people’s interest at heart, you need to think again.
In the entire history of mankind there has never been a political elite sincerely concerned about the well-being of regular people. What makes any of us think that it is different now? If the age of enlightenment has brought forth anything then, certainly this: never take anything any government tells you at face value
Always question everything any government does or does not do. Always look for ulterior motives. And always ask cui bono?, who benefits?
Whenever a political elite pushes an agenda this hard, and resort to extortion and manipulation to get their way, you can almost always be sure your benefit is definitely not what they had at heart.
As far as I’m concerned, I will not be vaccinated with anything that has not been properly vetted and tested and has shown no sound scientific evidence that the benefits outweigh the disease itself in possible long-term side effects, which to this day we don’t know anything about.
I will not be reduced to a mere guinea pig by getting vaccinated with an experimental drug, and I will most assuredly not get vaccinated because my government tells me to and promises, in return, I will be granted freedom.
Let’s be clear about one thing: No one grants me freedom for I am a free person.
So, I dare the European Commission and the German government: Throw me in jail, lock me up and throw away the key for all I care. But you will never be able to coerce me into being vaccinated if I, the free citizen that I am, choose not to be vaccinated.
Must Watch Very Powerful.
“In the entire history of mankind there has never been a political elite sincerely concerned about the wellbeing of regular people. What makes any of us think that it is different now. – Christine Anderson European Parliament.” pic.twitter.com/oSVYzg81p5
Today, Governor Kristi Noem signed Executive Order 2021-14, protecting state employees from President Biden’s federal vaccine mandates. She also released this video announcing her decision.
“South Dakota is fighting back against President Biden’s illegal vaccine mandates,” said Governor Kristi Noem. “Our state has many contracts with the federal government, and President Biden is attempting to use those contracts to force state employees to be vaccinated against their will. My executive order will protect their rights to medical and religious exemptions under any federal vaccine mandates. I am already talking with legislators about extending these protections to private employees through legislation as well.”
For the medical exemption, employees need a written statement from a physician stating that the COVID-19 vaccination is contraindicated for medical reasons.
For the religious exemption, a form will be made available by the Bureau of Human Resources that shall read in full, “I, [insert person’s full name], dissent and object to receiving a COVID-19 vaccine on religious grounds, which includes moral, ethical, and philosophical beliefs or principles.”
Due to established precedent, this Executive Order does not apply to service members with the South Dakota National Guard who must meet federal readiness responsibilities for deployment.
During the 2022 legislative session, Governor Noem will work with the legislature to make these protections for state employees permanent, and to extend similar health and religious liberty protections to employees of private businesses who adopted mandatory COVID-19 vaccination policies.
Today, following Governor Noem’s promise to “see [President Biden] in court,” the State of South Dakota joined a lawsuit against the Biden Administration’s COVID vaccine mandate for federal contractors.
“South Dakota is standing up with other states to protect our people from the Biden Administration’s illegal mandates,” said Governor Kristi Noem. “Though they are delaying their announcement of other mandates because they know those would be unconstitutional, we will not wait to fight this federal contractor mandate. We set up our defense with an executive order earlier this week. Now it’s time to go on offense.”
Earlier this month, the Biden Administration sent notices to federal contractors, including state entities, indicating that they will be enforcing the federal contractor mandate. This lawsuit is in response to those enforcement steps.
This action follows Governor Noem’s executive order earlier this week to protect South Dakota state employees from the Biden Administration’s illegal mandate for federal contractors. Governor Noem’s order guaranteed medical and religious exemptions for these employees, and Governor Noem also announced her intention to bring legislation to extend similar protections to private workers.
South Dakota is joined in the lawsuit by the states of Missouri, Nebraska, Alaska, Arkansas, Iowa, Montana, New Hampshire, North Dakota, and Wyoming. You can find the court filing here.
Florida Gov. Ron DeSantis is calling for employers to be held liable if their employees suffer injuries from mandated vaccines — even if the mandates were a result of federal edicts.
“We need to take action to protect Florida jobs and we have a situation now, unfortunately, in our country where we have a federal government that is very much trying to use the heavy hand of government to force a lot of these injections,” DeSantis said.
Saying he and his constituents believe in “basic medical freedom and individual choice,” and that “your right to earn a living should not be contingent upon COVID shots,” DeSantis said
If OSHA ends up coming out with the mandate dictated by President Biden, he plans to contest it, DeSantis added. He also plans to contest federal mandates on contractors that work with the federal government, but also work on the state level.
He also plans to contest the mandate that the Centers for Medicare & Medicaid Services are talking about handing down on hospitals and health care providers that accept Medicare and Medicaid.
“So what we’re going to be doing in addition to mounting aggressive legal challenges to federal mandates [is to] be taking legislative action to add protections for people.”
Safeway grocery store #1892 in Cortez, Colo., just lost its pharmacy manager because she no longer wants to administer “this poison,” referring to Wuhan coronavirus (Covid-19) “vaccines,” to customers.
According to reports, Nichole Belland took to the store’s intercom to announce that she is leaving her position for good because she can no longer in good conscience continue jabbing people with these “Operation Warp Speed” abominations they are calling “vaccines.”
“This is Nichole Belland, pharmacy manager for Safeway store at 1892 of Cortez,” Belland was heard saying over the intercom to a store full of surprised shoppers.
“I quit, effective immediately, because I will not give this poison to people. Wake up, everybody. This is poison. This is hurting people. I’ve seen it. I’ve seen customers die. Wake up, do not take it.”
If It Came Down To It, Would You Quit Your Job Rather Than Harm Others With Covid Jabs?
Steve Kirsh, the executive director of the COVID-19 Early Treatment Fund (CETF), got the chance to talk with Belland about what prompted her to leave her job in the dramatic way that she did.
It turns out that Belland had not worked at Safeway for several months prior to coming on the loudspeaker to make her announcement. Almost immediately after she was told by her supervisor that she would need to jab people with the “Operation Warp Speed” drugs, she decided to quit.
Belland was told at the time that she would have no choice but to administer the shots on demand, or else be fired from her position. She instead decided to go on temporary personal leave, but that was set to expire on October 15.
“I had tremendous concerns about these shots early on,” Belland says.
Not seeing any other way to get her message across before being forced out of her job, Belland went in on October 14, took her certificates and degrees off the wall, and proceeded to use the intercom to reveal publicly why she was essentially being forced to quit.
Belland says that around 8-10 customers were in front of her at the time when she picked up the intercom microphone and began speaking the truth into it. She had no idea that this brave act would end up going viral, possibly inspiring others who feel similarly to do the same.
Like many, Belland says that she is not necessarily “anti-vaccine.” She is anti-experimental gene therapy, which is technically what covid shots are since they were not developed using the same technologies as existing vaccines.
Prior to quitting, Belland had administered “thousands” of other shots to patients at her pharmacy, where she worked for 12 years after graduating from the University of Minnesota. However, when covid injections came along, it was a different story.
You can watch the full video interview between Kirsh and Belland at Red Voice Media.
“Bravo! Good for her, I would do the same thing if I was in her shoes!” wrote a commenter at Red Voice Media. “No job is more important than your overall health!”
“No job or any action is more important than the realization that you may be directly responsible for the injury or even death of another,” responded another, clarifying the reason why Belland quit.
“Every time a nurse who sticks a needle in someone’s arm who becomes ill or deceased later, and when on learning of their loss, she intentionally continues – is committing a premeditated harmful act to another.”
As the vaccine mandates pile on, we can expect more incidents like this to occur. More of the latest can be found at Pandemic.news.
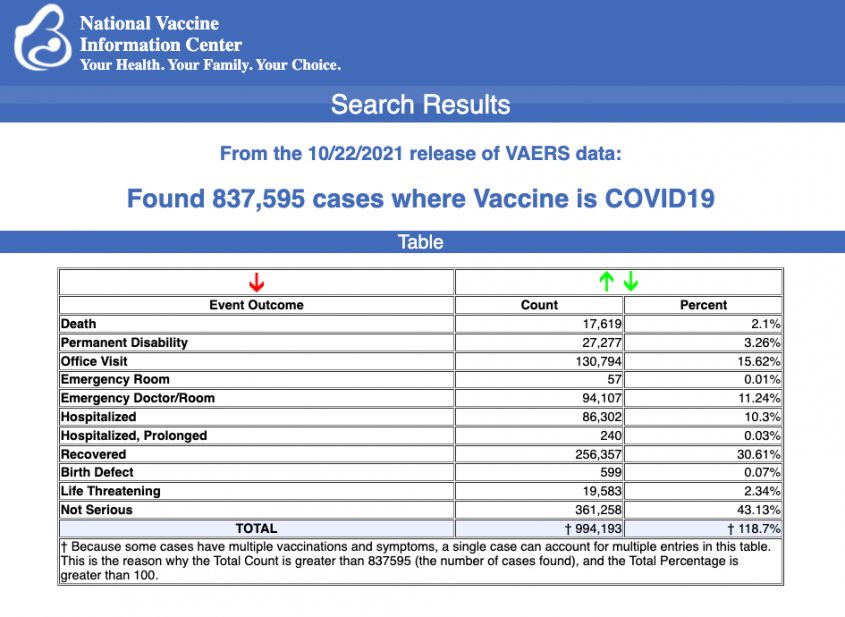
Data released Friday by the Centers for Disease Control and Prevention (CDC) showed that between Dec. 14, 2020, and Oct. 22, 2021, a total of 837,595 adverse events following COVID vaccines were reported to the Vaccine Adverse Event Reporting System (VAERS).
The data included a total of 17,619 reports of deaths — an increase of 491 over the previous week. There were 127,457 reports of serious injuries, including deaths, during the same time period — up 4,624 compared with the previous week.
Of the 8,068 U.S. deaths reported as of Oct. 22, 11% occurred within 24 hours of vaccination, 15% occurred within 48 hours of vaccination and 27% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 411.6 million COVID vaccine doses had been administered as of Oct. 15. This includes: 242 million doses of Pfizer, 154 million doses of Moderna and 15 million doses of Johnson & Johnson (J&J).
The data come directly from reports submitted to VAERS, the primary government-funded system for reporting adverse vaccine reactions in the U.S.
Every Friday, VAERS makes public all vaccine injury reports received as of a specified date, usually about a week prior to the release date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed.
Historically, VAERS has been shown to report only 1% of actual vaccine adverse events.
This week’s U.S. data for 12- to 17-year-olds show:
Another recent death includes a 15-year-old male who died six days after receiving his first dose of Pfizer’s COVID vaccine. According to his VAERS report (VAERS I.D. 1764974), the previously healthy teen complained of brief unilateral shoulder pain five days after receiving his COVID vaccine. The next day he played with two friends at a community pond, swung on a rope swing, flipped into the air, and landed in the water feet first. He surfaced, laughed and told his friends “Wow, that hurt!” He then swam toward shore underwater, as was his usual routine, but did not re-emerge.
An autopsy showed no external indication of a head injury, but there was a small subgaleal hemorrhage — a rare, but lethal bleeding disorder — over the left occiput. In addition, the boy had a mildly elevated cardiac mass, increased left ventricular wall thickness and small foci of myocardial inflammation of the lateral wall of the left ventricle with myocyte necrosis consistent with myocardial infarction.
58 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 96% of cases
attributed to Pfizer’s vaccine.
539 reports of myocarditis and pericarditis (heart inflammation) with 531 cases attributed to Pfizer’s vaccine.
125 reports of blood clotting disorders, with all cases attributed to Pfizer.
This week’s U.S. VAERS data, from Dec. 14, 2020, to Oct. 22, 2021, for all age groups combined, show:
19% of deaths were related to cardiac disorders.
54% of those who died were male, 41% were female and the remaining death reports did not include gender of the deceased.
FDA grants Emergency Use Authorization for Pfizer Vaccine for 5- to 11-year-olds
The U.S. Food and Drug Administration (FDA) today granted Emergency Use Authorization (EUA) for the Pfizer-BioNTech COVID vaccine for children 5 to 11 years old, The Associated Press reported.
The announcement followed Tuesday’s recommendation by the FDA’s vaccine advisory committee that the agency grant Pfizer’s request. The advisory committee vote passed with 17 in support, and one abstention.
“The vaccine was not granted FDA approval, but instead an emergency use authorization. Emergency authorizations are used when the secretary of health and human services has declared a public health emergency to more quickly clear the use of vaccines, treatments, and diagnostic tests. These authorizations lapse when the state of emergency ends. Pfizer’s vaccine was fully approved for those age 16 and older in August, and was previously granted an emergency use authorization for use in adolescents ages 12 to 15.”
The dose for younger children will be one-third the strength given to people 12 and older, with two shots given three weeks apart. Before the shots can be rolled out, the CDC must weigh in with its own recommendations.
Based on CDC data presented during the meeting, among children 5 to <12 years of age, there have been approximately 1.8 million confirmed and reported COVID cases since the beginning of the pandemic, and only 143 COVID-related deaths in the U.S. through Oct. 14.
Pfizer provided safety data on two study cohorts of children ages 5 to 11, both of roughly equal size. The first group was followed for only about two months, the second for only two-and-a-half weeks.
Pfizer said “post-vaccination myocarditis/pericarditis” in participants 5 to <12 years of age will not be studied until after the vaccine is authorized for children.
Pfizer vaccine ‘failed any reasonable risk-benefit calculus in connection with children,’ scientist says Brian Dressen, Ph.D., is one of the scientists who testified Tuesday during the FDA advisory committee’s 8-hour hearing. Dressen is also the husband of Brianne Dressen, who in 2020 developed a severe neurological injury during the Utah-based portion of the U.S. AstraZeneca COVID vaccine.
During his 3-minute testimony, Dressen, a chemist with an extensive background in researching and assessing the degree of efficacy in new technologies, told the FDA advisory panel Pfizer’s vaccine “failed any reasonable risk-benefit calculus in connection with children.”
Dressen said the decision to authorize for 5- to 11-year-olds is being rushed and is based on “incomplete data from underpowered trials, insufficient to predict rates of severe and long-lasting adverse reactions.”
Dressen urged the committee to reject the EUA modification and direct Pfizer to perform trials that decisively demonstrate the benefits outweigh the risks for children.
Dressen’s wife was severely injured last November after receiving her first and only dose of a COVID vaccine administered during a clinical trial.
“Because study protocol requires two doses, she was dropped from the trial, and her access to the study app deleted,” Dressen said. “Her reaction is not described in the recently released clinical trial report — 266 participants are described as having an adverse event leading to discontinuation, with 56 neurological reactions tallied.”
CDC updates guidance allowing immunocompromised to get a fourth COVID shot
Immunocompromised adults who received a third dose of either the Pfizer-BioNTech or Moderna COVID vaccine will become eligible for a fourth booster shot six months after receiving their third dose, according to CDC guidance issued Monday.
“In such situations, people who are moderately and severely immunocompromised may receive a total of four vaccine doses,” with the fourth coming at least six months after the third, the CDC’s new guidelines said.
However, a third dose is now considered part of the primary series, rather than a booster. The earliest that immunocompromised people who received a third mRNA vaccine shot can get a fourth shot as a booster would be February.
The agency said people could select that booster from any of the three COVID vaccines available in the U.S, including J&J, but specified a fourth dose of Moderna’s vaccine should be half the size of a normal dose.
Double-vaccinated can still spread the virus at home
Fully vaccinated people are catching COVID and passing it on to those they live with, warn experts in the UK. A British study published in the Lancet Oct. 29, showed individuals who have had two vaccine doses can be just as infectious as those who have not been jabbed.
Even if they are asymptomatic or have few symptoms, the chance of transmitting the virus to other unvaccinated housemates is about two in five, or 38%. This drops to one in four, or 25%, if housemates are also fully vaccinated.
“By carrying out repeated and frequent sampling from contacts of COVID-19 cases, we found that vaccinated people can contract and pass on an infection within households, including to vaccinated household members,” said Dr. Anika Singanayagam, co-lead author of the study.
“Our findings provide important insights into … why the Delta variant is continuing to cause high COVID-19 case numbers around the world, even in countries with high vaccination rates.
Vaccinated contacts who tested positive for COVID on average received their shots longer ago than those who tested negative, which the authors said was evidence of waning immunity and supported the need for booster shots.
Neil Ferguson, an Imperial epidemiologist, said the transmissibility of Delta meant that it was unlikely Britain would reach herd immunity for long.
“That may happen in the next few weeks: If the epidemic’s current transmission peaks and then starts declining, we have by definition in some sense reached herd immunity, but it is not going to be a permanent thing,” Ferguson told reporters.
16-year-old girl develops severe vulvar ulcers after second Pfizer shot
According to the report, a 16-year-old non-sexually active female presented to the pediatric gynecology clinic with vaginal pain six days after receiving her second dose of Pfizer’s COVID vaccine.
Within 24 hours of receiving the vaccine, the girl developed fever, fatigue, myalgias and “sores” in her vaginal area. Over the next two days, right-sided lesions in her vaginal area coalesced and became more painful. The teen went to the urgent care with a fever of 105 degrees. She was diagnosed with a Bartholin gland abscess.
Despite antibiotic therapy, her symptoms worsened and her lesions were covered in exudate with a necrotic, ring-like border. In the gynecology clinic, the patient’s lesions were exquisitely painful, resulting in difficulty with urination, defecation and walking. She had no respiratory symptoms and no history of COVID exposure.
The report said the findings “were consistent with vulvar aphthous ulcers in association with influenza-like symptoms following Pfizer BioNTech (BNT162b2) COVID-19 vaccination.”
“Our patient had typical clinical features of aphthous ulcer, including an influenza-like prodrome and characteristic dermatologic manifestations which occurred after receiving the Pfizer COVID vaccine,” the authors wrote. According to the report, the girl’s case was submitted to VAERS “due to the temporal relationship with COVID vaccine administration.”
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
The next wave of vaccination mandates will involve children. Since anyone raising concerns about this is considered an enemy of society, it’s been impossible to have a rational discussion about it.
Here’s what Harvey Risch, professor of epidemiology at the Yale School of Public Health and the Yale School of Medicine had to say about it this week.
“As far as I can tell, it’s a top-down structure, and most doctors do not get their information by going back and reading the original studies and making up their own minds. They get fed the information from pharma reps or from what they’re told from societies. The conflicts are legion. So it’s no surprise that most doctors don’t pay attention and think what they’re told…
“If the child has chronic conditions that make their risk appreciable, then there is a reason that they should be considered for vaccination. Other than that, if it were my child, I would homeschool them. Honestly, I would organize with other parents to take them out of the school and create a homeschooling environment.
There is no choice. Your child’s life is on the line.
“It’s not a high risk. Vaccination is not a high risk that’s going to kill every child by doing so. However, it’s enough of a risk that on the average the benefit is higher for homeschooling than it is for vaccination and being in school.”
Martin Kulldorff of Harvard is saying something similar:
“I don’t think children should be vaccinated for COVID. I’m a huge fan of vaccinating children for measles, for mumps, for polio, for rotavirus, and many other diseases. That’s critical. But COVID is not a huge threat to children….
“They can be infected, just like they can get the common cold, but they’re not a big threat. They don’t die from this, except in very rare circumstances. So if you want to talk about protecting children or keeping children safe, I think we can talk about traffic accidents, for example, which they are really at some risk…. And there are other things that we should make sure [of] to keep children safe. But COVID is not a big risk factor for children.”
Kulldorff points to the experience of his native Sweden. Beginning with the first wave in the spring of 2020, Sweden “decided to keep daycare and schools open for all children ages 1 to 15.
And there are 1.8 million such children who got through the first wave without vaccines, of course, without masks, without any sort of distancing in schools.
If a child was sick, they were told to stay home. But that was basically it. And you know how many of those 1.8 million children died from COVID? Zero. Only a few hospitalizations. So this is not a risky disease for children.”
He concludes: “If you’re a child, even if you haven’t had COVID, the risk of serious disease or death is minuscule … So it’s not at all clear that the benefits outweigh the risks for children.”
Try discussing this with friends and relatives on social media, and you run the risk of being silenced.
We are not even allowed to discuss these things. And when in our lifetimes has free discussion been more urgently needed?
There’s no censorship in my group, the Tom Woods Show Elite.
Here we discuss important matters like adults.
If you’re in a position where you don’t need such a thing, you are among the lucky few.
In the name of “public health,” the New York City government this week has been telling city employees to take the experimental coronavirus “vaccine” shots by Friday at 5 p.m. or be fired, or as the city government terms it, “placed on leave without pay.” Plenty of city workers of all types upset by this attack on their freedom have been taking to the streets in large numbers to protest, often admirably joined by leaders of their unions.
Apparently, New York City garbagemen upset with their mistreatment have chosen to skip days of work as well. The result, detailed in a Thursday article by Jean Lee at NBC News is trash piling up in parts of the city as regularly scheduled trash collection fails to occur.
What to expect after the Friday deadline? Continued piling up of trash on New York City sidewalks, right next to where millions of people in the densely populated city live, work, shop, and play each day is a good bet. Lee quotes the president of the Sanitation Officers Association:
Joseph Mannion, president of the Sanitation Officers Association, fears the trash pileups might foreshadow a possible worker shortage on Monday if vaccination rates among sanitation workers don’t increase by Friday. He said that the sanitation department has been moving to snow season shifts — 12 hours instead of eight — in anticipation of a possible worker shortage.
‘Prepare for the worst and hope for the best,’ Mannion said.
But Mannion is skeptical and said that he knows many sanitation workers are “hardened in their beliefs” and will refuse vaccination, even if it means being put on unpaid leave.
‘I know more people are getting vaccinated, but is it going to change around 60 percent to 80 percent?’ asked Mannion. ‘I don’t know. I don’t think so.’
More and more people in New York City must be asking themselves which is a healthier, and more pleasant, option: (A) letting trash continue to pile up on sidewalks while 100 percent of garbagemen are confirmed to have taken the experimental coronavirus vaccine shots, or (B) having trash regularly cleared from sidewalks while letting garbagemen choose whether they take the shots? My guess is that most people will choose option B, especially if the trash keeps piling up for weeks or even months on end.
The evidence is pouring in that the COVID-19 vaccines are not as efficacious as advertised against the Delta variant that became dominant in the fall of 2021. The Delta is learning how to thrive. The evidence has further accumulated to show that the vaccinated are showing viral loads (very high) similar to the unvaccinated, and the vaccinated are equally as infectious.
The gestalt of the findings implies that the infection explosion globally – post double vaccination e.g. Israel, UK, US etc. – that we have been experiencing may be likely due to the possibility that the vaccinated are driving the epidemic/pandemic and not the unvaccinated. We have been vaccinating against the wild-type virus that is no longer a pressing concern, even if the vaccine data so far suggests effectiveness for the demographic most susceptible to severe outcomes.
The data seems to suggest that the infection is 50:50 (vaccinated versus unvaccinated) while the UK is reporting 70% of deaths in the vaccinated (Delta variant) though there is debate on differential based on < 50 versus >50 years old. It appears that it is the vaccinated who are getting infected and thus transmitting the virus at a far greater rate. This unravels the demand for universal vaccine passports.
The Marek’s disease (‘leaky’ non-sterilizing, non-neutralizing imperfect vaccines that reduce symptoms but do not stop infection or transmission) in chickens model, and the concept of the Original antigenic sin (if an initial exposure or priming of the immune system is sub-optimal (Eugyppius) e.g. vaccination with the 2020 spike protein epitopes, then the sub-optimal priming is basically “fixed.” That is to say, it prejudices the life-long immune response with re-exposure due to the immune memory or learning.
Here I present a combination of 22 studies and stories that underscore just how big a problem this is for the NIH, CDC, FDA, and vaccine developers. It certainly highlights the problems with vaccine mandates that are currently threatening the jobs of millions of people. It raises further doubts about the case for vaccinating children.
Cases in point:
1) Gazit et al. out of Israel showed that “SARS-CoV-2-naïve vaccinees had a 13.06-fold (95% CI, 8.08 to 21.11) increased risk for breakthrough infection with the Delta variant compared to those previously infected.”
2) Acharya et al. found “no significant difference in cycle threshold values between vaccinated and unvaccinated, asymptomatic and symptomatic groups infected with SARS-CoV-2 Delta.”
3) Riemersma et al. found “no difference in viral loads when comparing unvaccinated individuals to those who have vaccine “breakthrough” infections. Furthermore, individuals with vaccine breakthrough infections frequently test positive with viral loads consistent with the ability to shed infectious viruses.” Results indicate that “if vaccinated individuals become infected with the delta variant, they may be sources of SARS-CoV-2 transmission to others.” They reported “low Ct values (<25) in 212 of 310 fully vaccinated (68%) and 246 of 389 (63%) unvaccinated individuals. Testing a subset of these low-Ct samples revealed infectious SARS-CoV-2 in 15 of 17 specimens (88%) from unvaccinated individuals and 37 of 39 (95%) from vaccinated people.”
4) Chemaitelly et al. reported a Qatar study which showed that the vaccine efficacy (Pfizer) declined to near zero by 5 to 6-months and even immediate protection after one to two months were largely exaggerated.
6) Riemersma et al. reported Wisconsin data that corroborate how the vaccinated individuals who get infected with the Delta variant can potentially (and are) transmit (ting) SARS-CoV-2 to others (potentially to the vaccinated and unvaccinated). They found an elevated viral load in the unvaccinated and vaccinated symptomatic persons (68% and 69% respectively, 158/232 and 156/225). This implied no difference between the vaccinated and unvaccinated in terms of carriage and transmission (symptomatic). Moreover, in the asymptomatic persons, they uncovered elevated viral loads (29% and 82% respectively) in the unvaccinated and the vaccinated respectively. This suggests that the vaccinated can be infected, harbour, cultivate, and transmit the virus readily and can be doing this unknowingly.
7) Subramanian reported that observed increases in COVID-19 are unrelated to levels of vaccination when they looked at 68 countries and 2947 counties in the United States. In other words, there is no clear discernable relationship (maybe a marginally positive association, where higher vaccination did not reduce the transmission).
8) Chau et al. (HCWs in Vietnam, Ho Chi Minh), looked at transmission of SARS-CoV-2 Delta variant among vaccinated healthcare workers in Vietnam, and their findings further ransacks the COVID-19 injection landscape and throws it into turmoil in terms of disastrous findings. 69 healthcare workers were tested positive for SARS-CoV-2. 62 participated in the clinical study. Researchers reported “23 complete-genome sequences were obtained. They all belonged to the Delta variant, and were phylogenetically distinct from the contemporary Delta variant sequences obtained from community transmission cases, suggestive of ongoing transmission between the workers. Viral loads of breakthrough Delta variant infection cases were 251 times higher than those of cases infected with old strains detected between March-April 2020”.
9) A CDC report by Brown in the MMWR (Barnstable, Massachusetts, July 2021) found that in 469 cases of COVID-19, there were 74% that occurred in fully vaccinated persons. “The vaccinated had on average more virus in their nose than the unvaccinated who were infected.”
10) Finland nosocomial hospital outbreak (spread among HCWs and patients): “In conclusion, this outbreak demonstrated that, despite full vaccination and universal masking of HCW, breakthrough infections by the Delta variant via symptomatic and asymptomatic HCW occurred, causing nosocomical infections.”
11) Israel nosocomial hospital outbreak (also spread among HCWs and patients) both revealed that the PPE and masks were essentially ineffective in the healthcare setting. The index cases were usually fully vaccinated and most (if not all transmission) tended to occur between patients and staff who were masked and fully vaccinated, underscoring the high transmission of the Delta variant among vaccinated and masked persons.
12) UK’s Public Health England Report # 42 on page 23 raised serious concerns when it reported that “waning of the N antibody response over time and (iii) recent observations from UK Health Security Agency (UKHSA) surveillance data that N antibody levels appear to be lower in individuals who acquire infection following 2 doses of vaccination.”
13) This UK report #42 (Table 2, page 13), as well as those reports 36 to 41, show a pronounced and very troubling trend, which is that the double vaccinated persons are showing greater infection (per 100,000) than the unvaccinated, and especially in the older age groups e.g. 30 years and above.
14) CDC’s Director Rochelle Walensky admitted that the vaccines are not stopping transmission which is an admission limits vaccine effectiveness.
15) Levin et al. “conducted a 6-month longitudinal prospective study involving vaccinated health care workers who were tested monthly for the presence of anti-spike IgG and neutralizing antibodies”…they found that “six months after receipt of the second dose of the BNT162b2 vaccine, humoral response was substantially decreased, especially among men, among persons 65 years of age or older….”
18) Suthar et al. examined the durability of immune responses to the BNT162b2 mRNA vaccine. They “analyzed antibody responses to the homologous Wu strain as well as several variants of concern, including the emerging Mu (B.1.621) variant, and T cell responses in a subset of these volunteers at six months (day 210 post-primary vaccination) after the second dose…data demonstrate a substantial waning of antibody responses and T cell immunity to SARS-CoV-2 and its variants, at 6 months following the second immunization with the BNT162b2 vaccine.”
19) Nordströmin Sweden report on their study which shows that (cohort comprised 842,974 pairs (N=1,684,958), including individuals vaccinated with 2 doses of ChAdOx1 nCoV-19, mRNA-1273, or BNT162b2, and matched unvaccinated individuals) “vaccine effectiveness of BNT162b2 against infection waned progressively from 92% (95% CI, 92-93, P<0·001) at day 15-30 to 47% (95% CI, 39-55, P<0·001) at day 121-180, and from day 211 and onwards no effectiveness could be detected (23%; 95% CI, -2-41, P=0·07).”
20) CDC Director Rochelle Walensky’s and Dr. Fauci’s call for boosters basically tells you all you needed to know, that the vaccine has failed to live up to its most elaborate promises.
21) Yahi et al. reported that “in the case of the Delta variant, neutralizing antibodies have a decreased affinity for the spike protein, whereas facilitating antibodies display a strikingly increased affinity. Thus, ADE may be a concern for people receiving vaccines based on the original Wuhan strain spike sequence (either mRNA or viral vectors).”
In conclusion, many people want the vaccine and they should be free to accept it as individuals. The public benefit of universal vaccination is now is grave doubt, and, as such, should not be expected to contribute to eliminating the social cost of the virus, much less be mandated by governments.
Dr Alexander holds a PhD. He has experience in epidemiology and in the teaching clinical epidemiology, evidence-based medicine, and research methodology. Dr Alexander is a former Assistant Professor at McMaster University in evidence-based medicine and research methods; former COVID Pandemic evidence-synthesis consultant advisor to WHO-PAHO Washington, DC (2020) and former senior advisor to COVID Pandemic policy in Health and Human Services (HHS) Washington, DC (A Secretary), US government; worked/appointed in 2008 at WHO as a regional specialist/epidemiologist in Europe’s Regional office Denmark, worked for the government of Canada as an epidemiologist for 12 years, appointed as the Canadian in-field epidemiologist (2002-2004) as part of an international CIDA funded, Health Canada executed project on TB/HIV co-infection and MDR-TB control (involving India, Pakistan, Nepal, Sri Lanka, Bangladesh, Bhutan, Maldives, Afghanistan, posted to Kathmandu); employed from 2017 to 2019 at Infectious Diseases Society of America (IDSA) Virginia USA as the evidence synthesis meta-analysis systematic review guideline development trainer; currently a COVID-19 consultant researcher in the US-C19 research group
Children’s Health Defense (CHD) on Nov. 3 will join organizations and individuals in “Worldwide Walkout” by calling in sick or taking a personal day to protest the unprecedented loss of freedom that has occurred the world over since the COVID pandemic began.
Parents will also pull their children out of school for the day to protest the many restraints that have applied directly to children.
“No government in history has ever surrendered power in the absence of a demand,” said Robert F. Kennedy, Jr., CHD chairman and chief legal counsel. “We need to tell these governments and their friends in the technocracy, the Silicon Valley billionaire boys club, the mainstream media and the pharmaceutical industry that we will no longer tolerate their trampling of citizens’ rights.”
Emboldened by reports of a recent walkout of Southwest employees — which led the airline’s management to drop plans to put unvaccinated employees on unpaid leave — nurses, doctors, teachers, police officers, firefighters and other workers are expected to participate in the protest.
“We need brave citizens to peacefully refuse to comply with unlawful and unethical edicts that for the past year-and-a-half have been allowed to trump individual rights and freedoms. Those days are over. There will be no business as usual until segregationist and coercive medical policies advanced by government authorities end once and for all.”
Organizers announced the protest after the Vaccines and Related Biological Products Advisory Committee (VRBPAC), which advises the U.S. Food and Drug Administration, on Tuesday recommended the agency authorize Pfizer’s Emergency Use Authorization COVID vaccine for children 5 to 11 years old.
The vote to recommend authorization of this vaccine, despite evidence that COVID does not pose a threat to young people, is causing even more unrest among those concerned with the safety of COVID vaccines in all age groups.
“This vote by VRBPAC to put young children at risk of serious injury, and even death, is one more reason people need to stand up to tyranny, and let businesses and governments know we will no longer comply with reckless decisions that threaten the health of our children,” said CHD Executive Director Laura Bono.
CHD chapters, coalition partners and local community organizers are planning mass gatherings of people in peaceful noncompliance to take place in high-exposure areas in many cities and states. Visit “Worldwide Walkout” for locations and details. If you don’t see one for your area, reach out to others in your community to plan an event. Choose a location that is easy to get to and can be seen by many.
Once your date, location and time are in place, tell us your plans so we can help amplify your message.
CHD.TV will carry live coverage of the day’s events.
IT’S hard to tell sometimes whether the mainstream media is ingenuous and stupid, or disingenuous and malign. Their across-the-board, uncritical and almost adulatory reporting of Israel’s ‘first out of the traps’ mass vaccination programme prompts this observation. Check out Israel on Google: however many pages you search, you won’t find one critical article on the Israeli vaccination programme’s efficacy or ethics.
Had it been an unmitigated success there’d be no cause for surprise. But the truth is otherwise. Despite its early roll-out and achieving rates of vaccination in vulnerable groups upwards of 90 per cent, it’s no secret that over the summer the country experienced another wave of the virus that vaccination proved no barrier to. By early August the vaccinated (not the unvaccinated) in Israel were reported by a leading Israeli health official to account for 95 per cent of severe and 90 per cent of new hospitalisations for Covid-19. Significant ‘excess’ deaths in non-Covid vulnerable age groups also raised serious questions about the vaccines’ safety. In addition, this pre-print study (un-peer reviewed) published in August found natural immunity conferred longer lasting and stronger protection against the disease and hospitalisation caused by the Delta variant than the vaccine.
None of this evidence caused Israel’s government even a pause for thought. Au contraire the country was first off the mark again – this time with ‘booster’ third and fourth jabs all endorsed by the MSM with articles crediting it with powers its predecessors strangely lacked:
‘ . . . third doses are highly effective at preventing people from becoming infected with Delta, among those who are willing to be vaccinated,’ one enthusiastic professor opined. He said they not only dramatically reduce a person’s susceptibility to infection, they create a barrier to the onward transmission and spread of the virus.
The message from Israel for the UK is clear, or so the i newspaper would also have us believe. The booster is the way forward that our Government must follow with all speed.
This is the theory we’ve explained more than once in these pages. It accounts for the unaccountable – in this case for vaccine enthusiasts’ (do more) irrational response to the vaccines’ failure to deliver; for the ‘doubling down’ phenomenon – anything rather than acknowledge they may have got it wrong or placed too much reliance on what was always uncertain.
Faithful to the theory, they claim in face of negative data that their actions were successful in averting the worst, going further into denial with professions that had they not acted it would have been worse; thus setting up a canny ‘heads-we-win, tails-you-lose’ interpretation of things.
Festinger, the originator of this particular theory of human behaviour, explains it as ‘a psychic condition of tension and discomfort brought about by a palpable contradiction in an individual’s mental world’. It is an unease that must be eliminated: ‘Accordingly, something in the individual’s conscious awareness has to be invented, altered, ignored or denied.’
What is undoubtedly being denied by the authorities and their propagandists is the other side of the story – not only the inconvenient data but the human testimonies of those who have fallen foul of the experimental vaccine. This is the ultimate denial, keeping invisible the very real victims and survivors of the vaccines whose accounts are too threatening to the official narrative for the authorities to acknowledge.
Thank God then for the The Testimonies Project from Israel … to make sure their voices are heard, since they are not being heard in the Israeli media.
It’s a project that needs replicating worldwide to ensure that the millions of Covid vaccine victims are not airbrushed out of history and that there will be record of the human suffering that politicians can and must be brought to account for.
The Canadian Trucking Alliance (CTA) has warned of substantial “supply chain disruptions” if the US enforces vaccine passports at the border.
A few weeks ago, the US Department of Homeland Security announced a vaccine mandate for all international travel including truck drivers that will take effect in January. The announcement has been heavily criticized by cross-border truckers. According to Transportation Network, one executive in the Canadian trucking industry warned that the mandate would lead to a “disaster.”
This week, the CTA warned that the mandate would increase supply chain disruptions. Trucks facilitate about 70% of the $650 billion trade between Canada and the US. About 40,000 US drivers and 120,000 Canadian drivers operate in the cross-border trade between the two countries.
The CTA said that about 20% of drivers will stop cross-border operations once the vaccine mandate is enforced.
“CTA conservatively estimates that 20 percent of Canadian truck drivers crossing the border (22,000), and 40 percent of U.S. truck drivers (16,000), would almost immediately exit the Canada-US trade system should the vaccination mandate take effect in January 2022,” the organization said.
It called on both the US and Canadian governments to “reexamine appropriate mandate timelines for cross-border truck drivers.”
The group also argued that more time is needed to create a “seamless mutual system of identification for drivers” to avoid delays when drivers are showing proof of vaccination.
However, the Biden administration appears to be disregarding the warnings of “dire consequences” from leading truck organizations by proceeding with the vaccine passport plans.
Reknowned economist M. Shahid Alamoffers this excellent critique of Noam Chomsky’s defective analysis of the relative influence of Oil versus the Israel lobby over US foreign policy: … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.