Yale Epidemiologist Cautions About Child Vaccination
By Tom Woods | Principia Scientific International | October 29, 2021
The next wave of vaccination mandates will involve children. Since anyone raising concerns about this is considered an enemy of society, it’s been impossible to have a rational discussion about it.
Here’s what Harvey Risch, professor of epidemiology at the Yale School of Public Health and the Yale School of Medicine had to say about it this week.
“As far as I can tell, it’s a top-down structure, and most doctors do not get their information by going back and reading the original studies and making up their own minds. They get fed the information from pharma reps or from what they’re told from societies. The conflicts are legion. So it’s no surprise that most doctors don’t pay attention and think what they’re told…
“If the child has chronic conditions that make their risk appreciable, then there is a reason that they should be considered for vaccination. Other than that, if it were my child, I would homeschool them. Honestly, I would organize with other parents to take them out of the school and create a homeschooling environment.
There is no choice. Your child’s life is on the line.
“It’s not a high risk. Vaccination is not a high risk that’s going to kill every child by doing so. However, it’s enough of a risk that on the average the benefit is higher for homeschooling than it is for vaccination and being in school.”
Martin Kulldorff of Harvard is saying something similar:
“I don’t think children should be vaccinated for COVID. I’m a huge fan of vaccinating children for measles, for mumps, for polio, for rotavirus, and many other diseases. That’s critical. But COVID is not a huge threat to children….
“They can be infected, just like they can get the common cold, but they’re not a big threat. They don’t die from this, except in very rare circumstances. So if you want to talk about protecting children or keeping children safe, I think we can talk about traffic accidents, for example, which they are really at some risk…. And there are other things that we should make sure [of] to keep children safe. But COVID is not a big risk factor for children.”
Kulldorff points to the experience of his native Sweden. Beginning with the first wave in the spring of 2020, Sweden “decided to keep daycare and schools open for all children ages 1 to 15.
And there are 1.8 million such children who got through the first wave without vaccines, of course, without masks, without any sort of distancing in schools.
If a child was sick, they were told to stay home. But that was basically it. And you know how many of those 1.8 million children died from COVID? Zero. Only a few hospitalizations. So this is not a risky disease for children.”
He concludes: “If you’re a child, even if you haven’t had COVID, the risk of serious disease or death is minuscule … So it’s not at all clear that the benefits outweigh the risks for children.”
Try discussing this with friends and relatives on social media, and you run the risk of being silenced.
We are not even allowed to discuss these things. And when in our lifetimes has free discussion been more urgently needed?
There’s no censorship in my group, the Tom Woods Show Elite.
Here we discuss important matters like adults.
If you’re in a position where you don’t need such a thing, you are among the lucky few.
New York City’s New ‘Public Health’ Plan: Let Garbage Pile Up on the Sidewalks

By Adam Dick | Ron Paul Institute | October 29, 2021
In the name of “public health,” the New York City government this week has been telling city employees to take the experimental coronavirus “vaccine” shots by Friday at 5 p.m. or be fired, or as the city government terms it, “placed on leave without pay.” Plenty of city workers of all types upset by this attack on their freedom have been taking to the streets in large numbers to protest, often admirably joined by leaders of their unions.
Apparently, New York City garbagemen upset with their mistreatment have chosen to skip days of work as well. The result, detailed in a Thursday article by Jean Lee at NBC News is trash piling up in parts of the city as regularly scheduled trash collection fails to occur.
What to expect after the Friday deadline? Continued piling up of trash on New York City sidewalks, right next to where millions of people in the densely populated city live, work, shop, and play each day is a good bet. Lee quotes the president of the Sanitation Officers Association:
Joseph Mannion, president of the Sanitation Officers Association, fears the trash pileups might foreshadow a possible worker shortage on Monday if vaccination rates among sanitation workers don’t increase by Friday. He said that the sanitation department has been moving to snow season shifts — 12 hours instead of eight — in anticipation of a possible worker shortage.
‘Prepare for the worst and hope for the best,’ Mannion said.
But Mannion is skeptical and said that he knows many sanitation workers are “hardened in their beliefs” and will refuse vaccination, even if it means being put on unpaid leave.
‘I know more people are getting vaccinated, but is it going to change around 60 percent to 80 percent?’ asked Mannion. ‘I don’t know. I don’t think so.’
More and more people in New York City must be asking themselves which is a healthier, and more pleasant, option: (A) letting trash continue to pile up on sidewalks while 100 percent of garbagemen are confirmed to have taken the experimental coronavirus vaccine shots, or (B) having trash regularly cleared from sidewalks while letting garbagemen choose whether they take the shots? My guess is that most people will choose option B, especially if the trash keeps piling up for weeks or even months on end.
Nov. 3: Join the ‘Worldwide Walkout,’ a Global Protest Against Government Overreach
Children’s Health Defense
Children’s Health Defense (CHD) on Nov. 3 will join organizations and individuals in “Worldwide Walkout” by calling in sick or taking a personal day to protest the unprecedented loss of freedom that has occurred the world over since the COVID pandemic began.
Parents will also pull their children out of school for the day to protest the many restraints that have applied directly to children.
“No government in history has ever surrendered power in the absence of a demand,” said Robert F. Kennedy, Jr., CHD chairman and chief legal counsel. “We need to tell these governments and their friends in the technocracy, the Silicon Valley billionaire boys club, the mainstream media and the pharmaceutical industry that we will no longer tolerate their trampling of citizens’ rights.”
Emboldened by reports of a recent walkout of Southwest employees — which led the airline’s management to drop plans to put unvaccinated employees on unpaid leave — nurses, doctors, teachers, police officers, firefighters and other workers are expected to participate in the protest.
“Coercive mandates of shoddily tested medical products and segregationist passports violate international human rights law,” said CHD President and General Counsel Mary Holland.
Holland added:
“We need brave citizens to peacefully refuse to comply with unlawful and unethical edicts that for the past year-and-a-half have been allowed to trump individual rights and freedoms. Those days are over. There will be no business as usual until segregationist and coercive medical policies advanced by government authorities end once and for all.”
Organizers announced the protest after the Vaccines and Related Biological Products Advisory Committee (VRBPAC), which advises the U.S. Food and Drug Administration, on Tuesday recommended the agency authorize Pfizer’s Emergency Use Authorization COVID vaccine for children 5 to 11 years old.
The vote to recommend authorization of this vaccine, despite evidence that COVID does not pose a threat to young people, is causing even more unrest among those concerned with the safety of COVID vaccines in all age groups.
From mid-December 2020 through Oct. 15, 2021, the Vaccine Adverse Events Reporting System (VAERS) received 818,044 reports of injury following COVID vaccination, including 17,128 deaths.
“This vote by VRBPAC to put young children at risk of serious injury, and even death, is one more reason people need to stand up to tyranny, and let businesses and governments know we will no longer comply with reckless decisions that threaten the health of our children,” said CHD Executive Director Laura Bono.
CHD chapters, coalition partners and local community organizers are planning mass gatherings of people in peaceful noncompliance to take place in high-exposure areas in many cities and states. Visit “Worldwide Walkout” for locations and details. If you don’t see one for your area, reach out to others in your community to plan an event. Choose a location that is easy to get to and can be seen by many.
Once your date, location and time are in place, tell us your plans so we can help amplify your message.
CHD.TV will carry live coverage of the day’s events.
The Covid vaccine victims who will not be silenced

By Kathy Gyngell | TCW Defending Freedom | October 28, 2021
IT’S hard to tell sometimes whether the mainstream media is ingenuous and stupid, or disingenuous and malign. Their across-the-board, uncritical and almost adulatory reporting of Israel’s ‘first out of the traps’ mass vaccination programme prompts this observation. Check out Israel on Google: however many pages you search, you won’t find one critical article on the Israeli vaccination programme’s efficacy or ethics.
Had it been an unmitigated success there’d be no cause for surprise. But the truth is otherwise. Despite its early roll-out and achieving rates of vaccination in vulnerable groups upwards of 90 per cent, it’s no secret that over the summer the country experienced another wave of the virus that vaccination proved no barrier to. By early August the vaccinated (not the unvaccinated) in Israel were reported by a leading Israeli health official to account for 95 per cent of severe and 90 per cent of new hospitalisations for Covid-19. Significant ‘excess’ deaths in non-Covid vulnerable age groups also raised serious questions about the vaccines’ safety. In addition, this pre-print study (un-peer reviewed) published in August found natural immunity conferred longer lasting and stronger protection against the disease and hospitalisation caused by the Delta variant than the vaccine.
None of this evidence caused Israel’s government even a pause for thought. Au contraire the country was first off the mark again – this time with ‘booster’ third and fourth jabs all endorsed by the MSM with articles crediting it with powers its predecessors strangely lacked:
‘ . . . third doses are highly effective at preventing people from becoming infected with Delta, among those who are willing to be vaccinated,’ one enthusiastic professor opined. He said they not only dramatically reduce a person’s susceptibility to infection, they create a barrier to the onward transmission and spread of the virus.
The message from Israel for the UK is clear, or so the i newspaper would also have us believe. The booster is the way forward that our Government must follow with all speed.
It’s not just the politicos and the MSM mouthing the mantra. The Brookings Institute has opined tortuously that despite Israel’s ‘successful’ vaccination programme, its mounting cases make ‘the booster shot of the Covid-19 vaccine more necessary than ever’.
No academic looking for a living, breathing example of cognitive dissonance could find a better one.
This is the theory we’ve explained more than once in these pages. It accounts for the unaccountable – in this case for vaccine enthusiasts’ (do more) irrational response to the vaccines’ failure to deliver; for the ‘doubling down’ phenomenon – anything rather than acknowledge they may have got it wrong or placed too much reliance on what was always uncertain.
Faithful to the theory, they claim in face of negative data that their actions were successful in averting the worst, going further into denial with professions that had they not acted it would have been worse; thus setting up a canny ‘heads-we-win, tails-you-lose’ interpretation of things.
Festinger, the originator of this particular theory of human behaviour, explains it as ‘a psychic condition of tension and discomfort brought about by a palpable contradiction in an individual’s mental world’. It is an unease that must be eliminated: ‘Accordingly, something in the individual’s conscious awareness has to be invented, altered, ignored or denied.’
What is undoubtedly being denied by the authorities and their propagandists is the other side of the story – not only the inconvenient data but the human testimonies of those who have fallen foul of the experimental vaccine. This is the ultimate denial, keeping invisible the very real victims and survivors of the vaccines whose accounts are too threatening to the official narrative for the authorities to acknowledge.
Thank God then for the The Testimonies Project from Israel … to make sure their voices are heard, since they are not being heard in the Israeli media.
It’s a project that needs replicating worldwide to ensure that the millions of Covid vaccine victims are not airbrushed out of history and that there will be record of the human suffering that politicians can and must be brought to account for.
You can watch it here.
Trucking Alliance warns of looming “disaster” if vaccine passports are introduced
The proposals would not only be an attack on civil liberties, it would cause further disruption to supply chains.
By Ken Macon | Reclaim The Net | October 27, 2021
The Canadian Trucking Alliance (CTA) has warned of substantial “supply chain disruptions” if the US enforces vaccine passports at the border.
A few weeks ago, the US Department of Homeland Security announced a vaccine mandate for all international travel including truck drivers that will take effect in January. The announcement has been heavily criticized by cross-border truckers. According to Transportation Network, one executive in the Canadian trucking industry warned that the mandate would lead to a “disaster.”
This week, the CTA warned that the mandate would increase supply chain disruptions. Trucks facilitate about 70% of the $650 billion trade between Canada and the US. About 40,000 US drivers and 120,000 Canadian drivers operate in the cross-border trade between the two countries.
The CTA said that about 20% of drivers will stop cross-border operations once the vaccine mandate is enforced.
“CTA conservatively estimates that 20 percent of Canadian truck drivers crossing the border (22,000), and 40 percent of U.S. truck drivers (16,000), would almost immediately exit the Canada-US trade system should the vaccination mandate take effect in January 2022,” the organization said.
It called on both the US and Canadian governments to “reexamine appropriate mandate timelines for cross-border truck drivers.”
The group also argued that more time is needed to create a “seamless mutual system of identification for drivers” to avoid delays when drivers are showing proof of vaccination.
However, the Biden administration appears to be disregarding the warnings of “dire consequences” from leading truck organizations by proceeding with the vaccine passport plans.
The Leaky Vaccine Breakthrough Variant Is Here
By Dr. Joseph Mercola | October 26, 2021
It was only a matter of time before a vaccine-resistant strain of COVID-19 would surface, and that time has already come to pass. As reported by The Conservative Treehouse October 3, 2021:1
“What this study2 finds is exactly what vaccine developer Geert Vanden Bossche (Belgium) has been predicting. The predominance of antibody-resistant SARS-Cov-2 variants in vaccine breakthrough cases from the San Francisco Bay Area, California …
Dr. Vanden Bossche has been using Israeli data and showing3 how the widespread vaccination rates were creating pressure on the virus to mutate into variants with higher levels of contagion.
The unvaccinated group has been keeping the pressure down by defeating the virus and carrying natural immunity. However, as the unvaccinated population is increasingly made smaller, the pressure on the virus to mutate increases. Subsequently, these mutations stay at higher or more effective levels of infection.”
Vaccine-Evading Variants Are Emerging
The study, posted on the preprint server medRxiv, August 25, 2021, concluded that those who are fully “vaccinated” against COVID-19 are in fact more susceptible to COVID variant infections than unvaccinated people.
Vanden Bossche’s theory was that vaccine antibodies would suppress natural antibody responses, allowing variants to slip through, and this seems to be what’s happening. As explained by The Conservative Treehouse October 3, 2021:4
“Among vaccinated individuals, a COVID variant virus is not recognized by the specialized antibodies provided by the vaccine, and the natural antibodies have been programmed to stand down.”
According to the authors of the study:5
“Associations between vaccine breakthrough cases and infection by SARS coronavirus 2 (SARS-CoV-2) variants have remained largely unexplored. Here we analyzed SARS-CoV-2 whole-genome sequences and viral loads from 1,373 persons with COVID-19 from the San Francisco Bay Area from February 1 to June 30, 2021, of which 125 (9.1%) were vaccine breakthrough infections.
Fully vaccinated were more likely than unvaccinated persons to be infected by variants carrying mutations associated with decreased antibody neutralization (78% versus 48%), but not by those associated with increased infectivity (85% versus 77%) …
These findings suggest that vaccine breakthrough cases are preferentially caused by circulating antibody-resistant SARS-CoV-2 variants, and that symptomatic breakthrough infections may potentially transmit COVID-19 as efficiently as unvaccinated infections, regardless of the infecting lineage.”
“Be careful around vaccinated people, because they can carry a more resistant form of COVID-19,” The Conservative Treehouse warns, adding that the narrow protection you get from the COVID shot will inevitably necessitate a booster shot for each emerging new variant that is resistant to the shots.
UK Data Show Increased COVID Mortality Among Fully Vaxxed
British data also raise serious questions about the wisdom of this injection campaign. In its Technical Briefing 23,6 published September 17, 2021, Public Health England reveals data showing the COVID death toll is actually higher among the fully vaccinated compared to the unvaccinated.
Between February 1, 2021, and September 12, 2021, 157,400 fully vaccinated patients (26.52% of total cases) were diagnosed with a Delta variant. Among the unvaccinated, there were 257,357 Delta variant cases (43.36% of total cases).
However, while Delta infections were far more prevalent among the unvaccinated, these patients also had better outcomes. In all, 63.5% of those who died from COVID-19 within 28 days of a positive test were fully vaccinated (1,613 compared to 722 in the unvaccinated group).
More Signs of Antibody-Dependent Enhancement
In a letter to the editor of the Journal of Infection,7 published August 9, 2021, three researchers point out that “infection-enhancing anti-SARS-CoV-2 antibodies recognize both the original Wuhan/D614G strain and Delta variants,” which suggests antibody-dependent enhancement (ADE) is emerging. According to the authors:8
“Antibody dependent enhancement (ADE) of infection is a safety concern for vaccine strategies. In a recent publication, Li et al. (Cell 184 :4203–4219, 2021) have reported that infection-enhancing antibodies directed against the N-terminal domain (NTD) of the SARS-CoV-2 spike protein facilitate virus infection in vitro, but not in vivo.
However, this study was performed with the original Wuhan/D614G strain. Since the Covid-19 pandemic is now dominated with Delta variants, we analyzed the interaction of facilitating antibodies with the NTD of these variants … [W]e show that enhancing antibodies have a higher affinity for Delta variants than for Wuhan/D614G NTDs …
As the NTD is also targeted by neutralizing antibodies, our data suggest that the balance between neutralizing and facilitating antibodies in vaccinated individuals is in favor of neutralization for the original Wuhan/D614G strain.
However, in the case of the Delta variant, neutralizing antibodies have a decreased affinity for the spike protein, whereas facilitating antibodies display a strikingly increased affinity. Thus, ADE may be a concern for people receiving vaccines based on the original Wuhan strain spike sequence (either mRNA or viral vectors).”
As noted by independent journalist Sharyl Attkisson,9 “Despite the fact that multiple medical authorities predicted, told us, and hoped, ADE would not impact Covid-19 vaccines, data from the study indicates it has done just that.”
Antibody Levels Decrease After Second Dose
While you’re not considered “fully vaccinated” until 14 days after your first dose of Janssen’s or AstraZeneca’s shot, or second dose of Moderna’s or Pfizer’s, a recent Israeli study found antibody levels actually decrease after the second dose of Pfizer’s COVID shot. The findings were reported by The Jerusalem Post, October 7, 2021:10
“Antibody levels decrease rapidly after two doses of the Pfizer coronavirus vaccine, a study11 by researchers at the Sheba Medical Center published … in the New England Journal of Medicine …
The research also showed the probability that different groups of individuals — based on age and general health status — will find themselves below a certain antibody threshold after a period of six months.”
In all, 4,868 staff members at the Sheba Medical Center participated in the study,12 undergoing monthly serological tests to measure their antibodies for up to six months after their second Pfizer shot.
Everyone, regardless of age or gender, saw a rapid decline in their antibodies after the second dose. IgG antibodies — which are part of your humoral immune response — decreased at a consistent rate over time, whereas the neutralizing antibodies rapidly decreased during the first three months, and then slowed down thereafter. According to the authors:13
“Although IgG antibody levels were highly correlated with neutralizing antibody titers (Spearman’s rank correlation between 0.68 and 0.75), the regression relationship between the IgG and neutralizing antibody levels depended on the time since receipt of the second vaccine dose …
The highest titers after the receipt of the second vaccine dose (peak) were observed during days 4 through 30, so this was defined as the peak period.
The expected geometric mean titer (GMT) for IgG for the peak period, expressed as a sample-to-cutoff ratio, was 29.3. A substantial reduction in the IgG level each month, which culminated in a decrease by a factor of 18.3 after 6 months, was observed.
Neutralizing antibody titers also decreased significantly, with a decrease by a factor of 3.9 from the peak to the end of study period 2, but the decrease from the start of period 3 onward was much slower, with an overall decrease by a factor of 1.2 during periods 3 through 6. The GMT of neutralizing antibody, expressed as a 50% neutralization titer, was 557.1 in the peak period and decreased to 119.4 in period 6 …
Six months after receipt of the second dose, neutralizing antibody titers were substantially lower among men than among women, lower among persons 65 years of age or older than among those 18 to less than 45 years of age, and lower among participants with immunosuppression than among those without immunosuppression.”
COVID-19 Unrelated to Jab in 68 Countries, 2,947 US Counties
The Israeli findings above can help explain the findings of a study14 published September 30, 2021, in the European Journal of Epidemiology, which found no relationship between COVID-19 cases and levels of vaccination in 68 countries worldwide and 2,947 counties in the U.S. If anything, areas with high vaccination rates had slightly higher incidences of COVID-19. According to the authors:15
“[T]he trend line suggests a marginally positive association such that countries with higher percentage of population fully vaccinated have higher COVID-19 cases per 1 million people.”
Iceland and Portugal, for example, where more than 75% of their populations are fully vaccinated, had more COVID-19 cases per 1 million people than Vietnam and South Africa, where only about 10% of the populations are fully vaccinated.16
Data from U.S. counties showed the same thing. New COVID-19 cases per 100,000 people were “largely similar,” regardless of the percentage of a state’s population that was fully vaccinated.
“There … appears to be no significant signaling of COVID-19 cases decreasing with higher percentages of population fully vaccinated,” the authors wrote.17 Notably, out of the five U.S. counties with the highest vaccination rates — ranging from 84.3% to 99.9% fully vaccinated — four of them were on the U.S. Centers for Disease Control and Prevention’s “high transmission” list. Meanwhile, 26.3% of the 57 counties with “low transmission” have vaccination rates below 20%.
The study even accounted for a one-month lag time that could occur among the fully vaccinated, since it’s said that it takes two weeks after the final dose for “full immunity” to occur. Still, “no discernable association between COVID-19 cases and levels of fully vaccinated” was observed.18
Key Reasons Why Reliance on Jabs Should Be Reexamined
The study summed up several reasons why the “sole reliance on vaccination as a primary strategy to mitigate COVID-19” should be reevaluated. For starters, the jab’s effectiveness is rapidly waning.
“A substantial decline in immunity from mRNA vaccines six months’ post immunization has … been reported,” the researchers noted, adding that even severe hospitalization and death from COVID-19, which the jabs claim to protect against, have increased from 0.01% to 9% and 0% to 15.1%, respectively, among the fully vaccinated from January 2021 to May 2021.19
If the jabs work as advertised, why haven’t these rates continued to rise instead of fall? “It is also emerging,” the researchers noted, “that immunity derived from the Pfizer-BioNTech vaccine may not be as strong as immunity acquired through recovery from the COVID-19 virus.”20
For instance, a retrospective observational study published August 25, 2021, revealed that natural immunity is superior to immunity from COVID-19 jabs. According to the authors:21
“This study demonstrated that natural immunity confers longer lasting and stronger protection against infection, symptomatic disease and hospitalization caused by the Delta variant of SARS-CoV-2, compared to the BNT162b2 two-dose vaccine-induced immunity.”
Reinfection Is Very Rare
The fact is, while breakthrough cases continue among those who have gotten one or more COVID-19 injections, it’s extremely rare to get COVID-19 after you’ve recovered from the infection. How rare? Researchers from Ireland conducted a systematic review including 615,777 people who had recovered from COVID-19, with a maximum duration of follow-up of more than 10 months.22
“Reinfection was an uncommon event,” they noted, “with no study reporting an increase in the risk of reinfection over time.” The absolute reinfection rate ranged from 0% to 1.1%, while the median reinfection rate was just 0.27%.23,24,25
Another study revealed similarly reassuring results. It followed 43,044 SARS-CoV-2 antibody-positive people for up to 35 weeks, and only 0.7% were reinfected. When genome sequencing was applied to estimate population-level risk of reinfection, the risk was estimated at 0.1%.26
There was no indication of waning immunity over seven months of follow-up, unlike with the COVID-19 injection, which led the researchers to conclude that “Reinfection is rare. Natural infection appears to elicit strong protection against reinfection with an efficacy >90% for at least seven months.”27
All Risk for No Reward?
The purpose of informed consent is to give people all of the data related to a medical procedure so they can make an educated decision before consenting. In the case of COVID-19 injections, such data initially weren’t available, given their emergency authorization, and as concerning side effects became apparent, attempts to share them publicly were suppressed.
In August 2021, a large study from Israel28 revealed that the Pfizer COVID-19 mRNA jab is associated with a threefold increased risk of myocarditis,29 leading to the condition at a rate of one to five events per 100,000 persons.30 Other elevated risks were also identified following the COVID-19 jab, including lymphadenopathy (swollen lymph nodes), appendicitis and herpes zoster infection.31
Dr. Peter McCullough, an internist, cardiologist and epidemiologist, is among those who have warned that COVID-19 injections are not only failing but putting lives at risk.32
According to McCullough, by January 22, 2021, there had been 186 deaths reported to the Vaccine Adverse Event Reporting System (VAERS) database following COVID-19 injection — more than enough to reach the mortality signal of concern to stop the program.
“With a program this size, anything over 150 deaths would be an alarm signal,” he said. The U.S. “hit 186 deaths with only 27 million Americans jabbed.” McCullough believes if the proper safety boards had been in place, the COVID-19 jab program would have been shut down in February 2021 based on safety and risk of death.33
Now, with data showing no difference in rates of COVID-19 cases among the vaxxed and unvaxxed, it appears more and more likely that the injections have a high level of risk with very little reward, especially among certain populations, like youth.
Mass Vaccination Drives Mutations
It’s well-known that if you put living organisms like bacteria or viruses under pressure, via antibiotics, antibodies or chemotherapeutics, for example, but don’t kill them off completely, you can inadvertently encourage their mutation into more virulent strains. Those that escape your immune system end up surviving and selecting mutations to ensure their further survival.
Many have warned about immune escape due to the pressure being placed upon the COVID-19 virus during mass vaccination,34 and according to one mathematical model,35 a worst-case scenario can develop when a large percentage of a population is vaccinated but viral transmission remains high, such as it is now. This is a prime scenario for the development of resistant mutant strains.36
At this point, COVID-19 injection failures and serious jab-related health risks are both apparent. We now also have data showing that having a high vaccination rate does nothing to lower COVID-19 incidence.
It might actually increase it slightly, as we’re seeing in India. In Kerala, India, which boasts a 93% vaccination rate, more than half of all new COVID cases are fully vaccinated, as are 57% of COVID-related deaths.37 With all data pointing in the same direction, it’s clear that COVID shots aren’t the answer. As noted in the European of Journal of Epidemiology :38
“Stigmatizing populations can do more harm than good. Importantly, other non-pharmacological prevention efforts (e.g., the importance of basic public health hygiene with regards to maintaining safe distance or handwashing, promoting better frequent and cheaper forms of testing) needs to be renewed in order to strike the balance of learning to live with COVID-19 in the same manner we continue to live a 100 years later with various seasonal alterations of the 1918 Influenza virus.”
If You’re ‘Vaccinated’ You May Be High-Risk for COVID
As predicted from the very beginning of the mass vaccination campaign, we’re now starting to see evidence of ADE, which makes people more prone to serious illness rather than less.
Even if your risk for ADE is small (and we have no data on prevalence as of yet), the data we do have suggest the shots aren’t ending outbreaks, and indeed can’t, end them, as it’s the vaccinated who are facilitating the emergence of vaccine-evading variants. The real answer is natural herd immunity, as natural immunity protects against most variants and not just one.
To be on the safe side, I recommend considering yourself “high-risk” for severe COVID if you’ve received one or more shots, and implement known effective treatment at the first sign of a respiratory infection.
Options include the Zelenko protocol,39 the MATH+ protocols40 and nebulized hydrogen peroxide, as detailed in Dr. David Brownstein’s case paper.41 Whichever treatment protocol you use, make sure you begin treatment as soon as possible, ideally at first onset of symptoms.
Sources and References
- 1, 4 Conservative Treehouse October 3, 2021
- 2, 5 medRxiv August 25, 2021, DOI: 10.1101/2021.08.19.21262139
- 3 YouTube Vejon Health Vanden Bosche and Robert Malone interview
- 6 Public Health England Technical Briefing 23, September 17, 2021
- 7, 8 Journal of Infection Letter to the Editor August 9, 2021
- 9 Sharyl Attkisson August 17, 2021
- 10 The Jerusalem Post October 7, 2021
- 11, 12, 13 NEJM October 6, 2021 DOI: 10.1056/NEJMoa2114583
- 14, 15, 16, 17, 18, 19, 20, 38 European Journal of Epidemiology September 30, 2021
- 21 medRxiv August 25, 2021
- 22, 23 Rev Med Virol. 2021;e2260
- 24 The Blaze July 14, 2021
- 25 News Rescue July 15, 2021
- 26, 27 medRxiv January 15, 2021
- 28, 30, 31 The New England Journal of Medicine August 25, 2021
- 29 MedPage Today August 25, 2021
- 32 BitChute, Episode 20 of Perspectives on the Pandemic: The Dangers of the Injections, August 26, 2021
- 33, 34 BitChute, Episode 20 of Perspectives on the Pandemic, ‘This Interview Could Save Your Life’ Part Two: The Dangers of the Injections, August 26, 2021
- 35, 36 Scientific Reports July 30, 2021
- 37 Onmanorama.com October 12, 2021
- 39 Zelenko protocol
- 40 Covid19criticalcare.com
- 41 Science, Public Health Policy and The Law July 2020; 1: 4-22 (PDF)
Pressure Mounts on the UKHSA to Stop Publishing Data Showing Infection Rates Higher in the Vaccinated
By Will Jones | The Daily Sceptic | October 27, 2021
The Prime Minister may have acknowledged reality and stated that being double vaccinated “doesn’t protect you against catching the disease, and it doesn’t protect you against passing it on” but others appear to remain in denial.
On Sunday I asked whether now that the PM had let the cat out of the bag the media would start reporting properly on the UKHSA data showing higher infection rates in the vaccinated than the unvaccinated. It appears the answer is no, at least if the Times‘s Tom Whipple is any indication.
In a typically mean-spirited piece – in which anyone who doesn’t agree with his favoured scientist of the hour is smeared as a conspiracy theorist and purveyor of misinformation – Whipple quotes Cambridge statistician Professor David Spiegelhalter, who heaps opprobrium on the U.K. Health Security Agency (the successor to PHE) for daring to publish data that contradicts the official vaccine narrative. Spiegelhalter says of the UKHSA vaccine surveillance reports:
This presentation of statistics is deeply untrustworthy and completely unacceptable… I cannot believe that UKHSA is putting out graphics showing higher infection rates in vaccinated than unvaccinated groups, when this is simply an artefact due to using clearly inappropriate estimates of the population. This has been repeatedly pointed out to them, and yet they continue to provide material for conspiracy theorists around the world.
This is the graphic he is presumably referring to.
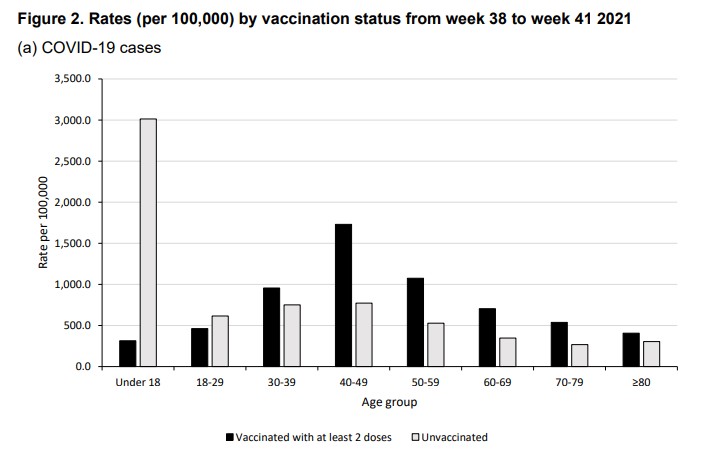
If Professor Spiegelhalter has a source for his claim that higher infection rates in the vaccinated are “simply an artefact” of erroneous population estimates then he doesn’t provide it.
Whipple says the data has been “seized upon around the world”.
The numbers have been promoted by members of HART, a U.K. group that publishes vaccine misinformation. They have also been quoted on the Joe Rogan Experience podcast in the US, which reaches 11 million people.
Appearing on that podcast, Alex Berenson, a U.S. journalist now banned from Twitter, specifically referenced the source to show it was reliable.
The UKHSA is adamant that it is doing nothing wrong. The Times quotes Dr Mary Ramsay, head of immunisation at the UKHSA, explaining: “Immunisation information systems like NIMS are the internationally recognised gold standard for measuring vaccine uptake.”
So Professor Spiegelhalter thinks that the gold standard gives “clearly inappropriate estimates of the population”, and using it is “deeply untrustworthy and completely unacceptable”? That may be his view, but the UKHSA can hardly be criticised for following the recognised standards for its work.
A more measured criticism is provided by Colin Angus, a statistician from the University of Sheffield, who the Times quotes saying that using NIMS data makes sense but the “huge uncertainty” in the population estimates should be clearer.
Whipple, however, goes further and claims that “using population data from other official sources shows, instead, shows that the protection of vaccines continues”. Yet he does not provide those sources or go into any detail about how they back up his claim.
For now, the UKHSA is defending its report (we’ll see how long it holds out for). But even so, Dr Ramsay is adamant that the report rules out using the data to estimate vaccine effectiveness: “The report clearly explains that the vaccination status of cases, inpatients and deaths should not be used to assess vaccine effectiveness and there is a high risk of misinterpreting this data because of differences in risk, behaviour and testing in the vaccinated and unvaccinated populations.”
This defence somewhat misses Professor Spiegelhalter’s criticism about population estimates. But it’s also misleading in that the report doesn’t “clearly” explain that its data “should not be used to assess vaccine effectiveness”. What it says is it is “not the most appropriate method to assess vaccine effectiveness and there is a high risk of misinterpretation”. But, as explained before, using population-based data on infection rates in vaccinated and unvaccinated is certainly a valid method of estimating unadjusted vaccine effectiveness, which is defined as the reduced infection rate in the vaccinated versus the unvaccinated. While a complete study would then adjust those raw figures for potential systemic biases (with varying degrees of success), we shouldn’t necessarily expect those adjustments to be large or change the picture radically. Indeed, when a population-based study from California (which showed vaccine effectiveness against infection declining fast), carried out these adjustments the figures barely changed at all.
The UKHSA report adds that: “Vaccine effectiveness has been formally estimated from a number of different sources and is described earlier in this report.” In fact, though, most of those estimates are reported as low confidence (see below), which means: “Little evidence is available at present and results are inconclusive.” While it claims high confidence for its estimates against symptomatic disease, a footnote explains that this only holds for 12-16 weeks: “This typically applies for at least the first three to four months after vaccination. For some outcomes there may be waning of effectiveness beyond this point.”
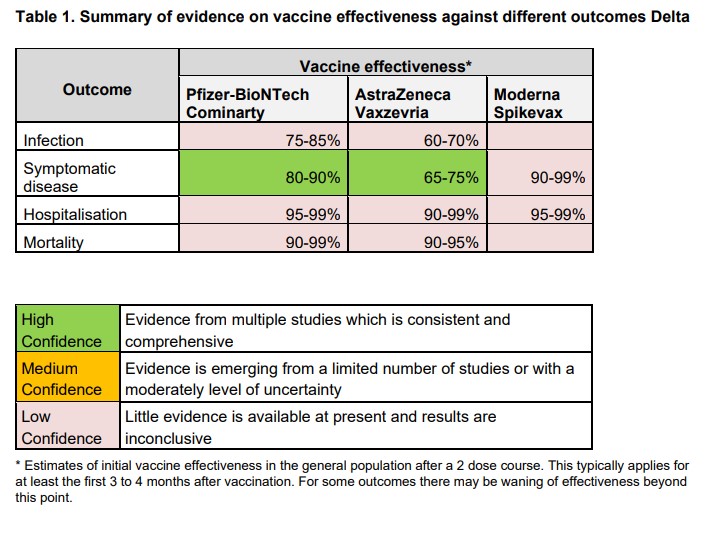
It is precisely this “waning of effectiveness” that the latest real-world data is giving us insight into. Rather than trying to discredit that data and those who report it by throwing around general, unquantified criticisms, scientists and academics like Professor Spiegelhalter should be redoubling efforts to provide constructive analysis to get to the bottom of what’s really going on with the vaccines. If there are issues with the population estimates then those need to be looked at, and if there are biases that need adjusting for then those need to be quantified. But do, please, get on with it – and lay off the smearing of those who raise the questions.
FDA Panel Backs Pfizer Shot For Kids: “We’re never going to learn about how safe this vaccine is unless we start giving it”
By Chris Menahan | InformationLiberation | October 26, 2021
An FDA vaccine advisory panel on Tuesday voted unanimously 17-0 in favor shooting up kids aged 5-11 with Pfizer’s experimental mRNA injection with panelist Dr Eric Rubin stating, “we’re never going to learn about how safe this vaccine is unless we start giving it.”
Full context:
https://twitter.com/politicalwilli/status/1453082309201117199?ref_src=twsrc%5Etfw%7Ctwcamp%5Etweetembed%7Ctwterm%5E1453082309201117199%7Ctwgr%5E%7Ctwcon%5Es1_&ref_url=https%3A%2F%2Fwww.informationliberation.com%2F%3Fid%3D62628
“We’re never going to learn about how safe this vaccine is unless we start giving it,” Dr Rubin said, urging other panelists to vote for it. “That’s just the way it goes.”
The panel voted in favor of experimenting on tens of millions of helpless children with zero long-term data on side effects because 94 children between 5 and 11 have died with COVID-19 (they claimed “of”) and “all have names. All of them had mothers,” to quote the emotional gobbledegook uttered by panelist Patrick S. Moore.
From The Washington Post :
“To me, it seems that it is a hard decision but a clear one,” said Patrick S. Moore, a University of Pittsburgh microbiologist and committee member. He noted that 94 children between 5 and 11 have died of covid-19, and “all have names. All of them had mothers.”
As the WSJ reported:
Members of the FDA’s vaccine-advisory panel supported Moderna’s booster dose even though the evidence for it was from a small study and had mixed results.
“It’s more a gut feeling rather than based on really truly serious data,” said Patrick Moore, a member of the committee and a professor of molecular genetics and biochemistry at the University of Pittsburgh School of Medicine. “The data itself is not strong, but it is certainly going in the direction that is supportive of this vote.”
This is how they “follow the science.”
LA City Council: ‘No Jab? That’ll Be $65, Please’
21st Century Wire | October 27, 2021
L.A. City Council unveiled its new plan to harass its unvaccinated workers with bi-weekly COVID tests to paid for by employees.
Los Angeles City Council has announced that its police officers, firefighters and other city workers who have not yet received their experimental COVID-19 pharmaceutical gene therapy injections – will be ‘given more time’ to get their jabs under the new plan approved by the City Council.
City officials hope that a constant campaign of harassment and financial penalties waged against its workers will encourage any remaining unvaccinated employees to submit to the corporate jabs.
City workers who haven’t given up their constitutional right to bodily autonomy by Dec. 18th will face “corrective action” and punishment by the city, including legalized targeted harassment by city officials, according to their plan released yesterday.
Until then, the city’s unvaccinated workers will be required to get tested for COVID-19 twice per week, on their own time, and at a cost of $65 for each test – deducted straight from their paychecks.
California official will be studying the results of this program closely, no doubt with plans to replicate it across other sectors of society, and as a coercive instrument for businesses as well.
More on Original Antigenic Sin and the Folly of Our Universal Vaccination Campaign
A deeper look at a decisive limitation of our adaptive immune systems
eugyppius | October 26, 2021
To review: We have now had ten months of mass vaccination against SARS-CoV-2. Nearly 7 billion doses have been administered worldwide. This unprecedented campaign has not eradicated Corona; it has not even suppressed infections. Instead, case statistics have ballooned almost everywhere. While the vaccinated appear to enjoy some protection against severe outcomes, skyrocketing transmission means most countries have seen little benefit, on balance, from their universal vaccination campaigns. The most pressing question has become, simply: What is going on?
I’ve explored a few different possibilities. First, there seems to be a Marek Effect at work. We might imagine that all viruses have an optimal level of population-wide virulence – an advantageous degree of aggression at which they can spread effectively, while not driving their hosts underground too soon. Certain Delta sub-strains, previously punished for their excessive aggression in unvaccinated populations, have likely been favoured by the vaccines, which reduce symptoms in the vaccinated without preventing infection for more than a few months. Our vaccines reduced the average virulence of SARS-2, and the virus adapted to reattain the prior, optimal balance.
But the virus and its interactions with human hosts constitute a complex system. In such systems, it is very unlikely that any effect can be put down to a single cause. The Public Health England data provide powerful reasons to suspect that the vaccines may be compromising immunity to SARS-2 via Original Antigenic Sin. This is not a crazy internet fantasy, but a well-observed limitation of human immunity. It is the primary reason that respiratory viruses like influenza return again and again. Despite multiple reinfections across the whole population, we are never quite immune to the flu, because its strategy is to exploit the way our immune systems learn.
The mechanisms of Original Antigenic Sin are not fully understood, but we have a rough idea of what might be happening. When a virus infects your body for the first time, your naive memory B cells imprint on specific virus proteins, or antigens, presented to them. These B cells then become either memory B cells or plasma cells. Forever after, they specialise in producing antibodies against those specific antigens. When a slightly mutated form of the virus arrives, these memory B-cells begin pouring forth the antibodies they learned to produce during the first infection. These antibodies bind to multiple epitopes on the virus particles, and in the process they give the slower-moving naive B-cells little chance to learn about any new, mutant virus features.
Original Antigenic Sin was most influentially described by Thomas Francis in 1960. He noted that, regardless of whatever influenza A strains were in circulation, subjects tended to have dominant antibody responses to the strains that were current in their early childhood:
The antibody of childhood is largely a response to … the virus causing the first Type A influenza infection of the lifetime. As the group grows older and subsequent infections take place, antibodies to additional families of virus are acquired. But … the antibody which is first established continues to characterize that cohort of the population throughout its life. The antibody forming mechanisms have been highly conditioned by the first stimulus, so that later infections with strains of the same type successively enhance the original antibody to maintain it at the highest level at all times in that age group. The imprint established by the original virus infection governs the antibody response thereafter. This we have called the doctrine of original antigenic sin.
An important consequence of this childhood conditioning, is that different age cohorts within the population have overlapping or layered immunity to different influenza strains. This is an important if subtle aspect of our population-wide immunity to influenza A. It looks like this:
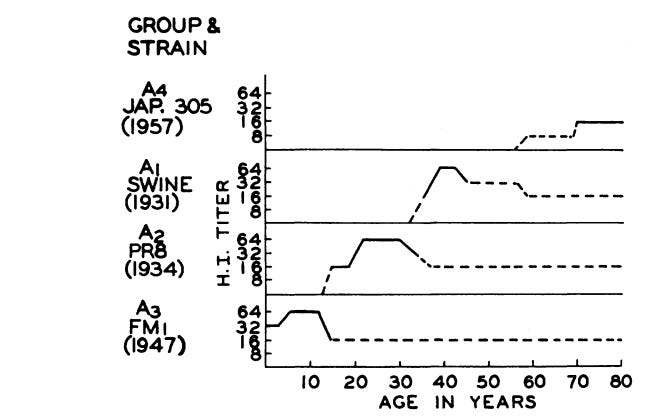
As older cohorts die, their immunity to older strains dies with them. These old strains, long suppressed, are then positioned to return, for very few human immune systems remember them any longer. Francis believed this was the mechanism underlying periodic cycles of pandemic influenza. The 1957 influenza pandemic, for example, featured a strain of flu against which only the oldest cohorts – those in their 70s – had specific antibodies. As these “immunological veterans” disappeared, this older, long-suppressed type of influenza was free to return and cause another pandemic event.
In conclusion, Francis proposed that optimised influenza vaccines might be administered to children before their first infection. He envisioned vaccines designed to confer immunity against “known or anticipated recurrent strains” and hoped that “In this manner the original sin of infection could be replaced by an initial blessing of induced immunity.”
Strategic vaccination conferring immunity against likely future strains is of course exactly the opposite of our current efforts to give every last living human multiple vaccinations against an extinct strain of SARS-2.
*
The existence of Original Antigenic Sin has been confirmed by generations of research, and the literature is full of curious findings. A major reason flu shots don’t work, for example, is that they are powerless to redirect adult immune systems against novel influenza strains. Most people who get flu shots are adults, with immune systems long since primed by childhood infection. Hence this old Lancet case study of influenza outbreaks among boys at Christ’s Hospital in Sussex in the 1970s:
In each outbreak, the protective effect of inactivated influenza-A vaccine was limited to those boys, not already immune, who were vaccinated for the first time with the most up-to-date strain. Revaccination with the same strain did not increase the degree of protection, and revaccination with a later strain did not afford protection against subsequent challenge.
The flu vaccines, in other words, work great if you’ve never had the flu before. Otherwise they don’t do anything.
And consider these remarks, from a 2005 article in Nature Medicine:
It is often difficult to further increase antibody levels, specificity and the quality of the immune response in individuals who have been repeatedly immunized through either vaccination or recurrent exposure to infectious agents or cross-reacting microbial antigens. This has been a particular concern for aging adults in the context of the antigenic drift of influenza virus, in view of their annual exposure to antigens of new but related influenza variants through either infection or vaccination. After exposure to a new but cross-reacting antigenic variant, such individuals may respond by producing antibodies that are primarily directed at antigens characterizing influenza viruses encountered during earlier epidemics.
The authors go on to write that the “impact” of Original Antigenic Sin “on protection is far from established,” noting earlier research showing substantial all-cause mortality reductions from flu shots. Later work, though, has shown that the mortality reduction of influenza vaccines is largely an illusion of selection effects. For a variety of reasons, those most likely to die of influenza are far less likely than healthier groups to be vaccinated.
Original Antigenic Sin has been famously implicated in dengue fever. This is considered to be an extreme case of the phenomenon, with “considerable bearing on vaccine strategies.” Here the conclusions are ominous and full of implications for our own situation:
Once a response has been established, it is unlikely that repeat boosting will be able to change its scope, meaning that balanced responses against the four virus serotypes will need to be established with the first vaccine dose.
The danger is that immunity to one strain alone may lead to permanently impaired immune response to the three other serotypes, causing worse and longer illness.
*
Influenza had been infecting humans for generations before anybody came up with the notion of influenza vaccines. Despite the efforts of public health authorities everywhere, most people catch the flu before they are ever vaccinated, and so flu shots have little opportunity to undermine population-wide immunity to influenza A.
The complex system constituted by SARS-CoV-2 and its interactions with the human immune system, on the other hand, remains barely understood. In chasing an empty fantasy of herd immunity, authorities are denying human populations everywhere the opportunity to develop the layered, population-wide resistance against successive SARS-2 strains that is the foundation of our immunity against other respiratory viruses. Aside from the minority that have managed to recover from natural infection before the vaccinators got to them, most humans will have their crucial, primary immune response conditioned by the spike protein of SARS-2 in its vintage 2020 configuration.
It is a near certainty that this immunity will attenuate antibody responses to the spike protein of current and future variants, forever. Mutant spike proteins will increasingly escape vaccine-conferred immunity, and breakthrough infections will elicit only partial response to the new epitopes. Insofar as the data also suggest that our vaccines will attenuate immunity to other virus proteins beyond spike, mass vaccination will lead to ever more volatile waves of infection – in exchange for limited and fading protection against severe outcomes.
The most dangerous thing to do, at this point, would be to vaccinate children. The virus is not a threat to them, and if they are infected by the new forms of SARS-2 that are sure to emerge every winter, we will begin to establish – through them and the as yet unvaccinated – the layered immunity that is the only way of coming to terms with SARS-2 in the longer term. As long as the vaccinators are permitted to continue their radical and increasingly insane campaign, though, nothing will improve. Indeed, their policies threaten to bring about a semi-permanent pandemic state for generations to come.
Featured Video

Get ready for the big Israeli false flag cyber-attack
or go to
Aletho News Archives – Video-Images
From the Archives
Some Call It Conspiracy Theory – Part 1
BY IAIN DAVIS | SEPTEMBER 25, 2023
There are certain assumptions that are applied to anyone labelled a “conspiracy theorist”—and all of them are fallacies. Indeed, the term “conspiracy theory” is nothing more than a propaganda construct designed to silence debate and censor opinion on a range of subjects. Most particularly, it is used as a pejorative to marginalise and discredit whoever challenge the pronouncements and edicts of the State and of the Establishment—that is, the public and private entities that control the State and that profit from the State.
Those of us who have legitimate criticisms of government and its institutions and representatives, who are therefore labelled “conspiracy theorists,” face a dilemma. We can embrace the term and attempt to redefine it or we can reject it outright. Either way, it is evident that the people who weaponise the “conspiracy theory” label will continue to use it as long as it serves their propaganda purposes.
One of the most insidious aspects of the “conspiracy theory” fabrication is that the falsehoods associated with the term have been successfully seeded into the public’s consciousness. Often, propagandists need do no more than slap this label on the targeted opinion and the audience will immediately dismiss that viewpoint as a “lunatic conspiracy theory.” Sadly, this knee-jerk reaction is usually made absent any consideration or even familiarity with the evidence presented by that so-called “lunatic conspiracy theorist.”
This was the reason why “conspiracy theorist” label was created. The State and its propagandists do not want the public to even be aware of inconvenient evidence, let alone to examine it. The challenging evidence is buried under the “wild conspiracy theory” label, thereby signalling to the unsuspecting public that they should automatically reject all of the offered facts and evidence.
There are a number of components that collectively form the conspiracy theory canard. Let’s break them down. … continue
Blog Roll
 Aletho News
- ‘Stop Putting Drugs in Our Food’: Scientists Link Folic Acid in Food to Rising Rates of Colorectal Cancer
- The 14 Things That Happen to Your Newborn in the First 48 Hours
- JFK’s Forgotten Confrontation with Israel
- Trump’s Cyber Director Pick Has Deep Ties To Israeli Intelligence
- Get ready for the big Israeli false flag cyber-attack
- The Ukrainian Reset experiment: A war and surveillance state blueprint for the EU
- Pentagon fails ninth financial audit in a row, unable to account for trillions in assets
- Russia rejects Danish plot claims, vows response to expulsion
- Study of 14,000 Children Links Vaccination to Higher Rates of Chronic Illness
- Strike Iran Again, Open Pandora’s Box | Brian McGlinchey
- If Americans Knew
- Reporting Raises Fresh Questions About Israeli Role in CNN’s ‘Preposterous’ Iranian Dirty Bomb Story
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Under the West’s watch, genocide apologism has become entirely respectable
- Israeli Diplomat Offered Iowa Attorney General Free Trip, Then Asked for Favors
- On World Children’s Day, 350 Palestinian Children Remain in Israeli Prisons
- Why Is Israel Jailing a Palestinian Student Without Trial? Because It Can
- ICJ ruling on Rohingya genocide could strengthen South Africa’s case against Israel
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Newly nominated House Speaker funded Gaza genocide
- Leaked: How Silicon Valley Elites Bankrolled an Anti-Migrant, Pro-Israel Propaganda Machine
- No Tricks Zone
- Germany’s Renewable Energies Lead to 1.4 Billion Euro Electric Power Trade Deficit
- Argentina’s Perito Moreno Glacier Joins Antarctica and Arctic In Defying Doomsday Melt Claims
- New Study: Barents Sea Temperatures Were Warmer And Sea Ice Less Extensive In The 1700s Than Today
- German Authorities Start Initiative To Evaluate Public Register For Climate “Disinformation” Spreaders!
- Zonal Asymmetry of Temperature Change in the Antarctic Circumpolar Current
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles

