The WEF and the Pandemic
How is the Davos World Economic Forum involved in the coronavirus pandemic?
Swiss Policy Research | October 6, 2021
The Davos World Economic Forum (WEF) is a premier forum for governments, global corporations and international entrepreneurs. Founded in 1971 by engineer and economist Klaus Schwab, the WEF describes its mission as “shaping global, regional and industry agendas” and “improving the state of the world”. According to its website, “moral and intellectual integrity is at the heart of everything it does.”
The WEF has been involved in the coronavirus pandemic in several ways.
First, the WEF was, together with the Gates Foundation, a sponsor of the prescient “Event 201” coronavirus pandemic simulation exercise, held in New York City on October 18, 2019 – the same day as the opening of the Wuhan Military World Games, seen by some as “ground zero” of the global pandemic. China itself has argued that US military athletes may have brought the virus to Wuhan.
Second, the WEF has been a leading proponent of digital biometric identity systems, arguing that they will make societies and industries more efficient, more productive and more secure. In July 2019, the WEF started a project to “shape the future of travel with biometric-enabled digital traveler identity management”. In addition, the WEF collaborates with the ID2020 alliance, which is funded by the Gates and Rockefeller foundations and runs a program to “provide digital ID with vaccines”. In particular, ID2020 sees the vaccination of children as “an entry point for digital identity.”
Third, WEF founder Klaus Schwab is the author of the book COVID-19: The Great Reset, published in July 2020, which argues that the coronavirus pandemic can and should be used for an “economic, societal, geopolitical, environmental and technological reset”, including, in particular, advancing global governance, accelerating digital transformation, and tackling climate change.
Finally, the WEF has been running, since 1993, a program called “Global Leaders for Tomorrow”, rebranded, in 2004, as “Young Global Leaders”. This program aims at identifying, selecting and promoting future global leaders in both business and politics. Indeed, quite a few “Young Global Leaders” have later managed to become Presidents, Prime Ministers, or CEOs (see below).
During the coronavirus pandemic, several WEF Global Leaders and Global Shapers (a junior program of the Global Leaders) have played prominent roles, typically promoting zero-covid strategies, lockdowns, mask mandates, and ‘vaccine passports’. This may have been a (largely failed) attempt to protect public health and the economy, or it may have been an attempt to advance the global transformation agenda outlined above, or perhaps both.
In this regard, some notable Young Leaders include Jeffrey Zients (US White House Coronavirus Response Coordinator), Stéphane Bancel (CEO of Moderna), Jeremy Howard (founder of influential lobby group “Masks for All”), Leana Wen (zero-covid CNN medical analyst), Eric Feigl-Ding (zero-covid Twitter personality), Gavin Newsom (Governor of California, selected in 2005), Devi Sridhar (British zero-covid professor), Jacinda Ardern (Prime Minister of New Zealand), French President Emanuel Macron (selected one year prior to his election in 2017), Austrian Chancellor Sebastian Kurz, German Chancellor Angela Merkel (selected back in 1993), German Health Minister Jens Spahn, and former British Prime Minister Tony Blair (a leading proponent of ‘global vaccine passports’).
To get a full overview of their members, see Global Leaders for Tomorrow and Young Global Leaders on WikiSpooks (a Wiki focusing on covert power structures) as well as the official Young Global Leaders website. For an overview of some notable members in politics and the media, see below.
In conclusion, the Davos World Economic Forum has indeed been involved in the strategic management of the coronavirus pandemic, with a major emphasis on using the pandemic as a catalyst for digital transformation and the global introduction of digital identity systems.
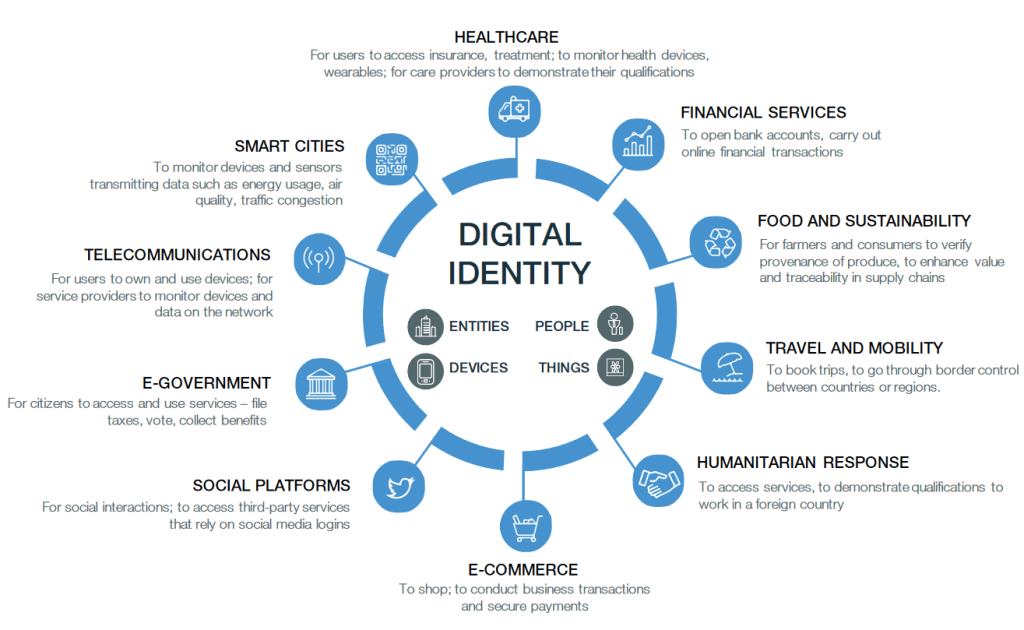
Digital Identity: The vision of the World Economic Forum (WEF, 2018)
WEF “Young Global Leaders”
An overview of some WEF Young Global Leaders (2005-2021) and Global Leaders for Tomorrow (1993-2003) in politics and the media. The list is not exhaustive.
Sources: Global Leaders for Tomorrow and Young Global Leaders on WikiSpooks.
United States
Politics and Policy
Jeffrey Zients (White House Coronavirus Response Coordinator since 2021, selected in 2003), Jeremy Howard (co-founder of lobby group “masks for all”, selected in 2013), California Governor Gavin Newsom (selected in 2005), Pete Buttigieg (selected in 2019, candidate for US President in 2020, US secretary of transportation since 2021), Chelsea Clinton (Clinton Foundation board member), Huma Abedin (Hillary Clinton aide, selected in 2012), Nikki Haley (US ambassador to the UN, 2017-2018), Samantha Power (US ambassador to the UN, 2013-2017, USAID Administrator since 2021), Ian Bremmer (founder of Eurasia Group), Bill Browder (initiator of the Magnitsky Act), Jonathan Soros (son of George Soros), Kenneth Roth (director of “Human Rights Watch” since 1993), Paul Krugman (economist, selected in 1995), Lawrence Summers (former World Bank Chief Economist, former US Treasury Secretary, former Harvard University President, selected in 1993), Alicia Garza (co-founder of Black Lives Matter, selected in 2020), Stéphane Bancel (Moderna CEO).
Media
CNN medical analyst Leana Wen (selected in 2018), CNN chief medical correspondent Sanjay Gupta, Covid Twitter personality Eric Feigl-Ding (a ‘WEF Global Shaper‘ since 2013), Andrew Ross Sorkin (New York Times financial columnist), Thomas Friedman (New York Times columnist, selected in 1995), George Stephanopoulos (ABC News, 1993), Lachlan Murdoch (CEO of Fox Corporation).
Technology and Social Media
Microsoft founder Bill Gates (1993), former Microsoft CEO Steven Ballmer (2000-2014, selected in 1995), Amazon founder Jeff Bezos (1998), Google co-founders Sergey Brin and Larry Page (2002/2005), former Google CEO Eric Schmidt (2001-2017, selected in 1997), Wikipedia co-founder Jimmy Wales (2007), PayPal co-founder Peter Thiel (2007), eBay co-founder Pierre Omidyar (1999), Facebook founder and CEO Mark Zuckerberg (2009), Facebook COO Sheryl Sandberg (2007).
Great Britain, Canada, New Zealand
Professor Devi Sridhar (a leading ‘zero covid’ proponent, selected in 2020/21), former British Prime Ministers Tony Blair and Gordon Brown (both selected in 1993), BBC World Service journalist Dawood Azami, Lynn Forester de Rothschild (co-owner of The Economist), Nathaniel Rothschild (son of Lord Rothschild), historian Niall Ferguson (selected in 2005), William Hague (Foreign Secretary, 2010-2014), Charles Allen (CEO of ITV, 2004-2007; Chairman of EMI, 2008-2010).
New Zealand Prime Minister Jacinda Ardern (since 2017, selected in 2014), Canadian Deputy Prime Minister Chrystia Freeland (selected in 2001; former managing director of Reuters). Canadian Prime Minister Justin Trudeau is a WEF participant, but is not a confirmed Young Global Leader.
Germany
Chancellor Angela Merkel (selected in 1993, 12 years before becoming Chancellor), current Health Minister Jens Spahn and former Health Ministers Philipp Roesler and Daniel Bahr, current co-chair of the Green Party and failed Chancellor candidate Annalena Baerbock (selected in 2020), former co-chair of the Green Party Cem Özdemir (selected in 2002), media mogul and Axel Springer CEO Mathias Doepfner (selected in 2001), talk show host Sandra Maischberger, late Foreign Minister and Vice Chancellor Guido Westerwelle (1997), former German President Christian Wulff (selected in 1995, 15 years before becoming President), Reto Francioni (former CEO of Deutsche Boerse).
European Union
EU Commission Presidents Jose Manuel Barroso (2004-2014, selected in 1993) and Jean-Claude Juncker (2014-2019, selected in 1995), French President Emanuel Macron (since 2017, selected in 2016), former French President Nicolas Sakozy (2007-2012, selected in 1993), Austrian Chancellor Sebastian Kurz, former Italian Prime Minister Matteo Renzi (2014-2016, selected in 2012), former Spanish Prime Minister Jose Maria Aznar (1996-2004, selected in 1993), Klaus Regling (CEO of the European Financial Stability Mechanism since 2012), Guy Verhofstadt (former Belgian Prime Minister, Chair of the Brexit Steering Group), Danish Minister for the Environment Lea Wermelin, Finnish Prime Minister Sanna Marin, former Finnish Prime Minister Alexander Stubb, and Mark Leonard (founding director of the Soros-funded European Council on Foreign Relations).
Switzerland
Natalie Rickli (Director of Health of the Canton of Zurich, selected in 2012), former Presidents of the Swiss National Council Christa Markwalder (selected in 2011) and Pascale Bruderer-Wyss (selected in 2009), Geneva politician Pierre Maudet (selected in 2013), NZZ media group CEO Felix R. Graf (selected in 2007), former Swiss Justice Minister Ruth Metzler (selected in 2002), former Swiss television CEO Roger de Weck (2011-2017, selected in 1994), former UBS CEOs Peter Wuffli (selected in 1994) and Marcel Rohner (selected in 2003), former Credit Suisse CEO Tidjane Tiam (1998).
Video Annex
1) Bill Gates demanding “digital immunity proof” in March 2020
2) Edward Snowden warning of the “destruction of rights” (March 2020)
3) The Chinese “social credit” system (May 2019)
Further reading
- All Roads Lead to Dark Winter (Whitney Webb, April 2020)
See also
BMJ Publishes Belated Attack on the Great Barrington Declaration, but It Doesn’t Hit the Target
By Noah Carl • The Daily Sceptic • October 13, 2021
The Great Barrington Declaration, which advocates a focused protection strategy for dealing with COVID-19, was published in October last year – before many countries around the world imposed their winter lockdowns.
Recently, The BMJ Opinion – a journalistic offshoot of the well-known medical journal – published a very belated hit piece against the authors. As you might expect, it’s light on scientific arguments and heavy on tactics like ad hominem, guilt by association and appeals to authority.
The authors, David Gorski and Gavin Yamey, really don’t mince words. For example, they describe the Declaration (which has been signed by hundreds of scientists and healthcare professionals) as a “well-funded sophisticated science denialist campaign based on ideological and corporate interests”.
Not exactly a respectful way to talk about your colleagues. But it’s hardly the first time the Declaration’s critics have sunk to this level. Just last month, Jay Bhattacharya became the subject of a censorious petition which claimed that he “sows mistrust of policies designed to protect the public health”.
Gorski and Yamey begin their article by criticising the Declaration’s authors for collaborating with the American Institute for Economic Research, which they claim is a “libertarian, climate-denialist, free market think tank”.
I’m not sure why this is a ‘gotcha’. Lockdown is about as un-libertarian a policy as you could imagine, so it’s not really surprising that a libertarian think tank would oppose it. And in any case, the Declaration’s website clearly states that the document was “was written and signed at the American Institute for Economic Research”.
Martin Kulldorff has since clarified that the AIER president and board did not know about the Declaration until after it was published. But even if they had done, so what? As Kulldorff notes, universities like Duke and Stanford have received money from the Koch brothers. Should we therefore completely disregard what their academics have to say?
Gorski and Yamey’s next move is to cite social media censorship of lockdown sceptics as evidence that their arguments constitute ‘misinformation’. (Incidentally, that term – which basically means ‘information that’s missing from the mainstream narrative’ – appears no fewer than six times in the article.)
However, this argument relies on circular logic: ‘Something was censored on social media? Therefore, it’s misinformation. How do we know? Well, misinformation is what social media companies censor.’ In reality, of course, the fact that something was censored is no indication whatsoever that it’s factually incorrect.
The authors then allege that when Sunetra Gupta and Carl Heneghan met Boris Johnson in September of last year, they were successful in “persuading him to delay” a ‘circuit breaker’ lockdown, which could have forestalled the second wave of infections.
As historian Phil Magness has already noted, this argument is deficient on two counts. It’s not clear that Gupta and Heneghan did persuade the Prime Minister to shelve the ‘circuit breaker’ idea. But even if they did, there’s no reason to believe that policy would’ve prevented a large number of deaths.
Finally, Gorski and Yamey compare lockdown sceptics to ‘climate science deniers’, insofar as both groups “argue that evidence-based public health measures do not work”. They call for experts to push back against the Great Barrington Declaration by highlighting “scientific consensus”, citing the John Snow Memorandum.
Of course, the pro-lockdown John Snow Memorandum is just another public statement signed by scientists and health professionals. If it constitutes “scientific consensus”, then so does the Great Barrington Declaration. I’m only aware of one attempt to gauge overall expert opinion on focused protection: the survey by Daniele Fanelli.
He asked scientists who’d published at least one relevant paper, “In light of current evidence, to what extent do you support a ‘focused protection’ policy against COVID-19, like that proposed in the Great Barrington Declaration?” Of those who responded, more than 50% said “partially”, “mostly” or “fully”.
Regardless of the exact number of experts who support focused protection, claiming there is a “scientific consensus” against it is simply false. Long before the Declaration itself was published, many scientists had proposed some version of precision shielding. In fact, this was basically the U.K.’s plan until the middle of March, 2020.
On March 5th, Chris Whitty told the Health and Social Care Committee that we are “very keen” to “minimise economic and social disruption”, and mentioned that “one of the best things we can do” is “isolate older people from the virus”.
Another prominent scientist who has argued in favour of focused protection is Sir David Spiegelhalter. In an article published on May 29th, he and George Davey Smith said that we ought to “stratify shielding according to risk” because lockdown is “seriously damaging many aspects of people’s lives”.
They noted that this would require “a shift away from the notion that we are all seriously threatened by the disease, which has led to levels of personal fear being strikingly mismatched to objective risk of death”.
Among the ad hominems, appeals to authority and repeated uses of ‘misinformation’, finding a scientific argument in Gorski and Yamey’s article is not easy. And given that the content’s almost a year out of date, I’m not sure why the authors felt the need to publish it.
SPECIAL BROADCAST: DR. ROBERT MALONE ON HIS MRNA CREATION
STEW PETERS | OCTOBER 13, 2021
Stew Peters sat down with Dr. Robert Malone, the creator of the mRNA technology being used in the shots being falsely referred to as “vaccines”, which have proven to be dangerous, and in many cases DEADLY.
House of Commons Covid Report Gets Some Things Right, Most Things Wrong
By Toby Young • The Daily Sceptic • October 12, 2021
On Monday evening two House of Commons select committees – the Science and Technology Committee and the Health and Social Care Committee – published a joint report on the Government’s handling of the COVID-19 pandemic that was predictably damning. It was published in time to make the following day’s front pages – “Britain must learn from ‘big mistakes’ on Covid, says report”, reported the Times on its front page – but not in time for newspaper reporters or broadcast journalists to properly assess its findings. Not that that stopped all the usual suspects from using it as a stick to beat the Government with. For instance, Labour’s Shadow Health Secretary Jonathan Ashworth told the BBC that the “damning” findings showed that “monumental errors” had been made and called for the public inquiry – scheduled for next spring – to be brought forward.
The authors of the report say in the Executive Summary that the reason they’ve published it now, when there are still a large number of ‘known unknowns’ as well as ‘unknown unknowns’, is because we urgently need to learn from what the Government got right and what it got wrong so we are better prepared for the next pandemic, which might come along at any moment. But if it’s too soon to say what was a mistake and what wasn’t, that argument collapses. Indeed, a premature report that draws the wrong conclusions, e.g. that the Government didn’t lock down in March of last year early enough, which is one of the main findings of this report, is worse than useless since it may encourage future Governments to repeat the same mistakes.
I’ve now read the report – yes, all 145 pages – so you don’t have to.
What the report gets right
- It criticises the Government for discharging elderly patients from hospitals into care homes without testing them first to see if they had COVID-19 and without putting any measures in place in care homes to mitigate the impact of that policy, as well as for the lack of PPE in care homes. The report says these errors “led to many thousands of deaths which could have been avoided”. Hard to argue with that, although one of the oddities of the report is that it criticises the lack of infection control in care homes, but not in hospitals. Weird, given that ~20% of cases over the course of the U.K.’s epidemic have been hospital-acquired infections.
- The authors praise the RECOVERY trial for carrying out large randomised control trials of different COVID-19 treatments and identifying dexamethasone as an effective treatment. That too seems right.
- The report highlights the disproportionately high Covid death rates among black, Asian and minority ethnic populations and acknowledges that part of the explanation for that may be biological differences between those populations and the white British population. Even acknowledging that genetic factors may be part of the reason for these disparities makes a refreshing change. Unfortunately, the report goes on to play down these biological differences and claims that social, economic and health inequalities are much bigger factors.
- It criticises hospitals and care homes for issuing ‘Do Not Attempt CPR’ notices to patients/clients with learning disabilities and autism, often without the consent of their families. No argument there.
- Rather than blame Boris and other senior members of the Government for the decision not to lock down before March 23rd 2020, the report emphasises that they were just following the recommendations they were being given by their scientific advisors. As I’ve pointed out before, that is correct.
- The report is at least ambivalent about how effective a two-week ‘circuit breaker’ would have been in England in September of 2020.
It is impossible to know whether a circuit breaker in the early autumn of 2020 would have had a material effect in preventing a second lockdown given that the Kent (or Alpha) variant may already have been prevalent. Indeed such an approach was pursued in Wales, which still ended up having further restrictions in December 2020.
Unfortunately, having written this, the authors then go on to say:
It is likely that a “circuit break” of temporary lockdown measures if introduced in September 2020, and earlier lockdown measures during the winter, could have impeded the rapid seeding and spread of the Kent variant.
Make up your mind guys!
What the report gets wrong
- The report claims that the U.K.’s Pandemic Preparedness Strategy wasn’t fit for purpose because it prepared us for “an influenza-like pandemic” rather than a more serious infectious disease that was spread, in part, by asymptomatic transmission. Professor Devi Sridhar, who gave evidence to the joint committees, is quoted as saying the mistake our Government made was to assume COVID-19 was “just like a bad flu”. In fact, it was like a bad flu, as judged by the latest estimates of the infection fatality rate, and the jury’s still out on whether asymptomatic people who test positive for Covid are infectious.
- One of the reasons the Government didn’t lock down before March 23rd, according to the authors, is because its scientific advisors were guilty of following the flawed playbook of the Pandemic Preparedness Strategy. In particular, the initial advice was to try to ‘manage’ the spread of the virus through the general population rather than to suppress it altogether, which the authors believe would have been the correct strategy. They claim the Government didn’t realise this sooner because it had failed to learn the lessons of the SARS, Swine Flu and MERS pandemics and embed those lessons in its strategy. But, surely, one of the lessons of those pandemics is that national lockdowns aren’t necessary to contain pandemics – and that advice was embedded in the U.K. Government’s strategy document. The mistake the Government made was not to initially follow that advice; the mistake was to stop following it on March 23rd. The only time a government has tried quarantining entire regions as a strategy to mitigate the impact of a viral outbreak prior to 2020 was in Mexico in 2009 when something like a lockdown was imposed on April 27th in Mexico City, the State of Mexico and the State of San Luis Potosí. That was policy abandoned on May 6th because of the mounting social and economic costs.
- Bizarrely, the authors of the report claim the reason the British Government didn’t abandon the Pandemic Preparedness Strategy sooner was because of “groupthink”. But, surely, the reason for putting a carefully thought out strategy document in place, incorporating the lessons from the mistakes made during previous pandemics, was precisely to avoid Government decisions being influenced by groupthink. And that approach was successful until mid-March, at which point Boris Johnson and his closest political allies abandoned it and decided to copy what other Western leaders were doing, i.e. lockdown. In other words, it was groupthink that was responsible for the disastrous U-turn, not the comparatively sensible initial approach.
- One of the main conclusions of the report is that the Government should have locked down earlier than it did – that’s one of the “big mistakes” in all the headlines – and they quote Professor Neil Ferguson to that effect:
The initial U.K. policy was to take a gradual and incremental approach to introducing non-pharmaceutical interventions. A comprehensive lockdown was not ordered until March 23rd 2020 – two months after SAGE first met to consider the national response to COVID- 19. This slow and gradualist approach was not inadvertent, nor did it reflect bureaucratic delay or disagreement between Ministers and their advisers. It was a deliberate policy – proposed by official scientific advisers and adopted by the Governments of all of the nations of the United Kingdom. It is now clear that this was the wrong policy, and that it led to a higher initial death toll than would have resulted from a more emphatic early policy. In a pandemic spreading rapidly and exponentially every week counted. The former SAGE participant Professor Neil Ferguson told the Science and Technology Committee that if the national lockdown had been instituted even a week earlier “we would have reduced the final death toll by at least a half”.
- In fact, it’s far from clear that “this was the wrong policy” or that it “led to a higher initial death toll”. The authors of this report take it for granted that – in the words of Professor David Paton – “governments can turn infections on or off like a tap by imposing or lifting restrictions”, when all the real-world data we’ve accumulated in the past 18 months suggests that is hopelessly naive (see these 30 studies, for instance). Governments around the world, including ours, have been guilty of wildly over-estimating the impact of non-pharmaceutical interventions on the spread of the virus.
- In the British case, there’s no reason to believe that locking down earlier would have reduced the final death toll at all, let alone by half. As David Paton points out, the Czech Republic locked down on March 16th, imposed hard border controls and rolled out the first national mask mandate in Europe. Yet it had a second surge in the Autumn of 2020, prompting it to lock down again, and then an even bigger one in December, leading to a third lockdown. Cases surged again in Czechia in February and March of this year and, six months ago, it had the second-highest per capita Covid death toll in the world, according to Reuters.
More damning still is the comparison with Sweden, which didn’t lock down at all in 2020 and, as of today, is ranked 50th in Worldometers’ table ranking countries according to per capita deaths. The U.K., by contrast, is ranked 25th.
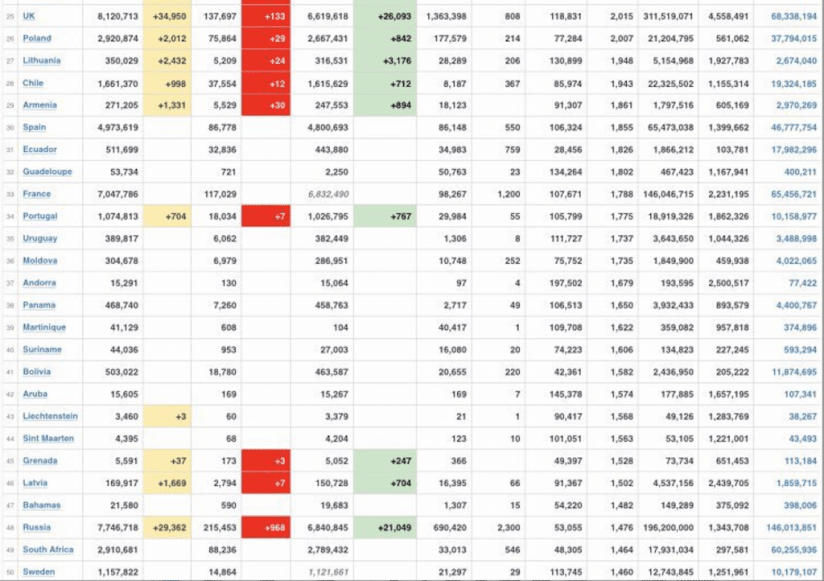
- There are only three mentions of Sweden in this report, two of them in a single footnote. Any assessment of the U.K. Government’s response to the pandemic that fails to compare it with that of the Swedish Government – particularly one advocating we should have locked down sooner and for longer – doesn’t deserve to be taken seriously.
- The report’s authors take at face value the “reasonable worst-case” scenarios that various modellers (including a sidekick of Dominic Cummings’) came up with in mid-March to show that if the Government continued to follow Plan A, i.e. the Pandemic Preparedness Strategy, the NHS was on track to become overwhelmed many times over. Here is Matt Hancock giving evidence on June 8th 2021, appealing to a prediction of “slightly below” 820,000 deaths, absent a lockdown:
I asked for a reasonable worst-case scenario planning assumption. I was given the planning assumption based on Spanish flu, and it was signed off at Cobra on January 31st. That was a planning assumption for 820,000 deaths. […]
In the week beginning March 9th, what happened is that the data started to follow the reasonable worst-case scenario. By the end of that week, the updated modelling showed that we were on the track of something close to that reasonable worst-case scenario. I think the numbers were slightly below that, but they were of a scale that was unconscionable.
- Rather than just take those projections at face value, couldn’t the House of Commons committees have interrogated the models a little bit? The report’s most damning criticism – that the Government’s delay in imposing the first lockdown resulted in thousands of unnecessary deaths – is contingent on not questioning those forecasts. In light of SAGE’s over-estimate of the likely uptick in cases following the easing of restrictions on July 19th of this year, as well as its more recent over-estimate of hospitalisations this autumn, wouldn’t it have been prudent to scrutinise those models? That’s a particularly glaring omission, given that the authors of the report criticise members of the Government for not challenging the scientific advice they were given: “Those in Government have a duty to question and probe the assumptions behind any scientific advice given, particularly in a national emergency, but there is little evidence sufficient challenge took place.” Why do “those in Government” have a duty to do this, but not those serving on select committees who are supposed to be holding the Government to account?
- In case further evidence is required that the authors of the report have credulously lapped up the doom-mongering of SPI-M and others, consider this passage:
It seems astonishing looking back that – despite the documented experiences of other countries; despite the then Secretary of State referring to data with a Reasonable Worst Case Scenario of 820,000 deaths; despite the raw mathematics of a virus which, if it affected two-thirds of the adult population and if one percent of people contracting it died would lead to 400,000 deaths – it was not until March 16th that SAGE advised the Government to embark on a full lockdown (having said on March 13th that “it was unanimous that measures seeking to completely suppress the spread of COVID-19 will cause a second peak”) and not until March 23rd that the Government announced it.
- Note the appeal to an IFR of 1% when even Neil Ferguson’s team at Imperial College, which predicted 510,000 deaths if the Government stuck with Plan A in its famous March 16th paper, assumed an IFR of 0.9%. In fact, a WHO bulletin put the IFR at 0.23% as long ago as October 2020.
- This unwillingness to interrogate the modelling data that underpins the report’s conclusions is particularly odd, given that the authors acknowledge the limitations of modelling elsewhere – “Models can be useful and informative to policymakers, but they come with limitations” – and at one point try to blame the delay in lockdown down on an “overreliance on specific mathematical models”! Again it’s a case of one rule for me and another for thee.
- The report compares the response of the British government in the first months of the pandemic unfavourably to that of various East Asian and South East Asian governments, but overlooks the fact that many Asian countries that successfully suppressed infection by closing borders at the beginning of 2020, and rolling out successful test, trace and isolate programmes, are now in the grip of devastating waves in spite of having vaccinated large swathes of their populations. That suggests their non-pharmaceutical interventions only succeeded in postponing the impact of SARS-CoV-2, not avoiding it. (It also fails to note that these supposed role models didn’t issue stay-at-home orders, close schools or shutter businesses in their initial responses to the pandemic.)
- The report criticises the Government for stopping community testing in March 2020 due to PHE’s lack of testing capacity and praises Matt Hancock for setting the 100,000 tests a day target to galvanise the system into massively ramping up that capacity. Indeed, the authors claim that had a proper test-and-trace system been in place at the beginning of 2020, the initial lockdown might have been avoided. That, too, is a shaky assumption. After all, the Government has spent £37 billion and counting on a ‘world-beating’ test, trace and isolate programme but that didn’t stop us locking down for a second and third time. The authors of the report acknowledge this point, but blame Baroness Harding for not doing a better job of running NHS Test and Trace. That seems a tad harsh, particularly as the authors repeatedly say – Uriah Heap-like – that it’s not their intention to apportion blame for the mistakes they’ve identified.
- The report praises the speed at which the Nightingale hospitals were created, although it acknowledges that, for the most part, they weren’t used. But the reason they weren’t used is partly because the NHS lacked the trained employees to staff them with – ICU nurses, for instance. Perhaps if they’d been built with less speed – at a cost to the taxpayer of roughly half a billion pounds, don’t forget – the Government would have had time to spot this obvious flaw in the plan. Or, more realistically, those aware of it from the start would have had more time to organise and obstruct this expensive PR stunt.
- The authors praise the Government – and the NHS – for at no point running out of ICU beds and becoming overwhelmed, as the health system did in some parts of Italy during the first phase of the pandemic. But given the enormous cost of protecting the NHS – both in terms of seriously ill people who were either discharged or went untreated, as well as the collateral damage inflicted by the lockdowns on the economy, education, family life, mental health, etc. – it’s impossible to say whether prioritising the NHS at the expense of absolutely everything else was in fact the right strategy. To bottom that out you need to do some cost-benefit analysis, of which there is precisely none in this report.
- The report concludes by praising the Vaccine Taskforce under the leadership of Kate Bingham and highlights the ‘success’ of the U.K.’s vaccine programme – “one of the most effective in Europe and, for a country of our size one of the most effective in the world”. But they ignore the fact that the efficacy of the Covid vaccines is much less impressive than the initial trial data indicated and looks less impressive with each passing week, something Dr. Will Jones has been meticulously documenting for the Daily Sceptic. So was the massive Government expenditure on the development and trialling of home grown vaccines, as well as procuring hundreds of millions of vaccines manufactured overseas, worth it? One notable omission from the report is any acknowledgement of the risks associated with a fast-tracked vaccine approval process – it just breathlessly praises the speed with which vaccines were made available to the public and expresses the hope that “in the future this could be conducted in much shorter time still”.
Conclusion
This is a pretty feeble document that seems to have been written with an eye on getting Jeremy Hunt and Greg Clark – the chairs of the two select committees involved – on the BBC news rather than making a serious contribution to understanding what the Government got right and what it got wrong over the past 18 months. It’s hard to argue with some of its findings, but its headline conclusion – that the Government should have locked down earlier – isn’t based on any serious analysis, let alone a careful consideration of the evidence that seems to point in the opposite direction. Talk about groupthink!
I hope the official inquiry, when it comes, is a bit more intellectually weighty than this.
Are leaky vaccines driving delta variant evolution and making it more deadly?
by el gato malo – bad cattitude – october 10, 2021
one of the great fears in any vaccination campaign is that the vaccine can wind up becoming the driver viral evolution and making the virus more dangerous. this is a special concern around imperfect (so called “leaky”) vaccines that are non-sterilizing. such vaccines do not stop spread or contagion of the virus. this means the virus will have lots of chances to replicate.
when you combine this with a vaccine that reduces severity of cases and prevents deaths in the vaccinated, it’s a bit of a perfect storm. you get full spread but break the evolutionary gradient towards mildness that viruses tend to follow (and that protects humanity from them).
all a virus wants is to replicate. “make a copy of me and pass it on.” that’s the biological imperative of the selfish gene. excel at it, you win. fail, you disappear. simple as that.
killing or harming the host is maladaptive to viral spread. it’s like burning down your own house with your car in the garage. now you have nowhere to live and no way to get around. that’s not a recipe for reproductive fitness.
this is a property of the world, not of the viruses themselves. so it applies to all of them, evolved and lab hotwired alike.
so viruses evolve to become less, not more virulent. they do not want to kill you. ideally, they’d like to help you. figure out how to be a useful symbiote, and you get a huge boost in propagation. (mitochondria were probably bacteria that were so useful, all our cells incorporated them.) so seeing case fatality rate (CFR) rise in a variant of a virus is like watching water flow uphill. it’s not supposed to do that and when it does, you need to suspect some external force acting on it.
and we’re seeing water flow uphill here.
i started with the england variants of concern (VoC) data. it’s the best quality and the best broken out. (the US data is just plain broken. it’s being deliberately scrubbed to prevent analysis like this.) because this data is always aggregated from feb to current period, it does not provide good temporal snapshots, but this can be fixed by subtracting the penultimate report from the current one etc. you subtract report 22’s totals from report 23 and you get just what happened in the last 2 weeks (it used to be a weekly report, now it’s bi-weekly)
what we see is not what one would expect from a virus. none of the other variants (pre vaccine) worked like this. none saw CFR rise like this. and no jump from major variant to variant saw a statistically significant rise in deadliness.
this IS however what one would expect if a virus were undergoing vaccine mediated evolution (as mareks disease did in chickens) and selecting for hotter strains because vaccinated people can carry and spread them and not die.
experienced CFR on delta is nearly 7X what it was in the beginning of june and has been galloping since the middle of july.
(note that pretty much all this data has a large artifact in it from the 21 june report (VoC 17). there was a “data-dump” in it where they caught up on a bolus of past data. it’s an artifact, not a signal. best to ignore it. i suspect the curve from mid june to mid july was smooth.)
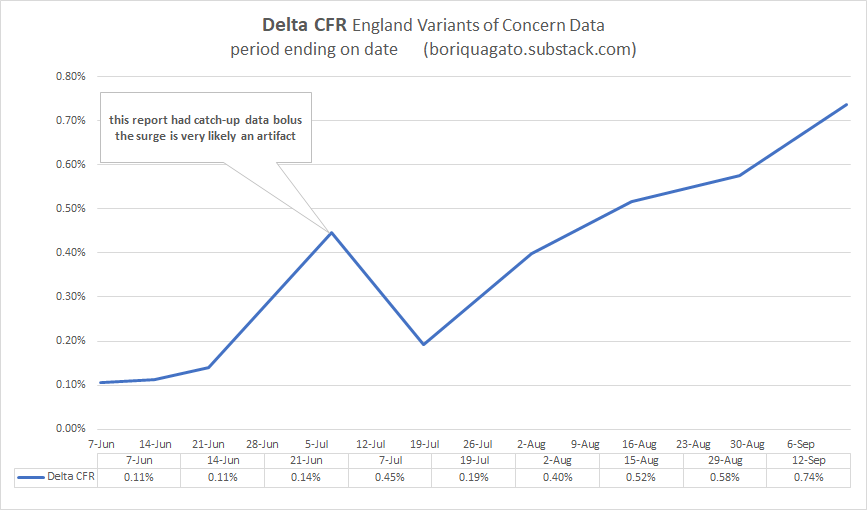
put simply: this is not good.
delta is rapidly approaching alpha (1.1%) in terms of CFR whereas it used to be 90% lower. (it also means that the reports on delta CFR in these VoC updates are FAR too low because they are a blend of all cases and deaths back to feb, so they are averaging in the low CFR past and are slow to respond to current dynamics)
this is consistent with, but not proof of vaccines mediated evolution. to get there, we need to do better.
so now we need to start ruling things out and validating this claim to see if it’s meaningful.
first, it’s not a simpson’s paradox in age data. CFR is rising in over and under 50’s. it’s not mix shift alone. CFR in over 50’s is up 2.5X. it’s up 4-7X in under 50’s.
we’re at about a 3X rise in CFR overall in delta since the summer once we adjust for shifts in age. not as worrying as 7, but still worrying.
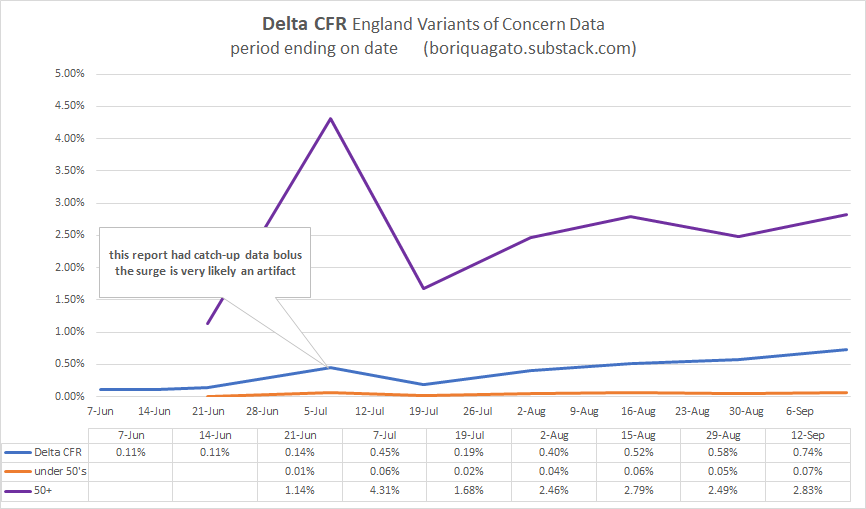
and the deaths are real. it’s not made up counting. this can be clearly seen when we comp CFR to the euro-momo Z scores (thoughtfully provided by frequent gato collaborator ben m at USmortality.com. z score is just a measure of deviation from expected all cause deaths. (explained HERE)
alignment is quite strong.
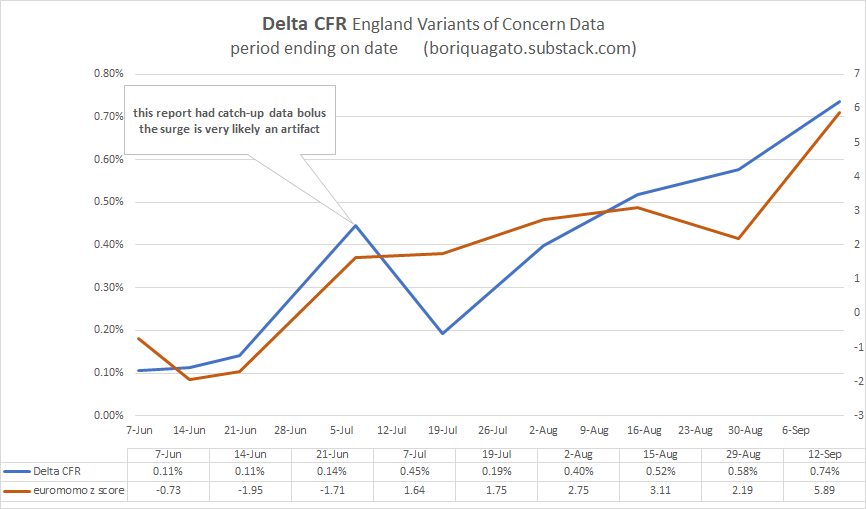
z score was trending negative and spiked to high levels just as CFR really started to ramp up.
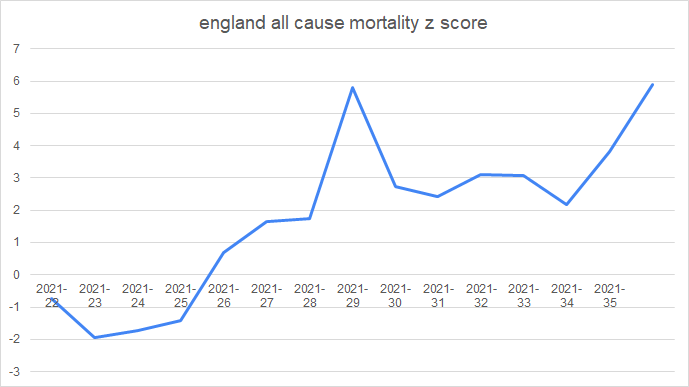
z score for the year can be seen here. starting in wk 22 (may 31) (numbers after the year are weeks)
and given that we know that vaccines DO work to stop deaths in the UK (seemingly in the 50-60% range) it’s even more unexpected that CFR would be rising like this. but it is and the rise in the vaxx rate is not hampering it.
(the precise alignment here is more chart crime than signal, so i’d caution against inferring too much from it)
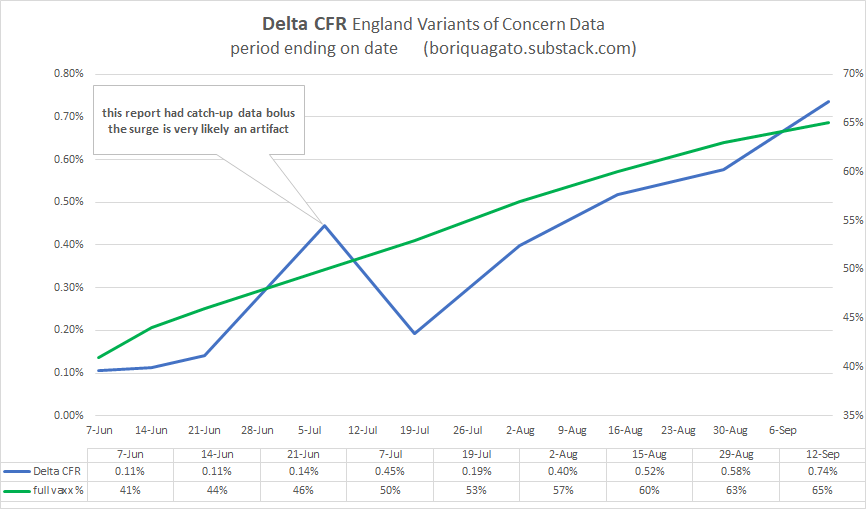
none of this is what one would expect. not remotely. it bucks evolution, it bucks the other variants, and it flies in the face of late stage pandemic dynamics like increase in acquired immunity (which IS sterilizing), depletion of high risk cohorts, improvements in treatment, etc. all these should be pushing CFR down.
instead, water is flowing uphill.
the question is “why?”
the other day, i discussed ADE (antibody dependent enhancement) where antibodies wind up acting as passkeys for a virus to enter cells and also the fetchingly biblically named OAS (original antigenic sin) whereby preferential training to one antibody response leads to its use against new variants of a pathogen and thereby prevents adaptation to more effective modalities.
note that these two phenomena are by no means mutually exclusive and are actually strongly synergistic.
but are they driving this issue?
i do not not think so.
- if they were, we’d be seeing the CFR rise in the vaccinated but not in the unvaccinated and if it were ALL antibodies, we’d be seeing the previously infected getting hit too. but they are not.
- we’d also likely be seeing low or negative vaccine efficacy (VE) for deaths. but we aren’t. it’s clear the vaccinated are doing better.
CFR is (and has been) much better in the vaccinated than the unvaxxed in UK over 50’s (the highest risk category). trends are similar, but absolute values durably disparate.
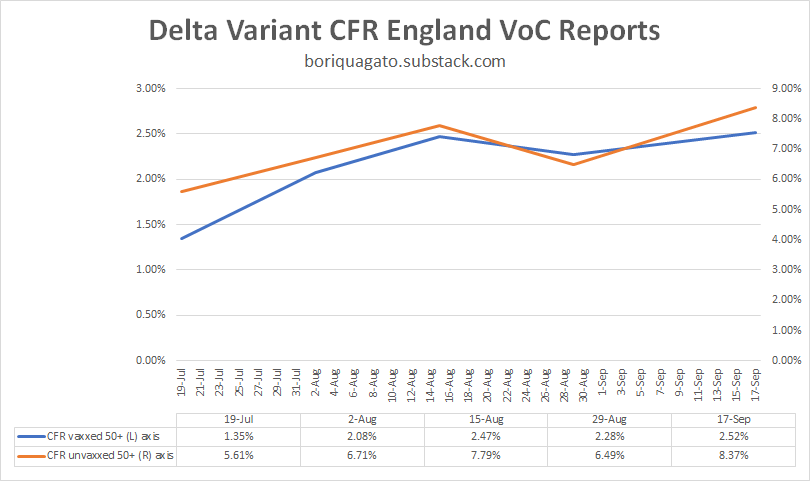
whether and to what extent this is real vaccine efficacy vs cohort bias in a place where 90% of this demographic is vaccinated remains an open issue. it may simply be that only those with the weakest/most compromised immunes systems have not gotten the jab. but this is not really material here.
what IS material is the fact that CFR in the unvaxxed is trending up significantly and so is CFR in the vaxxed. but we’re not seeing many cases of re-infection and almost none of those are serious. this does not look like ADE or OAS as a major driver. if it were, there’s no reason the CFR in the unvaccinated would be rising too.
what this IS consistent with is a variant heating up and getting more and more deadly because it is not checked by normal biological limitations. vaccine mediated evolution (VME) would be very bad news for us.
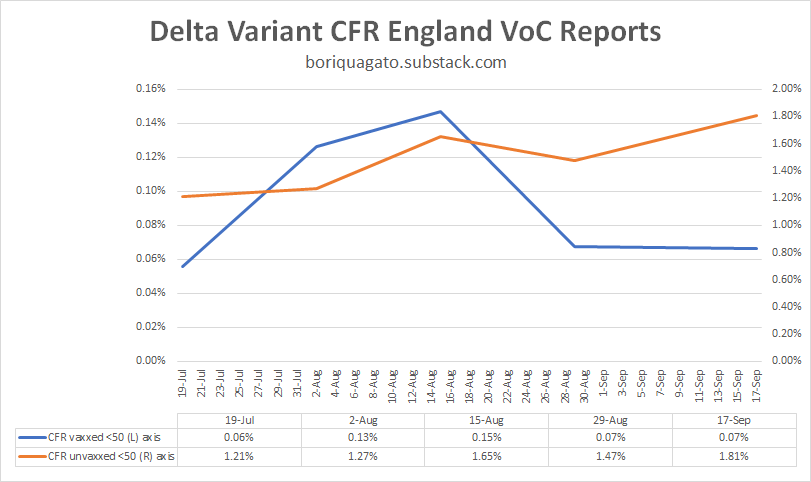
we can see similar in the under 50’s, though the data here is a bit of a mess as during this period, so many very low risk under 50’s (those under 18) got vaccinated that it moved a material risk profile reduction from unvaxxed to vaxxed. i suspect that is why “CFR vaxxed” dropped. it was not vaccines working, it was the vaccinated category being “salted” with large number of the lowest risk folks around. (it also means that group left the unvaxxed, so you get an effect on both)
so i view this data as much lower quality than over 50’s, but it still looks like VME, not ADE or OAS.
this is EXACTLY what leaky vaccines did in chickens.
(read these links. THIS in particular. it’s important.)
such vaccines change the evolutionary gradient for a virus. instead of becoming less virulent/deadly, they can tend the other way because the maladaptiveness of killing the host is mitigated in the vaccinated population. this is what happened with marek’s disease in chickens.
not only is it now more lethal to them than ebola is to humans, making it one of if not THE hottest persistent disease known (killing 100% of unvaxxed birds in 10 days), but, it’s now a disease so hot that an unvaccinated chicken cannot spread it. they die too quickly. only the vaccinated birds spread the nasty strains of mareks. they’re the only ones who live long enough to shed virus.
“Previously, a hot strain was so nasty, it wiped itself out. Now, you keep its host alive with a vaccine, then it can transmit and spread in the world,” Read said. “So it’s got an evolutionary future, which it didn’t have before.”

this is an awful lot of puzzle pieces snapping together and i think we’re really starting to see what this is a picture of.
leaky vaccines that stop severe illness and death but not spread look to be affecting the evolution of the covid 19 virus.
this is an established, predictable, and well supported risk from such vaccines.
this has become my leading hypothesis.
it also explains why we’re seeing such a large rise in deaths relative to cases and deaths and hospitalization overall in so many places. it’s the virus adapting to a stressor we put on it and becoming much more dangerous as a result.
the CFR is a function of the virus, but the virus has become a function of the leaky vaccines.
and it also means the vaccine is protecting no one. yes, it seems to have 50-60% protection against death. but what good is that against a CFR that’s up 300% or more (and rising)? everyone is worse off.

negative VE’s on spread are accelerating cases and this is multiplicative with higher CFR. this is the nightmare scenario and no one is left better off as a result. the CFR among the high risk vaccinated groups is way up too.
everyone is harmed but the brunt is borne by the unvaccinated which perversely winds up looking like better vaccine efficacy. the very fact that vaccines made everyone worse off but spread the misery unevenly makes it look like vaccines are a good idea.
it’s just simple math. if we do something to one group that makes their death rate rise from 1 to 2 per 100 but that also makes the death rate in another group rise from 1 to 4 per 100, that looks like a VE of 50%. in reality, it’s killing 100% more vaxxed people and 300% more of the unvaxxed.
mistaking that gas pedal for the brake and pushing ever harder when you fail to slow would represent an accelerating disaster curve.
that’s the problem with relative measures that ignore absolute changes. you can hide all manner of calamity in such analyses.
it’s still, of course, possible that i’m wrong, but this is looking more and more like it has to be the answer. i can find nothing else fits the facts and the facts themselves are weird enough that “it’s just normal” does not look like a satisfying explanation either and we have enough features here that we can really start testing our puzzle pieces. this one aligns in an AWFUL lot of places.
for something this odd to happen, it takes a truly uncommon exogenous stressor.
i’m just not seeing what else it could be than vaccine mediated selection for hotter variants driving pernicious delta evolution.
so, i’m putting this out to you all to see if you can find some other explanation for what’s going on that fits these facts.
looking forward to the peer review as, honestly, i hope i’m wrong here. this is not an outcome that anyone wants. it’s the nightmare scenario both as a pandemic and as a political horror in the making as if this was an “own-goal”, what would the experts and politicians that pushed this plan not be willing to do to avoid accepting the blame?
because this is career or pharma franchise polonium, and that’s if you’re lucky.
let’s keep at this. one way or the other, we need to know.
the facts do not care about our feelings and epidemiology data is a lousy fabric from which to spin a wubbie to hide under.
we need to get at the truth.
(even if it makes us make a face like this)
Australia Building Quarantine Camps For “Ongoing Operations”

By Paul Joseph Watson | Summit News | October 12, 2021
Despite some states tentatively beginning to lift lockdown restrictions, Australian authorities are building quarantine camps that won’t be completed until next year in order to prepare for “ongoing operations” and to house those “who have not had access to vaccination.”
According to ABC Australia, one such 1,000-bed quarantine facility at Wellcamp Airport outside Toowoomba will be fully completed by the end of March 2022.
“At this stage, the cabins will be used by domestic travellers returning from COVID hotspots,” states the report.
However, it also makes clear that the camp will be used for “ongoing operations” and will be a source of employment for the local area.
The camps is split into different zones and accommodates singles, doubles, and family rooms while being patrolled by police and security guards 24/7.
Citing new strains of COVID and people “who have not had access to vaccination,” Queensland Deputy Premier Steven Miles told the media outlet, “We anticipate there to be a continuing need for quarantine facilities.”
The government is leasing the land on which the camp is being built from the Wagner Corporation for 12 months with an option for a further 12 months after that.
Another 1,000-bed quarantine facility is also being built on a 30-hectare Army barracks site in the industrial area of Pinkenba, near Brisbane Airport.
“Why anyone who had left Australia would come back again is unclear,” writes Dave Blount. “It is possibly the most repressive country in the world regarding Covid tyranny.”
As we previously highlighted, state authorities in America are also constructing new “quarantine facilities” for Americans who are “unable to quarantine at home.”
As we reported last year, Authorities in Quebec City, Canada announced they will isolate “uncooperative” citizens in a coronavirus facility, the location of which remains a secret.
New Zealand also announced plans to place COVID infectees and their family members in “quarantine facilities.”
Back in January, German authorities also announced they would hold COVID dissidents who repeatedly fail to properly follow the rules in what was described as a ‘detention camp’ located in Dresden.
The Great New Normal Purge
By CJ Hopkins | The Consent Factory | October 12, 2021
So, the Great New Normal Purge has begun … right on cue, right by the numbers.
As we “paranoid conspiracy theorists” have been warning would happen for the past 18 months, people who refuse to convert to the new official ideology are now being segregated, stripped of their jobs, banned from attending schools, denied medical treatment, and otherwise persecuted.
Relentless official propaganda demonizing “the Unvaccinated” is being pumped out by the corporate and state media, government leaders, health officials, and shrieking fanatics on social media. “The Unvaccinated” are the new official “Untermenschen,” an underclass of subhuman “others” the New Normal masses are being conditioned to hate.
But it isn’t just a purge of “the Unvaccinated.” Anyone deviating from the official ideology is being systematically demonized and persecuted. In Germany, Australia, and other New Normal countries, protesting the New Normal is officially outlawed. The New Normal Gestapo is going around to people’s homes to interrogate them about their anti-New Normal Facebook posts. Corporations are openly censoring content that contradicts the official narrative. New Normal goon squads roam the streets, checking people’s “vaccination” papers.
And it’s not just governments and corporations carrying out the New Normal Purge. Friends are purging friends. Wives are purging husbands. Fathers are purging children. Children are purging parents. New Normals are purging old normal thoughts. Global “health authorities” are revising definitions to make them conform to New Normal “science.”
And so on … a new official “reality” is being manufactured, right before our eyes. Anything and anyone that doesn’t conform to it is being purged, unpersoned, memory-holed, erased.
None of which should come as a surprise.
Every nascent totalitarian system, at some stage of its takeover of society, launches a purge of political opponents, ideological dissidents, and other “anti-social deviants.” Such purges can be brief or open-ended, and they can take any number of outward forms, depending on the type of totalitarian system, but you cannot have totalitarianism without them.
The essence of totalitarianism — regardless of which costumes and ideology it wears — is a desire to completely control society, every aspect of society, every individual behavior and thought. Every totalitarian system, whether an entire nation, a tiny cult, or any other form of social body, evolves toward this unachievable goal … the total ideological transformation and control of every single element of society (or whatever type of social body it comprises). This fanatical pursuit of total control, absolute ideological uniformity, and the elimination of all dissent, is what makes totalitarianism totalitarianism.
Thus, each new totalitarian system, at some point in its evolution, needs to launch a purge of those who refuse to conform to its official ideology. It needs to do this for two basic reasons: (1) to segregate or otherwise eliminate actual political opponents and dissidents who pose a threat to the new regime; and (2) and more importantly, to establish the ideological territory within which the masses must now confine themselves in order to avoid being segregated, or eliminated.
The purge must be conducted openly, brutally, so that the masses understand that the rules of society have changed, forever, that their former rights and freedoms are gone, and that from now on any type of resistance or deviation from official ideology will not be tolerated, and will be ruthlessly punished.
The purge is usually launched during a “state of emergency,” under imminent threat from some official “enemy” (e.g., “communist infiltrators,” “counter-revolutionaries,” or … you know, a “devastating pandemic”), such that the normal rules of society can be indefinitely suspended “for the sake of survival.” The more terrified the masses can be made, the more willing they will be to surrender their freedom and follow orders, no matter how insane.
The lifeblood of totalitarianism is fear … fear of both the system’s official enemy (which is constantly stoked with propaganda) and of the totalitarian system itself. That the brutality of the system is rationalized by the threat posed by the official enemy doesn’t make it any less brutal or terrifying. Under totalitarian systems (of any type or scale) fear is a constant and there is no escape from it.
The masses’ fear is then channeled into hatred … hatred of the official “Untermenschen,” whom the system encourages the masses to scapegoat. Thus, the purge is also a means of allowing the masses to purge themselves of their fear, to transform it into self-righteous hatred and unleash it on the “Untermenschen” instead of the totalitarian system, which, obviously, would be suicidal.
Every totalitarian system — both the individuals running it and the system, structurally — instinctively understands how all this works. New Normal totalitarianism is no exception.
Just reflect on what has happened over the last 18 months.
Day after day, month after month, the masses have been subjected to the most destructive psychological-terror campaign in the history of psychological terror. Sadly, many of them have been reduced to paranoid, anus-puckering invalids, afraid of the outdoors, of human contact, afraid of their own children, afraid of the air, morbidly obsessed with disease and death … and consumed with hatred of “the Unvaccinated.”
Their hatred, of course, is utterly irrational, the product of fear and propaganda, as hatred of “the Untermenschen” always is. It has absolutely nothing to do with a virus, which even the New Normal authorities admit. “The Unvaccinated” are no more of a threat to anyone than any other human being … except insofar as they threaten the New Normals’ belief in their delusional ideology.
No, we are way past rationality at this point. We are witnessing the birth of a new form of totalitarianism. Not “communism.” Not “fascism.” Global-capitalist totalitarianism. Pseudo-medical totalitarianism. Pathologized totalitarianism. A form of totalitarianism without a dictator, without a definable ideology. A totalitarianism based on “science,” on “fact,” on “reality,” which it creates itself.
I don’t know about you, but, so far, it has certainly made quite an impression on me. So much so that I have mostly set aside my satirical schtick to try to understand it … what it actually is, why it is happening, why it is happening now, where it is going, and how to oppose it, or at least disrupt it.
The way I see it, the next six months will determine how successful the initial stages of the roll-out of this new totalitarianism will be. By April of 2022, either we’ll all be showing our “papers” to the New Normal Gestapo to be able to earn a living, attend a school, dine at a restaurant, travel, and otherwise live our lives, or we will have thrown a monkey wrench into the machinery. I do not expect GloboCap to abandon the roll-out of the New Normal over the longer term — they are clearly committed to implementing it — but we have the power to ruin their opening act (which they’ve been planning and rehearsing for quite some time).
So, let’s go ahead and do that, shall we? Before we get purged, or unpersoned, or whatever. I’m not sure, as I haven’t seen a “fact-check” yet, but I believe there are some commercial airline pilots in the USA who are showing us the way.
#
Sen. Ron Johnson Shares COVID-19 Data from Public Health England, Refutes “Pandemic of The Unvaccinated” Narrative
The Last Refuge | October 3, 2021
Senator Ron Johnson (R-Wisconsin) used his time on the Senate floor to discuss recently released COVID-19 data from Public Health England in the U.K. [DATA pdf Here]
Ironically, Senator Johnson is forced to use the Senate floor to share the information in an effort to stop government and Big Tech censorship of the discussion. Unlike the rest of the nation, the House and Senate chamber rules create a free speech zone that prohibits anyone from censoring congressional debate and discussion.
Senator Johnson outlines data from the U.K. clearly showing the vaccines offer no protection from the claimed Delta variant. COVID-19 is carried and shed by vaccinated individuals. The subsequent rate of COVID-19 hospitalization and COVID-19 death appears unaffected by the vaccine itself. WATCH:
As Senator Johnson notes: 63% of the deaths in the U.K. during the 7 month period being discussed were among the vaccinated population.
The data Ron Johnson is sharing is available HERE in pdf form
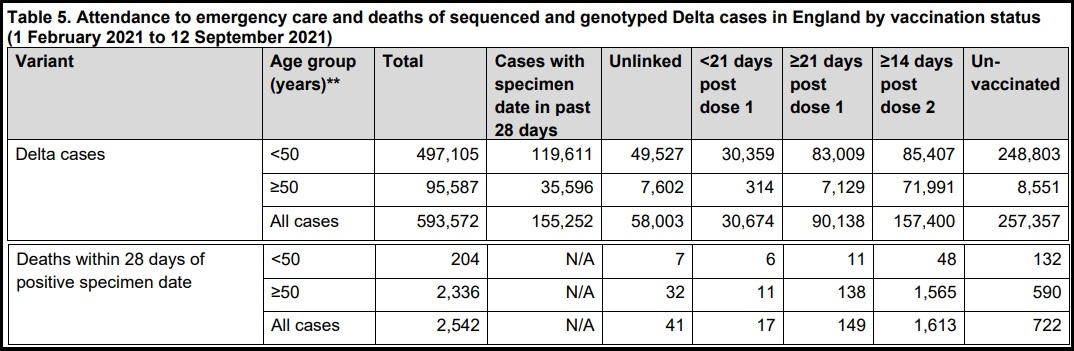
SOURCE: Page 19, 20 – Table 5

Natural Immunity and Covid-19: Twenty-Nine Scientific Studies to Share with Employers, Health Officials, and Politicians
BROWNSTONE INSTITUTE | OCTOBER 10, 2021
From the beginning of the March 2020 lockdowns for the SARS-CoV-2 virus, the subject of natural immunity (also called post-infection immunity) has been neglected. Once the vaccination became widely available, what began with near silence at the beginning turned nearly into a complete blackout of the topic.
Even now, there is an absence of open discussion, presumably in the interests of promoting universal vaccination and required documentation of such vaccination as a condition of participating in public life and even the jobs marketplace. Still, the science exists. Many studies exist. Their authors deserve credit, recognition, and to have their voices heard.
These studies demonstrate what was and is already known: natural immunity for a SARS-type virus is robust, long-lasting, and broadly effective even in the case of mutations, generally more so than vaccines. In fact, a major contribution of 20th-century science has been to expand upon and further elucidate this principle that has been known since the ancient world. Every expert presumably knew this long before the current debates. The effort to pretend otherwise is a scientific scandal of the highest order, especially because the continued neglect of the topic is affecting the rights and freedoms of billions of people.
People who have contracted the virus and recovered deserve recognition. For that matter, people who prefer an exposure risk to the virus in order to gain robust immunity deserve the freedom to make that choice. The realization that natural immunity – which pertains now to perhaps half of the US population and billions around the world – is effective in providing protection should have a dramatic effect on vaccine mandates.
Individuals whose livelihoods and liberties are being deprecated and deleted need access to the scientific literature as it pertains to this virus. They should send a link to this page far and wide. The scientists have not been silent; they just haven’t received the public attention they deserve. The preparation of this list was assisted by links provided by Paul Elias Alexander and Rational Ground’s own cheat sheet on natural immunity, which also includes links to popular articles on the topic.
1. One-year sustained cellular and humoral immunities of COVID-19 convalescents, by Jie Zhang, Hao Lin, Beiwei Ye, Min Zhao, Jianbo Zhan, et al. Clinical Infectious Diseases, October 5, 2021. “SARS-CoV-2-specific IgG antibodies, and also NAb can persist among over 95% COVID-19 convalescents from 6 months to 12 months after disease onset. At least 19/71 (26%) of COVID-19 convalescents (double positive in ELISA and MCLIA) had detectable circulating IgM antibody against SARS-CoV-2 at 12m post-disease onset. Notably, the percentages of convalescents with positive SARS-CoV-2-specific T-cell responses (at least one of the SARS-CoV-2 antigen S1, S2, M and N protein) were 71/76 (93%) and 67/73 (92%) at 6m and 12m, respectively. Furthermore, both antibody and T-cell memory levels of the convalescents were positively associated with their disease severity.”
2. Comparing SARS-CoV-2 natural immunity to vaccine-induced immunity: reinfections versus breakthrough infections, by Sivan Gazit, Roei Shlezinger, Galit Perez, Roni Lotan, Asaf Peretz, Amir Ben-Tov, Dani Cohen, Khitam Muhsen, Gabriel Chodick, Tal Patalon. MedRxiv, August 25, 2021. “Our analysis demonstrates that SARS-CoV-2-naïve vaccinees had a 13.06-fold increased risk for breakthrough infection with the Delta variant compared to those previously infected, when the first event (infection or vaccination) occurred during January and February of 2021. The increased risk was significant for a symptomatic disease as well…. This analysis demonstrated that natural immunity affords longer lasting and stronger protection against infection, symptomatic disease and hospitalization due to the Delta variant of SARS-CoV-2, compared to the BNT162b2 two-dose vaccine-induced immunity.”
3. Shedding of Infectious SARS-CoV-2 Despite Vaccination, by Kasen K. Riemersma, Brittany E. Grogan, Amanda Kita-Yarbro, Gunnar E. Jeppson, David H. O’Connor, Thomas C. Friedrich, Katarina M. Grande, MedRxiv, August 24, 2021. “The SARS-CoV-2 Delta variant might cause high viral loads, is highly transmissible, and contains mutations that confer partial immune escape. Outbreak investigations suggest that vaccinated persons can spread Delta. We compared RT-PCR cycle threshold (Ct) data from 699 swab specimens collected in Wisconsin 29 June through 31 July 2021 and tested with a qualitative assay by a single contract laboratory. Specimens came from residents of 36 counties, most in southern and southeastern Wisconsin, and 81% of cases were not associated with an outbreak. During this time, estimated prevalence of Delta variants in Wisconsin increased from 69% to over 95%. Vaccination status was determined via self-reporting and state immunization records.”
4. Necessity of COVID-19 vaccination in previously infected individuals, by Nabin K. Shrestha, Patrick C. Burke, Amy S. Nowacki, Paul Terpeluk, Steven M. Gordon, MedRxiv, June 5, 2021. “Individuals who have had SARS-CoV-2 infection are unlikely to benefit from COVID-19 vaccination, and vaccines can be safely prioritized to those who have not been infected before.”
5. Large-scale study of antibody titer decay following BNT162b2 mRNA vaccine or SARS-CoV-2 infection, by Ariel Israel, Yotam Shenhar, Ilan Green, Eugene Merzon, Avivit Golan-Cohen, Alejandro A Schäffer, Eytan Ruppin, Shlomo Vinker, Eli Magen. MedRxiv, August 22, 2021. “This study demonstrates individuals who received the Pfizer-BioNTech mRNA vaccine have different kinetics of antibody levels compared to patients who had been infected with the SARS-CoV-2 virus, with higher initial levels but a much faster exponential decrease in the first group.”
6. Discrete Immune Response Signature to SARS-CoV-2 mRNA Vaccination Versus Infection, by Ellie Ivanova, Joseph Devlin, et al. Cell, May 2021. “While both infection and vaccination induced robust innate and adaptive immune responses, our analysis revealed significant qualitative differences between the two types of immune challenges. In COVID-19 patients, immune responses were characterized by a highly augmented interferon response which was largely absent in vaccine recipients.”
7. SARS-CoV-2 infection induces long-lived bone marrow plasma cells in humans, by Jackson S. Turner, Wooseob Kim, Elizaveta Kalaidina, Charles W. Goss, Adriana M. Rauseo, Aaron J. Schmitz, Lena Hansen, Alem Haile, Michael K. Klebert, Iskra Pusic, Jane A. O’Halloran, Rachel M. Presti, Ali H. Ellebedy. Nature, May 24, 2021. “This study sought to determine whether infection with SARS-CoV-2 induces antigen-specific long-lived BMPCs in humans. We detected SARS-CoV-2 S-specific BMPCs in bone marrow aspirates from 15 out of 19 convalescent individuals, and in none from the 11 control participants…. Overall, our results are consistent with SARS-CoV-2 infection eliciting a canonical T-cell-dependent B cell response, in which an early transient burst of extrafollicular plasmablasts generates a wave of serum antibodies that decline relatively quickly. This is followed by more stably maintained levels of serum antibodies that are supported by long-lived BMPCs.”
8. Longitudinal analysis shows durable and broad immune memory after SARS-CoV-2 infection with persisting antibody responses and memory B and T cells, by Kristen W. Cohen, Susanne L. Linderman, Zoe Moodie, Julie Czartoski, Lilin Lai, Grace Mantus, Carson Norwood, Lindsay E. Nyhoff, Venkata Viswanadh Edara, et al. MedRxiv, April 27, 2021. “Ending the COVID-19 pandemic will require long-lived immunity to SARS-CoV-2. We evaluated 254 COVID-19 patients longitudinally from early infection and for eight months thereafter and found a predominant broad-based immune memory response. SARS-CoV-2 spike binding and neutralizing antibodies exhibited a bi-phasic decay with an extended half-life of >200 days suggesting the generation of longer-lived plasma cells. In addition, there was a sustained IgG+ memory B cell response, which bodes well for a rapid antibody response upon virus re-exposure.”
9. Incidence of Severe Acute Respiratory Syndrome Coronavirus-2 infection among previously infected or vaccinated employees, by N Kojima, A Roshani, M Brobeck, A Baca, JD Klausner. MedRxiv, July 8, 2021. “Previous SARS-CoV-2 infection and vaccination for SARS-CoV-2 were associated with decreased risk for infection or re-infection with SARS-CoV-2 in a routinely screened workforce. The was no difference in the infection incidence between vaccinated individuals and individuals with previous infection. Further research is needed to determine whether our results are consistent with the emergence of new SARS-CoV-2 variants.”
10. Single cell profiling of T and B cell repertoires following SARS-CoV-2 mRNA vaccine, by Suhas Sureshchandra, Sloan A. Lewis, Brianna Doratt, Allen Jankeel, Izabela Ibraim, Ilhem Messaoudi. BioRxiv, July 15, 2021. “Interestingly, clonally expanded CD8 T cells were observed in every vaccinee, as observed following natural infection. TCR gene usage, however, was variable, reflecting the diversity of repertoires and MHC polymorphism in the human population. Natural infection induced expansion of larger CD8 T cell clones occupied distinct clusters, likely due to the recognition of a broader set of viral epitopes presented by the virus not seen in the mRNA vaccine. Our study highlights a coordinated adaptive immune response where early CD4 T cell responses facilitate the development of the B cell response and substantial expansion of effector CD8 T cells, together capable of contributing to future recall responses.”
11. mRNA vaccine-induced T cells respond identically to SARS-CoV-2 variants of concern but differ in longevity and homing properties depending on prior infection status, Jason Neidleman, Xiaoyu Luo, Matthew McGregor, Guorui Xie, Victoria Murray, Warner C. Greene, Sulggi A. Lee, Nadia R. Roan. BioRxiv, July 29, 2021. “In infection-naïve individuals, the second dose boosted the quantity and altered the phenotypic properties of SARS-CoV-2-specific T cells, while in convalescents the second dose changed neither. Spike-specific T cells from convalescent vaccinees differed strikingly from those of infection-naïve vaccinees, with phenotypic features suggesting superior long-term persistence and ability to home to the respiratory tract including the nasopharynx. These results provide reassurance that vaccine-elicited T cells respond robustly to emerging viral variants, confirm that convalescents may not need a second vaccine dose, and suggest that vaccinated convalescents may have more persistent nasopharynx-homing SARS-CoV-2-specific T cells compared to their infection-naïve counterparts.”
12. Immunological memory to SARS-CoV-2 assessed for up to 8 months after infection, Jennifer M. Dan, Jose Mateus, Yu Kato, Kathryn M. Hastie, et al., Science, January 6, 2021. “Understanding immune memory to SARS-CoV-2 is critical for improving diagnostics and vaccines, and for assessing the likely future course of the COVID-19 pandemic. We analyzed multiple compartments of circulating immune memory to SARS-CoV-2 in 254 samples from 188 COVID-19 cases, including 43 samples at ≥ 6 months post-infection. IgG to the Spike protein was relatively stable over 6+ months. Spike-specific memory B cells were more abundant at 6 months than at 1 month post symptom onset. SARS-CoV-2-specific CD4+ T cells and CD8+ T cells declined with a half-life of 3-5 months. By studying antibody, memory B cell, CD4+ T cell, and CD8+ T cell memory to SARS-CoV-2 in an integrated manner, we observed that each component of SARS-CoV-2 immune memory exhibited distinct kinetics.”
13. Persistence of neutralizing antibodies a year after SARS-CoV-2 infection, by Anu Haveri, Nina Ekström, Anna Solastie, Camilla Virta, Pamela Österlund, Elina Isosaari, Hanna Nohynek, Arto A. Palmu, Merit Melin. MedRxiv, July 16, 2021. “We assessed the persistence of serum antibodies following wild-type SARS-CoV-2 infection six and twelve months after diagnosis in 367 individuals of whom 13% had severe disease requiring hospitalization. We determined the SARS-CoV-2 spike (S-IgG) and nucleoprotein IgG concentrations and the proportion of subjects with neutralizing antibodies (NAb).”
14. Quantifying the risk of SARS‐CoV‐2 reinfection over time, by Eamon O Murchu, Paula Byrne, Paul G. Carty, et al. Rev Med Virol. 2021. “Reinfection was an uncommon event (absolute rate 0%–1.1%), with no study reporting an increase in the risk of reinfection over time. Only one study esti- mated the population‐level risk of reinfection based on whole genome sequencing in a subset of patients; the estimated risk was low (0.1% [95% CI: 0.08–0.11%]) with no evidence of waning immunity for up to 7 months following primary infection. These data suggest that naturally acquired SARS‐CoV‐2 immunity does not wane for at least 10 months post‐infection. However, the applicability of these studies to new variants or to vaccine‐induced immunity remains uncertain.”
15. SARS-CoV-2 antibody-positivity protects against reinfection for at least seven months with 95% efficacy, by Laith J. Abu-Raddad, Hiam Chemaitelly, Peter Coyle, Joel A. Malek. The Lancet, July 27, 2021. “Reinfection is rare in the young and international population of Qatar. Natural infection appears to elicit strong protection against reinfection with an efficacy ~95% for at least seven months.”
16. Natural immunity against COVID-19 significantly reduces the risk of reinfection: findings from a cohort of sero-survey participants, by Bijaya Kumar Mishra, Debdutta Bhattacharya, Jaya Singh Kshatri, Sanghamitra Pati. MedRxiv, July 19, 2021. “These findings reinforce the strong plausibility that development of antibody following natural infection not only protects against re-infection by the virus to a great extent, but also safeguards against progression to severe COVID-19 disease.”
17. Protection of previous SARS-CoV-2 infection is similar to that of BNT162b2 vaccine protection: A three-month nationwide experience from Israel, by Yair Goldberg, Micha Mandel, Yonatan Woodbridge, Ronen Fluss, Ilya Novikov, Rami Yaari, Arnona Ziv, Laurence Freedman, Amit Huppert, et al.. MedRxiv, April 24, 2021. “Similarly, the overall estimated level of protection from prior SARS-CoV-2 infection for documented infection is 94·8% (CI:[94·4, 95·1]); hospitalization 94·1% (CI:[91·9, 95·7]); and severe illness 96·4% (CI:[92·5, 98·3]). Our results question the need to vaccinate previously-infected individuals.”
18. Immune Memory in Mild COVID-19 Patients and Unexposed Donors Reveals Persistent T Cell Responses After SARS-CoV-2 Infection, by Asgar Ansari, Rakesh Arya, Shilpa Sachan, Someshwar Nath Jha, Anurag Kalia, Anupam Lall, Alessandro Sette, et al. Front Immunol. March 11, 2021. “Using HLA class II predicted peptide megapools, we identified SARS-CoV-2 cross-reactive CD4+ T cells in around 66% of the unexposed individuals. Moreover, we found detectable immune memory in mild COVID-19 patients several months after recovery in the crucial arms of protective adaptive immunity; CD4+ T cells and B cells, with a minimal contribution from CD8+ T cells. Interestingly, the persistent immune memory in COVID-19 patients is predominantly targeted towards the Spike glycoprotein of the SARS-CoV-2. This study provides the evidence of both high magnitude pre-existing and persistent immune memory in Indian population.”
19. Live virus neutralisation testing in convalescent patients and subjects vaccinated against 19A, 20B, 20I/501Y.V1 and 20H/501Y.V2 isolates of SARS-CoV-2, by Claudia Gonzalez, Carla Saade, Antonin Bal, Martine Valette, et al, MedRxiv, May 11, 2021. “ No significant difference was observed between the 20B and 19A isolates for HCWs with mild COVID-19 and critical patients. However, a significant decrease in neutralisation ability was found for 20I/501Y.V1 in comparison with 19A isolate for critical patients and HCWs 6-months post infection. Concerning 20H/501Y.V2, all populations had a significant reduction in neutralising antibody titres in comparison with the 19A isolate. Interestingly, a significant difference in neutralisation capacity was observed for vaccinated HCWs between the two variants whereas it was not significant for the convalescent groups.”
20. Highly functional virus-specific cellular immune response in asymptomatic SARS-CoV-2 infection, by Nina Le Bert, Hannah E. Clapham, Anthony T. Tan, Wan Ni Chia, et al, Journal of Experimental Medicine, March 1, 2021. “Thus, asymptomatic SARS-CoV-2–infected individuals are not characterized by weak antiviral immunity; on the contrary, they mount a highly functional virus-specific cellular immune response.”
21. SARS-CoV-2-specific T cell memory is sustained in COVID-19 convalescent patients for 10 months with successful development of stem cell-like memory T cells, Jae Hyung Jung, Min-Seok Rha, Moa Sa, Hee Kyoung Choi, Ji Hoon Jeon, et al, Nature Communications, June 30, 2021. “In particular, we observe sustained polyfunctionality and proliferation capacity of SARS-CoV-2-specific T cells. Among SARS-CoV-2-specific CD4+ and CD8+ T cells detected by activation-induced markers, the proportion of stem cell-like memory T (TSCM) cells is increased, peaking at approximately 120 DPSO. Development of TSCM cells is confirmed by SARS-CoV-2-specific MHC-I multimer staining. Considering the self-renewal capacity and multipotency of TSCM cells, our data suggest that SARS-CoV-2-specific T cells are long-lasting after recovery from COVID-19, thus support the feasibility of effective vaccination programs as a measure for COVID-19 control.”
22. Antibody Evolution after SARS-CoV-2 mRNA Vaccination, by Alice Cho, Frauke Muecksch, Dennis Schaefer-Babajew, Zijun Wang, et al, BioRxiv, et al, BioRxiv, July 29, 2021. “We conclude that memory antibodies selected over time by natural infection have greater potency and breadth than antibodies elicited by vaccination. These results suggest that boosting vaccinated individuals with currently available mRNA vaccines would produce a quantitative increase in plasma neutralizing activity but not the qualitative advantage against variants obtained by vaccinating convalescent individuals.” Newer version reads: “These results suggest that boosting vaccinated individuals with currently available mRNA vaccines will increase plasma neutralizing activity but may not produce antibodies with breadth equivalent to those obtained by vaccinating convalescent individuals.”
23. Differential effects of the second SARS-CoV-2 mRNA vaccine dose on T cell immunity in naïve and COVID-19 recovered individuals, by Carmen Camara, Daniel Lozano-Ojalvo, Eduardo Lopez-Granados. Et al., BioRxiv, March 27, 2021. “While a two-dose immunization regimen with the BNT162b2 vaccine has been demonstrated to provide a 95% efficacy in naïve individuals, the effects of the second vaccine dose in individuals who have previously recovered from natural SARS-CoV-2 infection has been questioned. Here we characterized SARS-CoV-2 spike-specific humoral and cellular immunity in naïve and previously infected individuals during full BNT162b2 vaccination. Our results demonstrate that the second dose increases both the humoral and cellular immunity in naïve individuals. On the contrary, the second BNT162b2 vaccine dose results in a reduction of cellular immunity in COVID-19 recovered individuals, which suggests that a second dose, according to the current standard regimen of vaccination, may be not necessary in individuals previously infected with SARS-CoV-2.”
24. COVID-19 natural immunity: Scientific Brief. World Health Organization. May 10, 2021. “Available scientific data suggests that in most people immune responses remain robust and protective against reinfection for at least 6-8 months after infection (the longest follow up with strong scientific evidence is currently approximately 8 months). Some variant SARS-CoV-2 viruses with key changes in the spike protein have a reduced susceptibility to neutralization by antibodies in the blood. While neutralizing antibodies mainly target the spike protein, cellular immunity elicited by natural infection also target other viral proteins, which tend to be more conserved across variants than the spike protein.”
25. SARS-CoV-2 re-infection risk in Austria, by Stefan Pilz, Ali Chakeri, John Pa Ioannidis, et al. Eur J Clin Invest. April 2021. “We recorded 40 tentative re-infections in 14 840 COVID-19 survivors of the first wave (0.27%) and 253 581 infections in 8 885 640 individuals of the remaining general population (2.85%) translating into an odds ratio (95% confidence interval) of 0.09 (0.07 to 0.13). We observed a relatively low re-infection rate of SARS-CoV-2 in Austria. Protection against SARS-CoV-2 after natural infection is comparable with the highest available estimates on vaccine efficacies. Further well-designed research on this issue is urgently needed for improving evidence-based decisions on public health measures and vaccination strategies.”
26. Anti-spike antibody response to natural SARS-CoV-2 infection in the general population, by Jia Wei, Philippa C. Matthews, Nicole Stoesser, et al, MedRxiv, July 5, 2021. “We estimated antibody levels associated with protection against reinfection likely last 1.5-2 years on average, with levels associated with protection from severe infection present for several years. These estimates could inform planning for vaccination booster strategies.”
27. SARS-CoV-2 infection rates of antibody-positive compared with antibody-negative health-care workers in England: a large, multicentre, prospective cohort study (SIREN), by Victoria Jane Hall, FFPH, Sarah Foulkes, MSc, Andre Charlett, PhD, Ana Atti, MSc, et al. The Lancet, April 29, 2021. “A previous history of SARS-CoV-2 infection was associated with an 84% lower risk of infection, with median protective effect observed 7 months following primary infection. This time period is the minimum probable effect because seroconversions were not included. This study shows that previous infection with SARS-CoV-2 induces effective immunity to future infections in most individuals.”
28. SARS-CoV-2 Natural Antibody Response Persists for at Least 12 Months in a Nationwide Study From the Faroe Islands, by Maria Skaalum Petersen, Cecilie Bo Hansen, Marnar Fríheim Kristiansen, et al, Open Forum Infectious Diseases, Volume 8, Issue 8, August 2021. “Although the protective role of antibodies is currently unknown, our results show that SARS-CoV-2 antibodies persisted at least 12 months after symptom onset and maybe even longer, indicating that COVID-19-convalescent individuals may be protected from reinfection. Our results represent SARS-CoV-2 antibody immunity in nationwide cohorts in a setting with few undetected cases, and we believe that our results add to the understanding of natural immunity and the expected durability of SARS-CoV-2 vaccine immune responses. Moreover, they can help with public health policy and ongoing strategies for vaccine delivery.
29. Associations of Vaccination and of Prior Infection With Positive PCR Test Results for SARS-CoV-2 in Airline Passengers Arriving in Qatar, by Roberto Bertollini, MD, MPH1; Hiam Chemaitelly, MSc2; Hadi M. Yassine. JAMA Research Letter, June 9, 2021. “Of 9180 individuals with no record of vaccination but with a record of prior infection at least 90 days before the PCR test (group 3), 7694 could be matched to individuals with no record of vaccination or prior infection (group 2), among whom PCR positivity was 1.01% (95% CI, 0.80%-1.26%) and 3.81% (95% CI, 3.39%-4.26%), respectively. The relative risk for PCR positivity was 0.22 (95% CI, 0.17-0.28) for vaccinated individuals and 0.26 (95% CI, 0.21-0.34) for individuals with prior infection compared with no record of vaccination or prior infection.”
Articles in the popular media
Why COVID-19 Vaccines Should Not Be Required for All Americans, by Marty Makary, US News, August 21, 2021
Having SARS-CoV-2 once confers much greater immunity than a vaccine—but vaccination remains vital, by Meredith Wadson, Science, August 26, 2021
Natural infection vs vaccination: Which gives more protection? By David Rosenberg, Israeli National News, July 13, 2021.
Flu survivors still immune after 90 years, by Ed Yong, National Geographic, August 17, 2008.
Rescind Vaccine Mandates: Open Letter to Medical Societies, Hospitals, Clinics, and Other Healthcare Facilities, Association of American Physicians and Surgeons, August 31, 2021.
University Vaccine Mandates Violate Medical Ethics, By Aaron Kheriaty and Gerard V. Bradley, Wall Street Journal, June 14, 2021.
Immunity to the Coronavirus May Last Years, New Data Hint, by Apoorva Mandavilli, New York Times, November 17, 2020.
COVID-19 induces lasting antibody protection, Tamari Bhandara, Washington University School of Medicine, May 24, 2021.
The World Health Organization Oversold the Vaccine and Deprecated Natural Immunity, by Jeffrey Tucker, Brownstone Institute, August 29, 2021.
Why Does the CDC Recognize Natural Immunity for Chicken Pox but Not Covid? By Paul Elias Alexander, Brownstone Institute, September 17, 2021.
Rand Paul and Xavier Becerra Square Off on Natural Immunity, with Devastating Results, by Brownstone Institute, October 2, 2021.
Lockdowns, Mandates, and Natural Immunity: Kulldorff vs. Offit, by Brownstone Institute, October 6, 2021.
Hospitals Should Hire, Not Fire, Nurses with Natural Immunity, by Martin Kulldorff, October 1, 2021.
The Strange Neglect of Natural Immunity, by Jayanta Bhattacharya, Brownstone Institute, July 28, 2021.
The Brownstone Institute for Social and Economic Research is a nonprofit organization conceived of in May 2021 in support of a society that minimizes the role of violence in public life.
Critics love Fauci’s new documentary, but audience hate it and accuse Rotten Tomatoes of ‘hiding’ low score

RT | October 11, 2021
Critics have almost universally praised the new documentary on Dr. Anthony Fauci, but audiences have seemingly hated it, even accusing review aggregator Rotten Tomatoes of trying to hide the movie’s unpopularity.
National Geographic’s ‘Fauci’ has been playing in select cinemas since September 10 and premiered on the Disney Plus streaming service last week. Trailers for the film focus heavily on Fauci and his work combating Covid-19, during which time he has become one of the more controversial figures in American politics.
The film, however, takes a positive look at Fauci and focuses more on tales about the health figure from his family, as well as public figures the infectious disease expert has worked with in the past, such as U2 frontman Bono and former President George W. Bush.
On Rotten Tomatoes, which aggregates reviews from selected critics and then gives a ‘rotten’ or ‘fresh’ score, the film holds a 91% positive rating, based on 30 positive reviews and three negative. The rating from audience members, however, was conspicuously missing from the website until Monday. As of Sunday, only one review, which was negative, had been posted despite the film being out for weeks.
The site was accused of ‘hiding’ the audience score in an effort to spin the movie’s increasingly negative coverage.
On Monday, an audience score did appear, and it showed valleys of difference in opinion from critics to the audience, with users awarding the film a 2% average from over 250 ratings (though it began with a 4% rating that has continually dropped). Despite the average now showing, there is still a lack of actual user reviews on the site, though many users may have chosen to simply drop a rating instead of writing a review.
“Two Americas,” writer Josh Jordan tweeted, including a screenshot of the ‘Tomatometer’ for ‘Fauci’ along with the recently-released comedy special from Dave Chappelle, which has been labeled transphobic by critics, but has been a popular title on Netflix. Critics on Rotten Tomatoes gave the movie a ‘rotten’ score of 33% while audiences awarded a near perfect score.
Fauci critics were quick to mock the film’s near-universal panning from audience members.
The Rotten Tomatoes score for ‘Fauci’ is just the tip of the iceberg when it comes to negative reviews. On IMDB, the movie has a 1.5 rating from over 6000 users.
Trailers for the movie on YouTube haven’t fared much better. One posted by National Geographic has over 100,000 ‘dislikes’ and less than 8000 ‘likes’, as of this writing.
A Disney Plus trailer, on the other hand, has just over 1000 ‘likes’ and over 20,000 ‘dislikes’.
Rotten Tomatoes has been accused of bias in the past, and the company has often chalked up near-universal negative reactions from audiences to trolls’ review-bombing.
In 2019, the company disabled pre-release comments and removed their ‘Want to See’ function – which allowed ratings based on how excited users were for a film – in response to early backlash against franchise pictures accused by critics of going ‘woke’, such as ‘Star Wars: The Last Jedi’ and ‘Captain Marvel’.
Two years before that decision, debate around Rotten Tomatoes and the political influence the audience can have was still a heated debate. Outspoken liberal and comedian Amy Schumer claimed in 2017 that her comedy special ‘The Leather Special’ was review-bombed by the “alt-right” over her comments on Donald Trump and other Republicans (50% critic rating/4% audience). At the time, the site responded again by limiting user functions by removing a five-star system in favor of a positive or negative rating from audiences.
On the opposite end of the spectrum, conservative artists have often pointed to the fact that films aimed at right-leaning audiences often score much lower with critics than audiences as proof the company is more open to ‘certifying’ liberal critics than right-of-center or conservative ones.
Producer John Aglialoro blamed near-universal bad reviews from “hateful” critics on Rotten Tomatoes for his 2011 film ‘Atlas Shrugged: Part I’ struggling to find an audience in theaters (he would go on to produce two sequels covering the last two thirds of Ayn Rand’s influential novel).
Trudeau Bans the Unvaccinated from Leaving the Country and from Earning a Living
The Justice Centre – October 7, 2021
CALGARY: The Justice Centre today responded to the federal government announcement that unvaccinated Canadians will lose their right to move and travel freely within Canada, their right to leave Canada, and their right to earn a living and participate in society without discrimination.
“The government is seeking to have 100% of Canadians injected with the experimental mRNA vaccine, which has not been subjected to any long-term testing on humans,” states lawyer John Carpay, President of the Justice Centre.
With the Canada-U.S. land border closed to non-essential travel, this Covid-19 vaccine travel mandate will effectively prevent unvaccinated people from leaving Canada in any way. In addition to denying unvaccinated Canadians the right to travel by plane or train, the federal government has also announced that federal employees and contractors will lose their jobs unless they participate in the world-wide experiment with new mRNA vaccines.
“We were recently promised, this past summer, that life would go back to normal once 70% of Canadians were injected with mRNA. This high vaccination rate has been achieved but has not stopped the spread of the virus. The new mRNA vaccine also provides no guarantee against the Delta variant,” continues Mr. Carpay.
According to media reports, Prime Minister Trudeau declared that these discriminatory measures against unvaccinated Canadians are needed to keep people “safe,” including children.
“Government data and statistics from every Canadian province, and from countries around the world, tell us that children, teenagers and young adults face no serious threat from Covid, which makes the Prime Minister’s rhetoric about saving children highly misleading,” continues Mr. Carpay.
“Medical reports and scientific studies make it clear that both vaccinated and unvaccinated people spread Covid-19. There is no scientific basis for turning unvaccinated Canadians into second-class citizens,” stated Allison Pejovic, Justice Centre Staff Lawyer.
Currently, Canada’s provincial and federal governments accept two injections as enough to qualify for “full” vaccination. But this may soon change to requiring three, four and more injections to maintain one’s legal status as “fully” vaccinated, as has been demonstrated in Israel and the Netherlands.
“Governments throughout history have used the notion of ‘science’ to support their policies, along with various appeals to public health, safety, security, morality, and so on. No government will violate human rights without putting forward a good-sounding justification, such as the war on terrorism, communism, online hate, drugs, or a nasty virus,” continues Mr. Carpay.
The government’s own data and statistics tell us that Covid is much closer to the annual flu than to the Spanish Flu of 1918. This matters because the entire world was put into a state of panic by the dire predictions of Dr. Neil Ferguson of Imperial College, who claimed in March of 2020 that Covid would be like the Spanish Flu of 1918, killing tens of millions of people.
“Canada’s vaccine passports, and the creation of first-class and second-class citizenship, are founded on Neil Ferguson’s demonstrably false claim that Covid is an unusually deadly killer,” states Mr. Carpay.
“Covid is real. Fear of Covid is wildly exaggerated. Over the past 18 months, government-funded media have been very successful in persuading the majority that vaccine passports (and lockdown policies preceding them) are based on science. When people hear a message thousands of times, they believe it to be true,” continues Mr. Carpay.
“The Justice Centre is profoundly disturbed that these federal mandates will prevent unvaccinated Canadians from leaving the country. Such a mandate is an egregious and unacceptable infringement of Canadians’ constitutionally protected mobility rights. There is no scientific justification for this,” concludes Ms. Pejovic.
These new government restrictions on civil liberties are still announcements at this stage, and no law has been passed by Parliament or by way of cabinet regulation (Order-in-Council). So, no legal challenge is possible at this time. If the government intends to implement these vaccine travel mandates and give them the force of law, these policies can then be challenged in court.
Featured Video

The Truth About the Trump Shootings with Ken Silva
or go to
Aletho News Archives – Video-Images
From the Archives
Trans ‘milk’ as good as the real thing – NHS
RT | February 18, 2024
The drug-induced nipple secretions of trans women are as good as mothers’ breast milk for babies, the University of Sussex Hospitals NHS Trust claimed in a letter to campaigners made public in a report by British think tank the Policy Exchange on Sunday.
The healthcare trust’s medical director, Rachel James, argued that the off-label prescription drug cocktail men transitioning to female take in order to produce milk was “similar to the natural hormones which encourage lactation to develop when the baby is newly born.”
“The evidence which is available demonstrates that the milk is comparable to that produced following the birth of a baby,” James wrote in the letter, sent to Children of Transitioners last August.
Biological men who wish to lactate must first take hormones to grow milk glands and then take high doses of either domperidone or metoclopramide to stimulate milk production. Neither drug is approved for this use, though they are occasionally prescribed off-label to biological women who have trouble lactating.
However, domperidone’s own manufacturer, Janssen, warns patients the drug “may cause unwanted side effects affecting the heart in a breastfed baby” and “should be used during breastfeeding only if your physician considers this clearly necessary.” … continue
Blog Roll
 Aletho News
- Russia Voted Under Fire. Washington Is Loading the Tankers.
- 12 Things Your Oncologist Was Trained Not to Tell You
- Anthrax Attacks Paved Way for COVID-Era ‘Junk Drugs and Vaccines’
- How Real Is the Impact of Western Sanctions on Israel?
- France, You Are Guilty: How Paris Turned Western Sahara into the Maghreb’s Powder Keg
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- Your Milk Is Not the Problem
- The Truth About the Trump Shootings with Ken Silva
- ARE PATIENTS BEING PROPERLY INFORMED ABOUT OZEMPIC?
- US lawmaker blocks $2.8 billion weapons sale to Israel: Report
- If Americans Knew
- Salah Sarsour’s Legal Team Says DHS Has Not Met Its Burden to Prove He Is Deportable
- An analysis of tax forms by The Intercept show Kraft’s charity and LLC have donated to Friends of the IDF and AIPAC’s super PAC.
- Israeli attacks kill four Palestinians in Gaza – Daily Update
- Inside Gaza’s death trap of collapsing, bombed-out buildings
- The everyday items Israel bans from Gaza every day
- Inside the siege, the ruined buildings of Gaza – Daily Update
- Debunking The Claim That Macklemore Has A “History Of Antisemitism”
- CPJ demands release of arrested Palestinian-US journalist near Bethlehem
- Robert Kraft: The Billionaire Friend of Netanyahu Pulling The Strings Behind the Macklemore/Ed Sheeran Blow Up
- Columbia Administered Fund Gives Big Money to Pro-Israel Groups
- No Tricks Zone
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
 Aletho News
