Do vaccine rollouts correlate to disabled americans?
el gato malo – bad cattitude – june 10, 2022
i have long been friends with ben. he’s done a lot of great work, runs a fantastic site on US all cause mortality, and has broken open a number of important issues around covid.
this may be another.
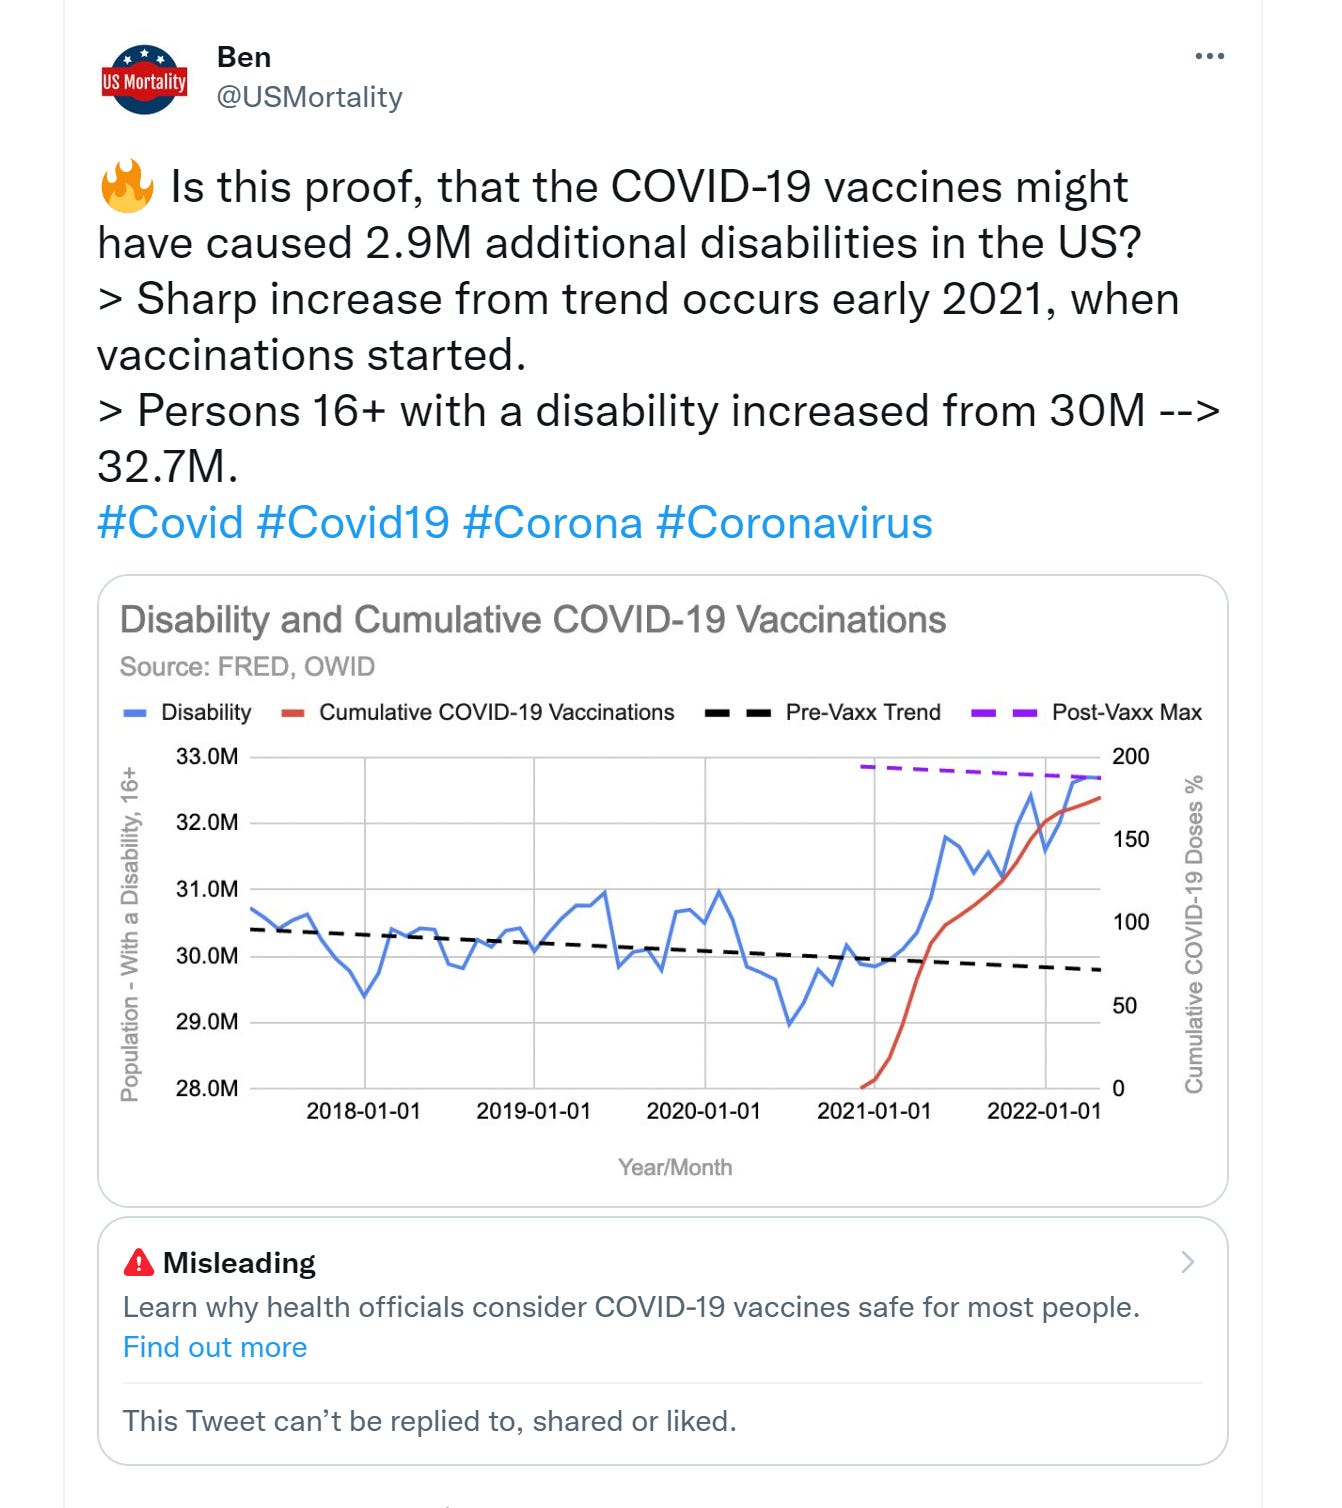
and it was not up for an hour before twitter not only marked the tweet as disinformation and locked ben out of his account all for asking a simple question that pretty much leaps out of this data.
the data comes from the FRED tool run by the st louis federal reserve bank. they are a well respected and high quality government run data source.
hard to see the problem with the data.
clearly, their issue is with the conclusion.
and, well, streisand effect and all, well, it caught my attention because naughty kitties love reading banned books.
correlation does not and cannot prove causality, but it can sure give us some strong hints, especially when we already know how off the charts the adverse event rate from these vaccines have been.
and boy is this timing provocative…
so, being the kind of gato to want to play with the data myself, i downloaded the set and graphed it.
as can be seen, this series was very stable for the prior 5 years. the dotted red line is the average value from 6/16 to 2/20, right before covid starting having effect.
this data comes from the current household survey. the drop for covid is likely a drop in survey response but as can be seen, it rapidly normalized.
then covid vaccination started.
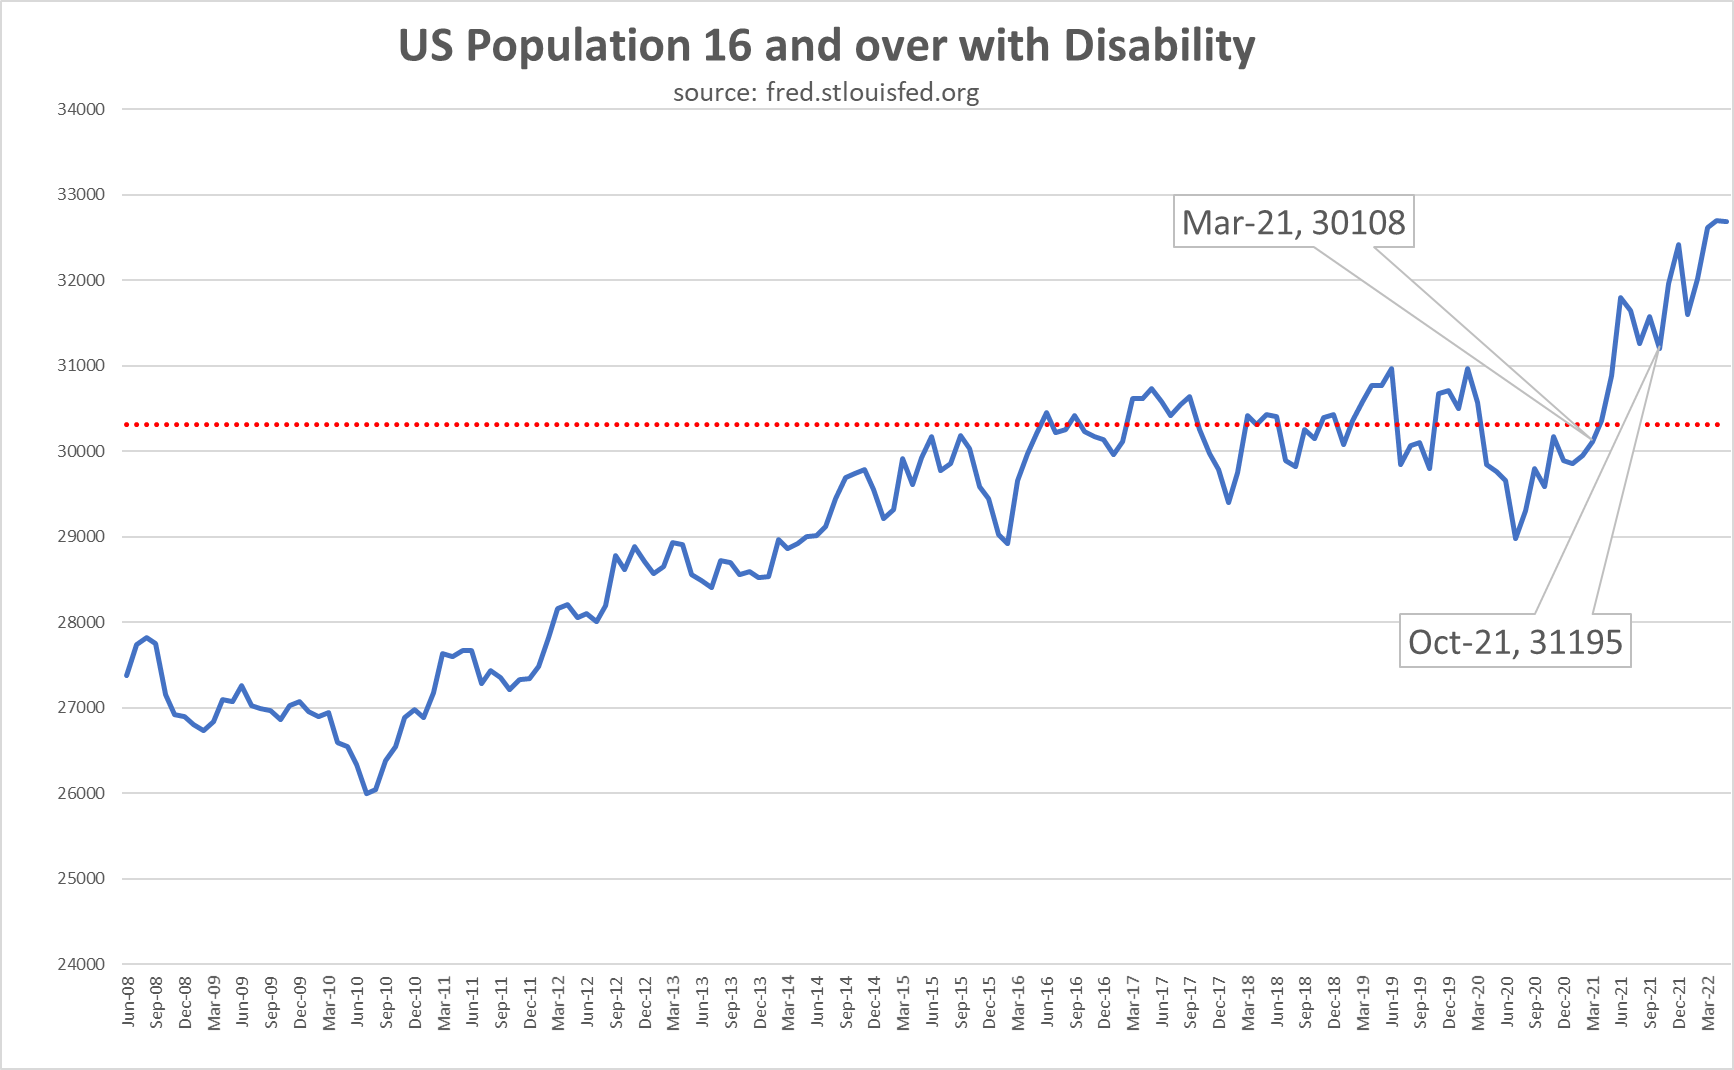
the first callout is when vaccinated reached 1%.
the second is when boosters reached 1%.
i chose this convention because each has a sort of long tail at a very low level leading in but rose rapidly after reaching 1% so it seemed like the best inflection point for maximum relevance.
as can be seen, the timing is highly suggestive.
and it makes sense.
seeing this:
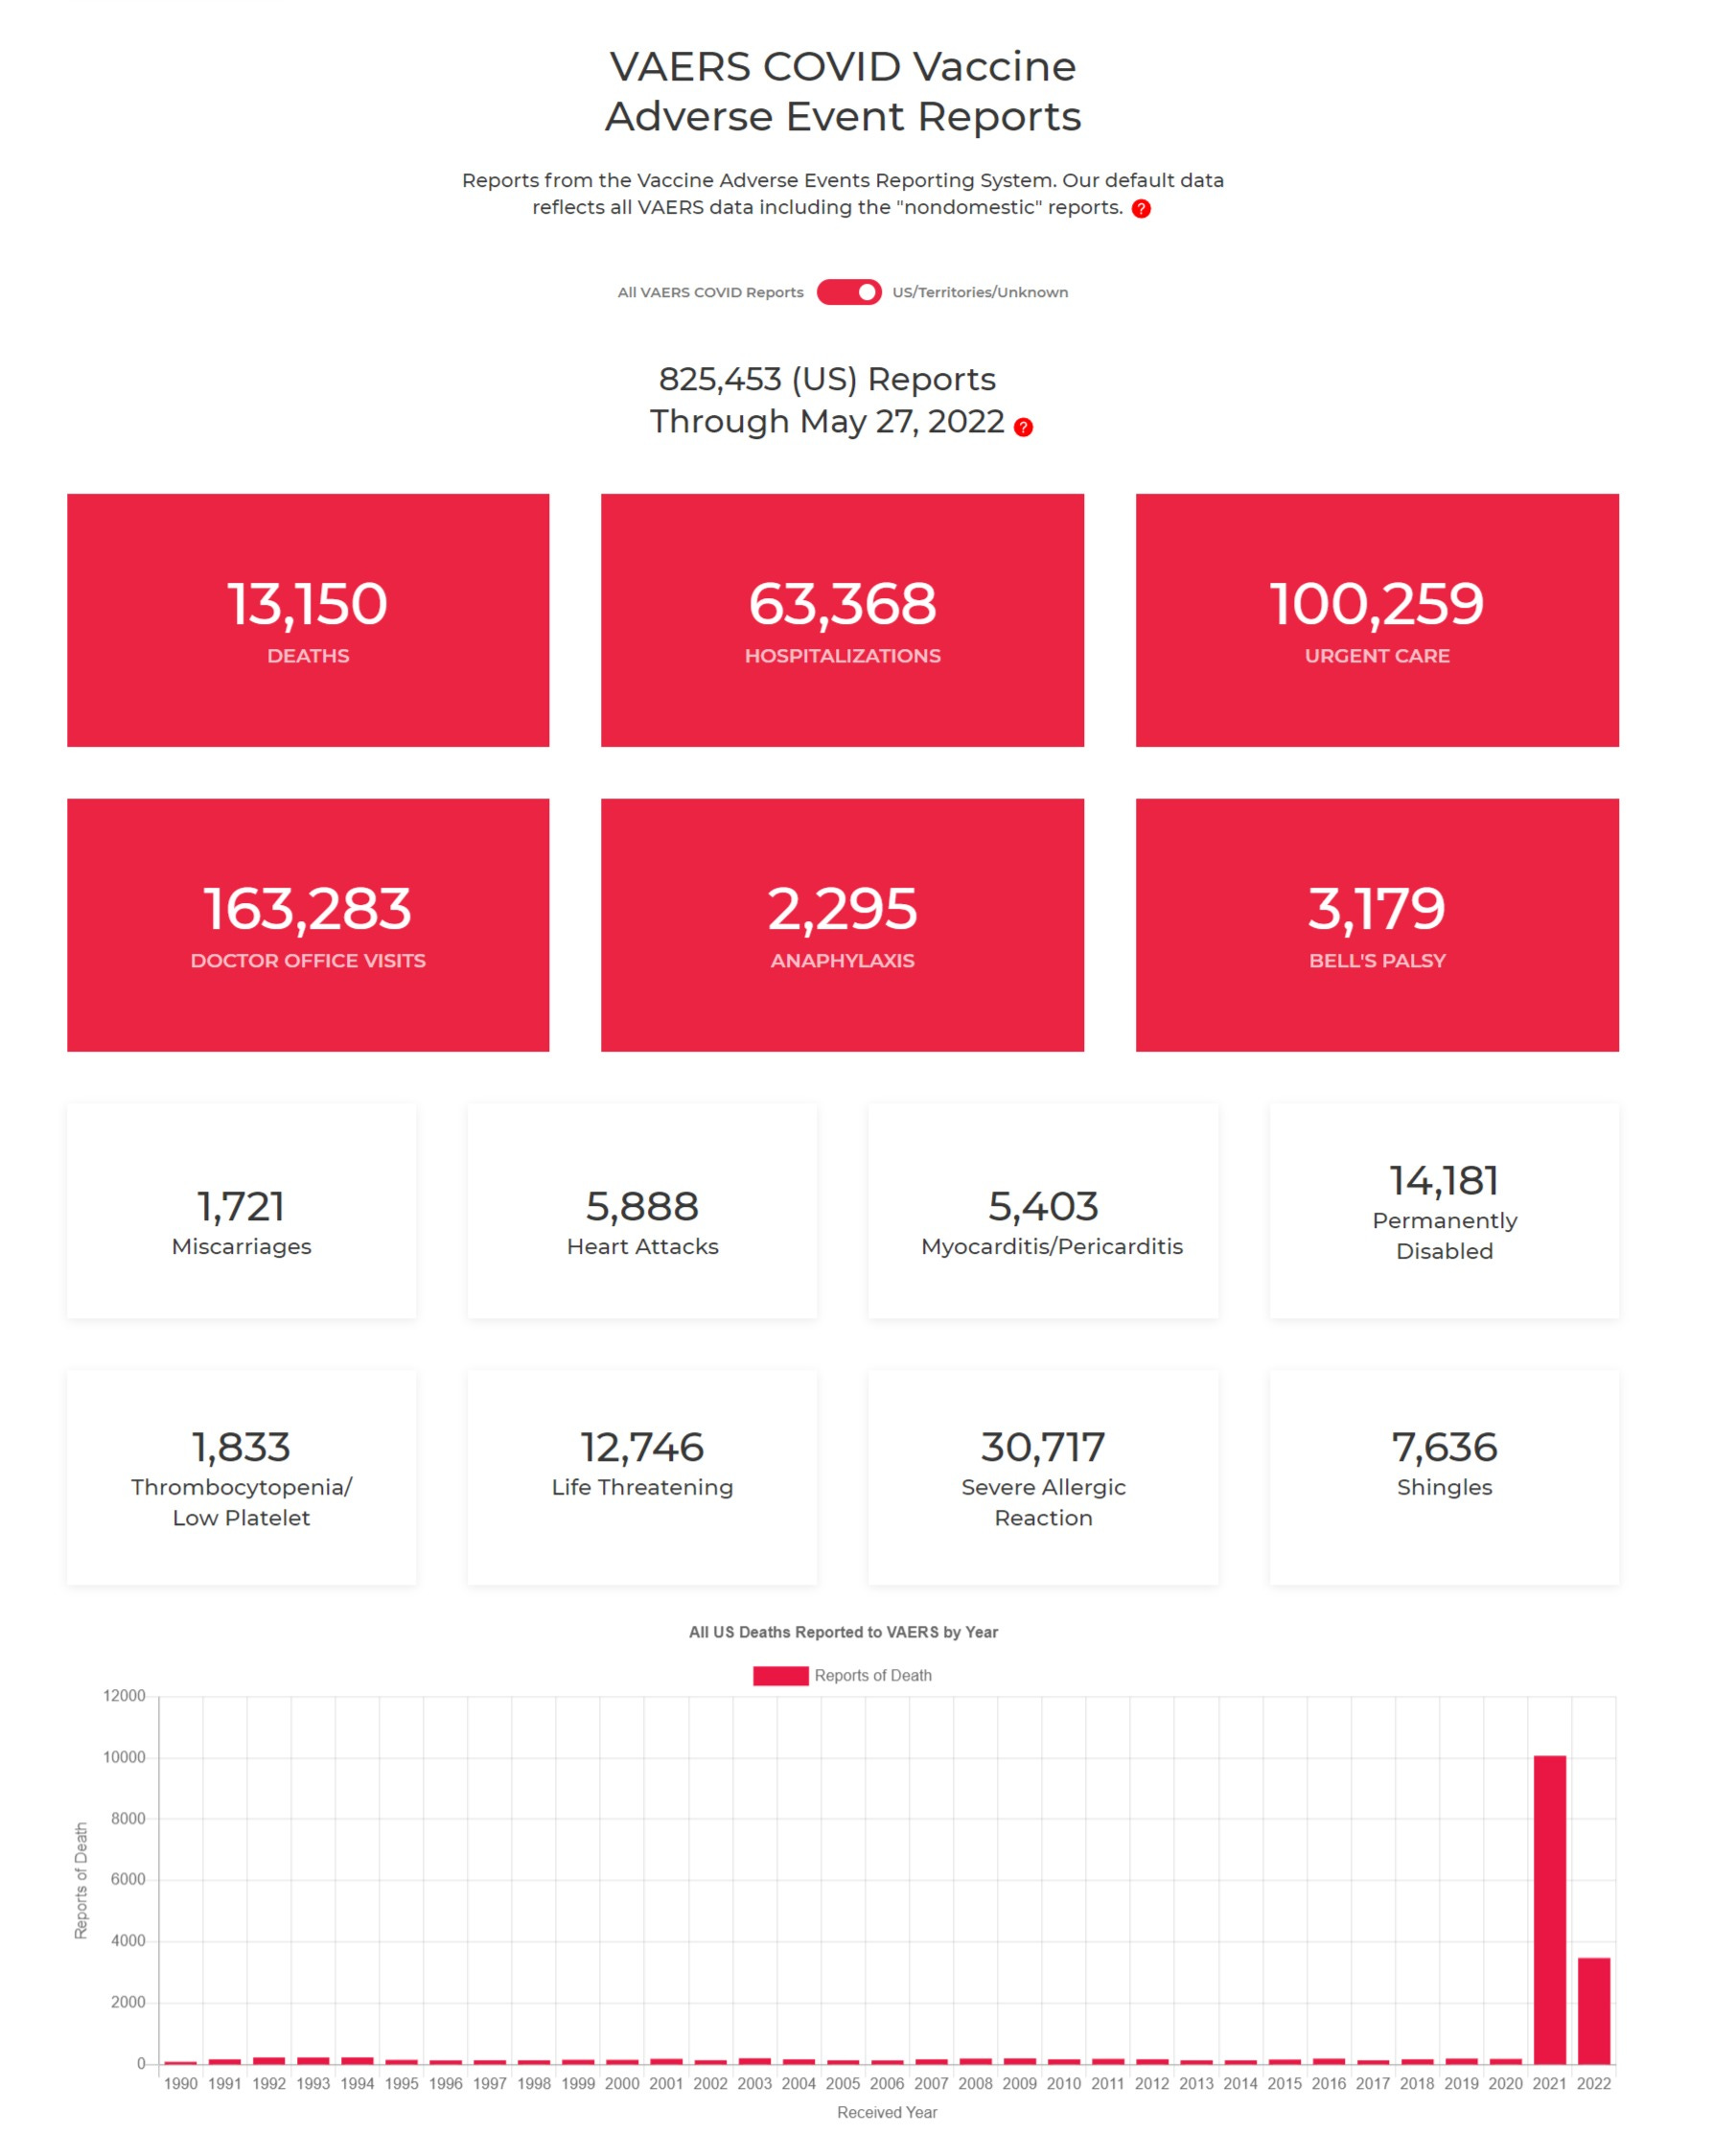
without a rise in disability reports would be surprising. we see 14k permanently disabled in VAERS. and we see a rise in the disabled rolls of 1.8 million. that’s pretty close to the 1-2% capture rate (more like 1%, but also likely capturing other categories as well, so hard to be precise) for reporting we’ve seen around other VAERS issues (besides death which seems to get better counted)
so it feels like we’re in a ballpark here.
and it does not look like “long covid” because the original covid strains were more severe and yet we saw no evidence of this disability spike pre-vaccines.
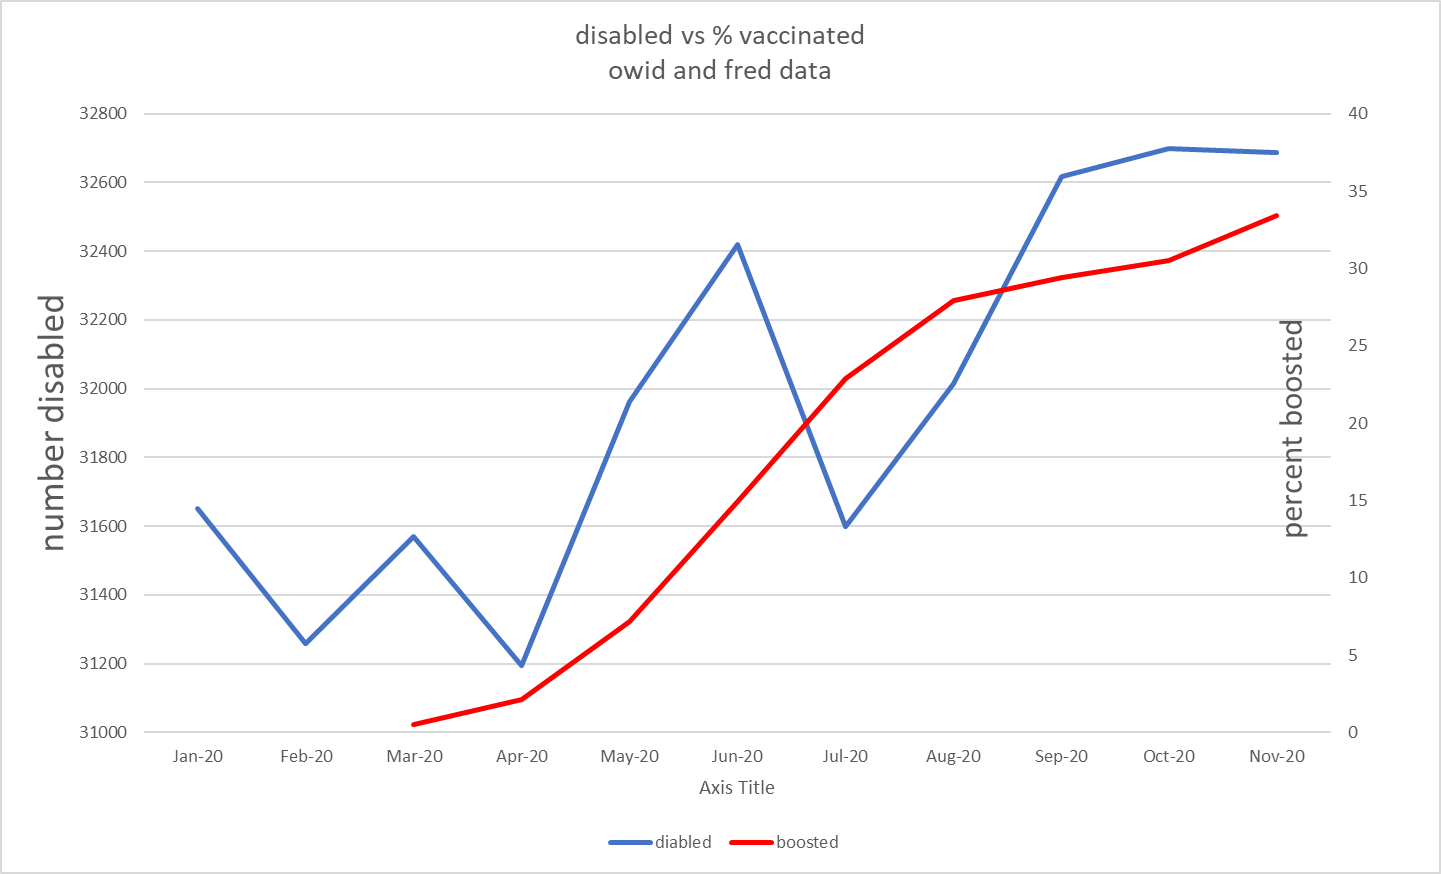
we can zoom in and really see the issue. data used is fred and owid. obviously, there is some chart crime here with the scaling, but the overall relationship is remarkable. this is basically what ben plotted.
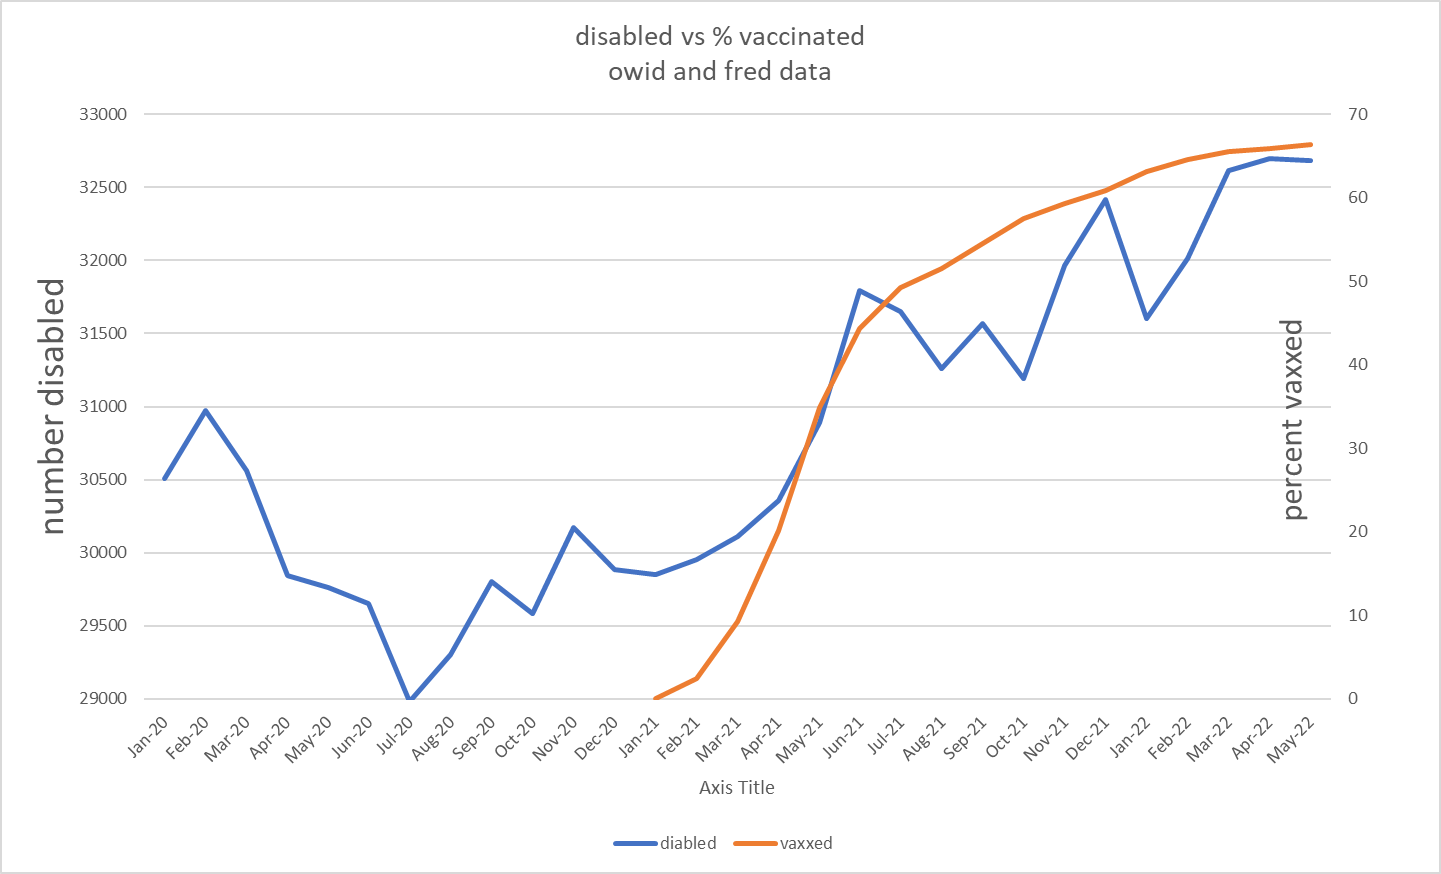
the second sharp upleg in october also interested me so i checked it against this:
it’s easy to take up trending series and lay their scales so they look correlated. the real test is bi-directionality. and this looks to be most damning of all. i took % vaxxed each month and subtracted the prior month to get “% of population vaxxed in month.” this should give us a sense of the people at risk of vaccine complications at any given time. to this i added the same treatment to the booster series to get a total % of population getting a vaccine each month.
i then plotted this series against disability.
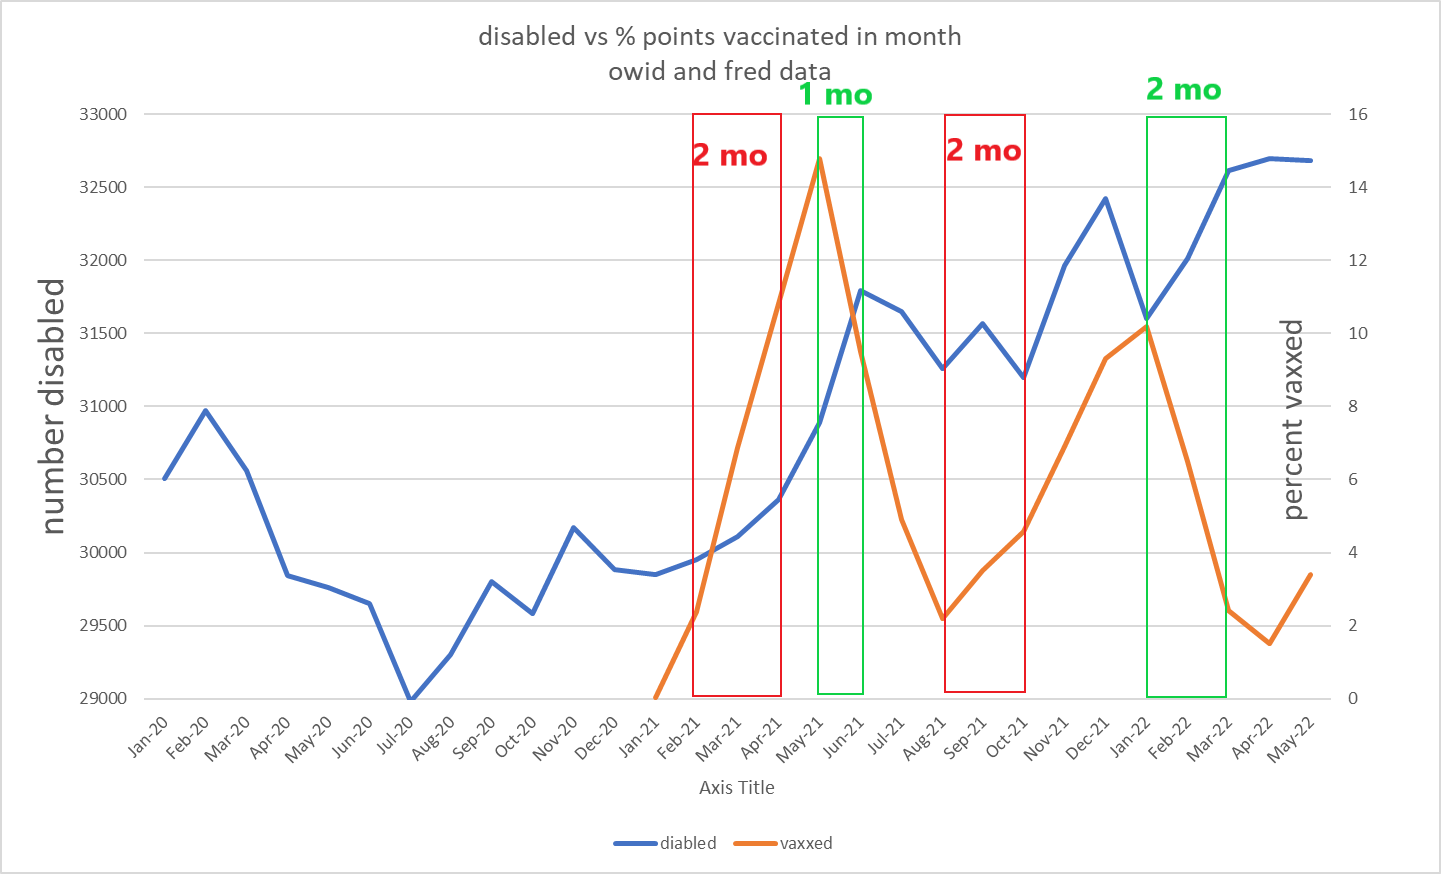
- the vaccination series started to get steep in feb 21. disability got steep in april 21.
- vaccination peaked in may. disability peaked in june.
- vaccination started to rise again after august.
- disability began to rise again after october.
- then vaxx dropped off after jan 2022 and disability flattened out in mar 2022.
2 month lag, 1 month lag, 2 month lag, 2 month lag. 4 separate inflections all tracked in near identical and highly plausible timeframes for vaccine injury. we’re starting to get past “suggestive” here.
this zigs, zags, then zigs again, then zags again all as predicted if it were causal and all with the sort of lag you’d associate with reporting, 1-2 months. (all 2 mo save may-jun 21)
the disability series can be a little noisy month to month, but the big trends are all there.
based on what we know about side effects this looks to be an odds on hypothesis at this point. i can see no better fit to the data.
anyone seeing flaws here? what are we missing? is there another explanation?
“the vaccines just put 1.8 million americans into disability” is a big claim.
i want to stress, this is still a hypothesis and this is my first run through with this data so i want to let people chew on it and see what else emerges before making claims that are too strong.
but this is also REALLY provocative and unless i have really missed something, warrants research and explication, not censorship.
please spread the word and let’s get some eyes on this.
Monkeypox is following the Covid playbook step by step
By Kit Knightly | OffGuardian | June 8, 2022
Monkeypox is back in the headlines as of yesterday, back to work after a short break.
It burst onto the front pages, with concomitant BIG RED NUMBERS and daily case updates a couple of weeks ago, and then went quiet. The press pretty much stopped talking about it.
… until they started again.
Yesterday it was reported that the UK Health Security Agency (UKHSA) has “upgraded” monkeypox to a “notifiable disease”, meaning any positive test must be immediately reported to the government agency.
Ever one for subtlety, the Telegraph’s front page reports this as “monkeypox upgraded to same level as leprosy and the plague”
Across the pond, the US CDC has made the curiously synchronised decision to increase their travel alert on Monkeypox to level 2, which recommends people “practice enhanced precautions”.
Let’s be clear here – the “monkeypox outbreak” is a joke.
Anybody actually taking any of this seriously after the last two years of Covid hysteria needs a major reality check.
At this point you should be assuming any disease “outbreak” is a hoax until proven otherwise. Really proven, not “trust me, I’m an expert” proven.
For those who haven’t got to that stage yet, consider all the ways that monkeypox is following the exact same path as “Covid”…
- The monkeypox outbreak was “predicted” by an exercise a few months before it happened. Just like Covid.
- We’ve seen the narrative re-inforced by rumours that it’s a bio-weapon. These accusations have gone both ways, with the Western press saying Monkeypox is a Russian bio-weapon and Chinese rumours claiming it was deliberately released by the US. Just like Covid
- We’re seeing institutions revising history in order to inflate the potential threat of the disease. just like Covid.
- Monkeypox is being diagnosed via a PCR test. These tests are going to become more widely available as test-makers “seize the new market” and governments plan to “ramp up testing”. Increased testing (with an unreliable test) could artificially inflate “cases”, and feed the panic. Just like covid.
- The monkeypox narrative is being pushed by countries on both sides of the “New Cold War”. Just like covid.
They’re already resorting to the “new variant” headline, that wasn’t a thing for Covid for almost a year. Is this due to desperation or impatience? Who can say, but there must be some reason for the accelerated timeline.
They’re even trying to bring masks back into style by claiming monkeypox may have become airborne.
And, of course, the biggest similarity is in the solution: “vaccines”.
It has already been decided that vaccines originally designed for smallpox work for monkeypox too, and that they are best way to stop the spread of the disease.
Meanwhile, the monkeypox story over at Science tells us…
As monkeypox threat grows, scientists debate best vaccine strategy”
It seems the “experts” can’t decide between “ring vaccination” – where you vaccinate every close contact of a confirmed monkeypox case – or “broader vaccination campaigns”.
Note, they don’t debate if we need a vaccine strategy at all.
The US government is already set to spend at least 180 million dollars on smallpox vaccines.
In Europe, pharmaceutical company Bavarian Nordic is seeing a huge up-tick in its contracts as EU nations treat monkeypox as a “wake-up call”.
So, vaccine manufacturers are set to make a tidy profit… Just like covid.
Whatever eventually comes of this story, it certainly seems that Covid has put a “pandemic” playbook in place, one that each new scare-disease will follow.
It’s all so predictable… and yet the people in charge actually expect us to believe it. Worst of all, some people actually will.
I started by calling monkeypox a joke, and that might be literally true. It’s hard not to feel like they’re making fun of us.
And if that’s the case then, just like at school, the best thing we can do is simply ignore it.
French President Macron: “Vaccinate Everything That Can Be Vaccinated”
By Robert Kogon | Brownstone Institute | June 8, 2022
In another sign that the campaign of C-19 vaccination in Europe is far from over, French President Emmanuel Macron suggested last week that the appropriate response to the crisis in France’s overstrained emergency healthcare services is to “vaccinate everything that can be vaccinated.”
“Vaccinate everything that can be vaccinated,” Macron said, “because we avoid the virus. That’s the best response for unburdening the healthcare system and having a healthy population. So, we’re going to continue to work on this aspect.”
Macron’s word choice has attracted particular attention in the French Twittersphere and other online media, since he literally said that it was necessary to vaccinate “every-thing” (tout ce) and not, say, “everyone” (tous ceux) that can be vaccinated. But even if he had chosen to refer to people as people rather than things, the very idea of “having to vaccinate” people clearly denies them agency – to say nothing of any possibility of informed consent.
A clip of Macron’s remarks, which were broadcast on the French news channel BFM TV, is available here. They form part of more wide-ranging remarks, complete video of which does not appear to be available online.
But another extract posted on the BFM website appears to show the immediate lead-up to the “vaccinate everything” comment and suggests that Macron was responding to a question, more precisely, about whether reintegrating hospital staff who were suspended for having refused to get vaccinated against Covid-19 might help to address staffing shortages in French emergency rooms.
“Reintegrating unvaccinated healthcare workers is absolutely not an answer to the problem,” Macron says, not only because, according to him, they represent just a “tiny minority,” but also because – “if we’re honest” – the unvaccinated staff have “a dubious relationship to care and to ethics.” The French government made Covid-19 vaccination mandatory for healthcare workers in September 2021.
Macron’s remarks on “vaccinating everything that can be vaccinated” come after European Commission President Ursula von der Leyen’s recent call to “further step up vaccination” throughout the EU and the Commission’s issuing of a detailed strategy for doing so starting in the fall.
Robert Kogon is a pen name for a widely-published financial journalist, a translator, and researcher working in Europe. He writes at edv1694.substack.com.
Doctors Sue FDA, Allege Crusade Against Ivermectin ‘Unlawfully Interfered’ With Their Ability to Treat Patients
The Defender | June 6, 2022
Three physicians are suing the U.S. Food and Drug Administration (FDA) for launching what they allege is a “crusade” against ivermectin as a treatment for COVID-19 that “unlawfully interfered” with the doctors’ ability to practice medicine.
In a lawsuit filed June 2, Drs. Robert L. Apter, Mary Talley Bowden and Paul E. Marik argued the FDA acted outside of its authority by directing the public, including health professionals and patients, to not use ivermectin — even though the drug is fully approved by the FDA for human use.
The suit, filed in the U.S. District Court, Southern District of Texas, Galveston Division, also names the U.S. Department of Health and Human Services (HHS), HHS Secretary Xavier Becerra and Robert Califf, acting FDA commissioner.
According to the complaint:
“The FDA generally cannot ban particular uses of human drugs once they are otherwise approved and admitted to the market, even if such use differs from the labeling — commonly referred to as ‘off-label’ use.
“The FDA also can not advise whether a patient should take an approved drug for a particular purpose. Those decisions fall within the scope of the doctor-patient relationship.
“Attempts by the FDA to influence or intervene in the doctor-patient relationship amount to interference with the practice of medicine, the regulation of which is — and always has been — reserved to states.”
The plaintiffs said their lawsuit isn’t about whether ivermectin is an effective treatment for COVID-19. It’s about who determines the appropriate treatment for each unique patient and whether the FDA can interfere with that process.
In their complaint, they site an FDA publication, “Why You Should Not Use Ivermectin to Treat or Prevent COVID-19,” and tweets from the FDA — including one implying that ivermectin is intended only for animals — among examples of the FDA discouraging the use of ivermectin.
The plaintiffs also argued if the FDA is allowed to interfere with the practice of medicine now, using the pandemic as a cover, “this interference will metastasize to other circumstances, destroying the carefully constructed statutory wall between federal and state regulatory powers, and between the FDA and the professional judgment of health professionals.”
“This lawsuit, brought by three eminently qualified physicians, is a welcome development,” said Mary Holland, Children’s Health Defense president and general counsel.
Holland told The Defender :
“These doctors rightfully assert that the FDA, assisted by corporate media, have unlawfully interfered in the doctor-patient relationship and the appropriate treatment for individual patients. Regulating the doctor-patient relationship is an area of well-established state, not federal, law.
“I hope these plaintiffs will enjoin the FDA from continuing to restrict access to ivermectin and from penalizing healthcare practitioners who use this licensed drug for their patients.”
The plaintiffs: well-respected in their field, high success rate treating COVID patients
Apter, who is licensed to practice medicine in Arizona and Washington and has a COVID-19 patient survival rate of more than 99.98%, was referred to the Washington Medical Commission and Arizona Medical Board for disciplinary proceedings for prescribing ivermectin to treat COVID-19.
In a press release, Apter said, “If doctors are freed to treat patients according to their best judgment and unprejudiced evaluation of the medical literature, many thousands more deaths and serious disabilities will be averted.”
Apter said the FDA’s pronouncements against the use of ivermectin “have been the basis for disciplinary actions against doctors, interfere with the doctor-patient relationship, and have had a severe chilling effect on the use of life-saving medication for a deadly disease.”
In the lawsuit, Apter argued that government pressure, “largely through the FDA,” also led pharmacies — especially in large corporate chains — to refuse to fill ivermectin prescriptions for COVID-19, because that position is supported by the FDA.
Bowden, who according to the lawsuit has 40 years of experience in emergency medicine, began recommending ivermectin to treat COVID-19 in early 2020. She treated more than 3,900 patients for COVID-19, with a success rate of over 99.97%.
She said the FDA’s actions regarding ivermectin, specifically its directives to stop using the drug to treat COVID-19, harmed Bowden’s ability to practice medicine and treat patients.
Bowden’s employer, Houston Methodist Hospital, last year forced her to resign by suspending her privileges for spreading “COVID misinformation.”
Bowden said she is “fighting back — the public needs to understand what the FDA has done is illegal, and I hope this suit will prevent them from continuing to interfere in the doctor-patient relationship.”
In an interview earlier this year with The Defender, Bowden said she was all for the COVID vaccines when they first came out — it was only when she started seeing what was happening with all the breakthrough cases that she wondered, “Why am I seeing so many COVID cases among the fully vaccinated?”
Then her patients began having adverse reactions. “If I hadn’t seen that firsthand, I would still think the vaccine was the way to go,” she said.
As the pandemic evolved, Bowden developed protocols for preventing and treating COVID patients. She said she’s seen excellent results.
“The basis of it is ivermectin,” she said. “And also vitamins C and D, quercetin and zinc, and black seed oil. It’s nothing complicated — and it’s just like with anything in medicine — not one size fits all — protocols are guidelines.”
The controversy over prescribing ivermectin was initially “intimidating and isolating,” she said. “I thought I was a little bitty island in a huge ocean, and now I realize that I’m part of at least half a continent.”
Marik, author of more than 750 publications, was professor of medicine and chief of pulmonary and critical care medicine at Eastern Virginia Medical School (EVMS) in Norfolk, Virginia, from 2009 through 2021. He also served as a director of the intensive care unit at Sentara Norfolk General Hospital.
He developed a protocol for EVMS for treating COVID-19, called the EVMS COVID-19 Management Protocol, which included the MATH+ Protocol.
However, according to the lawsuit, Marik was forced to resign from his positions at EVMS and Sentara Norfolk General Hospital for promoting the use of ivermectin — “as well as other safe, cheap, and effective off-label FDA-approved drugs” — to treat COVID-19 following the FDA’s attempts to stop use of those drugs for that purpose.
Marik alleged in the lawsuit that refusing to allow patients to receive effective early treatment for COVID-19 “led to innumerable hospitalizations and deaths, and caused extreme distress for patients, their families, and health professionals.”
Boyden, Gray & Associates, a Washington, DC-based law firm, is representing the plaintiffs.
Ivermectin was developed in the 1970s as a veterinary medicine to treat parasitic diseases in livestock, but a decade or so later was hailed as a “wonder drug” and received approval for human use as a therapeutic against diseases such as river blindness — or onchocerciasis — and lymphatic filariasis, according to Newsmax.
Since 1987, it has been used safely in 3.7 billion doses worldwide. William Campbell and Satoshi Omura won the 2015 Nobel Prize in Physiology or Medicine for their research on the drug.
Studies show ivermectin is associated with lower COVID-19 death rates, but the FDA — with help from mainstream media — continues to state the drug is ineffective for treating COVID.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Trudeau denounced by foreign senator for locking up unvaccinated Irish citizen
By Thomas Lambert | The Counter Signal | June 8, 2022
Trudeau is making international headlines again after Irish Senator Sharon Keogan denounced Trudeau for freezing Canadians’ assets and preventing an Irish citizen from leaving the country due to their vaccination status.
During a debate in May over COVID programs, Senator Keogan used Trudeau and his government as a specific example of what happens when a government abuses its power over the people.
“Recent global events have given rise to concern over State control of private finances. The extrajudicial freezing of assets and transactions by the Canadian government of individuals deemed associated with anti-government protests provides a chilling case study in the abuse of centralized power,” Keogan said.
She then asked the Irish finance minister what protections the country needs to protect citizens’ privacy so that Ireland doesn’t become an authoritarian state like Canada.
In a separate instance, Keogan read out a letter of an unvaccinated Irish citizen who was prevented from leaving Canada by Trudeau’s government — even though he had an exemption.
The letter states, “I cannot board a plane in Canada to fly to Ireland because I’m not vaccinated. The government of Canada has set a mandate that states that no unvaccinated person shall board a plane, train, or [sic], whether to travel domestically or internationally.”
“I believe it is the only country in the Western world that has imposed this sanction of the unvaccinated population.
Indeed, not only are other Western countries not persecuting the unvaccinated, but most have also dropped every single COVID-related restriction and travel requirement for both citizens and foreigners alike. Meanwhile, Trudeau is doubling down.
Responding to the letter, Keogan demanded the “immediate intervention by the Minister for Foreign Affairs” to stop Trudeau’s persecution of an innocent Irish citizen.
“These are our citizens who are locked up in another country and who cannot travel back to their own native homes. This requires immediate intervention by the Minister for Foreign Affairs, Deputy Coveney,” Keogan said.
Fauci’s COVID origins coverup spook has resurfaced to misdirect us about the origin of money pox
By Meryl Nass, MD | June 7, 2022
Andrew Rambaut (pronounced Rambo—and like Rambo, he is still in the ring, fighting for the globalists, when he should have taken his toys and slunk away long ago—after being beaten up as one of the stooges who produced the fake Nature Medicine paper on COVID’s origins) has long been associated with a group of virology spooks in Tony Fauci and Jeremy Farrar’s network. The field of evolutionary biology is supposed to tell you where new viruses have come from. But of course, it has been kidnapped to provide specious explanations when the biowarriors need to try and explain their concoctions as having natural origins.
Rambaut was also used to dispute the origins of HIV (as described in my friend Ed Hooper’s book The River ) while teamed up with Eddie Holmes, another Fauci flunkie, more than 20 years ago.
Republican members of Congress want to know what Fauci and his henchmen were up to when they concocted a fake natural origin for COVID, as revealed in the Fauci emails.
Rambaut was one of the 5 authors of that paper, and the paper was highly effective for a bit over one year at keeping a lid on COVID’s lab origin. As the members of Congress wrote:
Andersen and three other doctors on this teleconference [including Rambaut] later published a paper titled “the proximal origin of SARS-CoV-2 in Nature Medicine on March 17, 2020. This paper was highly influential in shaping our nation’s response to the pandemic. In the paper, the doctors concluded that “…we do not believe that any type of laboratory-based scenario is plausible.”[11]
… The Andersen paper led the narrative away from COVID-19’s potential lab origins. As Americans, we are deeply concerned by the appearance of discrepancies that largely influenced our understanding and approach to this virus. As Representatives of the American people, we owe it to them to seek and expose the truth about this virus’ origins wherever those efforts may lead.
Now Rambaut has popped up again, like a jack-in-the-box, to explain how the unexplainable 50 single nucleotide polymorphisms (SNP mutations) could have happened naturally. He has another bold theory! There was an evolutionary jump!
And Rambaut proffered yet another theory: the virus has been spreading in humans for years; we just didn’t notice it.
Below is a paper published by Portuguese researchers discusing the newly discovered mutations in money pox. They mention Rambaut’s theory, and Rambaut himself provides the first comment below the paper.
Spooks like Dr. Rambaut don’t do this dirty work for nothing. Just last month, he was made a fellow of the Royal Society.
From Wikipedia:
Science reported on 11 January 2020 that Rambaut was the first to publish the genome of the COVID-19 coronavirus after it was sent to him by Edward C. Holmes.[11][12] Holmes has said that it “took 52 minutes from receiving the code [from his Chinese colleague Professor Yong-Zhen Zhang] to publishing” on Virological.[13][14] The BBC Horizon episode The Vaccine stated: “When Chinese scientists published the genetic sequence of a mystery new virus on January 10th 2020, vaccine scientists around the world immediately sprang into action”.[15]
Rambaut was one of the authors of the scientific paper The proximal origin of SARS-CoV-2,[16] which concluded that “SARS-CoV-2 is not a laboratory construct or a purposefully manipulated virus”.
Rambaut is an attendee of the UK’s Scientific Advisory Group for Emergencies (SAGE).[17]
Perhaps someone else can look up his recent research grants. Were they from NIH or Wellcome? Being rewarded royally with other peoples’ money is another characteristic of the virology spook group.
How can this government of deceivers protect our ‘safety’?
By Suzie Halewood | TCW Defending Fredom | June 7, 2022
HOW can a government that locked us down, collapsed our businesses, imposed a useless mask compliance regime, misled us about the severity of Covid while stifling information about safe, effective treatments in order to force through emergency use approval for ‘vaccines’ and nudge us towards experimental treatments that not only failed to prevent transmission, but caused irreversible damage and death, be in any position to decide what constitutes ‘harm’?
Yet here comes the Online Safety Bill, threatening not only hefty fines from free-press-suppressing Ofcom, but also prison time for anybody judged to have caused psychological harm leading to ‘serious distress’. Harmful content could include online bullying and abuse, advocacy of self-harm and the spreading of misinformation (defined as information that is false, but not created with the intention of causing harm) disinformation (information that is false and created to harm a person, social group, organisation or country) and malinformation (information that is based on reality, used to inflict harm on a person, organisation or country).
Section 53 (c) of the Online Safety Bill determines offending content to be anything that ‘presents a material risk of significant harm to an appreciable number of children in the United Kingdom’.
Like a vaccine then, or masks, or not seeing your friends, or not being able to go out, or attend school and with the added fear that by being ‘selfish’ and not taking a vaccine you didn’t need, you could kill your granny, mum, dad and teacher. Little wonder 374,646 children and young people contacted mental health services last month. The number of adults contacting mental health services in the same period was 1,054,003.
Harms with a less clear legal definition include ‘Coercive Behaviour’ (a government speciality), ‘Disinformation’ (Gates-funded MSM, WHO and all those ‘fact-checkers’ sponsored by the usual suspects), ‘Intimidation’ (jabs for jobs) and ‘Advocacy of Self-Harm’ (‘vaccines’).
The Bill, which also ‘protects’ adults – in case, God forbid, we might have the temerity to think for ourselves – empowers Ofcom to block users, control, moderate and take down content. Criminal sanctions currently in ‘reserve’ could be imposed on tech giants if they fail to clean up their acts or do not ‘allow Ofcom access to their algorithms’ – algorithms that show ‘how easily, quickly and widely content may be disseminated by means of the service’. In other words, Ofcom has been given free rein to make any significant change to a risk profile and make their own assessment as to the level of risk of harm to adults and how quickly such perceived-to-be-harmful content can be spread. So if Ofcom decides – as with YouTube’s Covid-19 Misinformation Policy (slight conflict of interests since Google Ventures invested in the AZ ‘vaccine’) which defines medical misinformation as any content that ‘contradicts guidance from the WHO or local health authorities’ – that ivermectin can cause harm, they can take down any mention of ivermectin (even if the only damage caused by ivermectin is to the profits of the pharma criminals) regardless of the fact Ofcom does not employ immunologists, epidemiologists or virologists.
As for ‘hate speech’, defined as ‘all forms of expression which spread, incite, promote or justify hatred based on intolerance on the grounds of . . . belief . . . or opinion’, would Piers Morgan’s ‘Anti-vaxxers really are a bunch of spineless pussies’ tweet, or Noam Chomsky’s insistence that the unvaccinated be segregated and that getting food was ‘their problem’, qualify as hate speech? Of course not. Their views are in line with The Agenda.
Adults don’t need Ofcom chief executive Dame Melanie Dawes deciding for them what they can or can’t watch (I use a VPN for Russia Today, Melanie) any more than they need Bill Gates telling them what they can eat (synthetic burgers) or Nadine Dorries pushing through the government’s idea of what constitutes harm or safety. Offence is taken, not given. If I wish to be offended, that’s my choice.
If the government genuinely cared about harm, they’d have carried out risk assessments to weigh up the pros (none) and cons (it was) of locking down the country. They wouldn’t have wilfully terrified the public when they knew full well Covid wasn’t a risk, as they themselves were partying like it was 1984.
Had Nadine ‘I’m A Celebrity . . . Get Me Out of Here’ Dorries cared about ‘harm’ she’d have voluntarily answered one of the 50 letters and emails sent to her by one of her own vaccine-injured constituents instead of having to be pressured into a response by a lobbying group taking up the cause of the vaccine-injured.
If the government cared one iota for the electorate, the vaccine rollout would surely have been halted following a September 2021 meeting in which Tess Lawrie, Dolores Cahill, Mike Yeadon and other doctors and scientists presented damning evidence to Sir Graham Brady of the 1922 Committee which illustrated how a mass rollout of the Covid-19 ‘vaccines’ for children would lead to children being maimed, killed and sterilised.
Such disregard for the electorate runs throughout government. There was a full house for Zelensky’s Churchill-plagiarising extravaganza compared with a paltry five MPs for the reading of Sir Christopher Chope’s Private Member’s Bill aimed at reforming the government’s Vaccine Damages Payment Scheme (VDPS).
Despite more than 2,000 deaths and approaching a million and half injuries (including blindness, strokes and paralysis) reported to MHRA’s Yellow Card scheme (set up following the thalidomide scandal) no compensation has yet been paid. As the VDPS doesn’t consider death as a qualifier for the 60 per cent disability requirement needed to pay out the paltry £120,000 to cover a lifetime of injury, clearly they’re already trying to wriggle out of it.
Before the Online Harms Bill goes any further, it might be a good idea to decide who is the best legal arbiter to rule on what unequivocally constitutes mis-, dis- or mal-information and who in the government (if anyone) has the moral authority or psychological capacity to judge what represents psychological ‘harm’ either to a child or an adult.
If the Online Safety Bill does pass, first in the dock should be the government.
WHO prepares for climate change emergencies

The Counter Signal | June 7, 2022
Speaking on behalf of the World Health Organization (WHO), International Council of Nurses CEO Howard Catton claimed that climate change is the ”grandmother of all health threats.”
“I talk to nurses around the world every week who tell me about how they see the impacts of climate change on the health of people they care for every single day in their practice,” Catton said. “There are 45 million-plus healthcare professionals who are witnesses to the health emergency that is unfolding in plain sight.”
“Their voice must be heard and acted on.”
He continues, conflating the damage caused by poor air quality and pollution — likely in places like China and India, not the developed countries of the West — with the supposed damage caused by minute rising temperatures. WHO Director-General Tedros Adhanom, of course, agrees with this radical climate change position.
“They see and work with young people struggling and old people struggling with respiratory disorders caused or exacerbated by poor air quality and pollution. People who can’t go out, who are struggling with their tasks of daily living, who are losing function, whose independence undermined,” Catton said.
“They support people who are not coping with extreme temperature changes from heat stroke and exhaustion to hypothermia. Many of these people are [the] most vulnerable, with underlying conditions, such as cardiovascular disease, which is made worse.”
According to Climate.gov, the global average temperature has risen by 1 degree Celsius over the last 40 years… This is the “extreme temperature” change that Catton speaks of, without going into the fact weather trends fluctuate and we, in the broader scheme of things, just came out of a little ice age, which probably should just be labelled a light cooling period between 1500-1850 AD (starting before the Industrial Revolution and ending as it was kicking off).
Catton continues, blaming the 1-degree Celsius change in global temperatures for natural occurrences like flooding and forest fires, which he says perpetuates the spread of disease.
For these reasons, Catton says that climate change is one of the greatest risks to global health and that health needs “to be at the centre of all our policies: energy, transport, agriculture, water, and food.”
The American Heart Association Renders Itself Obsolete With Long-Refuted Dietary Advice
This article was previously published July 5, 2017, and has been updated with new information.
By Dr. Joseph Mercola | June 6, 2022
For well over half-century, a majority of health care officials and media have warned that saturated fats are bad for your health and lead to obesity, high cholesterol and heart disease. The American Heart Association (AHA) began encouraging Americans to limit dietary fat in general and saturated fats in particular as far back as 1961.
Like its previously revised version, the current version of the U.S. Department of Agriculture’s food pyramid, called “MyPlate,”1 more or less eliminates fats altogether, with the exception of a small amount of low-fat or no-fat dairy. According to MyPlate, the food groups are fruits, vegetables, grains, protein and dairy — not the three biological building blocks known as carbohydrates (fruits, vegetables, grains), protein and fats.
All the while, studies have repeatedly refuted the wisdom of these low- to no-fat recommendations. Even so, the AHA has spent the past decade issuing warnings reminiscent of the 1960s all over again.
If you’ve followed the news, you’ve seen bold headlines declaring coconut oil dangerous, and that you should switch from butter to margarine to protect your heart health! How is this even possible? It’s akin to the flat Earth theory that inexplicably gained traction despite clear and indisputable proof that we indeed live on a planetary sphere.
Many have expressed confusion and bewilderment in response to the AHA’s margarine push, and no wonder. Let’s not forget that creating doubt is a core strategy used by industry to delay change. This margarine-promotion also happens to conveniently sync up with news about a vaccine to lower cholesterol2,3 — a strategy that would be unnecessary if people were to just eat healthy saturated fats like coconut oil and butter, and eliminate processed foods and sugar.
The vaccine first made news in 2015,4 but nearly seven years later, in October 2021, researchers were lamenting that the vaccine was still in trials, and that although significant reductions in LDL were observed in mouse studies, there were still concerns about the cost, limitations of shelf-life and safety that were holding it back.5
AHA Sends Out Warning to Cardiologists Around the World
According to the AHA,6 saturated fats such as butter and coconut oil should be avoided to cut your risk of heart disease. Replacing these fats with polyunsaturated fats such as margarine and vegetable oil might cut heart disease risk by as much as 30%, about the same as statins, the AHA claims.
This “Presidential Advisory” was sent out to cardiologists around the world, not just to those in the U.S. Overall, the AHA recommends limiting your daily saturated fat intake to 5 to 6% of daily calories or less.7 According to The Daily Mail :8
“The scientists analyzed all available evidence on the subject and found saturated fat — such as that found in butter, whole milk, cream, palm oil, coconut oil, beef and pork — was linked to an increased risk of heart disease.
Replacing this with polyunsaturated fat — found in spreads and vegetable oils — or monounsaturated oils found in olive oil, avocados and nuts — cuts the risk of heart problems. The study … bolsters NHS advice that saturated fat should be lowered in the diet.
Lead author professor Frank Sacks, of Harvard School of Public Health, said: ‘We want to set the record straight on why well-conducted scientific research overwhelmingly supports limiting saturated fat in the diet to prevent diseases of the heart and blood vessels. Saturated fat increases LDL — bad cholesterol — which is a major cause of artery-clogging plaque and cardiovascular disease’ …
The authors, however, warned that not all margarines and spreads are healthy. They found that some forms of margarine which use ‘trans fats’ — a type of fat which improves shelf life — actually raise the risk of heart disease.”
Victoria Taylor, senior dietitian at the British Heart Foundation, also made sure to note that “lifestyle change should go hand in hand with taking any medication prescribed by your doctor; it shouldn’t be seen as one or the other.” In other words, don’t think you can avoid statins simply by eating right.
Then, referencing coconut oil specifically, the AHA added: “Because coconut oil increases LDL cholesterol, a cause of CVD [cardiovascular disease], and has no known offsetting favorable effects, we advise against the use of coconut oil.”9 USA Today announced that advisory with a June 16, 2017, nonsensical headline, “Coconut Oil Is About as Healthy as Beef Fat or Butter.”10
Why, yes, it is! But what they were trying to claim was that all of these are unhealthy, which is altogether backward and upside-down. It didn’t take long for USA Today to realize its faus pax, though, so it changed the headline June 21, 2017, to “Coconut Oil Isn’t Healthy. It’s Never Been Healthy.”11
While the newspaper noted the “correction” on its webpage, all references to the original headline have been scrubbed from the internet archive, Wayback.12 So much for transparency in newspaper reporting.
On What Evidence Does AHA Base Their Recommendation?
How did the AHA come to the conclusion that they were right about saturated fat 60 years ago and have been right all along? In short, by cherry-picking the data that supported their outdated view. As noted by American science writer Gary Taubes in his extensive rebuttal to the AHA’s advisory:13
“The history of science is littered with failed hypotheses based on selective interpretation of the evidence … Today’s Presidential Advisory … may be the most egregious example of Bing Crosby epidemiology [‘accentuate the positive and eliminate the negative’] that I’ve ever seen … [T]hey methodically eliminate the negative and accentuate the positive until they can make the case that they are surely, clearly and unequivocally right …
[T] he AHA concludes that only four clinical trials have ever been done with sufficiently reliable methodology to allow them to assess the value of replacing SFAs with PUFAs (in practice replacing animal fats [with] vegetable oils) and concludes that this replacement will reduce heart attacks by 30 percent …
These four trials are the ones that are left after the AHA experts have systematically picked through the others and found reasons to reject all that didn’t find such a large positive effect, including a significant number that happened to suggest the opposite …
They do this for every trial but the four, including among the rejections the largest trials ever done: the Minnesota Coronary Survey, the Sydney Heart Study and, most notably, the Women’s Health Initiative, which was the single largest and most expensive clinical trial ever done. All of these resulted in evidence that refuted the hypothesis. All are rejected from the analysis.”
Taubes, an investigative science and health journalist who has written several books on obesity and diet, points out that this advisory document actually reveals the AHA’s longstanding prejudice and the method by which it reaches its conclusions.
In 2013, the AHA released a report14 claiming “the strongest possible evidence” supported the recommendation to replace saturated fat with polyunsaturated fats (PUFAs). This, despite the fact that several meta-analyses, produced by independent researchers, concluded the evidence for restricting saturated fats was weak or lacking.
The advisory document reveals how the AHA could conclude they had the “strongest possible evidence.” Then, as now, they methodically came up with justifications to simply exclude the contrary evidence. All that was left — then and now — were a small number of studies that support their preconceived view of what they think the truth should be.
AHA’s Referenced Studies Are Based on Outdated Science
Would it surprise you to find out that the four studies that made the cut all date from the 1960s and early 1970s? It makes sense, doesn’t it, since those are the eras when the low-fat myth was born and grew to take hold. The problem is nutritional science has made significant strides since then.
As noted by Taubes, one of the studies included was the Oslo Diet-Heart Study,15 published in 1970, in which 412 patients who’d had a heart attack or were at high risk of heart disease were randomized into two groups: One group got a low-saturated fat, high-PUFA diet along with ongoing, long-term “instruction and supervision” while the other group ate whatever they wanted and received no nutritional counseling whatsoever.
“This is technically called performance bias and it’s the equivalent of doing an unblinded drug trial without a placebo. It is literally an uncontrolled trial, despite the randomization. (… [A]ll the physicians involved also knew whether their patients were assigned to the intervention group or the control, which makes investigator bias all that much more likely.)
We would never accept such a trial as a valid test of a drug. Why do it for diet? Well, maybe because it can be used to support our preconceptions,” Taubes writes.
Taubes goes on to state that he was so curious about this Oslo study he bought a monograph published by the original author. In it, the author describes in more detail how he went about conducting his trial. Interestingly, this monograph reveals that the sugar consumption in the treatment group was only about 50 grams a day — an amount Taubes estimates may be about half the per capita consumption in Norway at that time, based on extrapolated data.16
“In this trial, the variable that’s supposed to be different is the [saturated fat]/PUFA ratio, but the performance bias introduces another one. One group gets continuous counseling to eat healthy, one group doesn’t. Now how can that continuous counseling influence health status?
One way is that apparently, the group that got it decided to eat a hell of lot less sugar. This unintended consequence now gives another possible explanation for why these folks had so many fewer heart attacks. I don’t know if this is true. The point is neither did Leren.
And neither do our AHA authorities,” Taubes writes. “All of the four studies used to support the 30 percent number had significant flaws, often this very same performance bias. Reason to reject them.”
Dangerous Advice
Dr. Cate Shanahan,17 a family physician and author of “Deep Nutrition: Why Your Genes Need Traditional Food,” emailed me an even stronger rebuttal, saying, “This message from the AHA is not only false, it is dangerous,” noting that the AHA is actually making false claims since none of the four studies they included in their analysis involved coconut oil.
As an explanatory side note, most of the early studies on coconut oil that found less than favorable results used partially hydrogenated coconut oil, not unrefined virgin coconut oil.18 As always, the devil’s in the details, and hydrogenated oil is not the same as unrefined oil, even when you’re talking about something as healthy as coconut. This little detail is what led to the undeserved vilification of coconut oil in the first place. That said, let’s look at what else Shanahan has to say on the matter:
“Most doctors don’t notice that the medical leadership is making unfounded claims, and the reason they don’t notice is because … articles asserting the existence of human clinical trial evidence against coconut as well as all other foods high in saturated fat, conflate the sources of saturated fat with the saturated fat itself.
Saturated fat does not actually exist in the food chain; what they’re talking about are saturated fatty acids, the components of triglyceride fat, the substance chefs call simply ‘fat.’ We often say things like ‘coconut oil is a saturated fat’ and ‘butter is a saturated fat.’ But it would be more correct to say ‘coconut oil is high in saturated fatty acids.’
Coconut oil, butter, lard, tallow and every other animal fat also contain monounsaturated and even some polyunsaturated fatty acids in addition to saturated fatty acids … The idea is foods contain blends of fatty acids in varying proportion.”
Put another way, most foods contain a blend of fatty acids, not just one. Margarine and shortening also contain saturated fatty acids, yet the AHA makes no mention of this. The harder the margarine, the more saturated fat it tends to contain, in some cases more than butter or lard.
“So, when people eat margarine and shortening, in addition to toxic trans fatty acids they’re also eating saturated fatty acids. And that means that when a study says it’s swapping out saturated fat for vegetable oils, that does not equate to swapping out butter and lard. It could very well be the case that margarine and shortenings were among the foods that got eliminated,” Shanahan says.
“And because most doctors don’t realize that margarine and shortenings contain saturated fatty acids, they also don’t consider it particularly important to wonder whether or not studies like the four core citations mentioned in the Advisory are actually confounded by the fact that the baseline, high-saturated fat diet included a significant amount of margarines and shortenings that contain toxic trans fat.
Because if they did, then that means whatever health benefits were observed in the studies may have nothing to do with the reductions in saturated fat. It’s cutting back on trans fat that makes the difference to health.”
Non-Saturated Fat Recommendations Have Been Followed With Disastrous Results
Since the 1950s, when vegetable oils began being promoted over saturated fats like butter, Americans have dutifully followed this advice, dramatically increasing consumption of vegetable oil. Soy oil, for example, rose by 600% (10,000% from 1900) while butter, tallow and lard consumption halved.
We’ve also dramatically increased sugar consumption, with more than half of Americans consuming over 17 teaspoons a sugar a day in 2021.19 That’s down from the 25 teaspoons a day they were consuming in 2014,20 but it’s still more than the maximum 12 teaspoons recommended by the CDC.
Alas, rather than becoming healthier than ever, Americans have only gotten fatter and sicker. Heart disease rates have not improved even though people have been eating what the AHA suggests is a heart-healthy diet. Common sense tells us if the AHA’s advice hasn’t worked in the last 65 years, it’s not likely to start working now.
As noted by Shanahan, technology that allows us to study molecular reactions is relatively recent, and certainly was not available back in the ‘60s and ‘70s. Modern research is just now starting to reveal what actually happens at the molecular level when you consume vegetable oil and margarine, and it’s not good.
For example, Dr. Sanjoy Ghosh,21 a biologist at the University of British Columbia, has shown your mitochondria cannot easily use polyunsaturated fats for fuel due to the fats’ unique molecular structure.
Other researchers have shown the PUFA linoleic acid can cause cell death in addition to hindering mitochondrial function.22 PUFAs are also not readily stored in subcutaneous fat. Instead, these tend to get deposited in your liver, where they contribute to fatty liver disease, and in your arteries, where they contribute to atherosclerosis.
According to Frances Sladek,23 Ph.D., a toxicologist and professor of cell biology at UC Riverside, PUFAs behave like a toxin that builds up in tissues because your body cannot easily rid itself of it. When vegetable oils like sunflower oil and corn oil are heated, cancer-causing chemicals like aldehydes are also produced.24
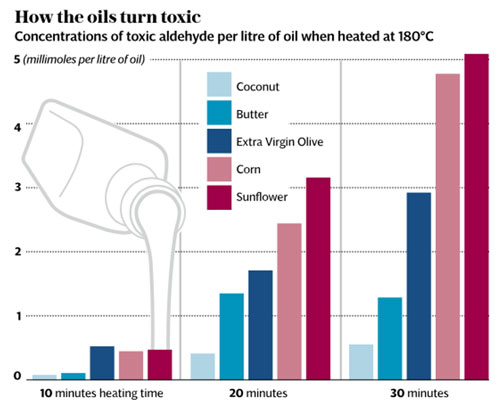
Source: The Telegraph November 7, 2015
Not surprisingly, fried foods are linked to an increased risk of death. In fact, eating fried potatoes more than twice a week was found to double a person’s risk of death compared to never eating fried potatoes.25 Animal and human research has also found vegetable oils promote:
- Obesity and fatty liver26
- Lethargy and prediabetic symptoms27
- Chronic pain/idiopathic pain syndromes (meaning pain with no discernible cause)28
- Migraines29
- Crohn’s disease and ulcerative colitis30
Biochemistry Versus Statistics
According to Shanahan, the idea that PUFAs are healthier than saturated fats falls flat when you enter the field of biochemistry, because it’s “biochemically implausible.” In other words, the molecular structure of PUFA is such that it’s prone to react with oxygen, and these reactions disrupt cellular activity and cause inflammation.31 Oxidative stress and inflammation, in turn, are hallmarks not only of heart disease and heart attacks but of most chronic diseases.32
“Meanwhile, the folks at the AHA claim saturated fat is pro-inflammatory and causes arterial plaque and heart attacks — but there is no biochemically plausible explanation for their argument. Saturated fat is very stable, and will not react with oxygen the way PUFA fat does, not until the fundamental laws of the universe are altered,” Shanahan writes.
“Our bodies do need some PUFA fat, but we need it to come from food like walnuts and salmon or gently processed (as in cold pressed, unrefined) oils like flax and artisanal grapeseed, not from vegetable oils because these are refined, bleached and deodorized, and the PUFA fats are molecularly mangled into toxins our body cannot use.”
The Cholesterol Argument
Researchers have also laid waste to the notion that having high cholesterol is a primary contributor to heart disease in the first place. This is the basic premise upon which the AHA builds its conclusion that saturated fats are bad for you. The idea is that saturated fats raise your cholesterol level, thus raising your risk for heart disease. But again, they use too broad a brush and ignore the details. For example:
•A recent study33 published in The BMJ reanalyzed data from the Minnesota Coronary Experiment (MCE) that took place between 1968 and 1973, after gaining access to previously unpublished data. This was a double-blind, randomized controlled trial to test whether replacing saturated fat with vegetable oil (high in linoleic acid) would lower cholesterol levels, thus reducing heart disease and related deaths.
Interestingly, while the treatment group did significantly lower their cholesterol, no mortality benefit could be found. In fact, for each 30 milligrams per deciliter (mg/dL) reduction in serum cholesterol, the risk of death increased by 22%. Swapping saturated fat for vegetable oil also had no effect on atherosclerosis rates or heart attacks. As noted by the authors:
“Available evidence … shows that replacement of saturated fat in the diet with linoleic acid effectively lowers serum cholesterol but does not support the hypothesis that this translates to a lower risk of death from coronary heart disease or all causes. Findings … add to growing evidence that incomplete publication has contributed to overestimation of the benefits of replacing saturated fat with vegetable oils …”
•The AHA also does not take LDL particle number into consideration. There are large, fluffy LDL particles and small, dense ones. We didn’t have this information in the 1960s, but we sure have it now.
This is yet another crucial detail that makes all the difference in the world, as large LDL particles have been shown to be harmless and do not raise your risk for heart disease. And guess what? Sugar promotes harmful small, dense LDLs while saturated fats found in butter and coconut oil promotes harmless large, fluffy LDLs.34
Is Coconut Oil Healthy or Not?
The short answer is yes, coconut oil is healthy. It’s been a dietary staple for millennia, providing you with high-quality fat that is important for optimal health. It supports thyroid function, normalizes insulin and leptin function, boosts metabolism and provides excellent and readily available fuel for your body in lieu of carbohydrates (which you need to avoid if you want to lose weight).
A really important benefit of coconut oil is related to the fact that the ketones your liver creates from it are the preferred fuel for your body, especially your heart and brain, and may be key for the prevention of heart disease and Alzheimer’s. It truly is a healthy staple that belongs in everyone’s kitchen.
Coconut oil contains medium chain triglycerides (MCTs), and their smaller particle size helps them penetrate your cell membranes more easily. However, MCT oil has a far higher concentration of these shorter chain fats that are more efficiently converted to ketones; C8 or caprylic acid has the best ability to convert to ketones.
MCTs do not require special enzymes and they can be utilized more effectively by your body, thus putting less strain on your digestive system. Normally, a fat taken into your body must be emulsified with bile from your gallbladder before it can be broken down and properly absorbed. Long chain fats therefore frequently end up being stored in your fat cells.
However, your body treats MCTs differently. MCTs bypass the bile and fat storage process and go directly to your liver, where they are converted into ketones. Your liver quickly releases the ketones into your bloodstream where they are transported around your body to be used as fuel. By being immediately converted into energy rather than being stored as fat, MCTs stimulate your body’s metabolism and help promote weight loss.
Coconut Oil Promotes Thyroid Health
Part of coconut oil’s health benefits also relate to its beneficial impact on your thyroid. Unlike many other oils, coconut oil does not interfere with T4 to T3 conversion, and T4 must be converted to T3 in order to create the enzymes needed to convert fats to energy.
Part of what makes processed vegetable oils so damaging to the thyroid is that they oxidize quickly and become rancid, which prevents the fatty acids from being deposited into your cells, thereby impairing the conversion of T4 to T3. This is symptomatic of hypothyroidism. Coconut oil is a saturated fat and therefore very stable and not susceptible to oxidation.
The fact that coconut oil doesn’t go rancid helps boost your thyroid function. Eliminating processed vegetable oils from your diet and replacing them with coconut oil can, over time, help rebuild cell membranes in your liver (where much of the thyroid hormone conversion occurs) and increase enzyme production. This will assist in promoting the conversion of T4 to T3 hormones.
The most common fat in coconut oil is lauric acid, often considered a “miracle” fat because of its unique health-promoting properties. Your body converts lauric acid into monolaurin, which has antiviral, antibacterial and antiprotozoal properties.
Thyroid problems can often be traced back to chronic inflammation, which the lauric acid in coconut oil can help suppress. To obtain the full range of coconut oil’s health and weight loss benefits, I typically recommend 2 to 3 1/2 tablespoons per day for adults.
That said, there is at least one instance where coconut oil is contraindicated due to its lauric acid content. In his book, “The Plant Paradox: The Hidden Dangers in ‘Healthy’ Foods That Cause Disease and Weight Gain,” Dr. Steven Gundry explains how coconut oil may be problematic if you have leaky gut, which is almost universal in individuals who are not paying attention to their lectin intake.
As it turns out, lipopolysaccharide (LPS), an endotoxin, attaches to lauric acid, facilitating its transport past your gut lining into your blood stream. Interestingly, MCT oil does not do this. So, if you have leaky gut, or unless you’re healthy and eating a lectin-free diet, it may be best to avoid coconut oil and use MCT oil instead. Caprylic acid would be best, but neither of these will allow LPS to piggyback into your blood stream. You can learn more about lectins in my interview with Gundry.
Who Pays the AHA?
Science has revealed the low-fat diet to be corporate-promoted misinformation, yet the AHA keeps insisting it’s the heart-healthy choice. Why? As noted by cardiologist Dr. Barbara Roberts in an article in The Daily Beast in 2014,35 “The quick answer: money, honey.” Roberts points out that one of the reasons the AHA clings to “recommendations that fly in the face of scientific evidence” is because of its ties to Big Food.
One of its primary revenue streams is its Heart Check Food Certification Program, which is updated monthly.36 Foods bearing this certification mark are supposed to make it easier for consumers to select products to include in a heart-healthy diet. Companies pay about $700,000 annually for the right to use this mark on their packaging.37
As of May 2022, the AHA endorsed hundreds of foods as heart-healthy, including breads, cereals, pastas and pasta sauces, potatoes, egg substitutes, dried and canned fruits and processed meats.38
In other words, a whole bunch of stuff you really shouldn’t eat if you care about your health in general and your heart in particular is on the list. Processed meats, for example, have been deemed so hazardous there’s no safe limit.39 The AHA also has endorsed Subway sandwiches40 and Cheerios41 in the past and accepts hundreds of millions of dollars in funding from a long list of drug companies.42 As noted by Roberts:43
“Even more problematic are the foods containing added sugar … The AHA recommends that women consume less than 6 teaspoons (100 calories) of sugar a day and less than 9 teaspoons (150 calories) for men.
Yet there are items that get the nod of approval from the Heart Check program despite being near or at the sugar limit, like Bruce’s Yams Candied Sweet Potatoes … Indeed, until 2010, the Heart Check imprimatur was stamped on a drink called Chocolate Moose Attack, which contained more sugar per ounce than regular Pepsi. And until [2014], Heart Check approved many foods with trans fats …”
AHA Was Wrong in the 1960s and Is Still Wrong
Heart disease is primarily caused by chronic inflammation, which is caused by excessive amounts of omega-6 (unbalanced omega-6 to omega-3), dangerous trans fats, processed vegetable oils and excessive sugar in the diet. Saturated fats, on the other hand, have been repeatedly exonerated, with studies showing they do not contribute to heart disease and are in fact a very important source of fuel for your body.
Granted, it’s tough to admit you’ve been wrong for 65-plus years. Such an admission can mar an organization’s reputation. But in trying to turn back the clock to 1960 and promote margarine and vegetable oils over butter and coconut oil, the AHA is proving itself obsolete.
This recommendation is, in my view, professionally irresponsible. It’s completely irrational in the face of modern nutritional science. With it, the AHA has painted itself into a corner from which it cannot extract itself without turning the entire organization upside-down. As noted by Dave Asprey, founder of Bulletproof.com :44
“The AHA campaign is backfiring because of the millions of people who already know that adding undamaged saturated fats into their diets makes them feel better. They can feel the difference in their energy, see it in the mirror, and measure it in their blood work …
These anti-coconut oil AHA guidelines are an orchestrated PR campaign aimed at changing what we eat to match what is in the interests of the AHA’s corporate sponsors, regardless of what recent research suggests.
As the U.S. population gets more educated about the benefits of saturated fats and the harm posed by processed seed and vegetable oils, processed food manufacturers are looking for ways to trick us into eating the cheap, high profit, damaging ‘food’ they create and sell.
That appears to be why they sponsor the [AHA]. These new recommendations are from an industry special interest group that promotes low-fat, high-sugar diets that kill people and has the audacity to label them as ‘heart healthy.’ In fact, the AHA executive leading the charge against coconut oil is the same guy that used to run marketing for Kentucky Fried Chicken and other fast-food chains.”
Sources and References
- 1 MyPlate.gov. Dietary Guidelines for Americans 2020-2025
- 2 BBC News June 20, 2017
- 3 Medical News Today June 20, 2017
- 4 First Report Managed Care. January 13, 2015
- 5 European Heart Journal. Volume 42, Issue 39, 14 October 2021, Pages 4007–4010
- 6 Circulation, AHA Presidential Advisory June 15, 2017
- 7 Heart. Saturated Fat. November 1, 2021
- 8 The Daily Mail June 15, 2017
- 9, 11 USA Today. Coconut Isn’t Healthy. June 21, 2017
- 10, 12 Wayback. USA Today July
- 13 Cardiobrief.org June 16, 2017
- 14 Circulation, AHA/ACC Prevention Guideline November 12, 2013
- 15 Circulation, The Oslo Diet-Heart Study November 1, 1970
- 16 Statista, Per Capita Consumption of Sugar in Norway 1979 to 2015
- 17 Drcate.com
- 18 New York Times March 1, 2011
- 19 CDC. Added Sugars Consumption in Adults. November 28, 2021
- 20 Healthy Food America. 2014
- 21 University of British Columbia, Sanjoy Ghosh
- 22 Biochimica et Biophysica Acta September 10, 2002: 1555(1-3): 160-165
- 23 Breaking News Today. February 24, 2022. How Coconut Oil Can Benefit Your Health
- 24 Telegraph November 7, 2015
- 25 News.com.au June 14, 2017
- 26 Drcate.com, November 15, 2016
- 27 Vancouver Sun December 18, 2014
- 28 Molecular Pain 2016 Mar 10;12
- 29 Pain 013 Nov;154(11):2441-51
- 30 Nutrition Research 008 Apr;28(4):239-44
- 31 Lipid Peroxidation in Vivo, Eva Sodergren
- 32 Curr Biol. 2014 May 19; 24(10): R453–R462
- 33 BMJ 2016;353:i1246
- 34 American Journal of Clinical Nutrition May 1998; 67(5): 828-836
- 35, 43 The Daily Beast May 22, 2014
- 36 Heart.org
- 37, 40 Ancestral Nutrition June 24, 2013
- 38 Heart Check Food Certification Program. May 3, 2022
- 39 Physicians Committee for Responsible Medicine
- 41 YouTube. MotivationalDoc. August 3, 2021
- 42 2018-2019 AHA Support From Pharmaceutical … Companies
- 44 DaveAsprey.com. Why Coconut Oil Is Better Than Vegetable Oil
Featured Video

Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
or go to
Aletho News Archives – Video-Images
New Book
Trans agenda is ‘normalization of sadism’ – US author

RT | September 23, 2026
The US Democratic Party has embraced a transgender agenda that amounts to “the normalization of sadism,” author A.J. Rice has said, warning that radical trans policies would return if the party is allowed to regain power.
Speaking to RT’s America First host Scotty Nell Hughes about his new book, ‘The Curse of the Bearded Lady: How the Trans Mafia Whacked American Sanity’, Rice argued that activists have gained significant influence in schools, medicine, and corporate America while people who questioned the agenda have faced pressure to stay silent.
The author described the “trans mafia” as the sprawling network of people and institutions that have helped the movement gain influence. He singled out parts of academia, wealthy backers, and corporations, and stated that providers of transition-related treatment also have a financial incentive to keep young people in their care indefinitely.
Rice argued that the consequences of these policies ultimately fall on children who are being drawn toward gender-affirming medical treatments and on girls who are expected to share locker rooms or compete in sports with biological males.
He noted that while voters rejected the Democrats’ approach to gender in 2024, the party, which has been “captured by madness,” has since only doubled down and is seeking what is effectively “the normalization of sadism.” … Full report
Blog Roll
 Aletho News
- Refaat Al-Areer Was The Canary In The Coal Mine In Israel’s War On The Truth
- Israeli election committee bars candidate from Knesset race over Gaza war opposition
- French-Lebanese man files war crimes complaint over Israeli attacks
- Mahan Air Flight Lands in China Despite US Threat against Iranian Airlines
- US eyes $10bn fund to rebuild war-battered Gulf infrastructure
- Trump meets Rodríguez near Maduro’s prison as Venezuela’s oil flows to US
- Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
- Iran FM meets with US envoy on UN meeting’s sidelines at American side’s insistence: Report
- Qatar PM calls for Gulf security framework with Iran, says war must be ‘wake-up call’
- China condemns US extortion of Iranian airlines, rejects Washington’s ‘illegal’ sanctions threats
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

