
State-sponsored/MSM supported medical tyranny is the new abnormal throughout the US/West and elsewhere worldwide.
I’m greatly indebted to numerous truth-telling medical and scientific experts for teaching me what I’ve learned about all things flu/covid — a medical education I never imagined getting pre-2020 but got since then on this most cutting edge of all issues.
To my great dismay, intelligent people I know are oblivious to reality on what’s crucial to know — believing rubbish fed them daily from official, MSM, and other disreputable sources instead of what’s scientifically indisputable.
Protecting and preserving public health and freedom depend on enough committed people rising up against what’s going on — slaying it before it slays us.
Relief won’t come judicially or legislatively.
On all issues mattering most, positive change never comes top down, only bottom up by committed people demanding no less.
The anti-public health/anti-freedom scheme was planned well before its rollout early last year.
As explained time and again, it’s all about wanting maximum numbers of unwanted people eliminated worldwide, along with transforming free and open societies into ruler/serf ones for survivors.
It’s a draconian new world order fit only for privileged interests at the expense or all others.
It’s what no one anywhere should tolerate, a tyrannical world that’s unsafe and unfit to live for the vast majority worldwide — the worst of all possible worlds.
Things don’t have to be this way.
Ordinary people have power to rise up against injustice, defy unjustifiable rules, disrupt best laid plans of dark forces and achieve positive change by their actions.
History proves it. Years of anti-war activism helped end a decade of US aggression in Southeast Asia — a pyrrhic victory as things turned out because anti-war activism waned.
The same applies to moving from chattel to wage slavery, from Jim Crow to its modern-day version, from freedom to mass incarceration, from healthcare as it should be to toxic mass-jabbing with unparalleled genocide in mind.
Governance of, by and for entrenched interests in the US/West and elsewhere is too debauched to fix.
The same goes for MSM guardians of wealth, power and privilege.
Scattered reforms won’t work. Transformational change is needed.
The only solution is popular revolution. Anything less assures no change of unacceptable same old, same old.
Wealth, power and privileged interests are enemies of ordinary people everywhere.
Collective defiance is needed to turn things from what’s destructive of the general welfare to what’s beneficial.
Former Pfizer vice president, its chief scientist for allergy and infectious diseases, co-founder of Doctors for (flu/covid) Ethics, Dr. Michael Yeadon, is on the right side of history for this most crucial of all issues.
Commenting on what’s gone on since early last year, he said the diabolical scheme has nothing to do with protecting us, everything to do with establishing “totalitarian control.”
Fundamental freedoms are being abolished incrementally.
Things began by denying refuseniks free access to restaurants and other places where large numbers gather.
Widespread use of freedom-destroying health passports may follow as a requirement to stay free from societal isolation altogether.
Yeadon compared the above to “dropping a cancerous cell into your body (that) grows and metastasizes and then it kills you.”
“(T)hat’s what” health passports are all about if instituted.
“So don’t tolerate them anywhere,” Yeadon stressed.
Once instituted, metastasizing will “regulate access to essential services like food, money, fuel, trains and things like that.”
“You’ll never get rid of (them). We’ve got to stop (what’s going on) beforehand.”
Otherwise we’ll “lose the ability to decide where to be at any time.”
Health passports will “regulate entry and exit from almost any controlled space, possibly even including your own home.”
“You’ll be required to keep your passport up to date by being fully jabbed” — meaning forever-jabbed one or more time annually.
The more toxic jabs gotten, the sooner your end time will arrive, most likely very unpleasantly from painful and/or debilitating disease(s).
Getting informed from reliable independent sources, getting motivated and enraged enough to no longer tolerate what’s going on is the only way to halt it once and for all.
“(I)t’s us” on our own against the diabolical scheme. We alone can and must stop it.
The alternative is deeply entrenched tyranny, a permanent new abnormal, dystopia no one should tolerate.
Jabs are vehicles of mass-extermination.
Pharma profiteers and Big Government backers “are the most ruthless of all corporate entities,” Dr. Vernon Coleman stressed, adding:
It’s been known since last year that mass-jabbing “cause(s) heart trouble, strokes, neurological problems,” and other serious health issues.
Coleman believes that most jabbed individuals will be “lucky to last five years.”
Individuals taking them “should be considered suicidal or certified insane.”
“Life expectation is going to fall dramatically – and not just because the quality of health care is deteriorating daily.”
“I honestly find it difficult to believe that there are people around who are so brainwashed and so terrified by the lies they’ve heard that they will accept as many jabs as they are offered.”
The power of repetition, especially on propaganda TV, gets most people — including intelligent ones — to believe almost anything no matter how scientifically or otherwise untrue.
With minimal effort, anyone connected online can learn enough about what’s going on from reliable, independent sources to know we’re being scammed by US/Western and other governments, Pharma and their MSM press agents.
Getting mad as hell, rising up and refusing to take it any more is the only way to beat the diabolical scheme.
Nothing else can work.
December 15, 2021
Posted by aletho |
Civil Liberties, Solidarity and Activism, Timeless or most popular | Covid-19, Human rights |
Leave a comment
It’s the 13th December 2021. In my video dated 11th December I detailed some of the health problems which face the gullible folk who have succumbed to the lies and misinformation shared so widely and enthusiastically by governments, the medical establishment and the mainstream media.
In that video, entitled ‘Here’s why most of the jabbed will die early’ I mentioned my fear that the jabbed might suffer brain damage as a result of the covid-19 jab.
That fear was real, as I will show in this video.
https://www.bitchute.com/video/LdgWQ1tIO8qV/
It has been established that there is much that no one yet knows about the covid-19 jabs and the eagerness of the Medicines and healthcare products regulatory agency in the UK to licence a product about which information appeared to be lacking has never been adequately explained. We do know however that, as I was the first to reveal, the MHRA received a huge sum of money from the Bill and Melinda Gates Foundation – which has financial links with jab producers such as Pfizer.
As far as the effect on the brain is concerned the big question is, can the lipid nanoparticles carry the mRNA jab across the blood brain barrier?
The blood brain barrier is a semi permeable barrier of cells which prevent some substances in the blood from crossing into the protective fluid around the central nervous system.
It is vital to know if this happens because if it does then all bets are off as to what might happen to the brain.
And after all, liquid nanoparticles are already used to deliver other drugs across the blood brain barrier.
If the LNPs carry the mRNA jab into the brain then the neurons, the brain cells, might be marked as foreign by the body’s immune system. And as more booster jabs are given the problem will get worse.
The worry is that brain cells might be targeted and killed by cytotoxic T cells.
It has now been established that mRNA has been found in all human tissues except the kidney. It has been found in heart, lung, liver, testicles – and brain. A Japanese study, for example, showed that the vaccine does end up in the brain.
Also worrying is the fact that researchers have called for studies to investigate any relationship between jabs and acute CNS demyelination.
How much damage will this do?
How long will it take before brain damage can be identified?
I don’t have the foggiest idea.
And nor does anyone else.
In a normal experiment with a new drug, doctors would be looking and checking all the possible problems before releasing the drug for widespread use.
But the covid-19 jabs are being rolled out to billions without any one having the faintest idea what will happen.
If you have been jabbed, the first certainty seems to be that the mRNA vaccine will enter your brain.
The second certainty is that the more covid jabs you have, the more dangerous this will be.
How many of your brain cells will die is something only time will tell. And children, of course, will be more vulnerable because they are more vulnerable anyway and because they are likely to live longer.
Some experts, advisors and regulators will tell you that the risks are small. But how can they know that? And what is small? They told us that the blood clotting problems were small.
In my view, having one of these jabs is the equivalent of taking a huge dose of LSD and waiting to see what happens. And hoping that you’re not going to end up like Peter Green for example.
And, remember, the covid-19 jabs don’t stop you getting covid-19 and they don’t stop you passing it on. According to the NHS’s own guidelines in the UK you can still get or spread covid-19 even if you have had three jabs.
The choice about whether or not to be jabbed should be yours.
But governments want to make these jabs compulsory.
You can find links to more information on my websites www.vernoncoleman.com and www.vernoncoleman.org
If this jab were being given for a lethal disease with a 50% mortality rate then the risks might be worth taking. It’s not and they’re not.
Thank you for watching an old man in a chair. And thanks to Brand New Tube and to Muhammad Butt. Please subscribe to my channel on Brand New Tube and spread my videos about on other platforms such as Rumble, Brighteon, Odysee and Bitchute. My thanks to everyone who does this. Put this video on Twitter and Facebook too. If you get your wrist slapped regard it as a war injury. Please do translations too. All the papers and so on that I refer to can easily be found on the internet. If I give you all the links I’ll never do anything else. We do put up transcripts of the videos on both websites and when possible we add important links.
For the record, this channel has not been monetised – none of my videos ever has been. There are no ads, no sponsors and no requests for funds on videos or websites.
Don’t forget to watch my friend Dr Colin Barron’s amazing videos which are always fantastic and often incredibly funny. And visit his website www.colinbarron.co.uk
Read www.theLightpaper.co.uk for all the news considered too truthful to print by the mainstream media. An amazing 200,000 copies are distributed. That’s a bigger circulation than The Guardian. Make sure you get hold of a copy of `We are the 99%’ recorded by Darren and the Daz Band which is the anthem for the Resistance Movement. It’s vital it’s the Christmas Number One. There is a link to it on both my websites. And visit and astandinthepark.org which will give advice on how and where to stand in a park.
Please visit my own websites www.vernoncoleman.org and www.vernoncoleman.com. www.vernoncoleman.com is more old fashioned but contains hundreds of articles on animal issues, politics and much else in addition to health. You can find free books on both sites and brand new stuff is added every weekday. There are hundreds of original articles to read and, of course, the feature detailing vaccine damage is updated every week. New articles are added most days.
Vernon Coleman’s Wednesday Review will, God willing, appear here every Wednesday at 7pm. If it doesn’t then either something has happened to me or the video has been suppressed as has so much of my work these days.
We all need to pray for the truth to be shared by the many, not just the few. Whatever your religion you need to pray because the people running this fraud respect only lies but, in the way that vampires fear sunlight, they fear the truth – it is your government’s greatest enemy and our only weapon. Finally, although it may feel like it at times, please remember that you are not alone. More and more people are waking up and once they are awake they don’t go back to sleep. – which means our numbers are growing daily.
If we are going to win this war then we have to fight hard and with determination and passion and the truth. Remember, this is primarily a propaganda and media war.
Distrust the government, avoid mass media and fight the lies.
Thank you for watching an old man in a chair.
The EMA covid-19 data leak, and what it tells us about mRNA instability
Summary of the public assessment report for covid-19 vaccine Pfizer/BioNTech
Assessment Report – Covid-19 Vaccine Moderna
Concerns of lipid nanoparticle carrying mRNA vaccine into the brain: what to make of it?
RNA vaccines and their lipids
Vernon Coleman’s no 1 bestselling book Endgame explains the awful truth behind the covid fraud and the global warming fraud – and explains where we are heading. Endgame is available from Amazon as a paperback and an eBook.
More at vernoncoleman.org
December 15, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular, Video | COVID-19 Vaccine |
Leave a comment
TO:
- Professor Lim, Chairman, JCVI COVID-19 subcommittee
- Dr June Raine, Chief Executive, MHRARt
- Hon Sajid Javid, Secretary of State for Health and Social Care
- Professor Chris Whitty, Chief Medical Officer for England
- Sir Patrick Vallance, Government Chief Scientific Adviser
- Dr Jenny Harries, Chief Executive, UKHSA
Dear Professor Lim, Dr Raine, Mr Javid, Professor Whitty, Sir Patrick Vallance & Dr Harries,
URGENT RE:
- (I) latest government guidance re myocarditis
- (II) decision to offer a second dose of Pfizer to 12-15s
- (III) reckless disregard for the benefits of natural immunity in children
As a group of senior scientists and clinicians, we wrote to you only two weeks ago regarding your decision to offer a second dose of the Pfizer COVID-19 vaccine to 16-17-year-olds despite lack of detailed safety data. We still await a reply, but are compelled to write again after this week’s UKHSA publication of guidance on myocarditis, coinciding with your latest unexpected advice to widen the age range for the second dose to include 12-15 year-olds. We also still awaiting a reply as to why the JCVI continue to recommend vaccination for those children who already have naturally-acquired immunity and for whom there is no possibility of any benefit from the COVID-19 vaccines.
I. Myocarditis guidelines
The following statements (in italics) from the UKHSA document require urgent clarification regarding our points (in red).
- “myocarditis and pericarditis following vaccination is usually mild or stable and most patients typically recover fully without medical treatment”
This unsubstantiated assertion is not compatible with the statement made in the bullet point below. Unless these children had cardiac MRI scans and follow-up, it is impossible to state that they ‘typically recover fully’
- “myocarditis – significant left ventricular (LV) fibrosis has been described in a high percentage of children admitted to hospital, with a small percentage of these having non-sustained ventricular tachycardia (VT)”
According to the authors, these children were not clinically distinguishable from children in other case series, also with an apparently ‘mild’ clinical course. The concerning findings on MRI were only discovered because the authors thoroughly investigated all children with serious VAEs.
- “no follow-up data is available yet on hospitalised patients”
This point undermines the claim made in the first bullet point.
- “the long-term consequences of this condition secondary to vaccination are yet unknown, so any screening recommendations need to be balanced against the frequency and severity of the disease with the aim to prevent complications, in particular of myocarditis (arrhythmias, long term myocardial damage or heart failure)”
As Pfizer have admitted, the children’s trials are too small to look for myocarditis, but long term studies are in progress due to report in 2025 Recommendations in paediatric patients: Why was there no consultation with the RCPCH?
- “Where appropriate, the patient should be seen face to face and this assessment should include their vital signs.”
When would it be ‘inappropriate’ to see face to face and check vital signs, in a child with any of the concerning symptoms listed?
- “If patients have mild symptoms, they do not require referral to secondary care at this point.”
How would you expect a GP to determine whether myocarditis was ‘mild’ in the absence of an ECG and a Troponin level? How does such an approach match up with rigorous post-marketing surveillance of a vaccine still under emergency use authorisation?
(II) Decision to offer a second dose of Pfizer to 12-15s
There has been no new follow-up data disclosed since the JCVI decision to offer only one dose to 12-15s regarding the outcome for children with vaccine-induced myocarditis. The suggestion that the MHRA has seen no new adverse event reports of myocarditis, is perhaps not surprising given that the UK has not proceeded to a second dose known to be associated with a greatly increased risk. How does the JCVI look at the concerns outlined in the government’s own myocarditis guidance and reconcile them with their duty of care to First do no Harm?
A systematic study from Hong Kong linking all vaccinations to health records has revealed myocarditis occurring 1 in 2,680 in young males after their second dose of Pfizer, and they have now dropped the second dose from their schedule. The latest FDA data similarly report 1 in 5000 for males age 16-17. How is it ethical to recommend a second dose to this cohort knowing the risks to the individual will far outweigh any benefits?
How will effective pharmacovigilance and real-time data be obtained on every child admitted with a diagnosis of myocarditis by vaccine status? How many child fatalities have you factored in as acceptable collateral damage resulting from your decision to recommend the second dose of this vaccine for a condition which poses no significant threat to this age group? The answer surely must be zero.
III. Naturally acquired immunity in children
Perhaps most pressing of all, why does the JCVI continue to disregard the obvious benefits of naturally acquired immunity? This has now been conclusively shown in adults to be much longer lasting and robust than that following vaccination . It is already known that children have good crossover immunity from previous coronaviruses, with excellent T-cell function. And it is widely recognised that their strong innate immune systems are the reason for Covid-19 being extremely mild in children. It is estimated that in England, 5.47 million 5-14-year-olds have already had SARS-CoV-2 infection (which represents 79% of the population of this age group). An international meta-analysis of re-infections post natural infection reported only 577 cases of reinfection from 22 countries over a 15-month period, including only 10 deaths, with not a single death in younger adults let alone in children. Numerous other publications have affirmed that naturally acquired immunity is robust, comprehensive and long-lasting.
Therefore, for the 80% of children who are already immune, there can be no benefit from vaccination and only the potential for serious or even life-threatening harm. For the 20% not yet infected, there are still unanswered questions about the potential for vaccination to interfere with the ability to mount a broad robust and long-lasting immunity and we risk committing these children to the theatre of ever more frequent boosters, each with its own risk of injury, which now seems to be the future for adults. Indeed, this becomes even more important with the new omicron variant. There is no point in vaccinating children with a vaccine which will cause immune imprinting to the Wuhan variant and will impede their ability to make antibodies to the new variants as they present.
We contend that any practitioner who chooses to vaccinate a child in the knowledge that they have recovered from SARS-CoV-2 infection, is in breach of their professional duty of care to put their patient’s best interest first. In addition. failure of the practitioner to disclose the full contents of the UKHSA Myocarditis guidance to the patient and parent would constitute a failure to obtain fully informed consent. See GMC Good Medical Practice Guidelines.
Yours sincerely,
- Dr Rosamond Jones, MD, FRCPCH, retired consultant paediatrician
- Professor Anthony J Brookes, Department of Genetics & Genome Biology, University of Leicester Professor David Livermore, BSc, PhD, Professor of Medical Microbiology, University of East Anglia
- Professor Angus Dalgleish, MD, FRCP, FRACP, FRCPath, FMed Sci, Professor of Oncology, St Georges Hospital, London
- Dr Theresa Lawrie, MBBCh, PhD, Director, Evidence-Based Medicine Consultancy Ltd, Bath
- Dr Clare Craig, BMBCh, FRCPath, Pathologist
- John Collis, RN, Retired specialist nurse practitioner
- Professor Keith Willison, PhD, Professor of Chemical Biology, Imperial, London
- Professor Richard Ennos, MA, PhD. Honorary Professorial Fellow, University of Edinburgh Professor John Fairclough FRCS FFSEM retired Honorary Consultant Surgeon
- Lord Moonie, MBChB, MRCPsych, MFCM, MSc, House of Lords, former parliamentary under- secretary of state 2001-2003, former consultant in Public Health Medicine
- Dr Roland Salmon, MBBS, MRCGP, FFPH, former Director, Communicable Disease Surveillance Centre, Wales
- Dr John Flack, BPharm, PhD. Retired Director of Safety Evaluation, Beecham Pharmaceuticals 1980-1989 and Senior Vice-president for Drug Discovery 1990-92 SmithKline Beecham
- Dr Alan Mordue, MBChB, FFPH. Retired Consultant in Public Health Medicine & Epidemiology
- Dr Geoffrey Maidment, MD, FRCP, retired consultant physician
- Dr Helen Westwood MBChB MRCGP DCH DRCOG, General Practitioner
- Mr James Royle, MBChB, FRCS, MMedEd, Colorectal surgeon Dr Elizabeth Evans MA(Cantab), MBBS, DRCOG, Retired Doctor Dr Emma Brierly, MRCGP, General Practitioner
- Katherine MacGilchrist, BSc (Hons), MSc, CEO/Systematic Review Director, Epidemica Ltd.
- Dr Alan Black, MBBS, MSc, DipPharmMed, retired pharmaceutical physician
- Mr Anthony Hinton, MBChB, FRCS, Consultant ENT surgeon, London
- Dr Greta Mushet, MBChB, MRCPsych, retired Consultant Psychiatrist in Psychotherapy
- Dr Kulvinder Singh Manik MBChB, MRCGP, MA(Cantab), LLM, Gray’s Inn
- Dr Rohaan Seth, Bsc (hons), MBChB (hons), MRCGP, Retired General Practitioner
- Mr Ian F Comaish, MA, BM BCh, FRCOphth, FRANZCO, Consultant ophthalmologist
- Dr Sarah Myhill, MBBS, Dip NM, Retired GP, Independent Naturopathic Physician
- Dr Christopher Exley, PhD, FRSB, Retired professor in Bioinorganic Chemistry
- Dr David Critchley, BSc, PhD, 32 years in pharmaceutical R&D as a clinical research scientist. Dr Gerry Quinn, PhD. Postdoctoral researcher in microbiology and immunology
- Dr Jonathan Engler, MBChB, LlB (hons), DipPharmMed
- Dr Mark Bell, MBChB, MRCP(UK), FRCEM, Consultant in Emergency Medicine
- Dr Zac Cox, BDS, LCPH, Holistic Dentist, Homeopath
- Dr Elizabeth Burton, MBChB, retired general practitioner
- Margaret Moss, MA (Cantab), CBiol, MRSB, Director, The Nutrition and Allergy Clinic, Cheshire
- Julia Annakin, RN,
- Dr Noel Thomas, MA, MBChB, DCH, DObsRCOG, DTM&H, MFHom, retired doctor
- Immunisation Nurse Specialist
- Dr Fiona Martindale, MbChB, MRCGP, GP in out of hours
- Dr Branko Latinkic, BSc, PhD, Molecular biologist
- Dr Jason Lester, MRCP, FRCR, Consultant Clinical Oncologist.
- Dr Sam White, MBChB MRCGP, General Practitioner, Functional medicine practitioner
- Dr Holly Young, BSc, MBChB, MRCP, Consultant Palliative Care Medicine
- Dr David Bramble, MB ChB, MRCPsych, MD, Retired Consultant Child & Adolescent Learning Disability
- Dr. Scott Mitchell, MBChB, MRCS, Associate Specialist, Emergency Medicine
- Dr Peter Chan, BM, MRCS, MRCGP, General Practitioner, Functional medicine practitioner
- Dr Stefanie Williams, Dermatologist
- Dr Andrew Isaac, MB BCh, Physician, retired
- Dr Christina Peers, MBBS, DRCOG, DFSRH, FFSRH, Menopause specialist
- Dr Michael D Bell, MBChB, MRCGP, retired General Practitioner
- Dr Livia Tossici-Bolt, PhD, NHS Clinical Scientist
- Dr Carmen Wheatley, D Phil, Orthomolecular Oncology
- Dr Ruth Wilde, MB BCh, MRCEM, AFMCP, Integrative & Functional Medicine Doctor
- Dr David Morris, MBChB, MRCP(UK), General Practitioner
- Dr Jayne LM Donegan, MBBS, DRCOG, DCH, DFFP, MRCGP, HMA, Integrative Medicine practitioner
- Dr Franziska Meuschel, MD, ND, PhD, LFHom, BSEM, Nutritional, Environmental and Integrated Medicine
- Dr Andrew Isaac, MB BCh, Physician, retired
December 14, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | COVID-19 Vaccine |
Leave a comment
Governments around the world have encouraged and enforced a new form of segregation based on vaccine status. This is not only dangerously inhumane; there is no scientific basis for this.
There seems to be an underlying presumption here that the unvaccinated are unclean (regardless of natural immunity) and their presence will spread disease. What if, however, existing studies reveal that there is little to no difference between the COVID vaccinated and unvaccinated in terms of becoming infected, harboring the virus (viral load in the oral and nasopharynx), and transmitting it?
As it relates to Omicron, two recent small but interesting preliminary studies show that 80% of the omicron cases were double vaccinated. Wilhelm et al. reported on reduced neutralization of SARS-CoV-2 omicron variant by vaccine sera and monoclonal antibodies. “in vitro findings using authentic SARS-CoV-2 variants indicate that in contrast to the currently circulating Delta variant, the neutralization efficacy of vaccine-elicited sera against Omicron was severely reduced highlighting T-cell mediated immunity as essential barrier to prevent severe COVID-19.” Further, the CDC has reported on the details for 43 cases of COVID-19 attributed to the Omicron variant. They found that “34 (79%) occurred in persons who completed the primary series of an FDA-authorized or approved COVID-19 vaccine ≥14 days before symptom onset or receipt of a positive SARS-CoV-2 test result.”
As it relates to the vaccinated and unvaccinated being similar in terms of infection, viral load, and transmission capacity, and thus no underlying evidence to separate them societally, we specifically focus on and present (and based largely on Delta variant data) the body of evidence.
1) Salvatore et al. examined the transmission potential of vaccinated and unvaccinated persons infected with the SARS-CoV-2 Delta variant in a federal prison, July-August 2021. They found a total of 978 specimens were provided by 95 participants, “of whom 78 (82%) were fully vaccinated and 17 (18%) were not fully vaccinated…clinicians and public health practitioners should consider vaccinated persons who become infected with SARS-CoV-2 to be no less infectious than unvaccinated persons.”
2) Singanayagam et al. examined the transmission and viral load kinetics in vaccinated and unvaccinated individuals with mild delta variant infection in the community. They found that (in 602 community contacts (identified via the UK contract-tracing system) of 471 UK COVID-19 index cases were recruited to the Assessment of Transmission and Contagiousness of COVID-19 in Contacts cohort study and contributed 8145 upper respiratory tract samples from daily sampling for up to 20 days) “vaccination reduces the risk of delta variant infection and accelerates viral clearance. Nonetheless, fully vaccinated individuals with breakthrough infections have peak viral load similar to unvaccinated cases and can efficiently transmit infection in household settings, including to fully vaccinated contacts.”
3) Chia et al. reported that PCR cycle threshold (Ct) values were “similar between both vaccinated and unvaccinated groups at diagnosis, but viral loads decreased faster in vaccinated individuals. Early, robust boosting of anti-spike protein antibodies was observed in vaccinated patients, however, these titers were significantly lower against B.1.617.2 as compared with the wildtype vaccine strain.”
4) Israel, 2021 looked at Large-scale study of antibody titer decay following BNT162b2 mRNA vaccine or SARS-CoV-2 infection, and reported as “To determine the kinetics of SARS-CoV-2 IgG antibodies following administration of two doses of BNT162b2 vaccine, or SARS-CoV-2 infection in unvaccinated individuals…In vaccinated subjects, antibody titers decreased by up to 40% each subsequent month while in convalescents they decreased by less than 5% per month. Six months after BNT162b2 vaccination 16.1% subjects had antibody levels below the sero-positivity threshold of <50 AU/mL, while only 10.8% of convalescent patients were below <50 AU/mL threshold after 9 months from SARS-CoV-2 infection.”
5) In the UK COVID-19 vaccine Surveillance Report for week #42, it was noted that there is “waning of the N antibody response over time” and “that N antibody levels appear to be lower in individuals who acquire infection following 2 doses of vaccination.” The same report (Table 2, page 13), shows that in the older age groups above 30, the double vaccinated persons have greater infection risk than the unvaccinated, presumably because the latter group include more people with stronger natural immunity from prior Covid disease. See also UK PHE reports 43, 44, 45, 46 for similar data.
6) In Barnstable, Massachusetts, Brown et al. found that among 469 cases of COVID-19, 74% were fully vaccinated, and that “the vaccinated had on average more virus in their nose than the unvaccinated who were infected.”
7) Riemersma et al. found “no difference in viral loads when comparing unvaccinated individuals to those who have vaccine “breakthrough” infections. Furthermore, individuals with vaccine breakthrough infections frequently test positive with viral loads consistent with the ability to shed infectious viruses.” Results indicate that “if vaccinated individuals become infected with the delta variant, they may be sources of SARS-CoV-2 transmission to others.” They reported “low Ct values (<25) in 212 of 310 fully vaccinated (68%) and 246 of 389 (63%) unvaccinated individuals. Testing a subset of these low-Ct samples revealed infectious SARS-CoV-2 in 15 of 17 specimens (88%) from unvaccinated individuals and 37 of 39 (95%) from vaccinated people.”
8) Ignoring the risk of infection, given that someone was infected, Acharya et al. found “no significant difference in cycle threshold values between vaccinated and unvaccinated, asymptomatic and symptomatic groups infected with SARS-CoV-2 Delta.”
9) Gazit et al. out of Israel showed that “SARS-CoV-2-naïve vaccinees had a 13-fold (95% CI, 8-21) increased risk for breakthrough infection with the Delta variant compared to those previously infected.”
Dr Alexander holds a PhD. He has experience in epidemiology and in the teaching clinical epidemiology, evidence-based medicine, and research methodology. Dr Alexander is a former Assistant Professor at McMaster University in evidence-based medicine and research methods; former COVID Pandemic evidence-synthesis consultant advisor to WHO-PAHO Washington, DC (2020) and former senior advisor to COVID Pandemic policy in Health and Human Services (HHS) Washington, DC (A Secretary), US government; worked/appointed in 2008 at WHO as a regional specialist/epidemiologist in Europe’s Regional office Denmark, worked for the government of Canada as an epidemiologist for 12 years, appointed as the Canadian in-field epidemiologist (2002-2004) as part of an international CIDA funded, Health Canada executed project on TB/HIV co-infection and MDR-TB control (involving India, Pakistan, Nepal, Sri Lanka, Bangladesh, Bhutan, Maldives, Afghanistan, posted to Kathmandu); employed from 2017 to 2019 at Infectious Diseases Society of America (IDSA) Virginia USA as the evidence synthesis meta-analysis systematic review guideline development trainer; currently a COVID-19 consultant researcher in the US-C19 research group
December 14, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science, Timeless or most popular | Covid-19, COVID-19 Vaccine, Human rights |
Leave a comment
Yesterday, in a statement to Parliament on the UK’s planned “vaccine passport”, Health Secretary Sajid Javid admitted the NHS Pass would require three shots for you to be considered “fully vaccinated”.
“Once all adults have had a reasonable chance to get their booster jab, we intend to change this exemption to require a booster dose,”
While many of us predicted this would be the case, it is the first time any British politician has actually said it out loud, and in front of parliament too.
This incredibly cynical “evolving definition” of “fully vaccinated” is not a new phenomenon, and is not isolated to the UK either.
Israel changed their definition of “fully vaccinated” to include the booster months ago. New Zealand’s ministry of health is “considering” doing the same, as is Australia.
The EU isn’t far behind either, with proposals in place to make travel dependent on having a third dose.
The US hasn’t formally adopted a new definition yet, but you’d have to be blind not to see the signs. Just yesterday the LA Times headlined:
Should the definition of ‘fully vaccinated’ be changed to include a booster shot?
An article on Kaiser Health News asks the same thing.
Tony Fauci is quoted in the Independent as saying it’s only a matter of time before the definition is updated:
“It’s going to be a matter of when, not if” getting a booster shot will be considered being “fully vaccinated,” Dr Fauci said.
Opinion pieces are already appearing asking “is it safe to hangout with the boosted”? (This headline was so unpopular, the Atlantic changed it only a couple of hours after it was published).
All in all it seems pretty clear that, by the time 2022 rolls around, most of the Western world will require three shots in order to qualify as “fully vaccinated”.
It’s also clear that this won’t stop at three. Already, just last week, Pfizer were claiming they may need to “move up the timeline” for a fourth vaccine dose.
This change is being blamed on Omicron, with articles warning the “new variant” can “hit” the vaccinated. Fortune reports:
Omicron is making scientists redefine what it means to be ‘fully vaccinated’ against COVID
So, the third (and maybe fourth) doses are (allegedly) for Omicron…but that model can extend to perpetuity. In order to go to five, six or seven they’ll only need to “discover” more “new variants”.
It will just keep going and going.
But there is good news in all this, every time the powers-that-shouldn’t-be change the rules in the middle of the game, it’s a chance to knock people out of their media-induced hypnosis.
There are promising signs that millions of already-vaccinated will reject the booster. We can build on that.
So tell your single and double jabbed friends, try to open their eyes to the path they are starting down.
They may consider themselves “fully vaccinated”, but the government doesn’t, and never will.
December 14, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science, Timeless or most popular | COVID-19 Vaccine, Human rights |
Leave a comment
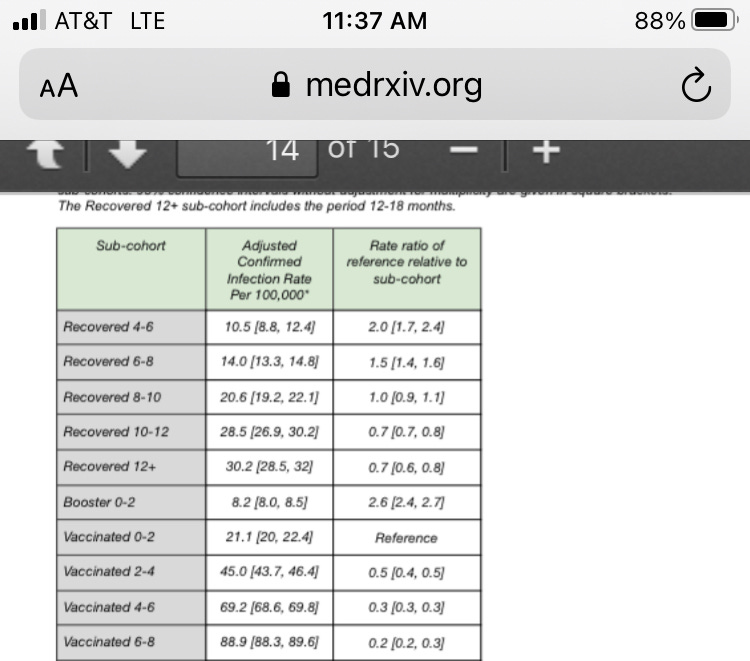
mRNA vaccine protection from Covid is far weaker than natural immunity and declines very fast, according to a new study of almost 6 million people in Israel.
During the summer Covid wave, more than 140,000 Israelis who had been vaccinated but not received a booster shot became infected with Covid. Put another way, in just two months, about 1 out of every 20 vaccinated Israelis became infected with Sars-Cov-2.
Natural immunity – the protection following infection and recovery – lasts much longer, the study shows.
In fact, people who had already had Covid once had better protection from the virus more than a year later than people who had been vaccinated only three months before.
The gap was even larger in cases of severe infection.
Vaccinated people were more than five times as likely to develop severe infections than people with natural immunity. Only 25 out of roughly 300,000 Israelis with natural immunity developed severe Covid infections in the summer wave – compared to almost 1,400 vaccinated Israelis.
The difference did not result from gaps in age between vaccinated and recovered people. People over 60 benefitted even more from natural immunity relative to vaccination than did younger people.

The study also showed that giving people who had natural immunity a vaccine dose did little to lower rates of infection for them, raising the question of why they should ever be vaccinated.
Finally, the study offered a disturbing signal that vaccination may ultimately interfere with the development of lasting immunity in people who are infected after being vaccinated.
A booster shot did lower the risk of infection about to the level of peak protection from natural immunity – but because the study ended in September, it is impossible to know how long that protection may last.
All these findings come out of a database of Covid infections among almost 6 million Israelis in August and September, at the peak of the fourth Covid wave in Israel. The database contains information on essentially every Israeli over age 16 who was fully vaccinated or had previously had a Covid infection.
The paper, “Protection and waning of natural and hybrid COVID-19 immunity,” is currently available as a preprint at:
https://www.medrxiv.org/content/10.1101/2021.12.04.21267114v1.full.pdf
Oddly, the paper’s title does not mention waning of vaccine immunity, although the figures it presents make the severity of the problem clear. Such shyness is common among researchers presenting bad news about Covid vaccines – they will offer the data, but not highlight it.

Israel has exclusively used the Pfizer mRNA vaccine, began mass vaccinations before almost any other country, and has an excellent health care database. As a result, it has among the best information on the effectiveness of the shots. It offers far more complete data than the United States.
The vaccine failure over the summer in Israel – following apparent success in the spring – has presaged a similar pattern across the United States and Europe, and a similar desperate campaign for boosters.
In this paper, the researchers examined infection rates among five different groups of Israelis – those with natural immunity, those who had received boosters, those who were vaccinated but had not received boosters, those with natural immunity who had also received a vaccine, and those who had become infected after being vaccinated.
The researchers specifically excluded unvaccinated Israelis without natural immunity from the comparison because Israel has very few of them and they are “unrepresentative of the overall population.”
In other words, the researchers explicitly denied the validity of the comparison that vaccine advocates make when they compare Covid rates among vaccinated and unvaccinated people in places with high vaccination rates (a point I have been trying to make for months).
The researchers found that the highest rates of infection by far came in people who had been vaccinated at least six months before. They had a nearly 3 percent chance of being infected per month (the researchers present the figure as 89 per 100,000 “person-days.”)
Those people were four times as likely to be infected as newly vaccinated people. They were also seven times as likely to be infected as people who had natural immunity from an infection six to eight months before, and three times as likely as those who had natural immunity from an infection more than year before.
A single vaccination dose in people with natural immunity temporarily produced strong protection, the researchers found. But after six months, the advantage had faded to within the margin of statistical error. In other words, so-called hybrid immunity hardly appeared to exist after six months – natural immunity was once again providing the protection.
Nor did vaccination appear to stop severe disease.
Nearly every case of severe disease in the database – almost 1,400 of the roughly 1,600 cases – came in vaccinated but unboosted people. Boosters did appear to reduce severe disease significantly. Again, though, the study covered less than two months after the booster program began, when boosters should be at peak effectiveness.
Finally, the study showed that people who had been vaccinated and then been infected and recovered were actually more likely to be infected again six months later than those who had only “pure” natural immunity.
That finding, though based on a small number of cases, adds to worrying data that mRNA vaccination may actually wrong-foot our immune systems in the long run and make it harder to build lifelong protection against Covid.
December 14, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | Covid-19, COVID-19 Vaccine |
Leave a comment
Russiagate is the biggest scandal in American history.
Nothing comes close in size, scope or harm to the republic than the years-long effort to cripple Donald Trump’s presidency by claiming he conspired with an enemy state to steal the 2016 election and then do its bidding as commander-in-chief.
Its notorious predecessors – L’Affaire Lewinsky, Iran-Contra, Watergate, Teapot Dome, Crédit Mobilier, the XYZ Affair – involved relatively small numbers of malefactors engaged in specific acts of illegality and corruption (we still don’t know who, if anyone, planned the Jan. 6 assault on the U.S. Capitol)
Russiagate, by contrast, is a vast conspiracy involving innumerable powerful forces, including the Democratic Party, NeverTrump Republicans, the Obama administration, the FBI, Department of Justice and the nation’s most prestigious news outlets.
Where previous scandals often ended with public accountability for the perpetrators – Watergate saw the imprisonment of top White House aides and President Nixon’s resignation – and public reforms, Russiagate has produced no such reckoning.
Russiagate began with a kernel of truth: Someone – probably Russians, though we still don’t know for sure – hacked the Democratic National Committee and Hillary Clinton’s private server. Fearful of what might be released, the Clinton campaign tried to discredit any damaging material by raising dark questions about its source. (Joe Biden executed this same strategy to great effect when he falsely described the evidence of corruption found on his son Hunter’s laptop as “Russian disinformation.”)
In response, the Clinton campaign financed an absurd collection of conspiracy theories involving peeing prostitutes and billion-dollar bribes, the so-called Steele dossier. Its importance cannot be overstated – it was the dossier that linked the Trump campaign to the hacking. No dossier, no collusion theory.
During the summer and fall of 2016, Hillary’s henchmen fed this preposterous concoction to Obama administration officials in the DOJ, FBI, CIA and State Department. Everyone knew it was a political operation: Declassified notes showed that then-CIA Director John Brennan briefed President Obama in July 2016 that Clinton planned to tie Trump to Russia as “a means of distracting the public from her use of a private email server.”
Clinton staffers – including Jake Sullivan, who now serves as Biden’s national security adviser – tried to interest the mainstream press in its scurrilous accusations, but got little traction because they could not be verified. Instead of laughing it all off as transparent campaign mud-slinging, however, the FBI joined the conspiracy. The bureau took the extreme step of opening a counter-intelligence probe into an ongoing presidential campaign – and its agents perjured themselves to obtain wire-tapping warrants.
Days after the November election, Hillary’s campaign focused on “Russian interference” as a chief reason for her defeat. On Jan. 5, 2017, President Obama, Vice President Biden and other key leaders met with FBI Director James Comey in the Oval Office to discuss Russia-related matters. We do not know what was discussed in that meeting, but the next day, Comey briefed President-elect Trump on some allegations in the Steele dossier. Four days later, on Jan. 10, CNN used that briefing as a news hook to report the collusion conspiracy theories as high-drama news.
Over the next few months and years, current and former officials illegally fed misleading classified material and partisan anonymous quotes to the New York Times, Washington Post, NBC News and other sympathetic press outlets to advance the narrative. Brennan and former National Director of Intelligence James Clapper became a constant presence on cable news, using the top-secret authority of their previous positions to assure the public that collusion was real – although in sworn testimony, Clapper admitted he had not seen such evidence.
Congressional Democrats, including Nancy Pelosi and Rep. Adam Schiff – who falsely claimed to have seen “more than circumstantial evidence” of Trump/Russia collusion – amplified the smears.
The appointment of Special Counsel Robert Mueller to investigate the fantasy in May 2017 fueled the fire. His effort became part of the scheme: He only looked for evidence that might implicate Trump, ignoring questions about who cooked up the conspiracy theory, how they disseminated it throughout the government and media, and the laws they might have broken in the process.
Despite his best effort, Mueller said he’d found no evidence of collusion when he released his report in April 2019. That should have killed the conspiracy theory and – following the script of previous major scandals – sparked a period of reflection by the government, the media and the American people that asked: How did we get this so wrong?
Such a broad reckoning has not yet happened. DoJ Inspector General Michael Horowitz’s 2020 report detailing grave abuses in the FBI’s handling of the matter prompted little outcry and no sweeping reform. The recent indictments of Clinton-connected actors filed by Special Counsel John Durham – who is finally doing the work Mueller should have, exposing the malfeasance that actually transpired during the 2016 campaign – have, bizarrely, led partisans to minimize his findings and actually double-down on the debunked collusion narrative. Recent pieces in The Atlantic and New York Times, for example, suggest, without evidence, that “Mueller never definitively got to the bottom of what happened.”
As Aaron Maté recently reported for RealClearInvestigations, many news organizations have refused to correct documented errors in Trump/Russia coverage, including deeply flawed articles thatwere awarded a Pulitzer Prize.
Leading peddlers of the hoax – including Brennan, Clapper, Pelosi, Schiff and Sullivan – have paid no price for their actions. To date, no one has conducted probing interviews with Hillary Clinton or Barack Obama about their roles in the scandal.
Engineered by broad swaths of the government and media, the effort to paint a sitting president as a foreign agent alone makes Russiagate the worst scandal in American history. But it is this second, still ongoing phase – this willful effort to deny what happened, this refusal to hold the perpetrators accountable – that presents the most serious danger to our nation.
If truth and justice don’t matter, what does?
December 14, 2021
Posted by aletho |
Civil Liberties, Deception, Fake News, Mainstream Media, Warmongering, Russophobia, Timeless or most popular | FBI, United States |
Leave a comment

This week’s nationwide annihilation of Biden’s Federal Contractor vaccine mandate at the hands Georgia Federal Judge R. Stan Baker has resulted in a landslide retreat of cowardly mega-corporations from their so-confident bullying of American workers.
Biden’s illegal gamble, the nationwide Federal contractor vaccine mandate, has like his previous Medicare mandate and OSHA if-you-have-100-workers-mandatory-vax mandate been ripped to shreds early on in the courts.
Biden’s mandates have always been a bullying gamble, an admission that they knew they were engaging in illegal acts but that they would continue to use the not-insignificant weapons of the executive branch to blast as much harm as possible until the courts stepped in and noted the obvious: “You can’t do this!”
Cynics – and I sympathize – will say that the courts could have ruled either way so don’t get too excited.
That’s the lesson of the past two years: There is nothing below us as we look down. It takes our breath away. We now understand that our civilization has been built on a pile of sand and any determined entity could tunnel under us as we are distracted by the human necessities of providing for our families and living our finite lives as best as possible.
This horrible reality cannot be unseen.
Previously we viewed our rulers – from dog catcher to president – as malevolent but for the most part at a distance. We never thought they would reach out with their gradually but steadily-acquired iron fist and squeeze the oxygen from our lungs: “Take a shot or starve!”
The Hungarians in early 1918 similarly were shocked that living somewhat silently among them were aliens who would activate themselves at the exact most fertile moment and literally up-end their somnambulant state, imposing “mandates” on their society that included mobile gallows – a crude earlier form of the forced vax.
With the welcome disintegration of this evil government decree – via Judge Baker’s ruling that the contractor mandate is illegal – one by one the mega-corporations also see their position as shifting to the untenable. They are bailing out as fast as possible.
Some 83,000 Florida healthcare workers no longer face being kicked to the street by US government-sponsored terrorism, until this week dutifully enforced by the “free market” prostitutes in bed with the state.
As hero Alex Berenson has reported Thursday, mega corporations in the US are also suddenly looking under themselves and finding that they are alone. No more government guns aimed at the powerless…at least for the time being.
General Electric, 3M, Verizon, and Oracle have in the past day or so hedged their bets and snuck out of bed with the US government: no more vax requirements! We are talking about a large group of people no longer bound by the brotherhood of the needle.
We are winning this for now and should pause to drink it in.
But at the same time we must also look at what has rotted in our civilization that would allow such a force to upend us, to unleash this iron fist once hidden in a velvet glove. Life will never be the same knowing what these people have done to us. They must never be allowed to forget it.
Copyright © 2021 by RonPaul Institute
December 13, 2021
Posted by aletho |
Civil Liberties, Timeless or most popular, War Crimes | COVID-19 Vaccine, Human rights, United States |
Leave a comment
CSE spied on Israel’s enemies and shared the intelligence with that country
This year marks the 75th anniversary of a little known but influential arm of Canada’s foreign policy apparatus. An entity called the Communications Security Establishment was established to spy internationally in 1946, operating secretly during its first four decades.
With an annual budget of $780 million and 3000 employees, the CSE has a variety of high-tech gadgets, including surveillance planes. In 2011 CSE moved into a new $1.2 billion home. The seven-building, 110,000 square metre complex is connected to the Canadian Security Intelligence Service’s (CSIS) headquarters in Ottawa.
Unlike CSIS, CSE is largely foreign focused. It seeks to “protect the computer networks and information of greatest importance to Canada” from international attack. CSE also gathers international signals intelligence (SIGINT), which it defines as “intelligence acquired through the collection of electromagnetic signals.” Historically, CSE largely intercepted electronic communications between embassies in Ottawa and other nations’ capitals. Today, CSE monitors phone calls, radio, microwave and satellite, as well as emails, chat rooms and other Internet exchanges. It engages in various forms of data hacking, sifting through millions of videos and online documents daily. Or, as Vice reporter Patrick McGuire put it, CSE “listens in on phone calls and emails to secretly learn about things the Canadian government wants to secretly learn about.”
After WWII the government established the Communications Branch of the National Research Council, which was renamed Communications Security Establishment three decades later. In Cautious Beginnings: Canadian Foreign Intelligence, 1939-51 Kurt Jensen explains: “the Gouzenko story [a Soviet diplomat who defected in September 1945, alleging widespread Russian spying in Canada] is almost entirely absent from the debate on Canadian postwar foreign intelligence. While the Soviet Union figured prominently in Canadian foreign intelligence interests, it was not an exclusive focus. The available evidence suggests that Canada had broad foreign intelligence interests that reflected current Canadian foreign policy interests.”
Since its creation CSE has been part of the Five Eyes intelligence-sharing framework though Ottawa didn’t admit its Five Eyes relationship until 1995. The main contributors to the Washington-led Five Eyes are the US’s NSA, Australian Signals Directorate, New Zealand’s Government Communications Security Bureau, British Government Communications Headquarters and CSE. A series of post-WWII accords, beginning with the 1946 UKUSA intelligence agreement, created the “AUS/CAN/NZ/UK/US EYES ONLY” arrangement.
CSE established SIGINT posts on the east and west coasts as well as in the north. According to a table produced by blogger Jerry Proc, there have been more than 50 Canadian SIGINT stations opened during the past century.
Canadian diplomatic posts have long housed SIGINT equipment. According to a NSA document released by whistleblower Edward Snowden, CSE operated clandestine surveillance activities in “approximately 20 high-priority countries.” In his 1994 book former CSE agent Mike Frost describes CSE listening posts at a number of embassies or consular posts while two papers in the early 2000s cite Beijing, Abidjan, New Delhi, Bucharest, Rabat, Kingston (Jamaica), Mexico City, Rome, San Jose (Costa Rica), Warsaw and Tokyo as diplomatic posts where CSE (probably) collected information.
Since the start of the 1960s CSE has listened to Cuban leaders’ conversations from an interception post inside the embassy in Havana. (Ottawa maintained diplomatic and economic relations with Cuba after its 1959 revolution, reports Three Nights in Havana, partly because “the United States secretly urged [Prime Minister] Diefenbaker to maintain normal relations because it was thought that Canada would be well positioned to gather intelligence on the island.”) Canada also spied on Cuba from a diplomatic post outside that country. In the early 1980s CSE wanted to establish a communications post in Jamaica, notes Frost, to intercept “communications from Fidel Castro’s Cuba, which would please NSA to no end.”
CSE also gathered intelligence on Palestinians for Israel. Frost notes, “[former Palestinian Liberation Organization chairman] Yasser Arafat’s name, for instance, was on every [CSE] key word list. NSA was happy about that.” According to files released by Snowden, CSE spied on Israel’s enemies and shared the intelligence with that country’s SIGINT National Unit. “Palestinians” was a “specific intelligence topic” of an NSA-GCHQ-CSE project shared with their Israeli counterpart.
In the late 1980s the Soviets jammed US and British listening operations in Moscow. In response, they asked CSE to take up the slack. “From summer 1987 to summer 1989”, notes Frost, “it was Canada that was providing the most powerful Western nations with the intelligence that had been so crucial to them and, in fact, to the whole Western Alliance.”
Economic espionage is a significant and growing component of CSE’s focus. In 1995 the agency began hiring more individuals with economics, commerce and international business qualifications “to build up its own analytical capacity in economic intelligence.” As part of the Snowden revelations, it came to light that CSE spied on Brazil’s Department of Mines and Energy.
In 1985 the government asked CSE to gather intelligence that could help a Canadian firm bidding for a major pipeline contract in India. A few years earlier the CSE overheard the US ambassador in Ottawa detailing his country’s negotiating position on a US$5 billion wheat sale to China, which helped Canada win the contract. CSE is also thought to have secured information useful to negotiating the mid-1990s North American Free Trade Agreement and World Trade Organization.
CSE has contributed intelligence to Canada and its allies’ wars. The agency’s sophisticated equipment and analytical and linguistic resources contributed significantly to the 2001-14 occupation of Afghanistan. The agency’s website says it played a “vital role” in the central Asian country and CSE head John Adams boasted that they were responsible for more than half the “actionable intelligence” Canadian soldiers used in Afghanistan. That included monitoring Taliban forces and leaders as well as allied Afghan government officials. Information CSE provided protected Canadian troops from attack and helped special forces assassinate Afghans.
As the Internet came onto the scene CSE was instructed to conduct Computer Network Exploitation. It went from intercepting communications (“data in motion”) to seeking information on foreign computer systems (“data at rest”). According to CSE expert Bill Robinson, “it became a hunter as well as a gatherer.” CSE could hack into computer systems, implant malware and copy information.
In 2017 CSE was further empowered to carry out offensive operations against foreign actors. The Communications Security Establishment Act authorized CSE “to degrade, disrupt, influence, respond to or interfere with the capabilities, intentions or activities” of international targets. In effect the intelligence agency could seek to take a government offline, shutter a power plant, knock a drone out of the sky or interfere in court proceedings and elections in countries Ottawa doesn’t deem “democratic”. There is no requirement that the target threaten Canadian security.
The legislation forbids offensive cyber activities that could cause injury or death or “obstruct, pervert or defeat the course of justice or democracy.” But, these limitations don’t apply if CSE conducts cyber-attacks on behalf of a Canadian military operation or receives approval of the foreign minister. Additionally, there is no independent oversight of CSE’s new offensive capabilities and CSE is allowed to do “anything that is reasonably necessary to maintain the covert nature of the activity.”
To mark the 75th anniversary of the Communications Security Establishment, it’s time to place this clandestine organization under far greater scrutiny.
On December 15 the Canadian Foreign Policy Institute will be hosting a webinar on “Canada and the Five Eyes”.
December 13, 2021
Posted by aletho |
Ethnic Cleansing, Racism, Zionism, Timeless or most popular, War Crimes, Wars for Israel | Canada, Human rights, Israel, Palestine |
Leave a comment
I checked the Federal Register and there has been no notice that Comirnaty has been added to the National Childhood Vaccine injury Program (NVICP). I confirmed this by checking whether Comirnaty had been added to the childhood schedule, and according to the HRSA, which manages both compensation programs, it has not.
So, if you receive the licensed Comirnaty vaccine, correctly labeled as the brand-name product and not the vaccine being fobbed off as licensed product, and you are injured, you are free to sue the manufacturer for your injury. Could this be why Pfizer wrote, “Pfizer does not plan to produce any product with these new [Comirnaty National Drug Codes] and labels over the next few months while EUA authorized product is still available and being made available for U.S. distribution.”
If, however, you receive the Pfizer-BioNTech vaccine under Emergency Use Authorization, or the Moderna or J and J vaccine, you can’t sue anyone. You have the right to beg HRSA for compensation of lost wages and unpaid medical bills, period. So far, HRSA and the Countermeasures Injury Compensation Program it administers have not paid out one dime for the approximately one million injuries and 20,000 deaths reported to VAERS for any COVID vaccine.
In other words, the federal government (DHHS) has not admitted a single injury was caused by a COVID vaccine. CDC says it has not linked a single death to a COVID vaccine–not even when the patient walked into the vaccination center but got carried out to the morgue. FDA doesn’t know much about myocarditis, Bell’s Palsy, thrombosis, thrombocytopenia, pulmonary emboli, etc. There are no black box warnings on any of the COVID vaccines.
HRSA, FDA, CDC and NIH are all agencies within the federal Department of Health and Human Services. They have all gotten their stories straight. They know nothing and they are just following orders. Heil HHS!
They can’t find a doggone problem in the 20 or so databases they are spending many $millions of your money to “study.”
Want to know the biggest conspiracy in the US right now? It is the HHS.
FDA has access to a bunch of electronic databases it has termed the “BEST” Initiative, and it published a plan to use them to study heart attacks, pulmonary embolism, thrombocytopenia, etc. back in July. Where are the results, FDA? What are you waiting for? (According to CDC, “More than 459 million doses of COVID-19 vaccines were administered in the United States from December 14, 2020, through November 29, 2021.”). It seems clear that we aren’t supposed to be informed of FDA’s findings until everyone possible has been vaccinated, at which point the results will be irrelevant.
In October 2020, FDA’s Steve Anderson told us there were even more databases that would be studied.
On August 23, 2021, FDA announced its databases were inadequate to assess myocarditis, so BioNTech would have to do it for them. Here is what FDA wrote about its inability to use VAERS and its many other databases:
- As noted above, the FDA acknowledges that “We have determined that an analysis of spontaneous postmarketing adverse events reported under section 505(k)(1) of the FDCA [in other words, VAERS–Nass] will not be sufficient to assess known serious risks of myocarditis and pericarditis and identify an unexpected serious risk of subclinical myocarditis.
- Furthermore, the pharmacovigilance system that FDA is required to maintain under section 505(k)(3) of the FDCA [in other words, FDA’s many other databases that cost the taxpayer zillions–Nass] is not sufficient to assess these serious risks.”
NOT SUFFICIENT???
Unsaid, but implied, is that if FDA is incapable of studying thousands of reported cases of myocarditis, it probably cannot study the other serious adverse events that have been reported in conjunction with COVID vaccines.
VAERS has operated for 30 years, collecting reports of vaccine adverse events. It averaged under 100 cases of myocarditis reported yearly until this year. Through November, CDC reports it received 1949 reports of myocarditis and pericarditis, in those under 30. CDC didn’t say what the total number of reports for all ages was.
Somehow, these HHS don’t seem all that concerned that the admitted reporting rate of myocarditis is over 20 times the average during the past 30 years. Why?
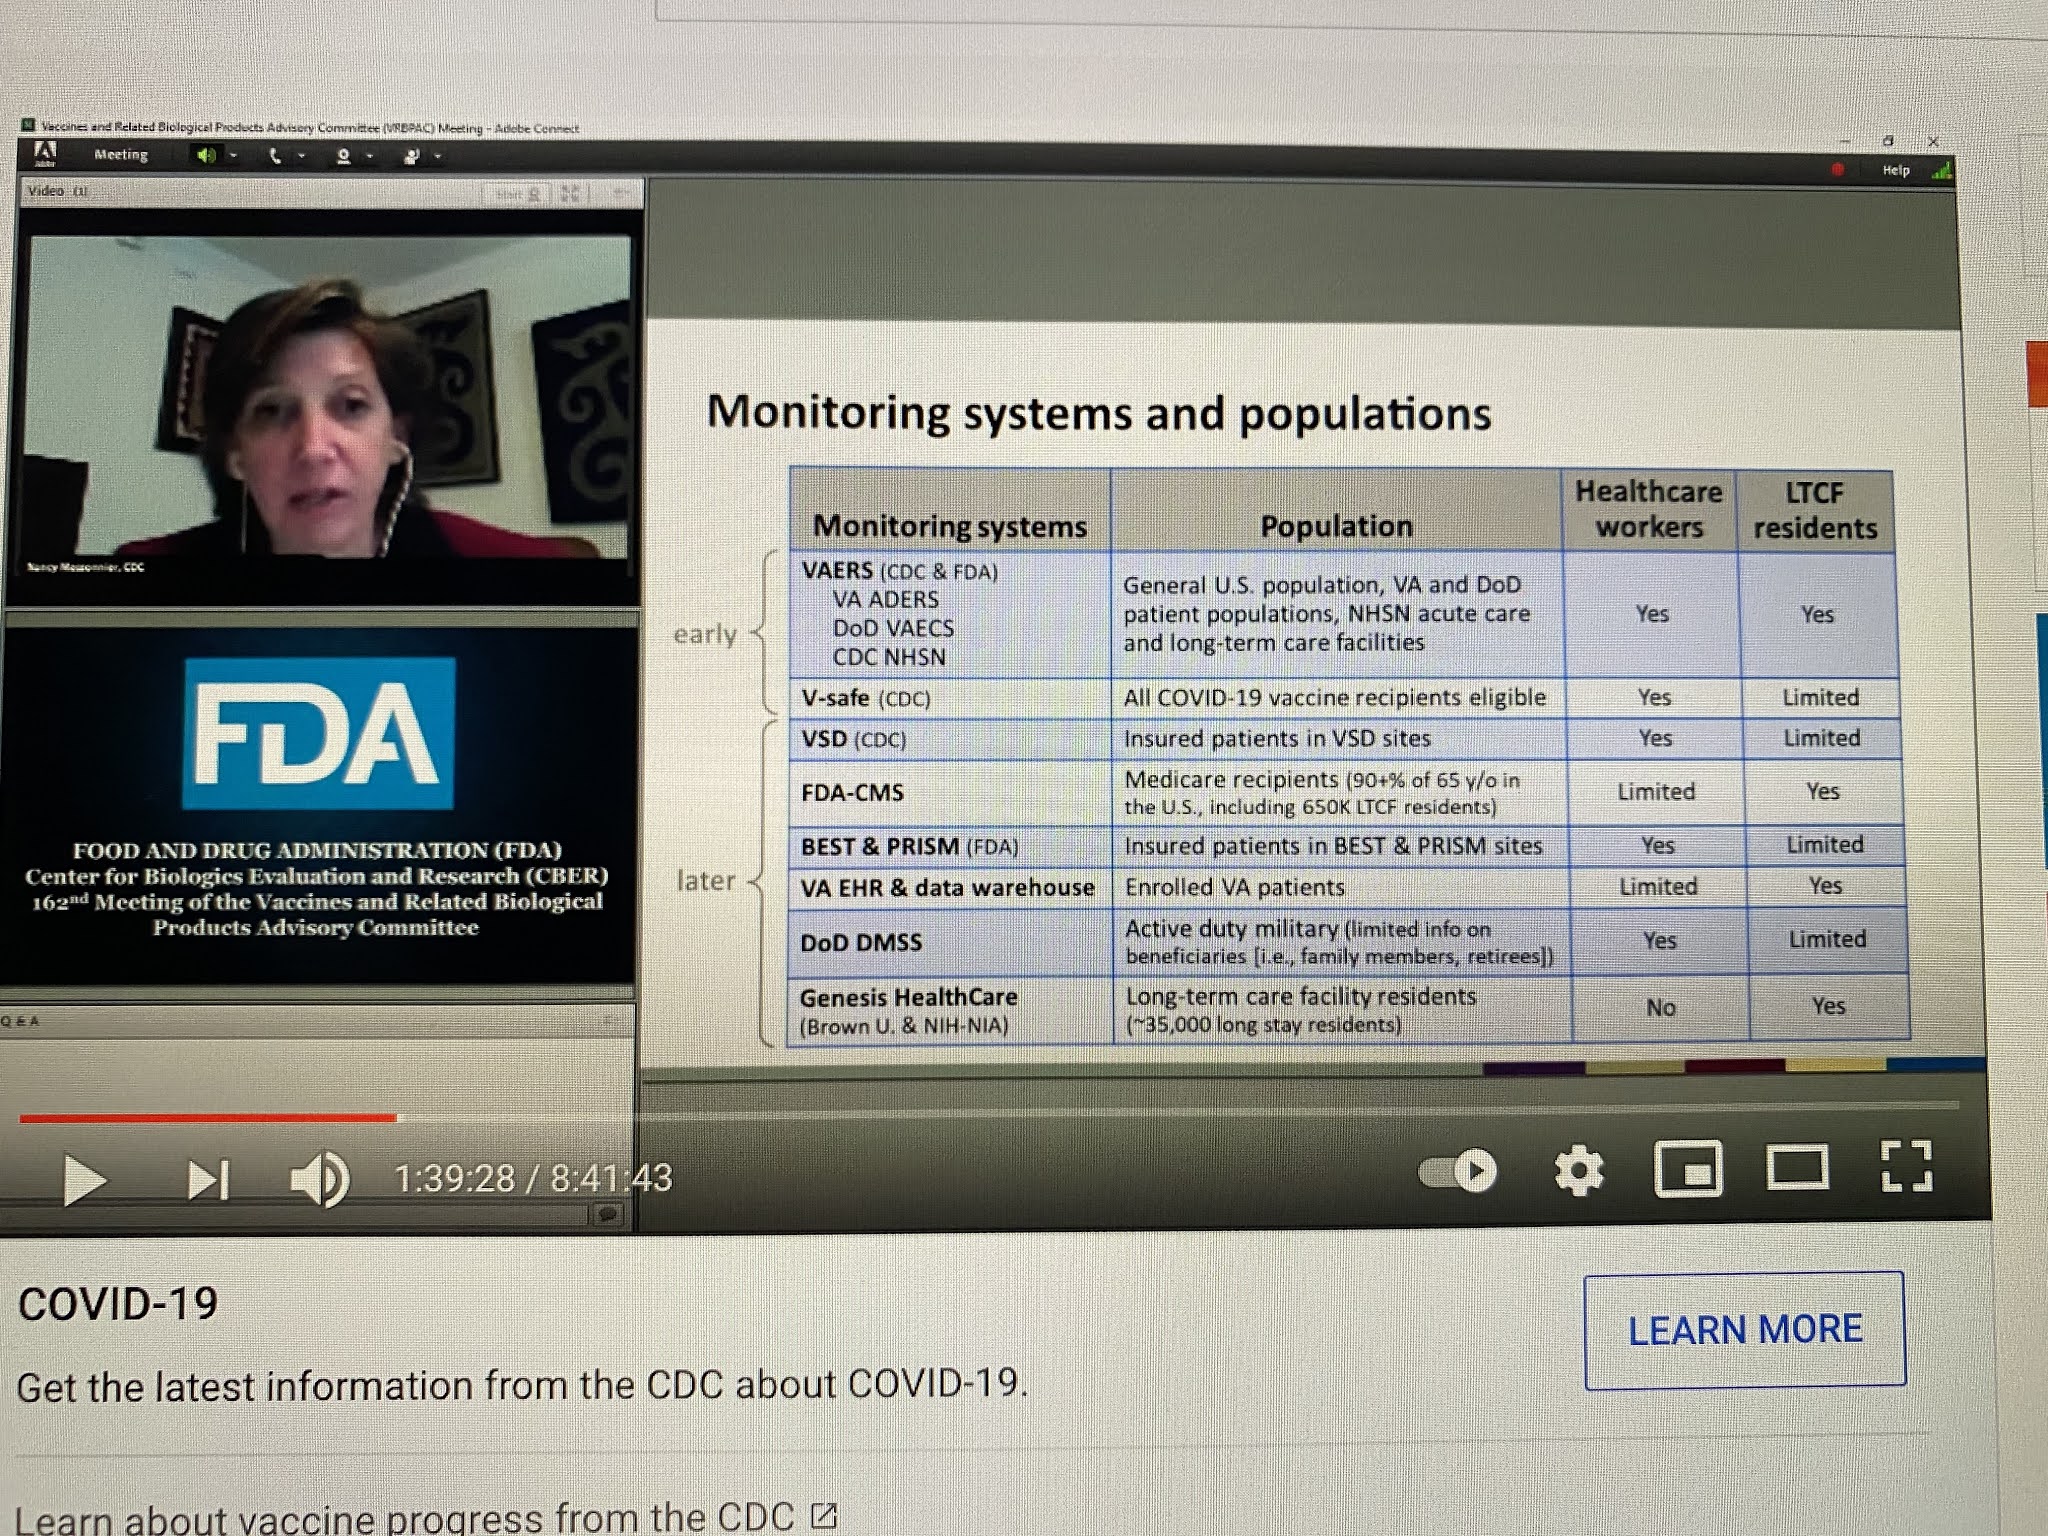
CDC has been even more shady in its analyses of safety as FDA, if that is even possible. Below, Nancy Messonier, then head of Immunizations and Respiratory Diseases at CDC, presented this list of databases that CDC would be using in the evaluation of COVID vaccine safety, on December 10, 2020. Apart from the V-safe (which they stopped talking about last January), VSD (which somehow can’t find any problems, not even myocarditis) and VAERS, all these other databases have been MIA.

NIH, whose job has never been to issue treatment guidelines, but instead to do and fund research, suddenly took over the treatment guidelines for COVID early in 2020. It formed a committee of internal and eternal “experts” to make up the guidelines. How were they chosen? That is not clear, but what is clear is that 16 of these so-called experts had current or recent financial entanglements with Gilead, the maker of remdesivir. NIH and the US Army also owned pieces of remdesivir. A number of other had financial conflicts with Merck. While NIH is the biggest single funder of medical research in the world, I cannot recall seeing a single study it funded on the safety of COVID vaccines. But somehow vaccines are its number one recommendation.
But it is not even clear that the committee is functional. The NIH has been sued to learn whether a vote was even taken by the committee regarding its ivermectin guidelines, which fly in the face of the evidence on ivermectin. How was NIH somehow authorized to issue guidelines in the first place?
Here is what has obviously occurred. All these agencies were told they had to keep quiet on vaccine problems (and perhaps problems of other COVID treatments), and they had to fiddle with their data or their analytic methods, or both, to get the required results. And there was to be NO BAD NEWS, no matter what. And no good news regarding generic treatments.
As we have seen, the so-called scientists and physicians working as bureaucrats in these agencies all caved, sucked it up, did the dirty work, kept their jobs, and betrayed their oaths and the trust of the people of the USA and the world.
December 12, 2021
Posted by aletho |
Deception, Science and Pseudo-Science, Timeless or most popular | CDC, Covid-19, COVID-19 Vaccine, FDA, United States |
Leave a comment
Time to save lives, not control them
When a pandemic hits, the facts reveal whether our public health system works. As we approach 800,000 COVD related deaths there is only one conclusion: The public health establishment of government agencies, hospitals and academic departments have failed. What a disgrace that so many have died; because nearly all could have been prevented. Mistakes, corruption and stubbornness have turned a treatable and not very deadly virus for nearly all people into a mass killing. Time to save lives, not control them.
Consider some famous mass killing events. The attack on Pearl Harbor and the 9/11 attacks each killed 3,000. The Oklahoma City Bombing less than 200. COVID deaths are an historic massacre not by bombs, bullets or explosions, but by medical incompetence never seen before. With nearly 800,000 dead in the US and over 5 million globally we see a historic genocide by governments mismanaging the pandemic.
Here are the main ways that lives could have been saved.
Cheap, safe and widely used generic medicines, principally ivermectin and hydroxychloroquine, found effective against COVID in early 2020, should have been promoted by all government public health agencies. Some bold physicians use them today. In California, Dr. George Fareed and partner Dr, Brian Tyson have treated over 7,000 COVID patients with such medicines; none have died (and half have been vaccinated). Similarly for Dr. V. Zelenko in New York with over 6,000 patients. Cases have shown ivermectin saving lives in very ill hospitalized patients.
Years of medical research data have proven unequivocally that vitamin D is an effective treatment and prophylactic for COVID. Recent German research found the necessary blood level is 50 ng/mL. Many Americans are deficient, with the Cleveland Clinic saying 42%, but that was before the higher needed level was determined. Vitamin D supplementation and blood testing for it could have been rigorously promoted.
From the beginning, CDC data showed that a very high fraction of very ill COVID patients were obese. About 30% of hospitalized COVID patients, many of whom died, were obese. Recent medical research has determined exactly how fat cells combine with the COVID virus to produce disease and illness. Yet the public health system never used a major campaign to fight obesity as a practical means of curbing COVID disease and death.
Recent analyses have shown quick home antigen test kits could have been widely and frequently used by Americans to determine whether they had COVID and needed medical assistance. But they had to be free or very cheap, as done by a number of European nations. Our government bungled this approach. Home test kits remain both scarce and expensive. Deaths result as many people let their symptoms get so bad that they need hospital care. But hospitals do not use proven generics; their approved protocols share responsibility for the 800,000-death figure.
Add in refusal to fully recognize the proven effectiveness of natural immunity acquired through prior COVID infection. Dr. Paul Alexander has concluded that about two-thirds of Americans have natural immunity. Many studies have shown that this immunity lasts longer and is even more effective against variants than vaccine immunity. Being vaccinated when there is natural immunity can wreck immune systems and cause long term health problems.
The final nail in the coffin to explain the failure of the public health system is its stubborn commitment to using experimental “vaccines” to fight COVID. Set aside the fact that CDC changed the definition of vaccine to legitimize these genetic therapies. They themselves have resulted in at least 150,000 deaths and hundreds of thousands harmful health impacts. That 800,000 figure, includes more deaths in 2021 when these “vaccines” have been widely used than in 2020 without their use. Vaccinated people keep getting breakthrough infections, with some dying. Booster shots are not the answer. Paul Alexander has explained how mass vaccination produces new variants and some like Delta are very bad.
The “follow the money” wisdom explains the collusion between government, mainstream media and drug companies to force mass (and highly profitable) vaccination through mandates and other means. This requires suppression of the generic medicines, inattention to vitamin D and obesity, and not allowing natural immunity as an alternative to vaccination.
Especially tragic is that nearly all US physicians have obeyed the dictates of the public health system, not science. They either have not done their own research or ignored extensive medical research that challenges what the public health system does. They have failed their Hippocratic oath. They should have been free to use personalized medicine – make the medicine fit the person approach, and use alternative options, besides vaccines, to save lives, not control them.
And the one physician that merits special outrage, unsurprisingly, is Dr. Anthony Fauci, the power behind the entire public health system. History will eventually cast a dark shadow on him. Meanwhile, Americans and people globally keep dying unnecessarily. There are street riots all over Europe because of pandemic insanity. We need a rebellion in the US to say “NO” to what our public health system is doing. Watch that 800,000 death figure keep increasing; without profound reforms it will reach one million. Reject what public health officials and their political bosses keep doing what has not worked for nearly two years.
December 12, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular, War Crimes | Covid-19, COVID-19 Vaccine, United States |
Leave a comment


 Aletho News

