Pro Forma Legal Letter For Parents of 12-15 Year-Olds Who Don’t Want Them to Get Jabbed
Lawyers For Liberty UK | September 2, 2021
Are you a parent? Is your 12-15 year old going back to school today? Are you worried about your child being given a Covid vaccine without your permission? Have you communicated with the school, but feel like you are being ignored?
Maybe you are concerned that ‘Gillick Competence‘ will be used to get your 12-15 year-old to make this complex decision alone?
Or that your child will be coerced or peer-pressured into making a decision without access to the full facts?
Lawyers for Liberty in association with the Jonathan Lea Network and Powerless 2 Powerful Parenting have created an anonymous “request a letter” to go from Lawyers for Liberty to your child’s school to let them know of the legal consequences of relying upon a child’s consent for a Covid vaccine, especially if a parent has specifically not consented.
We, as Lawyers For Liberty UK, will send an anonymous letter or email to schools on behalf of parents who are concerned about schools relying on their child to make a decision about whether or not to get jabbed.
If you’d like Lawyers For Liberty to send a letter or email on your behalf, fill in this form. You can read a note on the legal issues involved here and the pro forma letter here.
Top Misinformation Article Attributed to Chicago Tribune
By Dr. Joseph Mercola | September 2, 2021
According to Facebook’s content transparency report for the first quarter of 2021, released in mid-August 2021, the most popular article shared on the platform between January 2021 and March 2021 was about a 56-year-old Miami, Florida, obstetrician who died two weeks after his first Pfizer injection.1
The story initially ran in the South Florida Sun Sentinel 2 April 8, 2021, and was republished by the Chicago Tribune that same day.3 The doctor, Dr. Gregory Michael, received his first dose December 18, 2020.
Three days later, he developed small spots on his hands and feet, which prompted him to go to the emergency room, where they found he had an abnormally low blood count. Platelets stop bleeding by clotting, and when platelets drop too low, internal bleeding can occur, resulting in what looks like blood blisters on the skin.
Michael remained in intensive care for two weeks, but no matter what they did, his platelet count refused to budge. During the night of January 3, 2021, he died of a massive stroke. According to the coroner, the COVID injection could not be ruled out as a contributing or causative factor.
In a Facebook post, Michael’s widow stated he’d been “very healthy” and that he’d been a COVID-19 vaccine advocate. His death caused her to question the safety of the shot, however.
“I believe that people should be aware that side effects can happen, that the vaccine is not good for everyone and in this case destroyed a beautiful life, a perfect family and has affected so many people in this community.” she wrote. “Please do not let his death be in vain please save more lives my making this information news.”4
Even Viral Content Has Minor Reach
According to The New York Times,5 Facebook held off on publishing the first-quarter report for fear the findings might “look bad for the company.” Executives decided they wanted to make some “key fixes to the system” before releasing it. That’s why it wasn’t published until August.
Interestingly, the report reveals that even when something goes viral, the total number of views is still a tiny fraction of the overall content. Even the biggest accounts make up but a small portion of overall content views. Combined, the top 20 accounts with the most views during the first quarter — which included UNICEF, The Dodo and LADbible — accounted for only 1.18% of all U.S. content views.
As noted in the report, this “shows that, even though it may seem like a page or post has extensive reach on the platform, that isn’t the case when measured against the total amount of content available on the platform.”
Facebook Calls Out CCDH for Manufacturing ‘Faulty Narrative’
As you may know, an obscure one-man organization funded by dark money called the Center for Countering Digital Hate (CCDH) has published several reports, including “The Anti-Vaxx Playbook,”6 “The Disinformation Dozen”7 and “Disinformation Dozen: The Sequel,”8 in which the founder, Imran Ahmed — an unregistered foreign agent — claims to have identified the top most influential “anti-vaxxers” in the U.S.
In a completely unexpected turn of events, Facebook is now calling out the CCDH for having manufactured a faulty narrative without evidence against the 12 individuals targeted in its reports (myself included).9
This is important, seeing how the CCDH reports have been the primary “reference” source of authority used by media and government officials to smear, threaten and infringe on American citizens’ right to free speech.
The U.S. Department of Homeland Security even lists promulgating “false narratives” around COVID-19 as a top national security threat, which basically puts a “domestic terrorist” target on the backs of those of us who have been identified by the CCDH as the most prolific “superspreaders” of COVID misinformation.
As reported by GreenMed Info :10
“Google now shows an astounding 84,700 search results for CCDH’s defamatory phrase ‘disinformation dozen. ’Amazingly, this includes 16,000 news stories within the international press, approximately 100% of which are word-for-word amplifications of CCDH’s claims/defamatory statements and reported uncritically as fact.
In addition, the Surgeon General Vivek Murthy, the White House Press Secretary Jen Psaki, and president Biden all used CCDH’s report as the sole source for their own defamatory accusations, reaching a dangerous rhetorical climax on July 20th when Biden stated that these 12 individuals are literally “killing people” [by spreading misinformation].”
No Evidence to Support ‘Misinfo Superspreader’ Claim
In an August 18, 2021, Facebook report, Monika Bickert, vice president of Facebook content policy, sets the record straight, and in the process, demolishes the CCDH’s claims:11
“In recent weeks, there has been a debate about whether the global problem of COVID-19 vaccine misinformation can be solved simply by removing 12 people from social media platforms. People who have advanced this narrative contend that these 12 people are responsible for 73% of online vaccine misinformation on Facebook. There isn’t any evidence to support this claim …
That said, any amount of COVID-19 vaccine misinformation that violates our policies is too much by our standards — and we have removed over three dozen Pages, groups and Facebook or Instagram accounts linked to these 12 people, including at least one linked to each of the 12 people, for violating our policies.
We have also imposed penalties on nearly two dozen additional Pages, groups or accounts linked to these 12 people, like moving their posts lower in News Feed so fewer people see them or not recommending them to others. We’ve applied penalties to some of their website domains as well so any posts including their website content are moved lower in News Feed.
The remaining accounts associated with these individuals are not posting content that breaks our rules, have only posted a small amount of violating content, which we’ve removed, or are simply inactive.
In fact, these 12 people are responsible for about just 0.05% of all views of vaccine-related content on Facebook. This includes all vaccine-related posts they’ve shared, whether true or false, as well as URLs associated with these people.”
It’s worth restating the key point in this quote: Combined, the top 12 individuals and organizations identified by the CCDH as being responsible for a whopping 73% of vaccine misinformation on Facebook, are in fact only responsible for 0.05% of vaccine-related content — 1,460 times lower than the CCDH’s outrageous claim. That’s no small discrepancy.
CCDH Claims Blasted as Unjustified and Biased
Bickert goes on to refer directly to the CCDH report “The Disinformation Dozen,”12 stating:
“The report13 upon which the faulty narrative is based analyzed only a narrow set of 483 pieces of content over six weeks from only 30 groups, some of which are as small as 2,500 users.
They are in no way representative of the hundreds of millions of posts that people have shared about COVID-19 vaccines in the past months on Facebook.
Further, there is no explanation for how the organization behind the report identified the content they describe as ‘anti-vax’ or how they chose the 30 groups they included in their analysis. There is no justification for their claim that their data constitute a ‘representative sample’ of the content shared across our apps.”
CCDH Meets Definition of ‘Hateful Extremists’
Ironically, while the CCDH claims to “counter hate” online, and Ahmed sits on the Steering Committee of the U.K. Commission on Countering Extremism, CCDH itself actually meets the Commission’s definition of hateful extremists.14 In the 2019 Commission document, “Challenging Hateful Extremism,” the term is defined as:15
“Behaviours that can incite and amplify hate, or engage in persistent hatred, or equivocate about and make the moral case for violence; And that draw on hateful, hostile or supremacist beliefs directed at an out-group who are perceived as a threat to the wellbeing, survival or success of an in-group; And that cause, or are likely to cause, harm to individuals, communities or wider society.”
In addition, in the forward of the report, lead commissioner Sara Khan notes that “Hateful extremists seek to restrict individual liberties and curtail the fundamental freedoms that define our country.”
All of these definitions and clarifications of what hateful extremism is fit the CCDH to a T. Ahmed manufactured data to create a false narrative that 12 individuals pose a threat to the well-being and survival of the whole world, and then used that narrative to incite hate against us and curtail our freedom of speech.
Who Fact Checks the Fact Checkers?
In related news, the self-appointed arbiter of factual truths, NewsGuard, has had to backpedal in recent months and issue dozens of corrections to “fact checks” in which they’ve labeled the Wuhan lab leak theory as a debunked conspiracy theory with no basis in fact.
Since the beginning of the COVID pandemic, NewsGuard has wrongly down-rated 225 websites for articles mentioning the lab leak theory.16 In reality, there’s far more evidence to support the lab leak theory than any other theory, but it took over a year before the weight of this evidence became too obvious for the media to ignore.
NewsGuard’s erroneous fact checks were recently highlighted in an August 11, 2021, report by the American Institute for Economic Research (AIER).17
AIER decided to take a closer look at NewsGuard after receiving a request for comments on a NewsGuard fact check article regarding AIER and the Great Barrington Declaration — a statement written by public health experts from Harvard, Stanford and Oxford that calls on government to implement focused protection rather than lockdowns and self-isolation. AIERS investigation found that:18
“… NewsGuard falls far short of the very same criteria for accuracy and transparency that it claims to apply to other websites. Most of the company’s fact checkers lack basic qualifications in the scientific and social-scientific fields that they purport to arbitrate.
NewsGuard’s own track record of commentary — particularly on the Covid-19 pandemic — reveals a pattern of unreliable and misleading claims that required subsequent corrections, and analysis that regularly conflates fact with opinion journalism in rendering a judgement on a website’s content.
Furthermore, the company’s own practices fall far short of the transparency and disclosure standards it regularly applies to other websites … NewsGuard’s staff primarily evaluates scientific claims by appealing to the authority of public figures who they designate as ‘experts’ on the subject in question.
Their approach generally avoids direct examination of the evidence surrounding contested claims, and instead cherry-picks a figure to treat as an authoritative final word … many of their preferred authorities are political officeholders rather than persons trained in scientific or social-scientific methods.
By selectively curating cherry-picked political authorities rather than evaluating evidence directly, NewsGuard’s approach to fact-checking effectively sidesteps the scientific method. This strategy is rendered even more problematic by the general lack of scientific expertise within NewsGuard’s team of writers.
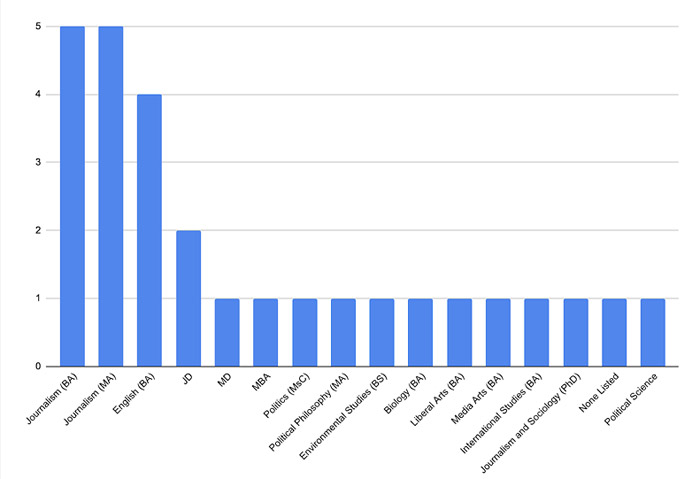
We examined the educational credentials, including the highest degree listed, for 28 publicly identified staff members on NewsGuard’s website. The company’s staff page reveals shockingly little expertise in either the hard sciences such as medicine or social sciences such as public policy, economics, and related fields …
Most NewsGuard articles on Covid-19 topics and policies are written by [NewsGuard Deputy Editor for Health, John] Gregory, whose only identified qualification is a bachelor’s degree in Media Arts … Gregory would not qualify as an expert in most of the fields he is responsible for fact-checking …
Of course, non-experts have every right to offer opinions on scientific and social-scientific matters. Whether or not they should be taken seriously as fact checkers or act as arbiters of scientific disputes is another question entirely.”
NewsGuard Staff by Field and Highest Degree Attained
NewsGuard Apologizes for Erroneous Fact Checks
After being confronted about its erroneous fact checks on the lab leak theory, NewsGuard offered the following apology in a statement sent to AIER:19
“NewsGuard either mischaracterized the sites’ claims about the lab leak theory, referred to the lab leak as a ‘conspiracy theory,’ or wrongly grouped together unproven claims about the lab leak with the separate, false claim that the COVID-19 virus was man-made without explaining that one claim was unsubstantiated, and the other was false.
NewsGuard apologizes for these errors. We have made the appropriate correction on each of the 21 labels.”
AIER commented on the apology:20
“Gregory and his colleagues appear to have simply decided that their own premature dismissal of the lab leak hypothesis equated to ‘fact’ and proceeded to penalize other sites not for factual errors, but rather for diverging from NewsGuard’s own editorial position on the same subject.
When this position turned out to be mistaken, NewsGuard pivoted to remove the errors — albeit in non-transparent ways that downplay the significance or pervasiveness of their mistake.”
NewsGuard Fails to Fulfill Its Own Credibility Criteria
In their report, AIER goes on to apply the criteria NewsGuard uses to evaluate a website’s credibility to NewsGuard itself. It’s ranking? A paltry 36.25 out of 100. According to AIER:21
“This website fails to adhere to several basic journalistic standards, and should be used with extreme caution as a source for verifying the reliability of the websites it purports to rate …
When we see fact checkers like NewsGuard, who not only fail to uphold their high-sounding principles but even publicly encourage working with the government to suppress speech, we should raise red flags.”
The NewsGuard ratings are meant to influence the reader, instructing them to disregard content with cautionary colors and cautions. That it would serve as the thought police of the technocratic establishment that seeks to silence dissent and bury information that doesn’t help move the Great Reset agenda forward is no surprise.
Especially considering its primary startup capital came from Publicis Groupe,22 a PR group that represents most of Big Pharma, including vaccine makers, and Big Tech. NewsGuard is also backed by Microsoft23 and Google.
The Publicis Groupe has been manipulating what people think about commercial products for nearly a century. Over that century, this advertising and communications firm bought or partnered with targeted advertising avenues, beginning with newspapers, followed by radio, TV, cinema and the internet.
With revenue avenues secured, Publicis’ clients and partners built a global presence that dominated the advertising world. Be it tobacco or sugar, Publicis Groupe found a way to promote and strengthen big industries. Publicis was recently sued24 for its deadly and illegal marketing of Purdue Pharma’s opioid products.
When you consider that Publicis describes its business model approach as putting clients and their needs and objectives at the center of all they do so their clients can “win and grow,” it’s easy to see what’s driving NewsGuard.
Overall, NewsGuard is just another big business aimed at keeping the chemical, drug and food industries, as well as mainstream media, intact by discrediting and eliminating unwanted competitors and analysts who empower you with information that runs counter to any given industry’s agenda.
If you’re as disturbed by censorship as I am, be sure to contact your local library today to find out if they’re one of the more than 700 libraries using NewsGuard. If they are, then ask them if they’re aware of NewsGuard’s censorship of truthful news that is now encroaching on scientific freedom and threatening the very roots of our democracy.
If your local library is using NewsGuard, it would be helpful to start a campaign to get it removed. Contact your neighbors and let them know what is happening so they can kick out this public health threat. Likewise, whenever you see someone referencing reports by the CCDH, call them out on it.
Sources and References
- 1 USA Today August 23, 2021
- 2 Sun Sentinel April 8, 2021
- 3 Facebook Heidi Neckelmann
- 4 Chicago Tribune April 8, 2021
- 5 New York Times August 20, 2021 (Archived)
- 6 The Anti-Vaxx Playbook (PDF)
- 7, 12, 13 CCDH, The Disinformation Dozen
- 8 Misinformation Dozen: The Sequel
- 9, 11 Facebook August 18, 2021
- 10 GreenMed Info August 19, 2021
- 14 Greenmed Info March 25, 2021
- 15 Challenging Hateful Extremism 2019
- 16, 17, 18, 19, 20, 21 AIER August 11, 2021
- 22 Washington Post March 3, 2018
- 23 axios.com August 23, 2018, NewsGuard Launches First Product With Help From Microsoft
- 24 Reuters May 6, 2021
La Résistance: French Create Their Own Makeshift Restaurant Again to Protest Vax Passports
Reims demonstrators return in greater numbers
By Paul Joseph Watson | Summit News | September 2, 2021
Another example has emerged of French people creating their own makeshift outdoor restaurant in protest against the country’s vaccine passport system.
Video footage out of Reims shows large numbers of people, including many families, camped out on the street enjoying picnics in defiance of the new rule, which bans the unvaccinated from entering bars, cafes or restaurants.
Vaccine passports are also being used to prevent people who haven’t been jabbed from using public transport and accessing a multitude of other venues.
The sit down protest took place at Place d’Erlon, near to restaurants that demonstrators are unable to enter because they haven’t taken the clot shot.
This is the second time the protest has taken place in this location, although this time the numbers appear to be even larger.
As we highlighted last month, anger at the vax pass system is running so rampant that many businesses are refusing to enforce it.
Former Google software engineer Mike Hearn revealed how compliance with the new rules was minimal as he was able to enter numerous venues without showing proof of vaccination or a valid negative test.
This contrasted with the early days of the introduction of the program, during which police were seen patrolling cafes demanding to see people’s medical papers.
Supporting Doctors’ Rights To Speak, Free From Censorship
doctors4covidethics.org

Dr. Paul Oosterhuis is an Australian anaesthetist with over thirty years experience, including in critical care and resuscitation, who urgently needs your support.
He is facing a hearing by the Medical Board of NSW for posting information on social media regarding COVID-19. His posts related to early treatment and prophylaxis, PCR tests, and risk-benefit calculations regarding COVID-19 vaccination and lockdowns (scroll down for details). His hearing is on September 3rd. Please help him by signing and sharing this petition.
We are practicing doctors and allied health professionals and/or scientists and academics and/or members of the public and/or represent professional organisations. We support the right of Dr Oosterhuis, and that of all doctors, to offer informed medical opinions on COVID-19 and to discuss the available evidence on COVID-19 interventions.
As doctors we too have advised and continue to advise patients and the general public about the medical management of COVID-19 disease and vaccination on the basis of good science. As members of the public we reserve the right to receive honest information, opinion and advice from our doctors, free from government interference.
From Dr Oosterhuis:
Dear colleagues and concerned citizens,
Thank you for taking the time to read this petition.
My name is Dr Paul Oosterhuis. I am an anaesthetist from Australia. I have been called before the NSW Medical Board for a hearing on September 3rd 2021 following anonymous complaints about my social media posts on Facebook regarding COVID-19. I have been advised by the Medical Council that:
“The Medical Council of NSW received two anonymous notifications regarding your activity on social media.
Due to the concerns outlined in the notifications the Council has resolved to convene proceedings under section 150 of the Health Practitioner Regulation National Law (NSW) to consider whether any action is required for the protection of the health and safety of the public or in the public interest.”
Ahead of the hearing I am seeking signatures from my medical and scientific colleagues and members of the public to help me defend my own and all doctors’ rights to offer our informed medical opinions, share our expertise, and engage in open discussion regarding COVID-19.
I am a Sydney University trained medical graduate. I undertook my internship and residency at Prince of Wales Hospital in Sydney, followed by postgraduate training in Anaesthesia at The Royal Prince Alfred Hospital. I have more than 30 years of practice, the first 20 years involving hands-on critical care and resuscitation, and the last 10-plus years as a senior Visiting Medical Officer working in the Sydney Local Health District.
In the social media posts for which I face a Medical Board hearing, I discussed issues such as early treatment and prophylaxis against COVID-19, evidence for government measures such as lockdowns and PCR tests, and evidence regarding risk-benefit analyses of COVID-19 vaccines.
For example:
“I wish you could just add EARLY TREATMENT and drug PROPHYLAXIS …..Tell everyone to take Vit D, Zinc, and EARLY TREATMENT with IVM/ HCQ as evidence based medicine alternatives.”
I provided a link to a presentation by Dr Paul Marik on prophylaxis in support of the post, highlighting a chart of vitamin D versus risk of COVID from Dr Marik’s presentation, to illuminate the low hanging fruit of prophylaxis.
In other posts I questioned the evidence base for the government’s policies of lockdowns and mask mandates, and pointed out that there is evidence of vaccines having low effectiveness and real risks and harms (which are being suppressed), along with harms from the totalitarian lockdowns causing massive damage society-wide.
The risk of Antibody Dependent enhancement of disease, predicted by Dr Geert Vanden Bossche, driven by immune escape from the selective evolutionary pressure of vaccinating with a non sterilising agent is a real and present danger and needs to be discussed. The danger to millions is distressing to me, and discussing that danger is, I believe, unarguably in the public interest.
Early in 2020, I was active in criticising my medical administrators for failure to prepare for an outbreak such as COVID-19 when it was apparent that PPE was being rationed (P95’s were in short supply). I urged my colleagues to perform quantitative fit testing of our available P95 masks in early 2020 during which we found a surprising number of staff failed quantitative fit testing with the hospital issued PPE. This was something I had hypothesised after looking at the number of healthcare workers in Northern Italy catching the disease.
I withdrew from clinical practice last year out of concerns about the increasing incompetence of the health administrators and the rapidly reduced autonomy of doctors to just be able to be a doctor.
Over the last 18 months I have been increasingly concerned about the misinformation and censorship creeping into science and medicine. Fellow physicians were saving lives with early treatment and medication/supplement approaches to prevention but it was THIS that was attacked and censored! People like Dr Paul Marik, Dr Pierre Kory of the FLCCC Alliance, Dr Robert Malone, Dr Geert Vanden Bossche, Dr Michael Yeadon, Dr Vlad Zelenko, Dr Chris Martensen, Dr Eric Weinstein and others are making credible and serious warnings about the gene therapy being coerced upon our populations.
Censoring their work, and the research of experts like Dr Tess Lawrie, Dr Peter McCullough, Dr Sucharit Bhakdi and America’s Frontline Doctors is dangerous.
The Medical Board of NSW is now using intimidation, threatening doctors like myself, who share data which questions the official narrative. I don’t believe that censorship is compatible with good science and good medicine, and I believe that it needs to stop now, in the name of public health and public interest.
I would be very grateful if you could help to support me in my effort to inform as many as possible about their true health choices. My hearing is in a matter of days.
While I wish I did not have to defend my right to speak truthfully as a doctor, the song and video below captures my attitude to fighting for that right. I hope you enjoy it.
With my most sincere thanks,
Dr Paul Oosterhuis
Australia
See also:
NZ Doctors Speaking Out with Science (petition)
UK Schoolchildren To Be Covid Vaxxed With Or Without Parental Consent
ALERT: ALL PARENTS IN U.K. WITH CHILDREN AGED 12 – 15 years
By Dr. Mike Yeadon | Health Impact News | August 26, 2021
I’ve just been informed via someone senior in the vaccination authorities that they will begin VACCINATING ALL SCHOOL CHILDREN AGED 12 – 15 years old STARTING SEPTEMBER 6th 2021.
WITH OR WITHOUT YOUR CONSENT.
Children are at no measurable risk from SARS-CoV-2 & no previously healthy child has died in U.K. after infection. Not one.
The vaccines are NOT SAFE. The USA reporting system VAERS is showing around 13,000 deaths in days to a few weeks after administration. A high % occur in the first 3 days. Around 70% of serious adverse events are thromboembolic in nature (blood clotting- or bleeding-related).
We know why this is: all of the gene-based vaccines cause our bodies to manufacture the virus spike protein & that spike protein triggers blood coagulation.
The next most common type of adverse events are neurological.
Death rates per million vaccinations are running everywhere at around 60X more than any previous vaccine.
Worse, thromboembolic events such as pulmonary embolisms, appear at over 400X the typical low rate after vaccination.
These events are serious, occur at a hideously elevated level & are at least as common in young people as in elderly people. The tendency is that younger people are having MORE SEVERE adverse events than older people.
There is literally no benefit whatsoever from this intervention. As stated, the children are unquestionably NOT AT RISK & vaccinating them WILL ONLY RESULT IN PAIN, SUFFERING, LASTING INJURIES AND DEATH.
Children rarely even become symptomatic & are very poor transmitters of the virus. This isn’t theory. It’s been studied & it pretty much doesn’t happen that children bring the virus into the home. In a large study, on not one occasion was a child the ‘index case’ – the first infected person in a household.
So if you’re told “it’s to protect vulnerable family members”, THAT IS A LIE.
The information emerging over time from U.K. & Israel is now showing clearly that the vaccines DO NOT EVEN WORK WELL. If there’s any benefit, it wanes.
Finally, the vaccines ARE NOT EVEN NECESSARY. There are good, safe & effective treatments.
IF YOU PERMIT THIS TO GO AHEAD I GUARANTEE THIS: THERE WILL BE AVOIDABLE DEATHS OF PERFECTLY HEALTHY CHILDREN, and severe illnesses in ten times as many.
And for no possible benefit.
KNOWING WHAT I KNOW FROM 40 years TRAINING & PRACTISE IN TOXICOLOGY, BIOCHEMISTRY & PHARMACOLOGY, to participate in this extraordinary abuse of innocent children in our care can be classified in no other way than MURDER.
It’s up to you. If I had a secondary school age child in U.K., I would not be returning them to school next month, no matter what.
The state is going to vaccinate everyone. The gloves are off. This has never been about a virus or public health. It’s wholly about control, totalitarian & irreversible control at that, and they’re nearly there.
PLEASE SHARE THIS INFORMATION WIDELY.
With somber best wishes,
Mike
ACIP vote yesterday, after deceitful CDC briefings, removes liability from Comirnaty and opens door to mandates
By Meryl Nass, MD | August 31, 2021
In a nutshell: Yesterday CDC asked its advisory committee to “recommend” the Comirnaty vaccine for 16 and 17 year olds. And it agreed, unanimously. Or pusillanimously.
The vote may seem silly or superfluous, because it had already been recommended for this age group as an EUA.
But this vote was anything but superfluous. This seemingly minor recommendation, which did not get headlines, moves the licensed Comirnaty vaccine from a place where the manufacturer is legally liable for injuries, to a berth within the Childhood Vaccine Injury Compensation Program, for which there is no manufacturer liability. Instead a $0.75 excise tax is charged per dose, which goes into a fund administered by DHHS to pay for injuries, if one is lucky enough to convince the special masters (judges) in the program that a vaccine caused your injury. Once a vaccine is recommended for children, its liability is waived no matter who receives it.
But the important part is that once this process is complete (which I expect to be only a very few weeks), Pfizer can roll out stocks of the licensed vaccine while still having its liability waived. That means that the loophole I told you about last week is being backfilled by the USG, with the help of the supine and spineless ACIP committee members, and will soon disappear.
I say spineless with true conviction, because the briefings they received yesterday were a load of fraud and hogwash. Yet no one challenged the data nor the conclusions. It is hard to believe that the lot of them are really that stupid that they believed what they heard. It is also hard to believe that none of them had a conflict of interest, which they all asserted along with their vote.
Furthermore, no one ever actually said why the vote was held: which was for liability purposes, nor that the vote would lead to mandates, which could not be implemented under the EUA.
So, it is disappointing.
Children’s Health Defense went to court today in Tennessee to challenge the FDA on issuing both a license and EUA for the same product. AFLDS also went to court today in Colorado challenging the mandate. More on these cases later.
The Science Is Clear – The Case Against Mandating Vaccines: One Executive’s POV
SOTT | August 31, 2021
SOTT Editors: We are publishing below, with permission, an email from a top executive at an American company whose clients include 100 of the Fortune 500 companies. The email was sent in reply to another executive asking for the writer’s thoughts on whether he plans to be vaccinated himself or mandate it for his employees as a requirement for returning to the office. All names and company references have been redacted for privacy reasons.
Unlike most of us who are worried about being on the receiving end of vaccine mandates by employers, this executive also has to worry about pressure from other executives and investors to mandate it on others. Few such business leaders are actively fighting for the rights, dignity, peace, and financial security of their employees. This exec is currently the only voice in his company opposing the madness.
Email to the executive:
Hey [REDACTED] – are you giving any thoughts to getting vaccinated with all this Delta variant stuff going on? We’ve been having management committee discussions here about mandatory vaccinations to be able to come in to the office. We have office support people coming in most days that are not vaccinated and some of those with kids don’t want to come in when they are in the office or invite clients into the office for meetings. Just curious as to how you are approaching it. Thx, [REDACTED]
The executive’s reply:
From: [REDACTED]
Date: Fri, Aug 27, 2021 at 9:56 PM
Subject: MY POV on Mandating Employee Vaccinations
To: [REDACTED]
I appreciate you reaching out. What follows is admittedly lengthy (though I do provide my “summary POV” a couple paragraphs down before I dive into supporting detail). I tried to be succinct, but practically speaking your question for me was akin to “hey, so what’s your take on management?” The analogy here being I’m passionate about both subjects so it was hard to choose between sending back a brief 2-minute POV, or filling this email with enough content fit for a university level course. I didn’t know what you had an appetite for, so I just simply did my best to try and be helpful (and heck, even had some fun while I was at it…).
My framework for this entire POV: in the famous words of W. Edwards Deming, “In God we trust. All others must bring data.” As I hope you’ve come to know me by now, I care more deeply about facts & morals than I do ideology or identity politics (for the latter I just don’t give a shit). If you give me a good reason to do something, I am 100% all over it. But if you give me either faulty reasoning or an unethical ultimatum, I simply cannot get on board out of a moral obligation to do what’s right.
So to answer your questions with that sole framework in mind, here’s my summary POV:
(#1) I still have no plans to get vaccinated anytime in the foreseeable future (unless something radically changes the risk equation), given:
(a) The virus at present poses de minimis risk for me personally (and virtually zero risk to any healthy child (a reference to your initial inquiry)); and
(b) Because these vaccines carry –> confirmed low/moderate short term — inferred moderate medium term — and expected high long-term health risk for what could be [though yet unknown] a majority of individuals who get the jab
(#2) I remain vehemently opposed to vaccine mandates for this specific virus (primarily on the basis of (i) 1b above, (ii) the medical literature, which strongly suggests that these vaccines will prolong this pandemic indefinitely through never-ending variants, and thus/therefore (iii) on moral grounds, as, if (i) and (ii) are true, then any decision to proceed with mandates would be nothing short of a descent by the West towards fascism**, the likes of which hasn’t reared its ugly head since the early 20th century. Finally, at a distant, distant second, I am against these mandates from a logistical perspective*.
*E.g., how will you account for boosters (i.e., will those who were vaccinated too far in the past e.g., January and thus have substantially waning transmission protection also be excluded from the office)? What about those who got a different jab (e.g., AstraZeneca, Sputnik, CoronaVac, etc.), each of which has varying levels of effectiveness (and varying levels of effectiveness reduction over time) against different variants? How will you handle those that already had COVID-19 (and therefore (a) have even higher immunity than the vaccinated, and (b) who face higher health risks if they get vaccinated post- natural infection)? What will you do with the immunocompromised (folks with organ transplants, lung problems or cancer patients) who got the vaccine but have low viable antibodies because they require evermore booster shots? What will you do when future variants require different jabs? I could go on, but I trust you get the point. My real question for you is, will you be responsible for coordinating monthly/quarterly management meetings to update & maintain these ever-changing mandate policies covering ever-growing future use cases?
**And if you think I’m exaggerating, look no further than NY State Assembly Bill A416, which proposes forcibly putting carriers of COVID-19 who do not conform to the state’s medical guidelines into something akin to internment camps, where they will be forced into a treatment deemed appropriate by the state and detained indefinitely until they comply. Imagine a U.S. legislative policy so bad, that even Russia Today was able to shit all over it as being far too draconian. And it’s not just the state of NY, but the CDC as well.
===================
Last comments before I dive into supporting details
To not lose sight of being pragmatic as it pertains to your inquiry, I want to point out that at this juncture even a discussion about vaccine mandates is mostly moot.
We already know (confirmed) that those who are vaccinated/infected carry as much viral load as the unvaccinated. Which, coupled with waning transmission prevention efficacy means for all practical intents & purposes those vaccinated and those unvaccinated pose similar risks to one another.
And this is notwithstanding even more cutting edge research (not even yet published i.e. currently pre-print in The Lancet), which suggests those vaccinated carry significantly (upwards of 200x) more viral load than the unvaccinated (which would, if peer-reviewed, flip the risk equation on its head even further in that those vaccinated would pose far greater risk to one another than those unvaccinated). (And it is worth noting that this development would be consistent with what has been found with other vaccines — in this 2017 study, for example, it was assessed that those who were vaccinated for influenza shed 6.3x as much virus as those who are unvaccinated. Crazy stuff.)
All of this is to say, despite the nationwide pushes you’re seeing for private & federal workplace vaccination mandates (which may have made at least some sense much earlier on), such mandates are unfortunately no longer effective models at this stage, unsupported by what we now understand via the latest science. Instead, if you really want to make a difference in improving workplace safety at this juncture, I would suggest implementing either the 1st, or both, of the following policies:
(1) Everyone at the company must perform a daily (pre-commute) self-assessment health survey, whereby all individuals must confirm they are not exhibiting any of the known symptoms of COVID-19 (i.e., if you can’t smell, have fever/chills, shortness of breath, etc., you can’t come in to the office, period), without any pressure from management to respond they are symptom-free.
(2) (Optional) everyone, irrespective of vaccination status, must get tested weekly for COVID-19, such testing to be reimbursed by the company. If you test positive, you aren’t allowed to come in until you test negative.
You asked how we’re handling it, and I can tell you that we’re doing the first one at [my company], and I would recommend utilizing the second one for any in-person company events. That’s it. No mandates. Anything beyond that will lead you into a logistical nightmare (at best), foster a false sense of security as it isn’t effective (worse), and in my humble opinion, is purely unethical (worst of all, which I’d like to think is a decent enough reason not to do something) at this stage.
So anyways, all of the above is the summary of my current POV. What follows below is/are the supporting details for the conclusions I reached in my summary POV 1(a), 1(b), and 2(i) above, if you’re interested in the data.
Always happy to chat/update further as the saga continues ✌
best, [REDACTED]
P.S. if you’re going to skip Parts 1 & 2 below*, then no worries… I get it, I probably wrote far more than you were looking for. But if indeed you do skip them, try to make it to the ‘Closing Thoughts’ section way down below — I’ve sourced a nifty chart down there that might give your colleagues pause in their ongoing discussions about mandates before they consider the unvaccinated to be idiots for whom behavioral mandates are the only appropriate solution.
*Though I highly recommend Part 1 (where it says “TWO OTHER THINGS TO CONSIDER” (then scroll to find #2)) as this contains a suggestion for how to naturally protect yourself from COVID-19.
===================
PART 1: RISK OF COVID-19 DEATH —> DE MINIMIS FOR ME
First I’ll address why I do not view COVID-19 as dangerous for me personally: from the CDC’s own data, available here, you can see current the Count of Cases and Count of Deaths by age ->
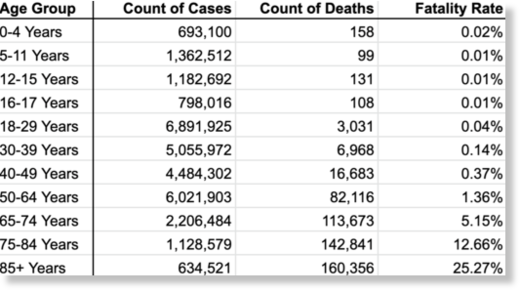
(Though before I go further, pardon me for abstaining from a lengthy discussion on the reliability of data from an organization that even Dr. Deborah Birx herself — (an individual who received a Meritorious Service Medal from the U.S. Department of Defense in 1991 and a Medal of Excellence from the CDC in 1994) — was quoted as saying she didn’t trust a single word from. Hmm, I wonder why she didn’t “trust” the data, could it be because they were —> overinflating “COVID-19 deaths”? <—… I digress.)
Anyways, according to the CDC, being 32, my “risk” stands at 0.14% (purely averages speaking, irrespective of the analysis below); a “starting statistic” you could call it.
The immediate issue with this data, unfortunately, is we’re only able to count cases with confirmed COVID-19 PCR (or other) test results, undercounting materially true case counts to date. As you might imagine, those asymptomatic do not test themselves regularly or out of nowhere. I mean, personally speaking, I am obviously not testing myself on any basis on any cadence — I’d only get tested if I had reason to. Thus is the reason, that the CDC already stated well early on in this pandemic that true case counts were “likely” to be upwards of 10x higher than we have documented (which they concluded based on widespread antibody testing).
Deaths in the U.S., on the other hand, are religiously tested for COVID-19, capturing the vast majority (if not nearly all) deaths, where a COVID-19 infection was present.
Using these two bits of information from the CDC, we can adjust for a “truer” baseline risk. Now, while I could exercise the luxury of taking on more than a 10x spread (because those younger tend to be more asymptomatic), I’ll be conservative just for the sake of it and just use the “10x average” figure. And so, a true starting statistic for me isn’t 0.14%, but a markedly lower 0.014%.
Next, we can use Exhibit B, taken right from the CDC website:
For… 5% of… [COVID-19] deaths, COVID-19 was the only cause mentioned on the death certificate. For deaths with conditions or causes in addition to COVID-19, on average, there were 4.0 additional conditions or causes per death.
Again, this is nothing new and has been known since very early in the pandemic, as you can see from this study for example listing the leading comorbidities as measured in NY as early as April 2020:

And herein lies my second issue with folks who preach to me that vaccines are necessary for my survival (the first being my initial lowly baseline risk).
Knock on wood, but I have no non- COVID-19 induced comorbidities — zero. My takeaway is just that: for someone like me, COVID-19 is mostly a virus known to exacerbate serious pre-existing conditions to the point of overwhelming the system definitively.
Put another way, imagine a motorcycle rider trying to assess their risk of death from riding (i.e., catching COVID-19). They see a study which puts the risk of death for those motorcycle riders who were (1) drunk (2) doing a wheelie on the highway (3) during a rainstorm, and (4) while texting with a friend (i.e., analogous to four comorbidities). It would be flawed reasoning for a rider who doesn’t do any of those things to put themselves in the same risk category as those who do. So while no one is saying motorcycles aren’t dangerous — they certainly are — they’re nowhere even in the vicinity as dangerous as riding while doing all the other things. Likewise, neither should a healthy teenager dwell on their COVID-19 risk with the same fervor as a 100 year-old morbidly obese individual with terminal cancer.
Okay, let’s revisit my personal risk again. First, I will ignore the 5% “no comorbidities” statistic above, because out of fairness I want to account for likely COVID-19 induced comorbidities like Respiratory Failure, Sepsis, etc. as well as possible ones like Renal Failure, Cardiac Arrest, and the like. So, let me simply reduce my risk not by 95%, but 57% (conservatively even rounded down further to a clean 50%), which removes just 1 non- COVID-19 induced comorbidity for my age group.
And just like that, my adjusted risk is downgraded to 0.0069% annually (annually, because it’s only once a year — after which time a better-than-vaccination natural immunity kicks in for that season).
So what really is 0.0069%, you might ask? After all, we humans aren’t terribly good with numbers like that. To help you put it in perspective, consider that according to the National Highway Traffic Safety Administration, your (or my) risk of dying from a freak car accident in any given year, is 1 in 5,407 or 0.018%.
Let that sink in: based on what we know today, I personally am 268% more likely to die in a car accident tomorrow (or any day this year) than COVID-19. But do you really think that in pre-pandemic times, the “1 in 5,407” statistic kept me locked up inside my house? You think even today (in the middle of a pandemic) that figure stops me from taking a leisurely drive to grab ice cream with my nephews? or catching a movie with my brother? or — God forbid!! — hanging out with and actually talking with my friends? No!, and it never could. Because life, my friend, is about dancing in the summer rain, not cowering in fear of getting struck by lightning. But hey, maybe that’s just me…
In any case, I want to come back to your comment about concerns your colleagues have regarding young children. When we look at the statistics available (table above), the results are even more stark: for kids aged 5-11, their odds of a fatal COVID-19 infection are 1 in 137,000 when you factor in asymptomatic cases. And again, we’re talking about a risk inclusive of those with comorbidities. For kids 5-11 who are perfectly healthy, you can consider their risk nil. Okay, well obviously it could never be actually zero, because we both know sometimes kids also fall off a bike and kill themselves — that’s life. But you don’t exactly see people running around freaking out over bicycles all day long, do you? Which is ironic as hell now that we’re on the subject, considering almost exactly the number of kids have died from bicycles as from COVID-19 in the same time frame.
So when I hear about folks taking their kids for a bike ride on the weekend (how awful), or worse!, maniacally driving their kids for ice cream (putting those precious kids at 5,091% (51x) the risk of death as COVID-19), but then trembling at the thought of walking into an office the following Monday because there’s an unvaccinated person there, so they feel the need to demand forcing medical decisions on those people (like getting jabs with vaccines made by companies whose rap sheets (Pfizer, J&J) would satisfy essay requirements at most colleges, approved by an organization that finds safety issues in 1/3 of its drugs post-approval), I come to the simple conclusion that common sense has left the building — it’s mass hysteria.
Alright, enough beating the completely de minimis personal risk dead horse because the point is clear. But let me add two more small things before getting to the dangers of the vaccine:
TWO OTHER THINGS TO CONSIDER
The section above looked at the whole thing purely from a mathematical risk perspective with neither proactive measures in mind, nor accounting for simple and effective (though IMO criminally suppressed) treatment options available to thwart COVID-19 risk even further.
(1) First, on the treatment side. Look, I know there was the whole “orange man (Trump) bad, the FDA disagrees” political BULLSHIT thing going on. Like I said above, I do not give a shit about the political angle of any of this. I require data, and the data could not be more ironclad on the subject matter. I will simply leave these two links here, and avoid another 5 pages in this POV on why IMO this is being criminally suppressed by federal agencies:
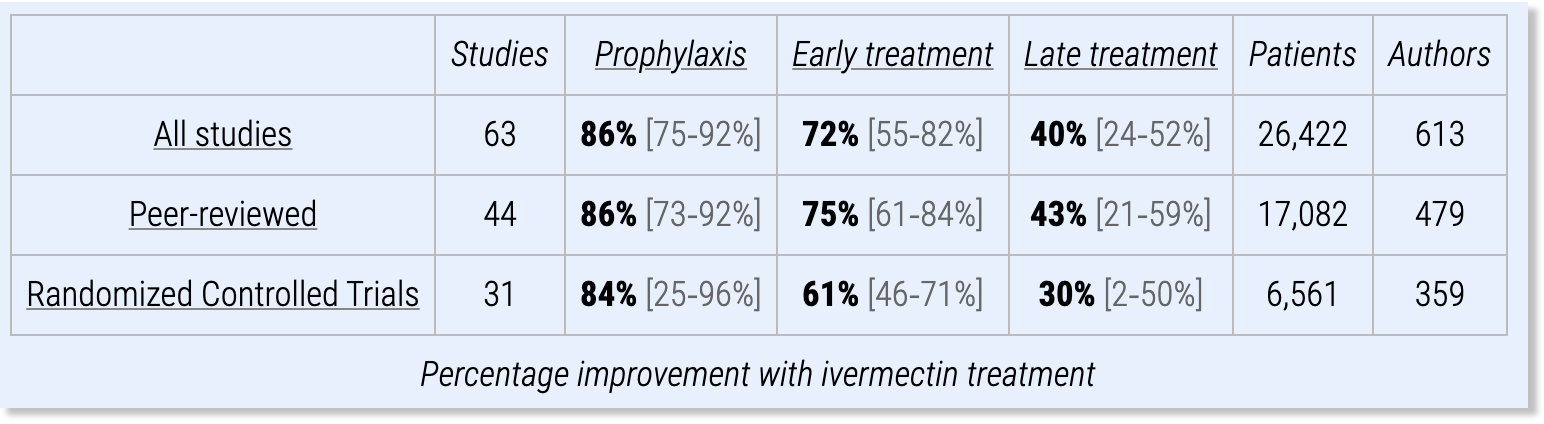
First, Ivermectin (links to the studies: (Link A & Link B)). Summary table as follows:
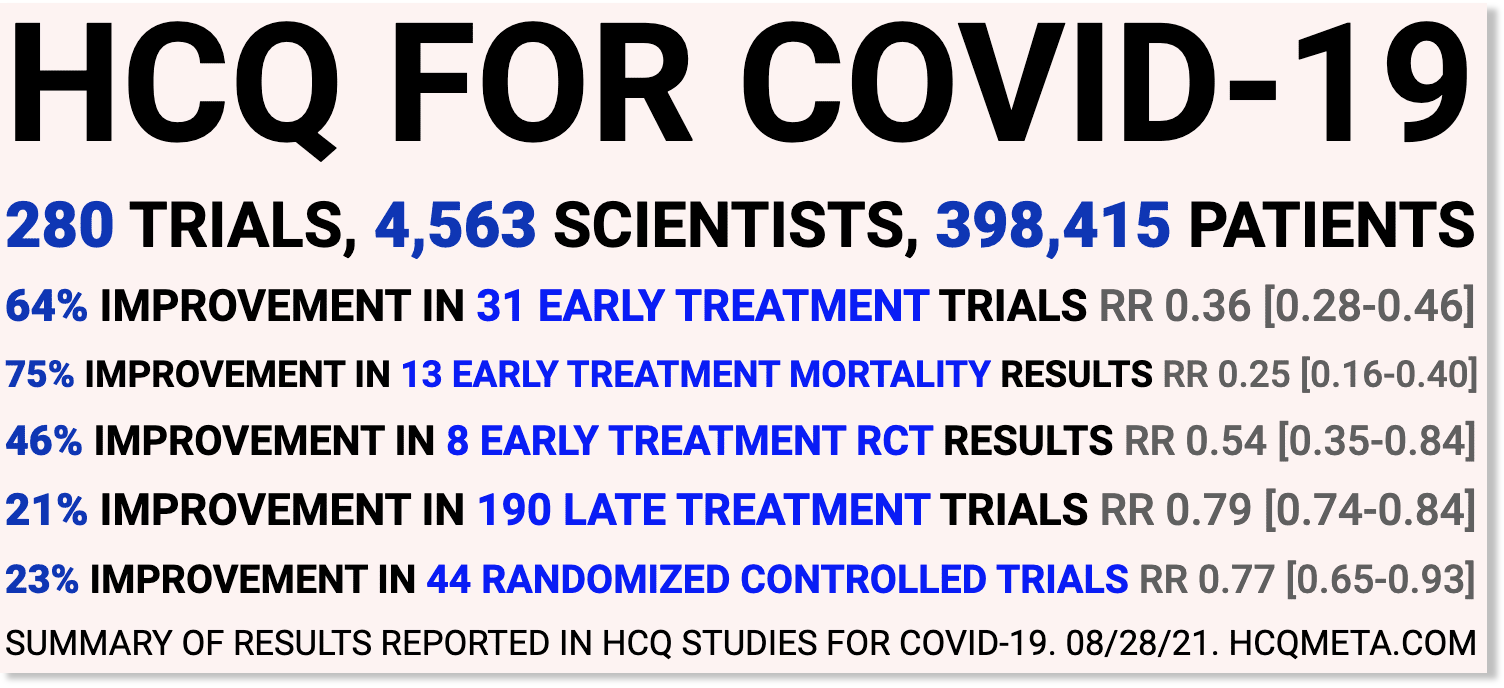
Second, Hydroxychloroquine (link to the studies). Summary table as follows:
By the way, it is worth noting I have a friend right now who has COVID-19. He has felt like shit for the past week. I sent him the studies, and he bought Ivermectin 3 days ago without a prescription from a local store I pointed him to. After a week of feeling like shit, it took him less than a day to get close to symptom free. But hey, I am not a doctor, and “your mileage may vary.” There are a dozen other treatments in addition to the ones above that aren’t getting approved for mass application, either. Go figure.. I could send you the studies if you want, but anyways let’s move on.
(2) As it pertains to the proactive side — okay, sit tight because I’m going to perform a holy miracle here and give you one of several simple things you can do to essentially ensure never needing to worry about COVID-19 again. Not for you, not for the kids, and not even for the neighbor’s dog. Ready? Okay drumroll please… . Did you catch that? If you didn’t, I’ll decipher it for you. It’s your new friend Vitamin D.
If you’d like dozens more studies on this subject, let me know, but start with this good summary I just found for you here — it’s worth a full read, but two pretty charts from the link sum it up:
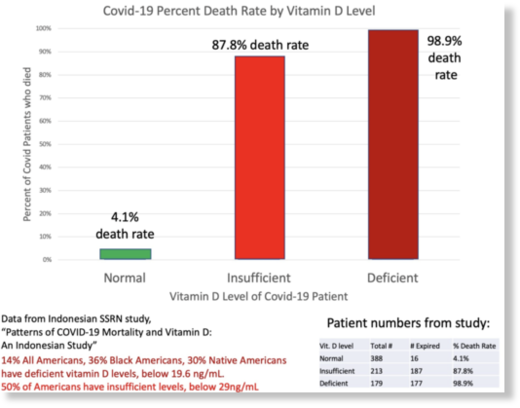
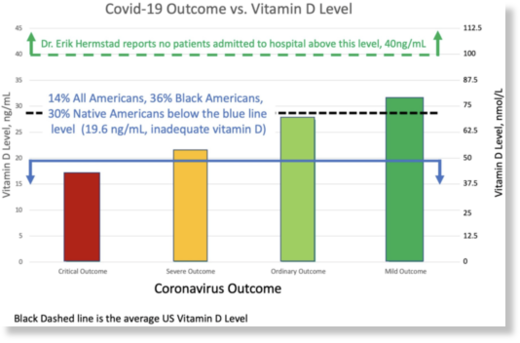
The first study is striking all on its own and worth internalizing, but unfortunately it did group an entire category called “normal” into a single bucket. FYI “normal” is what the medical world considers to be ~20ng/mL. But that’s all it is as a level: normal… but far from what we want, which is excellent.
That’s where the second study becomes helpful. It puts the explosive nature of the findings into real perspective: at levels of 25ng/mL in the study, no severe or critical hospitalized outcomes were observed. While at levels of 40ng/mL or greater, there were not even hospitalizations.
Now personally, I regard it as nothing less than a crime against humanity that neither the WHO nor CDC are PUSHING these (and dozens other peer-reviewed studies on the subject) onto the forefront of our collective media screens. But as for the reason, I must digress, because again I could go down a long and nasty rabbit hole about perverted incentives in the system in terms of why you likely haven’t seen them.
In any case, here’s what is just so awesome for me… remember when we concluded I had a higher risk of crashing & dying from my trip to the local ice cream shop than from COVID-19? Well, it just got a WHOLE lot better, because my Vitamin D levels happen to be considerably well above 40ng/mL. Which means we need to be honest with ourselves and admit that I effectively have a ZERO clinically observed risk of death from COVID-19. I mean shit…. at this point really the only way I can die of COVID-19 is by having it and then getting into a car accident. Then sure, I will die “with COVID-19” (and, as you’ll recall from the link above, they would count it!).
So my advice is as follows: get your dang sunshine first thing in the morning. Do not lockdown. In fact, I’d argue it’s what caused so many deaths. People were heavily Vitamin D deficient from sitting at home all day, and it literally increased their risk of death instead of reducing it. And what the CDC did in this regard was at best negligently or at worst intentionally, criminal, and I have nothing but disdain for the way they went about that. Don’t even get me started on the youth suicides it led to, the increases in domestic violence, increases in drug overdoses, infanticide, denial of healthcare, and let’s not dismiss the whammy of the sheer economic devastation to jobs and small businesses the world over, the bleak economic prognosis for the poorest (how convenient), and the future impact of staggering U.S. debt right here at home. All caused by the incompetence or criminality of the CDC and WHO.
Honestly — my personal advice if you want to stop worrying about COVID-19 for the rest of your life (if you still even are), would be to follow the Dan Miller protocol. Each of his bits of advice is like an extra layer of bulletproof glass on top of Kevlar against COVID-19. And remind your colleagues, too, to stop relying on the “American way” of taking a pill to solve all their problems and blaming the unvaccinated. That is not only completely debunked now as I’ve demonstrated throughout, but it is weak morally. It’s high time we all do the hard self-work of making ourselves physically resilient, and stop feebly making outward demands of others to inject into their bodies vaccines that are only now being tested, in vivo, on large numbers of human beings.
Speaking of which… perfect segway.
===================
(VERY BRIEFLY) PART 2: LONG-TERM RISKS OF [SPECIFICALLY] THE COVID-19 VACCINE –> HIGH
As I’m sure you’ll remember, a while back I mentioned I would send you a thorough, synthesized summary outlining the dangers of the COVID-19 vaccines and how the risks they carry far outweigh the risks of the virus itself. Unfortunately, I am not even a fraction of the way through the hundred plus pages of medical literature showing that conclusion — I’m still working through it. I absolutely feel terrible for not having lived up to my promise, though I’m sure you can appreciate the sheer herculean nature of synthesizing 7 months’ of research involving almost a thousand individual pieces of data, and weeks’ worth of video testimonials by researchers, all into something “succinct and digestible”, all the while working on [my company] in the middle of it all.
In any case, it would be disingenuous of me if I didn’t at least provide a sneak peak of a random assortment of links I had handy for why I will not get the vaccine (aside from the fact that COVID-19 poses no risk to me, per the first section):
- Imperfect Vaccination Can Enhance the Transmission of Highly Virulent Pathogens (bad for me, terrible for society; moral obligation not to partake in this)
- Is a Coronavirus Vaccine a Ticking Time Bomb? (Spoiler alert: likely is)
- A Pathologist Summary of What These Jabs do to the Brain & Other Organs
- Might COVID Injections Reduce Lifespan?
- MIT & International Journal of Vaccine Theory, Practice and Research: Worse Than the Disease? Reviewing Some Possible Unintended Consequences of the mRNA Vaccines Against COVID-19
- How COVID-19 Vaccine Can Destroy Your Immune System
- The Inanity of RNA Vaccines For COVID-19
- New Report Sheds Light on Vaccine Doomsday Cult (sketchy website, but well explained content. I suppose even a broken clock can be right twice a day…)
- Children 50 TIMES More Likely to Die from Covid Vaccine Than From Virus (from the former CSO of Pfizer)
- Pfizer vaccine in Israel: Mortality rate ‘hundreds of times greater in vaccinated young people’
- Are COVID shots fueling more dangerous mutations?
- Less than a third of delta variant deaths are in the unvaccinated (not really an article regarding vaccine dangers, but more so inefficacy)
- +1,000 additional articles, papers, studies, you name it that I could send anyone that wants the full dump of ’em (unsynthesized, of course)
Some bonus links in your spare time that caught my eye in just the past week:
- Fun Quick Video: Mt. Vernon, IN School Board Meeting (though he got a couple things wrong, some points are good food for thought)
- Podcast: The High Wire — A Sea of Lies (in depth discussion about perverse incentives driving bad decisions by the CDC (particularly the second half of the video))
- Podcast: Objective:Health – Study on the Adverse Effects of the Pfizer Vaccine (in which the presenters discuss a paper by the same name).
- Short & Sweet: Why non-lethal pressure on the virus is bad (versus natural immunity) -> Part 1 | Part 2
- +100 more videos and podcasts on the subject to anyone who asks (unsynthesized, of course)
===================
CLOSING THOUGHTS
If you made it this far and checked out even any of the content, kudos. Most folks here in the Northeast stop listening to me once I say “hey, there’s something not right here in this data” or “I’m not too worried about COVID-19 personally”. They think I’m a nut. Now, if you’ve made it this far and checked out most of the content, then I already know you’re starting to wonder if you’re losing your mind, because boy do I have a club pass with your name on it, if you’d like one.
Alas, contrary to popular belief it’s far from a nut club, despite how strong the external pressure is these days to try to make it out to be the case. Rather, It’s a club filled with precisely the very people who we’re supposed to be listening to as a society:
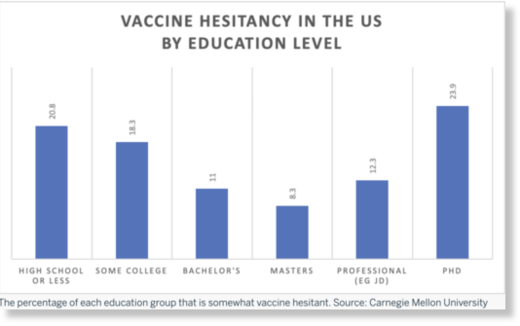
Source: https://www.medrxiv.org/content/10.1101/2021.07.20.21260795v1.full.pdf
AKA: a twisted rendition of the Dunning-Kruger effect in action
The CDC would have you believing it is just the crazy and uneducated who are most wary of their (and the FDA/WHO’s) conclusions — you know, it’s all the rednecks down south! And they’re right, it is the uneducated (left of the chart). But it is disingenuous for them to try and ignore on the nightly news research like this out of Carnegie Mellon suggesting the biggest group of those most vaccine-hesitant happen to be the smartest folks in the world — the ones I’ve certainly not been ignoring, despite their being shamed, cancelled off of social media, and publicly silenced.
Put another way, I would only posit the simple question of when in the history of the world have you ever had thousands of scientists, doctors, and researchers, some of the brightest minds* in their fields around the world sounding an alarm, and the official response be to label them all as batshit crazy and prevent them from speaking? Hint. Personally, I can’t support it. A free society must allow all open discussion without ridicule well before we dare discuss collectively forcing medical decisions on people using actual threats against their autonomy. We’re too far past that Vietnam-level of government lying bullshit that results in unholy suffering for society for this barbaric nonsense to continue, and it’s time for this country to start acting like we learned something about the importance of asking questions. I simply cannot place any trust in the idea I’m not being lied to until every scientist worth their salt has had an opportunity to speak up freely, and the nature of their concerns investigated transparently. And neither should anyone else.
*Such a fun fact it is that among this ocean of scientist voices being smeared & erased from history are (1) the guy who helped invent mRNA vaccine technology, and (2) the former Chief Scientific Officer (CSO) of Pfizer (who held that role for 16 years and focused on respiratory illnesses), both of whom are saying we have to stop vaccinations at once for those who aren’t at actual high-risk with COVID, because for everyone else they’re not only toxic & dangerous but will be the very cause of this never ending pandemic. Now I don’t know about you, but I neither invented mRNA technology nor worked at Pfizer for 16 years as CSO, but if I did, I’d sure prefer the American people heard my concerns, you know, sans the childish smear tactics part. Until then, I will not — cannot — accept any mandates on moral grounds.
And so there you have it. My opinion on mandatory vaccinations at this stage: if this were the Bubonic Plague, I’d be the first in line to get the shot. Same for Polio, Tetanus, and a whole lotta other great vaccines. But for COVID-19? Let’s just say I wouldn’t even know what to tell Saint Peter at the Pearly Gates to apologize sufficiently if I — knowing what I know now — supported a mandate. Come to think of it, there’s a quote that comes to mind here that I think is a nice way to wrap up this write-up, and commemorate those who continue to protect the rights of society:
‘The hottest places in Hell are reserved for those, who in time of moral crisis, preserve their neutrality.’ ~ unknown
========
DISCLAIMER –> OBLIGATORY
I obviously have to say this before I sign off.
At the end of the day, I’m not a doctor, I do not have an MD, a Ph.D., or any other useful acronym. All I am is an individual who values truth above hysteria & ideology. I will go wherever the truth points me to without regard for what “side” that puts me on. If it’s a contrarian side, then shit I guess I’m going to have to get in some fights. If I’m on the side of the majority, I guess I’ll rest easy. But wherever it is, I’m willing to go there, and as I said in my opening statement and reiterated to the group — I will always remain open to thoughtful and productive dialogue and my POV on every topic is subject to change through lifelong reflection. All I ask for these days is for those who disagree with me to either have the sincerity to work with me using the scientific method to get the facts on this subject, or if they have no interest in that, to let me do it alone without the constant coercion, which is how I’m sure the folks in your office who are unvaccinated, feel.
Anyways, for the actual disclaimer part: we all have to make our own decisions, do our own research (though I’m always happy to keep sending stuff I come across), and take our own risks. Freak accidents can happen, and just like I wouldn’t want to be responsible for a car accident that happens if you decide to go to a particular ice cream shop I recommend, it is the same for anything I’ve sent above and anything you or anyone you may share any of the information with do as a result of it. Always seek and follow professional, accredited advice! <– the disclaimer part.
Anyone who sees the vaccine as having more benefit than risk, should absolutely take it. I agree 100% with an 85 year-old with five comorbidities getting the jab — shit if that was me, I’d be getting quadruple jabbed walking around with a gas mask. No really, I would. Because for them the virus is actually very dangerous. And I’ve recommended it for some that I know personally would benefit from the vaccine because they are at high risk. But that’s where it ends. And not a single, inch, further.
VACCINATION: THEY’RE BECOMING DESPERATE
Computing Forever | August 21, 2021
Support my work here: https://computingforever.com/donate/
Support my work on Subscribe Star: https://www.subscribestar.com/dave-cullen
Follow me on Bitchute: https://www.bitchute.com/channel/hybM74uIHJKf/
Buy How is This a Thing Mugs here: https://teespring.com/stores/computing-forever-store
Source links:
https://www.irishmirror.ie/news/irish-news/irish-community-mourning-tributes-paid-24786114
https://www.which.co.uk/news/2021/08/travel-croatia-austria-vaccine-expiry-booster/
http://www.computingforever.com
KEEP UP ON SOCIAL MEDIA:
Gab: https://gab.ai/DaveCullen
Subscribe on Gab TV: https://tv.gab.com/channel/DaveCullen
Minds.com: https://www.minds.com/davecullen
Subscribe on Odysee: https://odysee.com/@ComputingForever
Revealed, the vaccine safety alert that drugs watchdog is ignoring
By Sally Beck | TCW Defending Freedom | September 1, 2021
FOR nearly a decade, Dr Tess Lawrie, MBBCh, DFSRH, PhD, has run the Evidence-Based Medicine Consultancy, an independent company concerned with rigorous medical research in healthcare.
She produces reports that can be found in the Cochrane Library, a respected organisation providing unbiased scientific paper analyses.
Dr Lawrie is a frequent member of technical teams developing international guidelines in the healthcare sector, and her peer-reviewed publications have received more than 3,000 citations. In short, Dr Lawrie should not be ignored.
Unless of course you are the Medicines and Healthcare products Regulatory Agency, the deaf-eared UK body regulating the novel, experimental, and under-tested Covid-19 mRNA and traditional vaccines.
With vaccine-associated deaths passing 1,600 in Britain, the MHRA should suspend the vaccination programme, like it did after 47 deaths caused by the Pandemrix swine flu jab.
However, it has no intention of doing so and continues to insist that the vaccine is ‘safe and effective and the best protection against Covid-19’.
Dr Lawrie sent Dr June Raine, the MHRA’s chief executive, a 39-page, fully-referenced paper criticising the agency’s complicated Yellow Card Scheme, a government system designed to collate information about adverse events caused by new drugs, as ‘not fit for purpose.’
She reminded Dr Raine, and copied in 15 of her colleagues, that they had a duty to ‘take any necessary action to minimise risk to individuals, after weighing risks against expected benefits.’ She pointed out that because of omissions in their data collecting, such as age and gender, and the timeframe of reaction post vaccination, the Yellow Card Scheme is non-transparent.
She said: ‘These omissions mean that basic conclusions about safety cannot be drawn. Consequently, the public and trial participants are not fully informed of the potential risks of taking a Covid-19 vaccine and are unable to give fully informed consent.’
Dr Lawrie concluded that the voluntary reporting system needed a complete overhaul, saying the Vaccine Adverse Event Reporting System (VAERS) in the US was doing a much better job giving citizens and healthcare professionals detailed information.
From VAERS’ database, she was able to conclude that more than 90 per cent of deaths occurred afterfirst vaccination and there was a clear link between vaccination and death, something MHRA members frequently say they cannot prove and insist is more than likely ‘coincidental’.
Speaking of VAERS, Dr Lawrie said: ‘From that system it is apparent that sporadic event reporting is high in number, as in the UK, and that there is a tight temporal relationship between Covid-19 vaccination and deaths: 15 per cent of deaths occurring within 24 hours, 22 per cent within 48 hours and in 37 per cent of deaths, the patient became unwell within 48 hours of Covid-19 vaccination with an event that led to their death.
‘The deaths analysed followed an almost equal number of Pfizer and Moderna Covid-19 vaccinations, and 91 per cent of deaths occurred after administration of the first Covid-19 vaccine.’
With the AstraZeneca #clotshot, which has not been approved for use in the US, double the number of people are impacted compared with Pfizer.
Dr Lawrie said that, as well as vaccine-induced immune thrombotic thrombocytopaenia (VITT), the European Medicines Agency has identified Guillain-Barreì Syndrome as a potential risk from the AstraZeneca vaccine.
It is adding a warning to the product information that ‘vaccinated persons need to seek immediate medical attention if they develop weakness and paralysis in the extremities.’
In conclusion, Dr Lawrie asked Dr Raine a simple question, yet to be answered: ‘Why is this clear safety signal not being acted upon by MHRA?’
This is an updated report published on August 26, 2021, detailing MHRA Yellow Card Reporting up to August 18:
• Pfizer – 21.3million people, 37.9million doses. Yellow Card reporting rate, one in 199 impacted.
• AstraZeneca – 24.8million people, 48.7million doses. Yellow Card reporting rate, one in 108 impacted.
• Moderna – 1.4million people, 2.1million doses. Yellow Card reporting rate, one in 100 impacted.
Overall, one in 135 people experience a Yellow Card Adverse Event from the 47.5million injected (20.7million men, women and children remain not injected in UK).
The Yellow Card reporting rate may be approximately ten per cent of actual figures, according to MHRA.
Proportional to the number of weeks each brand has been administered, currently the reported toll is:
• Approximately 47 linked deaths reported per week
• More than 10,500 reported adverse event injuries per week with unknown long-term consequences.
A significant proportion of these adverse events require urgent medical care, may be life-changing or long-lasting. These figures represent immense distress for those 351,404 people suffering adverse events and their families.
Reactions: 302,146 (Pfizer) + 816,393 (AZ) + 43,949 (Moderna) + 3,148 (Unknown) = 1,165,636.
Reports: 107,215 (Pfizer) + 229,134 (AZ) + 14,019 (Moderna) + 1,036 (Unknown) = 351,404.
Fatal: 508 (Pfizer) + 1,056 (AZ) + 17 (Moderna) + 28 (Unknown) = 1,609.
Acute Cardiac: 4,831 (Pfizer) + 9,102 (AZ) + 495 (Moderna) + 35 (Unknown) = 14,463.
Pericarditis/Myocarditis (Heart inflammation): 362 (Pfizer) + 245 (AZ) + 65 (Moderna) + 2 (Unknown) = 674
Anaphylaxis: 466 (Pfizer) + 810 (AZ) + 32 (Moderna) + 1 (Unknown) = 1,309
Blood Disorders: 10,283 (Pfizer) + 7,354 (AZ) + 829 (Moderna) + 44 (Unknown) = 18,510.
Infections: 7,116 (Pfizer) + 18,102 (AZ) + 730 (Moderna) + 89 (Unknown) = 26,037
Herpes: 1,574 (Pfizer) + 2,475 (AZ) + 75 (Moderna) + 13 (Unknown) = 4,137.
Headaches: 21,646 (Pfizer) + 83,513 (AZ) + 2576 (Moderna) + 229 (Unknown) = 107,964
Migraine: 2,474 (Pfizer) + 8,015 (AZ) + 284 (Moderna) + 29 (Unknown) = 10,802.
Eye Disorders: 5,025 (Pfizer) + 13,718 (AZ) + 495 (Moderna) + 55 (Unknown) = 19,293.
Blindness: 99 (Pfizer) + 281 (AZ) + 12 (Moderna) + 4 (Unknown) = 396.
Deafness: 185 (Pfizer) + 360 (AZ) + 13 (Moderna) + 2 (Unknown) = 560.
Psychiatric Disorders: 6,135 (Pfizer) + 17,011 (AZ) + 884 (Moderna) + 74 (Unknown) = 24,104.
Skin Disorders: 21,263 (Pfizer) + 50,240 (AZ) + 6,657 (Moderna) + 211 (Unknown) = 78,371.
Spontaneous Miscarriages: 278 + 6 stillbirth/foetal death (Pfizer) + 195 + 2 stillbirth (AZ) + 24 + 1 foetal death (Moderna) + 1 (Unknown) = 499 + 9 (figures imply 20 related maternal deaths – four more this week alone).
Vomiting: 3,242 (Pfizer) + 11,347 (AZ) + 496 (Moderna) + 41 (Unknown) = 15,126.
Facial Paralysis including Bell’s Palsy: 691 (Pfizer) + 860 (AZ) + 48 (Moderna) + 5 (Unknown) = 1,604.
Nervous System Disorders: 52,947 (Pfizer) + 173,935 (AZ) + 6788 (Moderna) + 600 (Unknown) = 234,270.
Strokes and CNS haemorrhages: 496 (Pfizer) + 1,993 (AZ) + 17 (Moderna) + 9 (Unknown) = 2,515
Guillain-Barré Syndrome: 42 (Pfizer) + 388 (AZ) + 2 (Moderna) + 5 (Unknown) = 437.
Tremor: 1,288 (Pfizer) + 9673 (AZ) + 153 (Moderna) + 38 (Unknown) = 11,152.
Pulmonary Embolism and Deep Vein Thrombosis: 601 (Pfizer) + 2,696 (AZ) + 25 (Moderna) + 18 (Unknown) = 3,340.
Respiratory Disorders: 12,950 (Pfizer) + 27,425 (AZ) + 1,138 (Moderna) + 109 (Unknown) = 41,622.
Seizures: 713 (Pfizer) + 1,874 (AZ) + 119 (Moderna) + 9 (Unknown) = 2715
Paralysis: 301 (Pfizer) + 735 (AZ) + 39 (Moderna) + 6 (Unknown) = 1,081.
Haemorrhage (All types): 2,568 (Pfizer) + 4713 (AZ) + 321 (Moderna) + 24 (Unknown) = 7,626.
Vertigo/Tinnitus: 2,692 (Pfizer) + 6313 (AZ) + 271 (Moderna) + 25 (Unknown) = 9,301.
Renal & Urinary Disorders: 795 (Pfizer) + 2,507 (AZ) + 93 (Moderna) + 23 (Unknown) = 3,418
Reproductive/Breast: 17,108 (Pfizer) + 16,689 (AZ) + 2,215 (Moderna) + 120 (Unknown) = 36,132.
For full reports see Annex One.
Where Are the Autopsies of People Dying Post COVID Vaccine?
By Dr. Joseph Mercola | August 31, 2021
Dr. Jane Orient, executive director of the Association of American Physicians and Surgeons, published a commentary July 7, 20211 asking an important question about the rising number of deaths being reported to the U.S. Vaccine Adverse Events Reporting System (VAERS) in conjunction with the COVID-19 injection program.
Her credentials2 are many: She’s a clinical lecturer in medicine at the University of Arizona College of Medicine. She received her medical degree from Columbia University and is the author of several books. And, as president of Doctors for Disaster Preparedness and chairman of the Public Health Committee of the Pima County (Arizona) Medical Society, she asks: Why haven’t there been autopsies of healthy people who are dying unexpectedly after receiving a COVID jab?
It’s a reasonable and logical question since autopsies often reveal important information about diseases and illnesses — and it’s information that can help guide future medical treatment to reduce the risk of long-term disability and death after the vaccine.3 After all, without autopsy results, the ability to treat cardiovascular diseases,4 cancers,5 hereditary diseases like hypertrophic cardiomyopathy6 and even catch murderers7 would be incompetent.
Dr. Dylan Miller chairs the autopsy resource committee for the College of American Pathologists. He spoke with a reporter from The Wall Street Journal, saying,8 “We think we always know what’s going on inside our patients, but that’s a fallacy. There’s as much to be gained from an autopsy as ever.”
The nature of an autopsy is diagnosis.9 It can help family members come to terms with what caused a loved one’s death, identify unknown diseases and offer clinicians an opportunity for a greater understanding of what happened before a patient dies. It also can provide a valuable educational opportunity for health officials and even students, who study disease processes.
It’s been over eight months since the first COVID-19 vaccine was administered in the U.S. in December 2020.10 Since then, VAERS reports show there have been over 12,000 people who have died after the shot.11 Since autopsies are so incredibly important in the identification of disease and pathological processes, why haven’t healthy people who have died after the COVID jab been autopsied?
Lack of Autopsy Results May Mean Data Are Hidden
At the time of Orient’s published commentary,12 she quoted a death toll after the COVID shot of nearly 7,000 people as reported in VAERS. This was in early July. By the end of July that number had risen to 12,366 people.13 That’s a jump of over 5,000 people in less than 30 days who reportedly had died after the COVID injections.
Orient comments that while it’s the best system available now for recording adverse events from vaccines, VAERS is likely missing 90% or more of the actual number of individuals who are hospitalized, have suffered anaphylactic reactions, have Bell’s Palsy, had heart attacks or had life-threatening reactions. The lack of accurate recording also includes the actual number of people who have died after receiving an injection.
When it comes to death certificates, data from The Johns Hopkins Hospital were published in the Archives of Internal Medicine in 2001,14 demonstrating that the accuracy and reliability of the recorded cause of death, on death certificates, was a significant problem, indicating the continued need for autopsies to correctly identify the cause of death.
According to Orient, the death of a 45-year-old mother after receiving the COVID-19 shot that was required for her to start work at the same institution, Johns Hopkins University, will likely not be investigated by autopsy. Additionally, the hospital has not paused their demand for the injection program for mothers and potential mothers who want to work at the university.
In the past, when an individual died without significant medical illness, they were designated a case for the medical examiner, who would decide whether an autopsy was needed. Any evidence that was related to the death was gathered and considered along with the autopsy report.
The most important reason for requesting and performing an autopsy was to ensure quality health care and at one time was required for hospital accreditation.15 However, that requirement has been dropped, and dropped along with it the number of autopsies routinely performed on patients who have died inside or outside the hospital.
The average rate for autopsies in the 1940s was 50%. That dropped to 41% in 1970, just before the Joint Commission on Accreditation of Hospitals removed the requirement that 20% of deaths in the hospital were to be autopsied to maintain accreditation.16
By 2018, experts estimated only 4% of in-hospital deaths were autopsied and only approximately 8% of all deaths. Since an estimated 700,000 die each year in the hospital, this means only approximately 28,000 of those deaths are autopsied. Experts have proposed three explanations for the falling rates, including:17
- Fear of finding mistakes leading to a malpractice lawsuit
- Lack of reimbursement for an autopsy
- The belief that medical technology has made autopsies obsolete
However, it’s important to note that knowledge of why a person dies after vaccination will not help the family recover damages since the pharmaceutical industry is immune from liability.18,19 Even so, this information should be used to inform public health policy and help people decide how they want to proceed with the genetic therapy injection program.
Death Certificates Are Notoriously Inaccurate
Orient also notes that death certificates, which researchers use to gather statistics on the cause of death, “are known to be extremely unreliable.”20 An evaluation of 494 death certificates at The Johns Hopkins Medical Institutions21 in 2001 showed 41% had improperly completed forms and the reliability and accuracy of the death certificates listing cause of death was a significant problem.
A study published in the Southern Medical Journal22 also found “major discrepancies” between the death certificates issued in the hospital and the information gathered on autopsy.
In 25% of the cases, the death was erroneously attributed to acute myocardial infarction, while an autopsy showed the deaths were actually from sepsis, cerebral hemorrhage, pneumonia and cardiac tamponade. Autopsy showed there were 52 myocardial infarctions that caused death, but death certificates accurately documented only 27. The researchers concluded:
“1) Death certificates are often wrong. 2) The time-honored autopsy is more valuable than ever. 3) Physicians need to write better death certificates and correct them. 4) Death certificate-based vital statistics should be corrected with autopsy results. 5) Vital statistics should note deaths confirmed by autopsy. 6) More autopsies would improve vital statistics and the practice of medicine.”
According to the Centers for Disease Control and Prevention’s document on understanding death data quality, hospitals and health care providers should use the following criteria when filling out cause of death on a patient’s death certificate:23
“When a person dies, the cause of death is determined by the certifier — the physician, medical examiner, or coroner who reports it on the death certificate.
Certifiers are asked to use their best medical judgment based on the available information and their expertise. When a definitive diagnosis cannot be made, but the circumstances are compelling within a reasonable degree of certainty, certifiers may include the terms “probable” or “presumed” in the cause-of-death statement.”
In other words, data being reported about cause of death can be manipulated with a “probable” or “presumed” assumption if the certifier makes a subjective evaluation and believes the “circumstances are compelling.” This poor degree of accuracy only adds to the already notoriously inaccurate information found on death certificates.
Treatment for COVID-19 Improved After Autopsy Results
As Orient points out, there were tens of thousands of patients who died from COVID disease after being placed on ventilators before a small series of 12 autopsies done in Germany showed that most of these patients had blood clots and using a ventilator may have caused more damage.24
The improvement and treatment modalities for COVID-19 came after patients had been autopsied. Mechanical ventilation can easily damage lung tissue because it forces air into the lungs. Patients with COVID-19 who were ventilated had at best a 50-50 chance of surviving.25
However, risk analysis being reported indicated this chance of survival was higher than what was being seen clinically. China reported26 of 22 patients on ventilators, 86% of them did not survive the treatment. A British study found two thirds of patients on mechanical ventilation died and a study of 320 mechanically ventilated patients in New York showed 88% of them died. … Full article
Sources and References
- 1, 12, 20 WND, July 7, 2021
- 2 The Heartland Institute
- 3 Academic Pathology, 2019;6: 2374289519834041
- 4 Human Pathology, 1998;28(12)
- 5 Cancers, 2021;13(3)
- 6, 8 Wall Street Journal, March 9, 2015
- 7 Dallas Morning News, April 23, 2018
- 9 Yale School of Medicine, Pathology: Reason for an Autopsy
- 10 BBC, December 14, 2020
- 11 OpenVAERS
- 13 OpenVAERS, July 30, 2021
- 14, 21 Archives of Internal Medicine, 2001;161(2)
- 15 American Society for Clinical Pathology
- 16, 17 Circulation 2018;137:2686
- 18 PHE.gov, Public Readiness and Emergency Preparedness Act
- 19 CNBC, December 17, 2020
- 22 Southern Medical Journal, 2006;99(7)
- 23 Centers for Disease Control and Prevention, Understanding Death Data Quality
- 24 University of Minnesota May 7, 2020
- 25, 26 Reuters, April 23, 2020
U.S. Government Stats on COVID Vaccines: 13,627 Deaths 2,826,646 Injuries 1,429 Fetal Deaths
By Brian Shilhavy | Health Impact News | August 30, 2021
According to the most recent stats released by the CDC this past Friday, August 27, 2021, their Vaccine Adverse Event Reporting System (VAERS) now has recorded more than twice as many deaths following COVID-19 shots during the past 8 and a half months, than deaths recorded following ALL vaccines for the past 30 years.
This has to be the most censored information in the U.S. right now, even though these statistics come directly from official government statistics.
They have now recorded 13,627 deaths, 2,826,646 injuries, and 1,429 fetal deaths from pregnant women who took a COVID shot.
They also report 17,794 permanent disabilities, 74,369 emergency room visits, 55,821 hospitalizations, and 14,104 life threatening events. (Source.)
And all of this has happened in just over 8 months.
From January 1, 1991 to November 30, 2020, the last month before the COVID shots were given emergency use authorization, there were only a total of 6,068 deaths recorded (mostly infant babies) following ALL vaccines. (Source.)
Featured Video

Seyed M. Marandi: US-Iran War Inevitable: Kuwait and Bahrain May Fall
or go to
Aletho News Archives – Video-Images
From the Archives
Oil and the Israel Lobby
Reknowned economist M. Shahid Alam offers this excellent critique of Noam Chomsky’s defective analysis of the relative influence of Oil versus the Israel lobby over US foreign policy: … continue
Blog Roll
 Aletho News
- ICC ignored ‘very well-documented’ NATO crimes – ex-Libyan minister
- SNSC secretary dismisses US response to Iran’s conditions as ‘inadequate’
- Sanaa says Taiz roads open, secure for residents, warns Saudi forces
- Iraqi resistance group urges Saudi leadership to admit defeat, lift Yemen siege
- Trump’s Retreat: How Al-Aqsa Flood Took Down the US Empire
- Israel’s Military Actions in Lebanon Grossly Violate International Law — Lavrov
- Seyed M. Marandi: US-Iran War Inevitable: Kuwait and Bahrain May Fall
- Leaders Condemn Ansarallah Attack on Saudi Arabia While Ignoring Illegal War Against Yemen
- Leaked: Britain’s Covert Iraqi Psyops Network
- Yemeni Armed Forces Warn Airlines Against Using Saudi Airports, Exempt Mecca and Medina
- If Americans Knew
- How Israel Conquered the Latin American Right
- Agents search Rep. Omar’s Washington home in criminal probe as she vows she won’t ‘be silenced’
- “The Rule Was: ‘Shoot Everyone You See'”
- Israel goes ballistic over Nobel Laureate Navi Pillay
- U.S. May Join Yet Another Middle Eastern War — TCN
- Yellow Line moves again as Israel closes in on trapped Gazans – Daily Update
- Israeli Attacks Kill Seven Palestinians in Gaza Including Six-year-old Girl
- Gaza: Ceasefire Anniversary Marks Year of Failed Promises
- The American Conservative: Mike Huckabee Should Resign
- A C-Section in Shackles: A Palestinian Woman’s Harrowing Birth in Israeli Detention
- No Tricks Zone
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI

