The last time tony fauci was pushing masks for disease mitigation he was making up his facts and scare mongering too
el gato malo – bad cattitude – december 6, 2021
many of you are probably too young to remember the AIDS panic of the 80’s.
but when it came out, the NIH, with tony fauci leading the charge, was getting literally everything wrong.
they pushed a narrative of fear, vilified the infected, interfered with the development and adoption of effective treatments, and completely misrepresented spread and mitigation.
it’s how we wound up with absolute garbage like this ad:

it’s probably pretty jarring to see, but this is because you now have perspective. at the time, A LOT of people believed this. fear of getting AIDS from public toilet seats was a very real thing. fear of getting AIDS from casual contact or sharing dining or cooking facilities was a very real thing. people worried they might be sitting near a gay person on a bus. the “moral majority” of dingbat tele-evangelists thundered about it daily.
and then, as now, one jumped up bureaucrat with no idea what he was talking about was running around like chicken little screaming of falling skies and grandstanding about non-existent risks to children.
the fact that it was literally the same guy who is still at it should deeply embarrass us all.
i urge you to watch the video and hear him, in his own words. because this is who tony fauci was, and he has not gotten better. he’s just become more powerful and more nastily manipulative and narcissistic.

the appalling inaccuracy and vicious othering of the AIDS campaign is still his bread and butter play. it’s what tony does. only the scale and scope of power has changed.
one day, 20 years from now, people will look back on these rushed and slipshod vaccine approvals and mandates for products that are not at all suited to task and claims about masks and lockdowns and feel sick to their stomachs.
they will not be able to believe how such pseudoscience and rapacious world wrecking doctrine not only got foisted upon the world, but accepted and cheer led by it.
they will, in the light of perspective, marvel that the same man who convinced us that our kids would get AIDS from being near a gay teacher was allowed to generate pretext to close the schools to “protect” children from a disease that poses them almost no risk, a disease they do not contract nor spread serious cases of.
they will be appalled by the suggestion that a non-sterilizing vaccine was forced on them even after the fact that the vaccine does not mitigate spread was known and despite a towering and dangerous adverse events profile that rendered it a clearly of negative benefit to cost proposition to the young and healthy.
in short, they’ll feel just like you probably did looking at that AIDS ad.
think very carefully about just who you are choosing to trust here.
these “experts” do not have track records of being correct or even of being honest.
check the date on this:

they told you not only that these vaccines would stop spread, but that they literally changed the definition of “herd immunity” so that it could ONLY be achieved by vaccines.
then the vaccines failed to stop spread, likely made it worse, and they doubled down on “you need to get vaxxed” in spite of this, pivoting to this bizarre new take of “you need to get vaxxed to save hospital space” which, of course, is ALSO not working. now they want boosters. soon it will be “variant boosters.” if you don’t think annual covid shots are coming, you probably fell for the “did you know the word gullible is not in the dictionary?” trick. twice.
this is not “changing your views when new facts arise” this is “finding new justifications for doing the same thing despite the facts being 180 degrees opposite to what you claimed.”
this is not science, it’s scientology.
it’s the same people making the same mess.
isn’t it about time we broke this cycle?
food for thought.
Nobody can explain why the vaccinated are more likely to get COVID and die
By Steve Kirsch | December 5, 2021
ICYMI, here’s a chart from a recent post by my good friend Mathew Crawford. It basically shows, the more you vaccinate, the more cases and deaths you get.

Critics would argue, “it’s confounded! more elderly are vaccinated.” But the same critics cannot show us this is false. They can only do “hand-waving” arguments that it must be wrong. Not very convincing.
Governments won’t release the data to show vaccinations are safe. I wonder why?
However, we actually agree with the critics that it is confounded but here’s why: governments don’t release the breakdowns publicly so we can’t do any better than this. If the vaccines are so safe, why don’t they release the data to the public to show this?
Is this just a fluke? I don’t think so. Watch this video starting at 7:00. The line goes the wrong way. The more you vaccinate, the worse it gets.
The health authorities are never going to figure this out because it would discredit them. So they have to keep on singing the same tune: “Safe and effective.”
LIFE INSIDE AN AUSTRALIAN COVID PRISON CAMP (CENTRE OF NATIONAL RESILIENCE)
CLOSE CONTACT SUSPECT HAYLEY HODGSON DESCRIBES 14 DAY INCARCERATION
See also:
Camp Australia: The brochure vs reality

Why hide what happens in the first two weeks after vaccination?
Hiding part of the data leads to wrong conclusions
Health Advisory and Recovery Team | December 1, 2021
There have been numerous papers published showing how well the vaccines protect people after the second dose. Some of this effect is an illusion. The effect happens as a result of inaccurate measuring and a phenomenon called survivorship bias.
Survivorship bias happens when a group is compared at two time points, but the members of the group change between the time points. It would be like assessing the quality of a swimming school which favours the technique of throwing people into the middle of the ocean, leaving them for a couple of hours and claiming credit for how well the remaining students can swim. After two hours, the only people left would be the ones who could already swim and possibly a few who learnt to swim the hard way! The poor souls who drowned in the interim don’t even make the count. Attributing the remaining people’s swimming ability to the coach who turned up 2 hours later would obviously give a very misleading picture. Pointing out that no-one drowned in later lessons would be equally misleading in determining the success of the ‘teaching technique’.
With covid vaccination there is a two week period after vaccination that is not included in the data. The rationale given for this is that vaccines take a while to induce antibodies and therefore the first two weeks’ data are not relevant. Obviously this is flawed. What if the vaccines have deleterious effects that are visible straightaway, that have nothing to do with antibody production? An example is the high rate of shingles seen after covid vaccination, suggesting there is a problem with viral reactivation. This may explain why Sars-CoV-2 infection rates are actually higher in the vaccinated than in the unvaccinated in the first two weeks after vaccination.
The effect of eliminating the first two weeks is a misleading data bias. If people become infected and are dying during that period, this needs to be included. The possibility that the vaccine itself may exert an effect on infection rate cannot be overlooked and the entire dataset needs to be included in order to accurately assess effectiveness. By only measuring the period after the higher risk of infection (0-14 days) it is possible to be deceived. Any signal would be missed.
Aside from it being nonsensical in terms of individual risk to remove this period of time, there will also be an impact on the wider community. If the vaccine in fact causes a spike in infections during the first two weeks, this will inevitably increase spread and will lead to an increased number of infections in that community during that time. Therefore, the assessment of the impact of the vaccination programme must include not only the effect on the individual, but the impact on the wider community.
This point is of particular relevance for close-knit communities where many are being vaccinated at the same time, such as schools and in particular communities with a high number of vulnerable people such as care homes and hospitals. What we are effectively doing is ‘speeding up’ the wave of infections (and deaths). Ultimately at the end of the viral season, the same number of people died. Because of excluding the earlier deaths (1-14 days), we are misled into thinking that the vaccines were more effective than they actually were. By only looking at the later period and seeing fewer deaths during that time, the illusion was created that lives were saved. This is evident in data from many countries following vaccine roll-out. The graph below showing the UK versus Europe illustrates this point, as the UK was the fastest to roll out the vaccine. The total number of deaths, represented by the area under the curve, was similar to other countries, but is just compressed into a shorter time period.
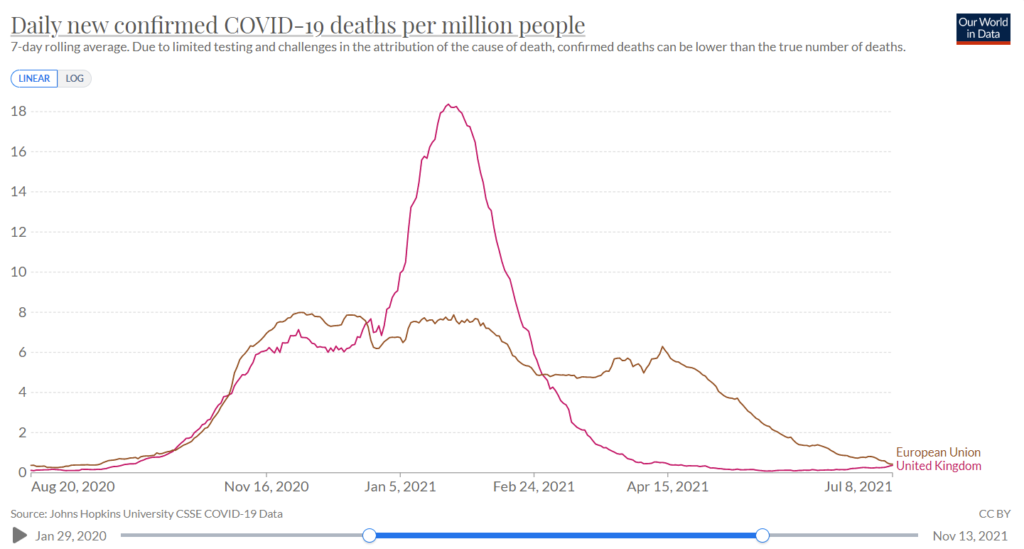
Figure 1: Covid Deaths in winter in UK and the European Union
Let’s now examine some specific examples, e.g. this study of nursing home residents in the United States. The results show that over the course of the study 6.8% of the vaccinated population were infected and 6.8% of the unvaccinated population were infected. However, by deciding that the first 14 days after vaccination should be excluded, the grey area for the vaccinated group is compared to the black and grey area combined for the unvaccinated. Doing so could lead to the claim of 66% vaccine efficacy against infection. The authors of this study were honest enough to share the raw data and did not claim 66% efficacy.
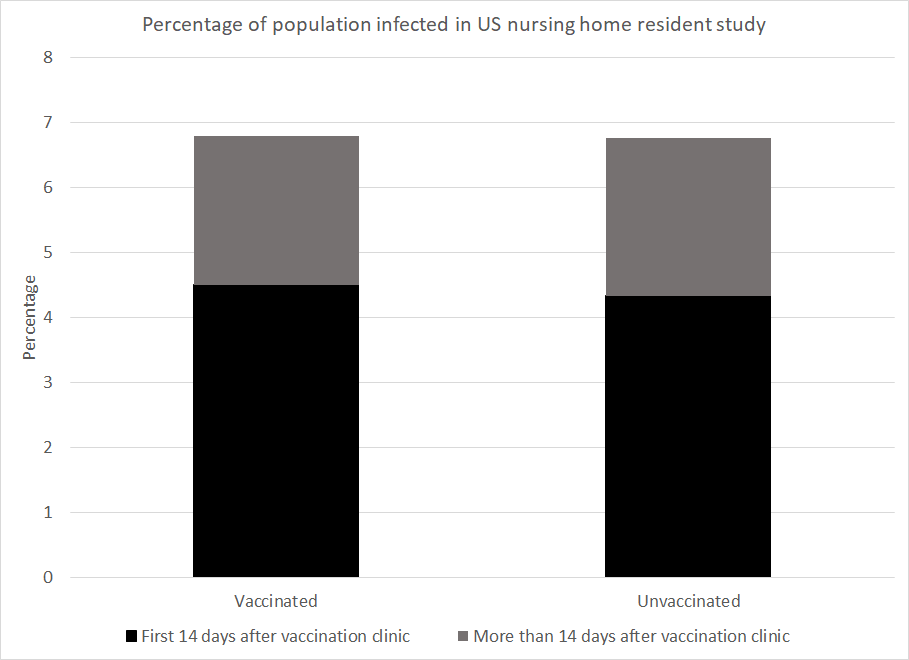
Figure 2: Data from US paper showing the percentage of the nursing home population to be infected by time after the clinic came to their home and by vaccination status
However, numerous studies have relied on this trick to make claims of vaccine efficacy. The most obvious examples of this are the original Pfizer trial study and the AstraZeneca trial.
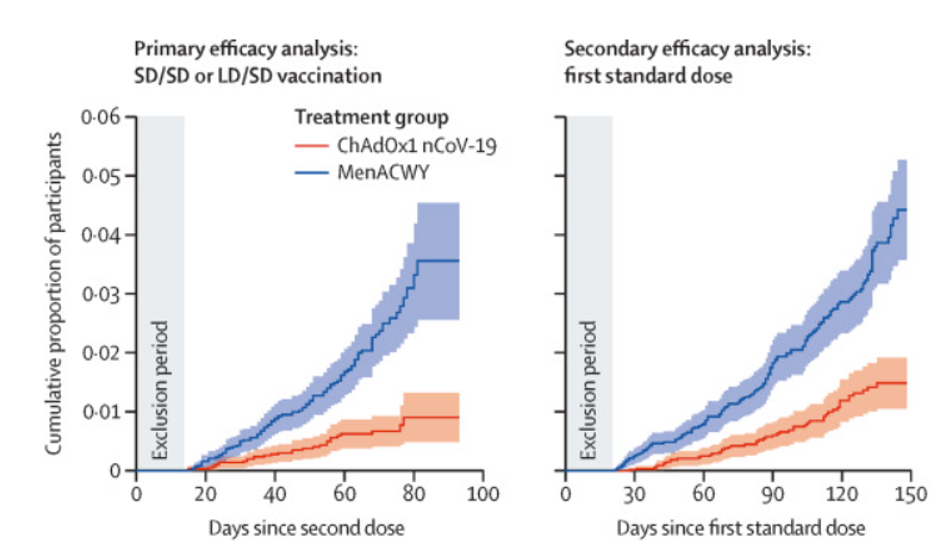
Figure 3: Graph from AstraZeneca trial showing censorship of early period (‘Exclusion Period’)
To take a second example, a Danish paper measured infection numbers in healthcare workers and care home residents. Prior to the beginning of the vaccination programme 4.8% of the healthcare workers had been infected and 3.8% of the care home residents had been. The study ended at the end of the Danish winter wave after 95% of the care home residents had been vaccinated and 28% of the healthcare workers had been. Given the worse position at the start and the lower vaccination rate in healthcare workers you might expect that they were worse off overall. However, the percentage infected by the end of the wave was 7.0% among healthcare workers but 7.7% among care home residents.
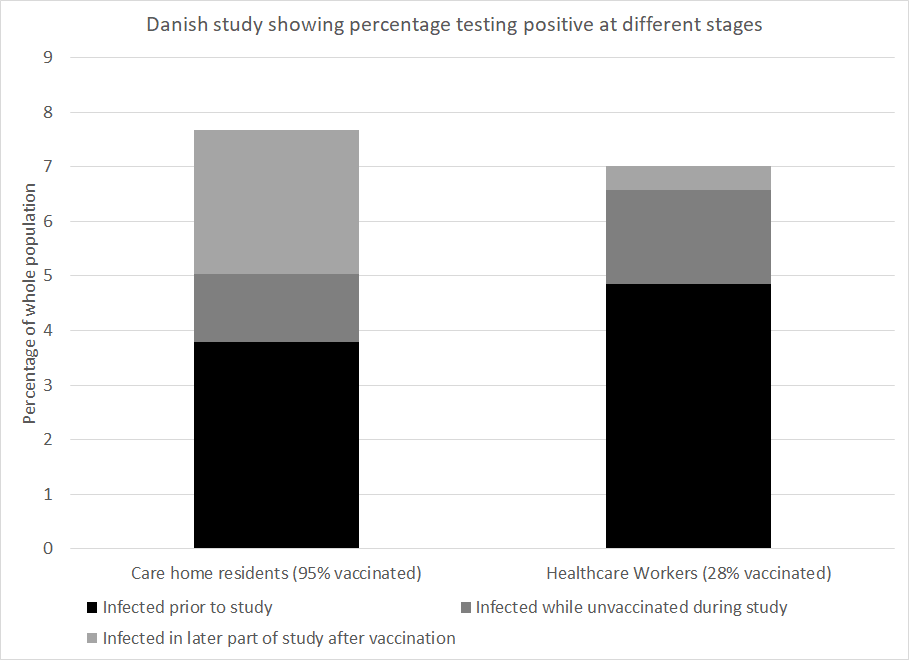
Figure 4: Data from Danish paper showing percentage of population infected among care home residents and healthcare workers
How much of the vaccine efficacy reported in covid research is really a measure of survivorship bias coupled with naturally acquired immunity? This is a critical question. No claim of vaccine efficacy should be made without first addressing this.
UK surgeon remains suspended a year after saying governments are using Covid to control people

By Christina Maas | Reclaim The Net | December 4, 2021
Last year, the UK medical register suspended a consultant surgeon for 12 months pending an investigation by the General Medical Council (GMC) for posting on social media that Covid-19 was being used by elites to control the world.
Colleagues wrote to the organization arguing he should not have been suspended for his personal opinion.
Mohammad Iqbal Adil, a Pakistan-born British doctor, has worked in the NHS for almost three decades. An interim orders tribunal suspended him for a year because of videos he posted on social media.
The doctor expressed “his point of view on the Covid-19 pandemic and the far-reaching effects of the lockdown on the economy, public health and wellbeing,” his campaign page states.
A spokesperson for the GMC at the time said: “The interim orders tribunal imposed an interim suspension on Dr Adil’s registration, following our referral, to protect patients and public confidence. This interim suspension remains in place while we consider concerns about Dr Adil’s fitness to practice.”
Some of his colleagues launched a petition on Change.org calling on the GMC to reinstate Dr. Adil. The petition argues that the GMC should have given him a chance to reflect on the videos “when the entire world is confused about the novel virus.”
The petition also noted that he had a family to support, adding, “UK needs doctors to work. It would not be in the best interest of the public and health system to lose [an] experienced and highly qualified surgeon like him.
“We, the doctors community within [the] UK and across the world, feel that it’s injustice to suspend Mr Adil on his personal point of view on the covid-19 without giving him [a] chance to reflect upon his video before enforcing suspension.
“We request to the GMC to revoke his unfair 12 months suspension . . . and allow him fair chance to work in this country [for the benefit of] the health system, communities, and medical graduates.”
“Dr Adil has been making a stand for freedom of speech for all doctors and nurses to speak their truth without fear of recrimination or persecution,” his campaign page states.
Researchers Acknowledge SARS-CoV-2 Is Gaining Vaccine Resistance
By Dr. Joseph Mercola | December 3, 2021
Looking at the viral evolution of SARS-CoV-2, researchers from the prestigious universities Harvard and MIT have found that the virus not only will continue to mutate and create new variants in the future, but will become resistant to the vaccines as it adapts to humans.
Their study, published December 2, 2021, in the journal Science, shows that the mutations serve as bridges to conferring resistance to neutralizing antibodies. “The severity of the phenotypes we observed in vitro suggest that further evolved variants will more adeptly escape therapeutic antibody neutralization than currently circulating variants of concern, with potential resistance to two-component antibody cocktails,” the study authors wrote.
The scientists urged that “proactively examining the consequences of further viral evolution before the next highly antibody resistant strain emerges is of utmost importance.”
A brief reminder: Health agencies were not always deranged
a trip down memory lane
el gato malo – bad cattitude – december 4, 2021
it was february of 2020, a kinder time. a gentler time.
and the WHO was putting out guidelines to avoid stigmatizing people who got covid…

never forget this.
they knew before 2020 than none of these interventions worked, that their prices were insanely high, and that they should never be undertaken.
they knew the dangers of vilification and polarization.
standing pandemic guidelines vehemently warned against any of this and especially against making pariahs of the infected and cultivating exaggerated fear to drive compliance.
this has NOT been “following the science” is has been the abrogation of a century of evidence based epidemiology and social mores in order to take a devastating and self-serving joy ride with the world’s populace like it was some sort of video game.
and all the health agencies were aware of that.
these were choices.
this was done to you, not for you.
and it was done by people who damn well knew better.
if you learn one thing from this, learn that, because these malefactors and agencies are still around and they are not done with you…
Huge new study shows ZERO Covid deaths of healthy German kids over 4 or adolescents
By Alex Berenson | December 2, 2021
German physician-scientists reported Monday that not a single healthy child between the ages of 5 and 18 died of Covid in Germany in the first 15 months of the epidemic.
Not one.
Even including children and adolescents with preexisting conditions, only six in that age range died, the researchers found. Germany is Europe’s largest country, with more than 80 million people, including about 10 million school-age children and adolescents.
Serious illness was also extremely rare. The odds that a healthy child aged 5-11 would require intensive care for Covid were about 1 in 50,000, the researchers found. For older and younger children, the odds were somewhat higher, about 1 in 8,000.
Another eight infants and toddlers died, including five with preexisting conditions. In all, 14 Germans under 18 died of Covid, about one per month. About 1.5 million German children or adolescents were infected with Sars-Cov-2 between March 2020 and May 2021, the researchers found.
“Overall, the SARS-CoV-2-associated burden of a severe disease course or death in children and adolescents is low,” the researchers reported. “This seems particularly the case for 5-11-year-old children without comorbidities.”
The researchers reported their findings in an 18-page paper published to the medrxiv preprint server on Monday.
The data came from a registry Germany established in March 2020 intended to capture all hospitalizations of people under 18 with Covid. All German children’s hospitals, pediatric infectious disease specialists, and pediatric societies were invited to participate.

(SOURCE: https://www.medrxiv.org/content/10.1101/2021.11.30.21267048v1.full.pdf)
British researchers have posted similar findings, reporting that only six healthy children (including those under 18) out of 12 million died of Covid.
Given the known risks of vaccine-induced myocarditis in young men, the fact that Pfizer tested its mRNA vaccines on barely 3,000 children 5-11 and followed most of them for only weeks after the second dose, the German data again raises the question of how health authorities can possibly justify encouraging children or teenagers to be vaccinated.
But they have.
So parents will have to decide what’s best for their children (at least in those states that bar vaccine fanatics from trying to vaccinate teenagers without parental consent).
Should employers require vaccination without any other option? Comments to OSHA close on Dec 6.
By Steve Kirsch | December 3, 2021
ICYMI, here’s the URL to file your comments before the comment period closes on December 6, 2021.
In a nutshell, OSHA believes that:
- Face coverings work and should be used.
- COVID recovered people who have not been fully vaccinated still face a grave danger from workplace exposure to SARS-CoV-2.
- They should impose a strict vaccination mandate ( i.e., all employers required to implement mandatory vaccination policies as defined in this ETS) with no alternative compliance option.
I believe:
- The scientific evidence (Danish mask study, Bangladesh mask study) shows that face coverings are completely ineffective.
- COVID recovered people should be exempt from all rules. If COVID recovered people are re-infected, they don’t get hospitalized, don’t die, and don’t spread the virus to others. The CDC has no counter-examples.
- The vaccines kill more people than they save for all age groups according to the VAERS data. And even in Pfizer’s own study, there were significantly more deaths in the vaccine group than then in the placebo group. There is ZERO scientific evidence the vaccines save lives when you are looking for a reduction in all cause mortality. Businesses should BE PROHIBITED from requiring vaccination.
One of us is wrong. If you agree with me, please consider taking a few minutes to file a comment.
Featured Video

ARE PATIENTS BEING PROPERLY INFORMED ABOUT OZEMPIC?
or go to
Aletho News Archives – Video-Images
From the Archives
Trans ‘milk’ as good as the real thing – NHS
RT | February 18, 2024
The drug-induced nipple secretions of trans women are as good as mothers’ breast milk for babies, the University of Sussex Hospitals NHS Trust claimed in a letter to campaigners made public in a report by British think tank the Policy Exchange on Sunday.
The healthcare trust’s medical director, Rachel James, argued that the off-label prescription drug cocktail men transitioning to female take in order to produce milk was “similar to the natural hormones which encourage lactation to develop when the baby is newly born.”
“The evidence which is available demonstrates that the milk is comparable to that produced following the birth of a baby,” James wrote in the letter, sent to Children of Transitioners last August.
Biological men who wish to lactate must first take hormones to grow milk glands and then take high doses of either domperidone or metoclopramide to stimulate milk production. Neither drug is approved for this use, though they are occasionally prescribed off-label to biological women who have trouble lactating.
However, domperidone’s own manufacturer, Janssen, warns patients the drug “may cause unwanted side effects affecting the heart in a breastfed baby” and “should be used during breastfeeding only if your physician considers this clearly necessary.” … continue
Blog Roll
 Aletho News
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- Your Milk Is Not the Problem
- The Truth About the Trump Shootings with Ken Silva
- ARE PATIENTS BEING PROPERLY INFORMED ABOUT OZEMPIC?
- US lawmaker blocks $2.8 billion weapons sale to Israel: Report
- Yemeni army claims responsibility for strikes on sensitive sites in Saudi capital, Aramco facilities in Yanbu
- Iran Judiciary issues indictments against 159 US, Israeli officials for assassination of Leader, commanders
- Turkiye revokes Iranian bank license under US sanctions campaign
- US-Denmark Agreement on Greenland Is ‘PR Stunt’ Ahead of Midterms
- Araghchi: Military intervention cannot create security; coercion cannot bring peace
- If Americans Knew
- Salah Sarsour’s Legal Team Says DHS Has Not Met Its Burden to Prove He Is Deportable
- An analysis of tax forms by The Intercept show Kraft’s charity and LLC have donated to Friends of the IDF and AIPAC’s super PAC.
- Israeli attacks kill four Palestinians in Gaza – Daily Update
- Inside Gaza’s death trap of collapsing, bombed-out buildings
- The everyday items Israel bans from Gaza every day
- Inside the siege, the ruined buildings of Gaza – Daily Update
- Debunking The Claim That Macklemore Has A “History Of Antisemitism”
- CPJ demands release of arrested Palestinian-US journalist near Bethlehem
- Robert Kraft: The Billionaire Friend of Netanyahu Pulling The Strings Behind the Macklemore/Ed Sheeran Blow Up
- Columbia Administered Fund Gives Big Money to Pro-Israel Groups
- No Tricks Zone
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
 Aletho News
