Three US medical certifying boards have warned doctors that they risk losing their certification and licence if they spread covid vaccine misinformation.
Internists, family doctors, and paediatricians received an email on 9 September that quoted a warning from the Federation of State Medical Boards in July1 which read: “Providing misinformation about the covid-19 vaccine contradicts physicians’ ethical and professional responsibilities, and therefore may subject a physician to disciplinary actions, including suspension or revocation of their medical licence.”2
Richard Baron, president and chief executive of the American Board of Internal Medicine (ABIM), told The BMJ that the move was an attempt to establish a standard of care. “As standard setting organisations, we thought it was important to be on record, in a public way, to make clear that putting out flagrant misinformation is unethical and dangerous during a pandemic.” Baron said that the statement has been well received—“4 to 1 positive.” But community physicians contacted by The BMJ thought differently.
“When I got that email I thought I’d better not put anything on social media about vaccines,” said Shveta Raju, a community physician in the Atlanta, Georgia, area, who has treated covid patients and led the vaccination effort at her outpatient clinic.
“The email was sent more as a veiled threat to keep doctors on the official, established narrative, and that’s what I find chilling,” said a paediatrician who pseudonymously blogs under the name Elizabeth Bennett. “Pandemic or no, there is a problem with having an ill defined concept of misinformation that’s tied to public health messaging that hasn’t been consistent. How are physicians supposed to figure out what is misinformation when public health messaging swings so wildly?” Bennett asked.
Undefined offence
Baron said that the statement was also intended to signal the certifying boards’ support for physicians “trying to do the right thing.”
“We wanted to support that group and say ‘hey, we do have a standard of care here and you are doing the right thing when you uphold it,’” he said.
Raju responded, “If that was their intent, they should have defined misinformation. By leaving it undefined, the message was that we can’t talk about this at all.” She said that physicians are, by and large, a conservative group. “If they’re not sure what can be deemed misinformation, physicians would rather be quiet.”
Bennett concurred: “The thing I find most alarming is that they don’t define misinformation, but if they strip you of your board certification, you would lose your means of earning a living.”
Doctors spreading misinformation?
Official and social media company efforts to target “vaccine misinformation” predate the pandemic.3 But the new statement from ABIM, the American Board of Family Medicine, and the American Board of Paediatrics is one of several recent statements putting doctors in the spotlight for the first time.
In Canada, warnings about physician information began earlier, when in April the College of Physicians and Surgeons of Ontario declared that physicians “have a professional responsibility not to communicate anti-vaccine, anti-masking, anti-distancing, and anti-lockdown statements or promote unsupported, unproven treatments for covid-19.”4
The Canadian statement triggered an outcry, leading to a clarification that the statement was “not intended to stifle a healthy public debate about how best to address aspects of the pandemic.” But concerns continued. In June, a Canadian member of parliament held a press conference on censorship of Canadian clinicians and scientists. YouTube removed the video of the meeting.56
The BMJ asked ABIM about the size of the problem of board certified physicians spreading misinformation.
“We don’t have a sense of numbers of physicians spreading misinformation,” Baron said. “We’re at the beginning.” He believed it was only a “small number of doctors.” The medical boards opted to send the statement to all doctors, he said, because focusing on just the offending individuals would “miss the impact they’re having because of how much their voices are being amplified.”
As an example of “unprofessional or unethical behaviour,” Baron cited the case of a Florida doctor offering medical exemptions from mask wearing for $50 (£37; €43).7
Personalised medicine—or one-size-fits-all?
The BMJ asked whether physicians expressing doubt about the need for booster doses or vaccination of patients with natural immunity—two matters that have been the subject of debate and changing official guidance—would qualify as misinformation.8 “I don’t think we have concerns with doctors wrestling with areas where the science is unclear,” Baron said, “but there is no debate about whether people should get a primary vaccination series.”
Raju worries about the impact on personalised care. “The job of physicians is to take guidelines and apply them to the patient in front of them.” But now “physicians are basically being told that when it comes to covid vaccines it’s one-size-fits-all.”
Baron said, “We’re not trying to stifle conversations between doctors and patients. We understand that different people may look at evidence in different ways, but when you have an overwhelming preponderance of medical consensus in a certain area, you need at least to tell patients that there is an overwhelming professional consensus here.”
Cautious approach
Jeffrey Flier, former dean of Harvard Medical School, said that in the context of the pandemic, he was “not opposed to certain levels of misinformation triggering a decision to question somebody’s licence.” He said, “I can see this being an appropriate remedy at a time of public health emergency.
“But this is not how the system for licensure and certification has traditionally worked, and creates many opportunities for mistaken judgment about what is and is not misinformation, and those decisions would have to be rendered with extreme caution.”
Flier added, “We have to remember that there are legitimate areas of debate, and such matters should not fall within the scope of disciplinary actions.”
“There are reasons to be concerned that state boards might be unprepared for these kinds of decisions at a time when so many aspects of covid policy have been enmeshed with political views.”
Footnotes
-
This article was updated on 4 October to make clear that it was medical certifying boards, rather than licensing boards, that emailed physicians. The email quoted an earlier warning from the Federation of State Medical Boards.
-
Competing interests: PD gave a public statement at a 17 September 2021 FDA advisory committee to discuss covid-19 vaccines, where he highlighted the joint statement. The views and opinions expressed here are those of the author and do not necessarily reflect official policy or position of the University of Maryland.
-
Provenance: commissioned; not externally peer reviewed.
This article is made freely available for use in accordance with BMJ’s website terms and conditions for the duration of the covid-19 pandemic or until otherwise determined by BMJ. You may use, download and print the article for any lawful, non-commercial purpose (including text and data mining) provided that all copyright notices and trade marks are retained.
https://bmj.com/coronavirus/usage
View Abstract
October 7, 2021
Posted by aletho |
Deception, Full Spectrum Dominance, Science and Pseudo-Science, War Crimes | Canada, Covid-19, COVID-19 Vaccine, Human rights, United States |
Leave a comment

Dr. Rochagné Kilian
OWEN SOUND, Ontario – Dr. Rochagné Kilian recently resigned as an emergency room and family practice physician due to her concerns that the Ontario health system and Grey Bruce Health Services (GBHS) crossed ethical lines throughout the pandemic.
In a virtual meeting that included GBHS CEO Gary Sims and other staff members, Dr. Kilian asked Sims a series of questions about what she believes is unethical behaviour on behalf of the Ontario health system at all levels. Sims appeared to be unprepared for difficult questions pertaining to the ongoing rollout of vaccination mandates and vaccine segregation restrictions the Ontario heath system is championing.
Kilian estimated that 80 percent of the patients she saw in the ER during the past month who had inexplicable symptoms were “double vaxxed.”
Dr. Kilian relocated to Owen Sound – a small city in Grey County, Ontario – from South Africa after previously working in British Columbia. When she resettled in Owen Sound with her family, she expressed to a local paper how happy she was to live there: “Our recruitment to Owen Sound might have been by chance, but our choice to settle here was definitely not. Our four months in Owen Sound have been blessed. A little town with lots of soul, surrounded by beautiful landscapes, filled with welcoming residents and businesses, and exciting festivals, programs and activities. We truly feel fortunate to raise a family here.”
The first issue that Dr. Kilian brought up during the meeting was informed consent regarding the COVID jab and what she considered to be a coercive mentality of pressuring people to accept medications that she pointed out are still in “clinical trials.”
An GBHS administrator did not answer her question directly, but instead passed the buck to the provincial government and stated they do not have “oversight or input” regarding consent mechanisms presented to patients.
Kilian added that having more input into what patients are consenting to is something that GBHS “should consider,” especially in light of enacting the government-recommended vaccination mandates with their own staff.
Referring to informed consent and mandating experimental vaccines that been linked to thousands of deaths and injuries, Sims explained that because of the “pandemic,” certain procedural normalities will not take place.
“In a pandemic, some of those pieces that you think would be there [mechanisms of informed consent from the government] when you have lots of time to review stuff … in a pandemic, they’re going to pass mandates, and they’re going to pass laws, and they’re going to pass directives as needed to manage that pandemic,” he said. “And some of the things … will feel like they’re infringing on or taking short cuts … they are doing that directly to save lives.”
Sims then stated that there is a “massive scientific group” that has reviewed all the issues pertaining to the vaccines and their usage and rollout. This meeting took place August 23. Since then, the Ontario government has admitted that at least one of the vaccines pushed on the public has caused serious heart problems in young men, who are at virtually no statistical risk of suffering severely from COVID.
Dr. Kilian pressed Sims about claims that protocols of informed consent can be skirted due to an emergency, and clarified that the Tri-Council Policy Statement stipulates that an emergency situation does not warrant skirting protocols that protect the population from being put at risk due to medical experimentation. The Tri-Council Policy Statement is a Canadian guideline for the ethical conduct of research involving humans and/or human biological materials. As the vaccinations are still technically under experimental trial, they are being implemented under a research-based framework on the population.
It was Kilian’s opinion that the ethical framework is being ignored, thus health workers and citizens are being forced to take something against their will that is not proven to be safe or effective in the long term, as a result of vaccination mandates.
Sims reacted sharply to Kilian and said, “Nobody is forcing you to do this, you have a right to say no, but the reality is the government has the right to say that you’re not employed.”
“When the law looks at it, the law is saying you have the right to do it [enforcing vaccine mandates],” he added.
Dr. Byram Bridle, a University of Guelph professor, recently released a letter he sent to the president of his university that called into question the legitimacy of vaccine mandates, both from a medical and legal perspective. He stated in the letter that he is “confident there will be lawyers willing to test this in court.”
Dr. Kilian asked a final question in the virtual meeting about the claims that Sims and others at GBHS have made about the majority of COVID-associated cases in the region being among the unvaccinated. She asked if there was a detailed database that could be shared to prove this point. Sims stated that the vaccination status of the individuals who have been admitted in his region could not be released due to privacy reasons, but that the provincial government would have the information.
He then claimed that provincially, “less than 0.7 percent of people who ended up in ICUs were vaccinated.”
He referred to the “third wave” of COVID in Ontario that he said was due to the Delta variant, and stated that “it was all unvaccinated” who fell seriously ill at that time. The third wave in Ontario is reported to have happened in April and May. The vast majority of Ontarians had not received their second dose of any COVID jab by that point, and the province has made it clear in numerous places that a person only counts as “full vaccinated” for clinical purposes after 14 days have passed since they have received their second dose.
During the month of May in the Grey Bruce region, there were a total three confirmed hospitalizations with COVID-19. Five people in the region died that month with a COVID-positive diagnosis, and two of the deaths were residents who died outside of the county.
Sims said on the call that a minimum “80 percent” and up to “97 percent” of ICU patients with COVID across the province were unvaccinated. It is impossible to reach that number given the Grey Bruce statistics because there are too few people for calculations to be mathematical doable.
He then intimated that there will be great fears among pediatric physicians regarding autumn COVID numbers “if children start to die.” There is no evidence to suggest that COVID is dangerous to children in any statistically significant way.
Dr. Kilian resigned from her position while on the call with GBHS administration and spoke about her situation on the The Strong and Free TruthCast, where she criticized the state of health care in Canada. She expressed that care for the individual patient has gone by the wayside during the “farce that we have been living through.”
She said that throughout the entire time that the pandemic has been declared, she has only admitted two patients to the ICU that tested positive for COVID. She then clarified that this did not mean they were in the ICU due to COVID, but only that they had tested positive. She stated that her emergency department was “dead” throughout all of the declared waves of COVID, and that she took pictures of the official numbers to prove that they “had nothing to do” with lack of patients.
Dr. Kilian added that since the rollout of COVID jabs, she has seen a striking uptick in patients who have been admitted with heart issues and do not fit risk categories. She stated that as more and more people have received the jab, she has seen a host of strange events in her patients. She spoke of “people coming with newly diagnosed high blood-pressure, diabetics that was controlled that are no longer controlled – their sugars are either through the roof or they’re down in the ground … The only factor … constant that changed in their life was the injection of an experimental biologic.”
October 7, 2021
Posted by aletho |
Civil Liberties, War Crimes | Canada, Covid-19, COVID-19 Vaccine, Human rights |
Leave a comment
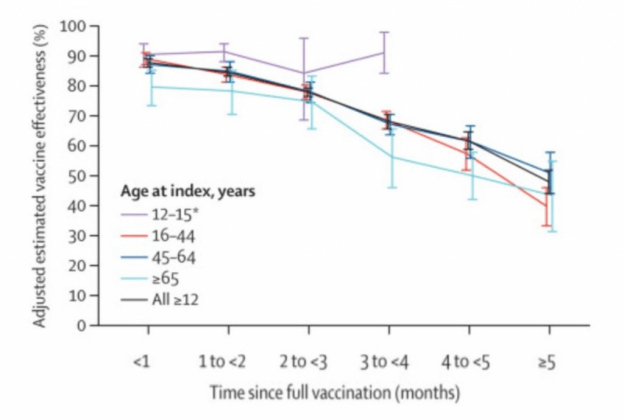
A study appeared in the Lancet this week confirming that vaccine effectiveness against infection is fading fast.
The study involved 3,436,957 people over the age of 12 who are members of the healthcare organisation Kaiser Permanente Southern California. It sought to assess the effectiveness of the Pfizer vaccine against SARS-CoV-2 infections and COVID-19-related hospital admissions for up to six months, with a study period covering December 14th, 2020, to August 8th, 2021.
Comparing fully vaccinated to unvaccinated, and controlling for confounders such as prior infection, the researchers found that effectiveness against infection plummeted from 88% (95% confidence interval 86-89%) during the first month after double-vaccination to 47% (43-51%) after five months. The variation by age (depicted above) was largely within the margins of error.
Among sequenced infections, the researchers found vaccine effectiveness against Delta infection was 93% (85-97%) during the first month after double-vaccination but dropped to 53% (39-65%) after four months. Effectiveness against infection from other variants the first month after double-vaccination was 97% (95-99%), but declined to 67% (45-80%) at 4-5 months.
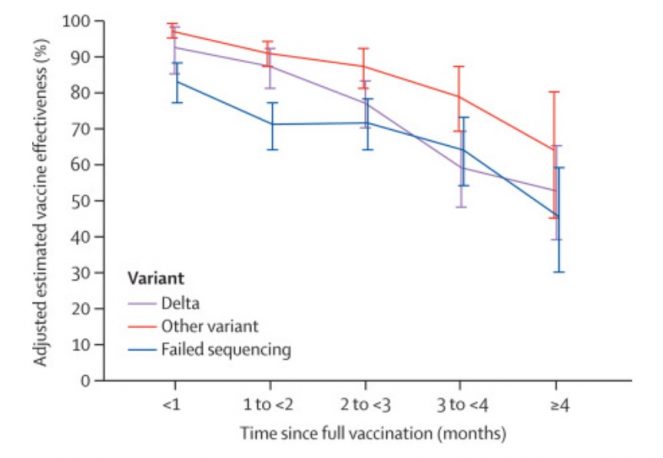
Pfizer vaccine effectiveness by Covid variant
Vaccine effectiveness against hospital admissions for Delta infection held up at around 93% (84-96%) for the six months across all ages.
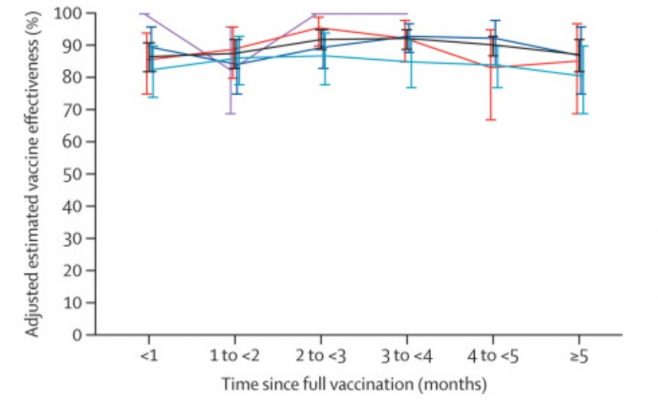
Pfizer vaccine effectiveness against Covid hospitalisation
However, the researchers note that the latest data from Israel “suggests that some reduction in effectiveness against hospital admissions has been observed among older people (65 years and over) roughly six months after receiving the second dose of [Pfizer]”.
One question that’s arisen recently is to what extent vaccine effectiveness estimates are affected by whether more people who have been previously infected decide not to be vaccinated. According to this study the answer is: not very much at all. Among the unvaccinated, 2.3% had one or more previous positive PCR tests, only slightly more than the 2% of the double-vaccinated who did.
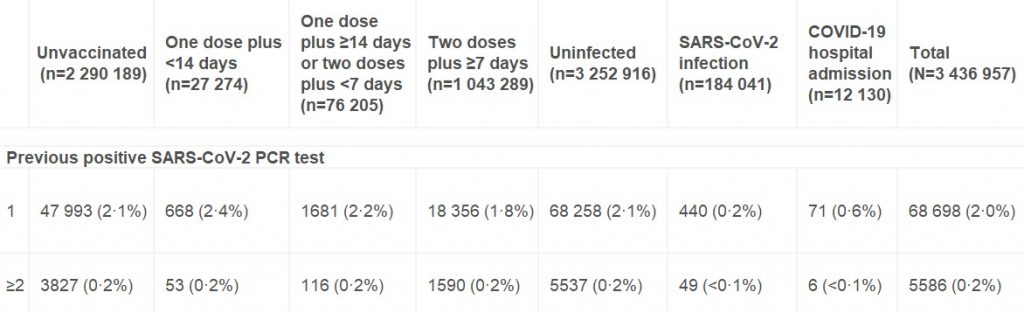
Number and percentage of individuals with one or more previous positive PCR tests
It’s also worth noting that although this study adjusts its raw estimates for no fewer than 22 potential confounding variables, the adjusted figures differ very little from the unadjusted figures in almost all cases. This suggests that unadjusted estimates from large population samples are often a fair approximation in the absence of sophisticated statistical analysis.
Given that the adjusted figures were little different to the unadjusted figures, however, it’s not immediately clear why the vaccine effectiveness estimates in this study, while low and declining, are so much higher than the latest unadjusted estimates derived from Public Health England data (namely, negative vaccine effectiveness in the over-40s, including minus-66% in those in their 40s). It doesn’t appear to be merely a matter of additional time elapsing, as most people in the U.K. weren’t double vaccinated until April, May or June, meaning only four or five months have elapsed until September, the same time period as in the study.
Could it be because the study period ended on August 8th, when the Delta surge in California was just getting going (see below)?
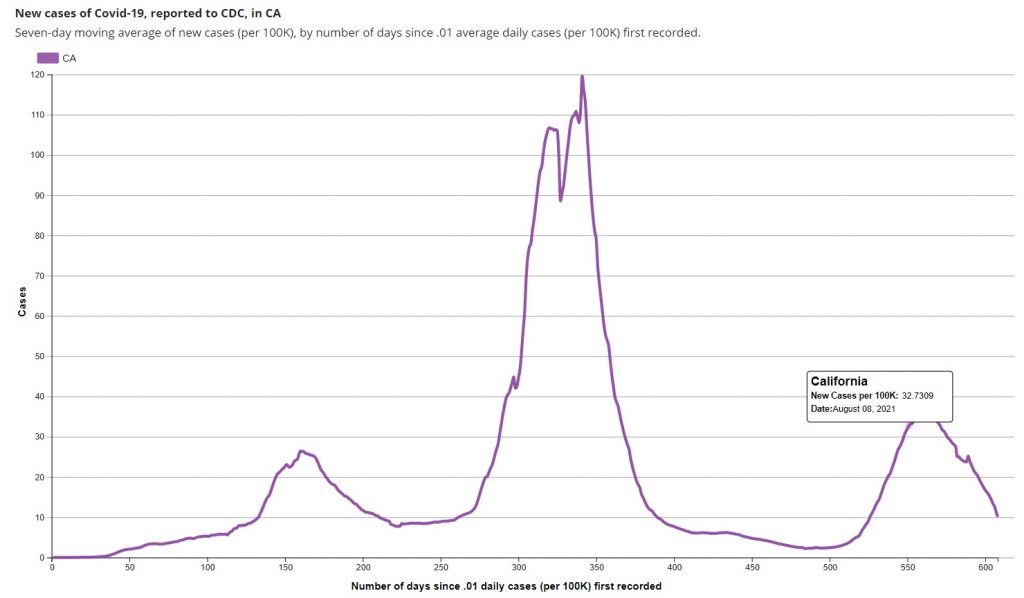
In the U.K. the vaccine effectiveness didn’t plunge until the second half of the Delta surge, the first part being dominated by infections in the unvaccinated (for reasons still not entirely clear). Did the new study finish too early to see the dramatic effect we’ve seen in England?
The authors say their study indicates that the decline in vaccine effectiveness is primarily a function of time rather than variant-related. However, the evidence from England would suggest otherwise, as in the same period of time, but later in the Delta surge, the decline has been far greater.
The decline in vaccine effectiveness in England was confirmed last week in a new Government-funded study (not yet peer-reviewed), which found that the reduction in transmission “declined over time since second vaccination, for Delta reaching similar levels to unvaccinated individuals by 12 weeks for [the AstraZeneca vaccine] and attenuating substantially for [Pfizer]”. In other words, within just three months AstraZeneca did nothing to prevent transmission, and Pfizer was scarcely better.
One of the main recommendations of the authors of both studies in light of their findings is for regular booster jabs – in the case of the first, where many of the authors are employees of and investors in Pfizer, this may be deemed hardly surprising. However, if effectiveness against serious disease is holding up, why give people boosters just to stop them getting and spreading what is effectively a cold, and which bestows more robust immunity as it goes? Furthermore, if the effectiveness declines after as little as three months, is it even possible to deliver enough boosters to have any impact on infection and transmission? Would it not be much better to say that the vaccines, by offering personal protection from serious disease to those who want it, have done their job? Better to move on and abandon any ideas of vaccine passports and mandates and boosters, and in general the now almost wholly pointless obsession with Covid vaccines.
October 7, 2021
Posted by aletho |
Science and Pseudo-Science | COVID-19 Vaccine |
Leave a comment
CNN reporter Randi Kaye visited my home unannounced, then tracked me down as I bicycled around my home town in August 2021. Her purpose was to publish a hit piece further labeling me as a “super-spreader of COVID-19 misinformation,”1 based primarily on the opinions of foreign agent Imran Ahmed, founding CEO Center for Countering Digital Hate (CCDH),2 which is a recently spun up front group funded by dark money.
https://twitter.com/AC360/status/1445192038845227008?ref_src=twsrc%5Etfw%7Ctwcamp%5Etweetembed%7Ctwterm%5E1445192038845227008%7Ctwgr%5E%7Ctwcon%5Es1_&ref_url=https%3A%2F%2Fblogs.mercola.com%2Fsites%2Fvitalvotes%2Farchive%2F2021%2F10%2F05%2Fsee-my-latest-response-to-cnns-hit-piece.aspx
After that story aired, she again contacted me, this time via email, to request an interview regarding my latest book, “The Truth About COVID-19: Exposing The Great Reset, Lockdowns, Vaccine Passports, and the New Normal.” Interview questions were provided via email, as were my responses. CNN ran this new story October 4, 2021.
In the interest of transparency, below I’ll post the email exchange so you can read my response to her questions firsthand. You can tell from the leading questions that this “story” isn’t true journalism but rather another hit piece manipulated to fit a preformed agenda.
CNN Interview Request for My Latest Book
August 26, 2021, Kaye emailed, “Here are the questions we would like answered about Dr. Mercola’s new book. We would welcome responses by 5pm tomorrow, please.” The questions, which are clearly accusatory, are as follows:
“You say in your book that “A large amount of data strongly suggests the COVID – 19 vaccine may be completely unnecessary, which means the global population is being bamboozled into participating in a dangerous and unprecedented experiment for no good reason whatsoever.” Can you please point us to that data that suggests the covid vaccines are unnecessary or dangerous?
You say in your book that “vaccine trials are rigged.” What proof do you have of that? Which trials? How many? Who rigged them and for what purpose?
You say in your book, “Common sense dictates that if the vaccines cannot prevent or reduce infection and transmission, hospitalization, or death, then they cannot possibly end the pandemic.” And that “There’s no telling whether they will ultimately prevent hospitalizations and deaths.”
Can you please provide us with the source and support for your statements since the CDC says vaccines are nearly 100% effective at preventing severe disease and death and greatly reduce infection.
How do you explain statements from hospitals and government officials that nearly all those who are getting sick and dying now are the unvaccinated?
Do you feel responsible for the spread of misinformation by writing a book full of conspiracy theories and false claims?
What were you paid for this book deal by the publisher?
Are you donating 100% of the earnings from your book?
If so, to which organization? Are you concerned this book will cost people their lives?”
My Response to CNN
Media organizations contact Mercola.com regularly, sometimes to challenge us on the researched, fact-checked articles we post for our readers. In CNN’s case, the information they were seeking was directly related to my book, which was the No. 1 best seller in all categories for four straight days with thousands of five-star ratings.
Much like the information on Mercola.com, the information in my book is thoroughly referenced, but Kaye, ironically, engaged in the dissemination of misinformation herself by describing my book as being “full of conspiracy theories and false claims.” My response to her questions follows:
“Many studies and other literature offer support for my position in answering several of your questions, which are combined since they can be answered with the same literature. Here are the important points that drive my book:
The vaccines are just 39% effective and waning, and the CDC’s Advisory Committee on Immunization Practices has now advised booster doses to the mRNA vaccines in immunocompromised persons. CDC’s goal is to begin offering booster doses to everyone else beginning this fall.3,4,5,6
Additionally, breakthrough infections among fully vaccinated persons are becoming more and more prevalent around the world. Evidence is beginning to mount that people with breakthrough infections can spread the Delta variant more easily.7,8,9,10,11,12,13
Most recently, researchers in Israel report that fully vaccinated persons are up to 13 times more likely to get infected than those who have had a natural COVID infection.
As explained by ScienceMag: The study “found in two analyses that people who were vaccinated in January and February were, in June, July and the first half of August, six to 13 times more likely to get infected than unvaccinated people who were previously infected with the coronavirus.
In one analysis, comparing more than 32,000 people in the health system, the risk of developing symptomatic COVID-19 was 27 times higher among the vaccinated, and the risk of hospitalization eight times higher.”14
The study also said that, while vaccinated persons who also had natural infection did appear to have additional protection against the Delta variant, the vaccinated were still at a greater risk for COVID-19-related-hospitalizations compared to those without the vaccine, but who were previously infected.
Vaccinees who hadn’t had a natural infection also had a 5.96-fold increased risk for breakthrough infection and a 7.13-fold increased risk for symptomatic disease.
“This study demonstrated that natural immunity confers longer lasting and stronger protection against infection, symptomatic disease and hospitalization caused by the Delta variant of SARS-CoV-2, compared to the BNT162b2 two-dose vaccine-induced immunity,” study authors said.15
A majority of gravely ill patients in Israel are double vaccinated.16 A majority of deaths over 50 in England are also double vaccinated.17 Also, mass vaccination of the population with the highly mutating coronavirus will only evolve perfectly vaccine-resistant strains of the virus.”18
Injection Trials Included COVID-19 Infections as Successes
The next part of my response focused more specifically on the vaccine trials, which were problematic from the start since they did not include prevention of infection as an endpoint. Instead, all study endpoints required infection with SARS-CoV-2, and “successes” included subjects with confirmed COVID-19 cases. The difference measured wasn’t whether or not the vaccines prevented COVID-19 but whether, and how, they modified symptoms among those infected.19
Also problematic is the unblinding of the vaccine trials, which means the placebo groups were removed. As medical investigative journalist Jeanne Lenzer wrote in the BMJ, “The data are now likely to be scanty and less reliable given that the trials are effectively being unblinded.”20 This is the next section of my response to Kaye:
“Regarding the vaccine trials: The vaccine trials were designed specifically to succeed for profit. The public health authorities and media like CNN are utilizing fear of the virus to induce psychological stress that promotes obedience and servitude.21
Additionally, proof that the trials are “rigged” can be shown by virtue of the fact that they’ve done away with the control groups — who were getting a placebo but who were then offered the vaccine, which virtually does away with the ability to compare adverse reactions including deaths. Pfizer’s own vaccine insert for Comirnaty admits that the control group hasn’t existed since December 2020:
Section 6.1 — “Upon issuance of the Emergency Use Authorization (December 11, 2020) for COMIRNATY, participants were unblinded to offer placebo participants COMIRNATY. Participants were unblinded in a phased manner over a period of months to offer placebo participants COMIRNATY.”22
NPR has noted that removing the placebo groups from vaccine trials will prevent accurate data from long-term studies from being known.23
Additionally, the CDC is being dishonest by utilizing data from the beginning of this year when the vaccine campaign had just been initiated to conflate their claim. They are using data that were scant early in the year because so few were vaccinated, as opposed to using current information.24
Proceeding with the FDA approval of Comirnaty this week was unprecedented. No other vaccine has ever received approval this fast — and without public comment being allowed through ACIP [the CDC’s Advisory Committee on Immunization Practices] or VRBPAC [the FDA’s Vaccines and Related Biological Products Advisory Committee] before approval was issued.
The approval is unconscionable because over 600,000 adverse reactions and 6,000 deaths [now over 14,500 deaths25] have been reported in the U.S. to VAERS. A majority of these reports are filed by medical professionals.
This shows that the safety of these vaccines is not proven. Besides, the experiments are continuing through 2027 as the FDA APPROVAL requires Pfizer to submit study results analyzing risk of myocarditis and pericarditis, and risk to long-term infant development in pregnant women. Study results will be submitted to the FDA for review on Oct 31, 2025 and May 31, 2027 respectively.”26
Lifesaving Information That CNN Won’t Share
CNN and other media outlets have the power to share lifesaving information that could turn the pandemic around and save lives in the process — but they won’t. Instead, the media are ignoring the basics of healthy immune function and the importance of early COVID-19 treatment to continue to push the narrative that the only solution is to get an injection.
The last part of my response to Kaye includes empowering steps that virtually everyone can take to support their health and reduce their risk of infectious disease. This includes having supplies from the Front Line COVID-19 Critical Care Working Group (FLCCC) I-MASK+ protocol on hand in the event you do get COVID-19.
FLCCC’s I-MASK+ protocol can be downloaded in full,27 giving you step-by-step instructions on how to prevent and treat the early symptoms of COVID-19. FLCCC also has protocols for at-home prevention and early treatment, called I-MASS, which involves ivermectin, vitamin D3, a multivitamin and a digital thermometer to watch your body temperature in the prevention phase and ivermectin, melatonin, aspirin and antiseptic mouthwash for early at-home treatment.
I also recommend getting a nebulizer, and the moment you feel a sniffle or something coming on, use nebulized hydrogen peroxide. Having a pulse oximeter on hand is also wise, as it’s a noninvasive way to measure the oxygen levels in your blood, allowing you to monitor your levels and help gauge whether a trip to the ER is truly in order.
As I told Kaye, taking control of your health continues to be the “secret” that I strive to share with the masses. The remainder of my response to CNN follows:
“I am donating all proceeds to the National Vaccine Information Center. I encourage every person to fully educate themselves to make individual decisions about medical risk-taking by talking with their personal physician and comparing the risks and benefits to make an informed decision that includes all the information on how these vaccines are working (or not working) and what all the possible side effects may be.
This pandemic is a direct reflection of the health of our population: 95% of COVID deaths have multiple comorbidities. Obesity, vitamin D deficiency and metabolic dysfunction are at the core of this pandemic and can be resolved by taking control of your health by following science-based dietary and lifestyle recommendations.
Since building up your health can’t be done overnight, what you can do beginning right now is avoid linoleic acid, check to ensure your vitamin D levels are above 40ng/ml, exercise, get fresh air and proper sun exposure, and restrict your eating window to a 6- to 8-hour time frame each day.
If you do get COVID-19, early treatment is crucial. Follow the Front Line Critical Care Alliance iMASK+ or MATH+ treatment protocols.”28
Sources and References
October 6, 2021
Posted by aletho |
Fake News, Mainstream Media, Warmongering, Science and Pseudo-Science | CDC, COVID-19 Vaccine |
Leave a comment
Because People were not Afraid Enough of the Flu Virus

Last night Alex Jones of Infowars.com did a special broadcast regarding an October, 2019 video that they had just become aware of that was a panel discussion hosted by the Milken Institute discussing the need for a Universal Flu Vaccine.
The video clip that they played of this event was a 1 minute and 51 second dialogue between the moderator, Michael Specter, a journalist who is a New Yorker staff writer and also an adjunct professor of bioengineering at Stanford University, Anthony Fauci, the director of the National Institute of Allergy and Infectious Disease, and Rick Bright, the director of HHS Biomedical Advanced Research and Development Authority (BARDA).
In this short clip, which was extracted from the hour long panel discussion, Anthony Fauci explains that bringing a new, untested kind of vaccine like an mRNA vaccine, would take at least a decade (“if everything goes perfectly”) to go through proper trials and be approved by the FDA.
He would know, because he had been trying to do it for about a decade already by then (October, 2019), trying to develop an mRNA based vaccine for HIV.
But now they were discussing something much bigger than just a vaccine for AIDS patients. They are talking about a “Universal Flu Vaccine” that everyone would have to take – a huge market for Big Pharma!
Rick Bright, the director of HHS Biomedical Advanced Research and Development Authority (BARDA), then speaks and states that what could happen is that “an entity of excitement that is completely disruptive and is not beholden to bureaucratic strings and processes” could change that.
Here is the short clip which I put on our Bitchute and Rumble channels last night:
Alex Jones spent over 50 minutes covering this on his show last night, and it looks like he covered it on his show today as well.
I have not had a chance to watch these yet, as I went and found the original 1 hour panel discussion video, and spent the day listening to and analyzing that, so that I could supply this report to our readers.
Joining Fauci, Rick Bright, and Michael Specter at this event were:
- Margaret Hamburg, Foreign Secretary, National Academy of Medicine
- Bruce Gellin, President, Global Immunization, Sabin Vaccine Institute
- Casey Wright, CEO, FluLab
In short, this panel discussion focused on what they perceived as the need for a universal flu vaccine, but they admitted that the old way of producing vaccines was not sufficient for their purposes, and that they needed some kind of global event where many people were dying to be able to roll out a new mRNA vaccine to be tested on the public.
They all agreed that the annual flu virus was not scary enough to create an event that would convince people to get a universal vaccine.
And as we now know today, about 2 years after this event, that “terrifying virus” that was introduced was the COVID-19 Sars virus.
And so now we know why the flu just “disappeared” in the 2020-21 flu season. It was simply replaced by COVID-19, in a worldwide cleverly planned “pandemic” to roll out the world’s first universal mRNA vaccines.
This was always the goal, and previous efforts through various influenzas, AIDS, Ebola, and other “viruses” were all unsuccessful in leading to the development of a universal vaccine to inject into the entire world’s population.
Margaret Hamburg stated regarding getting a “Universal Vaccine” into the market:
“It’s time to stop talking, and it’s time to act.”
“I think it is also because we haven’t had a sense of urgency.”
Michael Specter asks:
“Do we need lots of people to die for that sense of urgency to occur?”
Hamburg replies that: “There are already lots of people dying” from the flu each year.
Bruce Gellin states that basically people just are not afraid enough of the term “the flu.”
There are so many things that are revealed about how Big Pharma and government health authorities think in this panel discussion. For example, they bemoan the fact that if they do too good of a job in public health, then they lose funding to develop products that fight viruses.
Michael Specter states: “It seems to me that one of the curses of the public health world is, if you guys do your job well, everyone goes along well and healthy.”
Hamburg: “And they cut your funding.”
Rick Bright complains that the yearly distribution of flu vaccines is inefficient in terms of collecting data, and in the process actually admits that some vaccines just don’t work well:
“We distribute 150 million doses of the seasonal (flu) vaccines every year, we don’t even know how many people are being vaccinated from the doses that are delivered to the people, which doses they got, and what the real outcome was, so that we can learn from that knowledge base on how to optimize or improve our vaccine. So there are opportunities that we have today…”
I think if we uncloaked the poorest performing vaccines in the market place today, it might be very revealing to tell us which of the technologies we have, and allow us to go deeper into those technologies to determine why they are more effective. There are vaccines licenses today that are more effective. I think that we’re just afraid to admit the truth.”
So much for the public mantra that is espoused by Big Pharma and government that the “science” of vaccines is “settled,” and that they are completely “safe and effective.”
Casey Wright repeats the mantra that was publicized every year, before COVID, about just how deadly the flu virus was: “650,000 people die every year from the flu.”
As we have documented many times over the past decade here at Health Impact News, this is simply not true. This is an estimate because actual laboratory confirmed cases of influenza each year are very small, probably less than 1000 in the U.S.
Most flu-like symptoms are never tested in a lab to determine what is causing the symptoms. They were always just classified as “flu” to inflate the numbers to justify the very profitable flu shot each year. Some of our previous coverage of this issue:
Did 80,000 People Really Die from the Flu Last Year? Inflating Flu Death Estimates to Sell Flu Shots
So as they have inflated the COVID-19 cases since last year, they are simply continuing their policy of inflating flu numbers each year in order to sell their vaccines. They obviously could not have done both last year, as the public would have quickly seen that the math doesn’t work.
And yet, so many in the public bought the lie that the COVID-19 measures got rid of the flu, but not COVID-19.
Ultimately, this panel discussion can be boiled down to: Nobody wants to fund research for a universal flu vaccine. So how do we change that? Create a pandemic of fear over the flu (but they couldn’t call it the “flu” because people are no longer afraid of influenza, and the fear over “AIDS” had also subsided.)
Fauci then addressed this “perception problem.”
There’s this perception (about the flu), if it’s so serious, how come people get the flu each year and it isn’t a catastrophe?
When you’re dealing with a disease like HIV, if you get HIV, it’s serious. Whether you’re young, whether you’re middle aged, or whether you’re old. If you get cancer, that’s bad. Whether you’re young, whether it’s intermediate… whereas if it’s influenza, some people, they go throughout life and it doesn’t impact them at all.
There isn’t anyone who is afraid of influenza. You go into a focus group and you say: Are you afraid of getting HIV if you’re at risk? Oh, absolutely.
Are you afraid of getting cancer? Absolutely. Are you afraid of the flu? Don’t bother me.
That’s the reality of how people perceive flu.
And it is going to be very difficult to change that, unless you do it from within and say, I don’t care what your perception is, we’re going to address the problem, in a disruptive way…
Specter then asks:
In the long run, over time, if the 2009 pandemic had been much more deadly, would that have ended up being a better thing for humanity?
Everyone is silent as they obviously were thinking about how to answer that, and Specter says: “Come on gang.”
Fauci ultimately answers and says “No” because there were other years that were worse than 2009 and it didn’t change a thing in terms of creating a universal vaccine.
Hamburg then states:
The sad truth is that when there is a major crisis, it focuses attention and usually resources and some significant mobilization follows.
We need, #1, this time to be different, and we also need to really organize ourselves in a way where there will be accountability for sustained action, and not just response.
Specter states:
Craig Venter, who is a controversial person, but interesting to me, has written that he thinks we ought to have a vaccine, such that, if you take off in a plane from Hong Kong, and are infected, by the time your plane lands in New York, there ought to be a vaccine assembled and deliverable to you.
How crazy is that? How far are we from that? Are we ever going to get there?
Bright replies:
I’m not going to say how far away, but I don’t think that’s too crazy.
I think that if we move towards the era of synthetic-based vaccines, I think we remove the dependencies of thinking the vaccine that has be grown into something else, an egg, a cell, or insect cell – any type of dependency embryo.
If we can move into more synthetic, the nucleic acid based, messenger RNA based, those sequences can be rapidly shared around the world.
He then goes on to talk about using a 3D printer to print out a “vaccine patch” that people use to administer the “vaccine.”
We also learn in this panel discussion why Anthony Fauci is so opposed to natural immunity, because natural immunity for influenza, according to his view, translates to an immune response against other strains of a particular influenza virus, which will interfere with what they are trying to do with the vaccines.
That is why he wants to inject infants as young as 6 months old with a universal vaccine, as he states here, to prevent that “confused” natural immunity from happening before the child grows older.
So the big question that this panel was tackling, was how do they implement their strategies, and what is holding them back?
Certainly the government/regulatory issue is a big one, and now two years later we can see exactly how they did that, by controlling the FDA and the CDC to promote the “killer virus pandemic” narrative as long as possible to justify taking emergency measures that short-cut the normal procedures for bringing novel, new drugs to the market.
It also clearly explains the vicious opposition to existing, cheap therapeutics that very easily treated what is really just the seasonal flu “virus,” which stood in their way of rolling out a universal vaccine.
Casey Wright then made a rather remarkable comment about “philanthropy” and its role in this effort:
There’s a potential role for philanthropy to play there… we are in a position to take on a little more risk (she smiles eerily as she says this), to be open to a little bit more experimentation and methods in how we do things. That’s what I think is unique about FluLab, and its unique about other philanthropies.
I think they can play a really important role there, and fund a set of bolder, maybe earlier promising concepts.
Bingo! Think Bill and Melinda Gates Foundation, the Rockefeller Foundation, and other “philanthropies” that are “unburdened” by regulatory issues as they spend their money pretty much unchecked, with no accountability, all in the name of “science” and the “greater good.”
We have seen most certainly how the Gates Foundation has done this in India by luring poor people into highly questionable ethical experimentations with vaccines, such as the Gardasil vaccine which we have covered so often over the years here at Health Impact News.
Bruce Gellin then talks about a report published by his organization that called for an “entity” that would make these decisions and bring everyone together to collaborate to create this universal vaccine, and eliminate those who oppose.
The report was published in 2019, and here is the press release.
He states:
They called for this “entity” which is the collaboration we talked about. They called for the need to infuse innovation, to find some of these people who we don’t know might be part of the problem to come into this. And to try to think about how we talk about this differently so that your stomach flu doesn’t keep us from making progress. (everyone laughs…)
I assume that this “entity” is Gellin’s group, The Sabin-Aspen Vaccine Science & Policy Group.
Today, this is the main group fighting “vaccine hesitancy” and trying to silence any dissenting voices that get in their way of rolling out this universal vaccine, which of course we now know is the COVID-19 vaccine.
Watch the entire panel discussion to learn just how arrogant these people are. This is on our Bitchute and Rumble channels… Further analysis at Health Impact News.
October 5, 2021
Posted by aletho |
Deception, Timeless or most popular, Video | Covid-19, COVID-19 Vaccine, Gates Foundation, Rockefeller Foundation |
Leave a comment
- Nick Karl, Pfizer Scientist: “When somebody is naturally immune — like they got COVID — they probably have more antibodies against the virus…When you actually get the virus, you’re going to start producing antibodies against multiple pieces of the virus… So, your antibodies are probably better at that point than the [COVID] vaccination.”
- Chris Croce, Pfizer Senior Associate Scientist: “You’re protected for longer” if you have natural COVID antibodies compared to the COVID vaccine.
- Croce: “I work for an evil corporation… Our organization is run on COVID money.”
- Rahul Khandke, Pfizer Scientist: “If you have [COVID] antibodies built up, you should be able to prove that you have those built up.”
[NEW YORK – Project Veritas released the fourth video in its COVID vaccine investigative series today which exposed three Pfizer officials saying that antibodies lead to equal, if not better, protection against the virus compared to the vaccine.
Nick Karl, a scientist who is directly involved in the production of Pfizer’s COVID vaccine, said that natural immunity is more effective than the very vaccine he works on, and Pfizer produces.
“When somebody is naturally immune — like they got COVID — they probably have more antibodies against the virus… When you actually get the virus, you’re going to start producing antibodies against multiple pieces of the virus… So, your antibodies are probably better at that point than the [COVID] vaccination,” Karl said. Notwithstanding, Karl still believes that vaccine mandates are positive for society.
“The city [of New York] needs like vax cards and everything. It’s just about making it so inconvenient for unvaccinated people to the point where they’re just like, ‘F*ck it. I’ll get it.’ You know?”
A second Pfizer official, Senior Associate Scientist, Chris Croce, corroborated Karl’s assertion about COVID immunity derivative of antibodies:
Veritas Journalist: “So, I am well-protected [with antibodies]?”
Chris Croce, Pfizer Senior Associate Scientist: “Yeah.”
Veritas Journalist: “Like as much as the vaccine?”
Croce: “Probably more.”
Veritas Journalist: “How so? Like, how much more?”
Croce: “You’re protected most likely for longer since there was a natural response.”
Croce expressed dismay with his company’s direction and moral compass:
Veritas Journalist: “So, what happened to the monoclonal antibody treatments?”
Croce: “[It got] pushed to the side.”
Veritas Journalist: “Why?”
Croce: “Money. It’s disgusting.”
…
Croce: “I still feel like I work for an evil corporation because it comes down to profits in the end. I mean, I’m there to help people, not to make millions and millions of dollars. So, I mean, that’s the moral dilemma.”
Veritas Journalist: “Isn’t it billions and billions?”
Croce: “I’m trying to be nice.”
Veritas Journalist: “No, I hear you. I hear you. I do. I mean, I’ll still give you a hard time about it.”
Croce: “Basically, our organization is run on COVID money now.”
The third Pfizer scientist, Rahul Khandke, admitted his company demands that its employees keep information from the public.
“We’re bred and taught to be like, ‘vaccine is safer than actually getting COVID.’ Honestly, we had to do so many seminars on this. You have no idea. Like, we have to sit there for hours and hours and listen to like — be like, ‘you cannot talk about this in public,’” Khandke said.
Khandke also signaled that proof of antibodies is on par with proof of vaccination.
“If you have [COVID] antibodies built up, you should be able to prove that you have those built up,” he said.
Project Veritas will be releasing more Pfizer tapes in the very near future. To receive updates straight into your email inbox, click here.
October 5, 2021
Posted by aletho |
Corruption, Deception, Science and Pseudo-Science, Timeless or most popular, Video | COVID-19 Vaccine, Pfizer |
Leave a comment
Resistance to the introduction of vaccine passes, based on various grounds and gaining momentum for different reasons – is not present only among the general population and customers. In Scotland, owners of businesses have joined those who are opposed to a mandated COVID passport system by announcing a weekend boycott of the program.
Their argument is that the scheme Scotland launched via an app is so technically flawed that it is causing chaos and harming their businesses, as it keeps customers and visitors to places like night clubs and football stadiums away by simply not working.
This seems to be yet another in UK’s botched schemes rolled out over the course of the pandemic, and besides being riddled with technical problems, another thing these have in common is that they cost a lot of taxpayers’ money – although the latest Scottish “omnishambles” as some are calling the app is “cheap” compared to some other UK COVID fiascos – it cost a “mere” £600,000 ($816,520) to develop, although that’s probably £600,000 too much, considering that it doesn’t appear to work.
The first to defiantly pull out of the scheme once it became apparent it was useless were football clubs, who have been hard-hit by COVID restrictions that kept fans out of stadiums and seriously undermined their revenues for months on end.
The app was officially put in practice last Friday morning, with the SNP-led government announcing people would need to show proof of vaccination to be let into this type of venue. But the very same day, realizing the app wasn’t working, Aberdeen FC simply abandoned this requirement for its fans to attend the game upcoming on Sunday.
“Nobody will be asked to show proof of vaccine,” the club announced on Friday, reacting to fans being unable to buy tickets because the app could not be used to prove their vaccination status. Other Scottish clubs, like Rangers and Hearts, soon followed suit, while owners of nightclubs and others in the hospitality industry did the same, saying the confusion was “farcical.”
What followed was Health Secretary Humza Yousaf having to reverse previous policy, saying that “nobody should be denied entry this weekend if they failed to show proof of vaccination, and admitted the widespread technical problems may take ‘days’ to fix,” the Telegraph reported.
October 5, 2021
Posted by aletho |
Civil Liberties, Economics | COVID-19 Vaccine, Human rights, UK |
Leave a comment
A patient with Type 1 diabetes called to tell me the pharmacist at our local Walgreens refused to fill the prescription I had written for ivermectin, so I called to ask why.
The young pharmacist, a few years out of pharmacy school, informed me he did not understand why I was using ivermectin for early treatment of COVID because “SARS-CoV-2 does not have an exoskeleton.”
I explained I was not using ivermectin as an anti-parasitic medication, but that it had impressive data as an anti-inflammatory and anti-viral.
Furthermore, as a pediatrician, I have more than 40 years of experience managing multiple viral illnesses. There is value in treating viruses early, often with inexpensive natural remedies, rather than “staying at home until you have problems breathing then go to the hospital” as U.S. public officials have advised for COVID.
The pharmacist was not buying my initial explanation. “I am not going to fill prescriptions for ivermectin that are used in pseudo vaccine doses,” he told me.
I was surprised a young pharmacist was able to override an experienced physician’s prescription, effectively removing an inexpensive prevention and treatment option for selected patients in the middle of a pandemic.
The medical educator in me kicked in. “I would be happy to send you some references about the use of ivermectin for treatment and prevention. There are impressive studies from Argentina, Peru, Africa and India that suggest much better outcomes than we are achieving here in the U.S. with our single-minded focus on vaccines.”
He told me the U.S. Food and Drug Administration (FDA) did not recommend ivermectin for COVID. I asked to see the documentation and he agreed to fax it to me.
I hand-delivered 93 references and a great review article to the Walgreens.
The pharmacist faxed back a post from March 5, on the FDA website entitled “Why You Should Not Use Ivermectin to Treat or Prevent COVID-19.”
The next day, I received notice that a pharmacy in Northern Virginia would not fill any prescriptions for ivermectin if the diagnosis code mentioned COVID.
I had written an ivermectin prescription for a patient who has a history of bad reactions to vaccines and significant autoimmune illness. His adolescent age means that he is at very low risk of death from COVID itself.
Based on my experience as his doctor for over a decade, I was worried about potential adverse events if he got the COVID vaccine. I dug into the data about ivermectin, and it seemed like a great option for him to have on hand for early treatment of COVID if he got sick.
A pharmacist in a drug store, who never examined my patient or learned his extensive medical history, got to trump my best medical judgment by refusing to fill the prescription.
The same day, in a conversation with a compounding pharmacy, we learned of a case in which a patient’s family had to take a hospital to court to obtain treatment with ivermectin.
Bear in mind that the safety profile for ivermectin is excellent and the drug is spectacularly less expensive than the vast majority of hospital interventions.
Three days later, on a zoom call with a colleague whose parents live in Colorado, I learned that a pharmacist at a major drugstore was not only refusing to fill ivermectin for 86- and 87-year-old patients who held valid prescriptions, but the pharmacist was taking the initiative to remind the other King Soopers pharmacies in the state not to fill those prescriptions either.
My analysis of the medical literature is that ivermectin has an impressive safety record and there are multiple studies from around the globe suggesting it can decrease morbidity and mortality from COVID 19.
Two doctors who were actually in the ICU treating real patients, Dr. Paul Marik and Dr. Pierre Kory, looked at their prior experience with similarly sick patients and reviewed treatment strategies to determine what could be helpful.
As Dr. Anthony Fauci advised us to “stay home and wait for the vaccine,” frontline doctors took care of the patients before them, learning valuable lessons about what worked and what did not.
Let’s hit the highlights, quoting directly from the review paper by Kory et al, Jan 2021:
- Since 2012, multiple in vitro studies have demonstrated that ivermectin inhibits the replication of many viruses, including influenza, Zika, Dengue and others (Mastrangelo et al., 2012; Wagstaff et al., 2012; Tay et al., 2013; Götz et al., 2016; Varghese et al., 2016; Atkinson et al., 2018; Lv et al., 2018; King et al., 2020; Yang et al., 2020).
- ivermectin inhibits SARS-CoV-2 replication and binding to host tissue via several observed and proposed mechanisms (Caly et al., 2020a).
- ivermectin has potent anti-inflammatory properties with in vitro data demonstrating profound inhibition of both cytokine production and transcription of nuclear factor-κB (NF-κB), the most potent mediator of inflammation (Zhang et al., 2008; Ci et al., 2009; Zhang et al., 2009).
- ivermectin significantly diminishes viral load and protects against organ damage in multiple animal models when infected with SARS-CoV-2 or similar coronaviruses (Arevalo et al., 2020; de Melo et al., 2020).
- ivermectin prevents transmission and development of COVID-19 disease in those exposed to infected patients (Behera et al., 2020; Bernigaud et al., 2020; Carvallo et al., 2020b; Elgazzar et al., 2020; Hellwig and Maia, 2020; Shouman, 2020).
- ivermectin hastens recovery and prevents deterioration in patients with mild to moderate disease treated early after symptoms (Carvallo et al., 2020a; Elgazzar et al., 2020; Gorial et al., 2020; Khan et al., 2020; Mahmud, 2020; Morgenstern et al., 2020; Robin et al., 2020).
- ivermectin hastens recovery and avoidance of ICU admission and death in hospitalized patients (Elgazzar et al., 2020; Hashim et al., 2020; Khan et al., 2020; Niaee et al., 2020; Portmann-Baracco et al., 2020; Rajter et al., 2020; Spoorthi V, 2020).
- ivermectin reduces mortality in critically ill patients with COVID-19 (Elgazzar et al., 2020; Hashim et al., 2020; Rajter et al., 2020).
- ivermectin leads to striking reductions in case-fatality rates in regions with widespread use (Chamie, Juan, 2020).
- The safety, availability, and cost of ivermectin is nearly unparalleled given its near nil drug interactions along with only mild and rare side effects observed over almost 40 years of use and billions of doses administered (Kircik et al., 2016).
- ivermectin was successful at controlling several diseases which blighted the lives of billions living in poverty in the tropics.
- ivermectin’s discoverers were awarded the Nobel Prize in Medicine in 2015.
- ivermectin is included in the World Health Organization’s “List of Essential Medicines.” It has been widely distributed in countries like India for pennies a day. The out-of-pocket cost of ivermectin at my Walgreen’s is more than$1,000.
Kory and Marik compiled eight studies (three randomized controlled studies and five observational controlled studies) demonstrating efficacy in prevention of COVID-19 with significant decreased transmission.
They found 19 controlled studies that showed significant impacts on time to recovery, hospital stay, decrease in viral loads, reductions in duration of cough and decreased mortality.
In medical history pre-COVID, this body of research about ivermectin would be applauded for bringing value in the midst of a pandemic. In the medical era pre-COVID, the judgment and experience of clinicians at the patient’s bedside counted for something.
Pre-COVID, we taught medical students to use keen observational skills and keep accurate records of whether the patient improved or deteriorated after the treatment strategies used.
In the Age of COVID, pharmacists who chide doctors that “COVID does not have an exoskeleton” deny patients ivermectin — a safe, cheap, effective and potentially life-saving early treatment.

If you or your patients are having trouble getting ivermectin prescriptions filled for COVID 19 prevention or treatment, see this excellent resource from the Front Line COVID 19 Critical Care Alliance.
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
October 5, 2021
Posted by aletho |
Science and Pseudo-Science | Covid-19, COVID-19 Vaccine, Ivermectin, United States |
Leave a comment
The UK government’s Winter Plan is rife with nudges
There’s a chill in the air. Not from the changing seasons, it’s still beautifully balmy, but because the behavioural scientists’ fingertips have traced a hoar frost of psychocratic nudge on the government’s “Autumn and Winter Plan”.
The UK government’s Winter Plan plan contained some welcome news. The most draconian schedules of the Coronavirus Act will be revoked, including the powers to close schools, allow potentially infectious people to be detained, and restrictions on gatherings and events. The language around the plan’s launch was thankfully more cool-headed. The times are “challenging” but it is no longer claimed that Covid is the “biggest threat this country has faced in peacetime history”.
But the plan is also rife with “nudges” – sneaky ways to prime, prepare and prod you into the desired mindset and course of action.
The contents are freighted with the sunk cost fallacy; we’ve come so far, we mustn’t allow our good work to be undone. This also taps into people’s innate sensitivity to loss.
The trigger from Plan A to Plan B will be “unsustainable pressure” on the NHS rather than deaths. It’s under serious pressure every winter so consider yourselves to be put on notice.
There are other indications of the inevitability of Plan B. I spoke to behavioural scientist Patrick Fagan, who observed that:
“the Plan A / Plan B approach is a classic example of the foot-in-the-door technique. Firstly it makes us accept Plan A because, compared to Plan B, it looks more reasonable; then, once we have accepted and acclimatised to Plan A, we are more likely to then accept Plan B, because it is just one extra step on top of the commitment we’ve already made. The announcement of Plan B may also be an example of the mere exposure effect: simply by talking about the measures (even if, ironically, saying they won’t be implemented), the government makes them more familiar and therefore more psychologically acceptable.”
Bizarrely, after 18 months we’re trapped in a Groundhog Day of modelling and worst case scenarios. Almost a year ago, on the 21st September, Chris Whitty and Patrick Vallance warned of infections hitting 50,000 per day by mid-October in their “Shock and Awe” presentation. When the day arrived, the moving average was 16,228.
According to the doom-mongers at SAGE, up to 7,000 people could be hospitalised per day within the month. And this September the modellers were wrong once again – hospitalisations peaked at about a 1,000 a day and are now falling.
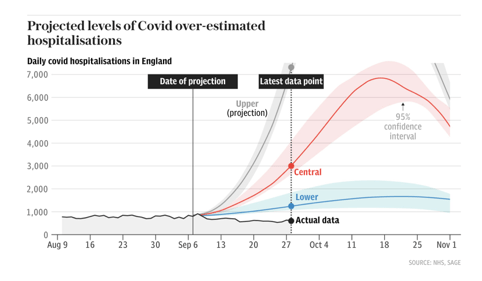
Source: The Telegraph
The big numbers both fuel the policies and justify them. It doesn’t matter that there are more optimistic scenarios, or that the modelling has limitations, because the first supine headline sticks in the brain. The behavioural psychology principle of “salience” draws your attention to what is novel and risky.
Dr Alex De Figueiredo, who conducts mathematical and statistical analyses for the Vaccine Confidence Project, told me that:
“Since the beginning of the pandemic it seems many modelling assumptions, such as the infection fatality rate, have been quite pessimistic. I think this has been why many of the predictions — such as hospitalisations and deaths — have been overstated. It also appears there has been little effort to validate forecasts out-of-sample, such as applying the models to Sweden or Florida, who have had far fewer restrictions.”
There are no quantifiable measures for what justifies each step from Plan A to Plan B. The parameters are fluid, unspecified. This creates confusion and stress, which infantilises people and makes them look to the government for direction. Essentially, confusion increases compliance.
The threat of lockdown hangs like a Sword of Damocles. Will we, or won’t we? It seems unlikely that the public and businesses could be persuaded again. Regardless, the threat of lockdown might be leveraged to justify the introduction of Covid Passports, in what is known as a “reciprocation nudge” – we appear to be given a concession in return for reduced resistance to another option.
Covid Passports have been vigorously opposed by MPs and civil liberties groups, and there hasn’t been a vote in Parliament yet. Despite this, they squat in Plan B as a fait accompli, in the denouement of the “door in the face” technique. This is when a huge request is made, then refused, to be followed by a second smaller request, in this case relegation to Plan B and for limited venues only. Boris Johnson said that it’s “not sensible to rule out this kind of option now when it might still make the difference between keeping businesses open or not.” But why would it be sensible when the Public Administration and Constitutional Affairs Committee produced a damning report against them and found the government could make no scientific case in their favour?
Covid Passports appear to be a behavioural science tool, used to increase vaccine uptake. This may backfire. ‘A Cross-Sectional Study in the UK and Israel on Willingness to Get Vaccinated against COVID-19’ found that vaccine passports deter a significant minority of people who want autonomy over their bodies. This also chimes with the research conducted by De Figueiredo and colleagues at The Vaccine Confidence Project. The bullying and resultant mistrust may impact Covid-19 vaccine uptake as well as other public health initiatives.
When my book A State of Fear: how the UK government weaponised fear during the Covid-19 pandemic was published some people believed, quite quaintly, that public health measures and messaging were unrelated to behavioural science. I think that the book and the writings of other academics and journalists have moved the dial. Once nudge is seen it can’t be unseen. The public increasingly see the nudge. If the behavioural scientists have been dazzling people with card tricks they have over-played their hand.
As such, there is more honesty about the purpose Covid Passports serve. Nicola Sturgeon, Scotland’s First Minister, said that the passport scheme
“will not eradicate transmission completely but it will help reduce it in some higher risk settings, and it will maximise protection against serious illness. And we believe – as we have seen already in some other countries – it will help encourage take-up of the vaccine.”
Similarly, Linda Bauld, Professor of Public Health and Interim Social Policy Adviser to the Scottish Government, also admitted that Covid Passports are “to increase uptake in vaccination” and the “rationale” is that it particularly boosts vaccination in 18 to 29 year olds.
While Covid Passports are in Plan B, Ministers say different things about them each day. Within the space of a week, Sajid Javid scrapped them but also didn’t rule them out for pubs. Javid admitted there’s “no evidence” for them but Boris Johnson called them “sensible”. Does the left hand not know what the right hand is doing? Or maybe a big behavioural science brain lurks in between. The epidemic management is reminiscent of the uncertainty created by Vladislav Surkov in the Soviet Union to deliberately turn politics into a performance of confusion – you don’t know what’s real anymore.
There are never-ending question marks over travel, although double-vaccinated travellers will no longer need expensive and inconvenient PCR tests. The double-jabbed will delight in the news, and it sounds sensible on the surface. However, this is not about “following the science”, since the previously infected do not benefit from the exemption. This is an incentive, a classic nudge, to encourage jabs. The vaccinated are rewarded and the unvaccinated are punished. Bearing in mind that negative tests and prior infection could suffice, this decision reeks of disdain for personal autonomy.
Vaccines for 12 to 15 year olds have been authorised. Politicians have stirred up debate amongst all corners regarding whether children should be jabbed with their parents’ consent or not. This utilises what Patrick Fagan calls “the leapfrog effect”. He says,
“it leapfrogs one stage of the debate and in doing so, sets the baseline assumptions which become accepted implicitly. Specifically, by having people debate whether or not parents’ consent should be sought, they are establishing the unspoken assumption that children should receive the jab in the first place. Those who think they are debating the government, arguing that parents’ consent is needed, are actually accepting its true goal, to jab kids.”
The government might be more in control of the narrative than many people like to believe. (Of course, chaos and confusion are alternatives…)
Worryingly, can teens truly provide informed consent? Throughout 2020 they were exhorted not to “kill granny”, which would provoke fear, shame and stress. Ads on Tiktok tell youngsters that the way to get back to normal is to take the vaccine. The vaccine will be rolled out in schools which will create peer pressure, in a particularly egregious use of “norms”. Finally, if the JCVI found the decision difficult, how is a 12 year old supposed to weigh up the evidence? (Nudging teens is the subject matter of my next article.)
Since the Cabinet reshuffle, Michael Gove has been informally dubbed the ‘Minister for Christmas’. Boris Johnson joked that he “didn’t want to have to cancel Christmas again”. Did you know Christmas might be cancelled and needs saving? You do now, the idea has been “seeded”.
Although it is ostensibly supply chains which threaten Christmas, the joke draws a comparison with last year’s Covid reasons. Again, you are put on notice. The nudges are still focussed on increasing vaccination, for now, but the threat to Christmas might hint at the beginning of a behavioural science approach to meet green targets.
We must be good boys and girls if we want Santa to come. And be aware, the nudgers are drafting our collective New Year’s Resolutions.
October 5, 2021
Posted by aletho |
Book Review, Deception, Science and Pseudo-Science | Covid-19, COVID-19 Vaccine, UK |
Leave a comment
Many years of research have demonstrated the multiple benefits of vitamin D to your health. These benefits include helping to build healthy bones and teeth,1,2 supporting lung3,4 and cardiovascular function,5,6 influencing genetic expression,7,8 supporting brain and nervous system health9,10 and regulating insulin levels.11
During 2020, scientists also discovered that the benefits of vitamin D for upper respiratory infections also include protection against COVID-19.12,13 In 2021, two new studies14,15 confirmed what many researchers had already determined: There is an association between vitamin D deficiency and “the risk of being infected with COVID-19, severity of the disease and risk of dying from it.”16
However, despite a known and safe side effect profile, benefits to patients with COVID-19 and the relative ease of acquiring the low-cost supplement, health “experts” have continued to suppress information that could very well save many lives. To achieve vitamin D toxicity, a person must take more than 40,000 international units (IU) each day and have a serum level above 500 to 600 nanograms per milliliter (ng/ml).17
In addition to this they must also be taking excessive amounts of calcium to experience vitamin D toxicity. In other words, it’s more difficult to overdose on vitamin D than it is to overdose on acetaminophen (Tylenol). Taking more than 3,000 milligrams (mg) of acetaminophen in one day18 can lead to symptoms of an overdose. Signs of toxicity can begin in as little as 30 minutes after ingestion.19
Additionally, it is not difficult to overdose on acetaminophen since it is an ingredient in many over-the-counter cold preparations. Many people who take the drug each week are unaware it is found in combined products.20 The drug is responsible for 500 deaths, 56,000 visits to the emergency room and 2,600 hospitalizations each year.
According to experts, 50% of these injuries are from unintentional overdoses. By contrast, research has found that vitamin D toxicity is rare21 and usually caused by formulation errors, inappropriate prescribing, accidental dispensing or inappropriate administration.22
However, toxicity is not defined consistently across studies. One Irish study found a prevalence of 4.8%, but they considered an elevated result anything above 50 ng/mL (125 nmol/L),23 which is within the normal range of 40 ng/ml to 60 ng/ml.24 Another comparison is that, while studies have shown that the prevalence of vitamin D deficiency25 is 41.6% in the overall population and as high as 82.1% in people with dark skin, there is no known deficiency for acetaminophen.
Vitamin D Deficiency Linked With COVID-19 Severity
One of the newer studies was published in June 2021.26 The researchers sought to determine the role that vitamin D may play in mitigating the impact that SARS-CoV-2 has on morbidity and mortality. They recognized that the production of vitamin D through sensible sun exposure is often limited by geographical location.
Clothing, sunblock and skin pigmentation also limit vitamin D production in the skin. Serum levels of 25-hydroxyvitamin D have been found suboptimal in adults from many countries and are not limited to specific risk groups. The study used an ecological design to find an association and looked at complications and mortality in 46 countries.
They used data from public sources to look for and find evidence of a vitamin D deficiency, which they defined as serum levels less than 20 ng/ml. Although lower than optimal levels for vitamin D, this has been a deficiency level consistently used by researchers.
The researchers gathered data from Worldometer on the number of cases, tests and deaths in a population. They found a statistically significant correlation between deficiency and infection and fatality.
Data analyses were not limited to a specific area of the world or population group but instead included data from 46 countries. The data from this study supported a review of evidence published in Nutrients in 2020 that demonstrated vitamin D levels were associated with:27
- A lower number of cases in the Southern Hemisphere
- An association with deficiency and the development of acute respiratory distress syndrome
- An increase in mortality rates in older adults and patients with chronic diseases that are associated with vitamin D deficiency
- Outbreaks during the winter months when serum levels of vitamin D are lowest
They concluded the data suggest28 “that vitamin D deficiency is associated with an increased risk of COVID-19 infection and mortality across a wide range of countries.”
Second Study Has Similar Results
A second study was published in September 2021 from Trinity College and the University of Edinburgh.29 These researchers also looked at the association between COVID-19 and vitamin D levels. What they found was that the level of ambient ultraviolet B light at a person’s home in the weeks before infection “was strongly protective against severe disease and death.”30
The study was published in the journal Scientific Reports.31 The researchers identified the association from data pulled from 417,342 records stored in the U.K. Biobank. This is a large-scale database that contains in-depth information on genetics and health from a half-million participants.32
From this cohort there were 1,746 cases and 399 deaths registered from March 2020 to June 2020. Unfortunately, on average, vitamin D levels were measured approximately 11 years before the pandemic. Therefore, the researchers looked at ambient UVB light that they found was strongly and inversely associated with hospitalization and death.33
These studies support and confirm earlier research published in 2020 and 2021 that demonstrate a strong association between vitamin D status and infection, hospitalization and death from COVID-19. Early papers published in May 2020,34 offered ample evidence that “vitamin D deficiency to address COVID-19 warrant aggressive pursuit and study.”35
By October 2020,36 research had revealed that people with vitamin D deficiency are at higher risk during the global pandemic and that supplements should be used to maintain circulating 25 hydroxyvitamin D at optimal levels. Retrospective data demonstrated that a deficiency was also associated with an increased risk of COVID1-19 infection.37
In a group of frail elderly nursing home residents with COVID-19 in France,38 researchers found that providing a bolus of vitamin D3 during illness or in the month prior had a significant impact on the severity of the illness and improved survival rates.
Further studies found similar results demonstrating that vitamin D deficiency was associated with increased severity and mortality39 and that supplementation may increase immunity and decrease susceptibility to the infection.40
Information Suppressed Despite Mounting Evidence
Despite mounting evidence that a simple and effective strategy was available to help reduce illness and mortality, health agencies sought to suppress the information. In the early months, many questioned the organized effort to create a situation in which more people were dying.
And yet, as the year wore on, it became more evident that U.S. health officials were intent on ensuring the highest number of people possible would take a genetic therapy experiment to protect themselves against a virus for which treatment protocols and preventive measures had been identified. The aim of some agencies was to put an end to Mercola.com. In the summer of 2020, the Center for Science in the Public Interest (CSPI) launched a social media campaign to that end.41
It’s important to note that this self-proclaimed consumer advocacy group is partnered with Bill Gates’ agrichemical PR group, the Cornell Alliance for Science,42 and is bankrolled by the Rockefeller Foundation, the Rockefeller Family Fund, Public Welfare Foundation, Tides Foundation and Bloomberg Philanthropies.43
The CSPI released a press release July 21, 2020,44 in which they falsely accused me of profiteering from the pandemic by selling “at least 22 vitamins, supplements and other products” to “prevent, treat or cure COVID-19 infection.”
However, in their own Appendix of Illegal Claims, it clearly shows that there are no COVID-19 related claims that exist on any of the products themselves. Rather, the links that CSPI uses go to Mercola articles and interviews — none of which are used to sell anything.45
NOTE: It is wise not to click on CSPI’s shortened links in the “website links” column as they do not currently point to Mercola.com product pages.
Three weeks later, CSPI president Dr. Peter Lurie46 sent an email August 12, 2020, to CSPI’s newsletter subscribers in which he repeated the spurious claim that I “profit from the COVID-19 pandemic” through “anti-vaccine fearmongering” and reporting of science-based nutrition shown to impact your disease risk.
CSPI Takes Public Credit for FDA Action
Interestingly, Lurie is a former FDA associate commissioner.47 It’s disheartening, but not surprising, that the FDA followed up with a warning letter in February 2021,48 for “Unapproved and Misbranded Products Related to Coronavirus Disease 2019.”
Lurie has publicly taken credit for this action,49 and thereby establishes the potential that CSPI is pulling the strings under the new administration through relationships they did not have in July 2020 when they first launched their assault on my free speech.
According to the letter, the FDA lists liposomal vitamin C, liposomal vitamin D3 and quercetin products for the treatment of COVID-19 as50 “unapproved new drugs sold in violation of section 505(a) of the Federal Food, Drug, and Cosmetic Act (FD&C Act), 2pt1 U.S.C. § 355(a).”
It’s ironic that Lurie offhandedly dismisses peer-reviewed published science51 that demonstrates your immune function is dependent on certain nutrients and they help to lower your risk of severe infection, whether it’s from COVID-19, the seasonal flu, the common cold or anything else.
Instead, he calls for mask-wearing52 that has no published scientific evidence to back universal use, as one of the most important prevention strategies against COVID-19. In a blog post, published May 18, 2021, he says, “… while mask relaxation may make sense for most of the vaccinated most of the time, it has the potential to destroy the social norm of mask wearing.”
CSPI Would Like to Censor Free Speech
I have been writing about the importance of vitamin D for your overall health for over a decade. Yet, the CSPI has chosen 2020 to censor my efforts to educate people on the importance of maintaining adequate vitamin D levels. In 2020, I co-wrote a paper with William Grant, Ph.D.,53 and Dr. Carol Wagner,54 both of whom are on the GrassrootsHealth vitamin D expert panel.55
The paper demonstrated the clear link that exists between vitamin D deficiency and severe cases of COVID-19. You can find the paper in the peer-reviewed medical journal Nutrients where it was published in October 2020.56
The FDA’s warning letter has highlighted statements in articles published on my website that are fully referenced, cited and supported by published science. I am committed to providing truthful information, for free, to anyone who wants it. I support having a rigorous scientific debate but cannot support unauthenticated and counterfeit accusations that fly in the face of published, peer-reviewed science.
It should never be a crime to report the findings of scientists and researchers. When censorship becomes the foundational method of influencing public opinion and health strategies, it is sure to lead down a disastrous road.
For the record, we have fully addressed the warning letter from the FDA. It is simply against the First Amendment of the U.S. Constitution for the FDA to stop free speech that the CSPI does not like.
CSPI Has Repeatedly Violated Its Mission Statement
This is not the first time that recommendations from the CSPI have endangered public health. In the past, CSPI described trans fats as “a great boon to American arteries”57 after heartily endorsing them years earlier by saying, “there is little good evidence that trans fats cause any more harm than other fats.”58
In the real world, this highly successful trans-fat campaign that began in 1986 resulted in an epidemic of heart disease. When the organization began reversing its decision on synthetic trans fats, it never admitted the error and simply switched the blame, erasing the previous pro-trans fat articles from its website and then posting a timeline59 on artificial trans fats that simply skips what they previously promoted.
The timeline begins in 1993 when CSPI “suddenly” decided to urge the FDA to label trans fats, and works up to 2003 when CSPI proudly says it took out a full-page ad in The New York Times “slamming McDonald’s for ‘Broken McPromise’ on trans fat.” This, despite the fact that in 198660 they criticized McDonald’s for not switching to trans fats sooner, like other fast-food restaurants already had.
While CSPI would prefer you to believe they’ve always been against trans fats, some people still remember what they and their officers said in the past, and comments their officers and members made when they switched their position have been preserved on others’ websites.
For example, Weston A. Price61 details how CSPI’s director of nutrition Bonnie Liebman changed her organization’s tune in December 1992, when she totally ignored CSPI’s support for trans fats only a few years earlier and blamed the margarine industry for promoting trans fats, writing:
“We’ve been crying ‘foul’ for some time now, as the margarine industry has tried to convince people that eating margarine was as good for their hearts as aerobic exercise … And we warned folks several years ago that trans fatty acids could be a problem.”
Continuing in their historical footsteps, the CSPI continues to recommend eating unsaturated fats like oil and canola oil,62 while avoiding butter and other healthy saturated fats, saying that “changing fats doesn’t lower the risk of dying.”63
Trans fats aren’t the only foods that CSPI made an about-face on something they’d promoted as healthy for years, however. It wasn’t until 2013 that CSPI downgraded the artificial sweetener Splenda from the “safe” category to “caution.”64 It took another three years to downgrade it again from “caution” to “avoid.”65
Yet, the organization continues to promote diet sodas as a safer alternative to regular soda, saying it “does not promote diabetes, weight gain or heart disease in the way that full calorie sodas do”66 — even though numerous peer-reviewed studies say otherwise.67,68,69
The CSPI’s support of suspected, and in some cases well verified, health hazards of trans fats, and artificial sweeteners, along with soy, GMOs, low-fat diets and fake meat, reveals that the intent of the organization to protect and advance public health is questionable to say the least.
The CSPI appears more interested in protecting profitable industries and their effort to destroy companies selling vitamins and supplements with natural antiviral effects is just more evidence of that.
Sources and References
October 5, 2021
Posted by aletho |
Civil Liberties, Deception, Full Spectrum Dominance, Timeless or most popular | Center for Science in the Public Interest, Covid-19, COVID-19 Vaccine, Vitamin D |
Leave a comment

Twitter’s fact-checkers appended a “misleading” alert to an obituary about a young woman who allegedly died after contracting a rare blood-clotting condition provoked by the COVID-19 vaccine.
After being accused of going so far with its censorship that it would resort to censoring an obituary, Twitter relented to the backlash and reversed the censorship.
The woman in question, Jessica Berg Wilson, a 37-year-old mother of two, died in the first week of September from Vaccine-Induced Thrombotic Thrombocytopenia, a rare blood disorder in which small clots grow throughout the body, damaging platelets and preventing blood from reaching key organs. According to her obituary, Wilson’s greatest life ambition was to “be the best mother possible” to her daughters Bridget and Clara.
“She had been vehemently opposed to taking the vaccine, knowing she was in good health and of a young age and thus not at risk for serious illness. In her mind, the known and unknown risks of the unproven vaccine were more of a threat,” it read.
Kelly Bee, a Twitter user, posted Jessica Berg Wilson’s obituary with the statement, “an ‘exceptionally healthy and vibrant 37-year-old young mother with no underlying health conditions,’ passed away from COVID Vaccine-Induced Thrombotic Thrombocytopenia. She did not want to get vaccinated.”

However, Twitter flagged the post as “misleading” and blocked it from being replied to, shared, or liked.
The majority of critics were outraged that Twitter was censoring an obituary and they responded by urging their followers to help the tweet go viral in violation of the company’s warning. Twitter has since removed the “misleading” designation and revoked the shadowban.
Additionally, several bloggers, including Ben Domenech of The Federalist, retweeted the obituary. Ben’s tweet reads: Who @Twitter decided it was okay to say an OBITUARY is ‘misleading’ ?”
Another tweet said “Twitter is now censoring obituaries,” – posted by Sean Davis.
Furthermore, Sebastian Gorka, who worked in the Trump administration’s Department of Defense, tagged Twitter CEO Jack Dorsey in a tweet asking what aspect of the obituary was incorrect or “misleading.”
“Hey @jack, Jessica was healthy and died. Why are you censoring that fact as ‘misleading??” he said.
October 4, 2021
Posted by aletho |
Civil Liberties, Full Spectrum Dominance | COVID-19 Vaccine, Human rights, United States |
Leave a comment



